Pertussis is one of those Step 1 bugs that shows up everywhere: microbiology, immunology, pediatrics, and even pharmacology (macrolides, vaccines). If you can explain why Bordetella pertussis causes the classic “whooping cough,” you’ll also understand its toxins, lab diagnosis, complications, and the key management/vaccine pearls that USMLE loves.
Quick ID: What is Bordetella pertussis?
Bordetella pertussis is a small, gram-negative coccobacillus that causes pertussis (whooping cough), a toxin-mediated respiratory infection.
High-yield characteristics (Step-ready)
- Gram stain: Gram-negative coccobacillus
- Oxygen: Obligate aerobe
- Motility: Nonmotile
- Reservoir: Humans only
- Transmission: Respiratory droplets
- Key virulence tools:
- Pertussis toxin (PT)
- Adenylate cyclase toxin
- Tracheal cytotoxin
- Filamentous hemagglutinin (adhesion)
First Aid cross-reference: Microbiology → Gram-negative bacteria → Bordetella (look for “pertussis toxin ADP-ribosylates → ↑cAMP” and “whooping cough,” plus “Regan-Lowe/Bordet-Gengou media”).
Pathophysiology: How it causes disease (the toxin story)
Pertussis is largely toxin-mediated, and it stays on the respiratory epithelium (it’s not a classic invasive bloodstream pathogen).
Step 1 core mechanism: Pertussis toxin
Pertussis toxin ADP-ribosylates → inactivates it → disinhibits adenylate cyclase → ↑cAMP.
Consequences of ↑cAMP (high yield):
- Lymphocytosis (classically absolute lymphocytosis)
- Impaired immune cell function (e.g., neutrophil/macrophage activity)
- Increased insulin release has been described historically, but lymphocytosis is the big testable clue
Other important virulence factors (often tested together)
- Adenylate cyclase toxin: directly increases cAMP inside phagocytes → impairs killing
- Tracheal cytotoxin: damages ciliated epithelium → loss of mucociliary clearance
- Filamentous hemagglutinin (FHA): promotes adherence to ciliated respiratory cells
Why the cough is so intense
Cilia damage + thick secretions + inability to clear debris → paroxysms of coughing. The “whoop” is often from a forceful inspiratory effort against a narrowed glottis after prolonged coughing.
Clinical presentation: Stages you should recognize instantly
Pertussis has a classic staged illness. USMLE questions often give a timeline plus a key symptom.
1) Catarrhal stage (≈ 1–2 weeks)
- Mild URI symptoms: rhinorrhea, sneezing, low-grade fever
- Mild cough that progressively worsens
- Most contagious stage
Exam trap: early pertussis can look like a common cold—this is why outbreaks happen.
2) Paroxysmal stage (≈ 2–6 weeks)
- Paroxysms of cough (sudden, violent coughing fits)
- Inspiratory “whoop” (more classic in children than adults)
- Posttussive emesis
- Apnea/cyanosis can occur in infants
High-yield complications
- Subconjunctival hemorrhages
- Rib fractures (from severe coughing)
- Pneumothorax
- Secondary bacterial pneumonia (major cause of death in infants)
- Seizures/encephalopathy (less common but testable, often related to hypoxia)
3) Convalescent stage (weeks to months)
- Gradual resolution
- Cough can persist (“100-day cough” concept)
Adults vs infants (common vignette patterns)
- Adults/teens: prolonged cough, may lack classic whoop; often source of spread to infants
- Infants: may present with apnea rather than a whoop; high risk for severe disease
Diagnosis: What to order and what you’ll see
Best initial practical test (board-style and real life)
- Nasopharyngeal swab for PCR (fast, sensitive)
Culture (classic Step fact)
- Culture on Bordet-Gengou agar or Regan-Lowe medium
- Regan-Lowe is commonly emphasized in clinical settings; FA often lists both.
Classic lab clue
- Marked lymphocytosis on CBC (due to pertussis toxin)
When to suspect pertussis (high-yield trigger)
- Paroxysmal cough + posttussive vomiting
- Cough illness >2 weeks, especially with household exposure
- Infant with apneic episodes
Treatment: What to give and why
Antibiotics (mainstay)
- Macrolides: azithromycin, clarithromycin, erythromycin
- Alternative: TMP-SMX (if macrolide intolerance)
Important concept: Antibiotics are best early (catarrhal stage) to reduce symptoms, but later they mainly:
- Reduce transmission
- May not dramatically change cough duration once paroxysmal stage is established
Supportive care (especially in infants)
- Oxygen, suctioning, hydration
- Monitor for apnea and complications
Post-exposure prophylaxis (PEP)
- Macrolide prophylaxis for close contacts (especially if high-risk contacts: infants, pregnant people, immunocompromised)
First Aid cross-reference: Pharm/micro crossover—macrolides for respiratory pathogens; pertussis management often appears in vaccine/immunization contexts.
Prevention: Vaccines & immunity (USMLE loves this)
DTaP/Tdap overview
Pertussis prevention uses acellular vaccine:
- DTaP (children): diphtheria, tetanus, acellular pertussis
- Tdap (adolescents/adults): booster with pertussis component
What’s in the “acellular” pertussis vaccine?
- Inactivated components such as:
- Pertussis toxoid
- Filamentous hemagglutinin, pertactin, fimbriae (varies by formulation)
High-yield vaccine pearls
- Immunity wanes over time → adolescents/adults can get mild disease and transmit to infants
- Tdap in pregnancy (each pregnancy, typically 27–36 weeks) to protect newborn via maternal antibodies
- Herd protection is imperfect because acellular vaccines reduce disease severity but don’t fully block colonization/transmission as well as older whole-cell vaccines (concept sometimes referenced in explanations)
High-yield associations & “favorite” exam hooks
The toxin mechanism (memorize this line)
- Pertussis toxin ADP-ribosylates → ↑cAMP → lymphocytosis
Symptom triad you should be able to recall instantly
- Paroxysmal cough
- Inspiratory whoop
- Posttussive vomiting
Commonly tested differentiators (mini table)
| Feature | Pertussis | Viral URI | Croup (Parainfluenza) |
|---|---|---|---|
| Cough quality | Paroxysmal fits, “whoop,” posttussive emesis | Mild/moderate, non-paroxysmal | Barking cough, inspiratory stridor |
| Fever | Low/absent | Variable | Usually low-grade |
| CBC | Lymphocytosis | Usually normal/mild changes | No classic lymphocytosis |
| Best test | PCR from nasopharyngeal swab | Clinical | Clinical ± viral testing |
“Buzzwords” that point to B. pertussis
- Unvaccinated child or waning immunity in teen/adult
- Apnea in an infant
- Household outbreak
- Cough so severe it causes vomiting or hemorrhages
First Aid-style micro summary (rapid review)
- Gram-negative coccobacillus, obligate aerobe
- Pertussis toxin: ADP-ribosylates → ↑cAMP → lymphocytosis
- Adenylate cyclase toxin: ↑cAMP in immune cells
- Tracheal cytotoxin: damages cilia → cough
- Diagnosis: PCR; culture on Bordet-Gengou / Regan-Lowe
- Tx: macrolides (treat + prophylaxis)
- Prevention: DTaP/Tdap (acellular; immunity wanes)
USMLE-style checkpoints (self-test)
- If a question says “ADP-ribosylates ”, you should think: pertussis toxin → ↑cAMP → lymphocytosis.
- If a question says posttussive emesis or apnea in an infant, think pertussis and choose PCR nasopharyngeal swab + azithromycin.
- If a question is about preventing newborn disease, think Tdap during pregnancy + ensure household contacts are vaccinated.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
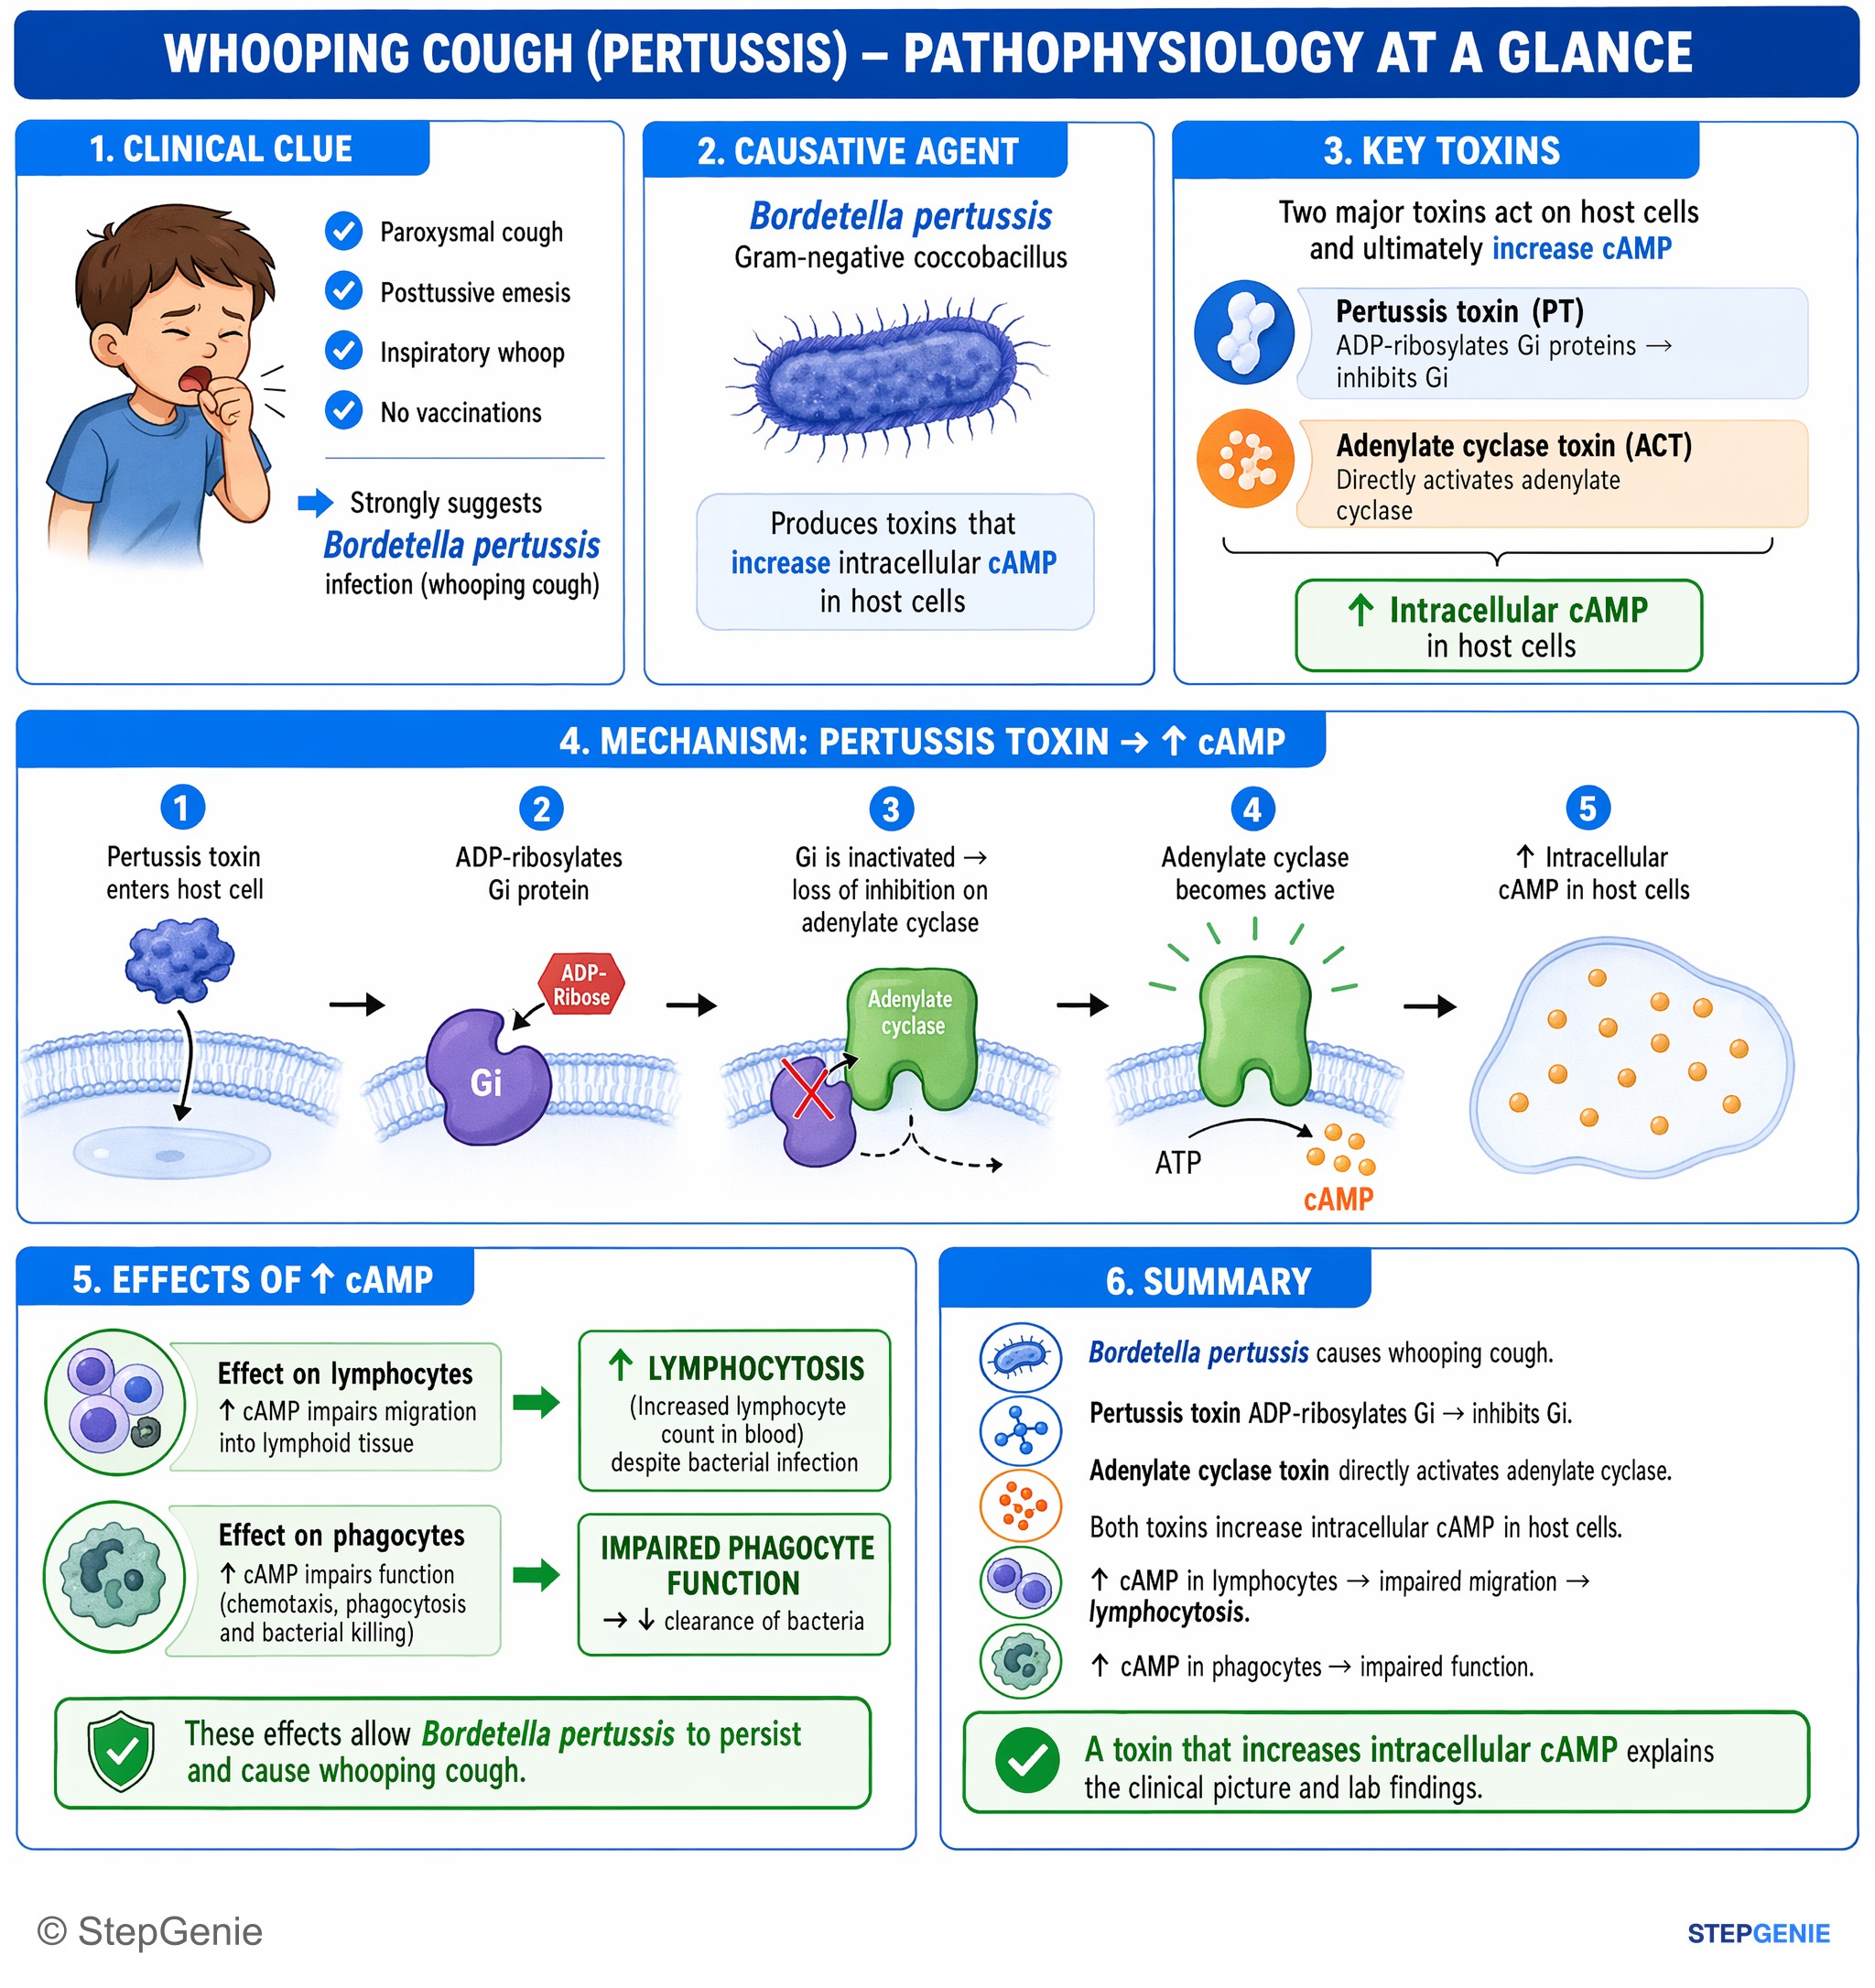
Bordetella pertussis causes whooping cough; its pertussis toxin ADP-ribosylates Gi, ↑intracellular cAMP, leading to lymphocytosis and…
USMLE Step 1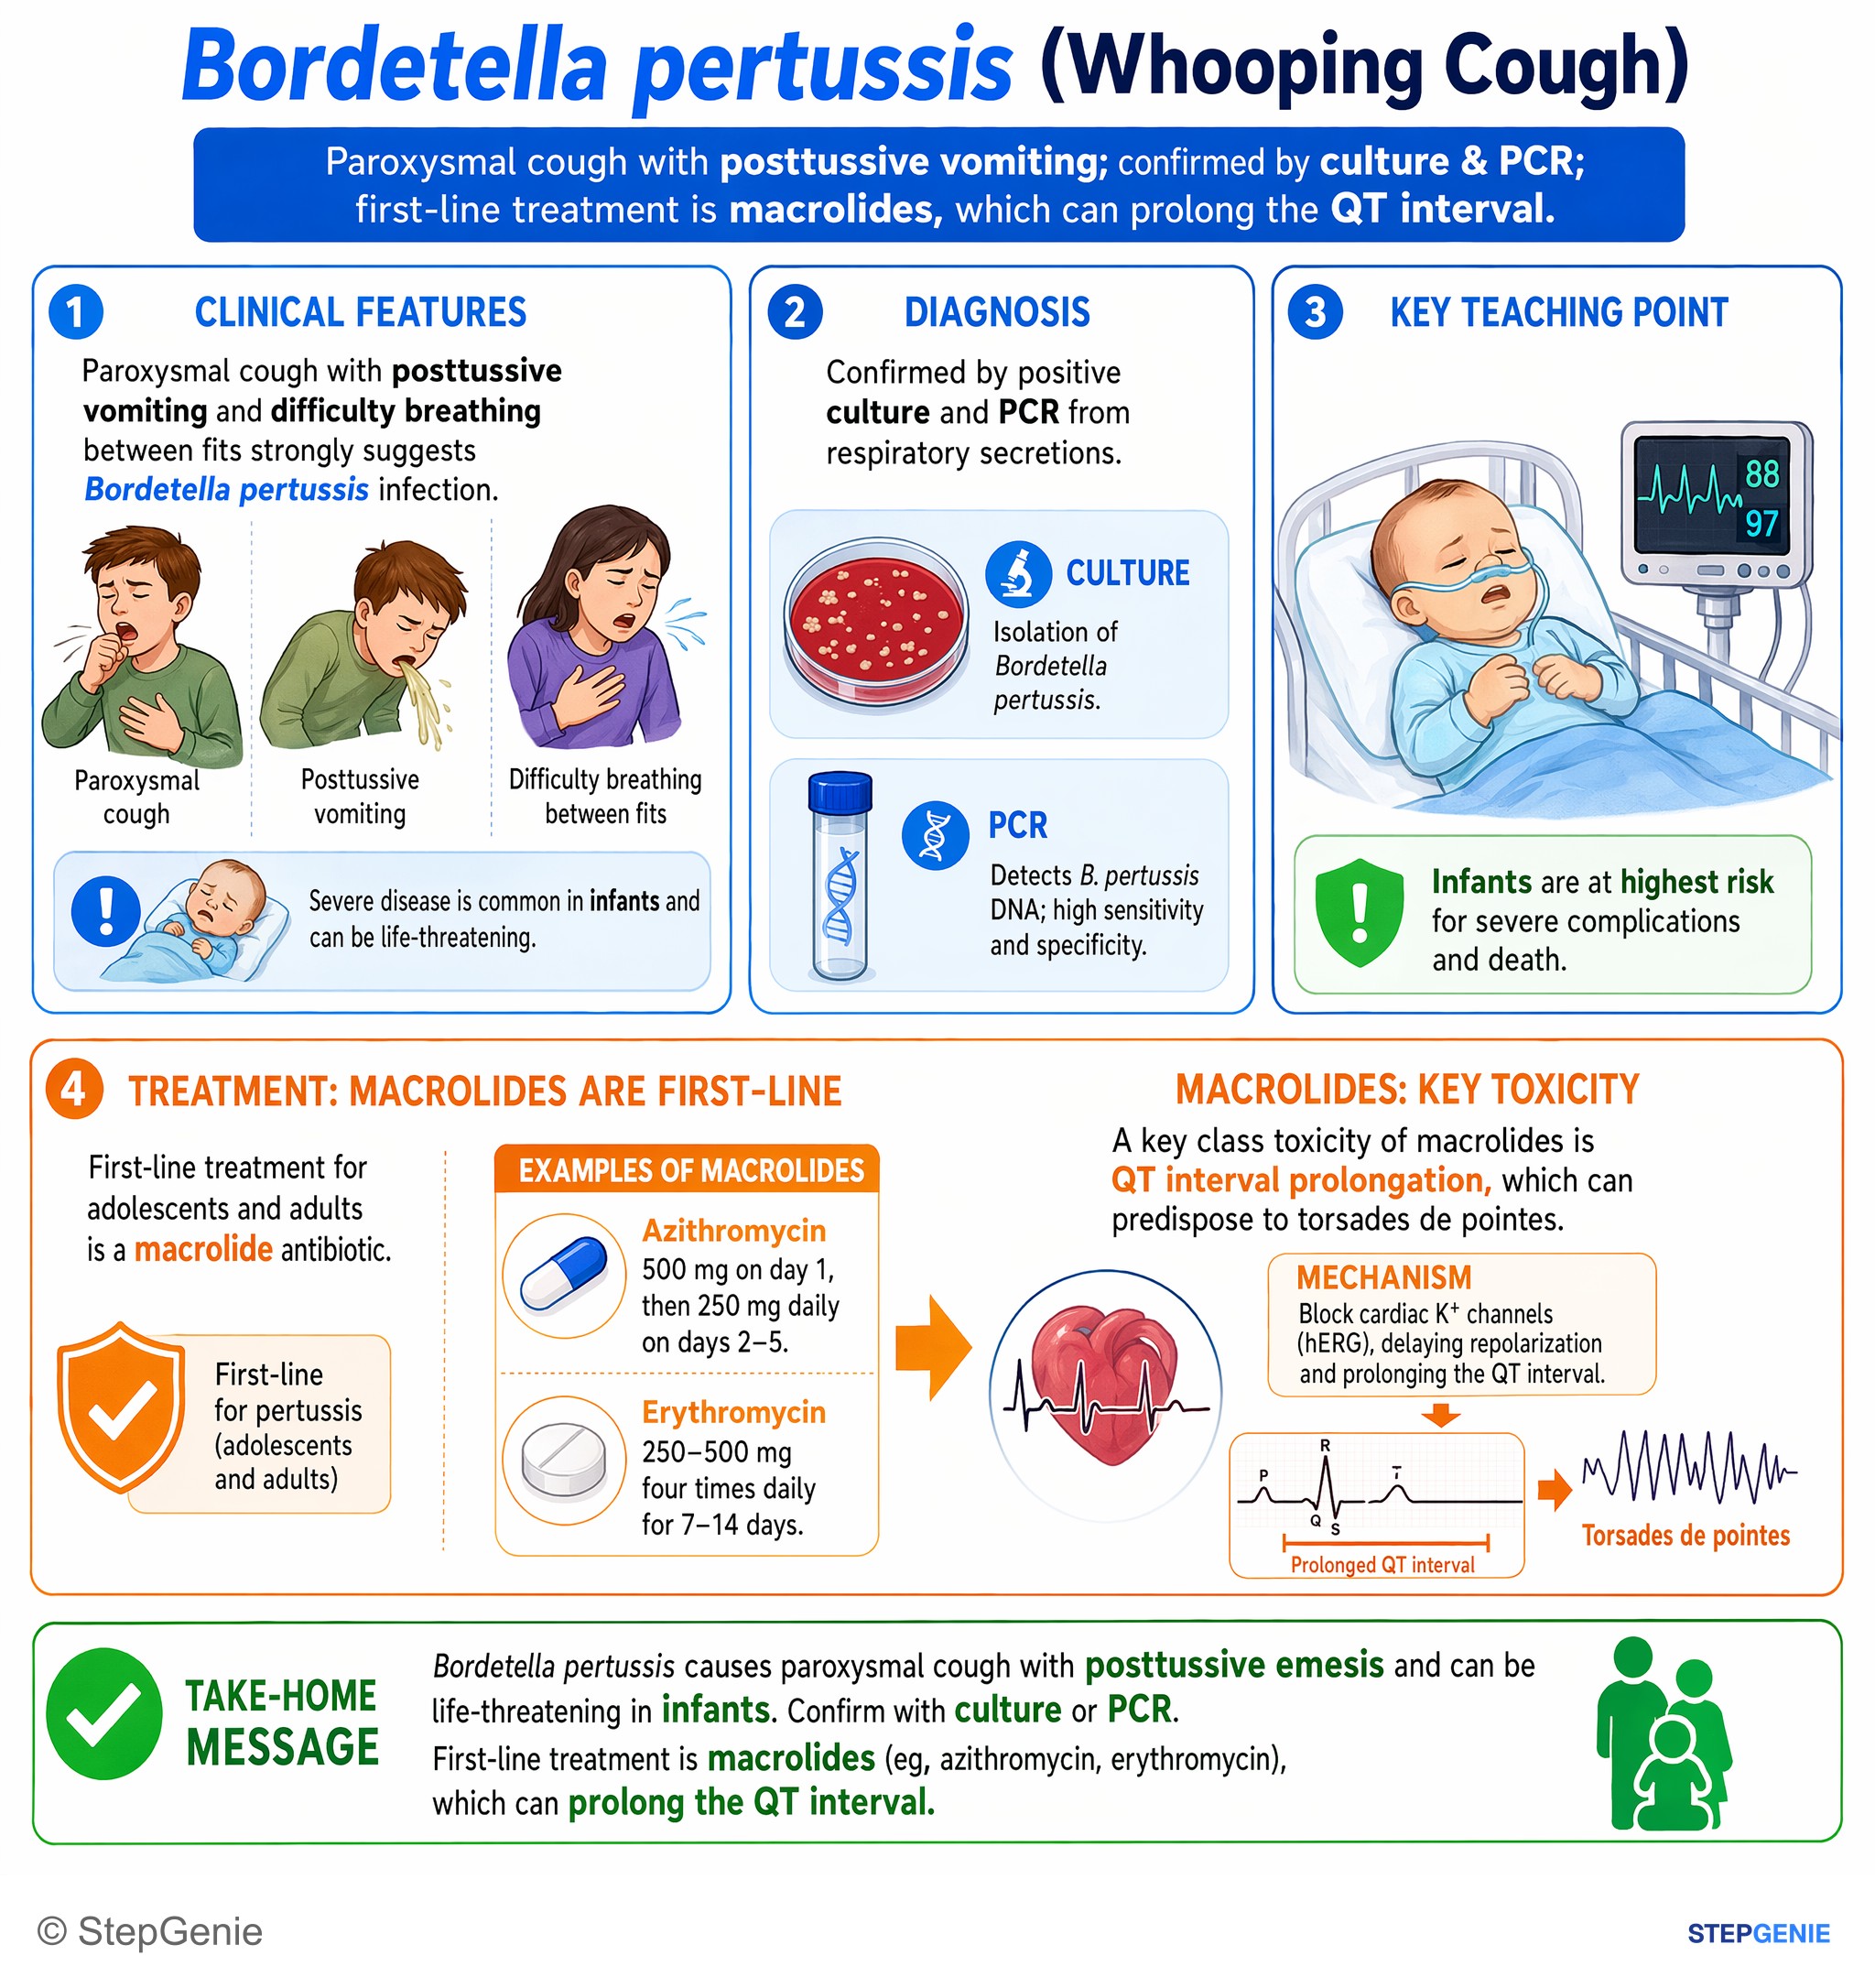
Bordetella pertussis causes paroxysmal cough with posttussive emesis; first-line treatment is macrolides, which can prolong the QT interval.
USMLE Step 1Frequently Asked Questions
Why does Bordetella pertussis cause lymphocytosis and whooping cough?
Bordetella pertussis causes lymphocytosis because pertussis toxin ADP-ribosylates Gi, inactivates it, and raises cAMP; absolute lymphocytosis is the classic lab clue. The severe whooping cough comes from toxin-mediated injury confined to the respiratory epithelium, especially tracheal cytotoxin damage to ciliated cells, which impairs mucociliary clearance and leads to thick secretions, coughing paroxysms, and the forceful inspiratory “whoop.”
How do you diagnose Bordetella pertussis on exams and in practice?
The best initial practical test is a nasopharyngeal swab for PCR because it is fast and sensitive. A classic Step-style culture fact is growth on Bordet-Gengou agar or Regan-Lowe medium. Another major clue is marked lymphocytosis on CBC, especially when the patient has a paroxysmal cough, posttussive vomiting, cough lasting more than two weeks, or infant apnea.
How do you recognize the stages of pertussis?
Pertussis is recognized by a staged illness that progresses from mild cold-like symptoms to violent coughing fits and then prolonged recovery. The catarrhal stage lasts about one to two weeks and causes rhinorrhea, sneezing, low-grade fever, and a worsening cough. The paroxysmal stage lasts about two to six weeks and causes coughing spells, inspiratory whoop, posttussive emesis, and possible apnea in infants. The convalescent stage brings gradual resolution, but cough can persist for weeks to months.
What is the first-line treatment for Bordetella pertussis, and when do antibiotics help most?
Macrolides are the first-line treatment for Bordetella pertussis, including azithromycin, clarithromycin, and erythromycin. They help most when given early in the catarrhal stage, when they can reduce symptoms. Once the paroxysmal stage is established, antibiotics mainly reduce transmission and may not dramatically shorten the cough. TMP-SMX is an alternative if the patient cannot tolerate macrolides, and supportive care is especially important in infants.
How is pertussis prevented, and why can vaccinated adults still spread it to infants?
Pertussis is prevented with the acellular pertussis vaccines DTaP in children and Tdap as a booster in adolescents and adults. The vaccine contains inactivated components such as pertussis toxoid and may include filamentous hemagglutinin, pertactin, and fimbriae. Vaccinated adults can still spread pertussis because immunity wanes over time, and acellular vaccines reduce disease severity but do not block colonization and transmission as well as older whole-cell vaccines.