Streptococcus pyogenes (group A strep, GAS) is a gram-positive coccus in chains that is catalase-negative, beta-hemolytic, bacitracin-susceptible and PYR-positive. It causes three kinds of disease: pus-forming infections (pharyngitis, impetigo, erysipelas, cellulitis, necrotizing fasciitis), toxin-mediated disease (scarlet fever, streptococcal toxic shock syndrome) and delayed immune sequelae (acute rheumatic fever and post-streptococcal glomerulonephritis). Penicillin or amoxicillin is first-line, and GAS has never shown clinical penicillin resistance; necrotizing fasciitis and toxic shock get penicillin plus clindamycin with surgical debridement of infected tissue. Treating strep throat prevents rheumatic fever, but there is no good evidence that it prevents glomerulonephritis.
The 5-second rule
Chains + beta + bacitracin-sensitive = group A. Then ask: pus, toxin or immune?
| Clue | GAS result | Why it matters |
|---|---|---|
| Gram stain | Gram-positive cocci in chains | Chains mean streptococci |
| Catalase | Negative | Part of the classic lab ID |
| Hemolysis on blood agar | Beta (complete) | Narrows to beta-hemolytic streptococci |
| Bacitracin disk (0.04 units) | Susceptible | Sets it apart from other beta-hemolytic streptococci. Mnemonic B-BRAS: group B Bacitracin Resistant, group A Sensitive |
| PYR (pyrrolidonyl arylamidase) | Positive | Identifies S. pyogenes among the beta-hemolytic streptococci |
| Lancefield antigen | Group A | For exam purposes, "group A strep" means S. pyogenes |
| ASO and anti-DNase B titers | Rise about 1 week after infection; peak about 3-6 weeks after pharyngitis (up to 1-2 months) | Prove a recent infection when diagnosing ARF or PSGN; not a test for acute pharyngitis |
For the rest of the gram-positive family, see group B strep and the gram-positive vs gram-negative hub.
| Bucket | Diseases | Mechanism |
|---|---|---|
| Pus (direct infection) | Pharyngitis, impetigo, erysipelas, cellulitis, necrotizing fasciitis; peritonsillar and retropharyngeal abscess, cervical lymphadenitis, mastoiditis | Invasion plus tissue-destroying enzymes |
| Toxin | Scarlet fever, streptococcal toxic shock syndrome (STSS) | Streptococcal pyrogenic exotoxins act as superantigens: nonspecific T-cell activation and a cytokine storm |
| Immune (delayed, nonsuppurative) | Acute rheumatic fever (ARF), post-streptococcal glomerulonephritis (PSGN) | ARF: molecular mimicry. PSGN: immune complexes |
Virulence factors
| Factor | What it does | Exam hook |
|---|---|---|
| M protein | Blocks complement binding, so the bacterium resists phagocytosis | Shares epitopes with synovium, heart muscle and valves: molecular mimicry in ARF; emm typing is based on its gene |
| Capsule | Antiphagocytic, alongside M protein | Helps GAS evade clearance |
| Streptolysins O and S | Destroy red and white blood cells | Antibodies to streptolysin O = the ASO titer |
| Hyaluronidase, streptokinase, DNases | Hyaluronidase digests connective tissue; streptokinase converts plasminogen to plasmin, which dissolves fibrin clots; DNases degrade DNA. All help GAS spread | Anti-DNase B adds to ASO when proving prior infection |
| Pyrogenic (erythrogenic) exotoxins | Superantigens | Scarlet fever rash; STSS |
Strep throat: who to test and how to treat
- Suggests GAS: sudden sore throat, fever, pain on swallowing, tender anterior cervical nodes, tonsillar erythema or exudate, palatal petechiae. Suggests a virus: cough, rhinorrhea, hoarseness, oral ulcers, conjunctivitis.
- Score first (IDSA 2025 update): use a clinical score to decide who to test. Centor gives 1 point each for absent cough, swollen tender anterior cervical nodes, fever above 38°C (100.4°F) and tonsillar exudate or swelling; 4 points carries about a 57% chance of GAS. McIsaac adds age, and FeverPAIN is an alternative. The scoring advice does not apply under age 3, when GAS presents atypically, and household GAS exposure, prior rheumatic fever or signs of complicated infection justify testing even with a low score.
- Test: a rapid antigen test or throat culture. Rapid tests are more than 95% specific but vary in sensitivity, so a negative rapid test in a child or adolescent is backed up with a culture; adults do not need a backup culture. GAS pharyngitis is uncommon under age 3.
- Treat: penicillin V or amoxicillin for 10 days, or one IM dose of benzathine penicillin G. Penicillin allergy: cephalexin or cefadroxil (not after an immediate-type reaction), clindamycin, azithromycin or clarithromycin; resistance to the macrolides and clindamycin is well known.
- Why treat: shorter illness, less spread, fewer complications and, above all, prevention of ARF, which follows less than 1% to 3% of untreated GAS pharyngitis. Children can return to school once afebrile and at least 12-24 hours into antibiotics.
Skin, soft tissue and toxin disease
- Impetigo: papules become pustules, then thick honey-colored crusts; most common at ages 2-5. Non-bullous impetigo is caused by S. aureus, GAS or both; bullous impetigo is S. aureus (toxin). Few lesions: topical mupirocin or retapamulin; many: oral antibiotics.
- Erysipelas: superficial cellulitis that involves the lymphatics, with shiny, red, raised, indurated plaques and sharp margins. Cellulitis involves deeper layers and can spread rapidly.
- Necrotizing fasciitis (type II = GAS, with or without others such as S. aureus): pain out of proportion to the skin findings, then bullae and skin turning red to purple to black within 24-48 hours. Imaging must never delay surgical exploration. Treat with emergency debridement plus high-dose penicillin and clindamycin, which interferes with toxin production. Mortality is about 15-20%.
- STSS: shock (hypotension) and multi-organ involvement with GAS isolated; risks include age 65 or older, recent surgery, varicella or other skin breaks, diabetes and alcohol use disorder. Mortality can exceed 30%. Give penicillin plus clindamycin and debride infected tissue; IVIG may be considered but is unproven.
- Scarlet fever: pyrogenic exotoxin-producing GAS, usually with pharyngitis (sometimes skin or wound infection), mostly ages 5-15. Sandpaper-like red rash, Pastia lines in flexor creases, circumoral pallor and a strawberry tongue; the rash lasts about a week and desquamation may follow. Treat as strep throat.
| Streptococcal TSS | Staphylococcal TSS | |
|---|---|---|
| Toxin | Streptococcal pyrogenic exotoxins | TSST-1 or related exotoxins |
| Typical setting | Minor trauma, surgery, varicella, NSAID use | Classically tampon or intrauterine device use in women colonized with S. aureus |
| Bacteremia | Frequent | Uncommon |
| Skin | Typical rash less likely | Diffuse erythroderma, then desquamation, especially of palms and soles, 3-7 days after onset |
Compare with S. aureus toxins.
ARF vs PSGN: the high-yield split
| Acute rheumatic fever | Post-streptococcal GN | |
|---|---|---|
| Trigger | Pharyngitis (classic rule; CDC now also lists skin infection such as impetigo) | Pharyngitis or skin infection |
| Latency | 1-5 weeks; chorea can appear months later | About 10 days after pharyngitis; up to 3 weeks after skin infection |
| Who | Ages 5-15 | Preschool and early school-age children; adults do worse |
| Mechanism | Molecular mimicry: M protein shares epitopes with synovium, heart muscle and valves, so the immune response cross-reacts with host tissue (type II hypersensitivity) | Immune complexes in glomeruli (type III); low C3 |
| Picture | Jones criteria (below); carditis can leave rheumatic heart disease, mainly of the mitral valve | Edema, hypertension, dark reddish-brown urine, proteinuria |
| Prevented by treating strep throat? | Yes | No good evidence |
| Long-term | Secondary prophylaxis with penicillin | Over 90% of children recover fully |
Jones criteria (2015 AHA revision): evidence of preceding GAS infection (positive throat culture or rapid test, or a raised or preferably rising ASO) plus 2 major, or 1 major and 2 minor criteria for a first episode.
- Major (J♥NES): Joints (migratory polyarthritis, the most common finding), ♥ carditis (apical pansystolic murmur of mitral regurgitation; echo-detected subclinical carditis counts), Nodules (subcutaneous), Erythema marginatum (serpiginous, painless, nonscarring), Sydenham chorea, which can fulfill the criteria on its own once other causes are excluded.
- Minor: fever (≥38.5°C), polyarthralgia, ESR above 60 mm/h or CRP above 30 mg/L, prolonged PR interval.
- Treat: aspirin or NSAIDs, corticosteroids for moderate to severe carditis, and penicillin to eradicate GAS.
- Secondary prophylaxis: IM benzathine penicillin G every 3-4 weeks (or oral penicillin V). Duration: no carditis, 5 years or until age 21; carditis without residual heart disease, 10 years or until age 21 (whichever is longer for both); carditis with residual valve disease, more than 10 years, and many experts continue it until age 40 or for life.
Deeper dives: rheumatic heart disease and mitral stenosis, molecular mimicry, and IgA nephropathy vs PSGN timing and C3.
How USMLE tests it
- Impetigo, then hematuria = PSGN. Sore throat, then joints, heart or chorea = ARF. The exam answer is still "ARF follows pharyngitis," even though CDC now also lists skin infection as a possible trigger.
- Antibiotics prevent ARF, not PSGN.
- Clindamycin in necrotizing fasciitis or STSS is about shutting down toxin production, not about penicillin resistance.
- Bacitracin separates group A (sensitive) from group B (resistant).
- ASO documents a past infection; it does not diagnose today's sore throat.
- PANDAS (a pediatric autoimmune neuropsychiatric disorder linked to GAS) is a tempting answer, but the association remains inconclusive, and prolonged antibiotics have not been shown to help.
Practice question
A 6-year-old boy is brought in with puffy eyes and dark, reddish-brown urine. Three weeks ago he had crusted, honey-colored lesions around his nose that were not treated and have since healed. Blood pressure is elevated for his age, and he has mild facial and ankle edema. Urinalysis shows blood and protein. Serum C3 is low. Which mechanism best explains his kidney disease?
A. Antibodies against streptococcal M protein that cross-react with host tissue B. Deposition of antigen-antibody complexes in the glomeruli C. Direct bacterial invasion of the renal parenchyma D. Superantigen-mediated nonspecific T-cell activation E. T cell-mediated delayed-type hypersensitivity
Answer: B. Nephritic syndrome (hematuria, hypertension, edema) weeks after GAS impetigo with low C3 is post-streptococcal glomerulonephritis, a type III (immune complex) disease in which complexes lodge in the glomeruli and consume complement. There is no good evidence that penicillin at the time of the impetigo would have prevented it.
- A: molecular mimicry by M protein-directed antibodies is the mechanism of acute rheumatic fever (type II), which presents with arthritis, carditis, chorea, nodules or erythema marginatum, not nephritis.
- C: PSGN is a nonsuppurative sequela; the kidney is not infected, and the skin lesions have already healed.
- D: superantigens cause scarlet fever and STSS at the time of infection, not nephritis weeks later.
- E: delayed-type (type IV) hypersensitivity is T cell-mediated and does not consume complement.
Key takeaways
- Chains + beta-hemolysis + bacitracin-susceptible (+ PYR-positive) = group A strep.
- Sort every GAS stem into pus (pharyngitis, impetigo, erysipelas, necrotizing fasciitis), toxin (scarlet fever, STSS) or immune (ARF, PSGN).
- M protein blocks complement and drives the molecular mimicry of ARF.
- Strep throat: score, then test (back up negative rapid tests with a culture in children); penicillin or amoxicillin for 10 days.
- ARF follows pharyngitis and is prevented by treatment; PSGN follows throat or skin infection, has low C3 and is not reliably prevented.
- Necrotizing fasciitis: emergency surgery plus penicillin and clindamycin; STSS: penicillin plus clindamycin and debridement of any infected tissue.
Sources
- Clinical Guidance for Group A Streptococcal Pharyngitis — CDC (2025)
- IDSA Clinical Practice Guideline Update on Group A Streptococcal Pharyngitis — Infectious Diseases Society of America (2025)
- Clinical Guidance for Acute Rheumatic Fever — CDC (2025)
- Rheumatic Fever — Merck Manual Professional Edition (2026)
- Clinical Guidance for Post-Streptococcal Glomerulonephritis — CDC (2025)
- Clinical Guidance for Group A Streptococcal Impetigo — CDC (2025)
- Clinical Guidance for Scarlet Fever — CDC (2026)
- Clinical Guidance for Streptococcal Toxic Shock Syndrome — CDC (2025)
- Clinical Guidance for Type II Necrotizing Fasciitis — CDC (2025)
- Streptococcal Infections — Merck Manual Professional Edition (2025)
- Toxic Shock Syndrome — Merck Manual Professional Edition (2025)
- Bacterial Infections of the Respiratory Tract — OpenStax Microbiology (2016)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
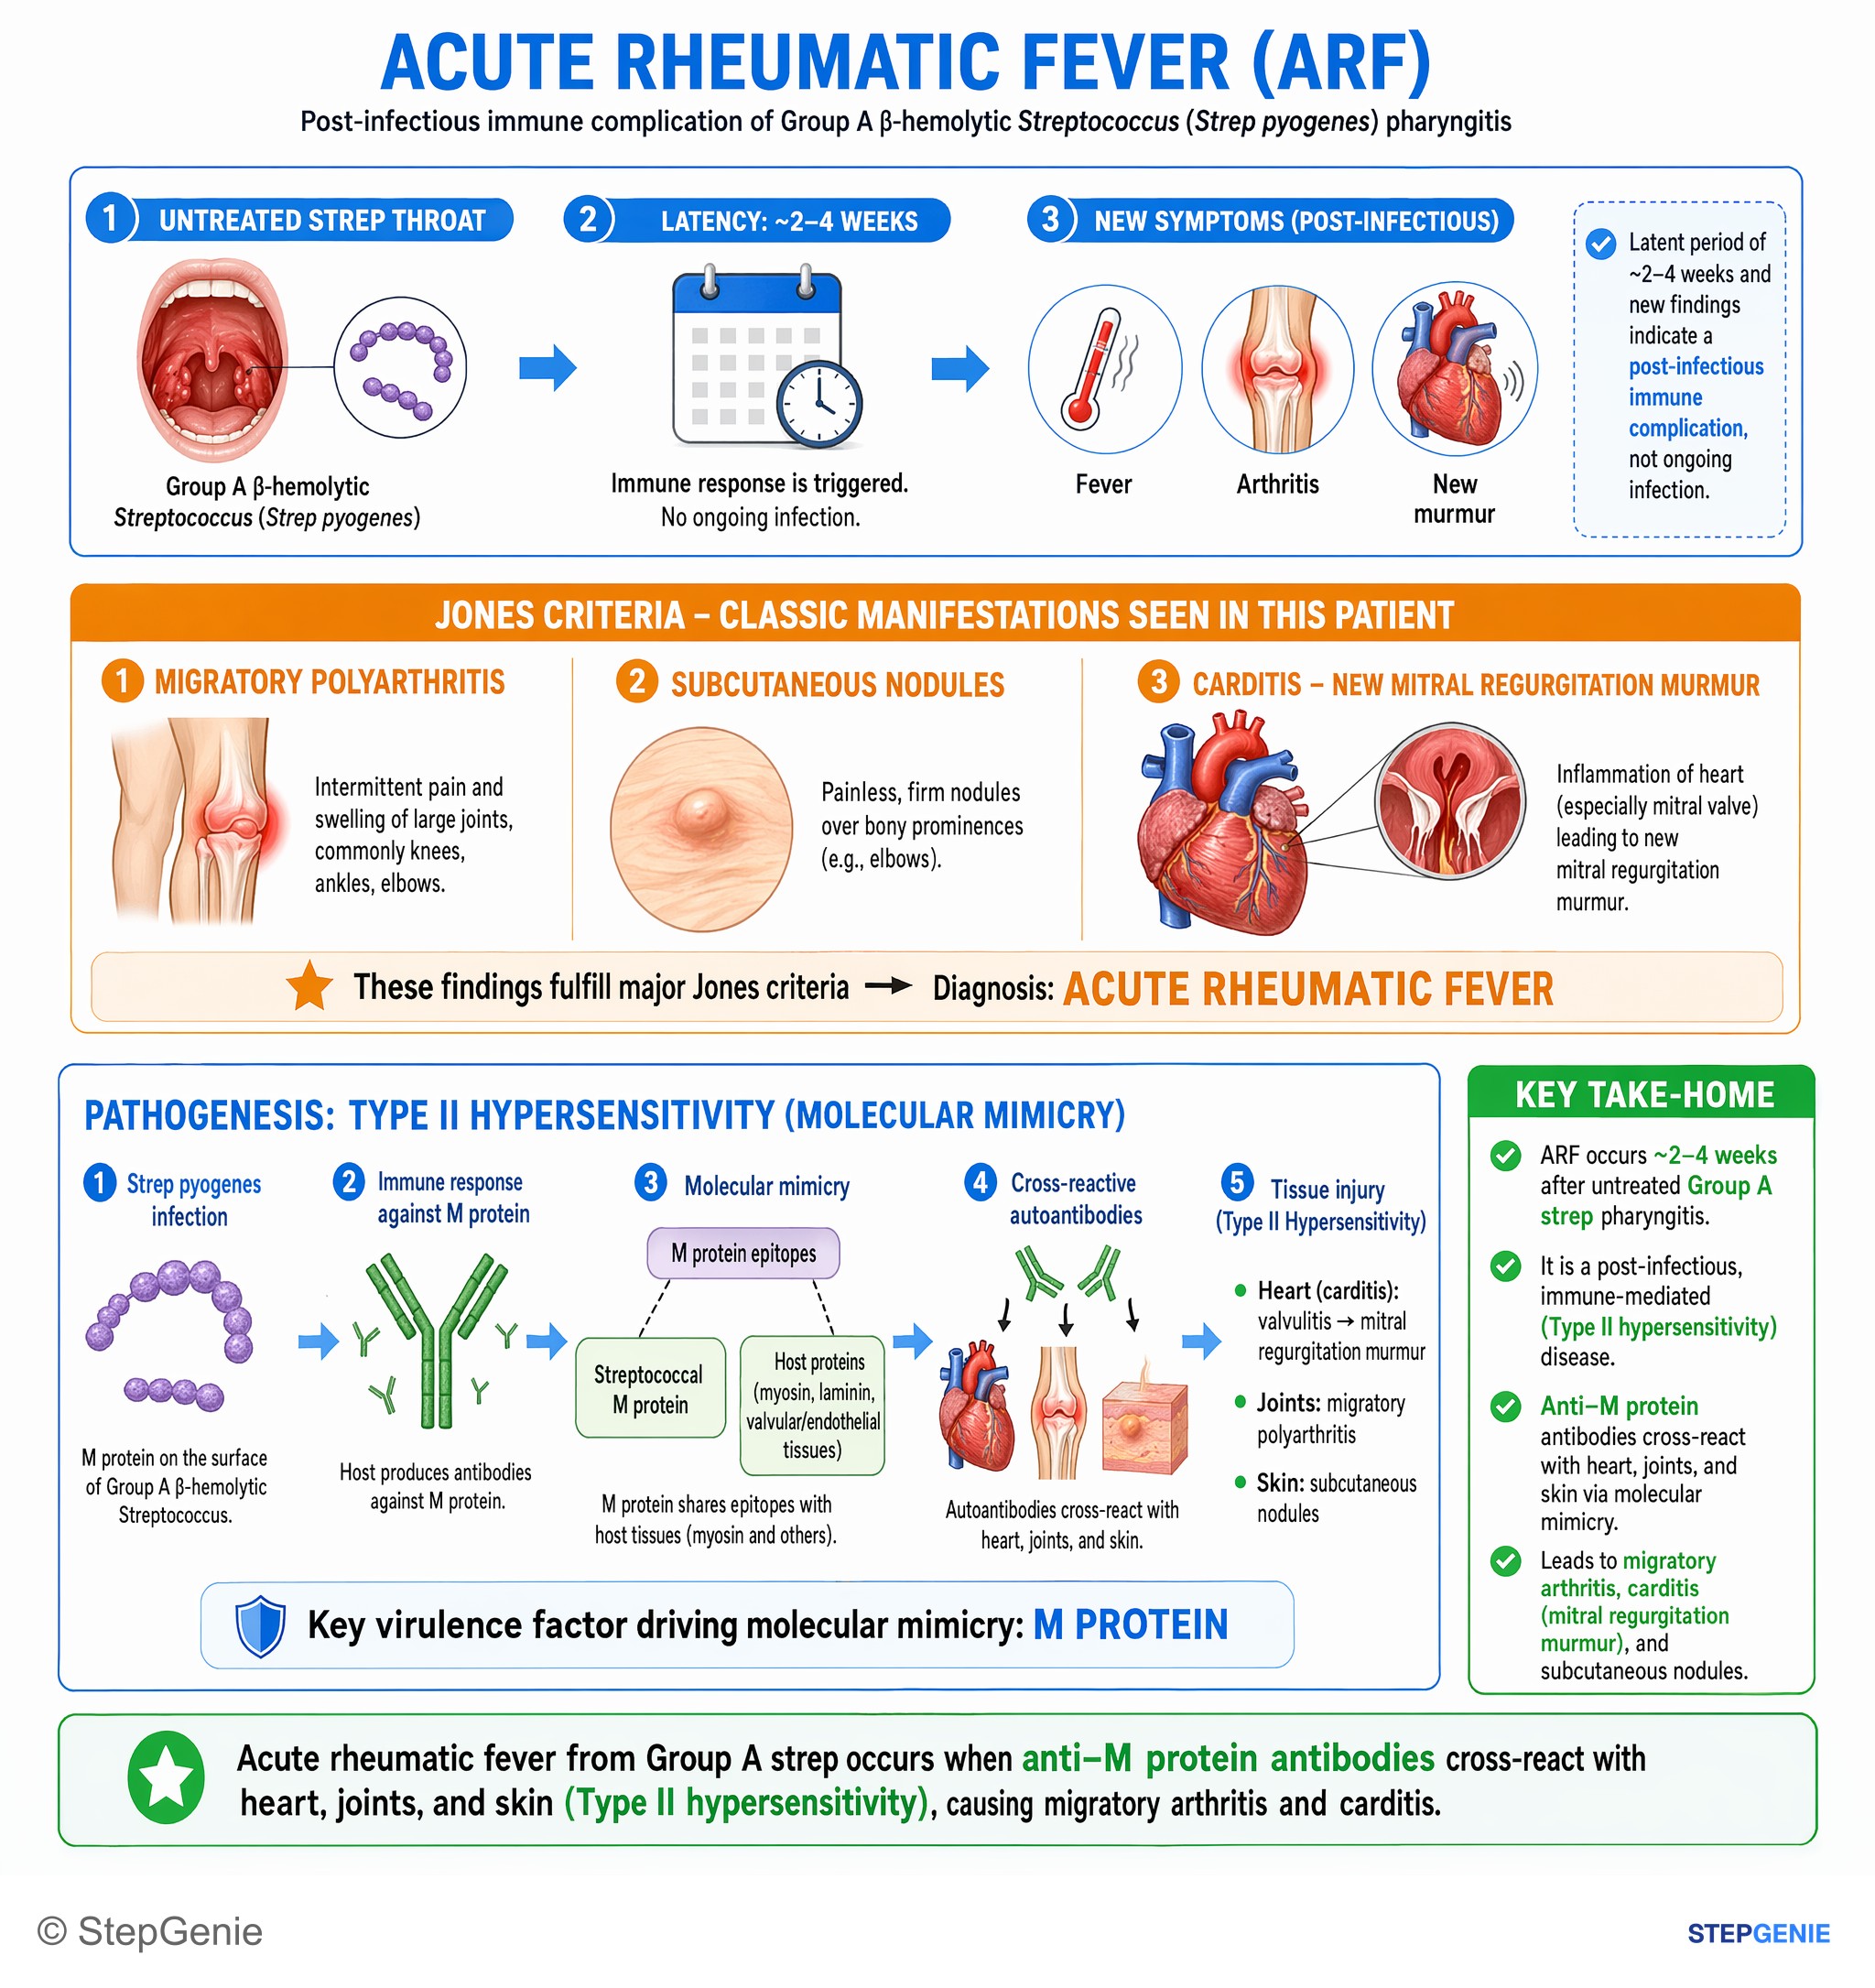
Acute rheumatic fever from group A strep: anti–M protein antibodies cross-react with heart, joints, skin (type II hypersensitivity)…
USMLE Step 1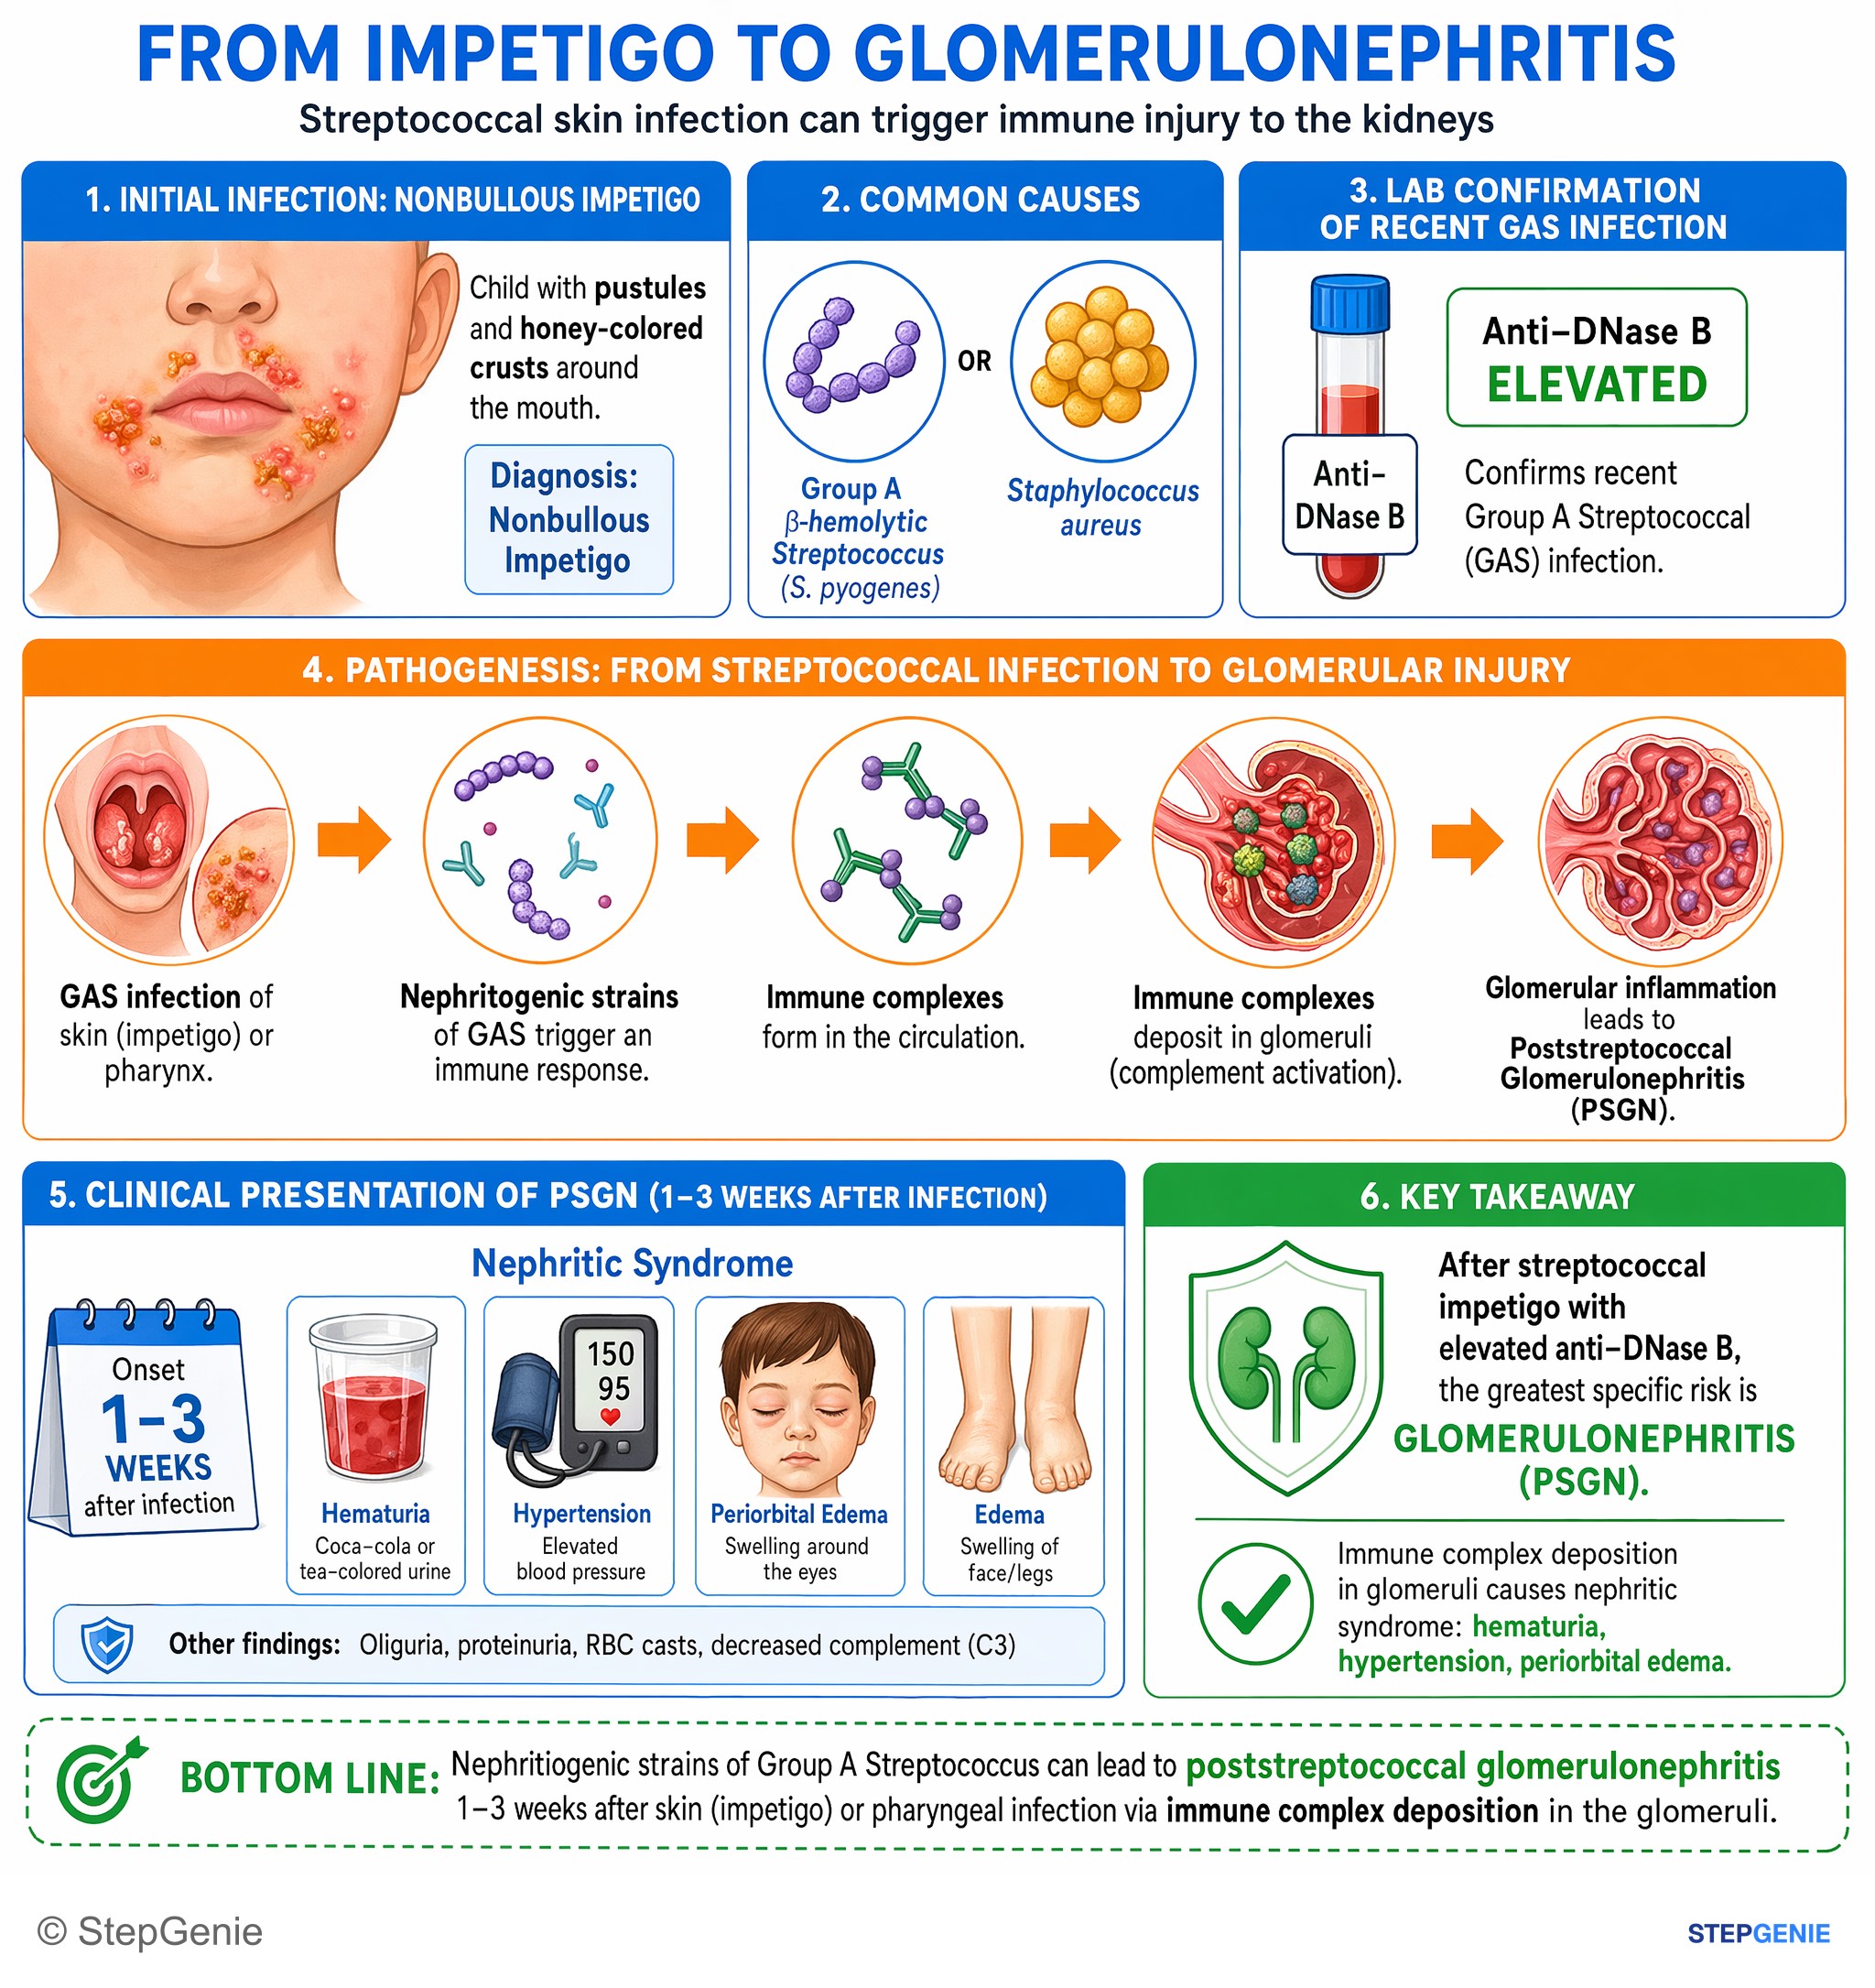
Poststreptococcal glomerulonephritis can follow streptococcal impetigo; immune complex deposition causes nephritic syndrome (hematuria…
USMLE Step 1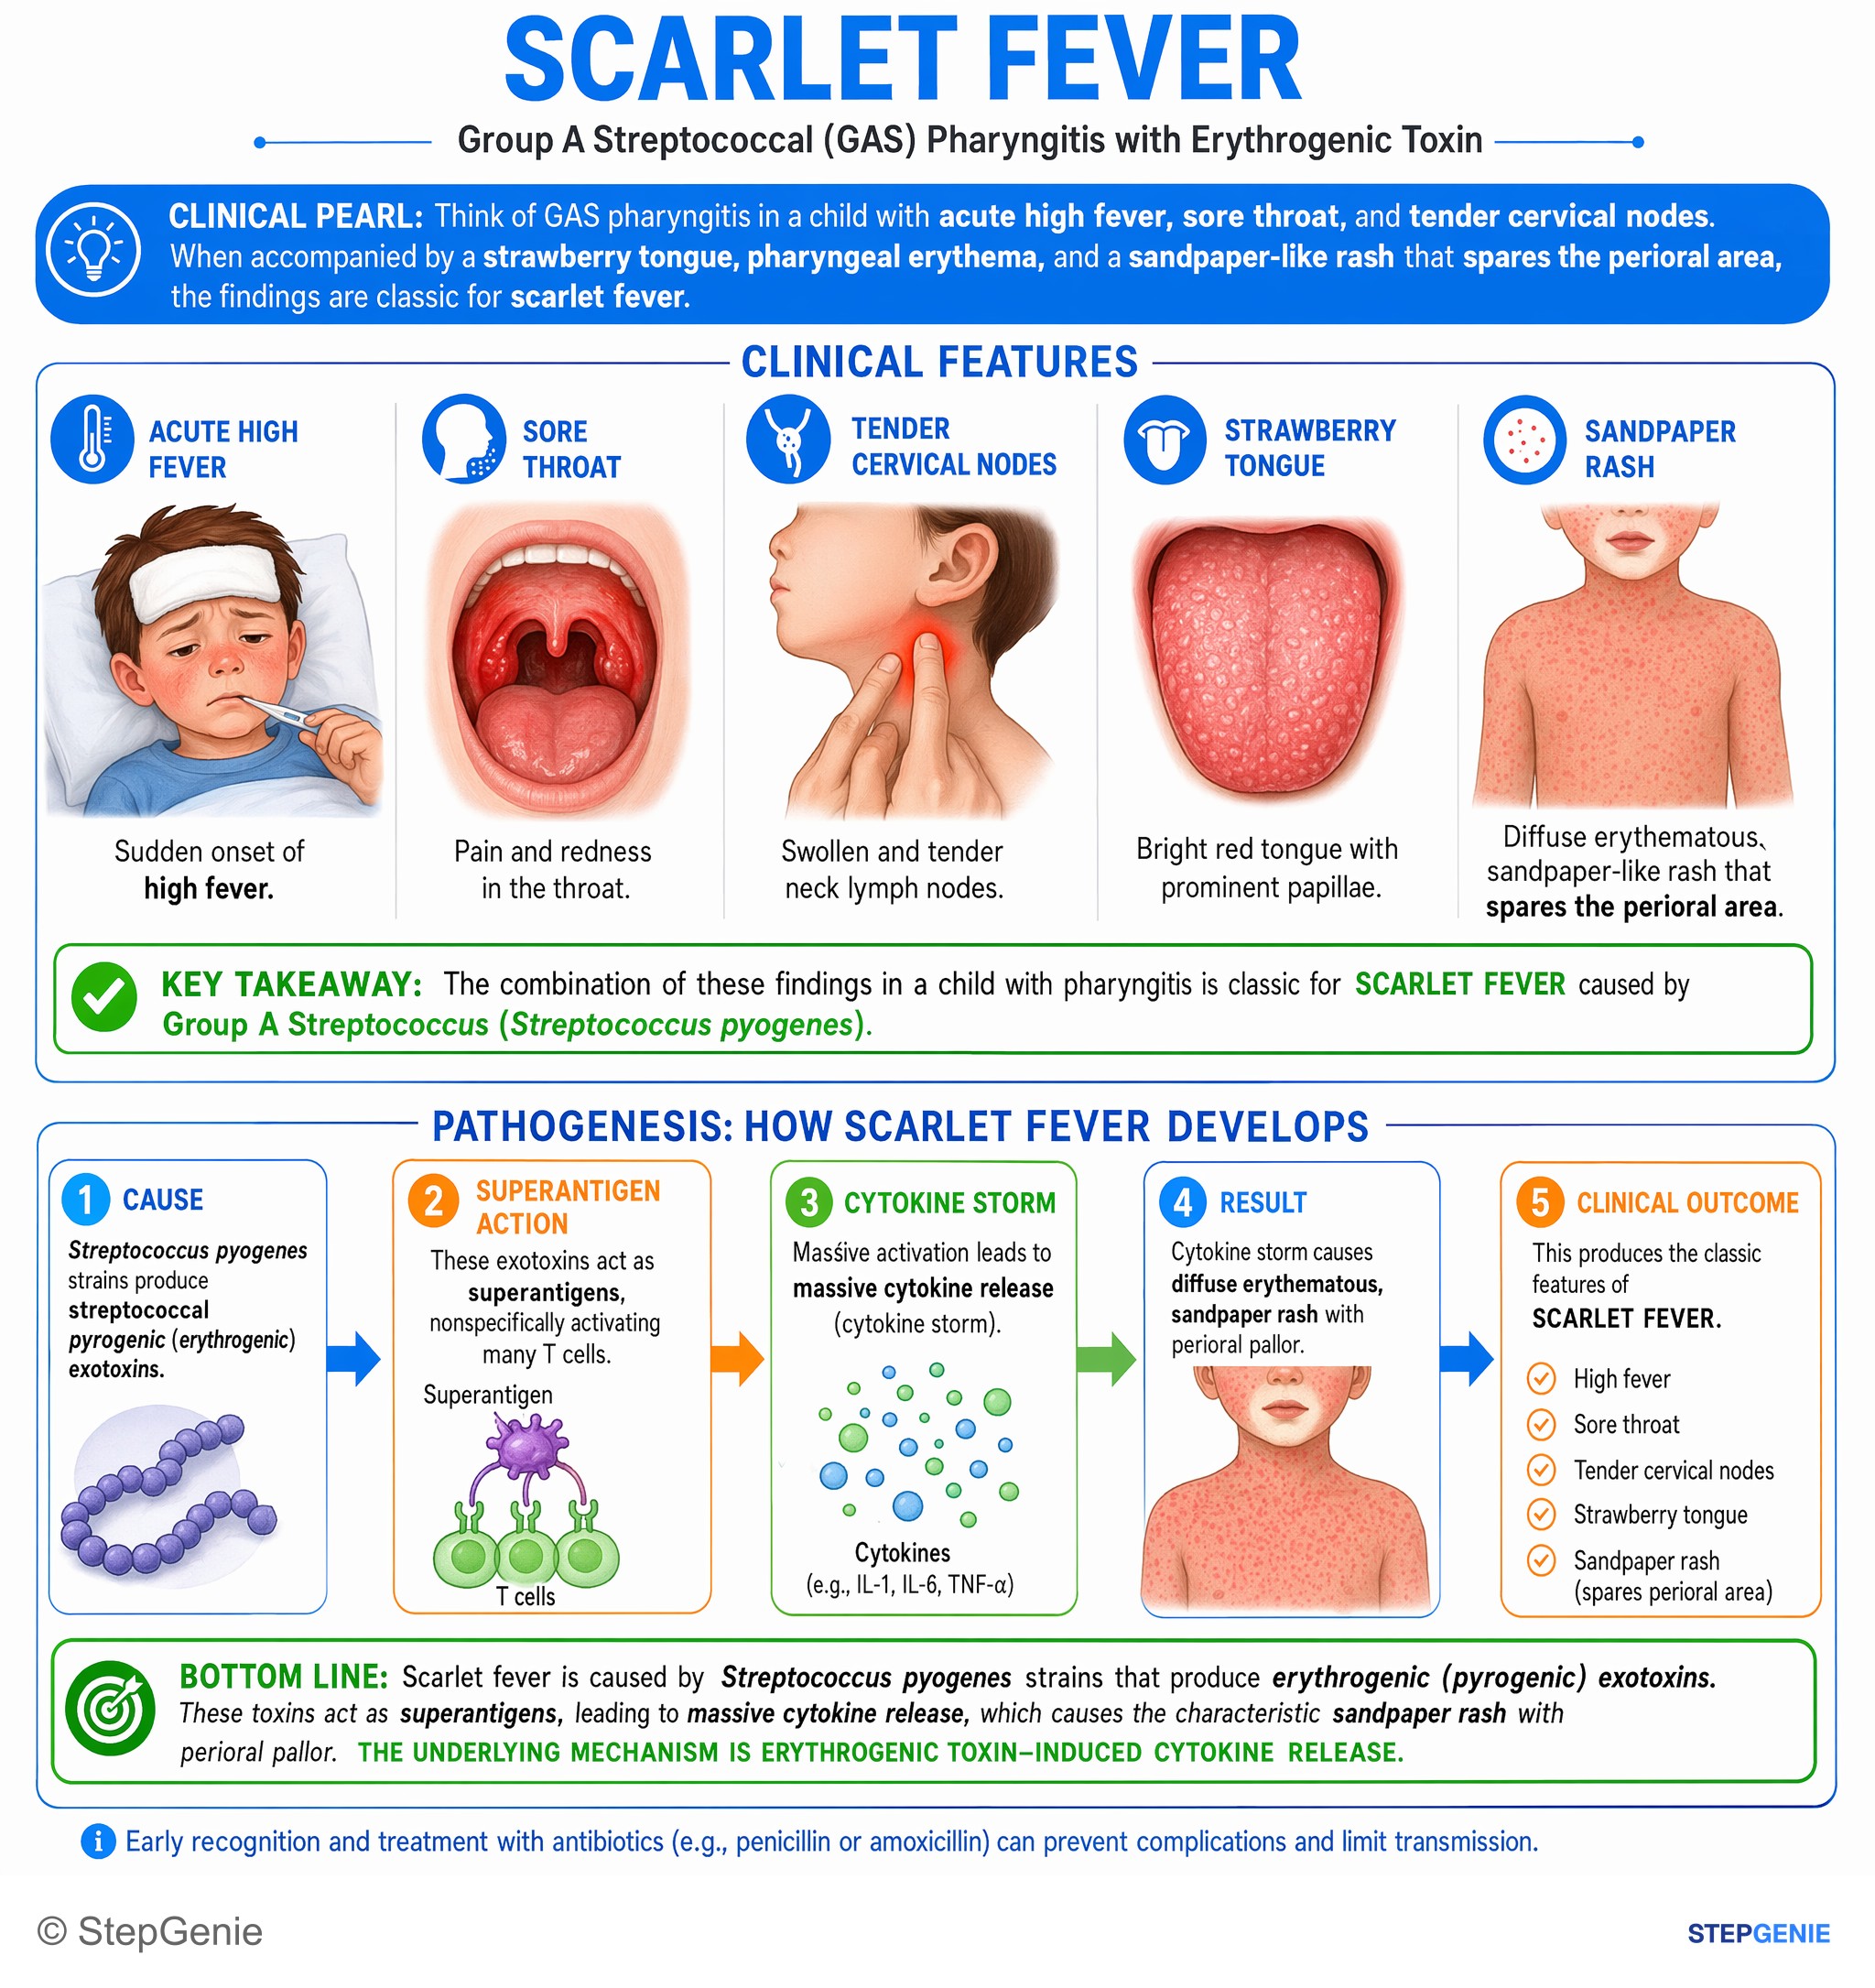
Scarlet fever from Group A Strep: erythrogenic (pyrogenic) exotoxin → superantigen → massive cytokine release → sandpaper rash with…
USMLE Step 1Frequently Asked Questions
How do you identify Streptococcus pyogenes in the lab?
Streptococcus pyogenes is a gram-positive coccus that grows in chains, is catalase-negative and produces beta (complete) hemolysis on blood agar. It is susceptible to a 0.04-unit bacitracin disk, which sets it apart from other beta-hemolytic streptococci (remember B-BRAS: group B bacitracin resistant, group A sensitive), and it is PYR-positive. Lancefield grouping confirms the group A antigen; for exam purposes, group A strep means S. pyogenes.
What is the difference between rheumatic fever and post-streptococcal glomerulonephritis?
Both are delayed immune complications of group A strep. Acute rheumatic fever classically follows pharyngitis by 1 to 5 weeks and is driven by molecular mimicry: M protein shares epitopes with heart muscle, valves and synovium, so the immune response attacks the heart and joints, and the autoimmune process can also cause Sydenham chorea. Post-streptococcal glomerulonephritis follows throat or skin infection, about 10 days after pharyngitis or up to 3 weeks after impetigo, and is an immune-complex disease with low C3, hematuria, edema and hypertension.
Does treating strep throat prevent rheumatic fever and glomerulonephritis?
Treating group A strep pharyngitis with penicillin or amoxicillin prevents acute rheumatic fever, which develops after less than 1 percent to 3 percent of untreated strep throat cases, and this is one of the most important reasons to treat. Antibiotics have not been shown to prevent post-streptococcal glomerulonephritis; CDC says the evidence is insufficient. Treatment also shortens symptoms, reduces spread to close contacts and lowers the risk of complications.
What are the Jones criteria for acute rheumatic fever?
A first episode requires evidence of a preceding group A strep infection plus two major criteria, or one major and two minor criteria. The major criteria are migratory polyarthritis, carditis (including subclinical carditis seen on echocardiography), subcutaneous nodules, erythema marginatum and Sydenham chorea, remembered as J-heart-NES. Minor criteria are fever of at least 38.5 degrees C, polyarthralgia, ESR above 60 mm/h or CRP above 30 mg/L, and a prolonged PR interval. Sydenham chorea alone can be enough once other causes are excluded.
What is the first-line treatment for strep throat?
Penicillin V or amoxicillin for 10 days, or a single intramuscular dose of benzathine penicillin G, is first-line, and group A strep has never shown clinical penicillin resistance. For penicillin allergy, options are cephalexin or cefadroxil if the reaction was not immediate-type, or clindamycin, azithromycin or clarithromycin, keeping in mind that resistance to macrolides and clindamycin is well known. Children can return to school once afebrile and at least 12 to 24 hours into antibiotics.
Why is clindamycin added to penicillin for necrotizing fasciitis or streptococcal toxic shock?
Clindamycin is a protein synthesis inhibitor that interferes with the production of streptococcal toxins, which drive the shock and tissue destruction of invasive group A strep infection. It is added to high-dose penicillin to switch off toxin production, not because group A strep resists penicillin. Antibiotics are only part of care: necrotizing fasciitis needs emergency surgical debridement, and imaging should never delay surgical exploration.