In a ventilator-associated pneumonia (VAP) stem with an oxidase-positive, non-lactose-fermenting gram-negative rod that makes blue-green pigment and smells grape-like, the answer is Pseudomonas aeruginosa. Each distractor fails on one discriminator: Acinetobacter baumannii is an oxidase-negative coccobacillus, Klebsiella pneumoniae ferments lactose, Serratia marcescens is oxidase-negative and may be red, and Haemophilus influenzae is a fastidious coccobacillus that needs factors X and V. The Step 2 CK follow-up is empiric coverage: one antipseudomonal agent (such as piperacillin-tazobactam, cefepime or meropenem), plus a second antipseudomonal agent from a different class and MRSA coverage when the patient has multidrug-resistance risk factors (IDSA/ATS 2016).
The vignette
A 62-year-old man with poorly controlled diabetes has been intubated in the ICU for 7 days after a stroke. Three weeks ago he received IV antibiotics for a urinary tract infection. He now has a temperature of 39.4°C (102.9°F), hypotension requiring vasopressors and copious green-tinged tracheal secretions. Chest x-ray shows a new right lower lobe consolidation. Tracheal aspirate culture grows gram-negative rods that are oxidase-positive and do not ferment lactose. The colonies produce a blue-green pigment and a grape-like odor.
Which of the following is the most likely pathogen?
A. Acinetobacter baumannii B. Haemophilus influenzae C. Klebsiella pneumoniae D. Pseudomonas aeruginosa E. Serratia marcescens
Answer: D. Pseudomonas aeruginosa
The lock-in clues are independent of each other, which is why the answer is secure:
- Setting: pneumonia more than 48 hours after intubation is VAP, and recent IV antibiotics plus septic shock are risk factors for a multidrug-resistant organism.
- Oxidase-positive and non-lactose-fermenting: the two lab results that separate it from the coliforms such as Klebsiella and Serratia (oxidase-negative) and from Acinetobacter.
- Blue-green pigment: pyocyanin, often with the fluorescent pigment pyoverdine (fluorescein). Pus and secretions may look green.
- Grape-like odor: from the volatile compound 2-aminoacetophenone.
Every answer choice side by side
| Choice | Shape | Oxidase | Lactose | Signature clue | Why it is wrong here |
|---|---|---|---|---|---|
| A. Acinetobacter baumannii | Coccobacillus | Negative | Nonfermenter | ICU, ventilators, wounds; multidrug and carbapenem resistance | Oxidase-negative, no pigment |
| B. Haemophilus influenzae | Small coccobacillus | Positive, but not used for ID | Not used for ID | Needs X (hemin) and V (NAD+); grows on chocolate agar | Fastidious; no pigment or odor |
| C. Klebsiella pneumoniae | Encapsulated, nonmotile rod | Negative | Ferments rapidly | Currant jelly sputum, upper lobes; alcohol use disorder, diabetes | Lactose fermenter |
| D. Pseudomonas aeruginosa | Rod | Positive | Nonfermenter | Blue-green pigment, grape-like odor | Correct |
| E. Serratia marcescens | Rod | Negative | Slow in some strains | Red pigment; nosocomial urinary, respiratory and wound infections | Oxidase-negative; red, not blue-green |
Why each distractor tempts you, and why it fails
A. Acinetobacter baumannii. It tempts because it is a leading ICU and ventilator pathogen that also does not ferment lactose and is notorious for multidrug and carbapenem resistance. It fails because it is an oxidase-negative, nonpigmented coccobacillus. If a stem says "ICU outbreak, ventilator, oxidase-negative coccobacillus, resistant to carbapenems," pick Acinetobacter.
B. Haemophilus influenzae. It tempts because it is a common respiratory pathogen. It fails because it is a small, fastidious coccobacillus that needs factor X (hemin) and factor V (NAD+) and grows on chocolate agar but not on sheep blood agar, with no pigment or odor. Nontypeable strains cause otitis media, sinusitis, conjunctivitis and bronchitis; type b caused most invasive disease (meningitis, epiglottitis) before the vaccine. Review it with this H. influenzae mnemonic.
C. Klebsiella pneumoniae. It tempts because it causes severe pneumonia in people with diabetes or alcohol use disorder. It fails because it is an encapsulated, nonmotile lactose fermenter (oxidase-negative, like the other coliforms) whose clues are "currant jelly" sputum, upper lobe disease and a bulging fissure. See the full Klebsiella pneumoniae breakdown.
E. Serratia marcescens. It tempts because it is a hospital gram-negative rod that causes urinary, respiratory and wound infections and outbreaks. It fails because it is oxidase-negative, and its pigment, when present, is red, not blue-green.
Where Pseudomonas shows up
P. aeruginosa favors moist environments (in hospitals: sinks, antiseptic solutions, urine receptacles) and mostly infects hospitalized, neutropenic, debilitated or immunocompromised patients.
| Setting | Stem clue |
|---|---|
| VAP or hospital-acquired pneumonia | Intubated more than 48 hours, prior IV antibiotics |
| Cystic fibrosis | Chronic lung infection with mucoid strains and biofilm |
| Burns | Infection under the eschar, blue-green drainage, bacteremia |
| Hot tub folliculitis | Folliculitis after hot tub use |
| Otitis externa | Swimmer's ear, the most common Pseudomonas ear infection |
| Malignant (necrotizing) otitis externa | Invasive ear infection in a patient with diabetes |
| Ecthyma gangrenosum | Skin lesion in a neutropenic patient |
| Osteomyelitis | Deep puncture wound of the foot |
| Keratitis | Corneal ulcer, usually after trauma; sometimes contaminated contact lenses or lens fluid |
| Nosocomial UTI | Urologic instrumentation, obstruction or a urinary catheter |
| Endocarditis | Prosthetic valve after heart surgery, or native valve in people who inject drugs |
Virulence factors worth one question
- Exotoxin A ADP-ribosylates elongation factor 2 (EF-2) and stops protein synthesis, the same mechanism as diphtheria toxin (compare it in this Corynebacterium diphtheriae review).
- Pyocyanin is toxic to host tissue as well as a pigment.
- A type III secretion system injects toxins directly into host cells.
- Biofilm protects the organism on devices and in the CF lung and adds to antibiotic resistance, along with efflux pumps and beta-lactamases.
Treatment (Step 2 CK)
Antipseudomonal agents: piperacillin-tazobactam; ceftazidime and cefepime; imipenem and meropenem; aztreonam (no gram-positive or anaerobic activity); ciprofloxacin and levofloxacin; and aminoglycosides, never as the only antipseudomonal drug. Not antipseudomonal: ceftriaxone and cefotaxime, and ertapenem (even strains susceptible to imipenem and meropenem are resistant to it). For multidrug-resistant strains, ceftolozane-tazobactam, ceftazidime-avibactam, imipenem-relebactam and cefiderocol keep activity against many isolates.
IDSA/ATS 2016 HAP/VAP guideline, in brief:
- Multidrug-resistance risk factors for VAP: IV antibiotics in the past 90 days, septic shock at the time of VAP, ARDS before VAP, 5 or more days of hospitalization before VAP, and acute renal replacement therapy before VAP.
- With a risk factor: the guideline suggests two antipseudomonal agents from different classes plus vancomycin or linezolid for MRSA. Double gram-negative coverage is also suggested when more than 10% of the unit's gram-negative isolates resist the planned agent (or local data are unavailable), and MRSA coverage when more than 10–20% of the unit's S. aureus isolates are methicillin-resistant (or the rate is unknown).
- Avoid aminoglycosides and colistin in empiric regimens when other active agents are available.
- Once susceptibilities return: one active agent if the patient is not in septic shock or at high risk of death; two active agents if still in septic shock or at high risk of death; never an aminoglycoside alone.
- Duration: 7 days for HAP and for VAP.
Multidrug-resistant P. aeruginosa caused an estimated 32,600 infections among hospitalized patients and 2,700 deaths in the United States in 2017 (CDC). For the broader workup, see this hospital-acquired pneumonia overview.
Worked example: the Step 2 CK follow-up
Vignette. Go back to the same patient on the evening VAP is suspected, before any culture result. He needs vasopressors, and he received IV antibiotics 3 weeks ago. Which empiric regimen is most appropriate?
A. Ceftriaxone plus azithromycin B. Piperacillin-tazobactam alone C. Vancomycin plus piperacillin-tazobactam plus levofloxacin D. Vancomycin plus ertapenem E. Gentamicin alone
Answer: C. Septic shock, IV antibiotics within 90 days and 5 or more days in hospital are multidrug-resistance risk factors, so IDSA/ATS 2016 suggests MRSA coverage plus two antipseudomonal agents from different classes (a beta-lactam and a fluoroquinolone here). When the isolate's susceptibilities return, narrow to active therapy and treat for 7 days.
Why the others are wrong:
- A: a community-acquired pneumonia regimen; ceftriaxone does not cover Pseudomonas.
- B: one antipseudomonal agent with no MRSA coverage is reasonable only without resistance risk factors (and without high local resistance rates).
- D: ertapenem lacks reliable antipseudomonal activity.
- E: the guideline recommends against aminoglycoside monotherapy for Pseudomonas pneumonia, and gentamicin does not cover MRSA.
Key takeaways
- Oxidase-positive + non-lactose-fermenting + blue-green pigment + grape-like odor = P. aeruginosa.
- Oxidase-negative coccobacillus in an ICU outbreak = Acinetobacter; lactose fermenter with currant jelly sputum = Klebsiella; red pigment = Serratia; needs X and V = H. influenzae.
- Exotoxin A inhibits EF-2, like diphtheria toxin.
- Classic settings: VAP, CF, burns, hot tubs, otitis externa, malignant otitis externa in diabetes, ecthyma gangrenosum in neutropenia, foot puncture wounds.
- VAP with resistance risk factors: two antipseudomonal classes plus vancomycin or linezolid, then narrow; 7 days total. Ceftriaxone and ertapenem do not cover Pseudomonas.
Sources
- Kalil AC, et al. Management of Adults With Hospital-acquired and Ventilator-associated Pneumonia: 2016 IDSA/ATS Guidelines — Clinical Infectious Diseases (PMC full text)
- Pseudomonas and Related Infections — Merck Manual Professional Edition
- About Pseudomonas aeruginosa — CDC
- Kesarwani M, et al. A Quorum Sensing Regulated Small Volatile Molecule Reduces Acute Virulence and Promotes Chronic Infection Phenotypes — PLOS Pathogens (2011)
- Michalska M, Wolf P. Pseudomonas Exotoxin A: optimized by evolution for effective killing — Frontiers in Microbiology (2015)
- Manual for the Laboratory Identification and Antimicrobial Susceptibility Testing of Bacterial Pathogens of Public Health Importance in the Developing World — CDC and WHO (2003)
- Yehya A, et al. The intricacies of Acinetobacter baumannii: a comprehensive review — Frontiers in Microbiology (2025)
- Klebsiella, Enterobacter, and Serratia Infections — Merck Manual Professional Edition
- Haemophilus Infections — Merck Manual Professional Edition
- Cephalosporins — Merck Manual Professional Edition
- Carbapenems — Merck Manual Professional Edition
- Monobactams — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
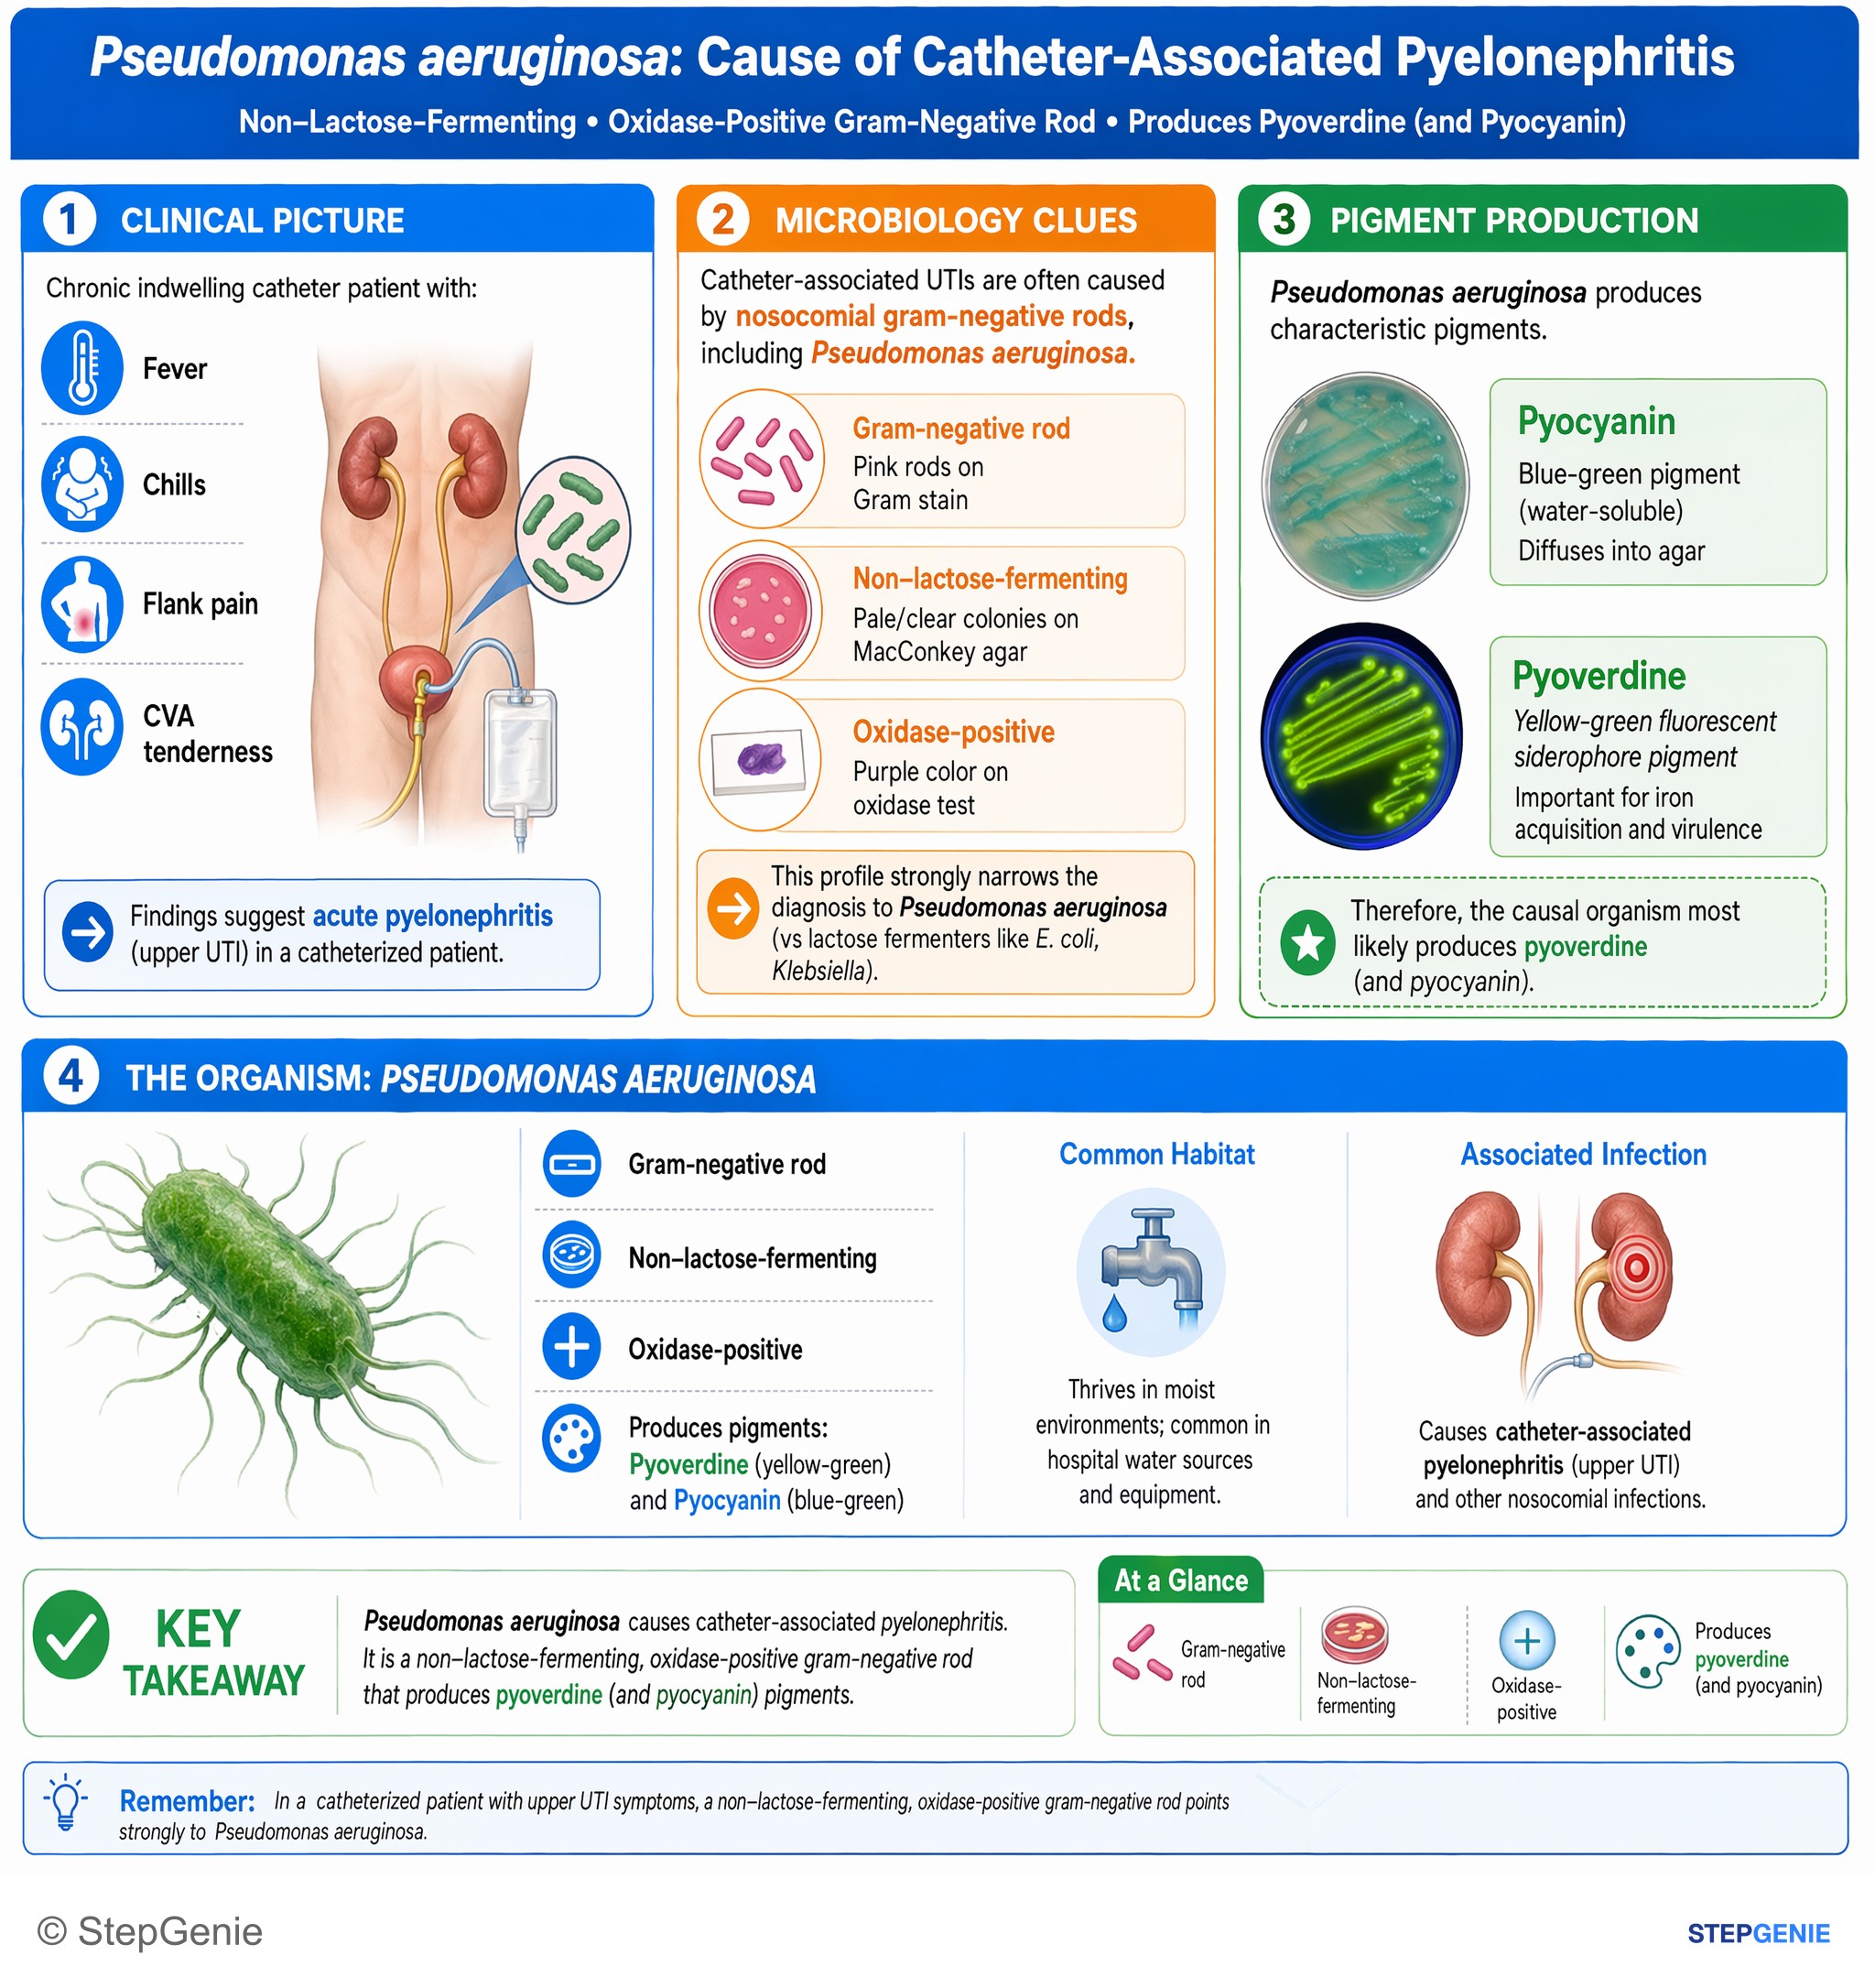
Pseudomonas aeruginosa causes catheter-associated pyelonephritis; it is a non–lactose-fermenting, oxidase-positive gram-negative rod that…
USMLE Step 1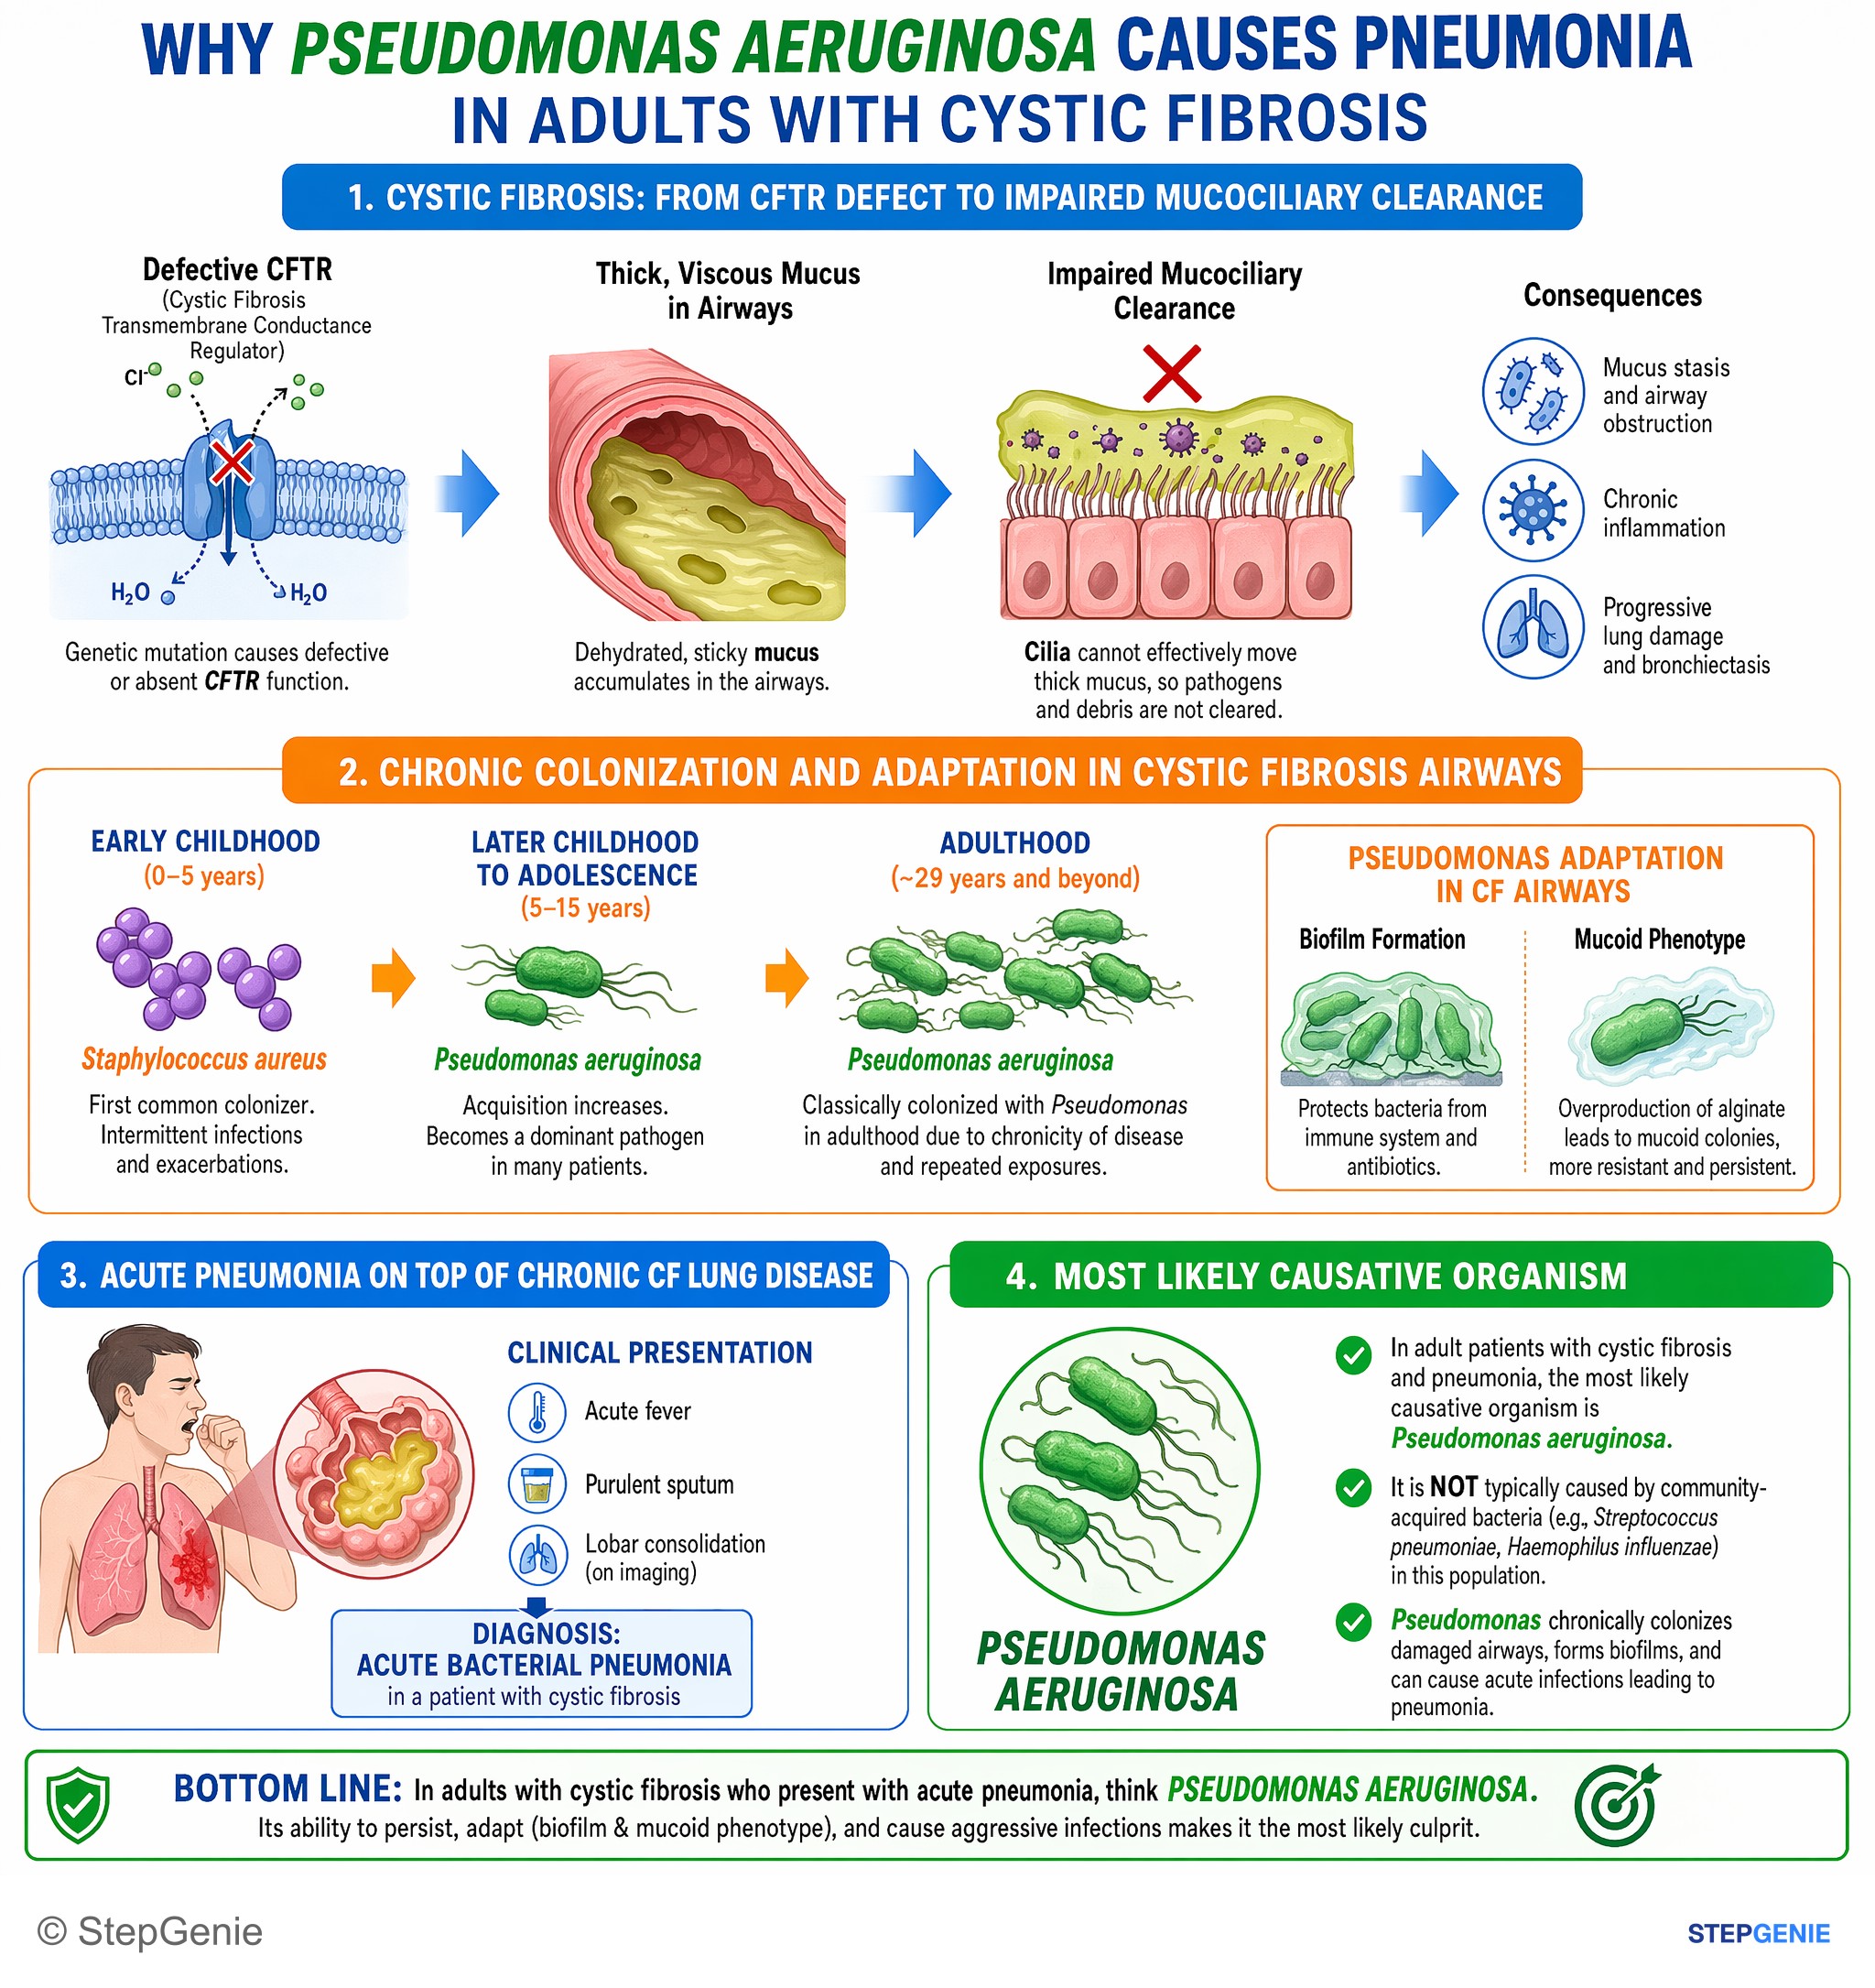
Pseudomonas aeruginosa commonly causes pneumonia in adults with cystic fibrosis due to chronic colonization of damaged airways and biofilm…
USMLE Step 1Frequently Asked Questions
What lab findings identify Pseudomonas aeruginosa?
P. aeruginosa is an aerobic gram-negative rod that is oxidase-positive and does not ferment lactose. Colonies make the blue-green pigment pyocyanin, often with the fluorescent pigment pyoverdine (fluorescein), and give off a grape-like odor from 2-aminoacetophenone. Mucoid, biofilm-forming strains are typical of chronic lung infection in cystic fibrosis.
How do you tell Pseudomonas from Acinetobacter on a USMLE question?
Both are hospital pathogens that cause ventilator-associated pneumonia, both are nonfermenters and both can be highly drug-resistant, so the setting alone will not separate them. The oxidase test does: Pseudomonas is oxidase-positive, while Acinetobacter is an oxidase-negative coccobacillus. Pseudomonas also adds blue-green pigment and a grape-like odor, whereas Acinetobacter is nonpigmented and is classically linked to ICU outbreaks and carbapenem resistance.
Which antibiotics cover Pseudomonas aeruginosa?
Antipseudomonal options include piperacillin-tazobactam, ceftazidime, cefepime, imipenem, meropenem, aztreonam, ciprofloxacin, levofloxacin and aminoglycosides, which should not be the only antipseudomonal drug. Ceftriaxone, cefotaxime and ertapenem do not reliably cover it. For multidrug-resistant strains, ceftolozane-tazobactam, ceftazidime-avibactam, imipenem-relebactam and cefiderocol remain active against many isolates.
When should VAP be treated with two antipseudomonal antibiotics?
The 2016 IDSA/ATS guideline suggests (a weak recommendation) two antipseudomonal agents from different classes for suspected VAP when the patient has a multidrug-resistance risk factor: IV antibiotics in the past 90 days, septic shock, ARDS before VAP, 5 or more days in hospital before VAP, or acute renal replacement therapy. It also applies when more than 10% of the unit's gram-negative isolates resist the planned agent or local data are unavailable. Therapy is narrowed once susceptibilities are known.
How does Pseudomonas exotoxin A work?
Exotoxin A transfers an ADP-ribose group from NAD+ onto elongation factor 2 (EF-2), which halts protein synthesis in the host cell. This is the same intracellular mechanism as diphtheria toxin, a pairing that boards like to test. Pseudomonas also injects other toxins directly into host cells through a type III secretion system.