The eight human herpesviruses (HHV-1 to HHV-8) are enveloped double-stranded DNA viruses that infect for life by going latent and reactivating later. The latency sites to know: HSV-1 in the trigeminal ganglion, HSV-2 in sacral ganglia, VZV in dorsal root and cranial nerve ganglia, EBV in B cells, and CMV in myeloid progenitors and monocytes. PCR has replaced the Tzanck smear, and a heterophile-positive mononucleosis is EBV, while CMV causes a heterophile-negative mono-like illness. Acyclovir needs viral thymidine kinase, ganciclovir needs the CMV UL97 kinase and suppresses the marrow, and foscarnet and cidofovir need no viral kinase, so they treat resistant virus at the cost of kidney toxicity.
The eight herpesviruses at a glance
| Virus | Latency | Classic diseases | Exam clue |
|---|---|---|---|
| HSV-1 (HHV-1) | Trigeminal ganglion | Gingivostomatitis, cold sores, keratitis, temporal lobe encephalitis | Painful grouped vesicles on a red base |
| HSV-2 (HHV-2) | Sacral ganglia | Genital herpes, neonatal herpes, viral meningitis | Painful genital ulcers |
| VZV (HHV-3) | Dorsal root and cranial nerve ganglia | Varicella, zoster, zoster ophthalmicus, Ramsay Hunt syndrome | Lesions in different stages; dermatomal rash |
| EBV (HHV-4) | B cells (enters via CD21) | Mononucleosis, Burkitt and Hodgkin lymphoma, nasopharyngeal carcinoma, post-transplant lymphoproliferative disorder | Heterophile-positive; atypical CD8+ T cells |
| CMV (HHV-5) | CD34+ myeloid progenitors and monocytes | Congenital infection, heterophile-negative mono, retinitis (AIDS), pneumonitis and colitis (transplant) | "Owl's eye" intranuclear inclusions |
| HHV-6B and HHV-7 | Monocytes and macrophages (HHV-6B); CD4+ T cells (HHV-7) | Roseola infantum | 3–5 days of high fever, then rash |
| HHV-8 (KSHV) | B cells and endothelial cells | Kaposi sarcoma, primary effusion lymphoma, multicentric Castleman disease | Purple skin plaques in AIDS or after transplant |
Shared biology: a large dsDNA genome in an icosahedral capsid, wrapped in a tegument and a lipid envelope picked up by budding through the nuclear membrane. Infected cells can fuse into multinucleated giant cells with intranuclear inclusions. Reactivation triggers for HSV include sunlight, fever, stress, immunosuppression and hormonal changes, and all herpesviruses are more dangerous in immunocompromised hosts (dissemination, hepatitis, retinitis, pneumonia, colitis).
HSV-1 and HSV-2
- Lesion: clusters of small, painful vesicles on an erythematous base. Either type can infect any site; HSV-1 causes a growing share of genital herpes, but genital HSV-2 recurs and sheds far more often (CDC).
- Other HSV lesions: dendritic corneal ulcers (keratitis), herpetic whitlow on a finger, eczema herpeticum, and HSV-triggered erythema multiforme.
- Encephalitis: classically temporal lobe; diagnose with CSF PCR and MRI and treat with IV acyclovir for 14–21 days (compare the causes in the viral meningitis and encephalitis guide).
- Neonatal herpes: usually appears in weeks 1–4 of life. Transmission risk is 30–50% when the mother acquires genital HSV near delivery versus under 1% with recurrent maternal herpes; in women with recurrent herpes, suppressive acyclovir from 36 weeks reduces cesarean deliveries.
- Esophagitis in immunocompromised patients: HSV causes more, smaller ulcers; CMV causes fewer, larger ones.
- Treating a primary episode does not prevent recurrences.
VZV: chickenpox now, shingles later
- Varicella: incubation 14–16 days (range 10–21); contagious from 1–2 days before the rash until all lesions crust. Lesions come in crops, so papules, "teardrop" vesicles and crusts coexist, almost always involving the upper trunk.
- Complications: bacterial skin infection in children, pneumonia in adults; severe disease in immunocompromised and pregnant people and in certain newborns.
- Zoster: pain first, then within 2–3 days a unilateral dermatomal vesicular rash. Hutchinson sign (vesicles on the nose tip) raises the risk of eye involvement in V1 zoster ophthalmicus; Ramsay Hunt syndrome (geniculate ganglion) causes ear pain, facial paralysis and taste loss. Postherpetic neuralgia is pain lasting more than 3 months, mostly in older adults.
- Treatment: acyclovir, valacyclovir or famciclovir, ideally within 72 hours of the rash.
- Prevention: 2 doses of varicella vaccine for children, adolescents and adults without evidence of immunity; recombinant zoster vaccine (2 doses, 2–6 months apart) for adults 50 or older and adults 19 or older who are or will be immunodeficient.
EBV: mono and malignancy
- Spread by saliva; enters B cells via CD21. The atypical lymphocytes (up to 30% of white cells) are mostly CD8+ T cells killing infected B cells.
- Mononucleosis: fever, pharyngitis and lymphadenopathy (posterior cervical or generalized nodes suggest mono), splenomegaly in about 50%, palatal petechiae, periorbital edema and raised aminotransferases in about 90%.
- Ampicillin or amoxicillin rash: the classic exam clue, but Merck notes newer data showing a rash in up to about 20% of patients and suggesting antibiotics may not raise that rate.
- Management: supportive; glucocorticoids only for complications such as airway obstruction; acyclovir is not clinically useful. No contact sports or heavy lifting for 1 month and until the spleen shrinks.
- Associations: Burkitt lymphoma (reviewed in the non-Hodgkin lymphoma Q-bank), Hodgkin lymphoma, nasopharyngeal carcinoma, post-transplant lymphoproliferative disorder and oral hairy leukoplakia in HIV. X-linked lymphoproliferative disease predisposes to severe EBV.
CMV: the opportunist
- Mono-like illness: fever, hepatitis and atypical lymphocytes without severe pharyngitis, and heterophile-negative.
- Congenital CMV: about 1 in 200 US babies; about 1 in 5 of them has birth defects or long-term problems such as sensorineural hearing loss. It is the most common infectious cause of birth defects in the US. Signs include petechiae, jaundice, microcephaly, growth restriction, hepatosplenomegaly, seizures, retinitis and periventricular calcifications. Test saliva, urine or blood by PCR within 2–3 weeks of birth; in newborns with signs of disease, ganciclovir or valganciclovir may improve hearing and developmental outcomes.
- AIDS: end-organ disease typically at CD4 < 50/µL. Retinitis shows fluffy yellow-white retinal lesions with or without hemorrhage; colitis and esophagitis also occur, but pneumonitis is uncommon in HIV. See the CD4 count and opportunistic infection table.
- Transplant: pneumonitis, colitis and esophagitis. A positive PCR alone does not prove disease; histopathology showing owl's eye inclusions is the gold standard for tissue-invasive disease.
HHV-6, HHV-7 and HHV-8
- Roseola infantum (HHV-6B, less often HHV-7): a child aged 6 months to 3 years has abrupt fever of 39.5–40.5 °C for 3–5 days, then a macular or maculopapular rash on the trunk as the fever falls. Febrile seizures can occur; care is supportive.
- HHV-8 is shed in saliva, likely an important route of spread, and exposure to genital secretions also plays a role. It is found in nearly all Kaposi sarcoma biopsies: classic (older men of Italian or Eastern European Jewish ancestry), endemic African, AIDS-associated and transplant-related forms, with red, purple or brown patches, plaques or nodules. It also causes primary effusion lymphoma and multicentric Castleman disease.
Diagnostic tests
| Test | What it shows | Key limitation |
|---|---|---|
| Tzanck smear | Multinucleated giant cells (HSV-1, HSV-2, VZV) | Low sensitivity; cannot tell HSV from VZV; CDC says it should not be relied on |
| PCR (NAAT) of lesion or CSF | HSV or VZV DNA | Preferred test; CSF PCR for encephalitis |
| Heterophile antibodies (Monospot) | Nonspecific antibodies of EBV mono, detected by a rapid agglutination card test | Positive in 85–90% of adolescents and adults but only about 50% of children aged 2–5; often negative in the first week; CDC does not recommend Monospot for general use |
| EBV-specific serology | VCA IgM without EBNA antibody = primary infection | EBNA antibody appears 2–4 months after onset and persists for life |
| CMV PCR and biopsy | Viral DNA; owl's eye inclusions | PCR alone does not prove tissue disease |
Antivirals: mechanism and toxicity
| Drug | How it works | Main uses | Toxicity |
|---|---|---|---|
| Acyclovir (valacyclovir is its prodrug; famciclovir becomes penciclovir) | Viral thymidine kinase adds the first phosphate, host kinases make the triphosphate, which inhibits viral DNA polymerase and terminates the chain | HSV, VZV | Crystal nephropathy (hydrate), neurotoxicity (lethargy, confusion, seizures) |
| Ganciclovir (oral prodrug valganciclovir) | CMV UL97 kinase adds the first phosphate; the triphosphate inhibits the UL54 DNA polymerase | CMV treatment and prevention | Neutropenia, anemia, thrombocytopenia; boxed warnings for impaired fertility, fetal toxicity and carcinogenicity |
| Foscarnet | Pyrophosphate analog that binds the polymerase's pyrophosphate site; no activation needed | CMV retinitis, ganciclovir-resistant CMV, acyclovir-resistant HSV | Nephrotoxicity; low calcium (including ionized), magnesium and potassium, and high or low phosphate, causing seizures; QT prolongation |
| Cidofovir | Nucleotide analog phosphorylated only by host kinases, so no viral kinase needed | CMV retinitis in AIDS; resistant virus | Nephrotoxicity (give with probenecid and IV saline), neutropenia, ocular hypotony |
| Letermovir | Inhibits the CMV DNA terminase complex | CMV prophylaxis after allogeneic stem cell or high-risk kidney transplant | Nausea, diarrhea; CYP3A drug interactions |
| Maribavir | Inhibits the UL97 kinase | Post-transplant CMV refractory to other drugs | Taste disturbance; antagonizes ganciclovir |
Resistance logic: HSV that escapes acyclovir usually has a mutant or absent thymidine kinase, and those mutants are cross-resistant to penciclovir. CMV that escapes ganciclovir carries UL97 (or UL54) mutations. Foscarnet and cidofovir bypass both kinases, although UL54 polymerase mutants can be cross-resistant to them.
Practice question
A 34-year-old man with untreated HIV (CD4 22/µL) has enlarging, painful perianal ulcers despite 10 days of high-dose valacyclovir. Lesion PCR detects HSV-2, and genotyping shows a thymidine kinase mutation. Which treatment is most appropriate?
- A. High-dose IV acyclovir
- B. Famciclovir
- C. Letermovir
- D. IV foscarnet
- E. IV cidofovir
Answer: D. Foscarnet is a pyrophosphate analog that blocks the viral DNA polymerase without activation by thymidine kinase, and CDC names it the treatment of choice for acyclovir-resistant genital herpes. Monitor creatinine, calcium (including ionized), magnesium, potassium and phosphate, and hydrate with every dose.
- A: acyclovir still needs viral thymidine kinase for its first phosphorylation, so a higher dose does not help.
- B: penciclovir, famciclovir's active form, is also activated by viral thymidine kinase; TK-negative acyclovir-resistant mutants are cross-resistant.
- C: letermovir inhibits the CMV terminase and is used only for CMV prophylaxis after transplant.
- E: cidofovir also bypasses viral thymidine kinase, but it is not CDC's treatment of choice: the guideline lists only compounded topical cidofovir gel (with imiquimod) as an alternative, and CDC notes that foscarnet and cidofovir are both nephrotoxic.
Key takeaways
- Latency: HSV-1 trigeminal, HSV-2 sacral, VZV dorsal root and cranial nerve ganglia, EBV B cells, CMV myeloid progenitors and monocytes, HHV-8 B cells and endothelium.
- EBV mono is heterophile-positive with atypical CD8+ T cells; CMV mono is heterophile-negative. Confirm EBV with VCA IgM without EBNA.
- Tzanck smear shows giant cells for HSV and VZV but is outdated; PCR is the test.
- Congenital CMV (about 1 in 200 births) causes hearing loss and periventricular calcifications; CMV retinitis appears at CD4 < 50/µL.
- Acyclovir needs viral thymidine kinase; ganciclovir needs UL97 and suppresses marrow.
- Foscarnet (electrolytes, seizures, kidneys) and cidofovir (kidneys, neutropenia) need no viral kinase and treat resistant virus.
Sources
- Herpes Simplex Virus (HSV) Infections — Merck Manual Professional Edition
- Herpes Zoster — Merck Manual Professional Edition
- Infectious Mononucleosis — Merck Manual Professional Edition
- Cytomegalovirus (CMV) Infection — Merck Manual Professional Edition
- Roseola Infantum — Merck Manual Professional Edition
- Genital Herpes: STI Treatment Guidelines, 2021 — CDC (updated 2022)
- Clinical Overview of Chickenpox (Varicella) — CDC
- Laboratory Testing for Epstein-Barr Virus (EBV) — CDC
- CMV in Newborns (Congenital CMV) — CDC
- Cytomegalovirus Disease: Adult and Adolescent Opportunistic Infection Guidelines — NIH, clinicalinfo.hiv.gov (2025)
- Crawford LB, et al. Advances in Model Systems for Human Cytomegalovirus Latency and Reactivation — mBio (2022)
- Ganciclovir Injection Prescribing Information — DailyMed, National Library of Medicine
- Foscavir (Foscarnet) Prescribing Information — DailyMed, National Library of Medicine
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
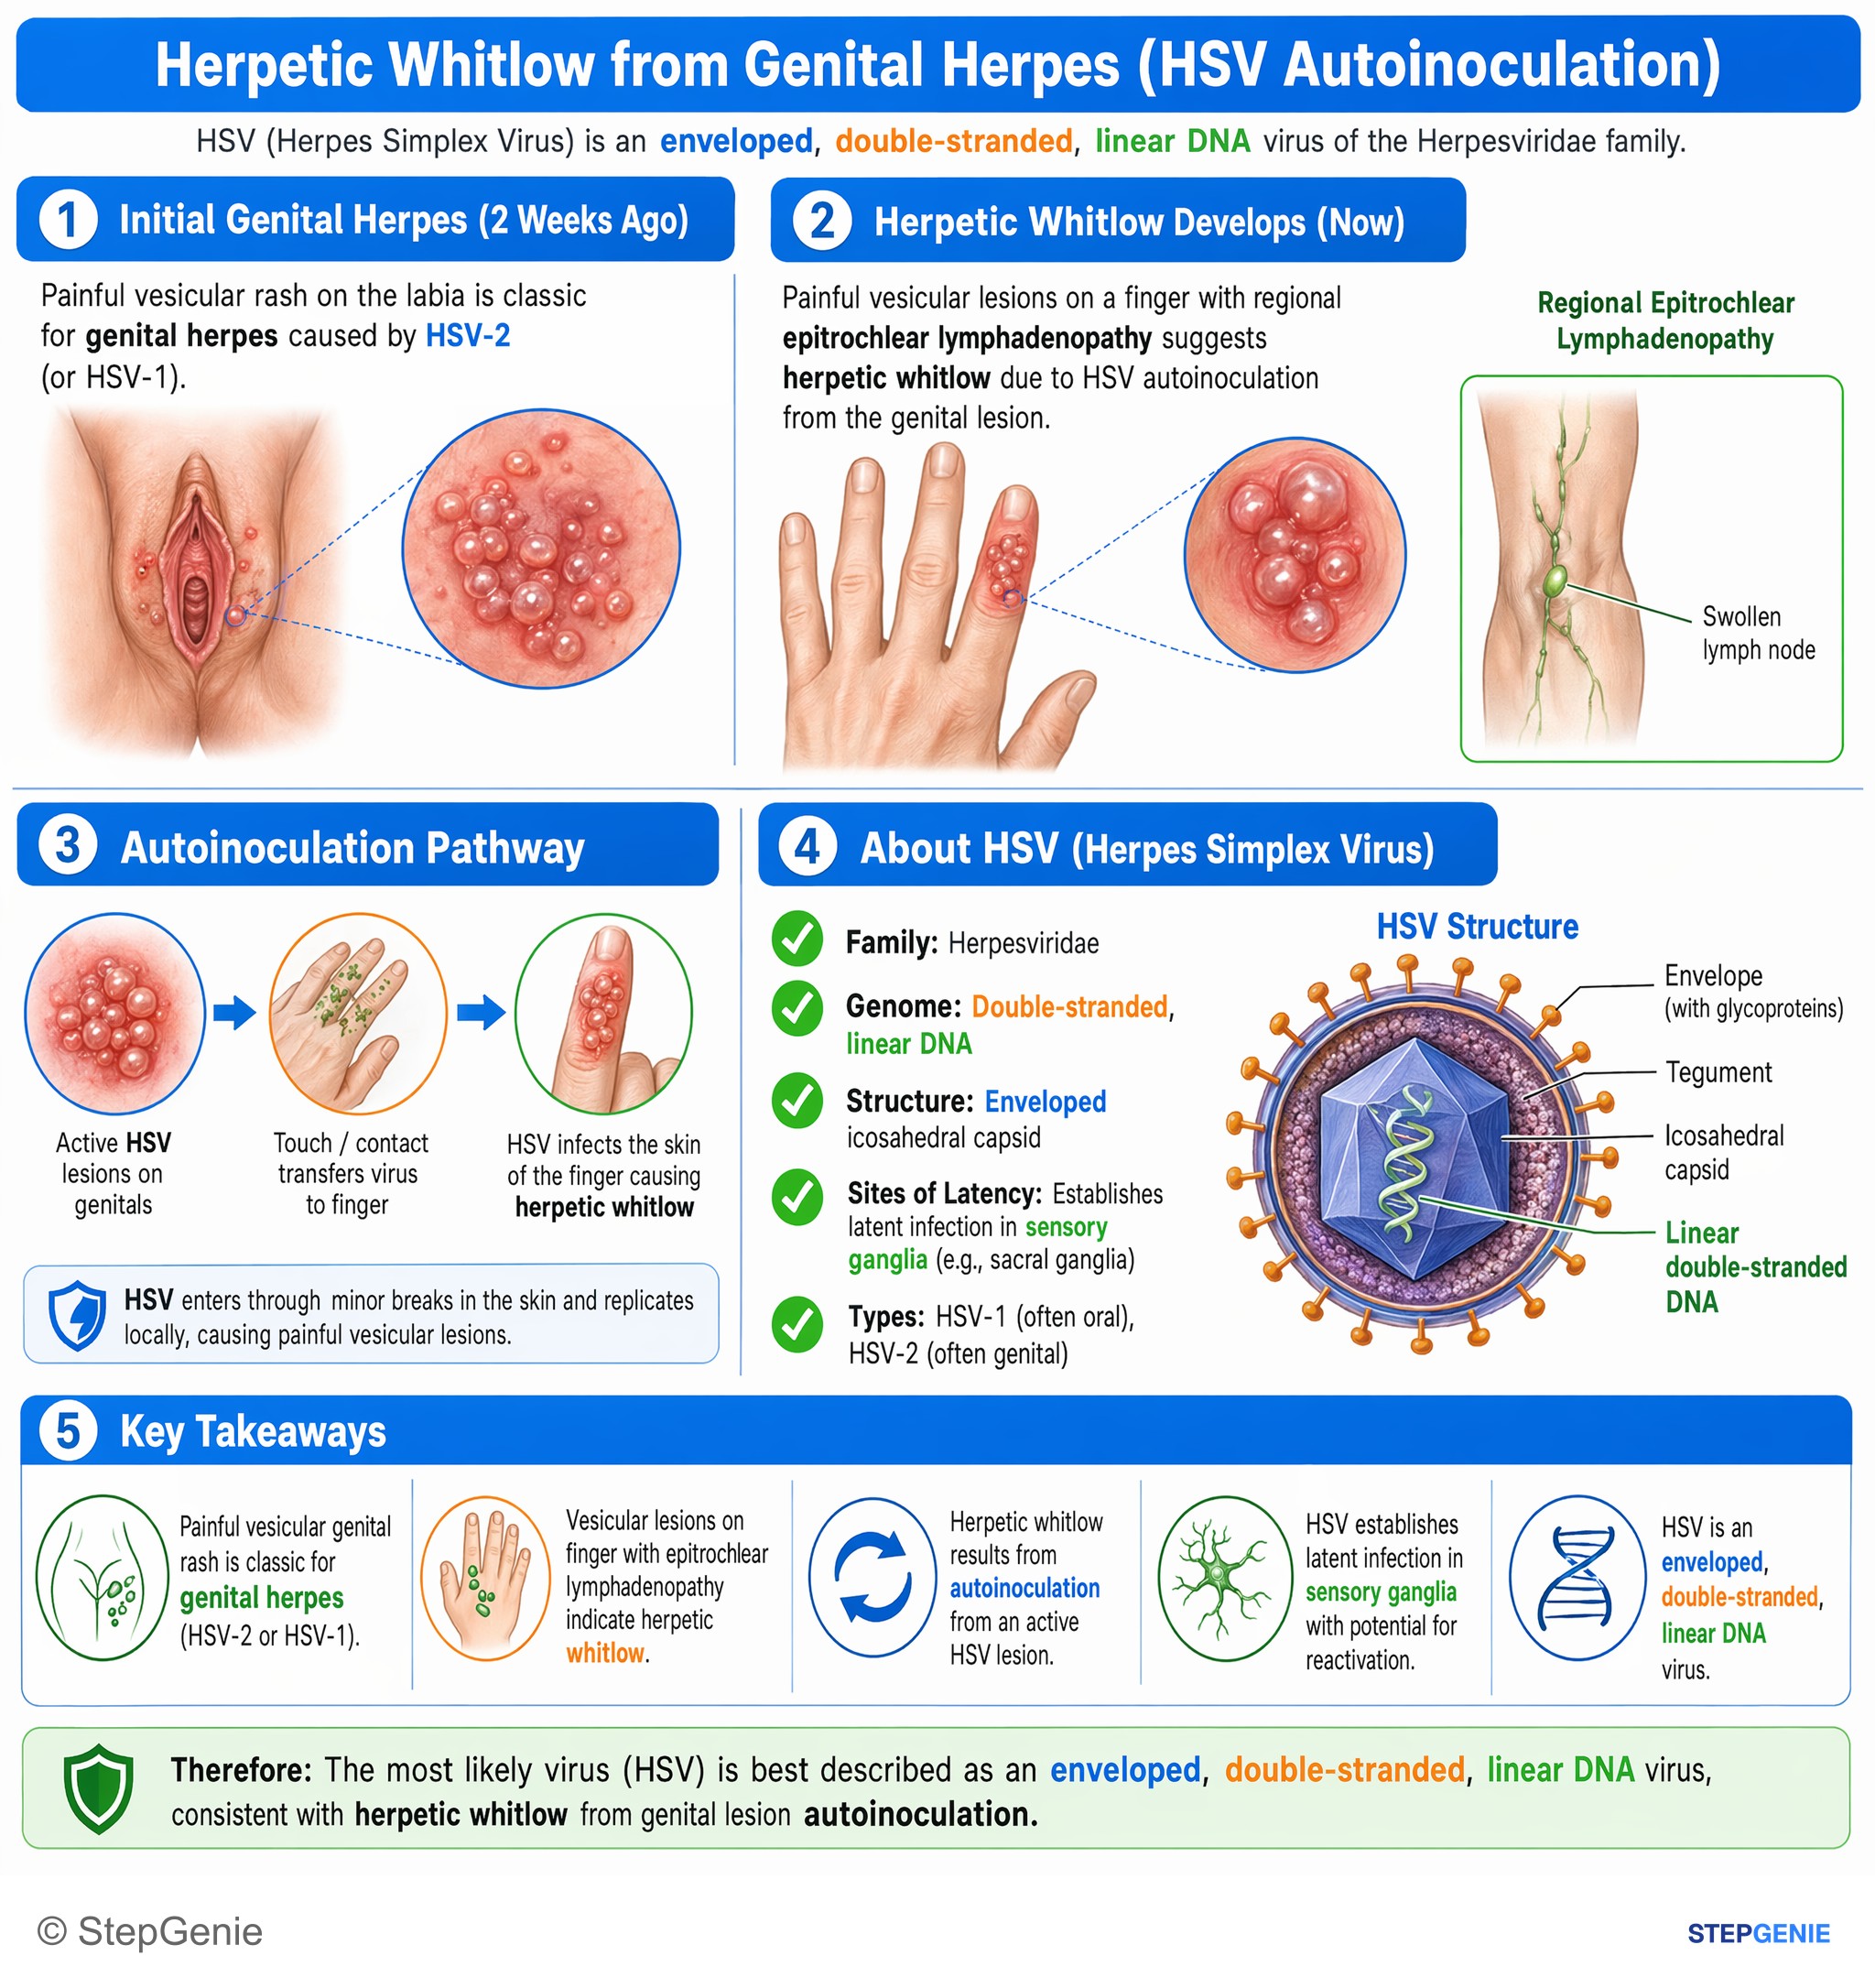
HSV infection (herpetic whitlow) from genital lesion autoinoculation; HSV is an enveloped, double-stranded, linear DNA virus establishing…
USMLE Step 1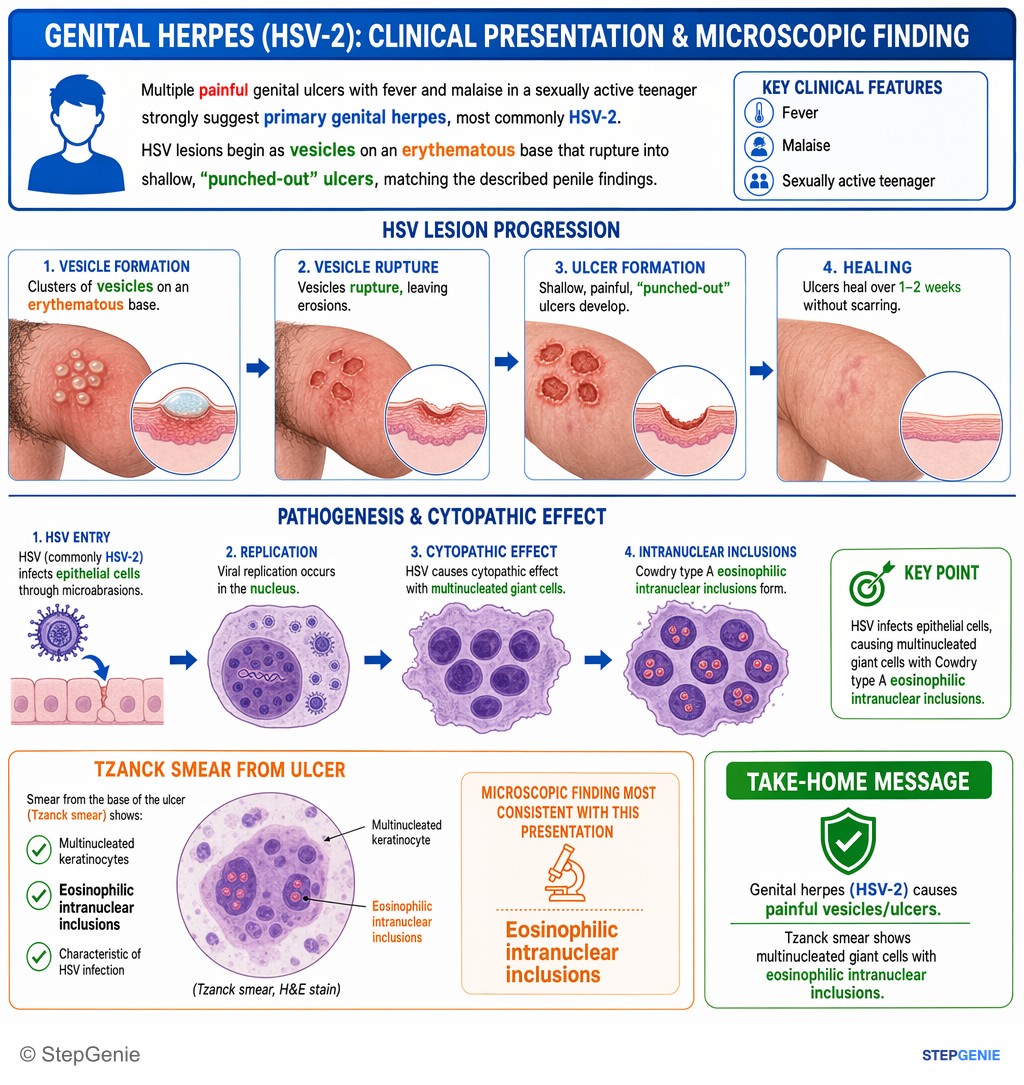
Genital herpes (HSV-2) causes painful vesicles/ulcers with multinucleated giant cells and eosinophilic intranuclear inclusions on Tzanck…
USMLE Step 1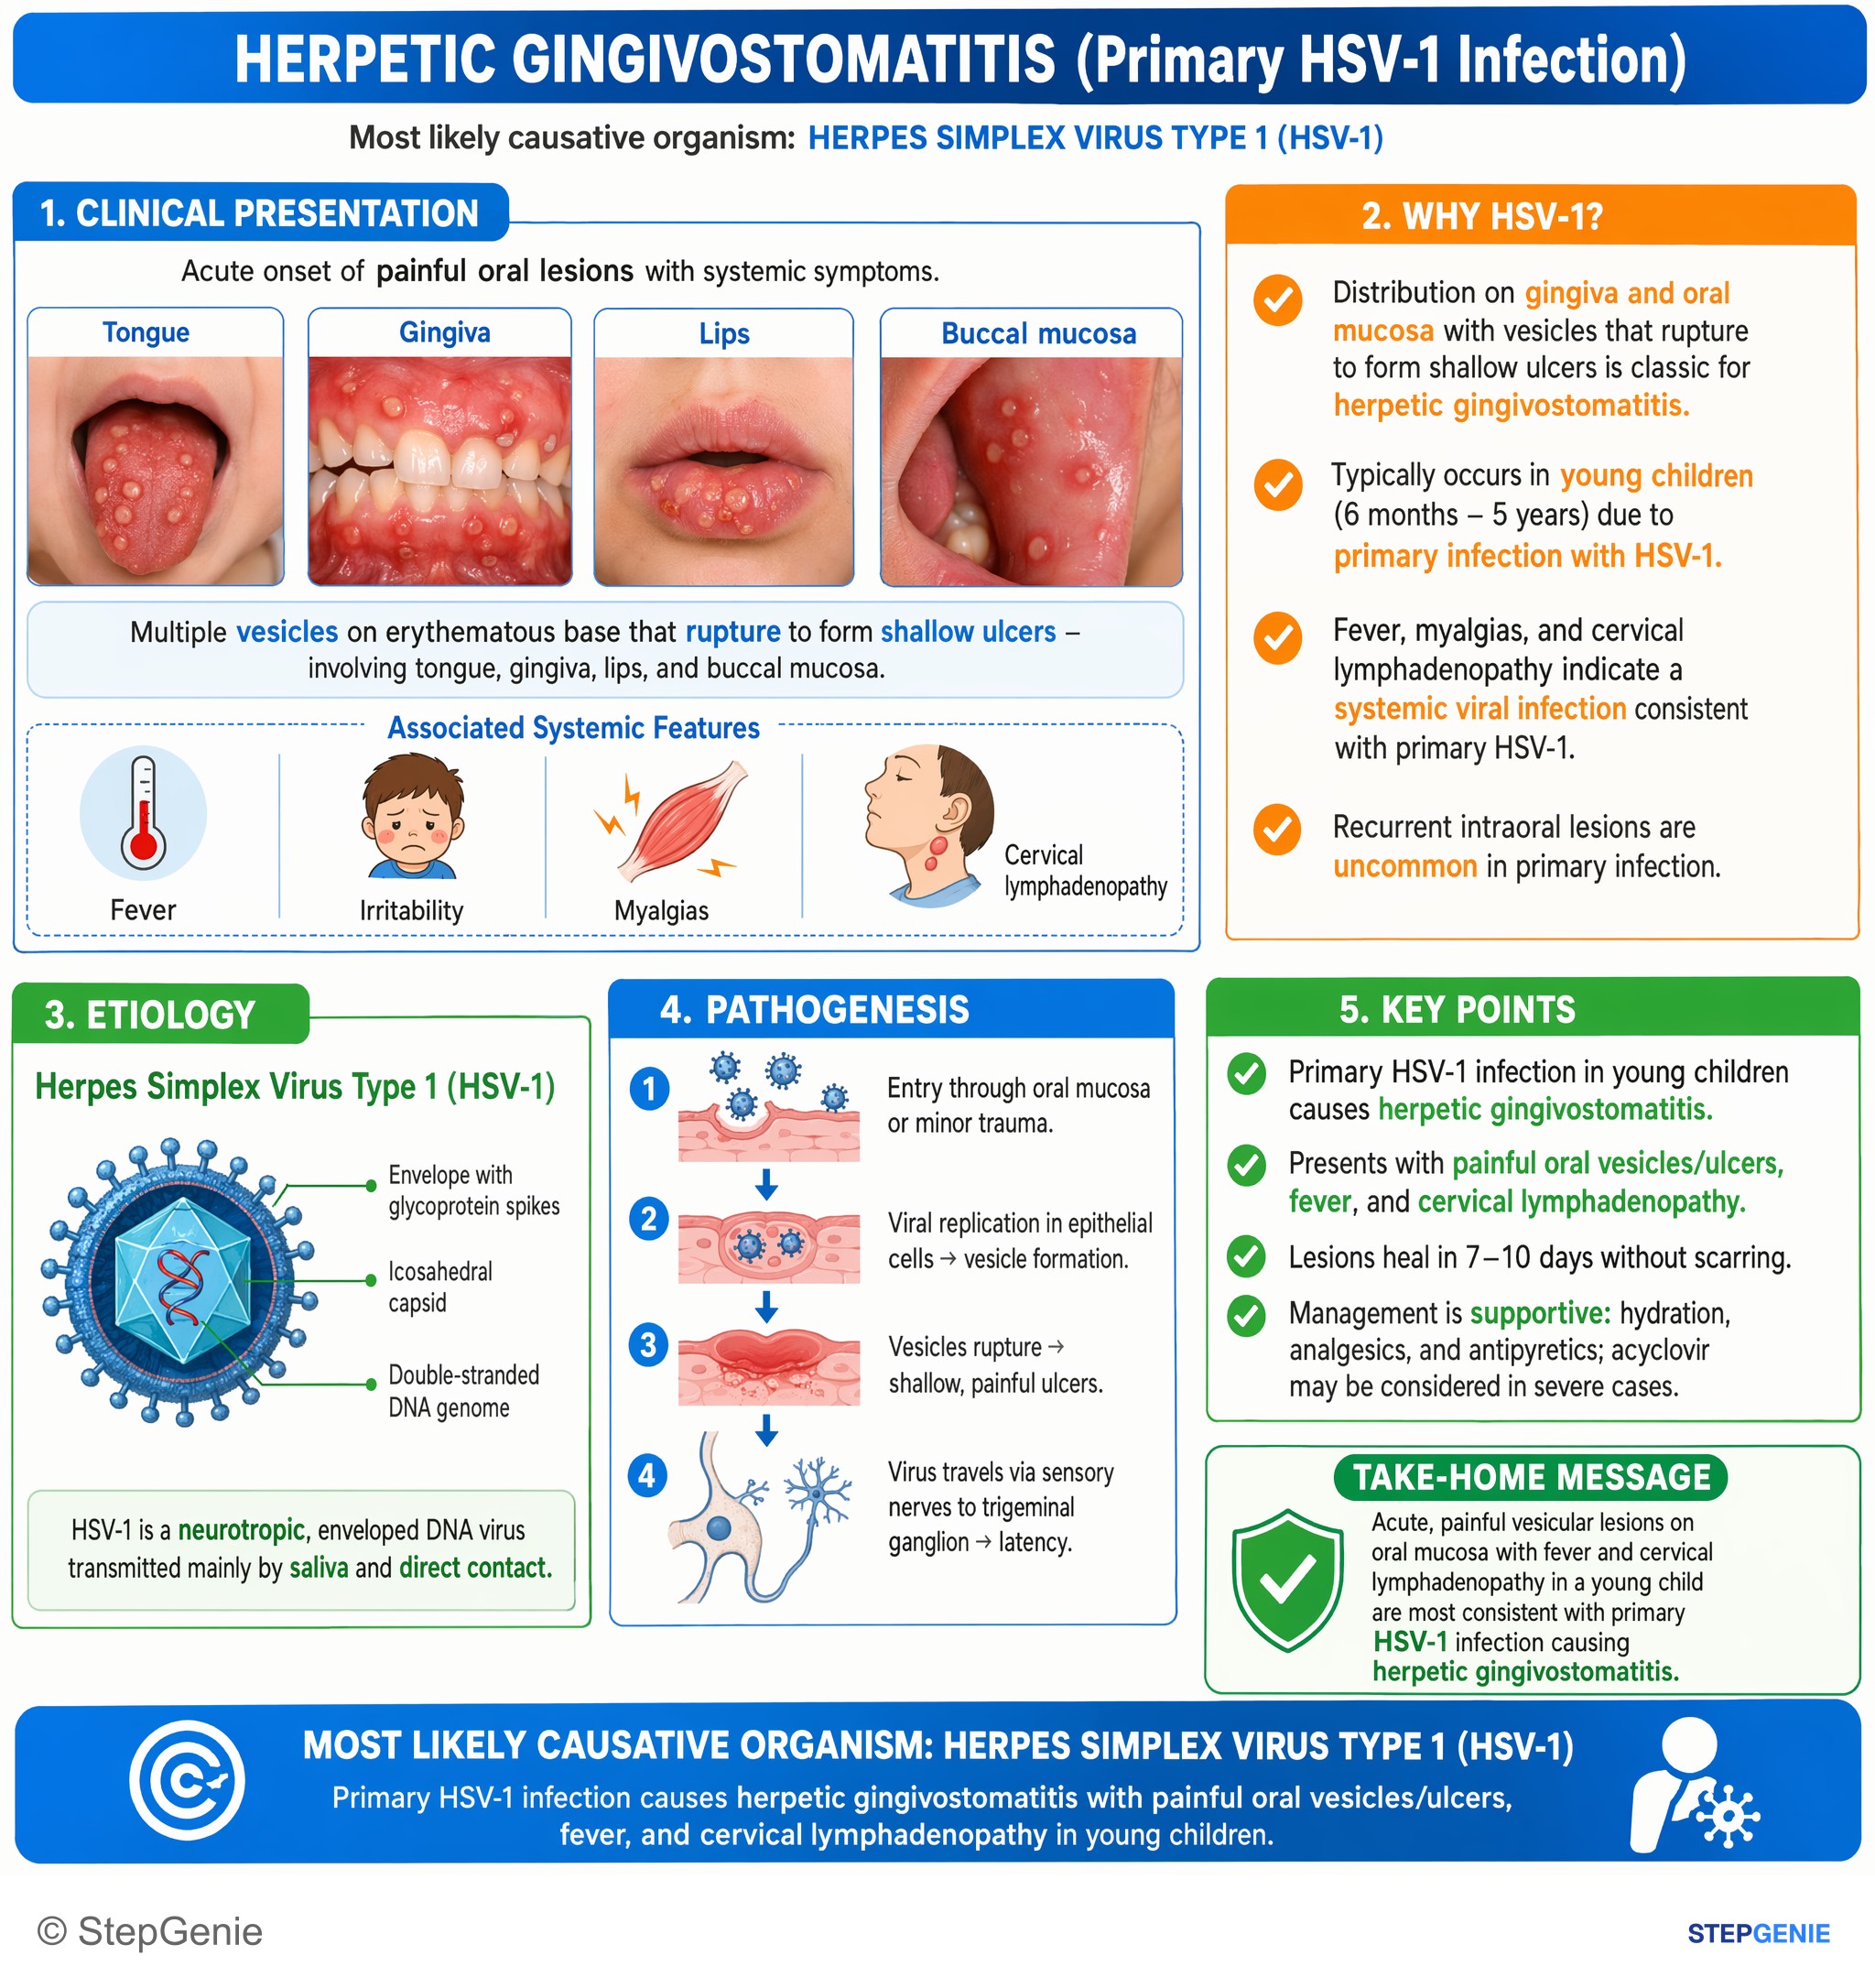
Primary HSV-1 infection causes herpetic gingivostomatitis with painful oral vesicles/ulcers, fever, and cervical lymphadenopathy in young…
USMLE Step 1Frequently Asked Questions
Where does each herpesvirus stay latent?
HSV-1 stays latent in the trigeminal ganglion, HSV-2 in the sacral ganglia, and VZV in dorsal root and cranial nerve ganglia. EBV persists in B cells and CMV in CD34+ myeloid progenitor cells and monocytes. HHV-6B persists mainly in monocytes and macrophages, HHV-7 in CD4+ T cells, and HHV-8 in B cells and endothelial cells.
What are the 8 human herpesviruses?
They are HHV-1 (herpes simplex virus 1), HHV-2 (herpes simplex virus 2), HHV-3 (varicella-zoster virus), HHV-4 (Epstein-Barr virus), HHV-5 (cytomegalovirus), HHV-6 (6A and 6B), HHV-7, and HHV-8 (Kaposi sarcoma-associated herpesvirus). All are enveloped double-stranded DNA viruses that establish lifelong latency and can reactivate.
How do you tell EBV mononucleosis from CMV mononucleosis?
EBV mononucleosis is usually heterophile-positive, with fever, pharyngitis, lymphadenopathy, splenomegaly and atypical CD8+ T cells. CMV causes a mono-like illness with fever, hepatitis and atypical lymphocytes but without severe pharyngitis, and the heterophile test is negative. Heterophile tests are often negative in young children and early in illness, so EBV-specific serology (VCA IgM without EBNA antibody) confirms primary EBV infection.
What does a Tzanck smear show?
A Tzanck smear of a vesicle base shows multinucleated giant cells in HSV-1, HSV-2 and VZV infections. It cannot tell HSV from VZV and has low sensitivity, and the CDC says it should not be relied on for genital lesions. PCR of the lesion is now the preferred test.
How do acyclovir, ganciclovir and foscarnet differ?
Acyclovir is first phosphorylated by viral thymidine kinase, then its triphosphate inhibits viral DNA polymerase and terminates the DNA chain; its main toxicities are crystal nephropathy and neurotoxicity. Ganciclovir is first phosphorylated by the CMV UL97 kinase and mainly causes neutropenia, anemia and thrombocytopenia. Foscarnet is a pyrophosphate analog that needs no activation, so it works against resistant virus, but it is nephrotoxic and lowers calcium and magnesium, which can cause seizures.
What is the treatment for acyclovir-resistant HSV?
Acyclovir resistance usually comes from a mutant or absent viral thymidine kinase. All acyclovir-resistant strains are also resistant to valacyclovir, and most are resistant to famciclovir. The CDC names IV foscarnet as the treatment of choice for acyclovir-resistant genital herpes, with topical imiquimod or compounded cidofovir gel as alternatives. Foscarnet requires hydration and close monitoring of kidney function and electrolytes.