Wiskott-Aldrich syndrome (WAS) is an X-linked recessive combined (B- and T-cell) immunodeficiency caused by mutations in the WAS gene, which encodes WASP, a protein that links cell-surface signals to the actin cytoskeleton. The classic triad is eczema, recurrent infections and thrombocytopenia with abnormally small platelets, in a boy who often bleeds first (petechiae, bloody diarrhea, prolonged bleeding after circumcision). Labs show low IgM, high IgA and IgE, and normal or low IgG, with poor antibody responses to polysaccharide antigens. Hematopoietic stem cell transplantation (HSCT) cures it, and in December 2025 the FDA approved the first gene therapy, etuvetidigene autotemcel (Waskyra), for patients without a suitable HLA-matched related donor.
The USMLE-style question
A 10-month-old boy is evaluated for recurrent infections. He has had three episodes of acute otitis media and one pneumococcal pneumonia. Since age 2 months he has had an itchy, scaly rash on his cheeks and in the flexural creases. Bleeding after his circumcision was prolonged, and he has had two episodes of bloody diarrhea. A maternal uncle died in early childhood of bleeding and infection. Examination shows eczematous plaques and scattered petechiae; tonsils are present. Hemoglobin and leukocyte count are normal. The platelet count is 28,000/mm³, and the smear shows unusually small platelets. Serum IgM is low, IgA and IgE are high, and IgG is normal. Which of the following is the most likely diagnosis?
A. Chronic granulomatous disease B. DiGeorge syndrome C. Hyper-IgE syndrome D. Immune thrombocytopenia E. Wiskott-Aldrich syndrome F. X-linked agammaglobulinemia
Answer: E. Wiskott-Aldrich syndrome
Every finding fits one diagnosis:
- Boy + affected maternal uncle = X-linked recessive inheritance.
- Eczema (present in about 80% of males with WAS) + recurrent pyogenic infections + thrombocytopenia with small platelets = the triad. Mnemonic WATER: WAS, Thrombocytopenia (tiny platelets), Eczema, Recurrent infections.
- Bleeding first: hemorrhage (bloody diarrhea, melena, purpura, epistaxis) is often the first manifestation, before infections and eczema.
- Low IgM, high IgA and IgE is the signature immunoglobulin pattern.
- Pneumococcal pneumonia and otitis reflect poor antibody responses to polysaccharide antigens (the capsules of encapsulated bacteria).
The single most discriminating clue is platelet size: GeneReviews' diagnostic criteria require a platelet count below 70,000/mm³ with small platelets (volume below 7 fL) plus another WAS feature. Platelets in immune thrombocytopenia are normal-sized or large.
Why every other answer is wrong
A. Chronic granulomatous disease (CGD)
- Tempting because: recurrent infections in a young boy; more than half of cases are X-linked.
- Wrong because: CGD is a phagocyte defect (no NADPH oxidase, so no respiratory burst). It causes recurrent abscesses and granulomas from catalase-producing organisms (S. aureus, Serratia, Klebsiella, Aspergillus), diagnosed with the dihydrorhodamine (DHR) flow test. Platelets and immunoglobulins are not the problem, and eczema is not part of the picture. Review it in the CGD guide.
B. DiGeorge syndrome
- Tempting because: T-cell immunodeficiency with recurrent infections in infancy.
- Wrong because: the 22q11.2 deletion disrupts the pharyngeal pouches: thymic hypoplasia (low T cells), hypocalcemia with tetany from underdeveloped parathyroids (often within 24-48 hours of birth), conotruncal heart defects (interrupted aortic arch, tetralogy of Fallot) and characteristic facies. No eczema, no small platelets. See the DiGeorge breakdown.
C. Hyper-IgE syndrome (Job syndrome)
- Tempting because: eczema-like dermatitis, recurrent infections and a high IgE, the closest overlap with WAS.
- Wrong because: autosomal dominant STAT3 disease (or recessive DOCK8) gives recurrent staphylococcal abscesses of the skin, lungs and joints, pneumonias, coarse facies, retained primary teeth and fractures, with IgE often above 2,000 IU/mL and eosinophilia. Nothing in it explains thrombocytopenia, small platelets or a low IgM. Use the Job syndrome FATED flowchart.
D. Immune thrombocytopenia (ITP)
- Tempting because: petechiae and isolated thrombocytopenia in a child, often after a viral infection.
- Wrong because: ITP is autoantibody-mediated platelet destruction with normal-sized or large platelets (raised mean platelet volume), normal other cell lines, and no eczema, immunodeficiency or immunoglobulin abnormality. Childhood ITP usually resolves within weeks to months.
F. X-linked agammaglobulinemia (Bruton)
- Tempting because: an X-linked disorder with recurrent encapsulated bacterial infections starting around 6 months, when maternal IgG wanes.
- Wrong because: BTK mutations block B-cell maturation, so B cells are absent and all immunoglobulins (IgG, IgA, IgM) are low, with very small or absent tonsils and lymph nodes. This boy has tonsils, high IgA and IgE, eczema and thrombocytopenia. Lock it in with the Bruton memory palace.
Wiskott-Aldrich syndrome: the high-yield facts
Pathophysiology
- Gene: WAS on the X chromosome; X-linked recessive, so affected patients are almost always boys. It is rare: MedlinePlus estimates 1-10 cases per million males, and GeneReviews 1-4 per million live male births. Place it among the other X-linked disorders.
- Protein: WASP relays signals from the surface of blood cells to the actin cytoskeleton. In white cells this lets the cytoskeleton build immune synapses, the contact zones between immune cells and their targets; without it, B- and T-cell signaling fails.
- Platelets: too few, too small (microthrombocytopenia) and defective.
Labs
| Test | Classic WAS finding |
|---|---|
| Platelet count | Below 70,000/mm³, confirmed on repeat |
| Platelet size | Small: volume below 7 fL (or MPV more than 2 SD below the mean) |
| IgM | Low |
| IgG | Normal or low |
| IgA and IgE | High |
| Antibody responses | Poor to polysaccharide antigens; isohemagglutinins absent |
| T cells | Decreased number and function |
| Confirmation | Flow cytometry for WASP protein (screen), WAS gene testing (definitive) |
Complications
- Infections: pyogenic bacteria and opportunistic organisms, especially viruses (varicella-zoster, herpes simplex) and Pneumocystis jirovecii.
- Bleeding: petechiae, bloody diarrhea, prolonged post-circumcision bleeding and intracranial hemorrhage.
- Autoimmunity: about 25-40% of those who survive early complications develop autoimmune hemolytic anemia, immune thrombocytopenia, vasculitis, arthritis or immune-mediated kidney disease.
- Cancer: about 15% develop lymphoma (average age about 30), often EBV-related and in unusual extranodal sites (brain, lung, gut) (GeneReviews; Merck puts cancer at about 10% of patients older than 10).
- Prognosis: without HSCT or gene therapy, most patients die by age 15 (Merck).
The WAS spectrum
| Phenotype | Variant | Picture |
|---|---|---|
| Classic WAS | Loss of WASP function | Microthrombocytopenia, eczema, immunodeficiency, autoimmunity, lymphoma |
| X-linked thrombocytopenia (XLT) | Loss-of-function variants, milder phenotype | Small platelets and thrombocytopenia; severe bleeding, autoimmunity, serious infection or cancer in a minority |
| X-linked neutropenia (XLN) | Gain-of-function variants in the GTPase-binding domain | Congenital neutropenia with myelodysplasia |
Treatment in 2026
- Allogeneic HSCT is the established cure, with 3-year overall survival above 85% (GeneReviews).
- Gene therapy: etuvetidigene autotemcel (Waskyra, Fondazione Telethon) was FDA-approved on 9 December 2025 as the first cell-based gene therapy for WAS. The patient's own CD34+ stem cells are transduced outside the body with a self-inactivating lentiviral vector carrying a working WAS gene and reinfused after reduced-intensity busulfan and fludarabine conditioning. It is indicated for patients aged 6 months and older with a WAS mutation for whom HSCT is appropriate but no suitable HLA-matched related donor is available. Because the cells are the patient's own, it avoids the graft-versus-host disease risk of donor cells, but the label lists risks including engraftment failure, cytopenias, serious infections and a lifelong risk of insertional oncogenesis. In the 27 patients behind the approval, severe infections fell by 93% and moderate or severe bleeding by 60% (FDA).
- Supportive care: immune globulin replacement (every 3-4 weeks), prophylactic antibiotics, platelet transfusions for hemorrhage, and non-live vaccines only (live vaccines are contraindicated).
- Splenectomy raises the platelet count and can be lifesaving in severe bleeding, but it is usually avoided because it increases the risk of overwhelming infection; patients who have one need lifelong antibiotic prophylaxis.
Differential diagnosis at a glance
| Disorder | Defect | Inheritance | Signature clues | Key lab |
|---|---|---|---|---|
| Wiskott-Aldrich | WAS (WASP, actin cytoskeleton) | XR | Eczema, infections, bleeding | Small platelets; low IgM, high IgA and IgE |
| X-linked agammaglobulinemia | BTK (B-cell maturation) | XR | Encapsulated bacteria from about 6 months; tiny or absent tonsils and nodes | Absent B cells; all Igs low |
| Hyper-IgE (Job) | STAT3 (most) | AD | Staphylococcal abscesses, coarse facies, retained teeth, fractures | IgE above 2,000 IU/mL, eosinophilia |
| DiGeorge | 22q11.2 deletion | Chromosomal microdeletion | Hypocalcemic tetany, conotruncal defects, facies | Low T cells, low calcium |
| CGD | NADPH oxidase | XR (most) or AR | Catalase-positive abscesses, granulomas, Aspergillus | Abnormal DHR test |
| LAD type 1 | CD18 integrin (ITGB2) | AR | Cord detachment after 3 weeks, infections without pus, periodontitis | Leukocytosis |
| SCID | IL-2Rγ (most common), ADA | XR or AR | Thrush, chronic diarrhea, failure to thrive, Pneumocystis by 6 months | Absent T cells; TREC newborn screen; see SCID made easy |
| ITP | Antiplatelet autoantibody | Acquired | Petechiae after a viral illness, otherwise well | Large or normal platelets |
How USMLE tests it
- "Small platelets" is the giveaway. Eczema plus infections without a platelet problem pushes you toward hyper-IgE syndrome; thrombocytopenia with large platelets pushes you toward ITP.
- The immunoglobulin pattern is asked directly: low IgM, high IgA and IgE, normal or low IgG.
- Second-order questions: the defective protein regulates the actin cytoskeleton; the patient is at risk of EBV-associated lymphoma and autoimmune hemolytic anemia; the cure is HSCT, with gene therapy for those without a matched related donor.
- Bleeding is a platelet problem: too few, small, defective platelets, not a clotting-factor defect.
Key takeaways
- WAS = X-linked recessive WAS/WASP defect (actin cytoskeleton), a combined B- and T-cell immunodeficiency.
- Triad (WATER): thrombocytopenia with small platelets, eczema, recurrent infections; bleeding is often the first sign.
- Ig pattern: low IgM, high IgA and IgE, normal or low IgG; poor polysaccharide responses.
- Long-term risks: autoimmunity (AIHA, immune thrombocytopenia, vasculitis, kidney disease) and EBV-related lymphoma.
- Cure: HSCT; etuvetidigene autotemcel (Waskyra) gene therapy, FDA-approved December 2025, when no suitable HLA-matched related donor exists.
- Support: IVIG, antibiotic prophylaxis, platelet transfusion for bleeding, no live vaccines.
Sources
- WAS-Related Disorders — GeneReviews, NCBI Bookshelf (2026)
- Wiskott-Aldrich Syndrome — Merck Manual Professional Edition (2026)
- Wiskott-Aldrich Syndrome — MedlinePlus Genetics, National Library of Medicine
- WASKYRA (etuvetidigene autotemcel) — U.S. Food and Drug Administration (2026)
- WASKYRA Prescribing Information — U.S. Food and Drug Administration (2026)
- FDA Approves First Gene Therapy Treatment for Wiskott-Aldrich Syndrome — U.S. Food and Drug Administration (2025)
- X-Linked Agammaglobulinemia — Merck Manual Professional Edition (2026)
- Hyper-IgE Syndrome — Merck Manual Professional Edition (2024)
- DiGeorge Syndrome — Merck Manual Professional Edition (2026)
- Chronic Granulomatous Disease (CGD) — Merck Manual Professional Edition (2026)
- Severe Combined Immunodeficiency (SCID) — Merck Manual Professional Edition (2026)
- Immune Thrombocytopenia (ITP) — Merck Manual Professional Edition (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
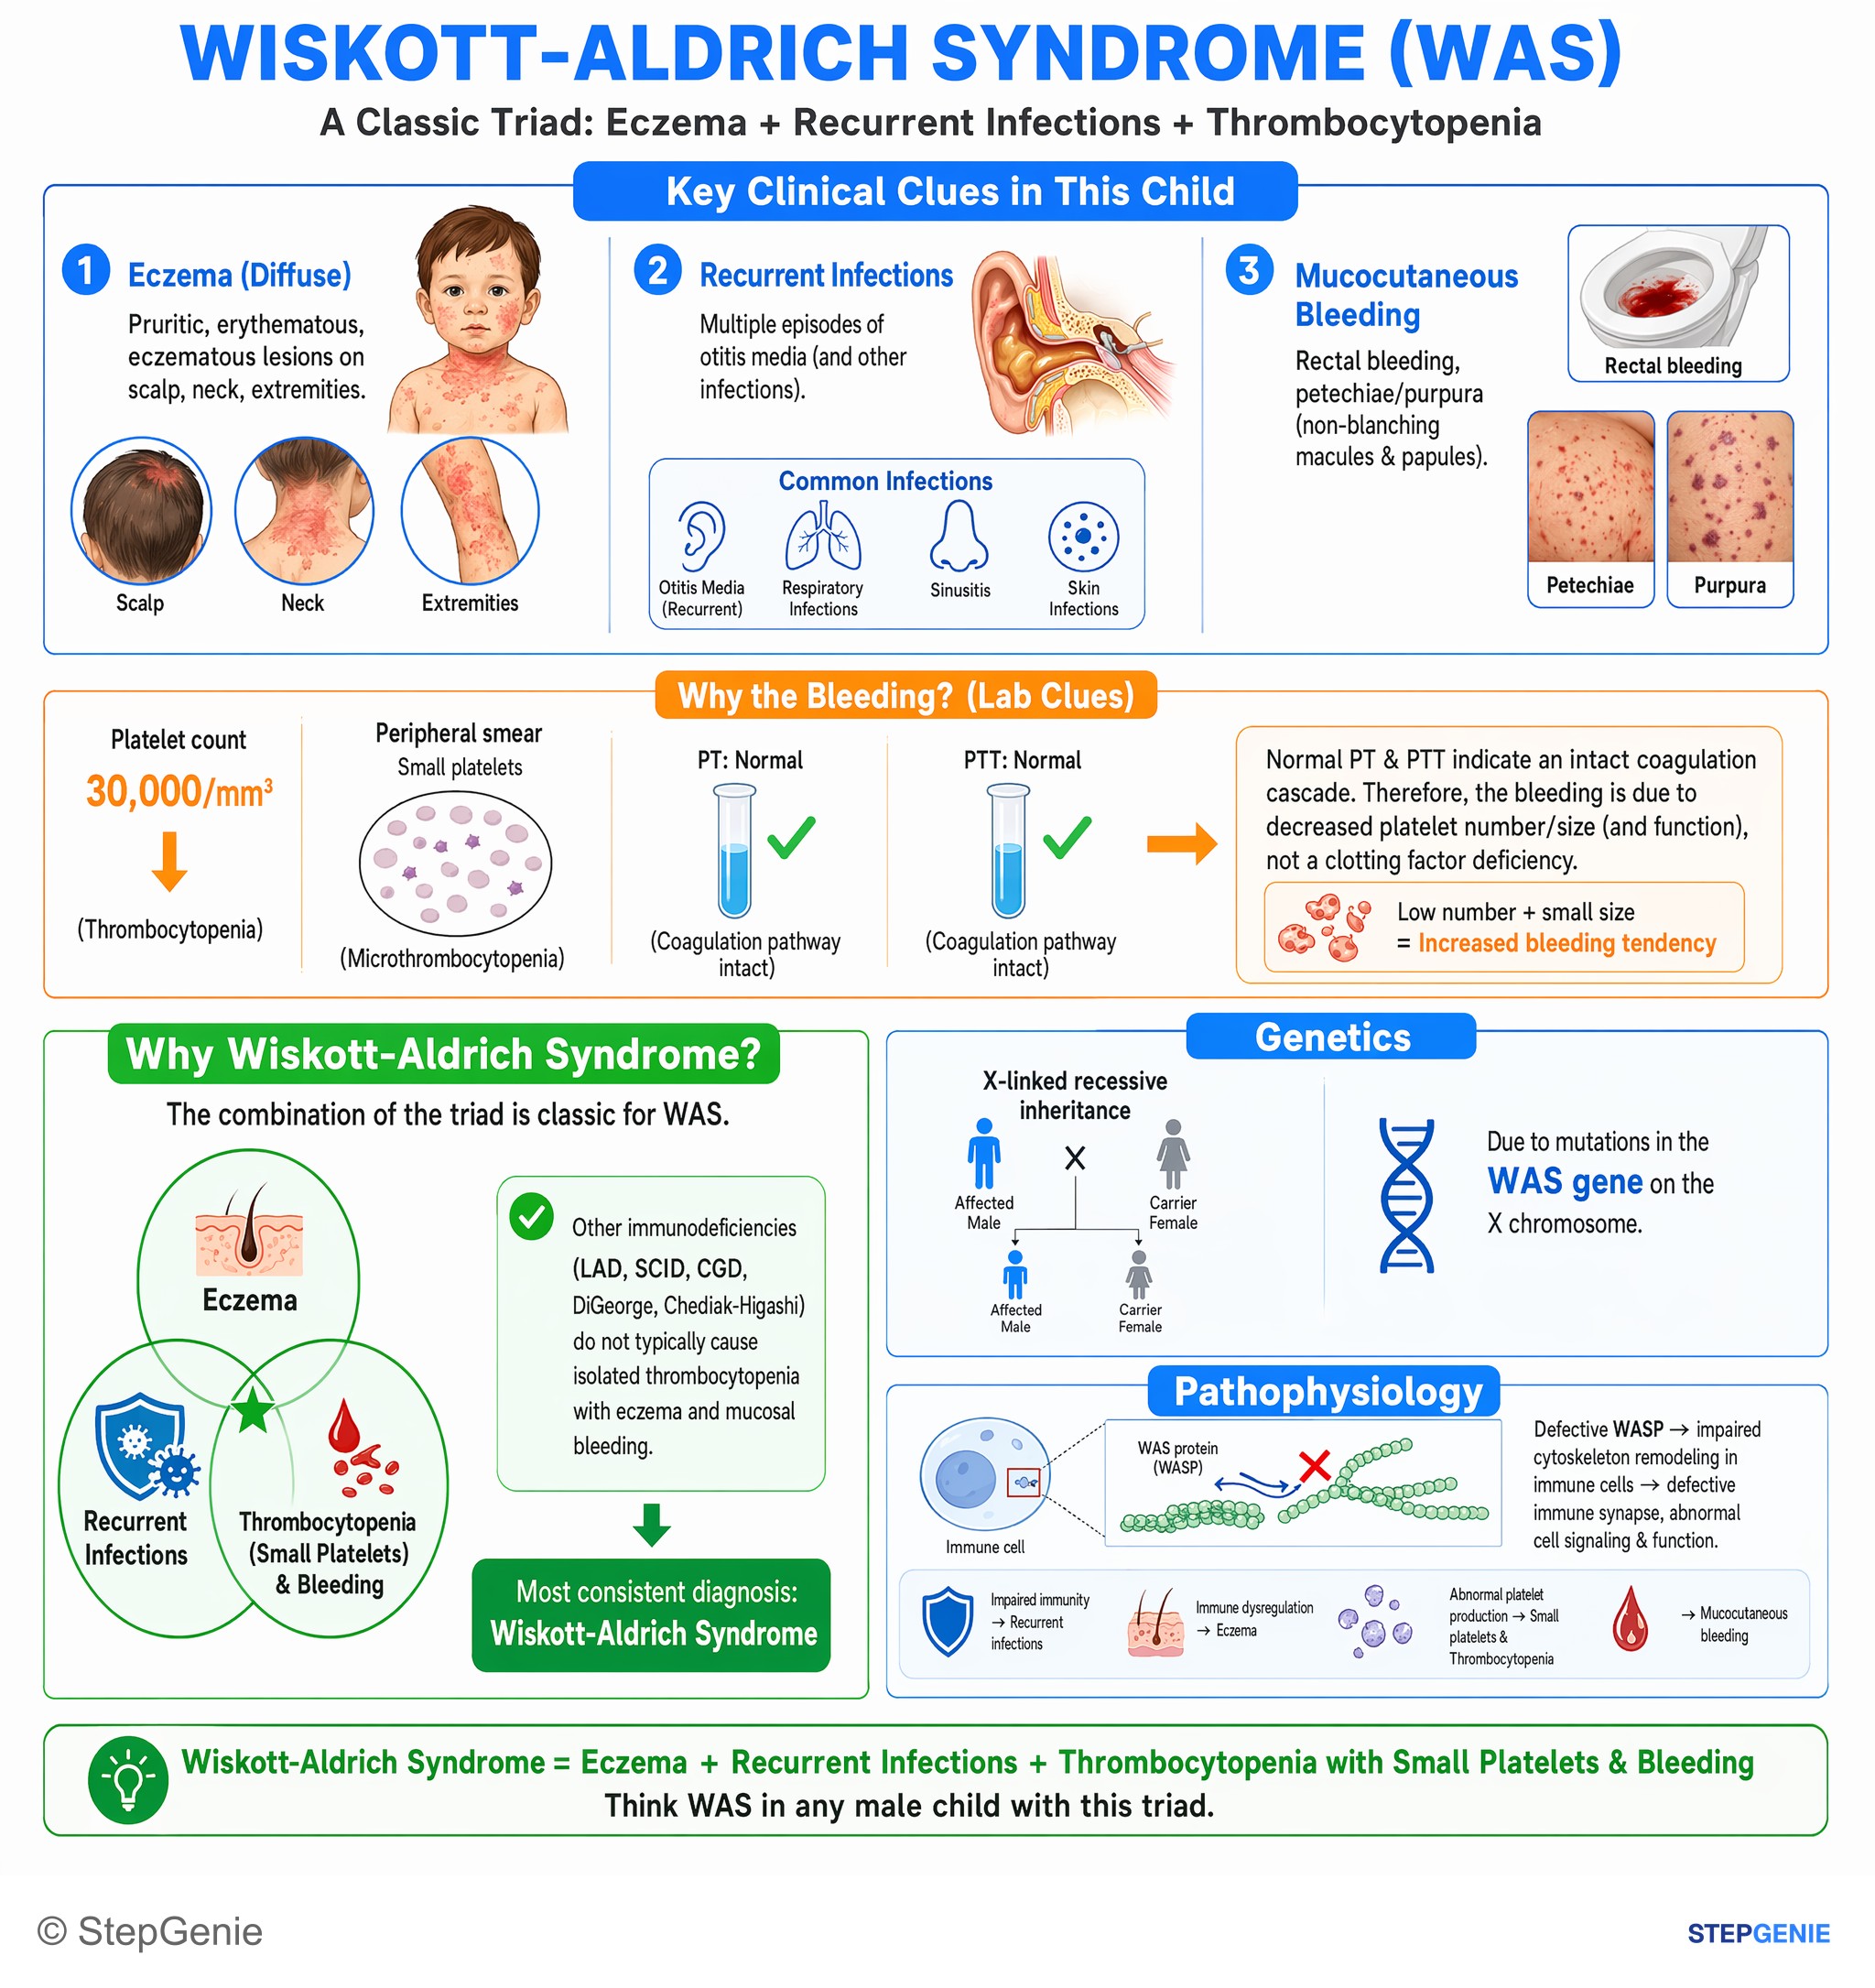
Wiskott-Aldrich syndrome: X-linked defect in WAS gene → impaired cytoskeleton remodeling in immune cells → eczema, recurrent infections…
USMLE Step 1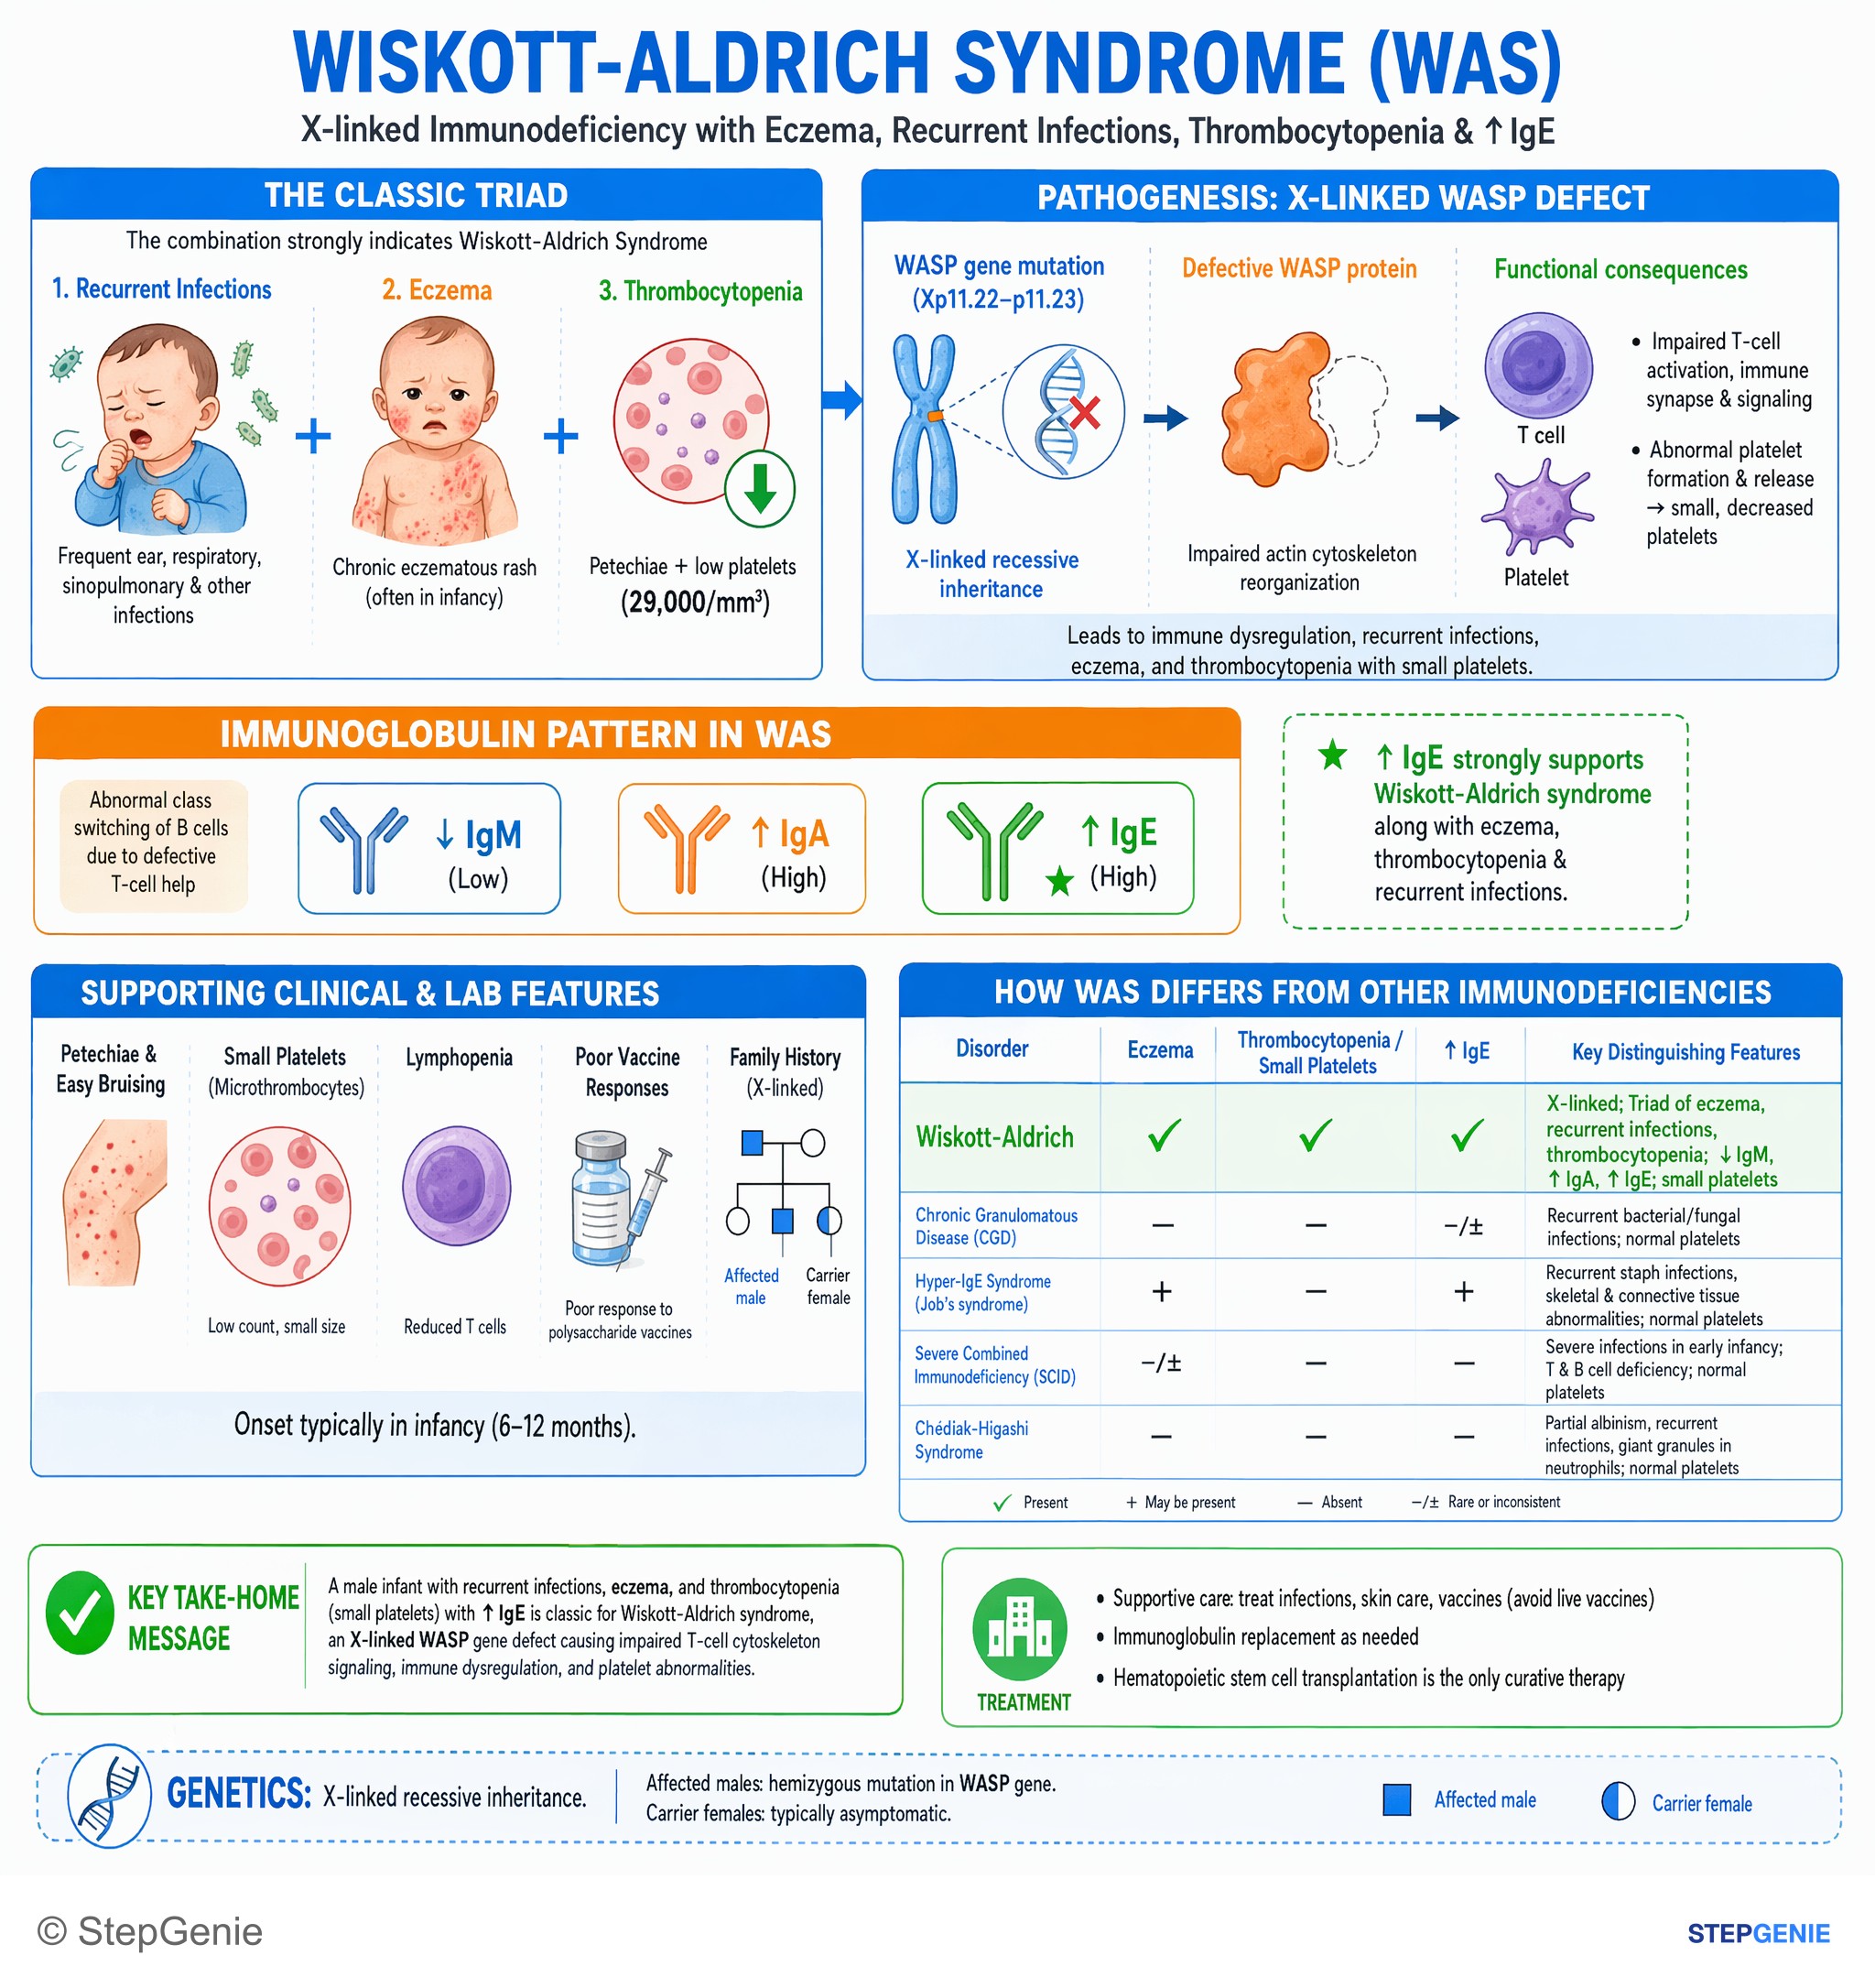
Wiskott-Aldrich syndrome: X-linked defect in WASP → impaired T-cell cytoskeleton signaling → eczema, recurrent infections…
USMLE Step 1Frequently Asked Questions
What is the classic triad of Wiskott-Aldrich syndrome?
The triad is eczema, recurrent infections and thrombocytopenia with abnormally small platelets (microthrombocytopenia). Bleeding is often the first sign, such as petechiae, bloody diarrhea or prolonged bleeding after circumcision, with infections and eczema following. The disorder is X-linked recessive, so it affects boys, and a maternal uncle may have been affected. Small platelets separate it from immune thrombocytopenia, where platelets are normal-sized or large.
What are the immunoglobulin levels in Wiskott-Aldrich syndrome?
The classic pattern is low IgM, high IgA and high IgE, with IgG normal or low. Antibody responses to polysaccharide antigens are poor and isohemagglutinins are absent, which helps explain infections with encapsulated bacteria such as Streptococcus pneumoniae. This mixed pattern differs from X-linked agammaglobulinemia, where IgG, IgA and IgM are all low because B cells are absent.
What gene and protein are defective in Wiskott-Aldrich syndrome?
Mutations in the WAS gene on the X chromosome cause Wiskott-Aldrich syndrome. The gene encodes the Wiskott-Aldrich syndrome protein (WASP), which relays signals from the surface of blood cells to the actin cytoskeleton; immune cells need this to form immune synapses with their targets. Loss of WASP function impairs B-cell and T-cell signaling and leaves platelets small and defective. Gain-of-function variants in the same gene cause X-linked neutropenia instead.
How do you tell Wiskott-Aldrich syndrome from immune thrombocytopenia?
Both cause petechiae and a low platelet count in a child, but Wiskott-Aldrich syndrome has small platelets (volume below about 7 fL), eczema, recurrent infections and an abnormal immunoglobulin pattern in a boy. Immune thrombocytopenia is caused by antiplatelet autoantibodies, shows normal-sized or large platelets with otherwise normal blood counts, often follows a viral infection, and in children usually resolves within weeks to months.
How is Wiskott-Aldrich syndrome treated?
Allogeneic hematopoietic stem cell transplantation is the established cure. In December 2025 the FDA approved etuvetidigene autotemcel (Waskyra), a gene therapy made from the patient's own stem cells corrected with a lentiviral vector, for patients 6 months and older who need a transplant but have no suitable HLA-matched related donor. Supportive care includes immune globulin, prophylactic antibiotics, platelet transfusions for bleeding and no live vaccines. Splenectomy raises platelets but requires lifelong antibiotics.
What are the long-term complications of Wiskott-Aldrich syndrome?
Beyond infections and bleeding, about 25 to 40 percent of patients who survive early complications develop autoimmune disease, such as autoimmune hemolytic anemia, immune thrombocytopenia, vasculitis, arthritis or immune-mediated kidney disease. About 15 percent develop lymphoma, often linked to Epstein-Barr virus and found in unusual sites such as the brain, lung or gut. Without transplantation or gene therapy, most patients die by about age 15.