DiGeorge syndrome is the classic infant presentation of 22q11.2 deletion syndrome, the most common chromosomal microdeletion syndrome: a heterozygous deletion of about 2.5-3 Mb on chromosome 22, including TBX1, disrupts development of the third and fourth pharyngeal pouches and the cardiac neural crest. The result is thymic hypoplasia (T-cell deficiency), parathyroid hypoplasia (hypocalcemia with low PTH) and conotruncal heart defects (tetralogy of Fallot, interrupted aortic arch, truncus arteriosus), plus palatal problems and, later, learning difficulties and schizophrenia in about 1 in 4. More than 90% of deletions are de novo. Chromosomal microarray is the current test of choice (FISH is the classic exam answer), and the rare complete, athymic form is treated with thymus tissue implantation.
The Q-bank vignette
A 3-day-old boy has jitteriness followed by a generalized seizure. He was born at term after an uncomplicated pregnancy. His newborn pulse-oximetry screen was abnormal, and echocardiography shows truncus arteriosus. He has a small jaw, low-set ears and a bifid uvula. Serum calcium is 6.4 mg/dL, phosphate is high, PTH is low and magnesium is normal. The absolute lymphocyte count is low, the chest x-ray shows no thymic shadow, and the state newborn screen reports low T-cell receptor excision circles (TRECs).
Which of the following is the most likely underlying cause?
- A. Mutation in Bruton tyrosine kinase (BTK)
- B. Mutation in the common gamma chain of cytokine receptors (IL2RG)
- C. Microdeletion at chromosome 22q11.2
- D. Microdeletion at chromosome 7q11.23
- E. Trisomy 21
Answer: C, 22q11.2 deletion syndrome (DiGeorge). The key findings map to the pharyngeal pouches and the cardiac outflow tract: low PTH with hypocalcemia and high phosphate (parathyroids), lymphopenia with no thymic shadow and low TRECs (thymus), and truncus arteriosus (cardiac neural crest). Merck notes that hypocalcemic tetany appears within 24-48 hours of birth, and GeneReviews notes that seizures in 22q11.2 deletion syndrome are most often associated with hypocalcemia. The bifid uvula hints at a submucous cleft palate.
Why every other answer choice is wrong
- A, BTK (X-linked agammaglobulinemia): B cells are absent and all immunoglobulin classes are low, but T cells, the thymus and calcium are normal. Infections with encapsulated bacteria (and enteroviral CNS infections) start once maternal antibodies decline, and the tonsils are tiny with no lymph nodes. Review it in the Bruton memory palace.
- B, IL2RG (X-linked SCID): the strongest mimic, because lymphopenia, an absent thymic shadow and low TRECs fit both. But SCID does not cause hypoparathyroidism or conotruncal heart disease. It presents in the first months with candidiasis, persistent viral infections, Pneumocystis pneumonia, diarrhea and failure to thrive, and its definitive treatment is hematopoietic stem cell transplantation (see SCID made easy).
- D, 7q11.23 deletion (Williams syndrome): another microdeletion with a heart lesion, but the lesion is supravalvular aortic stenosis, calcium can be high in infancy, and children have an outgoing, engaging personality. Compare it in the Williams syndrome guide.
- E, trisomy 21: heart disease is common, but the classic lesion is an atrioventricular septal defect, not a conotruncal defect, and trisomy 21 does not explain hypocalcemia with a low PTH. Look for hypotonia, a flat facial profile and duodenal atresia.
Embryology: why one deletion hits thymus, parathyroids and heart
| Structure | Origin | Effect of the deletion | Clinical result |
|---|---|---|---|
| Thymus | 3rd pharyngeal pouch (ventral wing) | Hypoplastic; rarely absent | Low T cells, small or absent thymic shadow, low TRECs |
| Inferior parathyroids | 3rd pouch (dorsal wing) | Hypoplastic | Low PTH: hypocalcemia, high phosphate, tetany, seizures |
| Superior parathyroids | 4th pouch (dorsal wing) | Hypoplastic | Adds to the hypoparathyroidism |
| Outflow tract and aortic arches | Cardiac neural crest | Abnormal migration and differentiation | Conotruncal defects, aortic arch anomalies |
- The inferior parathyroids start in the higher (third) pouch but end up lower because they descend with the thymus. The fourth pouch's other derivative, the ultimobranchial body (parafollicular C cells), is rarely the point of a DiGeorge question.
- TBX1 lies in the deleted region. Its haploinsufficiency tracks with the severity of cardiac, thymic and parathyroid defects, and TBX1 variants alone can mimic the syndrome.
CATCH-22: a useful mnemonic with caveats
| Letter | Feature | What the data show (GeneReviews unless noted) |
|---|---|---|
| C | Cardiac (conotruncal) | Congenital heart disease in 64%: VSD 23%, tetralogy of Fallot 18%, aortic arch anomalies 14% (right arch, double arch, vascular ring, aberrant right subclavian), interrupted aortic arch 11%, truncus arteriosus 4% |
| A | Abnormal facies | Often subtle (long face, bulbous nasal tip, small jaw, low-set ears, short philtrum) and may be absent, particularly in some ethnic groups (StatPearls) |
| T | Thymic hypoplasia | Immune deficiency in 77%, mostly partial; complete athymia in less than 1% (StatPearls) |
| C | Cleft palate | Palatal anomalies in 67%, but an overt cleft in only about 4%; velopharyngeal insufficiency (about 55%) and submucous cleft (about 23%) are more typical, causing hypernasal speech and feeding problems |
| H | Hypocalcemia | 17-60%; worst in newborns; can recur during illness, puberty and pregnancy |
| 22 | 22q11.2 deletion | Over 90% de novo, about 10% inherited |
The caveats:
- It leaves out what dominates later life: developmental delay or learning difficulties (70-90%, often a nonverbal learning disability), autism spectrum disorder (about 20%), schizophrenia (about 25%), renal anomalies (16% in GeneReviews; StatPearls cites 30-35%) and autoimmune disease (juvenile rheumatoid arthritis at about 20 times the general-population rate).
- No feature is constant. Expression is highly variable, even within families, so a parent who carries the deletion may have only subtle signs.
- The acronym has critics. A 1999 Journal of Medical Genetics editorial by John Burn, titled "Closing time for CATCH22", acknowledged criticism that the term carries a negative connotation (in Joseph Heller's novel, a catch-22 is a no-win situation). The preferred umbrella term, "22q11.2 deletion syndrome", covers what were called DiGeorge, velocardiofacial and conotruncal anomaly face syndromes.
Hypocalcemia: labs, timing, treatment
- Labs: low calcium, high phosphate and low (or inappropriately normal) PTH. Check magnesium, since hypomagnesemia also causes hypocalcemia.
- Timing: most serious in the newborn period; it often settles with age but can return during illness, puberty and pregnancy. GeneReviews advises checking calcium every 3-6 months in infancy, every 5 years through childhood, then every 1-2 years, plus before and after surgery and regularly in pregnancy.
- Treatment: calcium supplements plus active vitamin D (calcitriol), with recombinant PTH for refractory cases (StatPearls); watch urinary calcium. The physiology is reviewed in the hypoparathyroidism guide.
T-cell deficiency: partial vs complete DiGeorge
| Partial (most patients) | Complete (less than 1%) | |
|---|---|---|
| Thymus | Hypoplastic; some tissue present | Absent (congenital athymia) |
| T cells | Low to normal; often improve with age | Profound T-cell lymphopenia (fewer than 50 naive T cells/µL); TRECs very low or absent |
| Picture | Recurrent sinopulmonary infections; IgA deficiency in 13%; autoimmunity | SCID-like opportunistic infections; usually fatal by age 2-3 without treatment |
| Live vaccines | Withheld while lymphocytes are abnormal; StatPearls allows them after 12 months if CD4 is above 500/µL, CD8 above 300/µL and inactivated-vaccine responses are documented | Contraindicated |
| Blood products | Irradiated until the immune system normalizes | Irradiated, leukocyte-reduced, CMV-negative |
| Definitive therapy | Usually none | Thymus tissue implantation or hematopoietic stem cell transplantation |
Thymus implantation: allogeneic processed thymus tissue (RETHYMIC) was FDA-approved in October 2021 for immune reconstitution in children with congenital athymia. Slices are implanted into the quadriceps; protective immunity is unlikely before 6-12 months, and survival in the studies behind approval was 77% at 1 year. It is not for SCID: in SCID the lymphocytes themselves are defective, so the fix is new stem cells, whereas athymic infants have T-cell precursors with no thymus to mature in.
Conotruncal heart defects and psychiatric risk
- Heart: abnormal cardiac neural crest migration explains the outflow-tract lesions. The classic exam trio is tetralogy of Fallot, truncus arteriosus and interrupted aortic arch. Type B (interruption between the left carotid and left subclavian arteries) is the most common form of interrupted aortic arch, and almost half of all patients with an interrupted arch have a 22q11.2 deletion (StatPearls). Congenital heart disease, especially conotruncal, is a reason to test for the deletion. See the tetralogy of Fallot guide.
- Mind: ADHD, anxiety and autism features in childhood; psychotic disorders from adolescence, with schizophrenia in about 25% (StatPearls: 25-30% of adults). Haploinsufficiency of COMT, which breaks down dopamine, is one proposed contributor; StatPearls suggests structured screening for prodromal psychosis from about age 12-14. Symptom patterns are in the schizophrenia breakdown.
Diagnosis and inheritance
- Chromosomal microarray is the current gold standard. About 85% of patients have the typical 2.54-Mb deletion between low-copy repeats LCR22A and LCR22D; microarray also finds smaller atypical deletions. Standard FISH probes sit between LCR22A and LCR22B, so FISH misses deletions outside that segment, yet "FISH for a 22q11.2 deletion" remains the classic board answer.
- Newborn screening: TREC-based screening for SCID also picks up infants with 22q11.2 deletion and low T cells.
- Baseline workup: calcium, phosphate, magnesium, PTH; lymphocyte subsets and immunoglobulins; echocardiography; renal ultrasound; hearing, palate and developmental assessment.
- How common: it is the most common microdeletion syndrome. Estimates range from about 1 in 2,000-4,000 live births (StatPearls; one newborn-screening study found 1 in 2,148) to about 1 in 6,000 in a US population-based study (1 in 3,800 in Hispanic populations; GeneReviews).
- Inheritance: autosomal dominant. Over 90% of deletions are de novo; test both parents, and counsel that each child of an affected person has a 50% chance of inheriting the deletion.
Look-alikes and naming traps
| Condition | Overlap | How to tell |
|---|---|---|
| SCID | No thymic shadow, low TRECs, lymphopenia | Normal calcium and PTH, no conotruncal defect; HSCT |
| CHARGE syndrome (CHD7) | Can produce a DiGeorge phenotype | Coloboma, choanal atresia, ear anomalies; no 22q11.2 deletion |
| Phenocopies: maternal diabetes, fetal alcohol exposure, retinoic acid embryopathy, 10p13 deletion | Similar thymic, parathyroid and heart defects | Exposure history or a different genetic finding; 22q11.2 testing is normal |
| Velocardiofacial (Shprintzen) syndrome | Palate, heart and facial findings | Not a separate disease: an older name for the same 22q11.2 deletion |
| Isolated hypoparathyroidism | Hypocalcemia with low PTH | Normal thymus, T cells and heart |
Naming note: GeneReviews now reserves the term "DiGeorge syndrome" for people who have the clinical features but no identifiable 22q11.2 deletion. USMLE-style questions still treat DiGeorge syndrome as the 22q11.2 deletion.
Key takeaways
- 22q11.2 deletion (TBX1) disrupts the 3rd/4th pharyngeal pouches and cardiac neural crest: thymic hypoplasia (low T cells), parathyroid hypoplasia (low calcium, low PTH, high phosphate) and conotruncal defects.
- Classic trio: tetralogy of Fallot, truncus arteriosus, interrupted aortic arch (usually type B); overall congenital heart disease in 64%.
- CATCH-22 is a mnemonic, not a checklist: overt cleft palate in only about 4%, hypocalcemia in 17-60%, subtle facies; learning difficulties (70-90%) and schizophrenia (about 25%) are missing from it.
- Most patients have partial DiGeorge; complete athymia (less than 1%) is SCID-like and needs thymus tissue implantation or HSCT.
- No live vaccines while lymphocytes are abnormal; irradiated blood products.
- Absent thymus + hypocalcemia + conotruncal defect = DiGeorge; absent thymus with normal calcium = think SCID.
- Diagnose with chromosomal microarray (FISH misses atypical deletions); over 90% de novo, 50% risk to offspring.
Sources
- 22q11.2 Deletion Syndrome — GeneReviews, NCBI Bookshelf (2025)
- DiGeorge Syndrome — StatPearls, NCBI Bookshelf (2025)
- 22q11.2 Deletion Syndrome — MedlinePlus Genetics (2019)
- DiGeorge Syndrome — Merck Manual Professional Edition (2024)
- Embryology, Parathyroid — StatPearls, NCBI Bookshelf (2023)
- RETHYMIC (allogeneic processed thymus tissue–agdc) — US Food and Drug Administration (2021)
- RETHYMIC Prescribing Information — US Food and Drug Administration (2021)
- Severe Combined Immunodeficiency (SCID) — Merck Manual Professional Edition (2024)
- X-linked Agammaglobulinemia — Merck Manual Professional Edition (2024)
- Williams Syndrome — MedlinePlus Genetics (2022)
- Closing Time for CATCH22 — Journal of Medical Genetics (1999)
- Interrupted Aortic Arch — StatPearls, NCBI Bookshelf (2023)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
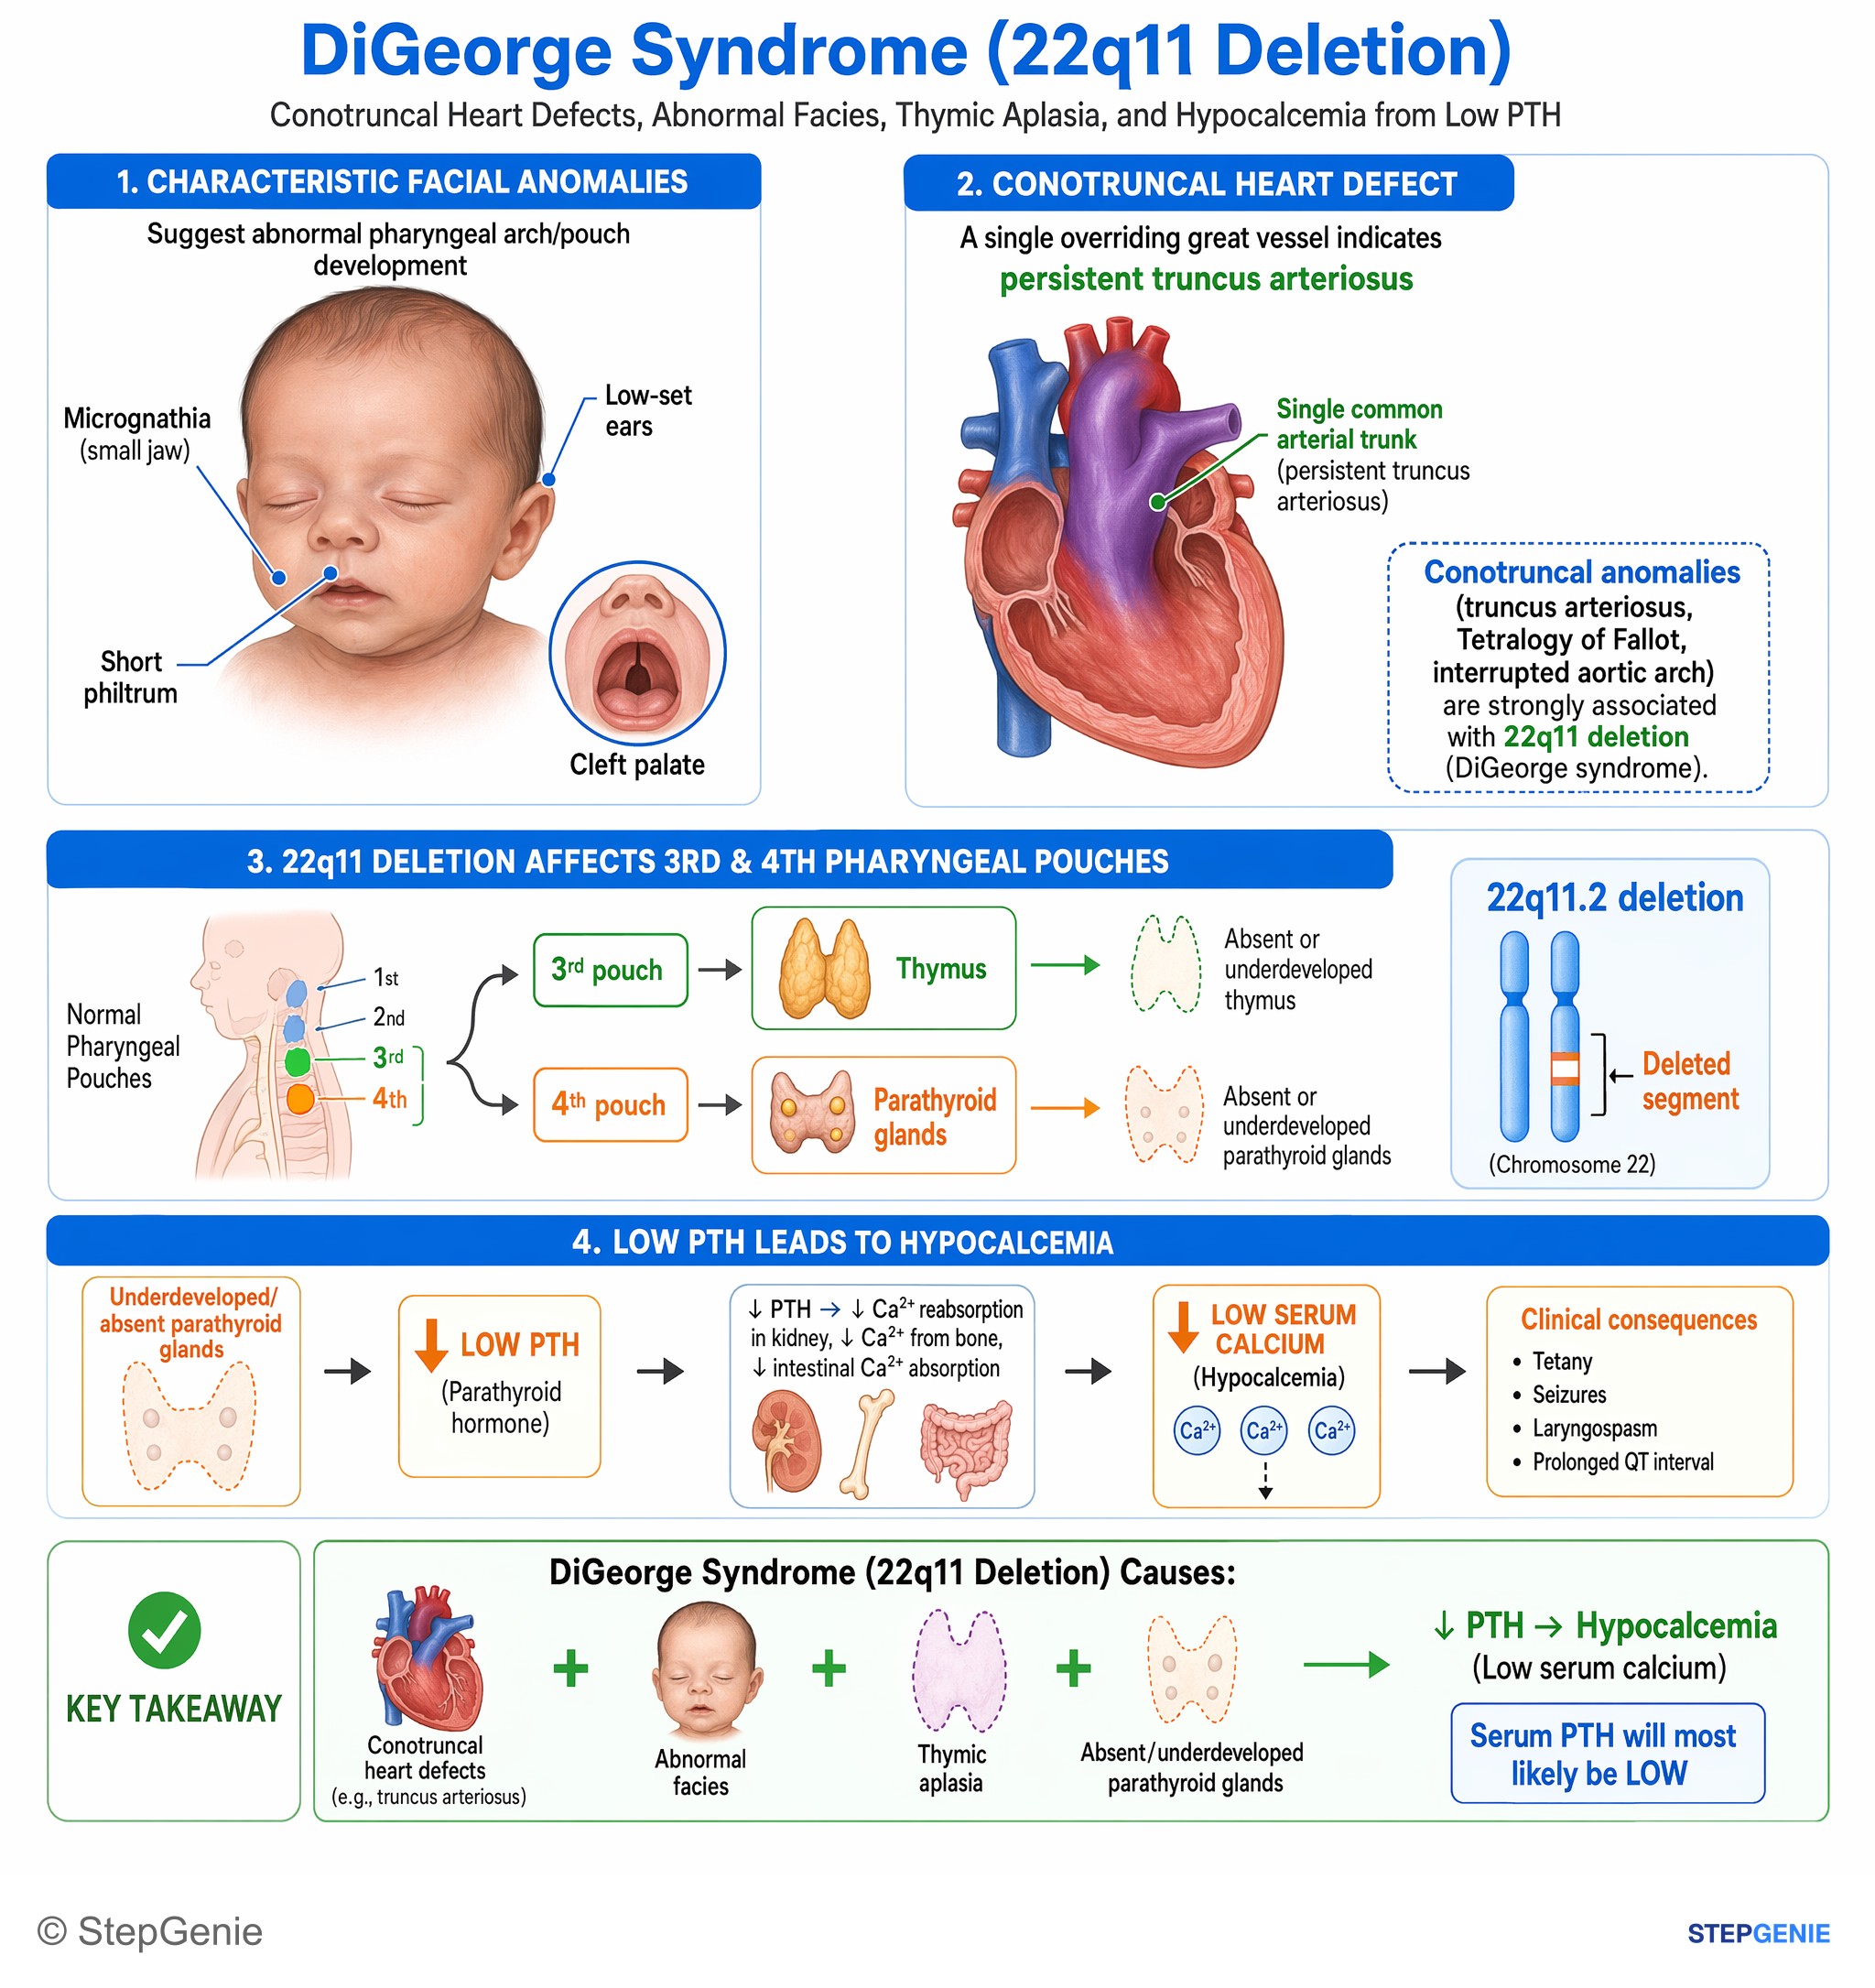
DiGeorge syndrome (22q11 deletion) causes conotruncal heart defects, abnormal facies, thymic aplasia, and hypocalcemia from low PTH.
USMLE Step 1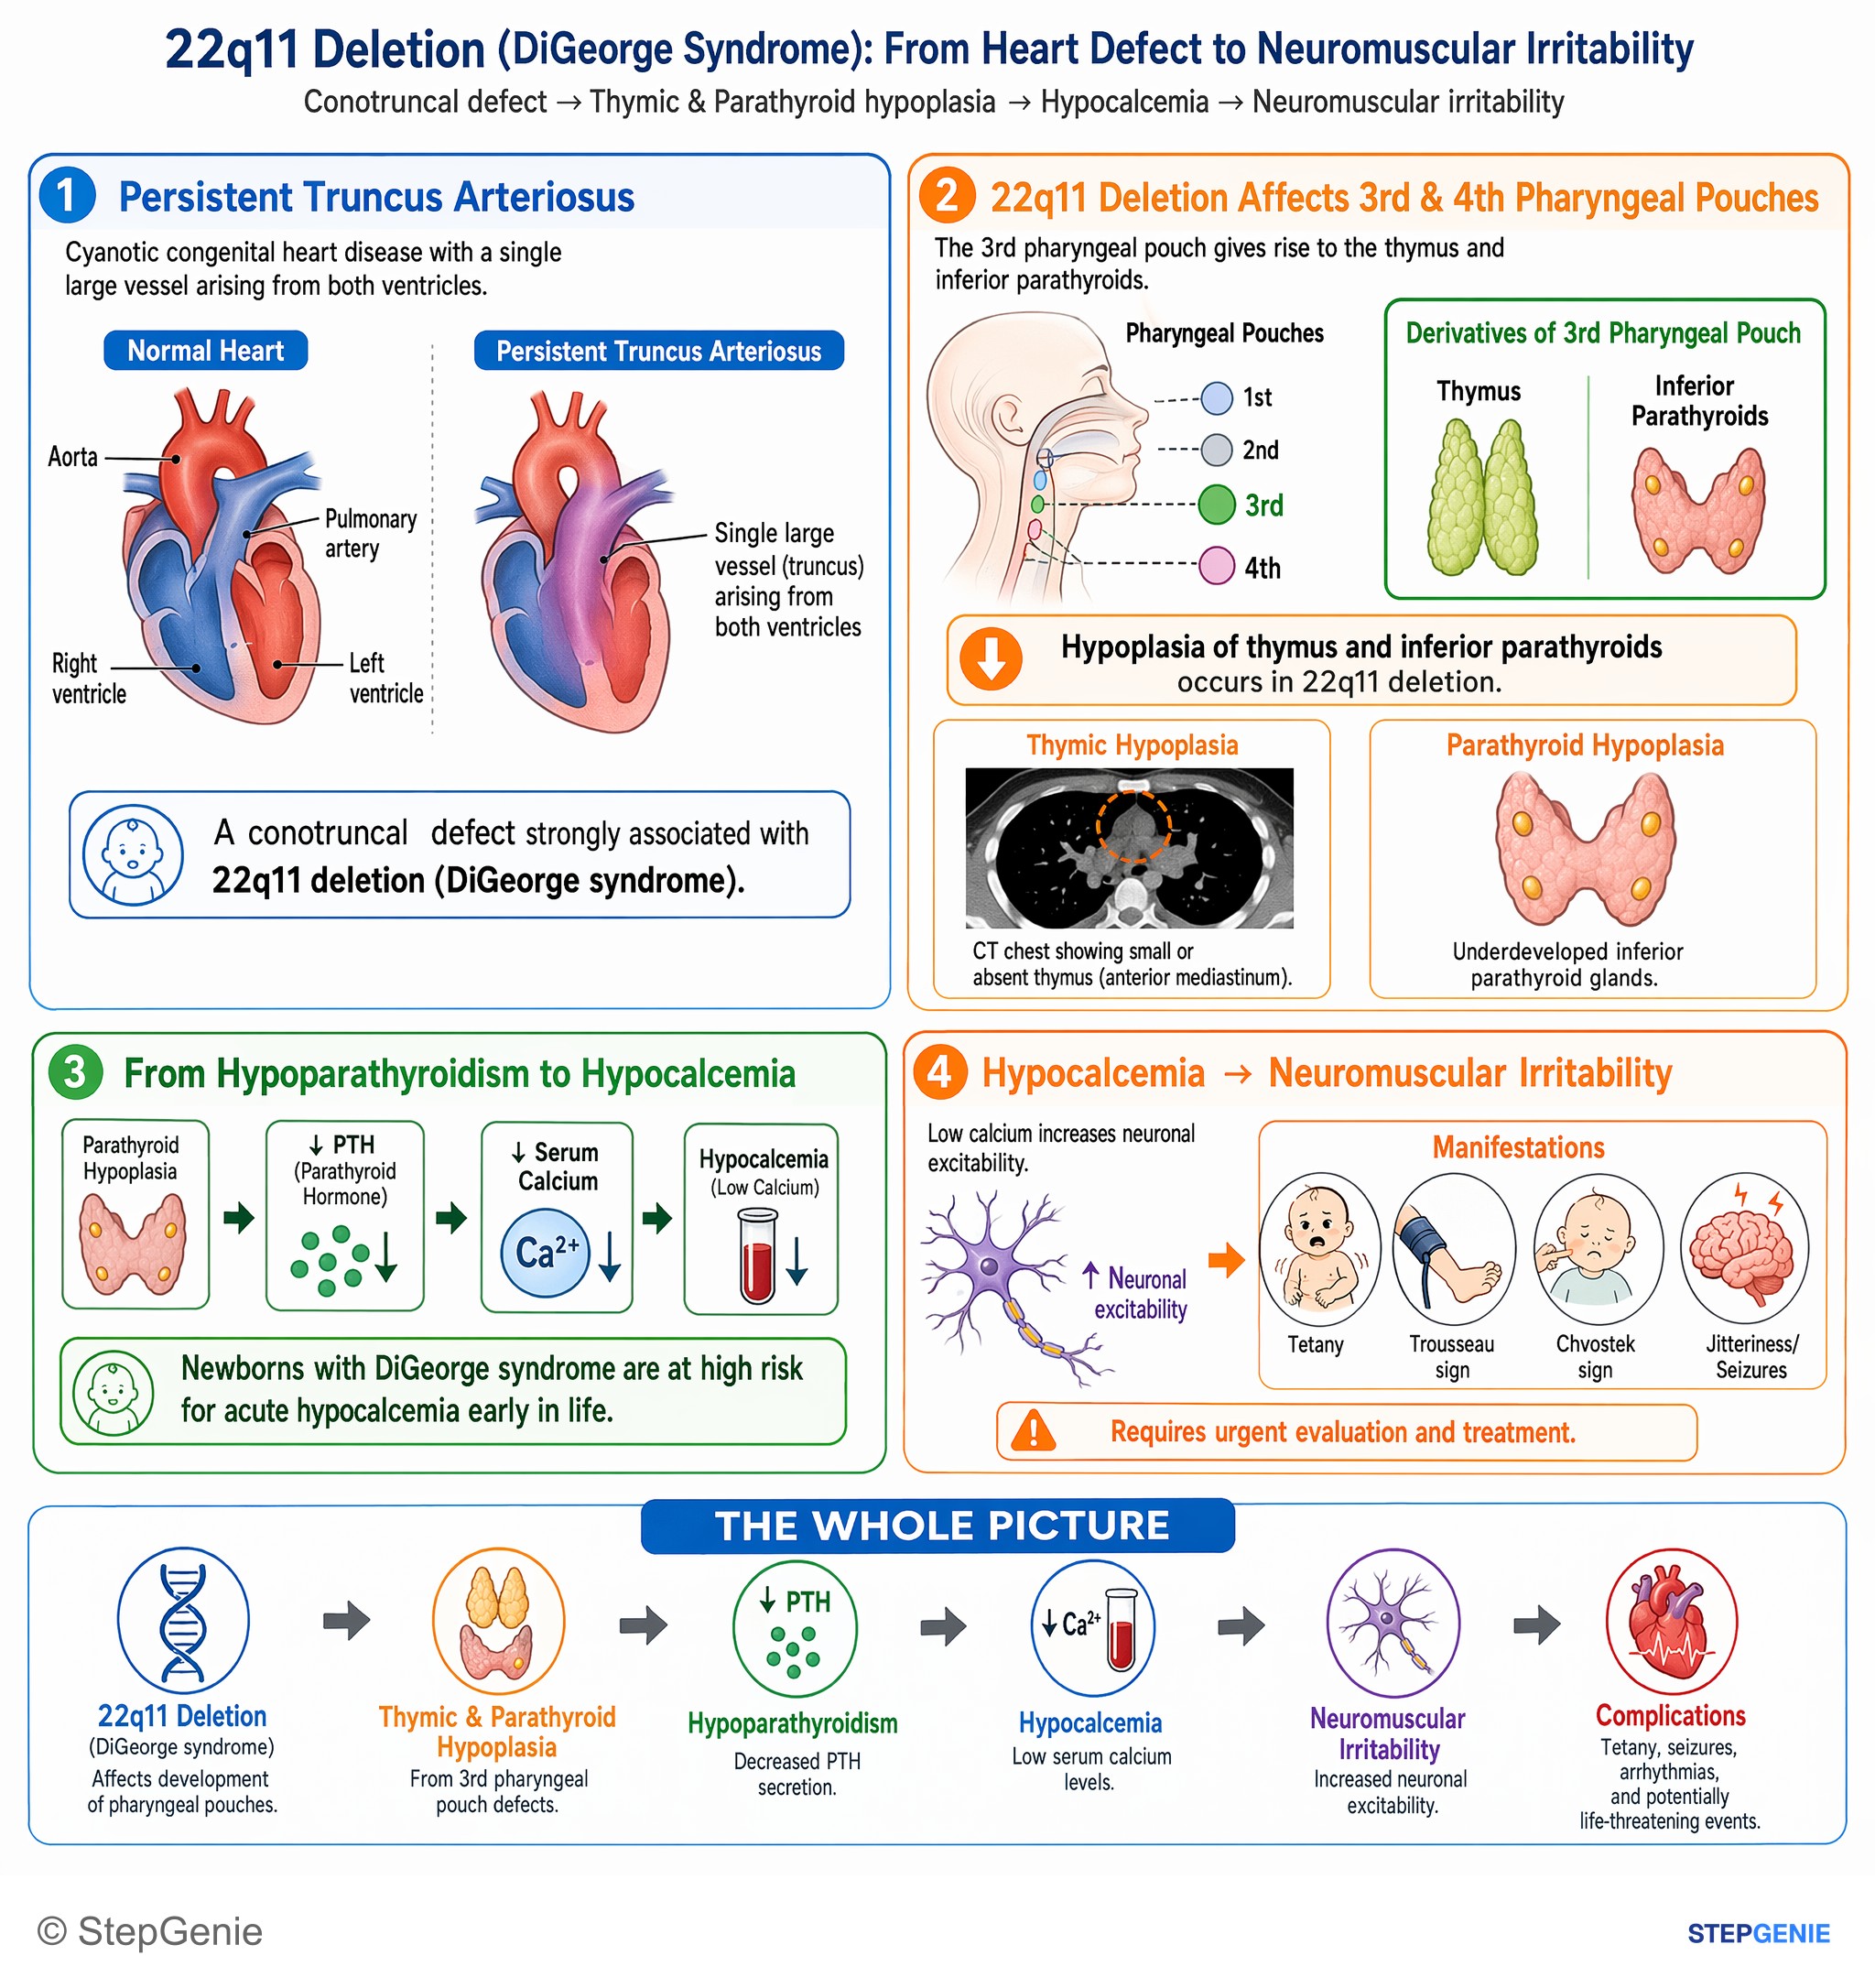
DiGeorge syndrome (22q11 deletion) → thymic & parathyroid hypoplasia → hypocalcemia → neuromuscular irritability, tetany, seizures…
USMLE Step 1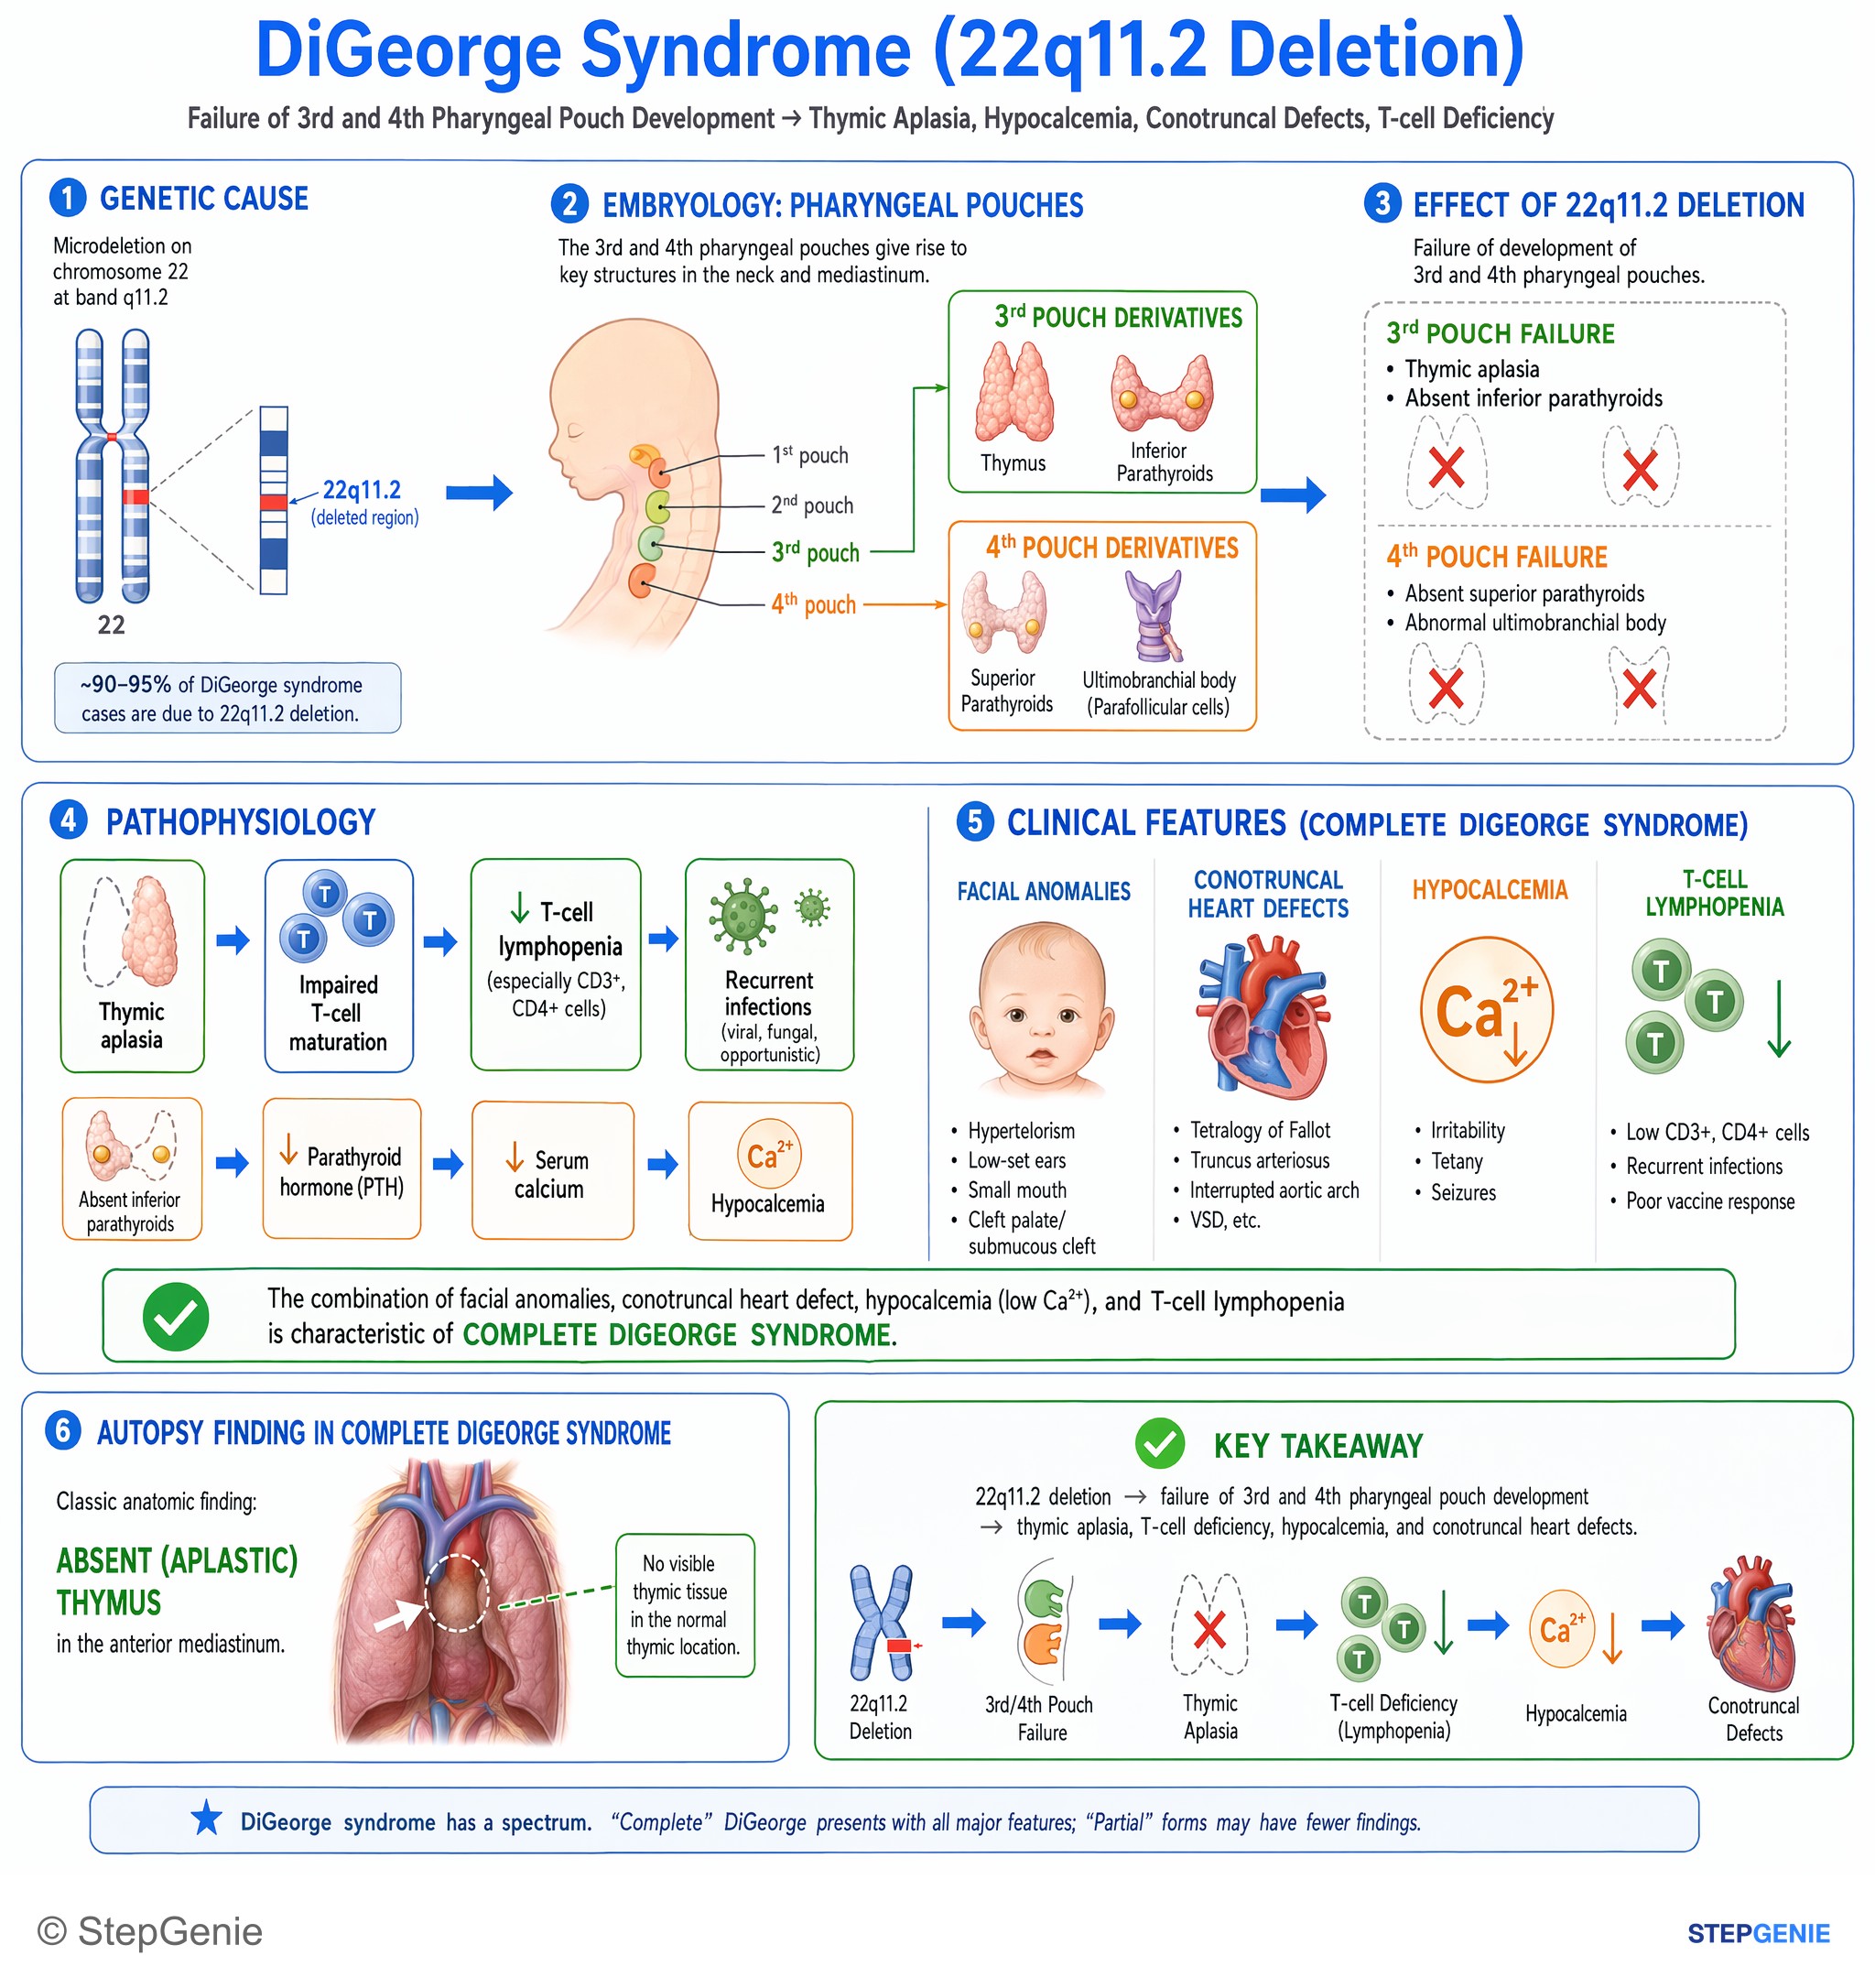
DiGeorge syndrome (22q11 deletion) causes failure of 3rd/4th pharyngeal pouch development → thymic aplasia, T-cell deficiency…
USMLE Step 1Frequently Asked Questions
Is DiGeorge syndrome the same as 22q11.2 deletion syndrome?
Mostly, yes. About 90% of people with the DiGeorge phenotype have a 22q11.2 microdeletion, and 22q11.2 deletion syndrome is now the umbrella name for what were called DiGeorge syndrome, velocardiofacial (Shprintzen) syndrome and conotruncal anomaly face syndrome. GeneReviews now reserves the term DiGeorge syndrome for people with the clinical picture but no identifiable deletion; causes include TBX1 or CHD7 (CHARGE) variants, 10p13 deletions and exposures such as maternal diabetes or retinoic acid. On exams, DiGeorge means the 22q11.2 deletion.
What does CATCH-22 stand for in DiGeorge syndrome?
CATCH-22 stands for Cardiac anomalies (conotruncal defects), Abnormal facies, Thymic hypoplasia, Cleft palate and Hypocalcemia, caused by a deletion on chromosome 22. It is a memory aid, not a checklist: overt cleft palate occurs in only about 4% (velopharyngeal insufficiency is more common), hypocalcemia in 17 to 60%, and learning difficulties and schizophrenia are left out. A 1999 editorial titled Closing time for CATCH22 noted criticism that the term carries a negative connotation.
Which pharyngeal pouches are affected in DiGeorge syndrome?
The third and fourth pharyngeal pouches. The third pouch forms the thymus and the inferior parathyroid glands, and the fourth pouch forms the superior parathyroid glands, so poor development causes T-cell deficiency and hypoparathyroidism. The heart defects come from abnormal migration of cardiac neural crest cells into the outflow tract, which explains tetralogy of Fallot, truncus arteriosus and interrupted aortic arch.
Why does DiGeorge syndrome cause hypocalcemia?
Hypoplastic parathyroid glands make too little parathyroid hormone, so serum calcium falls and phosphate rises. Hypocalcemic tetany typically appears within 24 to 48 hours of birth, and seizures in these infants are most often associated with hypocalcemia. It affects 17 to 60% of people with the deletion and is worst in the newborn period; it often improves with age but can return during illness, puberty and pregnancy, so calcium is checked for life, including around surgery. Treatment is calcium plus calcitriol.
What is the difference between partial and complete DiGeorge syndrome?
Partial DiGeorge, which covers most patients, has some thymic tissue, so T-cell numbers are low to normal and often improve with age; infections are usually mild. Complete DiGeorge, in fewer than 1%, means congenital athymia with almost no naive T cells and very low or absent TRECs, giving a SCID-like illness that is fatal without treatment. Complete DiGeorge is treated with thymus tissue implantation, FDA-approved in 2021, or hematopoietic stem cell transplantation, and live vaccines are contraindicated.
How is DiGeorge syndrome diagnosed?
Chromosomal microarray is the current gold standard because it detects the typical 22q11.2 deletion and smaller atypical deletions. FISH for the 22q11.2 deletion is the classic board answer but misses deletions outside the region its probes cover. Supporting tests include calcium, phosphate, magnesium and PTH, lymphocyte subsets, immunoglobulins, echocardiography and renal ultrasound. TREC-based newborn screening for SCID also flags some infants with the deletion and low T cells.