Complement deficiencies sort by where the cascade breaks. Early classical components (C1q, C1r/s, C2, C4) cause lupus-like immune-complex disease plus infections with encapsulated bacteria; C3 deficiency causes the most severe recurrent pyogenic infections; and terminal components (C5–C9), properdin and factor D leave patients open to recurrent Neisseria. Regulator defects cause the opposite problem, too much complement: C1-esterase inhibitor deficiency (hereditary angioedema), DAF/CD59 loss (PNH) and factor H or I defects (atypical HUS).
Complement deficiencies comparison table
| Deficiency | What the component does | Classic presentation | CH50 / AH50 | Exam hook |
|---|---|---|---|---|
| C1q, C1r/C1s, C4, C2 (early classical) | Start the classical pathway; help clear immune complexes and apoptotic debris | SLE-like disease; recurrent sinopulmonary infections (S. pneumoniae, H. influenzae type b) | Low / normal | "Lupus + recurrent infections." C1q carries the highest SLE risk; C2 is the most common classical-pathway defect and often silent |
| C3 | Main opsonin (C3b); all three pathways converge on it | Severe recurrent pyogenic infections from infancy; immune-complex glomerulonephritis | Low / low | "The worst one for infections" |
| C5–C9 (terminal) | Membrane attack complex (C5b-9) | Recurrent N. meningitidis meningitis or bacteremia; disseminated gonococcal infection | Low / low | "Second episode of meningococcal disease" |
| Properdin | Stabilizes the alternative-pathway C3 convertase | Severe, often fulminant meningococcal disease; X-linked, so affects boys | Normal / low | "Maternal uncle died of meningococcemia" |
| Factor D, factor B | Build the alternative-pathway C3 convertase | Neisseria and pyogenic infections (very rare) | Normal / low | "Isolated low AH50" |
| MBL (lectin pathway) | Binds mannose on microbes | Most common deficiency (about 5% of White people); usually silent; infections in infants | Normal / normal | "Screening tests normal; order an MBL level" |
| C1-esterase inhibitor | Inhibits C1r/C1s and kallikrein | Hereditary angioedema: non-itchy swelling of face, larynx and gut; no urticaria | Low C4; C3 and C1q normal | "ACE inhibitors contraindicated" |
| DAF (CD55) + CD59 | GPI-anchored shields that protect host cells from convertases and the MAC | PNH: Coombs-negative intravascular hemolysis, pancytopenia, venous thrombosis | Flow cytometry for CD55/CD59 | "Acquired PIGA mutation" |
| Factor H, factor I | Inactivate C3b | Atypical HUS, C3 glomerulopathy; secondary C3 depletion → infections | C3 often low (consumed) | "HUS without diarrhea" |
How to read CH50 and AH50
CH50 needs every classical-pathway and terminal component (C1–C9) to lyse its target cells. AH50 needs the alternative-pathway factors plus C3 and C5–C9. Together they localize the block:
| CH50 | AH50 | The block is in… |
|---|---|---|
| Low | Normal | Early classical: C1, C2 or C4 |
| Normal | Low | Early alternative: factor B, factor D or properdin |
| Low | Low | Shared components: C3 or C5–C9 |
| Normal | Normal | Lectin pathway (check MBL) or no inherited deficiency |
For suspected hereditary angioedema, don't start with CH50: order C4, which stays low even between attacks.
Why each defect causes its disease
- Early classical → lupus. C1q, C4 and C3b clear immune complexes and apoptotic debris. When clearance fails, nuclear antigens linger and drive autoantibody formation. Opsonization is weaker too, which explains the encapsulated organisms.
- C3 → the most severe infections. Without C3b there is little opsonization and no C5 convertase, so every pathway stalls.
- C5–C9 → Neisseria. Opsonization and C5a-driven neutrophil recruitment still work, so most bacteria are handled. Defense against Neisseria depends unusually heavily on MAC-mediated killing.
- C1-INH → angioedema. Unchecked kallikrein generates bradykinin, which causes vascular leak, and unchecked C1s consumes C4.
- DAF/CD59 → hemolysis. Red cells lose their complement shield and lyse inside vessels. Thrombosis (for example, Budd-Chiari syndrome) is the leading cause of death in PNH.
Classic vignette clues
- A teen or young adult with a second episode of meningococcal meningitis, or meningococcal disease plus a family history → check CH50 and AH50 → C5–C9 (both low) or properdin (AH50 alone low).
- A young woman with malar rash, arthritis and recurrent sinusitis or pneumonia, plus a low CH50 → early classical defect (C2, C4 or C1q).
- An infant with repeated pneumonia, otitis and bacteremia, plus hematuria → C3.
- Recurrent swelling of lips, tongue or larynx, or colicky abdominal attacks that mimic bowel obstruction, triggered by dental work or estrogen, with no hives → C1-INH deficiency.
- Dark morning urine, pancytopenia and hepatic vein thrombosis → PNH (CD55/CD59).
Traps and look-alikes
- Low complement isn't always an inherited deficiency. Consumption also lowers levels in SLE flares (C3 and C4), post-streptococcal glomerulonephritis (C3), serum sickness (C3 and C4), mixed cryoglobulinemia (C4) and C3-nephritic-factor MPGN (C3). Ask whether an active immune-complex disease explains the numbers.
- Hereditary angioedema is bradykinin, not histamine. There's no urticaria or itching, and epinephrine, antihistamines and steroids usually don't work. Acute attacks are treated with C1-INH concentrate, icatibant (bradykinin B2-receptor antagonist) or ecallantide (kallikrein inhibitor).
- Hereditary vs acquired C1-INH deficiency. Both have low C4; a low C1q points to the acquired form, seen with B-cell lymphoma or monoclonal gammopathy.
- ACE-inhibitor angioedema is also bradykinin-mediated, but C4 and C1-INH are normal.
- Drug-induced terminal deficiency. Eculizumab and ravulizumab block C5 (used for PNH, atypical HUS and myasthenia gravis). The CDC reports a 1,000- to 2,000-fold higher incidence of meningococcal disease with eculizumab; patients need MenACWY and MenB vaccines, and vaccination doesn't prevent every case.
- Asplenia vs complement deficiency. Both predispose to encapsulated organisms; Howell-Jolly bodies on the smear point to asplenia.
- Vaccines. Every complement-deficient patient should get pneumococcal and meningococcal vaccines; live vaccines are not contraindicated.
Worked example
Vignette: A 12-year-old boy develops purpura fulminans with Neisseria meningitidis bacteremia. His maternal uncle died of meningococcal sepsis at age 15. After recovery, CH50 is normal and AH50 is markedly low. Which protein is most likely deficient?
Answer: Properdin.
Reasoning: An isolated low AH50 localizes the defect to the alternative pathway, and disease passed through the maternal line to males fits X-linked inheritance, which among complement proteins is characteristic of properdin.
Key takeaways
- C1q, C1r/s, C2, C4: lupus-like disease plus encapsulated infections; low CH50, normal AH50.
- C3: the most severe pyogenic infections; CH50 and AH50 both low.
- C5–C9: recurrent Neisseria, both assays low. Properdin, factor B, factor D: Neisseria with an isolated low AH50 (properdin is X-linked).
- C1-INH: hereditary angioedema with low C4, normal C3 and C1q, no hives; avoid ACE inhibitors.
- DAF/CD59 (PNH) and factor H/I (atypical HUS) are regulator failures: too much complement, not too little.
- Anti-C5 drugs create an acquired terminal deficiency, so vaccinate against meningococcus.
Sources
- Complement Deficiency. StatPearls, NCBI Bookshelf
- Physiology, Complement Cascade. StatPearls, NCBI Bookshelf
- Hereditary and Acquired C1 Inhibitor Deficiency. Merck Manual Professional Edition
- High Risk for Invasive Meningococcal Disease Among Patients Receiving Eculizumab (Soliris) Despite Receipt of Meningococcal Vaccine. CDC MMWR, 2017
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
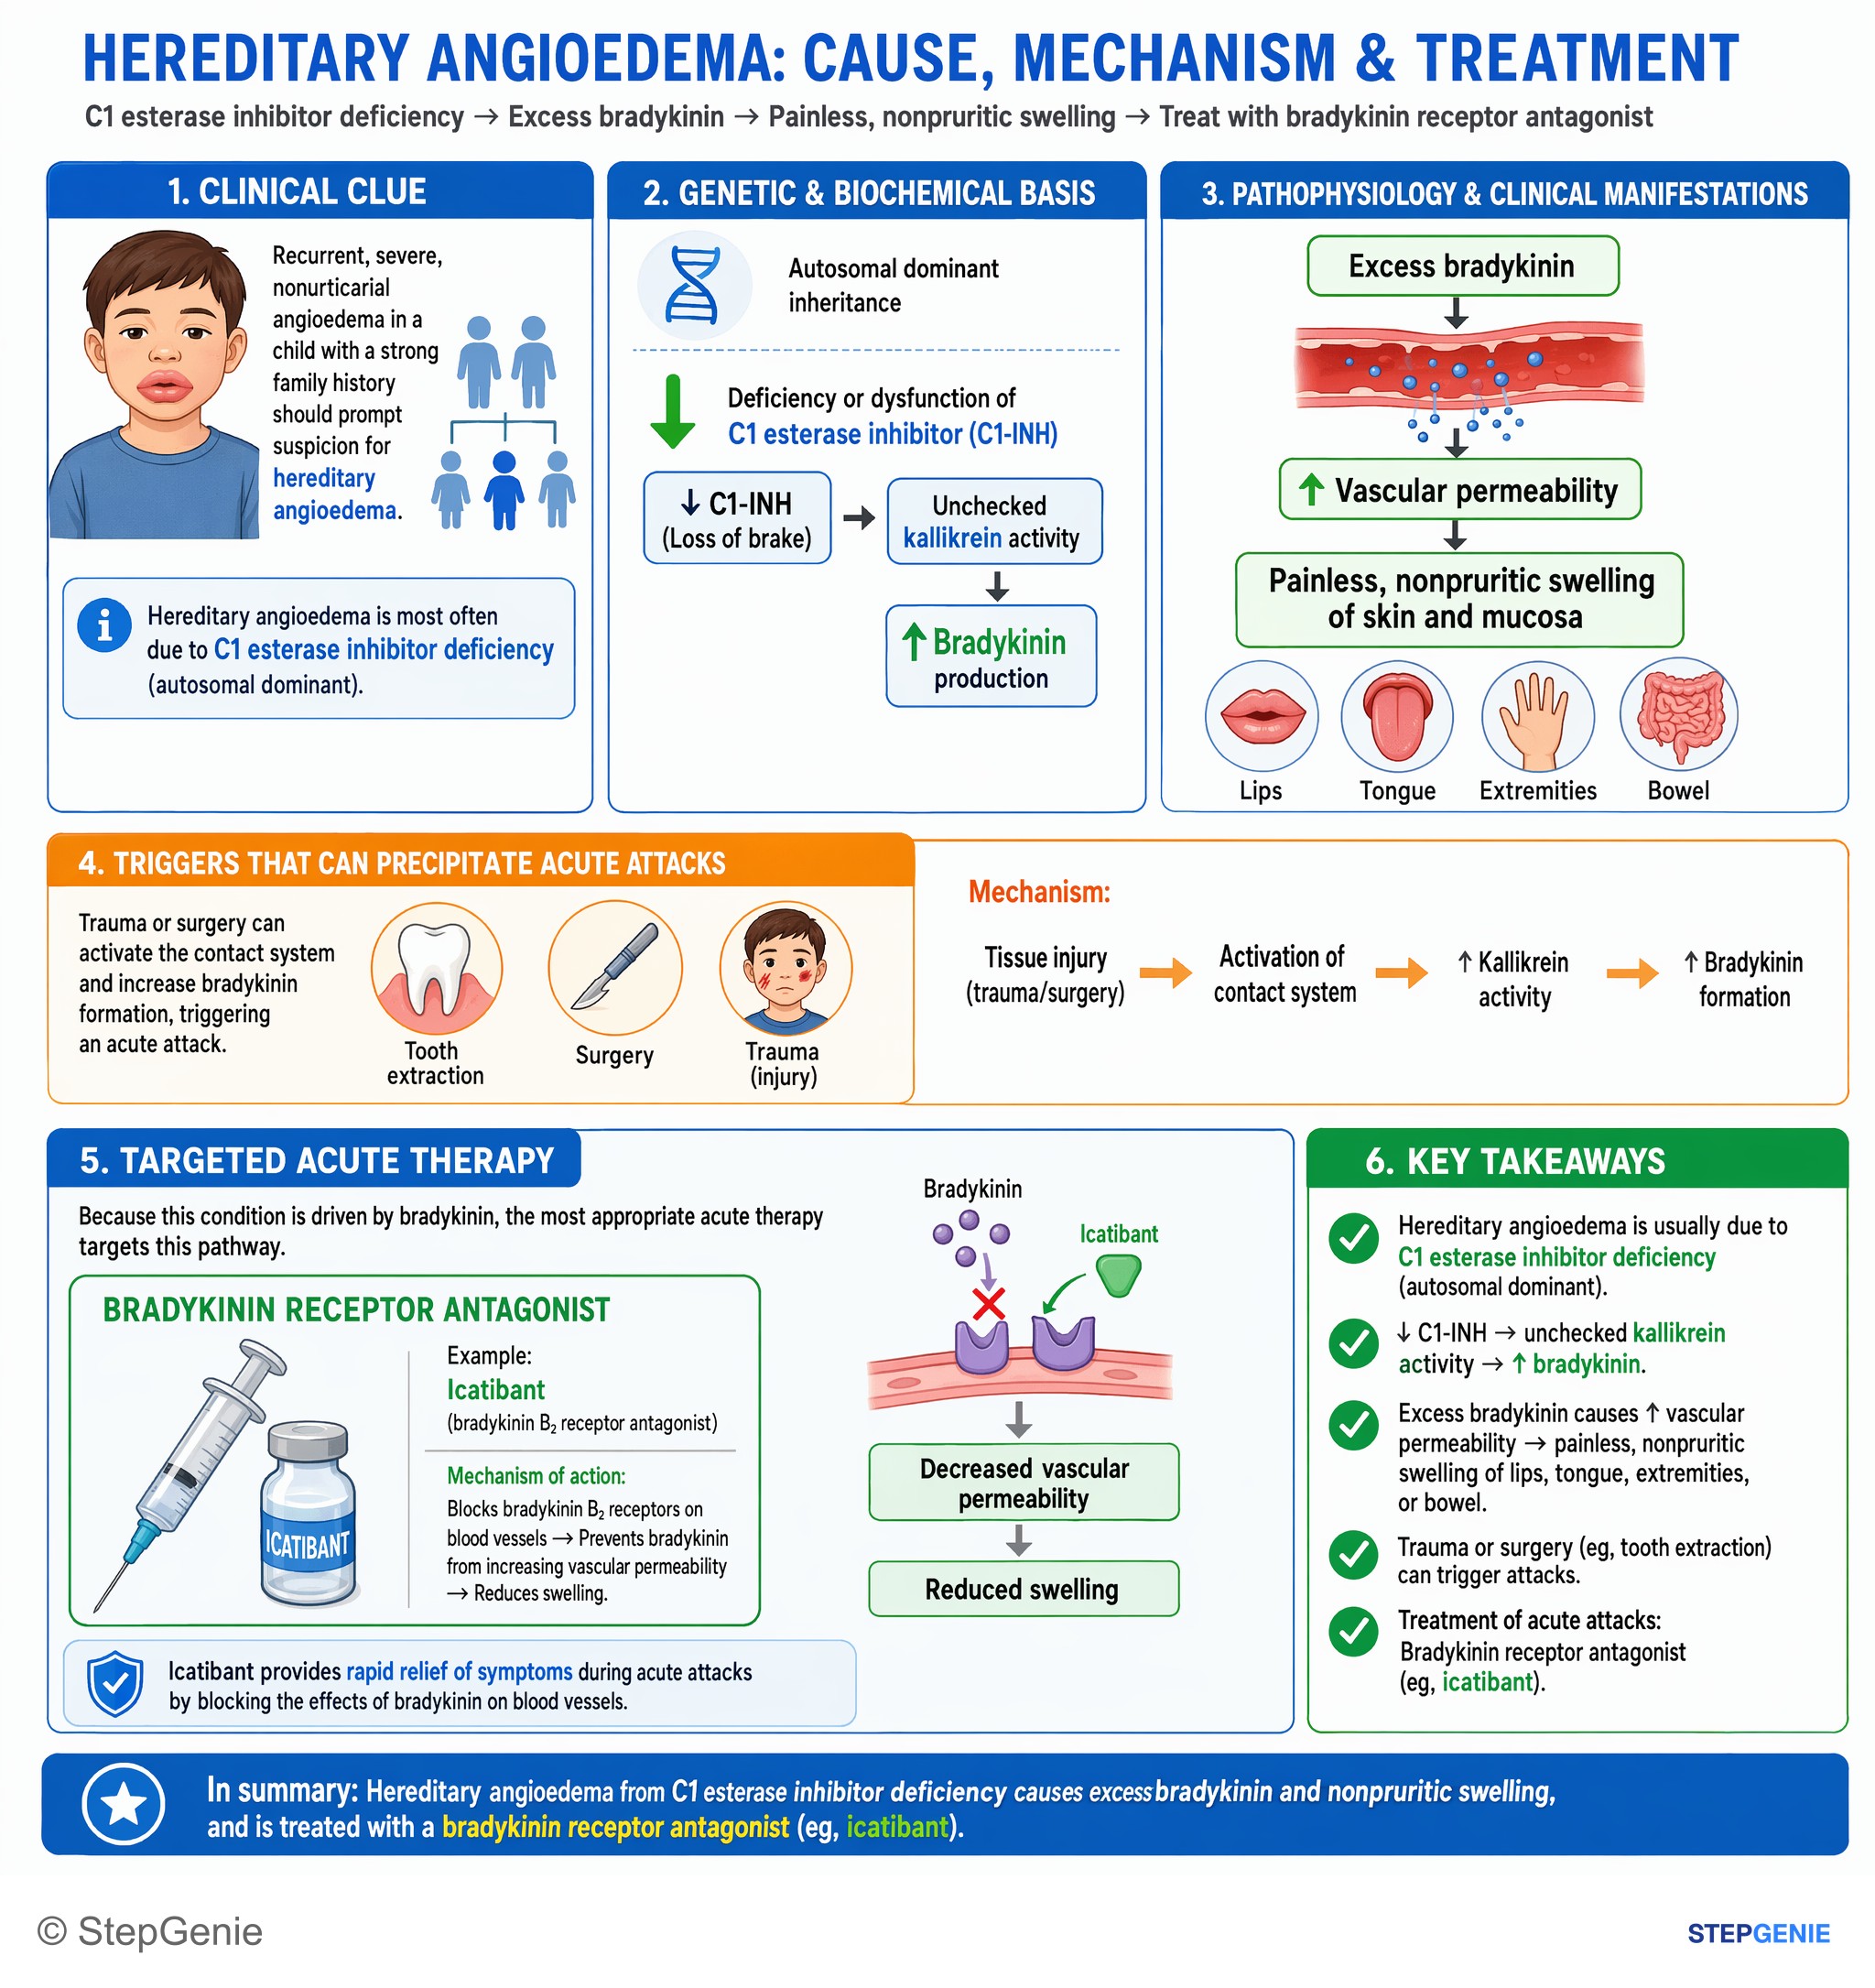
Hereditary angioedema from C1 esterase inhibitor deficiency → excess bradykinin → nonpruritic swelling; treat with bradykinin receptor…
USMLE Step 1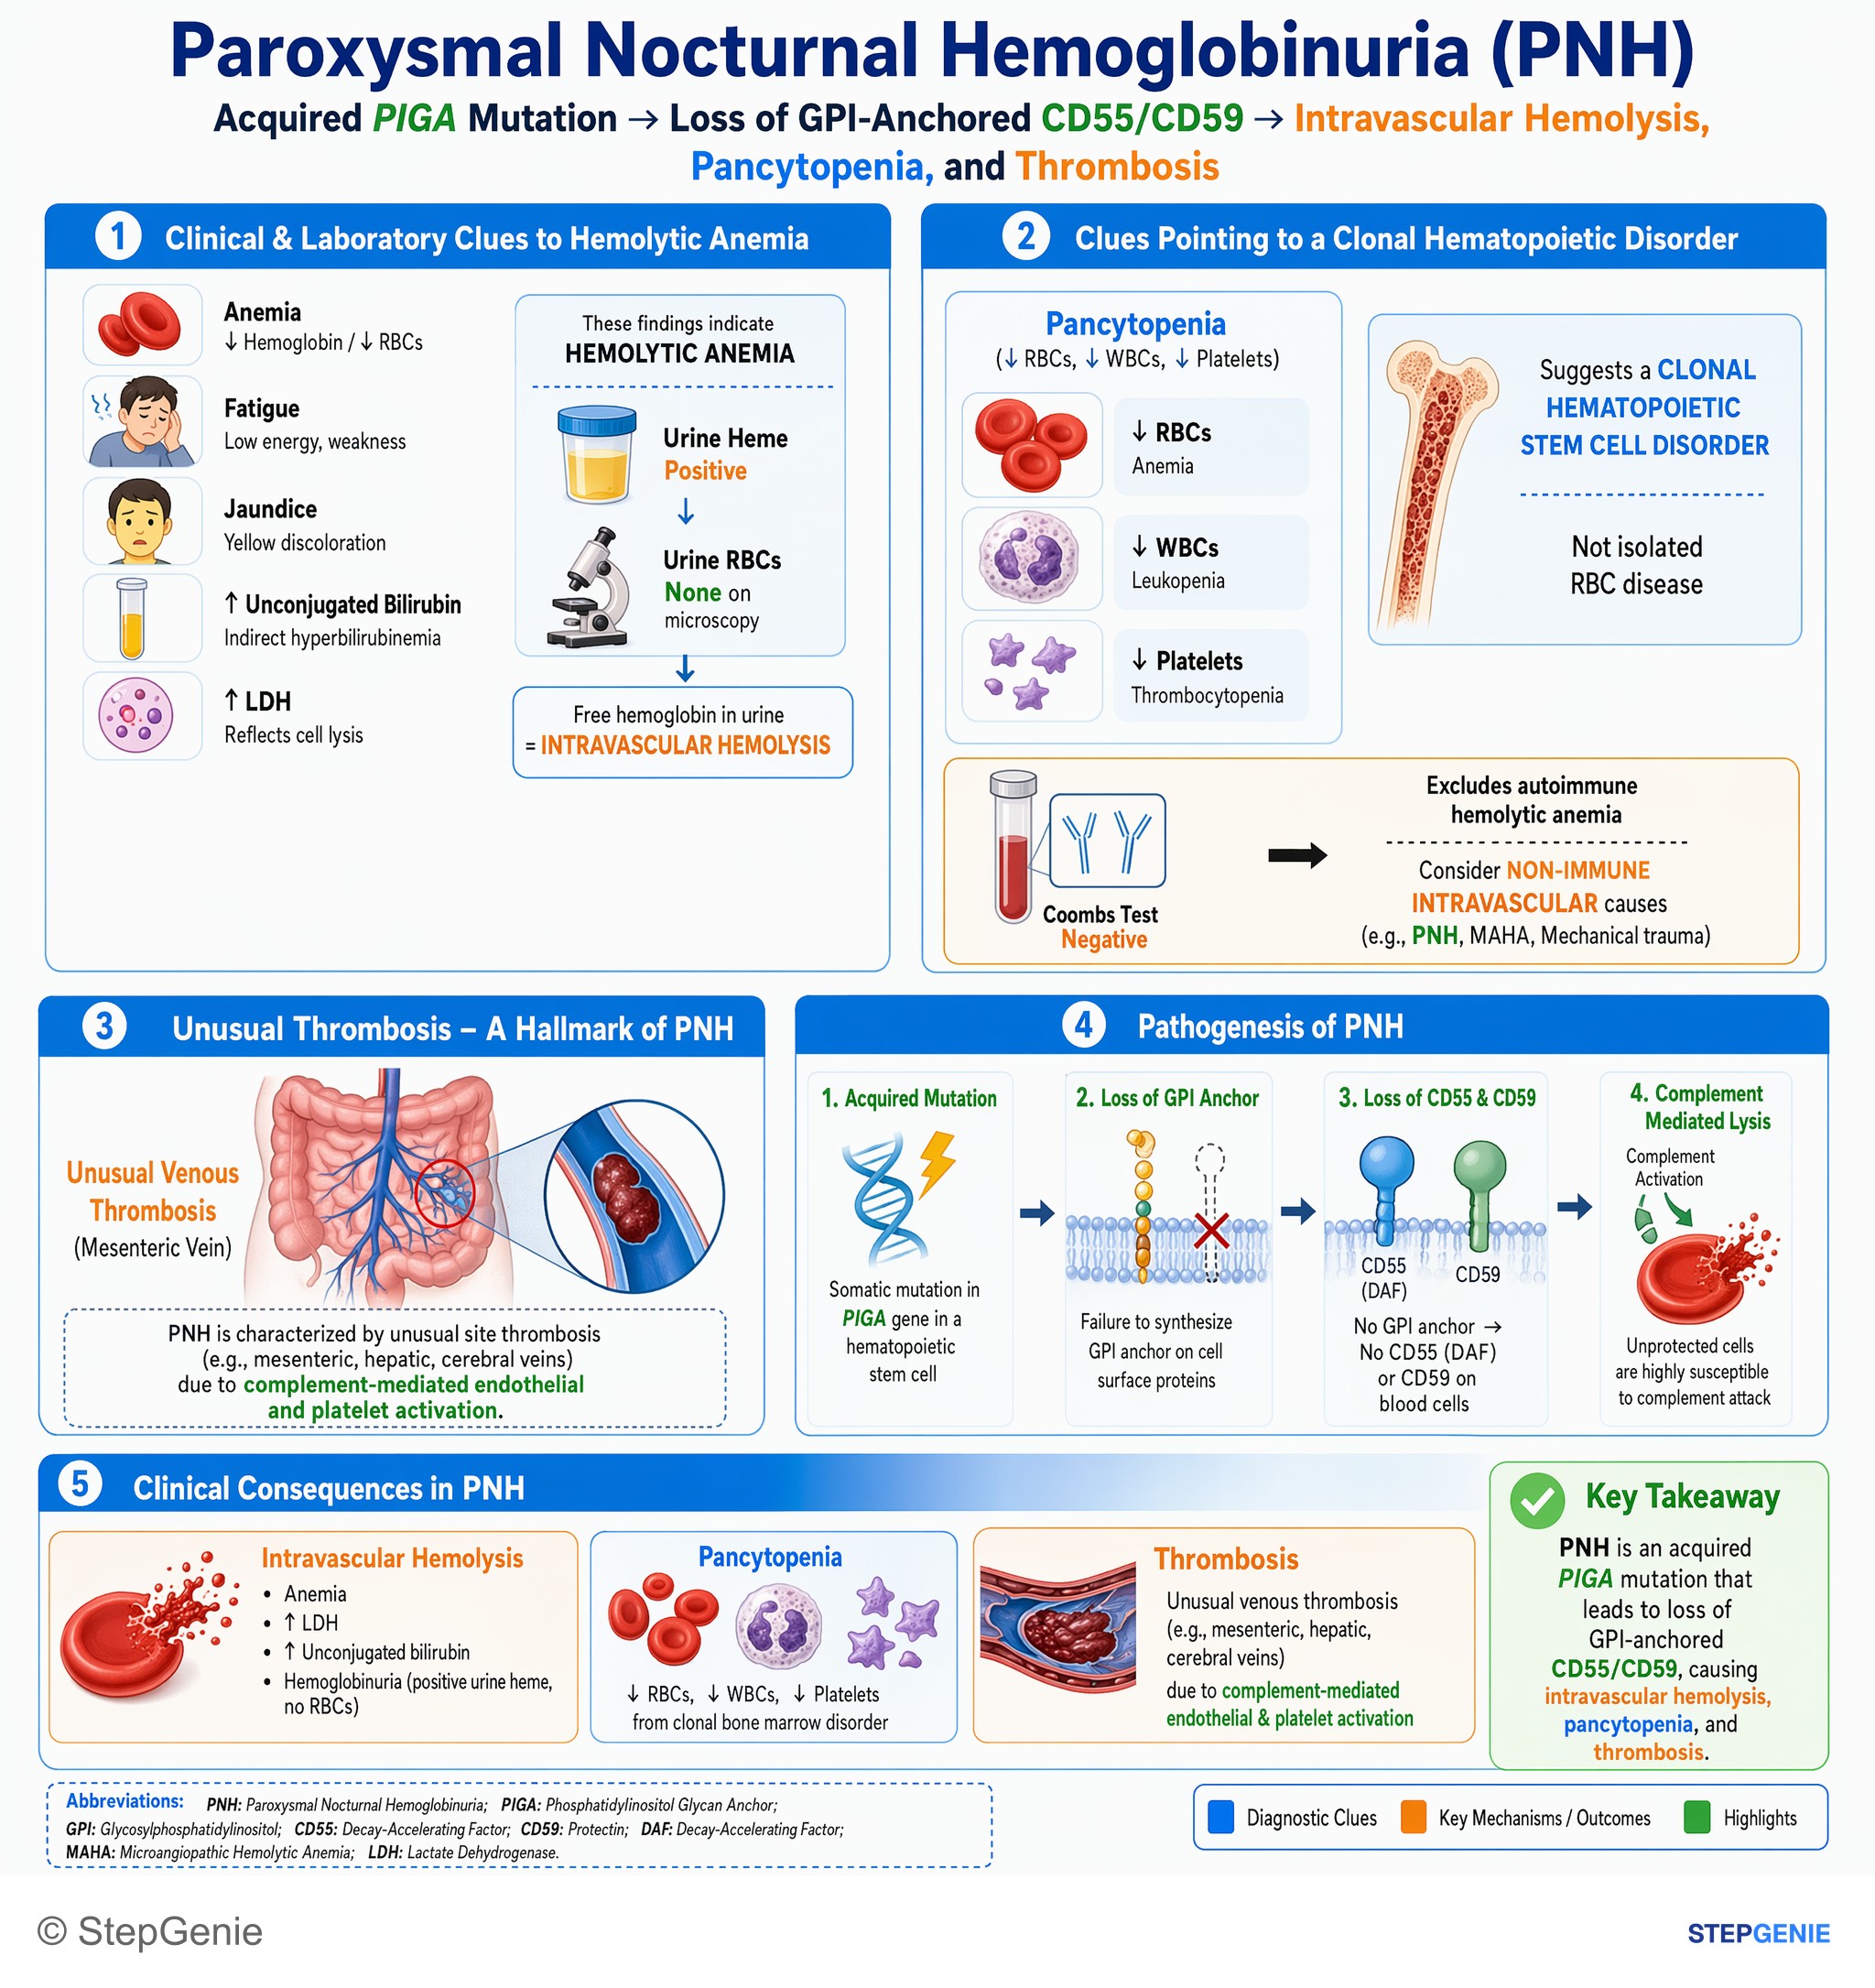
Paroxysmal nocturnal hemoglobinuria: acquired PIGA mutation → loss of GPI-anchored complement regulators (CD55/CD59) → intravascular…
USMLE Step 1Frequently Asked Questions
Which complement deficiency causes recurrent Neisseria infections?
Deficiency of any terminal component, C5 through C9, is the classic answer, because these proteins form the membrane attack complex that kills Neisseria. Alternative-pathway defects, especially X-linked properdin deficiency and factor D deficiency, also predispose to meningococcal disease. Patients taking the C5 inhibitors eculizumab or ravulizumab carry a similar drug-induced risk and need meningococcal vaccination.
What is the difference between CH50 and AH50?
CH50 tests the classical pathway through the terminal components, while AH50 tests the alternative pathway through the same terminal components. A low CH50 with a normal AH50 points to C1, C2 or C4; a normal CH50 with a low AH50 points to factor B, factor D or properdin; and both low points to C3 or C5-C9. Neither test detects mannose-binding lectin deficiency, which needs a separate MBL level.
Why do early complement deficiencies cause lupus?
C1q, C4 and C3b help clear immune complexes and apoptotic cell debris from the circulation and tissues. When these early classical proteins are missing, nuclear material persists and the immune system is more likely to make autoantibodies against it. C1q deficiency carries the highest risk, with most affected people developing SLE.
What lab finding is characteristic of hereditary angioedema?
A low C4 level, present even between attacks, is the best initial screening test, followed by measurement of C1-esterase inhibitor level and function. C3 is normal, and C1q is normal in the hereditary form but low in acquired C1-inhibitor deficiency. Urticaria and itching are absent because the swelling is driven by bradykinin rather than histamine.
What is the most common complement deficiency?
Mannose-binding lectin deficiency is the most common, reported in about 5% of White people, and it is usually silent or causes infections mainly in infancy. Among classical-pathway defects, C2 deficiency is the most common and is often asymptomatic, although it is associated with lupus. On exams, the most tested pairings are still C5-C9 with Neisseria and C1-esterase inhibitor with hereditary angioedema.