Type I hypersensitivity is the one that shows up everywhere—NBMEs, UWorld stems, and real wards—because it’s fast, dramatic, and medication-relevant. If you can instantly recognize the mechanism (IgE + mast cells) and the classic clinical patterns (anaphylaxis, atopy), you’ll grab easy points.
The “Type I = IgE = Immediate” visual hack
Visual mnemonic: “I = IgE = Instant”
Picture a big letter “I” shaped like a lightning bolt (immediate reaction).
At the top sits IgE like a hat, and along the bolt are mast cells/basophils popping open and spilling histamine + leukotrienes.
One-liner you should be able to say in your sleep:
Type I hypersensitivity = allergen cross-links IgE on mast cells → immediate histamine release + late leukotrienes/eosinophils.
High-yield pathway (Step-style)
Step 1: Sensitization (first exposure)
- Allergen (pollen, peanuts, cat dander, etc.)
- Th2 response → IL-4 & IL-13 drive B cells to class switch to IgE
- IgE binds FcRI receptors on mast cells & basophils
- Patient is now sensitized (no major symptoms required yet)
Step 2: Re-exposure (the reaction)
- Allergen cross-links IgE on mast cells
- Mast cell activation → two phases:
| Phase | Timing | Main mediators | What they do | Classic findings |
|---|---|---|---|---|
| Immediate | minutes | Histamine, tryptase | Vasodilation, ↑ vascular permeability, bronchoconstriction, pruritus | Urticaria, wheeze, flushing, hypotension |
| Late | hours | Leukotrienes (LTC4, LTD4, LTE4), cytokines (e.g., IL-5) | Sustained bronchospasm, mucus, inflammation, eosinophil recruitment | Persistent asthma symptoms, ongoing edema/inflammation |
USMLE pearl: Leukotrienes are often the reason symptoms persist (think asthma exacerbation with mucus + bronchoconstriction).
What Type I looks like clinically (pattern recognition)
Anaphylaxis (systemic Type I)
High-yield triggers
- Foods: peanuts, shellfish
- Stings: bees/wasps
- Drugs: penicillins/cephalosporins, NSAIDs (can also be non-IgE), biologics
- Latex
Classic presentation
- Hypotension (distributive shock), urticaria/angioedema, bronchospasm
- GI cramping, vomiting, diarrhea can occur
Test clue labs
- Elevated serum tryptase (mast cell degranulation marker)
Immediate management (Step 2 emphasis)
- IM epinephrine (anterolateral thigh) is first-line
- Then: airway/oxygen, IV fluids, H1/H2 blockers, corticosteroids, inhaled beta-agonists as needed
If the stem has airway swelling + hypotension after allergen exposure: epinephrine first.
Atopy (localized Type I)
The “atopic triad” is pure exam fuel:
- Atopic dermatitis (eczema)
- Allergic rhinitis
- Asthma
Pathophysiology snapshot
- Th2-skewed immune response → IgE + eosinophils
- Often a personal/family history of allergic disease
Classic Step associations
- Eosinophils (especially in asthma/allergic inflammation)
- Asthma: Curschmann spirals and Charcot-Leyden crystals can show up in questions
- Eczema: barrier dysfunction + itch-scratch cycle (often with elevated IgE)
Mini-mnemonics that actually help on exam day
“Type I: IgE, Immediate, Itchy”
- Itchy/wheezy symptoms = histamine + bronchoconstriction
- Immediate onset = minutes
“Th2 makes you ‘SNEEZE’”
- Switch to IgE (IL-4, IL-13)
- Nasal/allergic symptoms
- Eosinophils (IL-5)
- Exposure → cross-link IgE
- Zaps mast cells (degranulation)
- Edema/urticaria/bronchospasm
Ultra-high-yield differentiators (don’t mix these up)
| Reaction type | Key mechanism | Timing | Classic example |
|---|---|---|---|
| Type I | IgE-mediated mast cell degranulation | Minutes | Anaphylaxis, allergic rhinitis, asthma |
| Type II | IgG/IgM against cell surface/ECM | Hours–days | Autoimmune hemolytic anemia, Goodpasture |
| Type III | Immune complexes deposit | Days | Serum sickness, post-strep GN |
| Type IV | T-cell mediated (no antibodies) | 48–72 hrs | Contact dermatitis, PPD test |
Rapid-fire USMLE takeaways
- Type I = IgE + mast cells + immediate symptoms
- Sensitization first (Th2 → IL-4/IL-13 → IgE)
- Re-exposure → IgE cross-linking → mast cell degranulation
- Histamine = immediate, leukotrienes/eosinophils = late
- Anaphylaxis treatment = IM epinephrine (then supportive meds)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
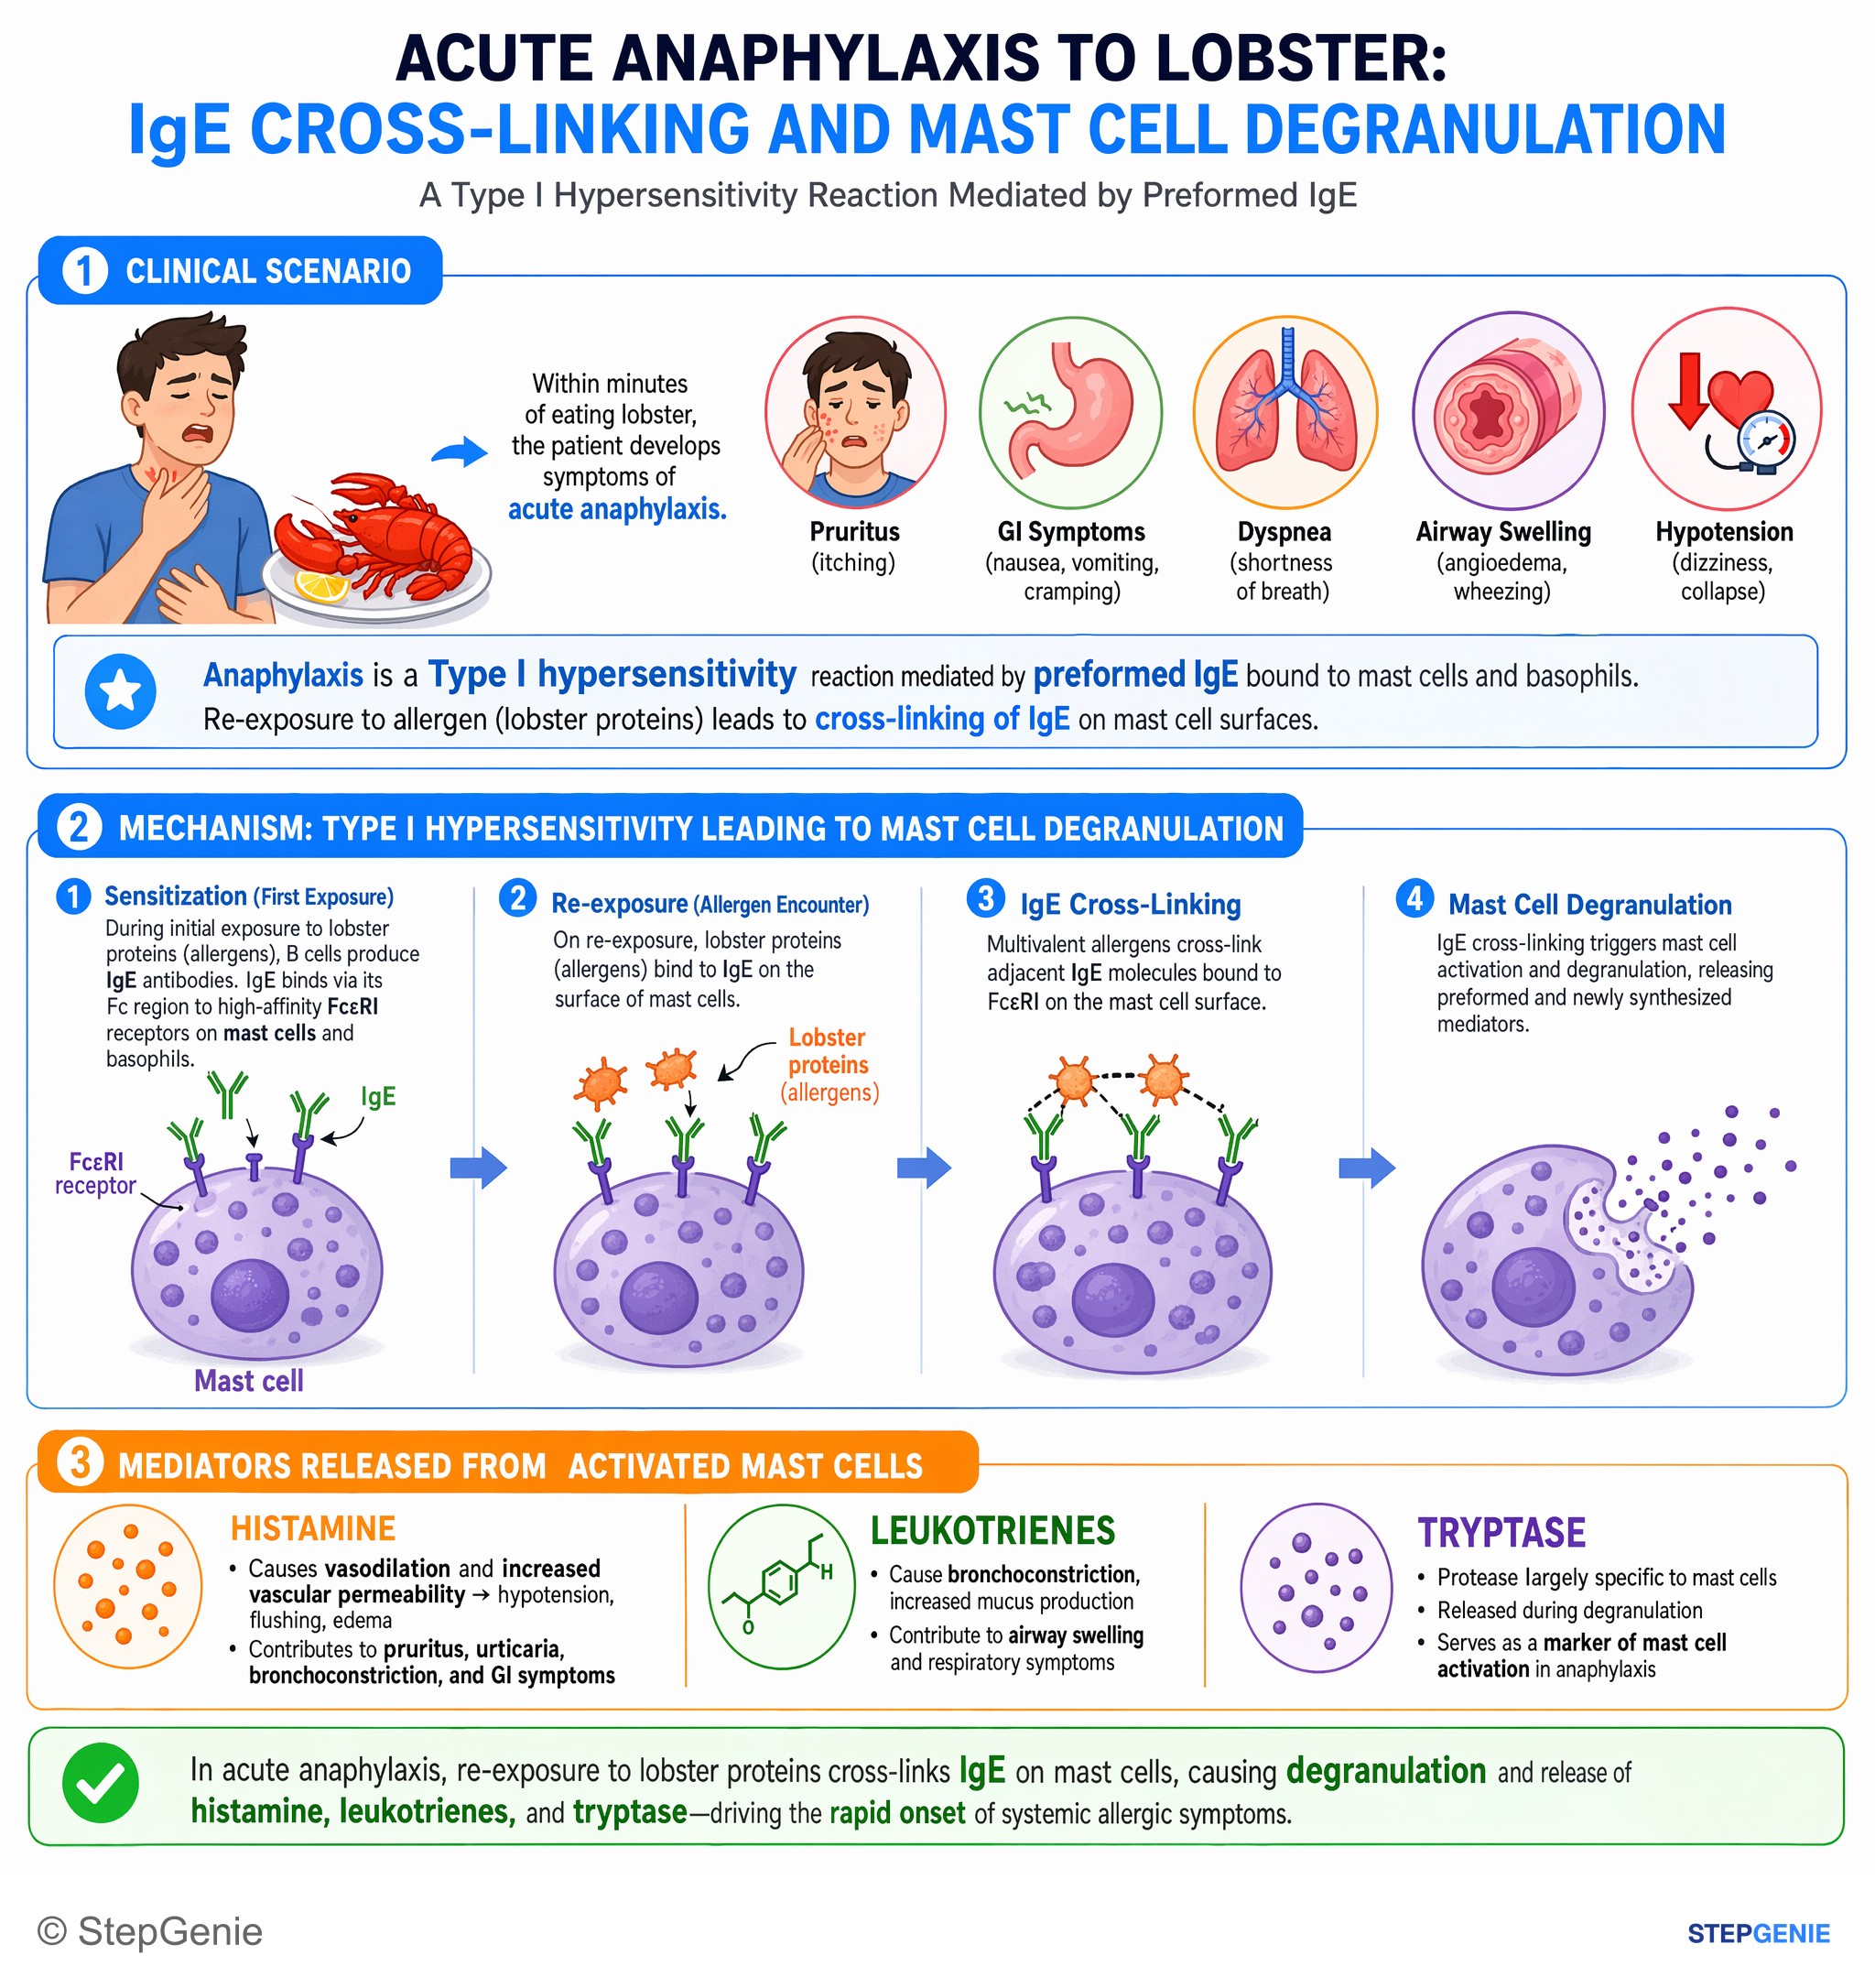
Type I hypersensitivity/anaphylaxis from IgE cross-linking on mast cells causes degranulation with release of histamine and tryptase.
USMLE Step 1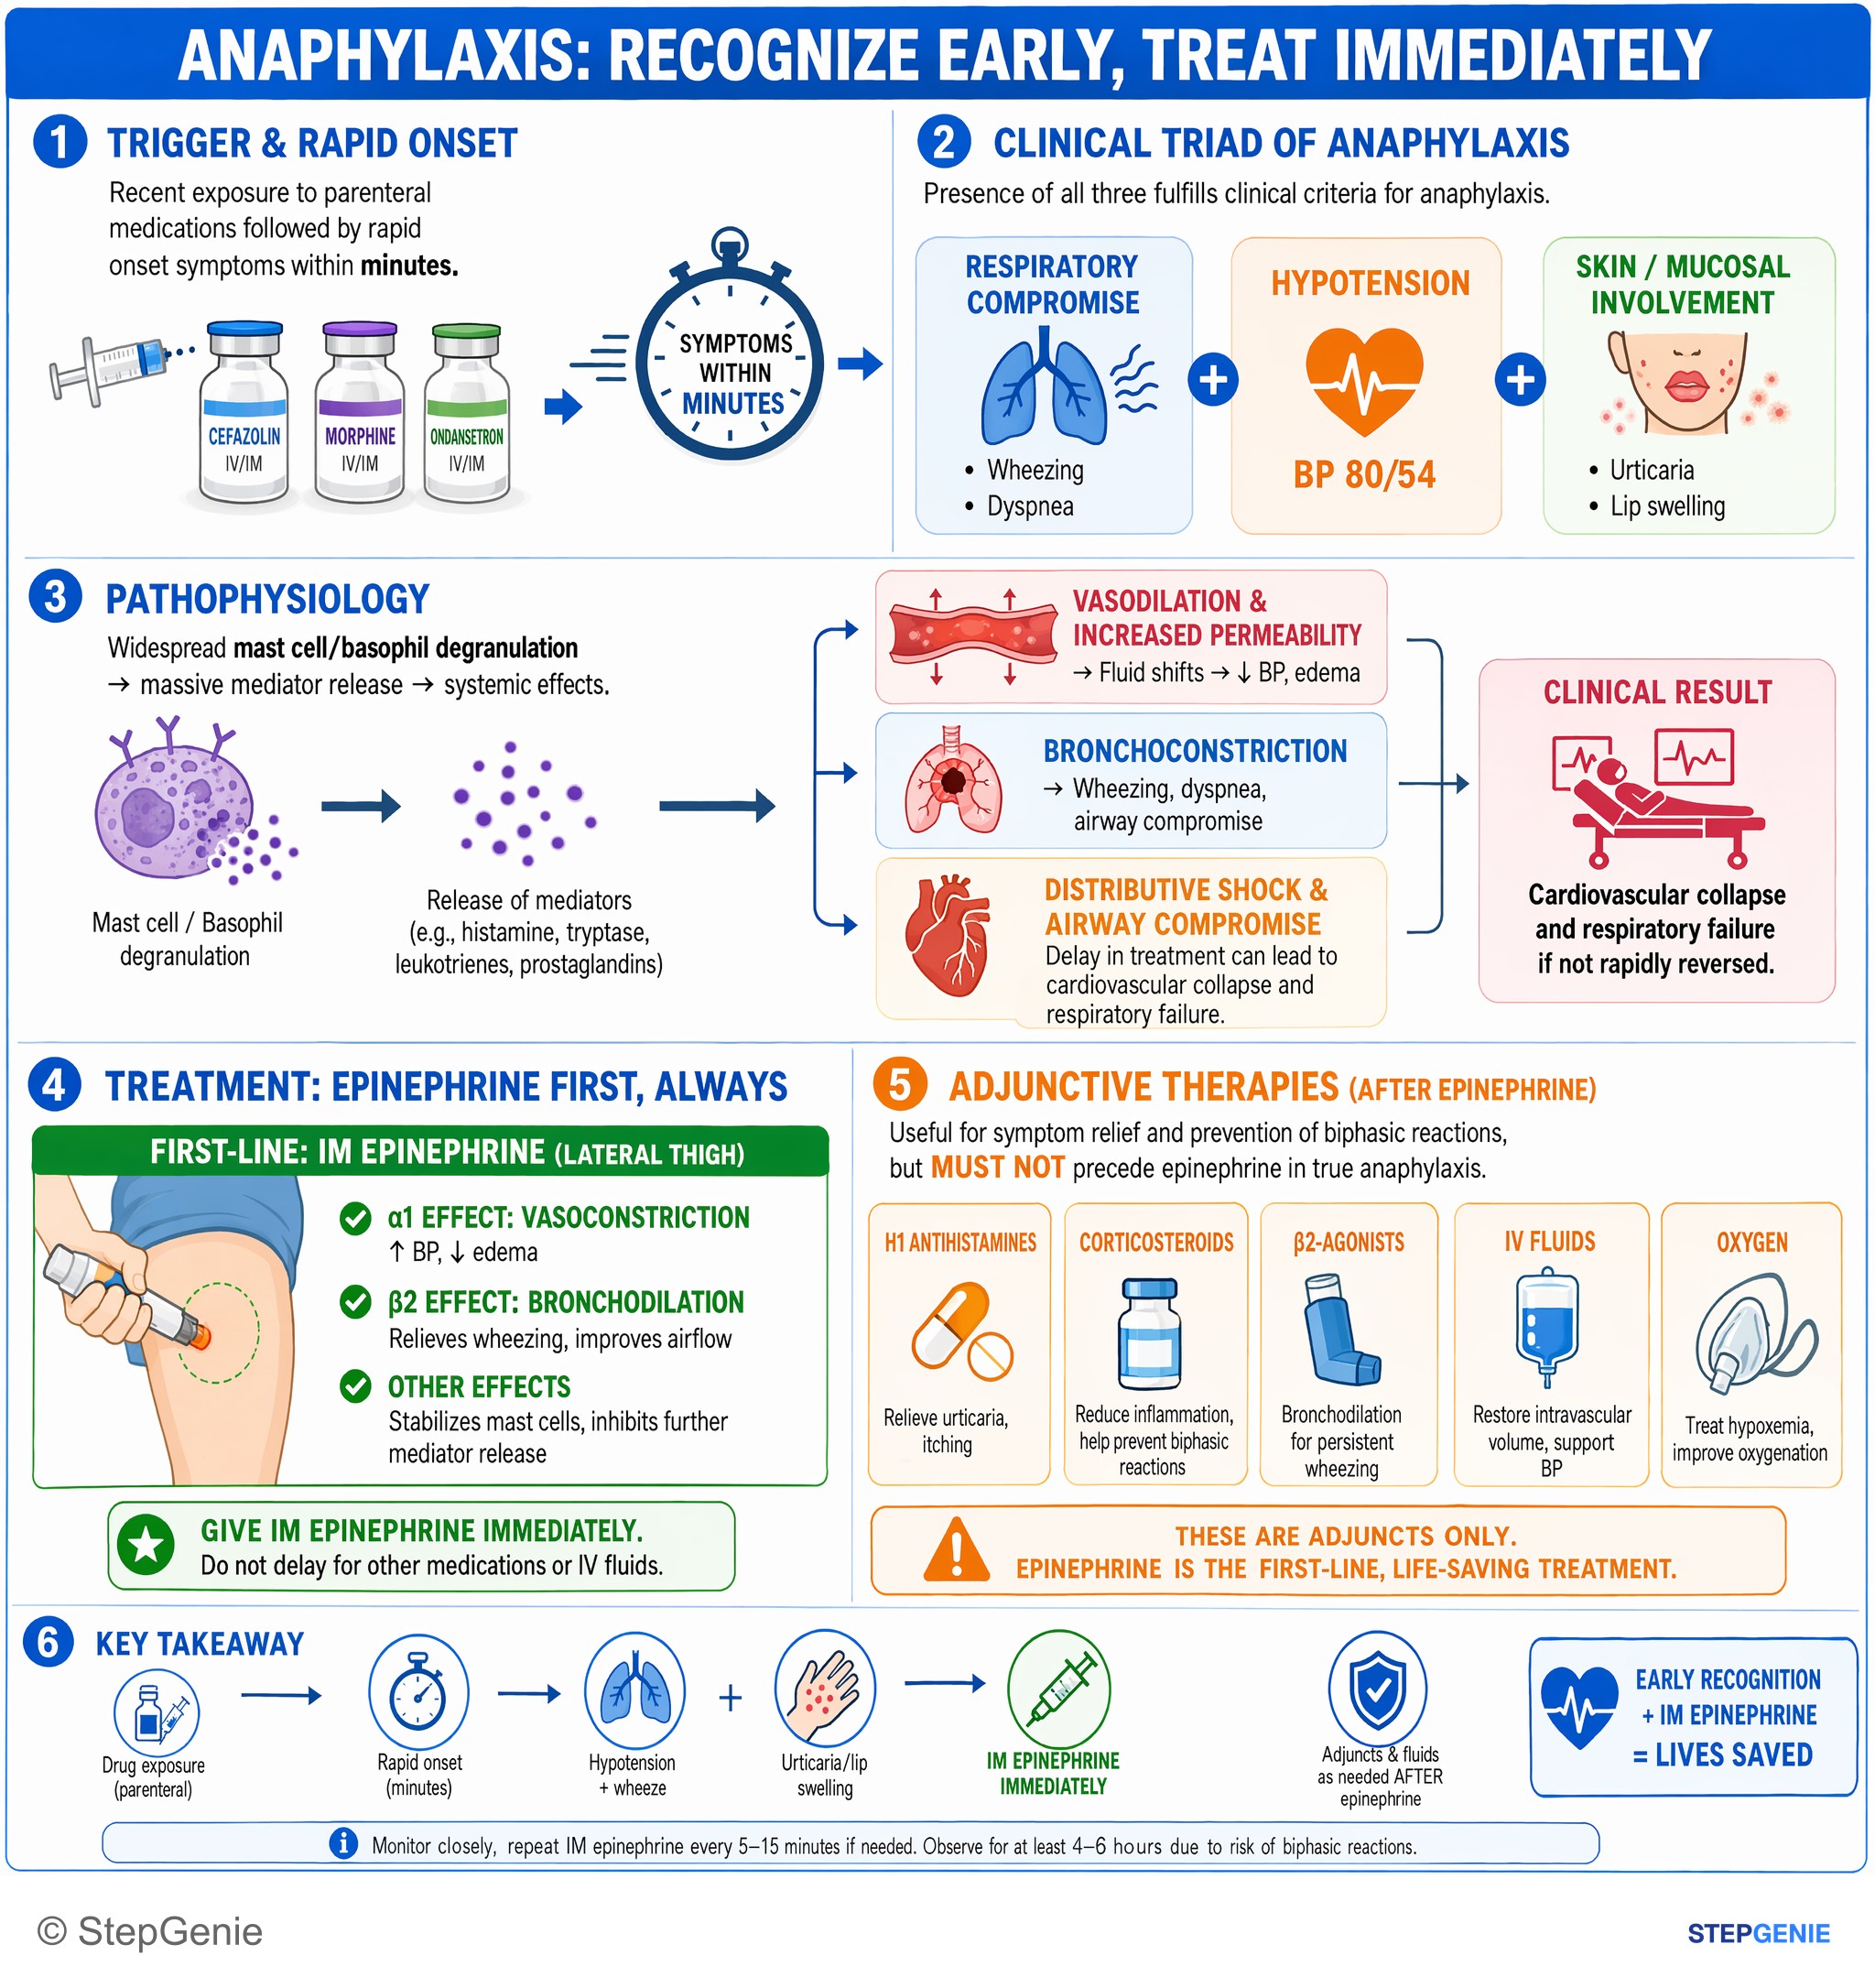
Anaphylaxis (hypotension, wheeze, urticaria after drug exposure) requires immediate IM epinephrine as first-line treatment, before…
USMLE Step 2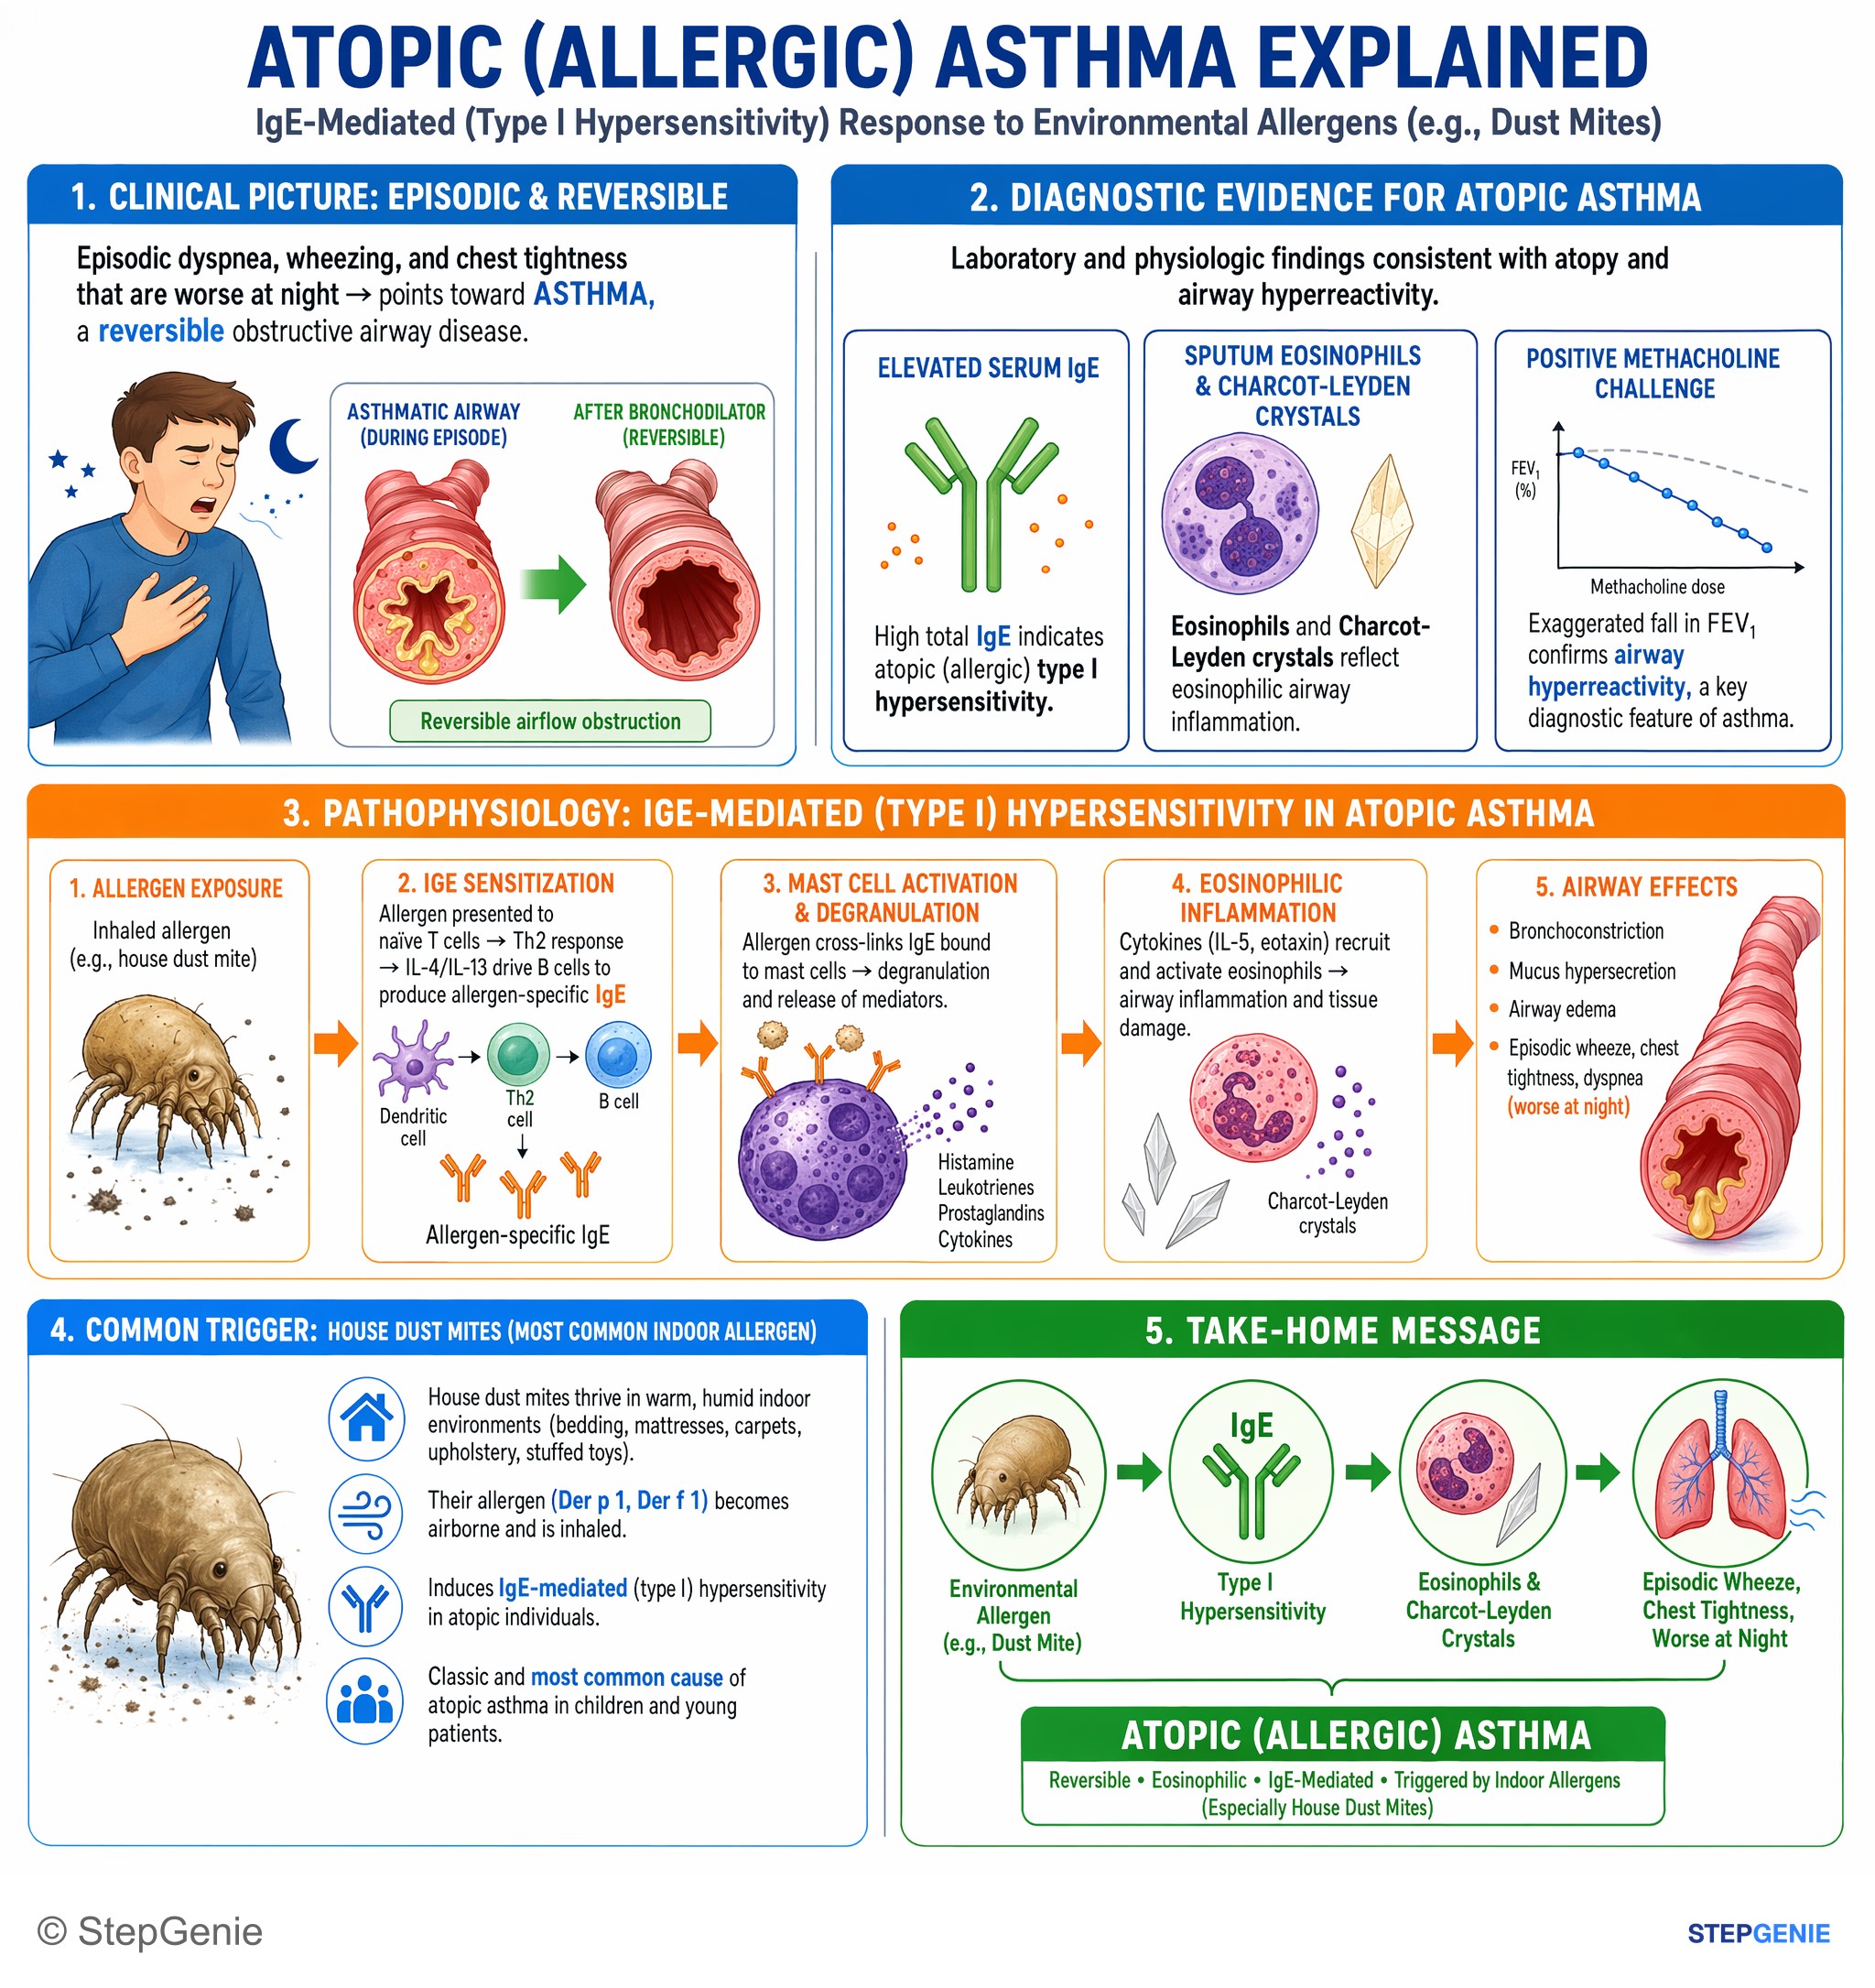
Allergic (atopic) asthma from environmental allergens (e.g., dust mites) → type I hypersensitivity with IgE, eosinophils, Charcot-Leyden…
USMLE Step 1Frequently Asked Questions
What is the mechanism of type I hypersensitivity?
Type I hypersensitivity is an IgE-mediated immediate reaction caused by allergen cross-linking of IgE on mast cells. On first exposure, a Th2 response with IL-4 and IL-13 drives B cells to class-switch to IgE, which binds FcεRI receptors on mast cells and basophils. On re-exposure, the allergen cross-links that IgE, triggering mast cell degranulation with histamine release and a later leukotriene- and eosinophil-driven phase.
Why do type I hypersensitivity symptoms happen immediately and then persist for hours?
The immediate symptoms are driven by histamine released from activated mast cells within minutes, while persistent symptoms are driven by later mediators such as leukotrienes and cytokines. Histamine causes vasodilation, increased vascular permeability, bronchoconstriction, and pruritus, producing urticaria, wheeze, flushing, and hypotension. Hours later, leukotrienes and IL-5 promote sustained bronchospasm, mucus production, inflammation, and eosinophil recruitment.
What is the first-line treatment for anaphylaxis?
IM epinephrine in the anterolateral thigh is the first-line treatment for anaphylaxis. This is especially important when a patient has airway swelling and hypotension after allergen exposure. Additional management can include airway support, oxygen, IV fluids, H1 and H2 blockers, corticosteroids, and inhaled beta-agonists, but epinephrine should come first in the acute setting.
How do you recognize anaphylaxis on a question stem?
Anaphylaxis is recognized by a rapid systemic allergic reaction with hypotension, urticaria or angioedema, and bronchospasm after exposure to a trigger. Common triggers include foods such as peanuts or shellfish, insect stings, drugs like penicillins or cephalosporins, and latex. Gastrointestinal cramping, vomiting, and diarrhea can also occur, and elevated serum tryptase is a clue to mast cell degranulation.
How do you tell type I hypersensitivity apart from the other hypersensitivity reactions?
Type I hypersensitivity is the immediate one: it is IgE-mediated, causes mast cell degranulation, and appears within minutes. Classic examples are anaphylaxis, allergic rhinitis, and asthma. By contrast, type II is IgG or IgM against cell surface or extracellular matrix targets over hours to days, type III is immune complex deposition over days, and type IV is T-cell mediated over 48 to 72 hours.