Type II hypersensitivity is one of those “easy to recognize once you see it” immunology patterns: IgG/IgM bind to antigens on cells or extracellular matrix → the immune system destroys or malfunctions that target. If you can picture the mechanism, you can usually nail the question stem in seconds.
The 10-second one-liner (what Step wants)
Type II (cytotoxic) hypersensitivity = IgG or IgM against fixed antigens (cell surface or ECM) → complement/opsinization/ADCC or receptor dysfunction.
Memory Palace: “The Antibody Police at Cell Surface City”
Walk into Cell Surface City, where antibodies act like cops tagging “criminals” stuck on buildings (cell membranes) or city walls (basement membrane/ECM).
Room 1: The “Badge & Siren” Station — Opsonization + Phagocytosis
You see IgG cops putting handcuffs on a red blood cell, then dragging it to the Spleen “Jail”.
Mnemonic image: IgG handcuffs + spleen jail cell
USMLE translation:
- IgG opsonizes cells → macrophages in spleen/liver remove them (extravascular hemolysis).
- Classically tested in:
- Autoimmune hemolytic anemia
- Hemolytic disease of the newborn (Rh incompatibility; IgG crosses placenta)
- ITP (platelet destruction)
- Transfusion reactions
High-yield clue words: spherocytes, splenomegaly, extravascular hemolysis, positive Coombs (DAT)
Room 2: The “Complement Cannon” — MAC-mediated cell lysis
In the next room, an IgM “pentamer tank” fires a complement cannon at a cell, punching holes with the MAC (C5b-9).
Mnemonic image: IgM pentamer tank launching complement cannonballs
USMLE translation:
- IgM is the best complement activator (also IgG can do it).
- Complement can:
- Lyse cells directly (MAC)
- Promote inflammation via C3a/C5a
- Increase opsonization via C3b
High-yield clue words: intravascular hemolysis (classically), low complement in immune complex processes (context matters)
Room 3: The “Natural Killer Bouncer” — ADCC
At a club door, an NK cell bouncer grabs an antibody-tagged target using Fc receptors (CD16) and kicks it out.
Mnemonic image: NK bouncer scanning Fc “VIP pass” (CD16)
USMLE translation:
- ADCC = antibody-coated target killed by NK cells (also eosinophils can do ADCC in parasites, but that’s more Type I/Th2 contexts).
Room 4: The “Broken Receptor Switchboard” — Antibodies alter receptor function
Finally, you enter a switchboard room where antibodies either jam the “OFF” button or hold the “ON” button down.
Mnemonic image: Sticky antibodies on a light switch: stuck OFF or ON
USMLE translation (mega-testable):
- Myasthenia gravis: antibodies block ACh receptors → decreased neuromuscular transmission
- Graves disease: antibodies stimulate TSH receptor → increased thyroid hormone
High-yield clue words:
- MG: ptosis, diplopia, fatigability; improves with rest; thymic abnormalities
- Graves: exophthalmos, pretibial myxedema, diffuse goiter, thyroid-stimulating immunoglobulins
Rapid-fire “Type II = Cytotoxic” anchor mnemonic
“C-I-T-Y” mnemonic (Cell surface City)
- Complement activation (IgM > IgG)
- Inflammation + opsonization (C3b, Fc-mediated phagocytosis)
- Target is Tethered (cell surface or ECM—not soluble antigen)
- You can get receptor dysfunction (on/off)
High-yield table: Type II vs common confusion points
| Feature | Type II (Cytotoxic) | Type III (Immune complex) | Type IV (Delayed, T-cell) |
|---|---|---|---|
| Main immune player | IgG/IgM | IgG immune complexes | T cells (Th1/Th17, CD8+) |
| Antigen location | Fixed (cell surface/ECM) | Soluble → deposits in tissues | Cellular antigens |
| Key mechanisms | Complement, opsonization, ADCC, receptor blockade/stimulation | Complement + neutrophils at deposition sites | Cytokine-mediated inflammation or direct cytotoxicity |
| Classic examples | AIHA, ITP, Goodpasture, MG, Graves | SLE, PSGN, serum sickness, Arthus reaction | Contact dermatitis, TB test, type 1 DM |
Classic diseases to attach to the palace (know these cold)
Goodpasture syndrome (Type II)
- Anti–type IV collagen (basement membrane) in glomeruli + alveoli
- Findings: hemoptysis + hematuria
- IF pattern: linear staining
Pemphigus vulgaris (often tested as Type II)
- Anti-desmoglein (desmosomes) → intraepidermal blister
- Findings: flaccid bullae, +Nikolsky sign
Bullous pemphigoid (also antibody-mediated, high-yield)
- Anti-hemidesmosomes → subepidermal blister
- Findings: tense bullae, typically negative Nikolsky
Exam tip: If the stem screams “antibodies against a structural protein in skin or basement membrane,” Type II should jump to mind.
The “2-step” exam approach (fast identification)
- Is the antigen fixed on a cell or basement membrane?
- Yes → think Type II
- Is it destruction or dysfunction?
- Destruction: complement/opsonization/ADCC
- Dysfunction: receptor blockade or stimulation
Mini self-check (one question worth of clarity)
If IgG binds RBC antigens and the patient gets anemia + jaundice + splenomegaly, what’s happening?
- Type II → IgG opsonization → splenic macrophages remove RBCs (extravascular hemolysis) → positive direct Coombs test.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
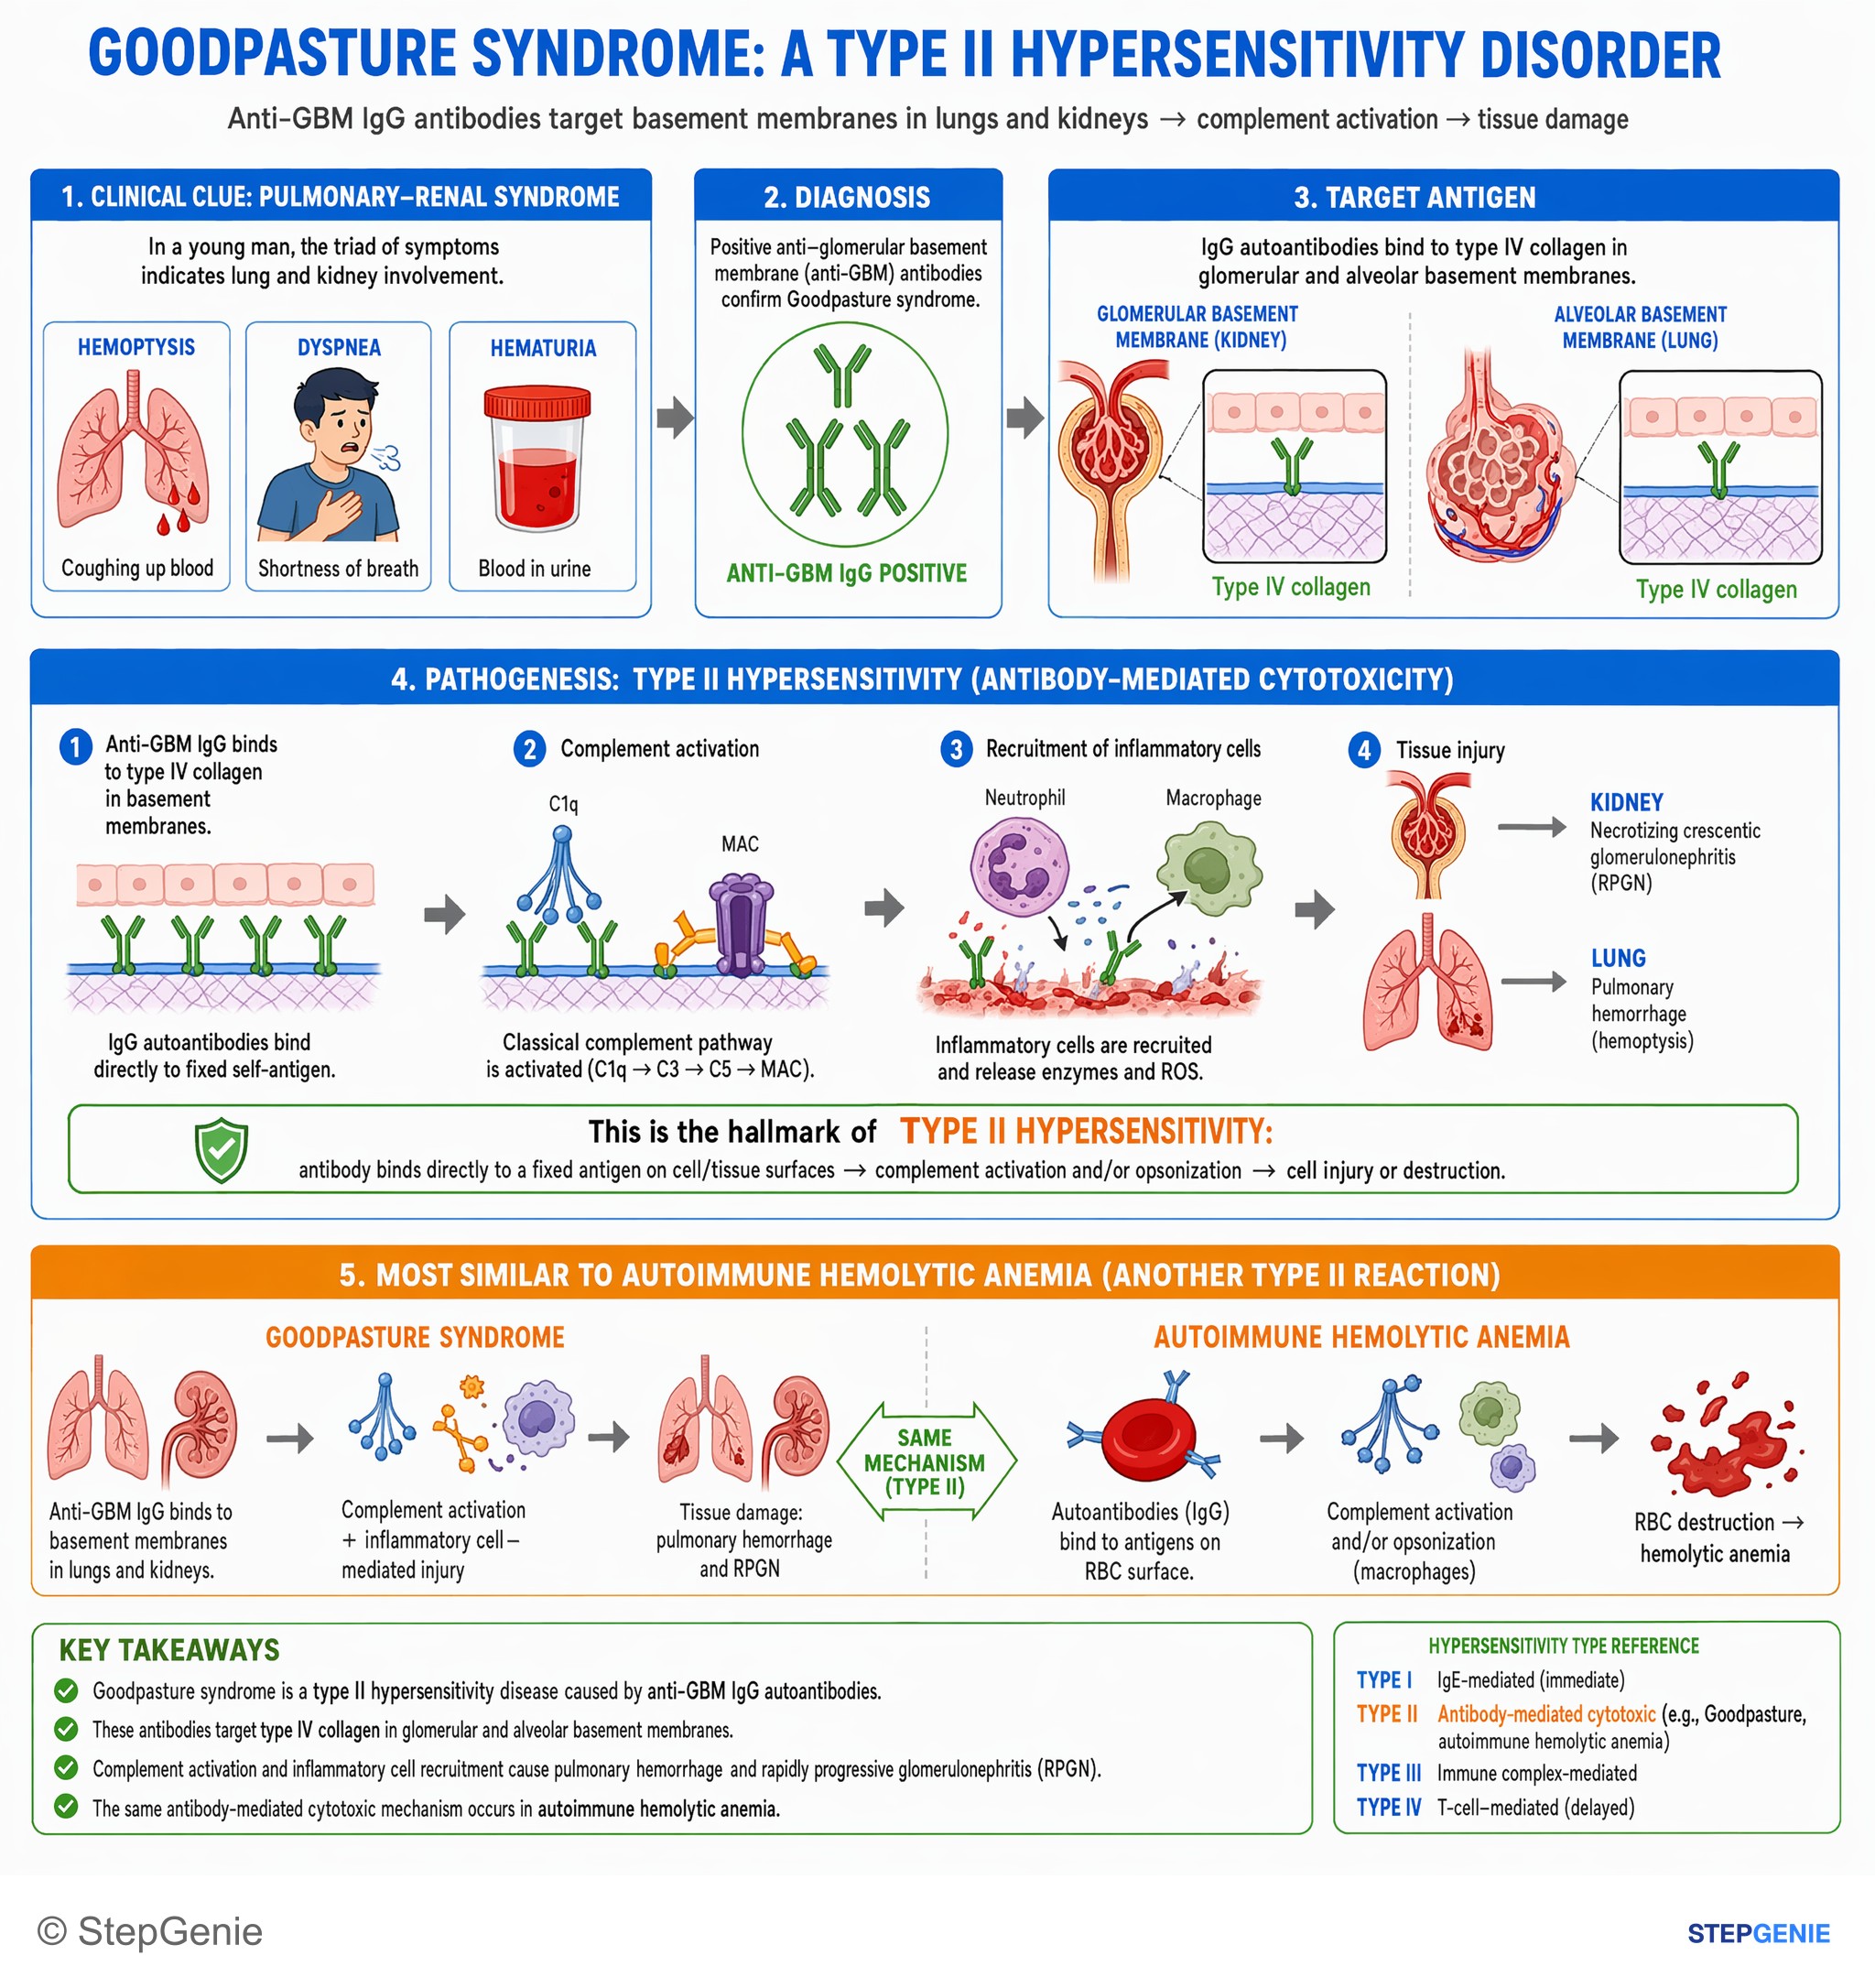
Goodpasture syndrome: type II hypersensitivity with anti-GBM IgG causing pulmonary hemorrhage and RPGN; mechanism mirrors other…
USMLE Step 1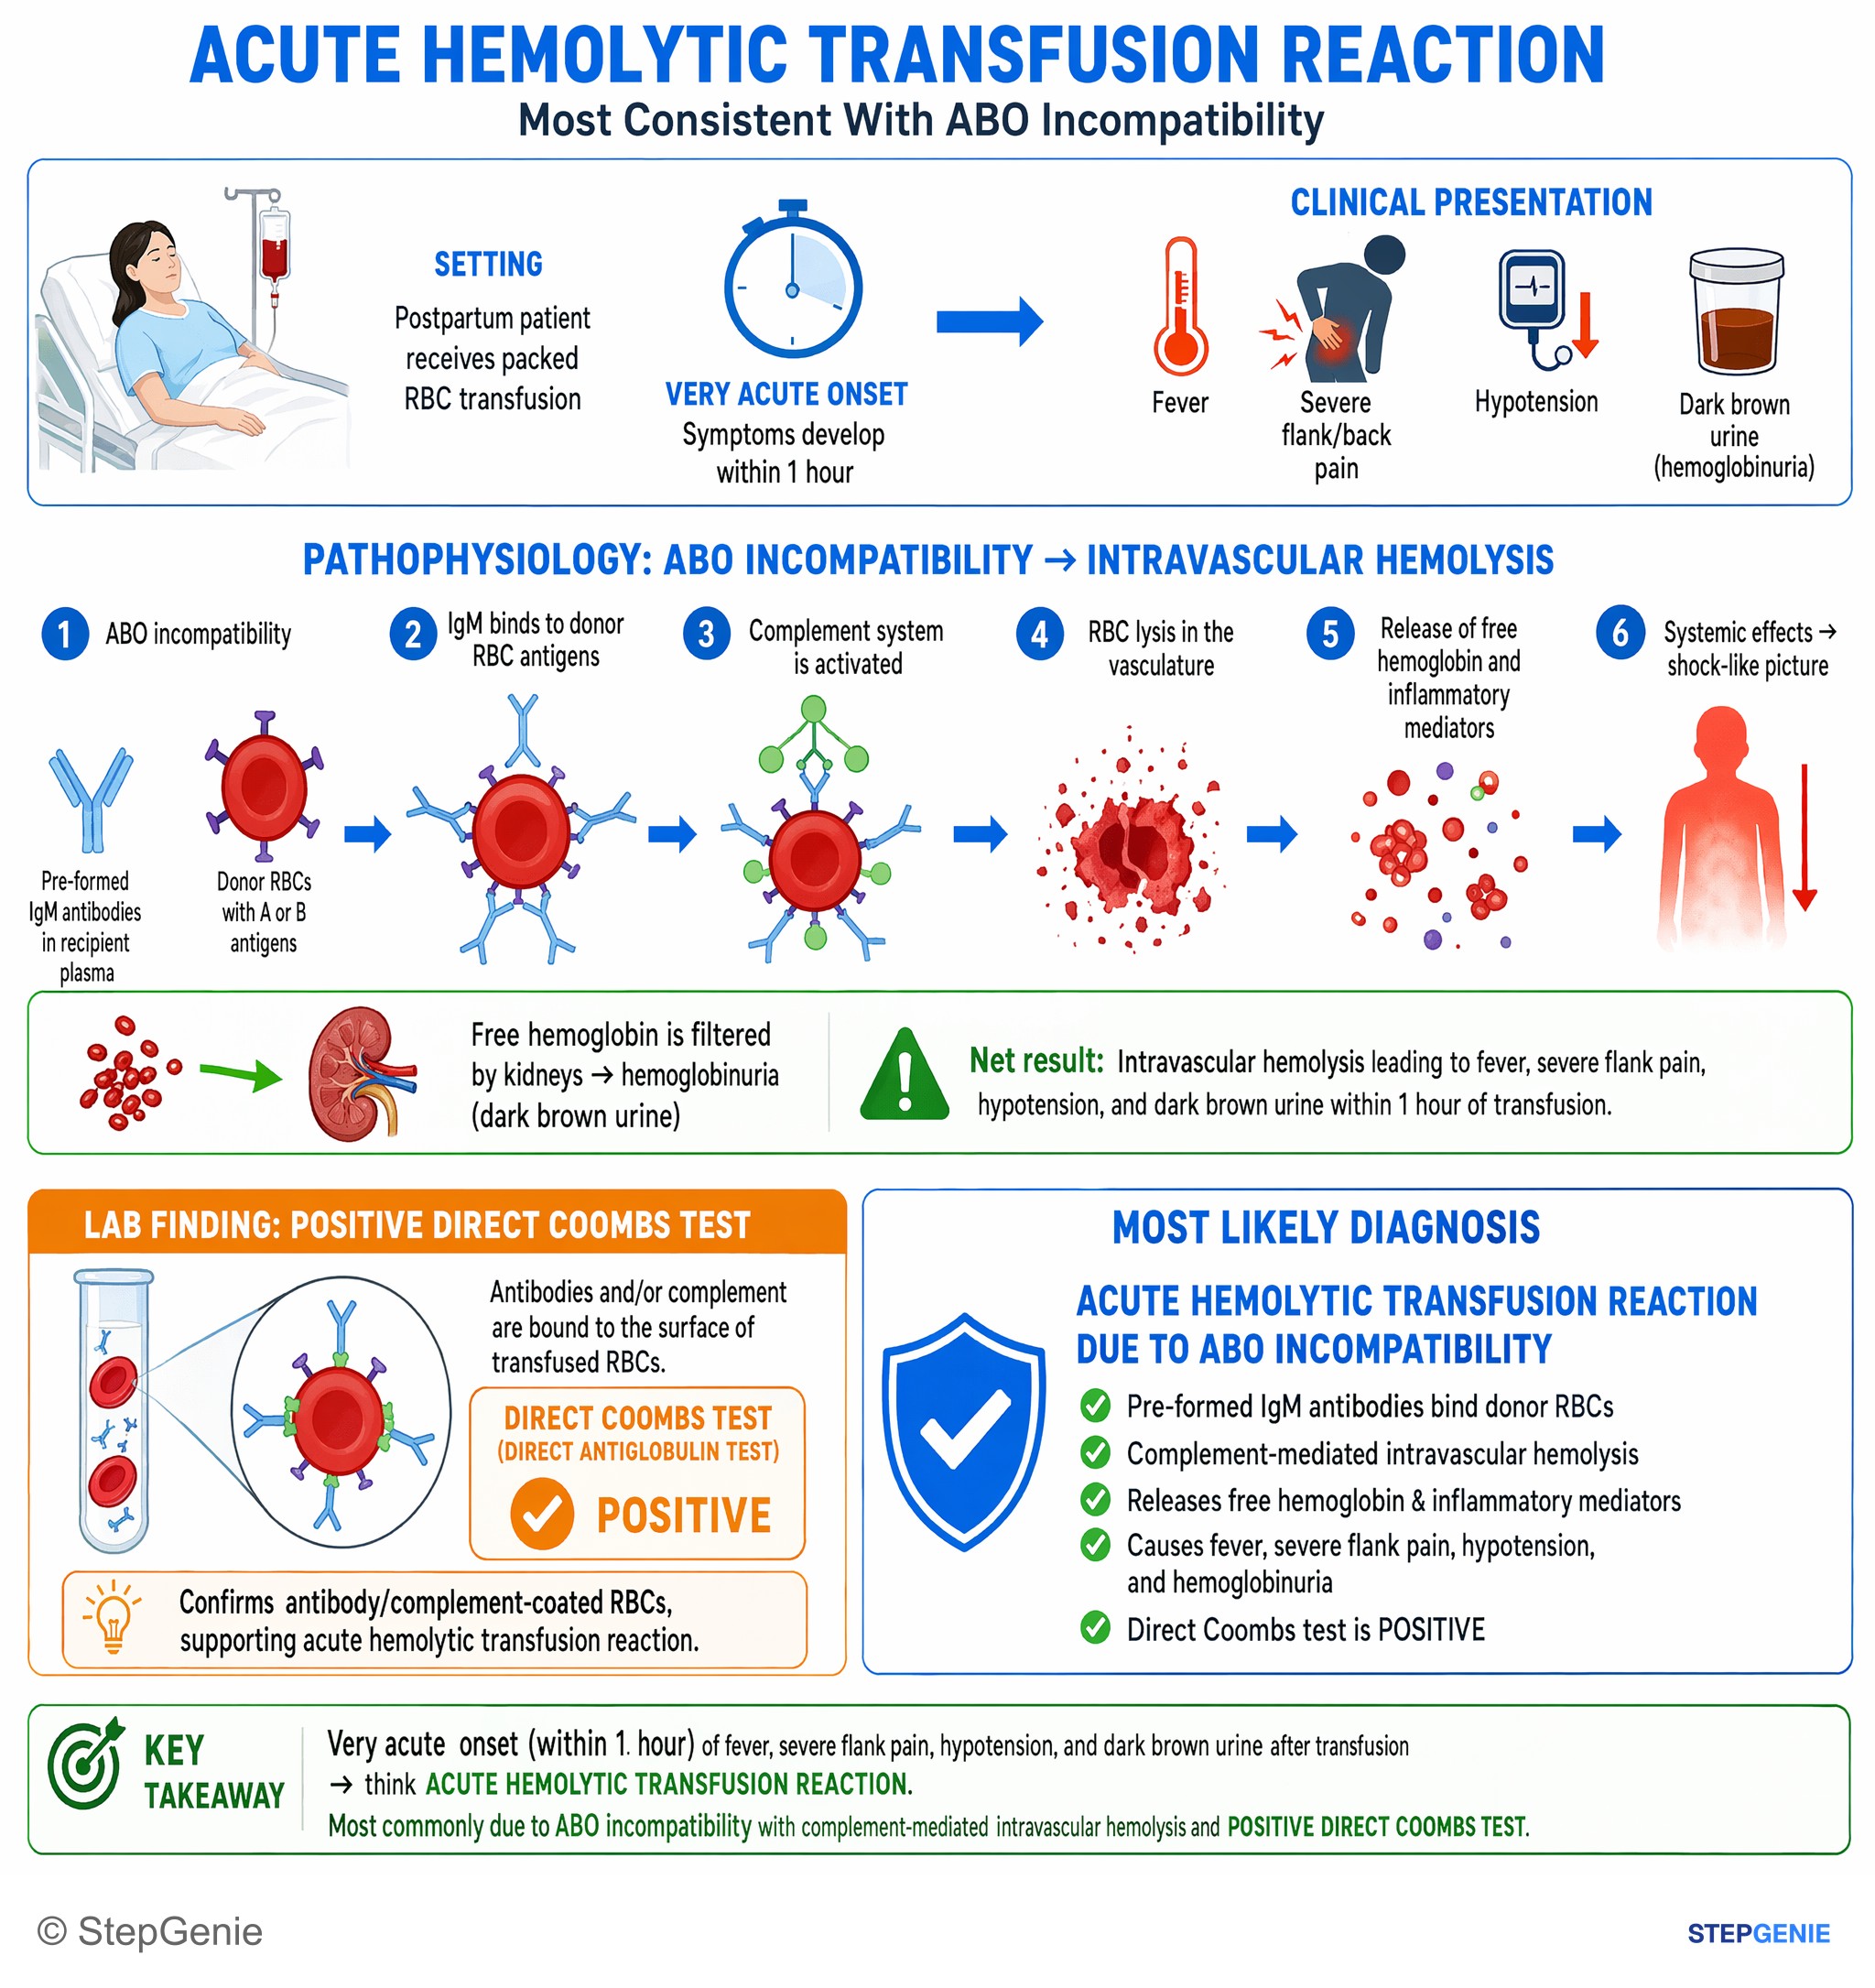
Acute hemolytic transfusion reaction due to ABO incompatibility: complement-mediated intravascular hemolysis → fever, flank pain…
USMLE Step 1Frequently Asked Questions
How do you recognize Type II hypersensitivity on a question stem?
Type II hypersensitivity is recognized by IgG or IgM targeting fixed antigens on a cell surface or extracellular matrix. Once antibodies bind, the target is either destroyed by complement, opsonization, or ADCC, or its receptor function is altered. A fast exam approach is to ask whether the antigen is tethered to a cell or basement membrane and then decide whether the effect is destruction or dysfunction.
Why does IgG binding to red blood cells cause extravascular hemolysis and a positive Coombs test?
IgG binding to red blood cells causes extravascular hemolysis because the antibody opsonizes the RBCs and splenic or hepatic macrophages remove them. This produces the classic Type II pattern seen in autoimmune hemolytic anemia and related disorders. Clue words include anemia, jaundice, splenomegaly, spherocytes, and a positive direct Coombs test, all pointing to antibody-mediated RBC destruction.
Why is IgM especially associated with complement-mediated cell lysis in Type II hypersensitivity?
IgM is especially associated with complement-mediated lysis because it is the best activator of complement, although IgG can also activate it. In Type II reactions, complement can directly lyse cells through the MAC, promote inflammation through C3a and C5a, and increase opsonization through C3b. A classic clue is intravascular hemolysis when complement-mediated destruction is emphasized.
How do myasthenia gravis and Graves disease fit into Type II hypersensitivity?
Both are Type II hypersensitivity because antibodies bind fixed receptors and change their function rather than simply destroying cells. In myasthenia gravis, antibodies block acetylcholine receptors, decreasing neuromuscular transmission and causing ptosis, diplopia, and fatigability that improves with rest. In Graves disease, antibodies stimulate the TSH receptor, increasing thyroid hormone and producing findings like exophthalmos, pretibial myxedema, and diffuse goiter.
How do you tell Goodpasture syndrome from pemphigus vulgaris and bullous pemphigoid as Type II diseases?
You distinguish them by the structural target and the clinical clue. Goodpasture syndrome involves antibodies to type IV collagen in glomerular and alveolar basement membrane, causing hematuria and hemoptysis with linear immunofluorescence. Pemphigus vulgaris involves anti-desmoglein antibodies causing intraepidermal blistering with flaccid bullae and a positive Nikolsky sign. Bullous pemphigoid involves anti-hemidesmosomes, producing subepidermal blistering with tense bullae and typically negative Nikolsky sign.