Drug hypersensitivity is one of those Step 1 topics that feels “pharm-ish,” “immunology-ish,” and “clinical-ish” all at once—which is exactly why it shows up in vignettes. The key is to stop thinking of it as a random list of allergic reactions and start classifying reactions by hypersensitivity type (I–IV), timing, and classic drug triggers. Once you do that, the patterns become very predictable (and very testable).
What is “Drug Hypersensitivity”?
Drug hypersensitivity = an immune-mediated adverse drug reaction (ADR).
This is different from:
- Side effects (predictable, dose-related; e.g., ACE inhibitor cough)
- Toxicity (excess dose; e.g., acetaminophen overdose)
- Idiosyncratic/non-immune reactions (unpredictable; e.g., malignant hyperthermia)
Why it matters for USMLE
Most hypersensitivity reactions map to the four Gell and Coombs types and frequently appear as:
- Rash + fever + eosinophilia
- Anaphylaxis after a drug
- Hemolytic anemia after antibiotics
- Stevens-Johnson/TEN after anticonvulsants
- Serum sickness-like reactions
First Aid cross-reference: Immunology → Hypersensitivity reactions (Types I–IV); Pharm sections for penicillins/cephalosporins, sulfonamides, anticonvulsants.
Pathophysiology: How Drugs Trigger Hypersensitivity
Most drugs are too small to be antigens. They act as:
- Haptens: bind to host proteins → new antigenic complex (classic: penicillin).
- Pro-haptens: metabolized into reactive intermediates (classic: sulfonamides, some anticonvulsants).
- Direct immune activation (non-hapten mechanisms): some drugs can activate T cells without classic hapten formation (conceptual, not usually tested deeply).
The immune response then follows one of the Type I–IV pathways.
The High-Yield Framework: Types I–IV Drug Hypersensitivity
Quick Table: Hypersensitivity Types with Drug Examples
| Type | Immune mechanism | Timing (classic) | Hallmark findings | High-yield drug examples |
|---|---|---|---|---|
| I | IgE-mediated, mast cells, histamine | Minutes–hours | Urticaria, angioedema, anaphylaxis, bronchospasm | Penicillin, cephalosporins; latex; some biologics |
| II | IgG/IgM vs cell-surface antigens → complement/ADCC | Hours–days | Hemolytic anemia, thrombocytopenia | Penicillin (hapten on RBC), cephalosporins, methyldopa |
| III | Immune complexes (IgG) deposit → complement | 1–2 weeks (or sooner with re-exposure) | Serum sickness: fever, urticaria, arthralgias, nephritis | Penicillin, cefaclor, some antivenoms/biologics |
| IV | T-cell mediated (delayed) | 48–72 hours to weeks | Contact dermatitis, morbilliform rash; severe: SJS/TEN, DRESS | Sulfonamides, anticonvulsants, allopurinol, penicillins (rash) |
First Aid cross-reference: Hypersensitivity table; dermatologic drug reactions often show up in Micro/Pharm mixed vignettes.
Type I (Immediate) Drug Hypersensitivity: The “Anaphylaxis” Bucket
Definition / Path
- Prior sensitization → drug-specific IgE bound to mast cells.
- Re-exposure → cross-linking → mast cell degranulation (histamine, tryptase, leukotrienes).
Clinical presentation (vignette clues)
- Rapid onset: minutes after exposure
- Urticaria, pruritus, flushing
- Angioedema (lip/tongue swelling)
- Wheeze, stridor, hypotension, GI cramping
High-yield drug examples
- Penicillins (classic)
- Cephalosporins (cross-reactivity is lower than historically taught, but still testable conceptually)
- Some perioperative drugs (varies), biologics
Diagnosis
- Clinical diagnosis for acute anaphylaxis.
- Serum tryptase can support anaphylaxis (peaks about 1–2 hours after onset).
- Allergy evaluation later: skin testing for some beta-lactams in select settings.
Treatment (Step-ready)
- IM epinephrine first-line
- Airway + oxygen + IV fluids
- Adjuncts: H1/H2 blockers ± steroids (secondary treatment only, not acute rescue). They do not reliably prevent biphasic anaphylaxis (the 2020 AAAAI/ACAAI practice parameter suggests against using them for that), and epinephrine is first-line for a biphasic reaction too.
USMLE pitfall: Don’t confuse ACE inhibitor angioedema with IgE-mediated allergy; ACEi angioedema is bradykinin-mediated (not urticaria, not IgE).
Type II (Cytotoxic) Drug Hypersensitivity: “Drug-Induced Autoimmune Blood Problems”
Definition / Path
IgG/IgM targets cells → complement activation or opsonization.
Mechanisms you should recognize:
- Hapten-mediated: drug binds RBC → antibodies target RBC-drug complex (e.g., penicillin).
- Autoantibody induction: drug triggers antibody vs self antigen (e.g., methyldopa → anti-RBC).
Clinical presentation
- Hemolytic anemia
- Fatigue, jaundice, dark urine
- ↑ LDH, ↑ indirect bilirubin, ↓ haptoglobin
- Positive direct Coombs test
- Thrombocytopenia (bleeding, petechiae) in some drug contexts
High-yield drug examples
- Penicillin → hemolytic anemia (hapten-type)
- Cephalosporins → hemolysis (less common but classic association)
- Methyldopa → autoimmune hemolytic anemia
Diagnosis
- CBC + hemolysis labs
- Direct antiglobulin (Coombs) test positive
Treatment
- Stop offending drug
- Supportive care; steroids if significant autoimmune hemolysis (clinical management concept)
First Aid cross-reference: Hemolytic anemia and hypersensitivity Type II.
Type III (Immune Complex) Drug Hypersensitivity: “Serum Sickness” Pattern Recognition
Definition / Path
Drug-antibody immune complexes form → deposit in tissues → complement activation → inflammation.
Classic presentation: Serum sickness (often 1–2 weeks after exposure)
Triad-style constellation:
- Fever
- Urticarial or morbilliform rash
- Arthralgias Plus possible:
- Lymphadenopathy
- Proteinuria/hematuria (glomerulonephritis)
High-yield drug examples
- Penicillin (again—it’s everywhere because it can act as a hapten and trigger multiple hypersensitivity types)
- Cefaclor (classic serum sickness-like reaction association)
- Antiserum/antivenom, some monoclonal antibodies (concept)
Diagnosis
- Mainly clinical + timing
- ↓ complement levels can occur (immune complex consumption)
Treatment
- Stop the drug
- Antihistamines/NSAIDs for mild cases
- Steroids for more severe symptoms
USMLE pitfall: Serum sickness is immune complex (Type III) and classically delayed; anaphylaxis is IgE (Type I) and immediate.
Type IV (Delayed, T-cell Mediated): From Contact Dermatitis to SJS/TEN
Type IV reactions are the most “derm-heavy” drug hypersensitivity reactions and very high yield.
Subtypes (helpful mental organization)
- IVa (Th1/macrophage): contact dermatitis (e.g., poison ivy—concept)
- IVc (cytotoxic T cells): SJS/TEN
- Mixed patterns: DRESS
You don’t need to memorize subtype letters for USMLE, but recognizing the clinical syndromes is crucial.
1) Simple Morbilliform (Maculopapular) Drug Eruption
Most common drug rash.
- Onset: usually days to 2 weeks after starting drug
- Diffuse erythematous maculopapular rash, often pruritic
- Usually no mucosal involvement, no skin sloughing
Common triggers
- Penicillins (notably with EBV infection → ampicillin rash)
- Sulfonamides
- Many others (broad category)
Treatment
- Stop drug if concerning/severe; supportive care
Step pearl: Ampicillin/amoxicillin rash with EBV is a classic vignette—rash after “strep treatment” but patient actually has mono.
2) Allergic Contact Dermatitis (Type IV classic)
- Localized pruritic, eczematous rash where exposure occurred
- Not the most common “drug” vignette, but topical agents can do it
3) SJS/TEN (Severe, Life-Threatening)
Think: painful rash + mucosal involvement + skin detachment.
- Stevens-Johnson syndrome (SJS): <10% BSA detachment
- Toxic epidermal necrolysis (TEN): >30% BSA detachment
(Overlap exists between 10–30%.)
Clinical clues
- Prodrome: fever, malaise
- Painful erythematous or dusky lesions → bullae
- Mucosal erosions (mouth, eyes, genitals)
- Positive Nikolsky sign (skin sloughing with pressure)
High-yield drug triggers
- Sulfonamides (big one)
- Anticonvulsants (especially aromatic): carbamazepine, phenytoin, lamotrigine
- Allopurinol
- NSAIDs (classically some oxicams—varies)
Management
- Stop drug immediately
- Supportive care (burn unit-style), fluids, wound care, infection prevention
- Consult derm/ICU/burn team
First Aid cross-reference: Dermatologic adverse drug reactions; immunology Type IV.
4) DRESS (Drug Reaction with Eosinophilia and Systemic Symptoms)
This one is a favorite because it screams “systemic immune activation.”
Timing: typically 2–8 weeks after starting the drug (later than a simple rash)
Clinical features
- Fever
- Diffuse rash (often facial edema)
- Eosinophilia
- Systemic organ involvement: hepatitis (common), nephritis, pneumonitis, myocarditis, lymphadenopathy
High-yield triggers
- Anticonvulsants (carbamazepine, phenytoin, lamotrigine)
- Allopurinol
- Sulfonamides
- Some antibiotics (varies)
Treatment
- Stop drug
- Systemic corticosteroids if significant organ involvement
Step pearl: If you see rash + eosinophilia + hepatitis weeks after a new drug → think DRESS.
How to Diagnose Drug Hypersensitivity on Exams (and in real life)
The USMLE approach = pattern recognition + timing
Ask:
- How fast did symptoms start?
- Which organ systems are involved?
- Is it mucosal + skin sloughing?
- Is there eosinophilia? hemolysis? arthralgia?
Useful tests (when relevant)
- CBC with differential (eosinophilia in DRESS; cytopenias)
- LFTs/creatinine (organ involvement)
- Direct Coombs (Type II hemolysis)
- Complement levels (sometimes in Type III)
- Skin biopsy (SJS/TEN confirmation; not typically required for Step, but relevant clinically)
USMLE pitfall: Not every “rash on antibiotics” is IgE allergy. Many are Type IV morbilliform rashes, especially with viral infections.
Treatment Principles You Should Memorize
Universal first step
- Stop the offending drug.
Supportive vs emergent therapy
- Type I anaphylaxis: IM epinephrine (+ airway/fluids)
- Mild rashes: antihistamines, topical steroids, observation
- Severe cutaneous adverse reactions (SCARs) like SJS/TEN: emergent supportive/burn care
- DRESS: stop drug + systemic steroids if organ involvement
- Type II hemolysis: stop drug; supportive ± steroids depending on severity
Desensitization (concept)
- Considered when a drug is essential (e.g., certain infections requiring beta-lactams) and reaction is compatible with desensitization protocols—not for SJS/TEN.
High-Yield Drug Hypersensitivity Examples (Rapid Review)
Beta-lactams (penicillins/cephalosporins)
- Type I: anaphylaxis, urticaria
- Type II: hemolytic anemia (Coombs+)
- Type III: serum sickness
- Type IV: morbilliform rash
Step take-home: Penicillin can be associated with multiple hypersensitivity types.
Sulfonamides
- SJS/TEN
- DRESS
- Morbilliform rash
Step take-home: If sulfa + mucosal lesions/skin pain → worry about SJS/TEN.
Anticonvulsants (carbamazepine, phenytoin, lamotrigine)
- SJS/TEN
- DRESS
Step take-home: “Aromatic anticonvulsants” are classic for severe delayed reactions.
Allopurinol
- SJS/TEN
- DRESS
Step take-home: Rash + eosinophilia + hepatitis after allopurinol = DRESS until proven otherwise.
Methyldopa
- Type II autoimmune hemolytic anemia (Coombs+)
Step take-home: If an antihypertensive causes hemolysis, think methyldopa.
Vignette-Style Mini Cases (How It’s Tested)
- Minutes after IV antibiotics: wheezing, hypotension, urticaria → Type I → IM epi
- 1 week after penicillin: fever + arthralgia + urticarial rash + low complement → Type III serum sickness
- New drug + fatigue/jaundice + Coombs+ → Type II hemolytic anemia
- 2–6 weeks after carbamazepine: rash + eosinophilia + hepatitis → DRESS
- After sulfonamide: fever + painful rash + mucosal erosions + skin sloughing → SJS/TEN
Where This Lives in First Aid (Quick Map)
While page numbers vary by edition, look under:
- Immunology: Hypersensitivity reactions (Types I–IV)
- Pharm: Beta-lactams (allergy/hemolysis associations)
- Pharm/Derm: Severe cutaneous adverse reactions (SJS/TEN, DRESS)
- Heme: Coombs test / hemolytic anemias
Ultra–High-Yield Checklist (Memorize These Anchors)
- Anaphylaxis = Type I = IgE = immediate = IM epinephrine
- Drug-induced hemolytic anemia = Type II = Coombs+
- Serum sickness = Type III = fever + urticaria + arthralgias + (↓ complement)
- SJS/TEN = Type IV = mucosal involvement + skin detachment (sulfa, anticonvulsants, allopurinol)
- DRESS = delayed weeks + eosinophilia + organ involvement (anticonvulsants, allopurinol, sulfa)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
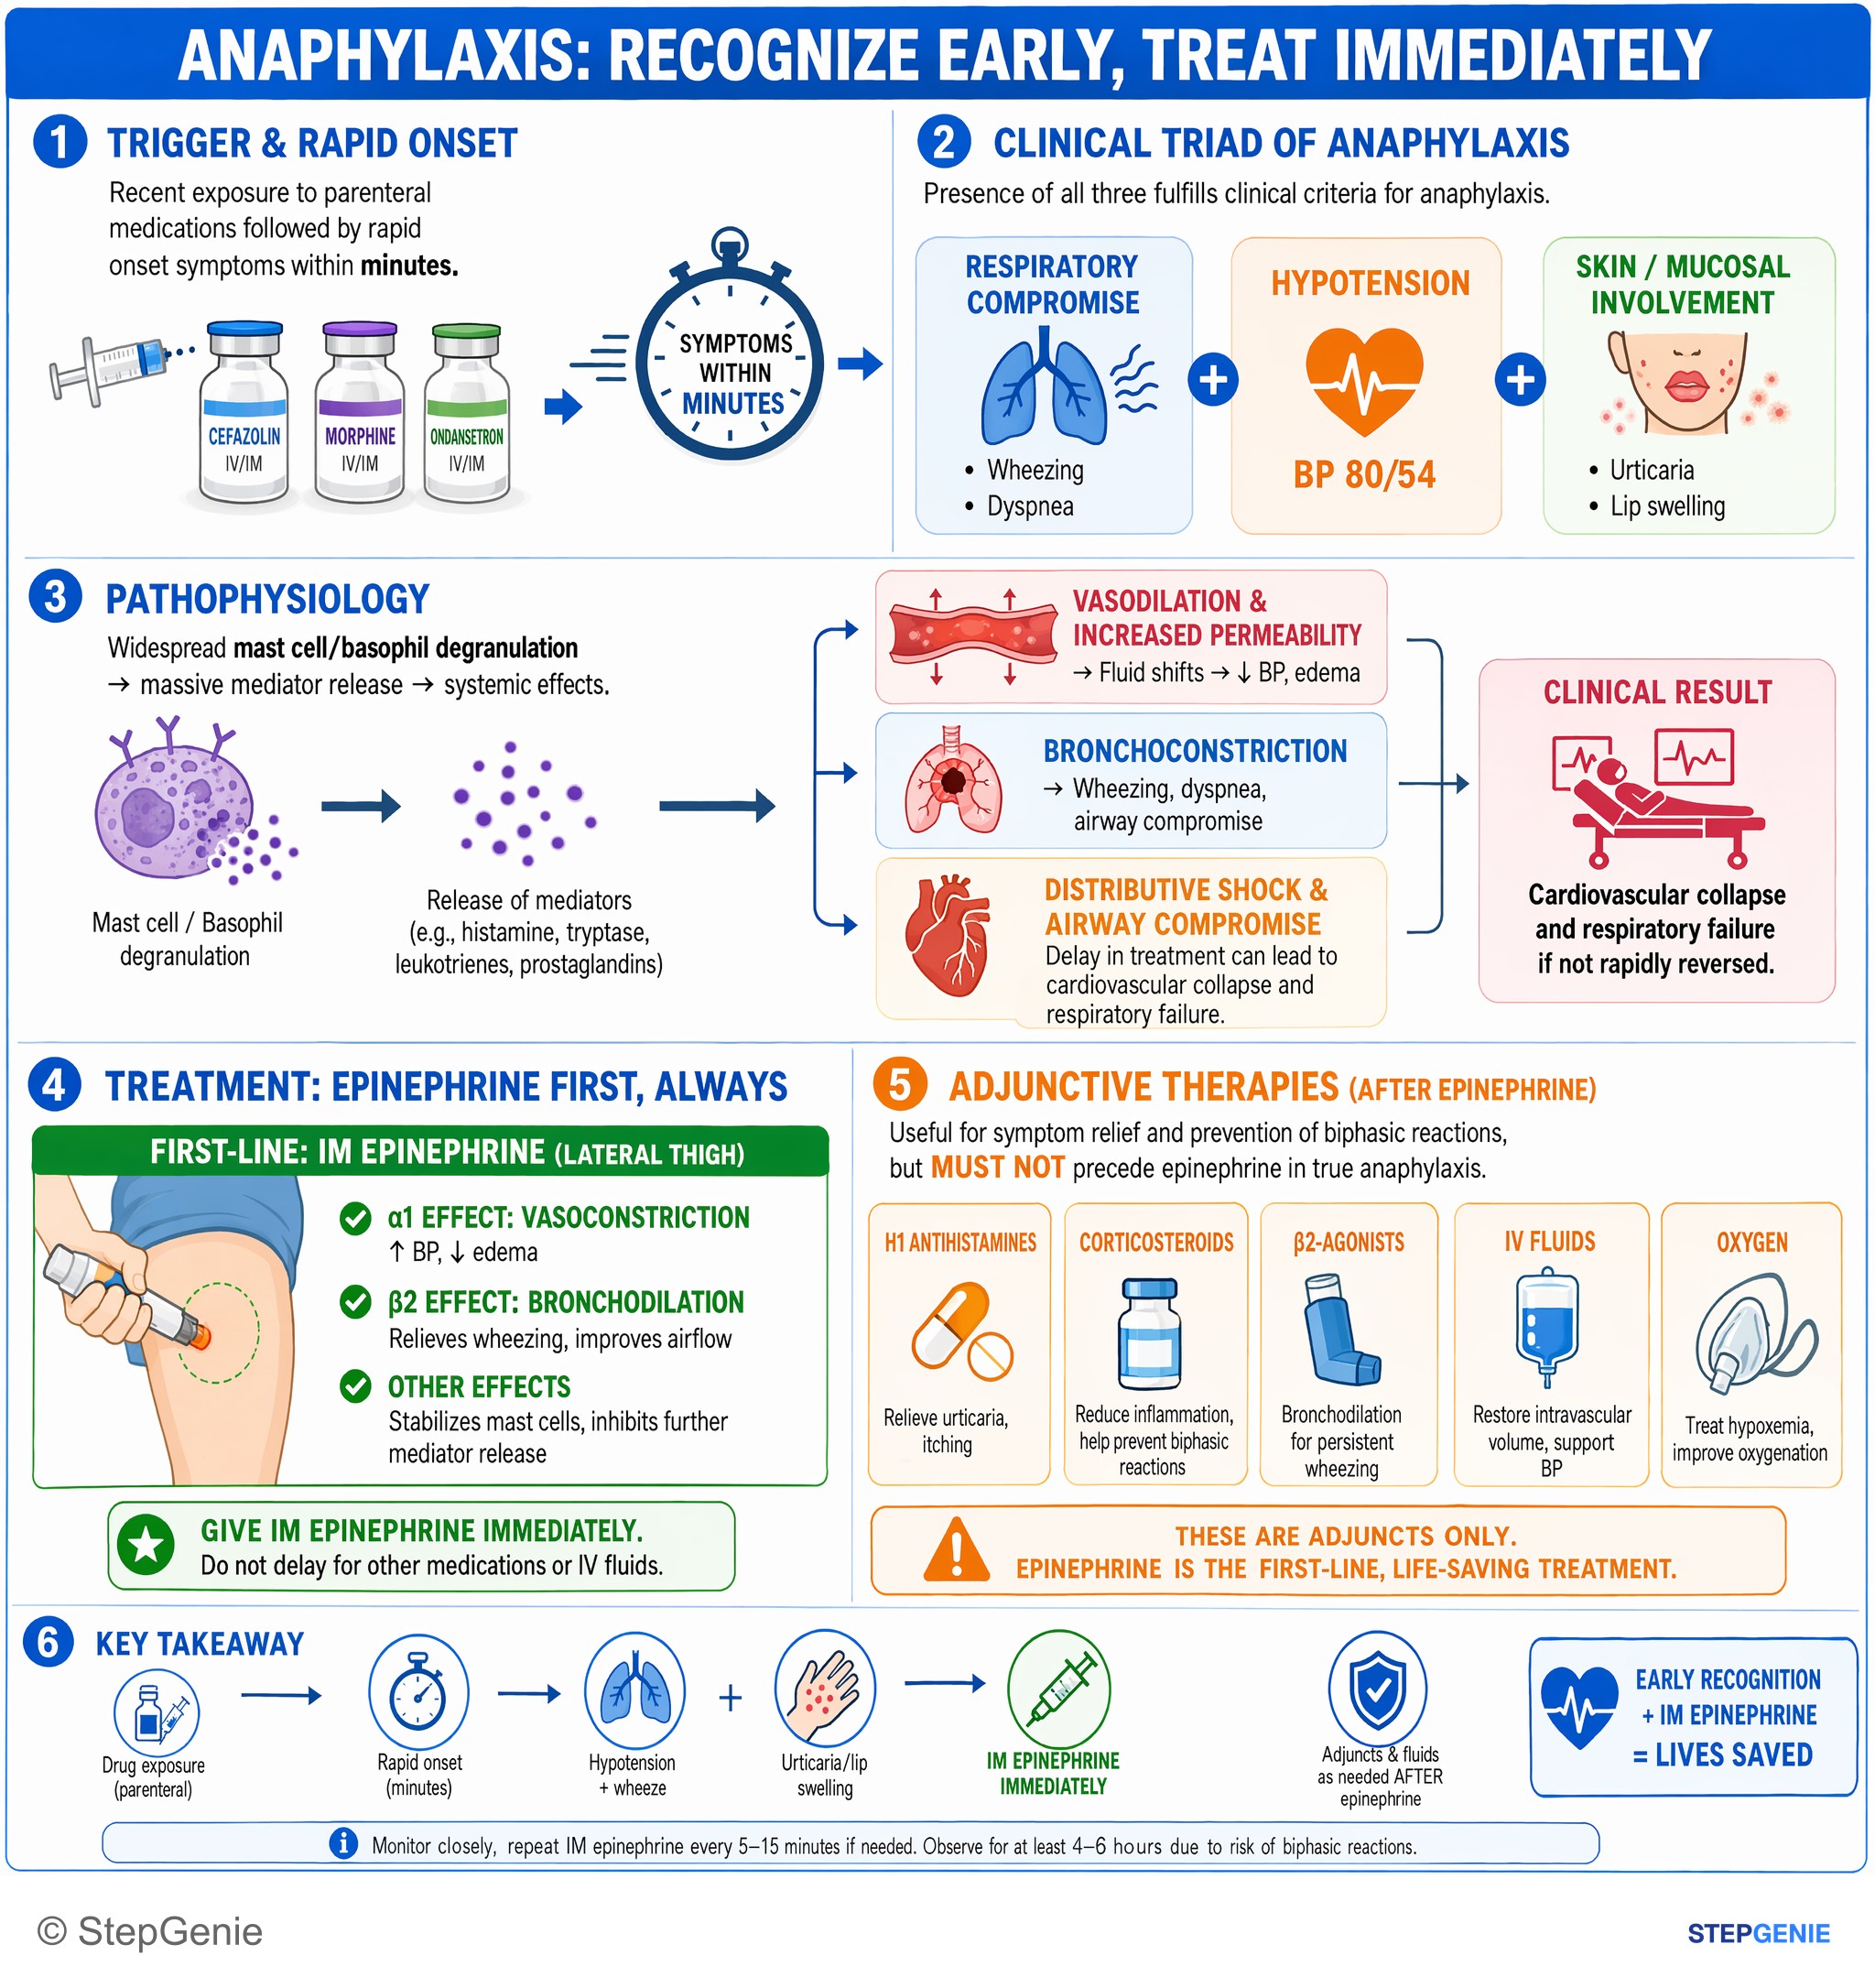
Anaphylaxis (hypotension, wheeze, urticaria after drug exposure) requires immediate IM epinephrine as first-line treatment, before…
USMLE Step 2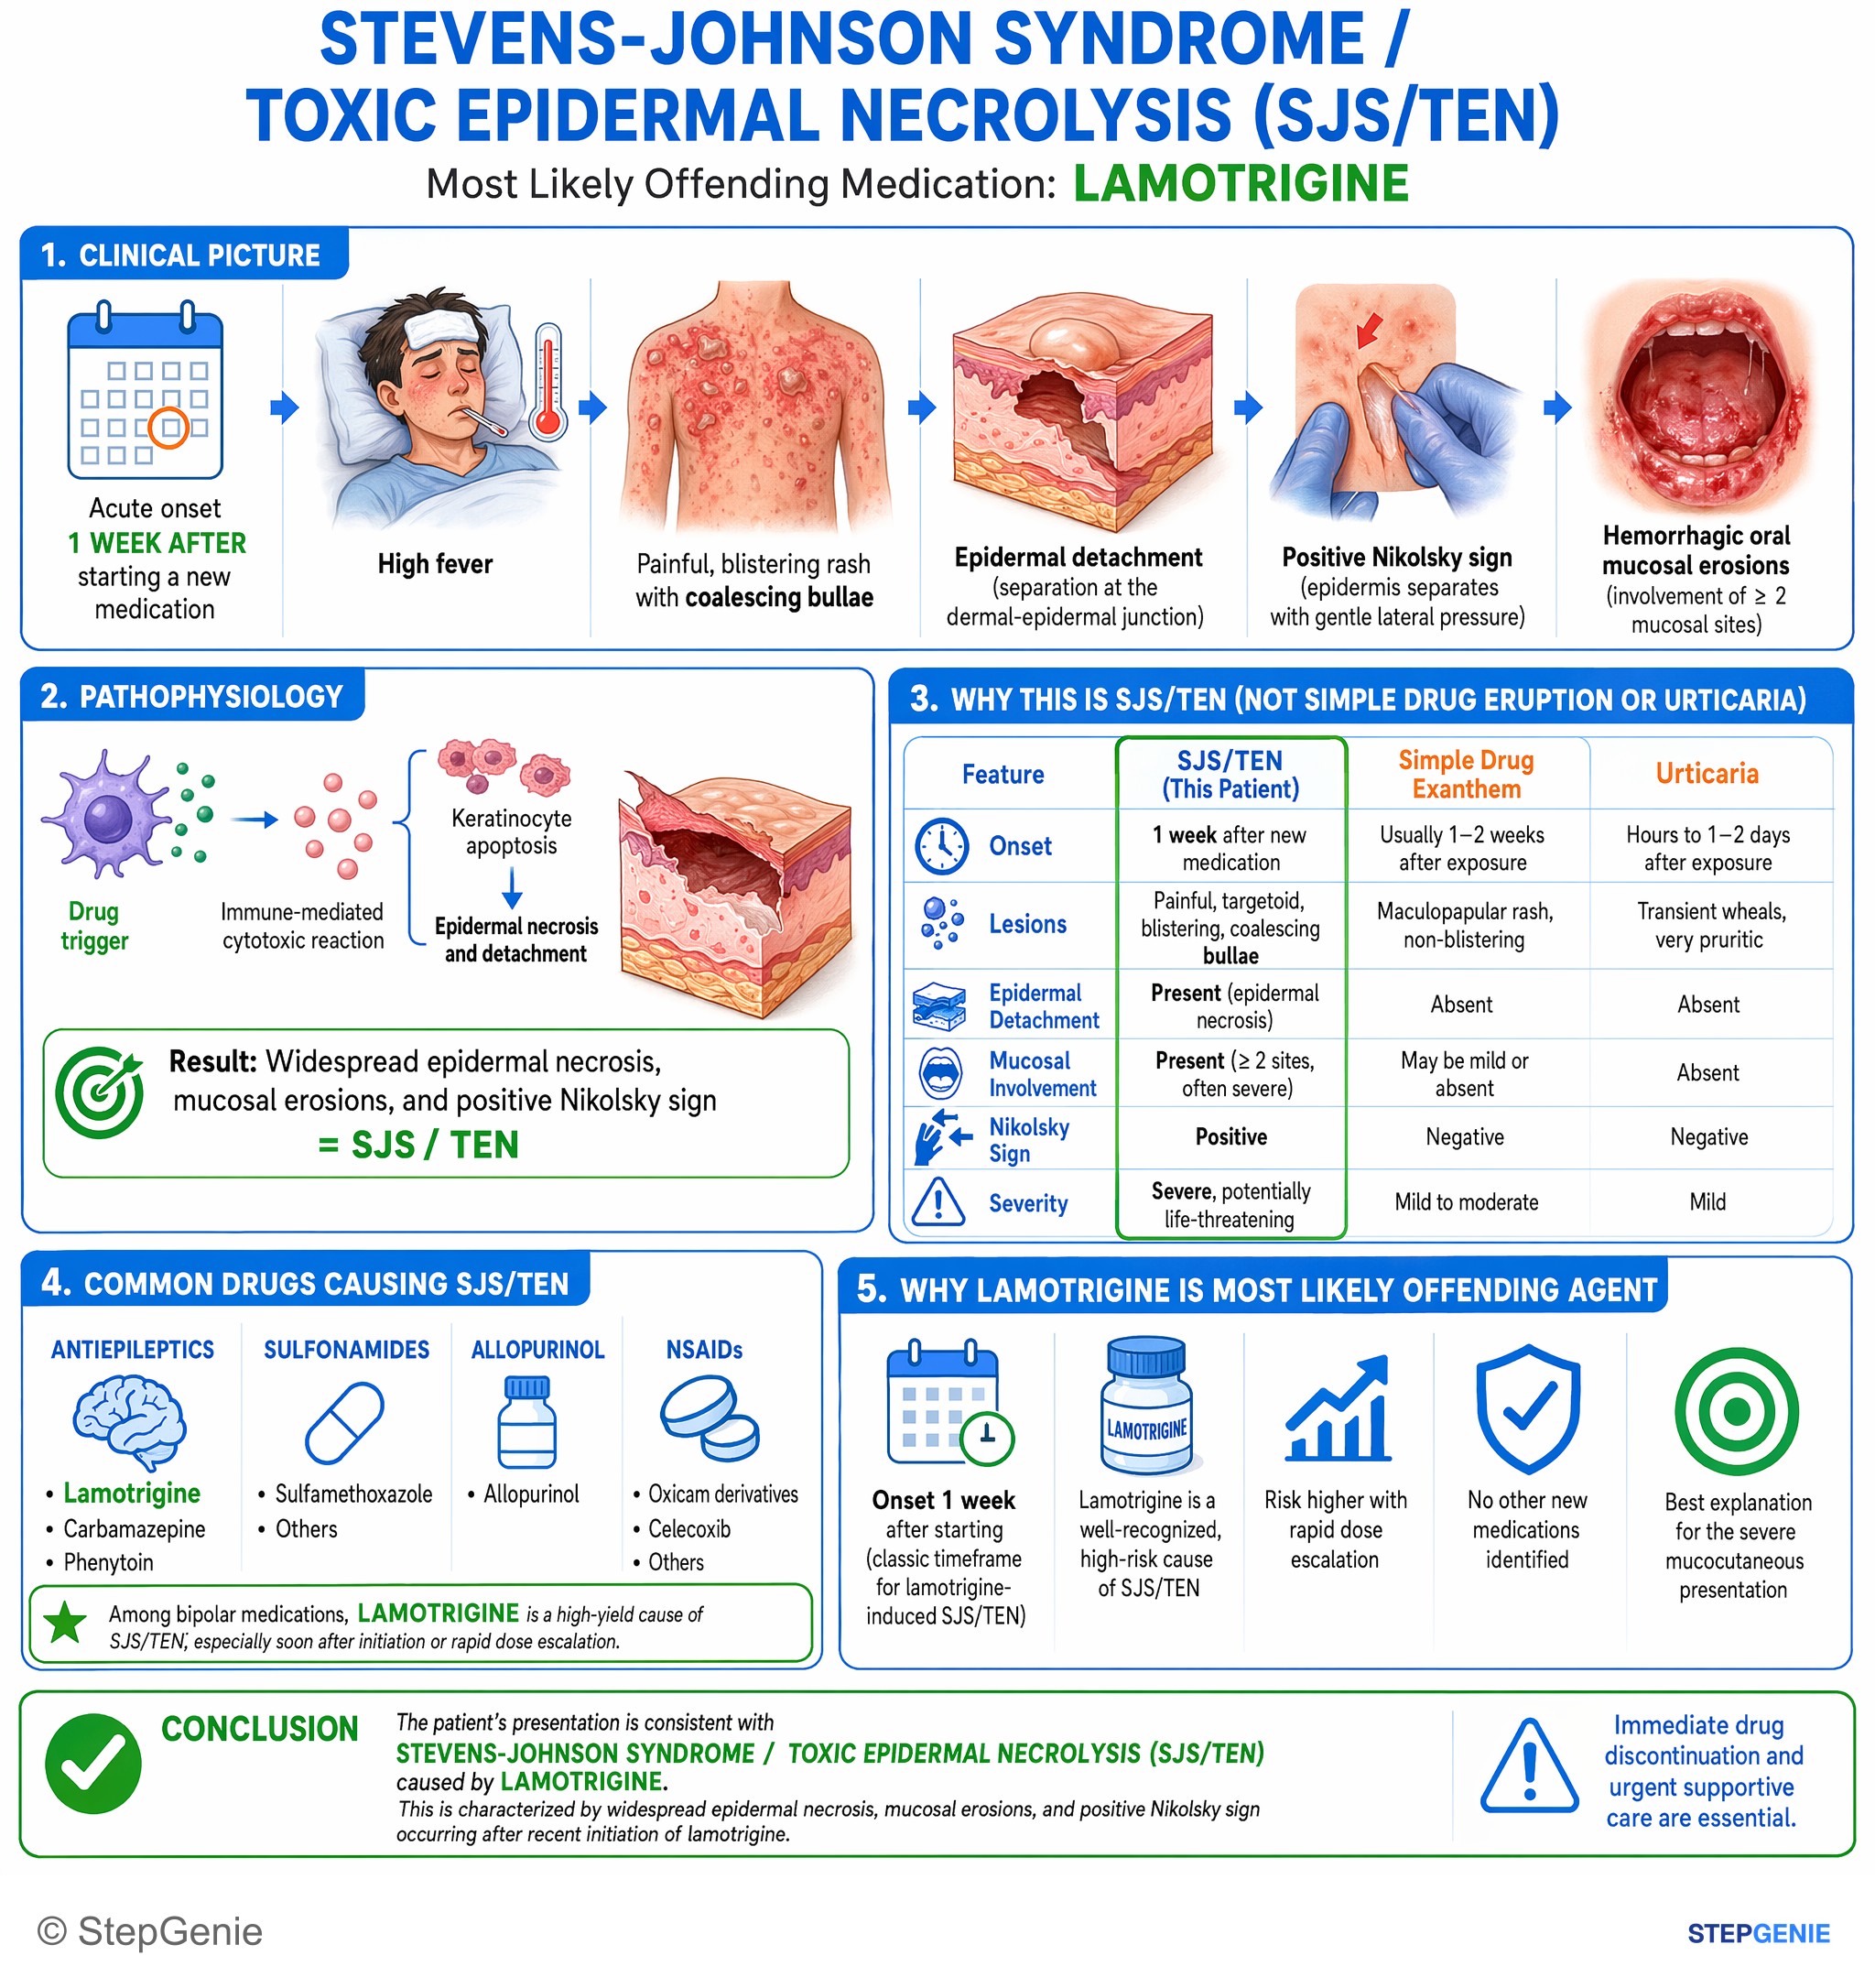
Stevens-Johnson syndrome/toxic epidermal necrolysis from lamotrigine: widespread epidermal necrosis, mucosal erosions, positive Nikolsky…
USMLE Step 1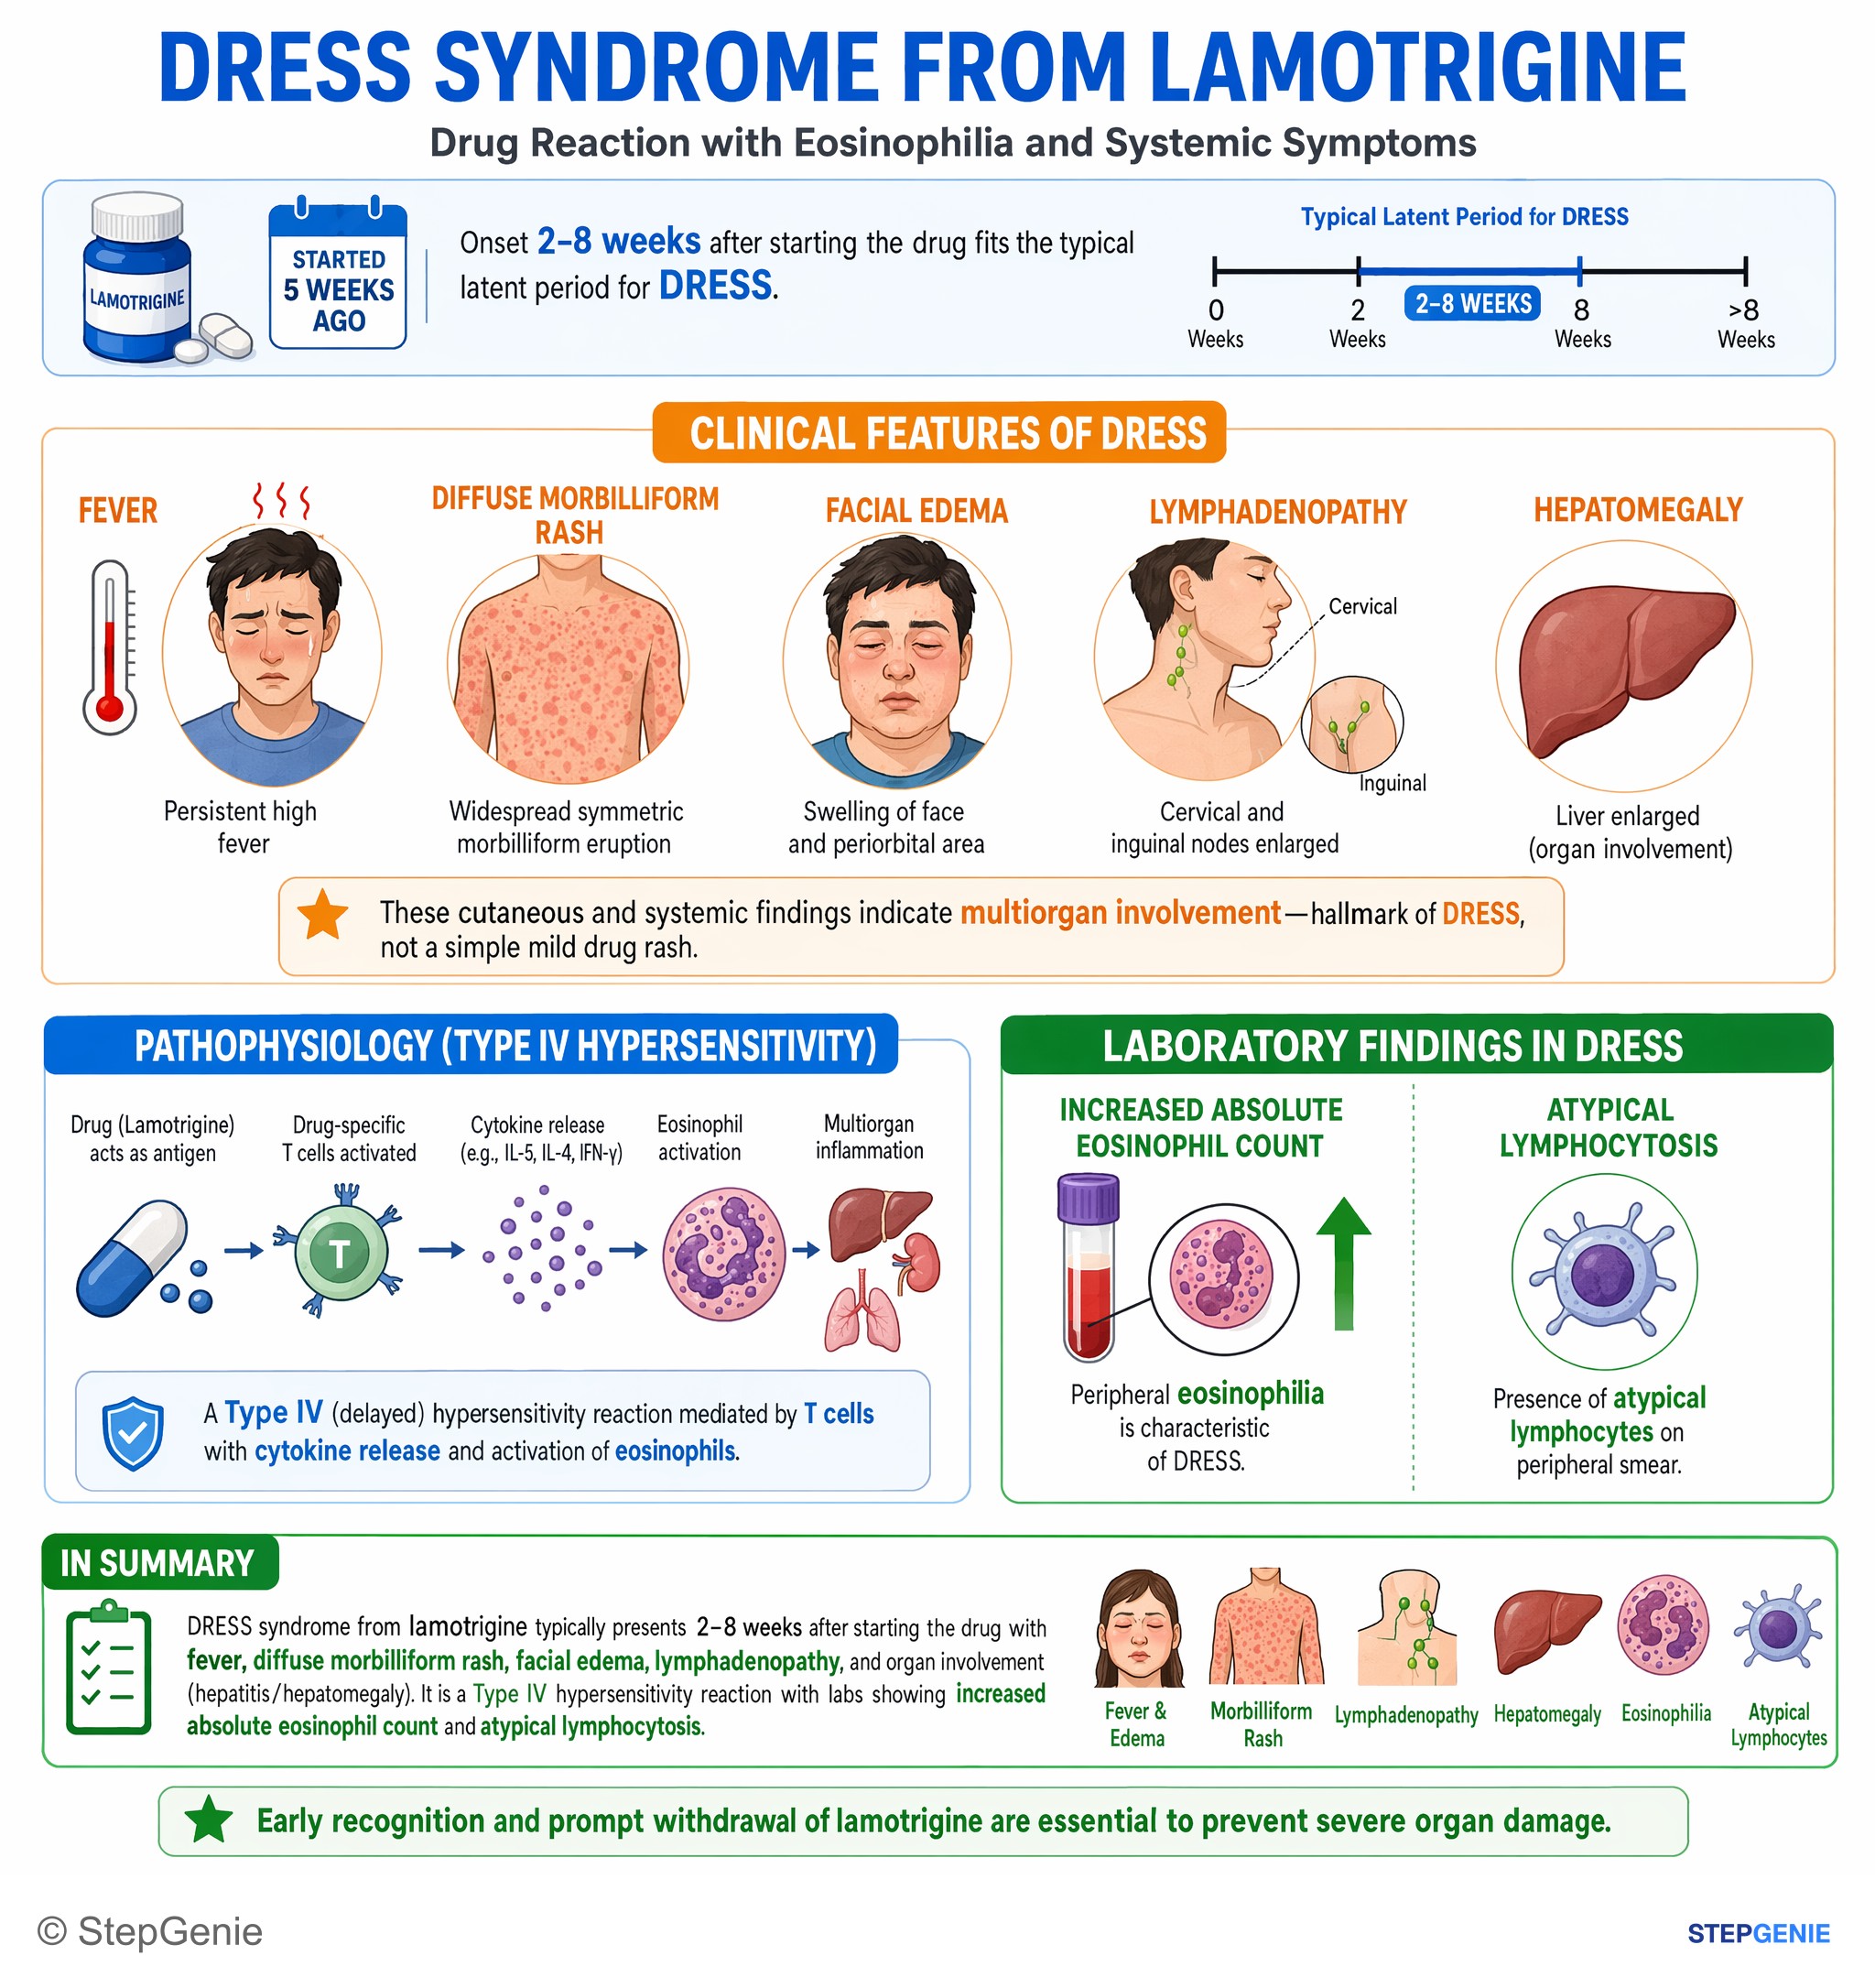
DRESS syndrome from lamotrigine: fever, morbilliform rash, facial edema, lymphadenopathy, organ involvement (hepatitis) → labs show…
USMLE Step 1Frequently Asked Questions
How do you classify drug hypersensitivity reactions for Step 1?
The most useful way to classify drug hypersensitivity is by hypersensitivity type I through IV, timing, and classic drug triggers. Drug hypersensitivity is an immune-mediated adverse drug reaction, unlike side effects, toxicity, or idiosyncratic non-immune reactions. This framework makes common vignette patterns easier to recognize, such as anaphylaxis, hemolytic anemia, serum sickness, and severe delayed skin eruptions.
Why can penicillin cause so many different hypersensitivity reactions?
Penicillin can cause multiple hypersensitivity reactions because it acts as a hapten by binding host proteins and creating a new antigenic complex. That immune trigger can then lead to different pathways, including Type I IgE-mediated anaphylaxis, Type II hemolytic anemia when antibodies target red blood cell-associated drug complexes, and Type III serum sickness through immune complex formation.
How do you recognize a Type I drug hypersensitivity reaction in a vignette?
A Type I drug hypersensitivity reaction is recognized by rapid onset, usually within minutes after exposure, with IgE-mediated mast cell degranulation. Typical clues include urticaria, pruritus, flushing, angioedema, wheezing, stridor, hypotension, and gastrointestinal cramping. Penicillins are the classic trigger, and the presentation points to immediate anaphylaxis rather than a delayed rash.
What is the first-line treatment for drug-induced anaphylaxis?
IM epinephrine is the first-line treatment for drug-induced anaphylaxis. Immediate management also includes airway support, oxygen, and IV fluids, because the reaction can cause bronchospasm, angioedema, and hypotension within minutes. H1 and H2 blockers and steroids may be used as adjuncts, but they are not the acute rescue treatment.
How do you tell Type II drug hypersensitivity from Type III serum sickness?
Type II drug hypersensitivity usually causes cytotoxic blood problems, while Type III causes immune complex disease with a serum sickness pattern. Type II presents with hemolytic anemia or thrombocytopenia, often with fatigue, jaundice, dark urine, hemolysis labs, and a positive direct Coombs test. Type III typically appears 1 to 2 weeks after exposure with fever, urticarial or morbilliform rash, arthralgias, and sometimes nephritis.