A naive T cell needs two signals to activate and a third that decides what it becomes. Signal 1 is the T-cell receptor recognizing a peptide presented on MHC (CD4 T cells with MHC class II, CD8 T cells with MHC class I). Signal 2 is costimulation, B7 (CD80 or CD86) on the antigen-presenting cell binding CD28 on the T cell; Signal 1 without Signal 2 produces anergy. Signal 3 is the cytokine environment (IL-12 → Th1, IL-4 → Th2, TGF-β + IL-6 → Th17, TGF-β + IL-2 → Treg), while CTLA-4 and PD-1 are the brakes that checkpoint inhibitors release.
The mnemonic: key, gas, steering and brakes
Picture starting a car. The key picks which car moves (specificity), the gas makes it go (costimulation), the steering wheel sets the direction (cytokines), and the brakes stop it (inhibitory checkpoints).
| Part | Car analogy | Molecules | If it is missing or blocked | Drug or disease hook |
|---|---|---|---|---|
| Signal 1 | Key | TCR with CD3 binds peptide–MHC; CD4 binds MHC II, CD8 binds MHC I | No antigen-specific response | Superantigens bypass the normal peptide groove (toxic shock) |
| Signal 2 | Gas | B7-1 (CD80) or B7-2 (CD86) on the APC binds CD28 on the T cell | Signal 1 alone → anergy | Abatacept and belatacept block B7 |
| Signal 3 | Steering | IL-12, IL-4, TGF-β + IL-6, TGF-β + IL-2 | The T cell follows whichever program the cytokines favor | Th2 in asthma and allergy; Th17 in autoimmunity |
| Brakes | Brakes | CTLA-4 (outcompetes CD28 for B7); PD-1 (binds PD-L1 and PD-L2) | Unchecked activation, autoimmunity | Ipilimumab (anti-CTLA-4); nivolumab and pembrolizumab (anti-PD-1) |
Rule of 8 for Signal 1: MHC class × CD number = 8. MHC I pairs with CD8 (1 × 8) and MHC II pairs with CD4 (2 × 4).
Signal 1: recognition (the key)
- The T-cell receptor, with CD3, recognizes a peptide sitting in an MHC molecule; the CD4 or CD8 coreceptor binds the MHC itself.
- MHC class I (HLA-A, -B, -C) is expressed on most somatic cells and displays peptides from degraded cytosolic proteins to CD8 T cells. Its light chain is β2-microglobulin, encoded on chromosome 15.
- MHC class II (HLA-DR, -DQ, -DP) is expressed on antigen-presenting cells (B cells, dendritic cells, macrophages, plus activated T cells and thymic epithelium) and displays peptides from endocytosed proteins to CD4 T cells. The HLA complex sits on the short arm of chromosome 6.
- Naive T cells are activated mainly by dendritic cells in lymph nodes, the most potent stimulators of naive T cells. To draw out the two presentation pathways, see MHC I vs MHC II.
Signal 2: costimulation (the gas)
- CD28 is expressed on all naive T cells. Its ligands, CD80 (B7-1) and CD86 (B7-2), are upregulated when a dendritic cell is activated through pattern-recognition receptors such as Toll-like receptors, so costimulation works as a danger check.
- CD28–B7 signaling drives IL-2 production, proliferation, survival and differentiation.
- Signal 1 without Signal 2 → anergy, a state of nonresponsiveness to antigen. The balance of CD28–B7 versus CTLA-4–B7 binding decides between activation and anergy, which is one way the body keeps self-reactive T cells quiet (see immune tolerance).
- Drugs that cut the gas: abatacept is the extracellular domain of CTLA-4 fused to the Fc portion of IgG1. It binds CD80 and CD86 and blocks their interaction with CD28; it is used for rheumatoid arthritis. Belatacept is a modified version that binds CD80 and CD86 more avidly and prevents kidney transplant rejection; its boxed warning is post-transplant lymphoproliferative disorder, so it is used only in Epstein–Barr virus–seropositive recipients.
After activation: IL-2 and clonal expansion
- Activated T cells make IL-2, which drives T-cell proliferation (clonal expansion) and supports regulatory T-cell survival.
- Calcineurin inhibitors block this step. Tacrolimus (bound to FKBP-12) and cyclosporine inhibit calcineurin, preventing dephosphorylation and nuclear translocation of NFAT, so IL-2 synthesis and T-cell activation fall.
- Aldesleukin is recombinant IL-2, used for metastatic renal cell carcinoma and metastatic melanoma.
Signal 3: cytokines steer the helper T cell (the steering wheel)
| Subset | Induced by | Master transcription factor | Main cytokines made | Main job and disease link |
|---|---|---|---|---|
| Th1 | IL-12 (plus IFN-γ) | T-bet | IFN-γ, IL-2, lymphotoxin-α | Intracellular pathogens; activates macrophages; organ-specific autoimmunity |
| Th2 | IL-4 (plus IL-2) | GATA3 | IL-4, IL-5, IL-13 (also IL-9, IL-10) | Helminths; asthma and allergy; IL-4 drives IgE class switching, IL-5 activates eosinophils |
| Th17 | TGF-β + IL-6 (IL-21 and IL-23 reinforce it) | RORγt | IL-17A, IL-17F, IL-21, IL-22 | Extracellular bacteria and fungi; autoimmunity |
| Treg (induced) | TGF-β + IL-2 | FOXP3 | IL-10, TGF-β, IL-35 | Tolerance; suppress other T cells; constitutively express CTLA-4 |
| Tfh | IL-6, IL-21 | Bcl6 | IL-21 (also IL-4 and CD40L help) | Help B cells become antibody-secreting plasma cells in germinal centers |
Two patterns make this table easier. The master regulators cross-inhibit: T-bet suppresses the Th2 and Th17 programs. TGF-β is shared: add IL-6 and you get Th17; add IL-2 and you get Treg.
The brakes: CTLA-4 and PD-1
- CTLA-4 is a CD28 homolog on T cells that binds B7 with much higher affinity than CD28 but delivers no stimulatory signal, so it outcompetes CD28. It acts early, while naive T cells are being primed in lymph nodes, and regulatory T cells express it constantly.
- PD-1 binds PD-L1 and PD-L2 and inhibits T-cell proliferation and production of IFN-γ, TNF-α and IL-2. It acts later, mostly in peripheral tissues, and tumor cells can express PD-L1 to switch off T cells that recognize them.
- Checkpoint inhibitors release the brakes: ipilimumab blocks CTLA-4; nivolumab and pembrolizumab block PD-1. The price is immune-related adverse events; with ipilimumab the gut and skin are hit most often (diarrhea, colitis, pruritic rash), and hepatitis and endocrinopathies such as hypopituitarism, adrenal insufficiency and thyroid dysfunction also occur.
- Same axis, opposite effect: abatacept and belatacept imitate CTLA-4 and turn T cells down; ipilimumab blocks CTLA-4 and turns T cells up.
Superantigens: activation without specificity
Staphylococcal enterotoxins, toxic shock syndrome toxin-1 and streptococcal pyrogenic exotoxins bind MHC class II outside the peptide-binding groove and link it directly to particular TCR Vβ regions, with no antigen processing. They activate roughly 5–30% of T cells, compared with less than 0.01% for a conventional antigen. The resulting cytokine storm (TNF-α, IL-1, IL-2, IFN-γ) causes the fever, hypotension and shock of toxic shock syndrome.
B cells use the same two-signal logic
T-dependent B-cell responses also need a second, contact-dependent signal: CD40 ligand on activated helper T cells binds CD40 on the B cell. Mutations in CD40LG cause X-linked hyper-IgM syndrome, with normal or high IgM but low IgG and IgA because class switching fails, and infections with encapsulated bacteria, Pneumocystis and Cryptosporidium. The rest of the B-cell story is in B-cell activation and class switching.
Exam traps
- Signal 1 alone means anergy, not activation.
- Who carries what: B7 (CD80/CD86) sits on the APC; CD28, CTLA-4 and PD-1 sit on the T cell; PD-L1 can sit on tumor cells.
- CTLA-4 beats CD28 for B7 because its affinity is much higher.
- Abatacept vs ipilimumab: the same B7–CTLA-4 axis with opposite clinical effects.
- Rule of 8: MHC I with CD8, MHC II with CD4.
- Superantigens skip specificity by binding outside the peptide groove, which is why they activate so many T cells at once.
- TGF-β + IL-6 = Th17; TGF-β + IL-2 = Treg.
- Calcineurin inhibitors lower IL-2 production; aldesleukin is IL-2 itself.
- CD40L deficiency is a T-cell defect that looks like an antibody problem (hyper-IgM).
Worked example
Vignette. A 61-year-old man with metastatic melanoma is treated with ipilimumab. Six weeks later he develops frequent watery diarrhea and abdominal cramping. Stool studies for infection are negative, and colonoscopy shows diffuse colitis. Which normal molecular interaction does his drug block?
Answer: CTLA-4 on T cells binding B7 (CD80/CD86) on antigen-presenting cells.
Reasoning: CTLA-4 is a CD28 homolog that binds B7 with much higher affinity without stimulating the T cell, which restrains priming. Blocking it frees B7 to engage CD28, so more T cells activate, including self-reactive ones; enterocolitis and diarrhea are among the most common immune-related adverse events. Abatacept is the opposite (a CTLA-4–IgG1 fusion that blocks B7 and suppresses T cells), and nivolumab or pembrolizumab would target PD-1 instead.
Key takeaways
- Signal 1 (key): TCR with CD3 recognizes peptide–MHC; MHC I with CD8, MHC II with CD4 (rule of 8).
- Signal 2 (gas): B7 (CD80/CD86) on the APC binds CD28; without it the T cell becomes anergic.
- Signal 3 (steering): IL-12 → Th1 (T-bet, IFN-γ); IL-4 → Th2 (GATA3; IL-4, IL-5, IL-13); TGF-β + IL-6 → Th17 (RORγt, IL-17); TGF-β + IL-2 → Treg (FOXP3, IL-10, TGF-β).
- IL-2 drives clonal expansion; calcineurin inhibitors block its production.
- Brakes: CTLA-4 (outcompetes CD28, priming phase) and PD-1 (PD-L1/PD-L2, peripheral tissues); checkpoint inhibitors release them at the cost of immune-related adverse events.
- Abatacept and belatacept block B7 to suppress T cells; superantigens bypass specificity and cause toxic shock.
Sources
- Genetics, Human Major Histocompatibility Complex (MHC) — StatPearls, NCBI Bookshelf
- Buchbinder EI, Desai A. CTLA-4 and PD-1 pathways: similarities, differences, and implications of their inhibition — American Journal of Clinical Oncology (PubMed Central)
- Luckheeram RV, et al. CD4+ T cells: differentiation and functions — Clinical and Developmental Immunology (PubMed Central)
- Ipilimumab — StatPearls, NCBI Bookshelf
- Disease-Modifying Antirheumatic Drugs (DMARDs) — StatPearls, NCBI Bookshelf
- Krakauer T. Staphylococcal superantigens: pyrogenic toxins induce toxic shock — Toxins (PubMed Central)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
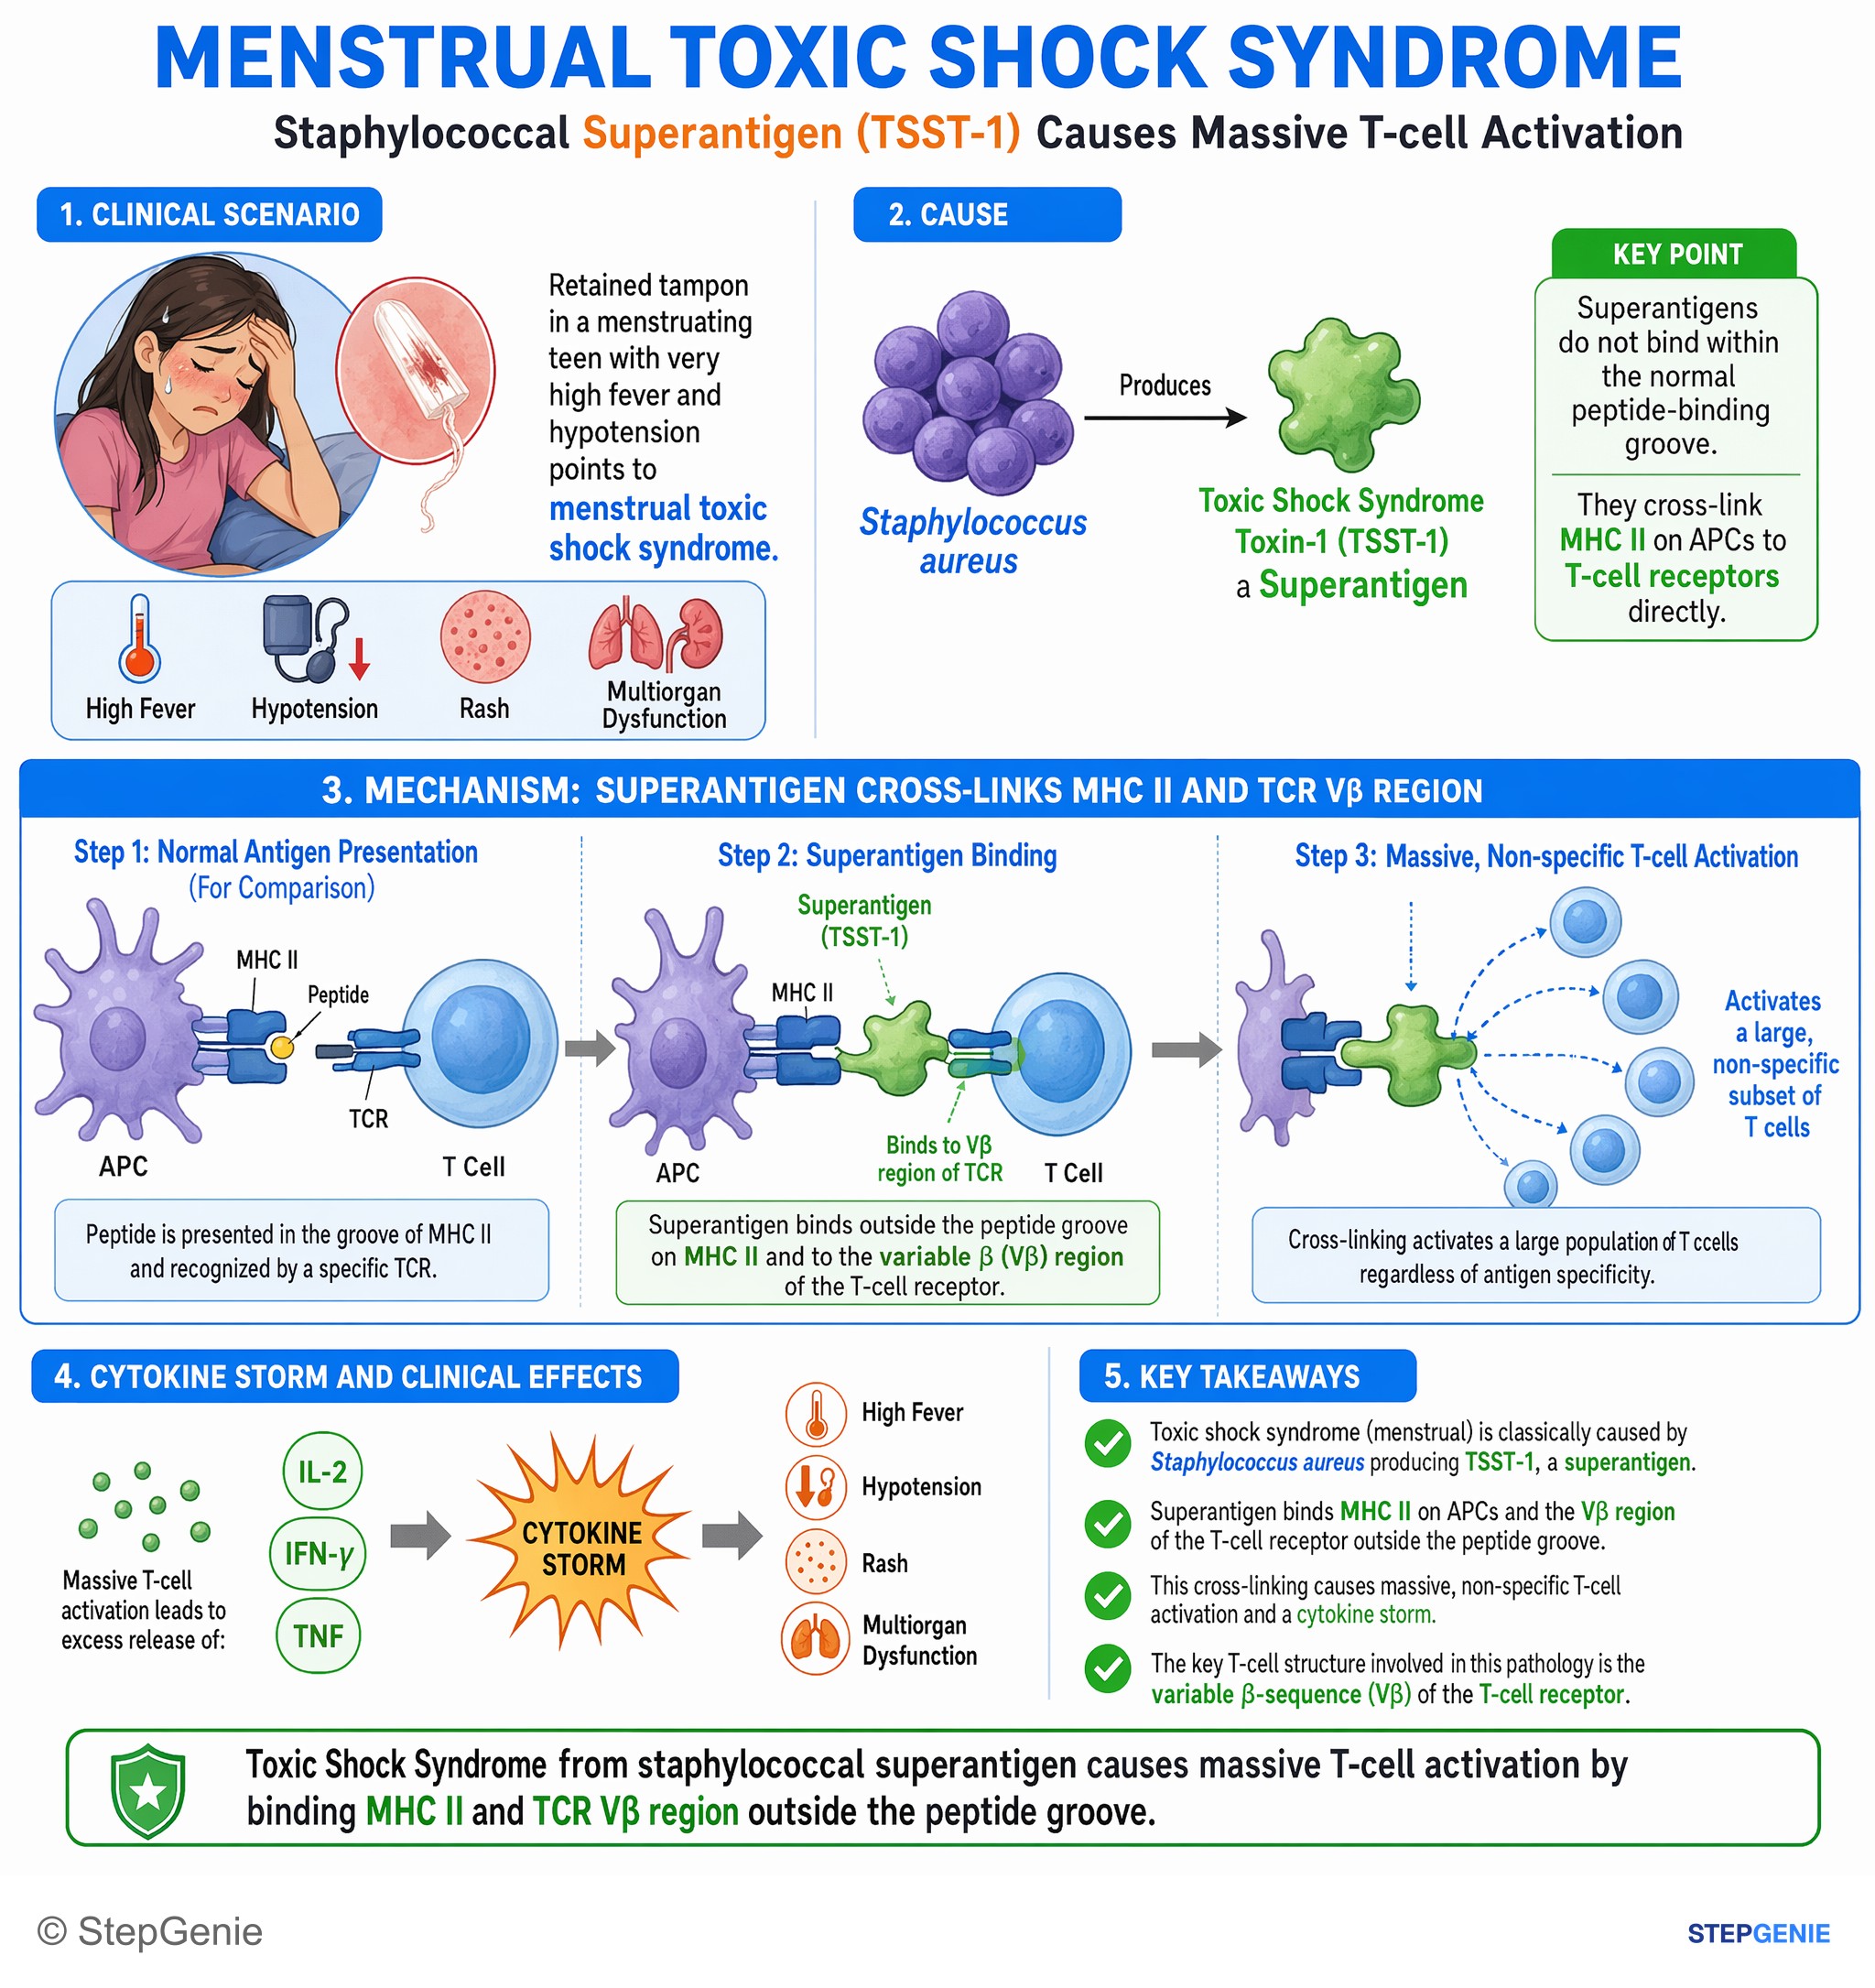
Toxic shock syndrome from staphylococcal superantigen causes massive T-cell activation by binding MHC II and TCR Vβ region outside the…
USMLE Step 1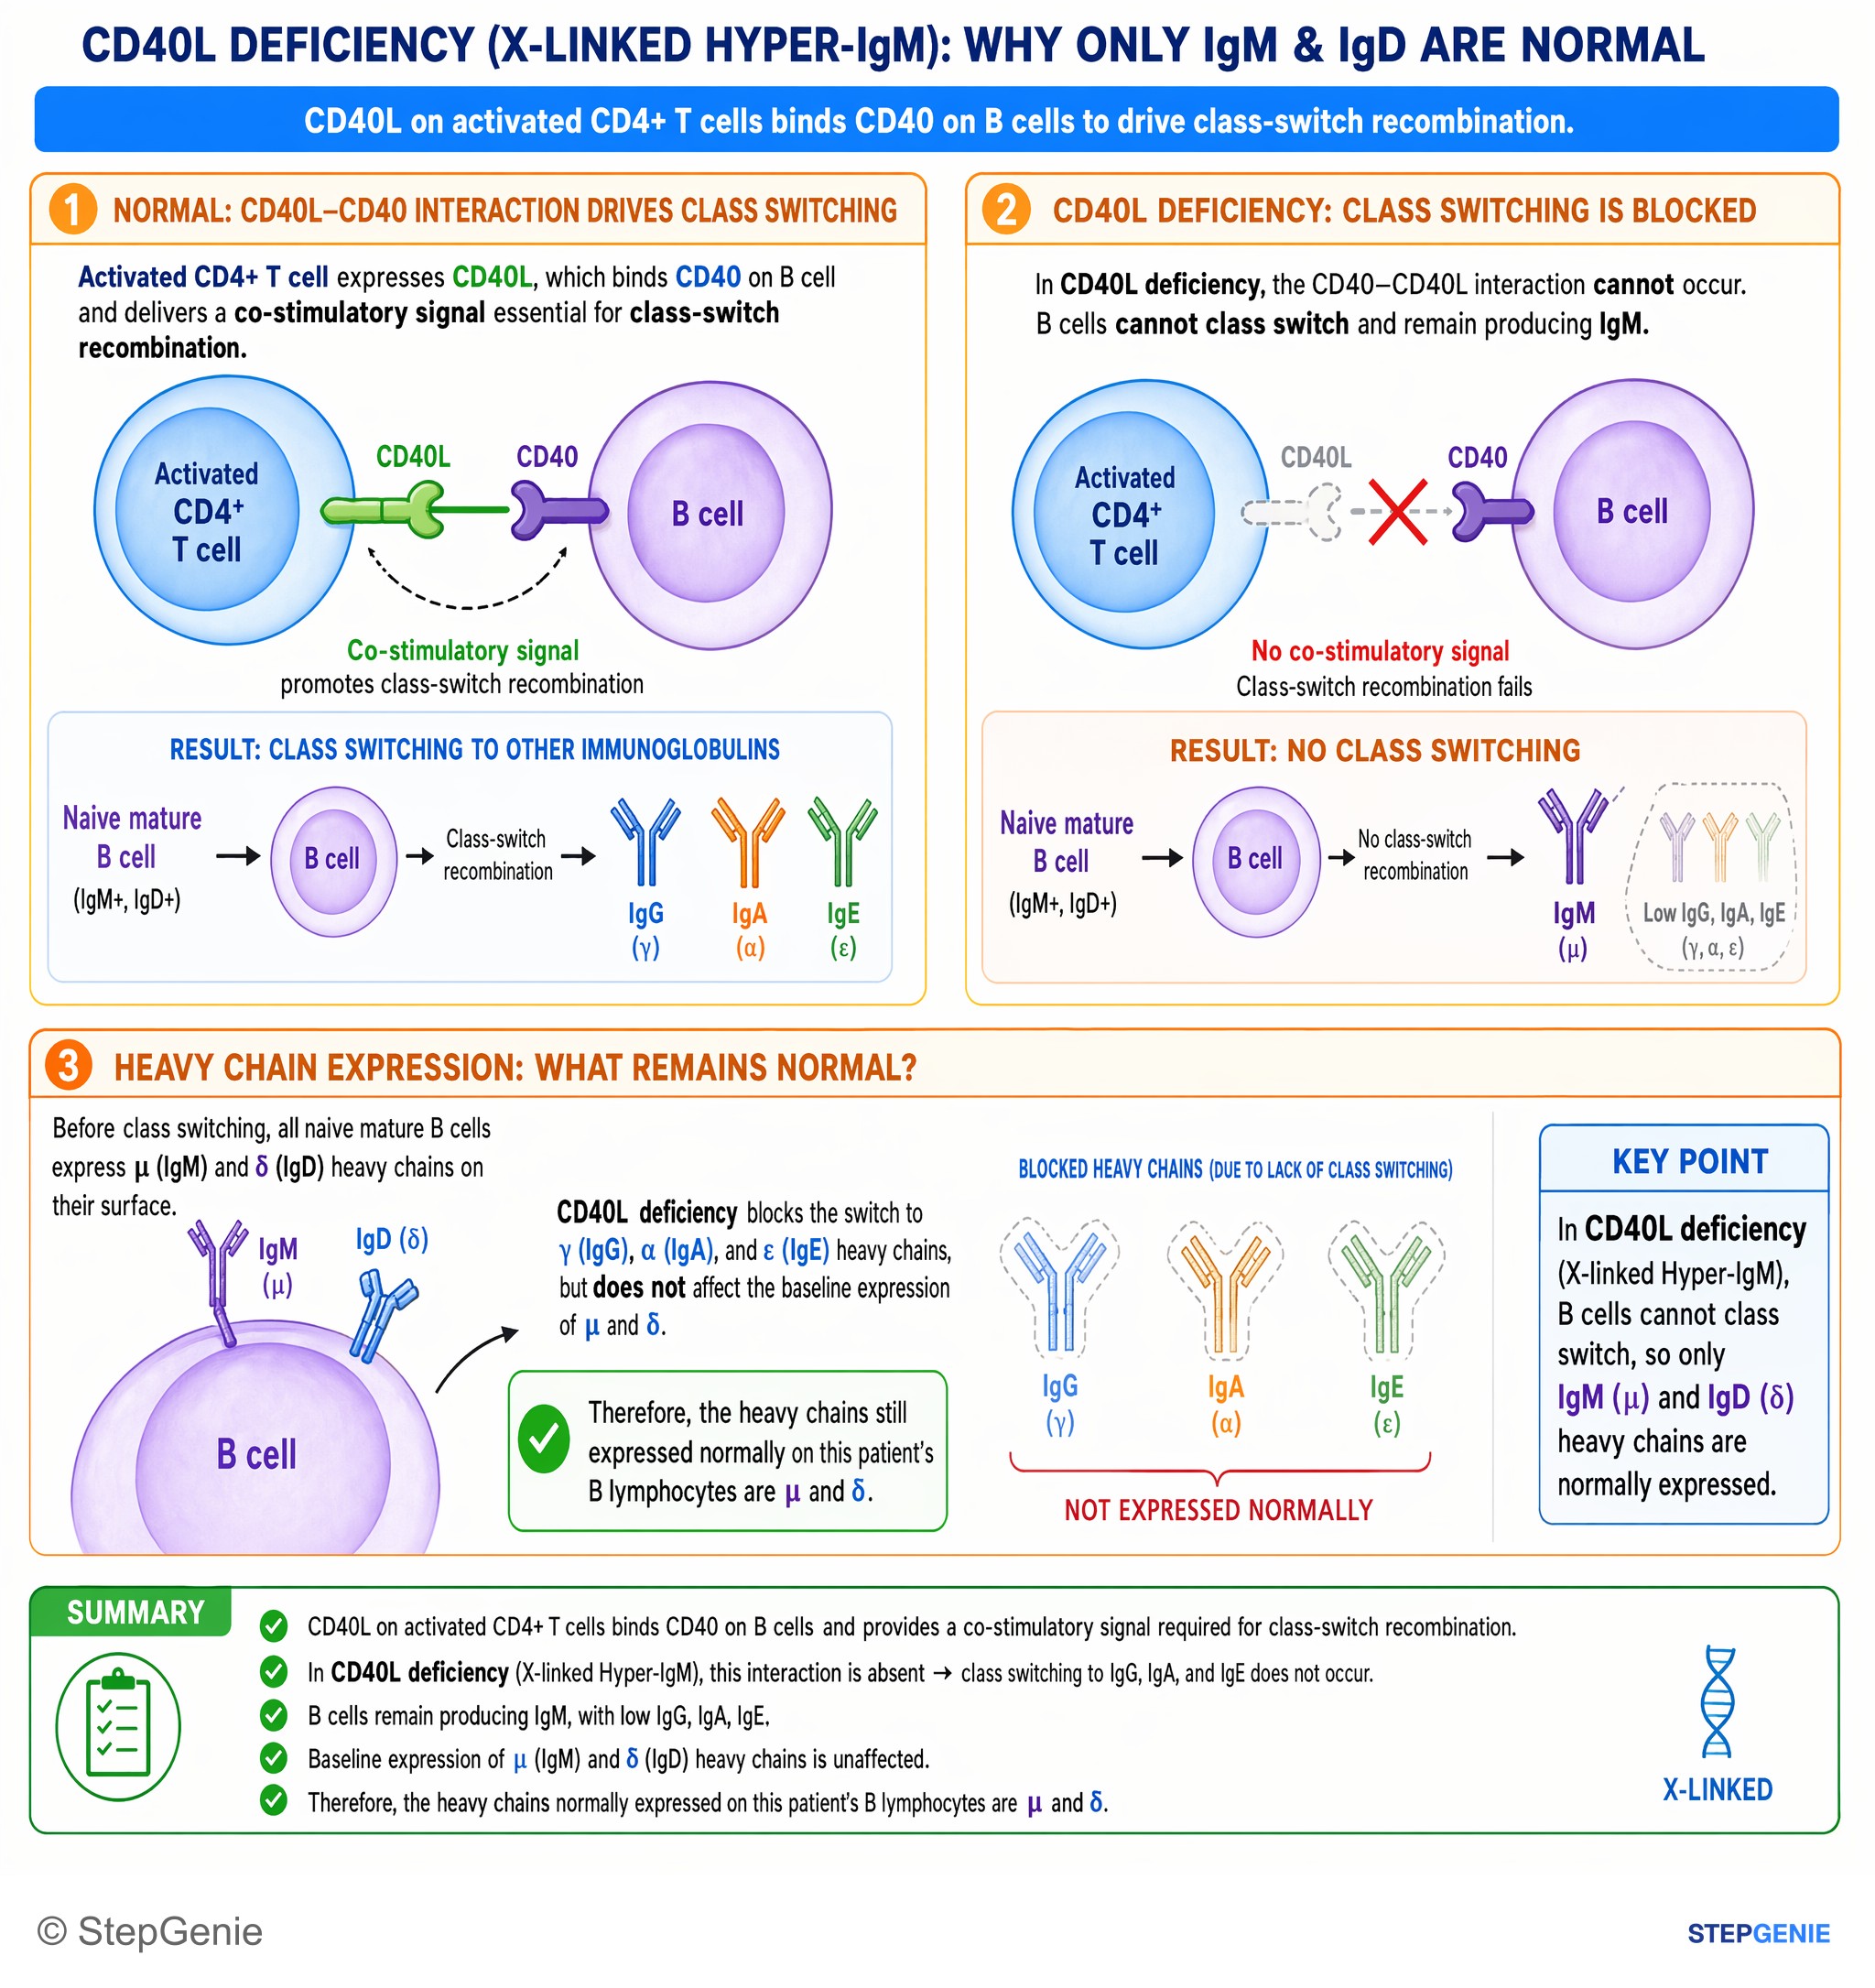
X-linked Hyper-IgM (CD40L deficiency): B cells cannot class switch, so only IgM (μ) and IgD (δ) heavy chains are normally expressed.
USMLE Step 1Frequently Asked Questions
What are the three signals of T-cell activation?
Signal 1 is antigen recognition: the T-cell receptor, with CD3, binds a peptide presented on MHC, with CD4 T cells recognizing MHC class II and CD8 T cells recognizing MHC class I. Signal 2 is costimulation, in which B7 (CD80 or CD86) on the antigen-presenting cell binds CD28 on the T cell. Signal 3 is the cytokine environment, such as IL-12 or IL-4, which directs what kind of effector cell the activated T cell becomes.
What happens if a T cell gets signal 1 without signal 2?
A T cell that recognizes its antigen without CD28–B7 costimulation becomes anergic, meaning it stops responding to that antigen. B7 molecules are upregulated on dendritic cells when they sense microbial products, so the costimulation requirement works as a danger check. It helps keep self-reactive T cells from being activated by self antigens presented without a danger signal.
What is the difference between CD28 and CTLA-4?
Both CD28 and CTLA-4 are receptors on T cells that bind B7 (CD80 and CD86) on antigen-presenting cells, but they have opposite effects. CD28 delivers the costimulatory signal that drives IL-2 production, proliferation and survival, whereas CTLA-4 binds B7 with much higher affinity without stimulating the cell, so it outcompetes CD28 and dampens activation. Ipilimumab blocks CTLA-4 to boost antitumor immunity, while abatacept and belatacept, fusion proteins built from CTLA-4, block B7 to suppress T cells.
Which cytokines drive Th1, Th2, Th17 and Treg differentiation?
IL-12 (with IFN-γ) drives Th1 cells through the transcription factor T-bet, and IL-4 drives Th2 cells through GATA3. TGF-β plus IL-6 drives Th17 cells through RORγt, with IL-21 and IL-23 reinforcing the response, while TGF-β plus IL-2 drives induced regulatory T cells through FOXP3. Th1 cells make IFN-γ, Th2 cells make IL-4, IL-5 and IL-13, Th17 cells make IL-17 and IL-22, and regulatory T cells make IL-10 and TGF-β.
How do superantigens activate T cells?
Superantigens such as toxic shock syndrome toxin-1 and staphylococcal enterotoxins bind MHC class II outside the peptide-binding groove and link it directly to specific T-cell receptor V-beta regions, without any antigen processing. This activates roughly 5% to 30% of all T cells, compared with less than 0.01% for a conventional antigen. The resulting cytokine storm of TNF-α, IL-1, IL-2 and IFN-γ causes the fever, hypotension and shock of toxic shock syndrome.