Job syndrome, the autosomal dominant hyper-IgE syndrome, is caused by a dominant-negative STAT3 mutation that leaves patients with almost no Th17 cells. Low IL-17 and IL-22 weaken the inflammatory call for white blood cells and the antimicrobial peptides that defend skin and lung, and blocked IL-6 signaling blunts inflammation, so Staphylococcus aureus abscesses are "cold" and pneumonias heal into pneumatoceles. Expect eczema from the newborn period, mucocutaneous candidiasis, IgE above 2,000 IU/mL with eosinophilia, and the non-immune clues summed up by FATED: coarse facies, cold abscesses, retained primary teeth, high IgE and dermatologic disease, plus fractures after minor trauma and scoliosis.
The flowchart in 6 steps
Step 1: Spot the infection pattern
- Recurrent S. aureus skin boils that are "cold": they lack the redness, warmth and tenderness you would expect.
- Recurrent pneumonias from early childhood, most often S. aureus, Streptococcus pneumoniae and Haemophilus influenzae.
- Chronic mucocutaneous candidiasis of the mouth, nails and vagina, in about 80% of patients.
Step 2: Check the skin history
A rash in the newborn period (often labeled eosinophilic pustulosis) that evolves into eczematoid dermatitis is typical. Eczema plus recurrent staph abscesses is the entry point to this diagnosis.
Step 3: Find the non-immune clues
- Retained primary teeth: baby teeth fail to shed because their roots don't resorb, so they sit alongside erupting permanent teeth.
- Characteristic face by adolescence: facial asymmetry, deep-set eyes, a broad nose and prominent skin pores.
- Bones and joints: osteoporosis with minimal-trauma fractures from early childhood, scoliosis (about 75% by age 16), joint hyperextensibility and sometimes craniosynostosis.
- Other: Chiari I malformation (about 20%), tortuous or dilated arteries including coronary artery aneurysms, and a higher lymphoma risk.
Step 4: Read the labs
- IgE above 2,000 IU/mL (adult normal is under 100 IU/mL).
- Eosinophilia (above 700/µL).
- Near absence of IL-17-producing Th17 cells, with fewer memory T and B cells.
Step 5: Name the mechanism
STAT3 carries signals from IL-6, IL-21 and IL-23. A dominant-negative mutant protein poisons the normal copy, so naive CD4 T cells cannot become Th17 cells:
- Less IL-17: the inflammatory signals that bring white blood cells into infected tissue are weak, so defense fails in skin and lung, the two sites where staph infections cluster.
- Less IL-17 and IL-22: keratinocytes and airway epithelium make fewer antimicrobial peptides such as β-defensins, and anti-Candida defense fails.
- Blocked IL-6 signaling: fever, CRP elevation and local inflammation are blunted, which is why abscesses look "cold."
- Abnormal lung healing: pneumonias leave pneumatoceles and bronchiectasis, which can become infected with Aspergillus fumigatus or Scedosporium.
How cytokines steer naive T cells into subsets is covered in T-cell activation.
Step 6: Confirm and treat
- Confirm with STAT3 genetic testing; the NIH clinical scoring system guides suspicion. Many cases (about half or more) are de novo, so the family history is often negative.
- Prevent staph: twice-daily trimethoprim-sulfamethoxazole prophylaxis, plus early, aggressive treatment of every infection, including drainage of abscesses.
- Skin: dilute bleach baths and chlorhexidine; dupilumab and omalizumab have improved the eczema.
- Selected patients: antifungal prophylaxis (for example, where Coccidioides is endemic) and IgG replacement.
- Hematopoietic stem cell transplant has improved the infection problem in successful recipients, but its effect on the skeletal and other non-immune features is unclear.
FATED: the mnemonic
| Letter | Feature | What the stem describes |
|---|---|---|
| F | Coarse Facies | Asymmetric face, deep-set eyes, broad nose, prominent pores by adolescence |
| A | Cold staphylococcal Abscesses | Recurrent skin boils without redness, warmth or tenderness |
| T | Retained primary Teeth | Baby teeth still in place while permanent teeth erupt |
| E | Hyper-IgE | IgE above 2,000 IU/mL, usually with eosinophilia |
| D | Dermatologic problems | Newborn pustular rash, then eczema |
FATED leaves out the skeleton, so add fractures after minor trauma and scoliosis to the checklist.
Job syndrome vs the look-alikes
| Disorder | Defect (inheritance) | Separating clue |
|---|---|---|
| Job syndrome (STAT3 hyper-IgE) | Dominant-negative STAT3, few Th17 cells (autosomal dominant, often de novo) | Cold staph abscesses, pneumatoceles, retained teeth, fractures, IgE above 2,000 IU/mL |
| DOCK8 deficiency | DOCK8, T-cell and NK-cell dysfunction (autosomal recessive) | High IgE with severe allergies and viral skin infections (herpes simplex, varicella-zoster, warts, molluscum), blood and skin cancers; no skeletal or dental features; transplant is curative |
| Chronic granulomatous disease | NADPH oxidase (X-linked in about 70%) | Catalase-positive infections (S. aureus, Burkholderia cepacia, Serratia, Nocardia, Aspergillus), granulomas; abnormal DHR test |
| Leukocyte adhesion deficiency type 1 | CD18, the β2 integrin subunit (autosomal recessive) | Delayed umbilical cord separation, omphalitis, no pus despite high white counts, poor wound healing |
| Wiskott-Aldrich syndrome | WAS protein (X-linked) | Eczema with thrombocytopenia (small platelets) and infections; low IgM, high IgA and IgE |
For the oxidative-burst defect in detail, see chronic granulomatous disease.
Exam traps
- High IgE alone is not Job syndrome. DOCK8 deficiency and Wiskott-Aldrich syndrome also raise IgE; the dental and skeletal findings point to STAT3.
- "Cold" is not "no pus." Job abscesses lack redness, warmth and tenderness. The infant who cannot form pus at all, with a very high white count and a late-separating umbilical cord, has leukocyte adhesion deficiency.
- Eczema plus small platelets is Wiskott-Aldrich syndrome.
- Warts, molluscum and severe herpes with bad allergies and autosomal recessive inheritance suggest DOCK8 deficiency.
- The defect is cytokine signaling and Th17 differentiation, not NADPH oxidase; an abnormal DHR test belongs to chronic granulomatous disease.
- Muted fever and CRP. Because IL-6 signaling is blunted, a serious infection can produce little fever or CRP.
Worked example
Vignette. A 10-year-old girl has had eczema since her first weeks of life, three S. aureus skin abscesses that were neither warm nor tender, and two pneumonias; chest CT shows a thin-walled lung cyst. Several primary teeth remain although her permanent teeth are erupting, and she fractured her forearm falling from a chair. IgE is 4,800 IU/mL and eosinophils are 1,100/µL. What is the underlying defect?
Answer: A dominant-negative STAT3 mutation that prevents Th17 differentiation (Job syndrome).
Reasoning: Cold staph abscesses, a pneumatocele, retained primary teeth, a minimal-trauma fracture and an IgE over 2,000 IU/mL complete the STAT3 picture. NADPH oxidase deficiency gives catalase-positive infections and granulomas, CD18 deficiency gives pus-free infections and delayed cord separation, and WAS protein deficiency gives thrombocytopenia with small platelets.
Key takeaways
- Job syndrome = autosomal dominant hyper-IgE syndrome = dominant-negative STAT3, often de novo.
- STAT3 → Th17 → IL-17 and IL-22: weaker white-cell recruitment and fewer antimicrobial peptides at skin and lung, plus blunted IL-6 inflammation.
- FATED: coarse Facies, cold staph Abscesses, retained primary Teeth, hyper-IgE (above 2,000 IU/mL), Dermatologic disease; add fractures and scoliosis.
- Lungs: staph pneumonias leave pneumatoceles and bronchiectasis that invite Aspergillus.
- Treatment: trimethoprim-sulfamethoxazole prophylaxis, early drainage and antibiotics, and skin care.
- DOCK8 deficiency is the autosomal recessive hyper-IgE look-alike with viral skin infections and no skeletal or dental signs.
Sources
- STAT3 Hyper IgE Syndrome — GeneReviews, NCBI Bookshelf
- Hyper-IgE Syndromes — StatPearls, NCBI Bookshelf
- Autosomal dominant hyper-IgE syndrome — MedlinePlus Genetics
- DOCK8 immunodeficiency syndrome — MedlinePlus Genetics
- Chronic Granulomatous Disease — StatPearls, NCBI Bookshelf
- Leukocyte Adhesion Deficiency — StatPearls, NCBI Bookshelf
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
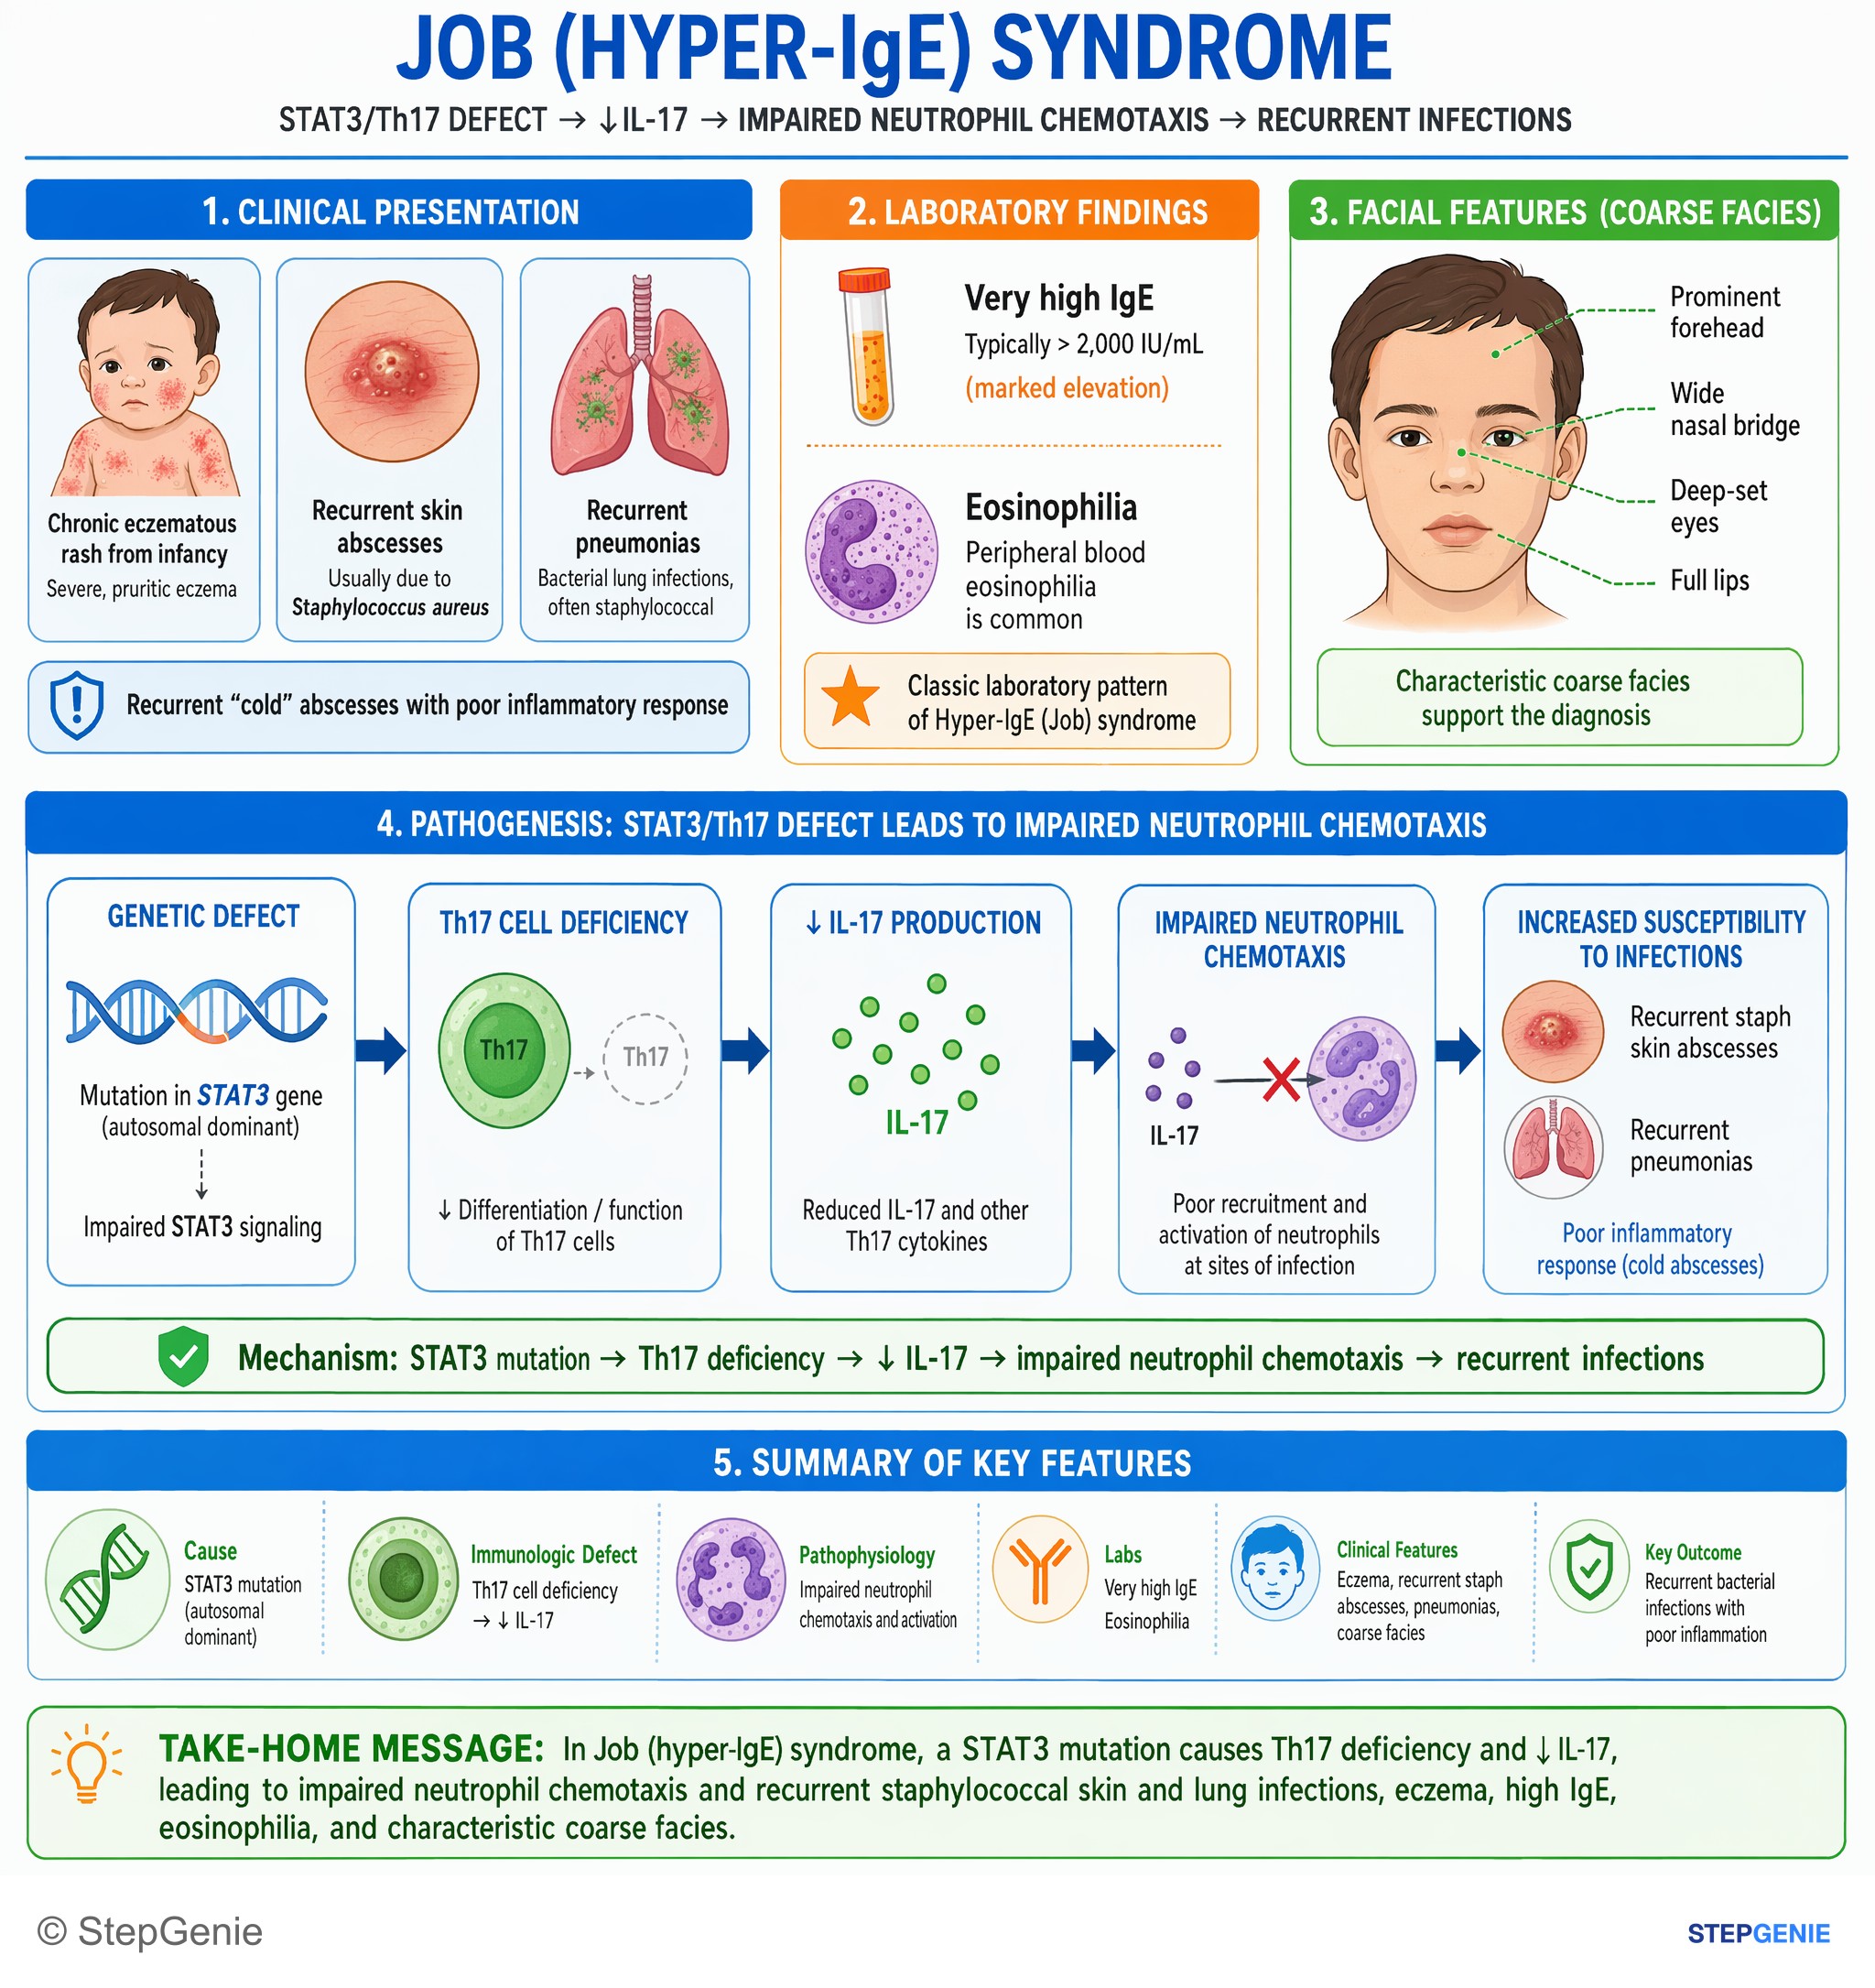
Job (hyper-IgE) syndrome from STAT3/Th17 defect → ↓IL-17, ↓neutrophil chemotaxis → recurrent staph abscesses, pneumonias, eczema…
USMLE Step 1Frequently Asked Questions
What causes Job syndrome?
Job syndrome, or autosomal dominant hyper-IgE syndrome, is caused by dominant-negative mutations in STAT3, a transcription factor that carries signals from IL-6, IL-21 and IL-23. Without STAT3 signaling, naive CD4 T cells cannot become Th17 cells, so IL-17 and IL-22 responses in the skin and lungs fail. Many cases, about half or more, arise from a new mutation, so there is often no family history.
Why are abscesses cold in Job syndrome?
The abscesses lack the usual redness, warmth and tenderness because inflammation is blunted. STAT3 is needed for IL-6 signaling, which drives fever, CRP and local inflammation, and for Th17 cells, whose IL-17 drives the local inflammation that brings in white blood cells. Staphylococcus aureus can therefore form abscesses that look deceptively quiet.
What does FATED stand for in Job syndrome?
FATED stands for coarse Facies, cold staphylococcal Abscesses, retained primary Teeth, hyper-IgE and Dermatologic problems such as eczema. IgE is typically above 2,000 IU/mL, usually with eosinophilia. The mnemonic leaves out the skeleton, so also remember fractures after minor trauma and scoliosis.
What is the difference between STAT3 and DOCK8 hyper-IgE syndrome?
STAT3 hyper-IgE syndrome (Job syndrome) is autosomal dominant and causes cold staphylococcal abscesses, pneumatoceles, candidiasis, retained primary teeth, fractures and scoliosis. DOCK8 deficiency is autosomal recessive and causes severe allergies, extensive viral skin infections such as herpes simplex, warts and molluscum, and a higher risk of blood and skin cancers, without the skeletal and dental features. Both have very high IgE, and stem cell transplant cures DOCK8 deficiency when done before irreversible organ damage.
How is hyper-IgE syndrome treated?
Treatment of STAT3 hyper-IgE syndrome centers on preventing staphylococcal infections with twice-daily trimethoprim-sulfamethoxazole and treating every infection early and aggressively, including draining abscesses. Skin care with dilute bleach baths and chlorhexidine helps the eczema, and some patients receive antifungal prophylaxis or IgG replacement. Stem cell transplant has improved infections in some patients, but its effect on the skeletal and other non-immune features is unclear.