Chronic granulomatous disease (CGD) is an inherited defect of the phagocyte NADPH oxidase (NOX2): neutrophils and macrophages engulf microbes normally but cannot make superoxide, so the respiratory burst fails and certain bacteria and fungi survive inside them. Patients get deep, recurrent infections with a short list of catalase-positive organisms (S. aureus, Burkholderia cepacia, Serratia marcescens, Nocardia, Aspergillus) plus granulomas that can obstruct the stomach outlet or urinary tract, and about two-thirds of cases are X-linked (CYBB, gp91phox). The test of choice is dihydrorhodamine (DHR) flow cytometry, which shows little or no oxidative burst, and management is TMP-SMX + itraconazole prophylaxis, interferon-γ, and hematopoietic stem cell transplant (HSCT) for cure.
CGD at a glance
| Feature | What to know |
|---|---|
| Defect | NADPH oxidase (NOX2) → no superoxide → no respiratory burst; phagocytosis itself is normal |
| Inheritance | X-linked recessive CYBB (gp91phox) in about two-thirds; the rest autosomal recessive, mostly NCF1 (p47phox) |
| Organisms | S. aureus, Burkholderia cepacia complex, Serratia marcescens, Nocardia, Aspergillus |
| Infections | Pneumonia, suppurative lymphadenitis, liver abscess, osteomyelitis, skin abscesses |
| Inflammation | Granulomas obstructing the gastric outlet or urinary tract; Crohn-like colitis |
| Age at diagnosis | Mostly before age 5; milder cases can surface in adolescence or adulthood |
| Best test | DHR flow cytometry: little or no fluorescence after stimulation |
| Classic test | Nitroblue tetrazolium (NBT): cells fail to turn blue |
| Prevention | Daily TMP-SMX + itraconazole; interferon-γ three times weekly |
| Cure | Allogeneic HSCT |
Pathophysiology: the respiratory burst, step by step
Inside the phagosome, NOX2 moves electrons from NADPH onto oxygen, and the products cascade:
- NADPH oxidase:
- Dismutation (superoxide dismutase or spontaneous):
- Myeloperoxidase (MPO): (hypochlorous acid, "bleach")
In CGD step 1 fails, so steps 2 and 3 run dry even though MPO is present. The NADPH comes from the pentose phosphate pathway, which is why severe G6PD deficiency sits on the differential (see the pentose phosphate pathway visual hack).
Why catalase-positive organisms? The classic explanation: catalase-negative bacteria such as streptococci make H₂O₂ but cannot break it down, so they supply the CGD phagocyte with the oxidant that kills them; catalase-producing pathogens like S. aureus and most gram-negative rods scavenge both their own and the host's H₂O₂. Use this logic on the exam, but don't over-apply it: catalase alone does not seem to be a significant virulence factor in animal models, and CGD patients have developed chronic infections with catalase-negative Actinomyces. Memorize the organism list rather than deriving it from a catalase test.
Why granulomas? NOX2 also helps regulate inflammation. Without it, neutrophil activity is poorly controlled, so patients develop granulomas and Crohn-like colitis that are treated with corticosteroids, not just antibiotics.
Genetics: which subunit is broken
gp91phox and p22phox form the membrane flavocytochrome b558; p47phox, p67phox and p40phox are cytosolic subunits that join it (with Rac2) on activation.
| Gene | Protein | Inheritance | Share of CGD |
|---|---|---|---|
| CYBB | gp91phox (NOX2), membrane | X-linked recessive | About 65–70% |
| NCF1 | p47phox, cytosolic | Autosomal recessive | About 20% |
| CYBA | p22phox, membrane | Autosomal recessive | About 7% |
| NCF2 | p67phox, cytosolic | Autosomal recessive | About 7% |
| NCF4 | p40phox, cytosolic | Autosomal recessive | Under 1% |
A sixth gene, CYBC1, accounts for only a few patients.
- X-linked disease is generally worse. Compared with autosomal recessive CGD, males with X-linked CGD are diagnosed earlier and have more perirectal abscesses, suppurative adenitis, gastric outlet and urinary obstruction, and higher mortality at a young age.
- Residual superoxide predicts survival. Patients with NCF1 (p47phox) variants have relatively good survival (beyond age 40 in more than 80%).
- Carrier mothers of X-linked CGD show two neutrophil populations on DHR because of X-inactivation. They are usually healthy but can have discoid-lupus-like skin lesions and aphthous ulcers, and when fewer than about 20% of their neutrophils are DHR-positive they become susceptible to CGD-type infections.
The organisms and where they strike
Hook for the big five: Some Nasty Bugs Survive Anyway (S. aureus, Nocardia, Burkholderia, Serratia, Aspergillus).
| Organism | Typical CGD infection | Exam clue |
|---|---|---|
| Staphylococcus aureus | Liver abscess, skin abscess, lymphadenitis, osteomyelitis | Liver abscess occurs in up to 35% of patients |
| Burkholderia cepacia complex | Pneumonia, sepsis | Also a classic cystic fibrosis lung pathogen |
| Serratia marcescens | Osteomyelitis; skin infection | The most common CGD infection in infancy is a Serratia skin or bone infection |
| Nocardia | Pneumonia, osteomyelitis, brain abscess | Branching, weakly acid-fast rods |
| Aspergillus | Pneumonia, osteomyelitis, brain abscess | Leading cause of death; A. nidulans is almost exclusive to CGD |
Rare bacteria considered pathognomonic for CGD: Granulibacter bethesdensis, Chromobacterium violaceum and Francisella philomiragia.
Classic stem clues
- First infections involve the lymph nodes, lungs, liver, bone and skin.
- Obstruction: vomiting from gastric outlet (pyloric) granulomas, or urinary obstruction from bladder granulomas.
- Colitis: about 40–50% develop intestinal inflammation that resembles Crohn disease.
- Labs: hypergammaglobulinemia and hematologic signs of chronic infection; antibody levels are not low.
- Exposure history: mulch, compost, potting soil or leaf raking can cause fulminant fungal pneumonia from inhaled spores. Live bacterial vaccines (BCG, oral typhoid) are contraindicated.
Diagnosis: DHR vs NBT
| Test | How it works | Normal result | CGD |
|---|---|---|---|
| DHR flow cytometry (preferred) | Stimulated neutrophils oxidize dihydrorhodamine 123 to fluorescent rhodamine 123 | Strong fluorescence shift | Absent or greatly reduced shift |
| NBT slide test (older) | Superoxide reduces yellow NBT to blue-black formazan | More than 95% of cells turn blue | Cells do not turn blue (no formazan) |
- DHR is easier, more reliable, quantitative and more sensitive than NBT, and it can usually separate X-linked CGD, autosomal recessive CGD and X-linked carriers (two peaks).
- NBT can be falsely normal in carriers (especially with skewed X-inactivation) and in hypomorphic CGD with residual activity.
- Confirm with gene testing: an abnormal DHR should be followed by mutation analysis.
- False-abnormal DHR: complete MPO deficiency gives an abnormal DHR because the dye's oxidation depends on MPO, but superoxide production and NBT staining are normal.
- Galactomannan is unreliable here: the IDSA guideline does not recommend it for screening in CGD, where results are often negative despite invasive aspergillosis.
Treatment and prevention
| Goal | Standard approach |
|---|---|
| Prevent bacterial infection | Lifelong daily TMP-SMX |
| Prevent fungal infection | Lifelong daily itraconazole (voriconazole or posaconazole are alternatives) |
| Immunomodulation | Interferon-γ-1b (FDA-approved for CGD): 50 mcg/m² subcutaneously three times weekly when body surface area is above 0.5 m² |
| Treat active infection | Aggressive, culture-directed therapy; drain abscesses; voriconazole for invasive aspergillosis; granulocyte transfusions can be lifesaving |
| Treat inflammation | Corticosteroids for obstructive granulomas and colitis |
| Cure | Allogeneic HSCT, best with matched donors at a younger age; gene therapy is under study |
- Interferon-γ evidence: in the placebo-controlled trial described in its FDA label (128 patients), serious infections occurred in 14 patients on interferon-γ-1b vs 30 on placebo, a 67% relative risk reduction. IDSA strongly recommends it as prophylaxis in CGD. Expect flu-like side effects (fever, headache, chills, fatigue).
- Prognosis: survival is now about 90% at age 10, and with treatment most patients live into mid- to late adulthood.
CGD vs its mimics
| Disorder | Defect | Distinguishing clue | DHR result |
|---|---|---|---|
| CGD | NADPH oxidase | Catalase-positive abscesses, granulomas | Absent or low |
| MPO deficiency | Myeloperoxidase (no HOCl) | Usually asymptomatic; severe Candida mainly with diabetes | Can be abnormal, but superoxide production and NBT are normal |
| LAD type 1 | CD18 (β2 integrin) | Cord separation after 3 weeks, no pus, persistently high WBC | Normal |
| Chédiak-Higashi | LYST | Oculocutaneous albinism, giant granules, neurologic problems, accelerated phase | Normal |
| Job syndrome (AD hyper-IgE) | STAT3 → weak Th17 | Staph skin and lung abscesses, eczema, retained baby teeth, IgE over 2,000 IU/mL | Normal |
| IL-12/IFN-γ axis defects | IL12RB1, IFNGR1 and others | Disseminated BCG or nontuberculous mycobacteria, Salmonella | Normal |
The DHR is normal in LAD, Chédiak-Higashi, Job syndrome and IL-12/IFN-γ defects because none of them damages the NADPH oxidase itself. An abnormal DHR points to CGD, but MPO deficiency can mimic it on the assay and severe G6PD deficiency can also blunt the burst.
Compare the granule defect in the Chédiak-Higashi mnemonic, the Th17 defect in the Job syndrome flowchart, and the mycobacterial pattern in the IL-12 receptor deficiency question.
Practice question
A 3-year-old boy has fever and right upper quadrant pain. CT shows a liver abscess, and the drained pus grows Staphylococcus aureus. At 18 months he had Serratia marcescens osteomyelitis of the foot, and last year a suppurative cervical lymph node was drained. His umbilical cord separated at 10 days. Neutrophil count and IgG are elevated; IgE is normal. Which finding is most likely?
- A. Absent fluorescence shift in stimulated neutrophils on DHR flow cytometry
- B. Absent CD18 on neutrophils by flow cytometry
- C. Giant cytoplasmic granules on the blood smear
- D. Absent myeloperoxidase with normal NBT reduction
- E. Serum IgE above 2,000 IU/mL
- F. Absent IL-12 receptor β1 on lymphocytes
Answer: A. S. aureus liver abscess, Serratia osteomyelitis and suppurative lymphadenitis in a boy is the catalase-positive pattern of X-linked CGD.
- B (LAD-1): these abscesses contained pus and the cord separated on time; LAD makes no pus and delays cord separation.
- C (Chédiak-Higashi): no albinism, neurologic problems or bleeding tendency.
- D (MPO deficiency): usually asymptomatic; it can make DHR look abnormal, but superoxide and NBT are normal.
- E (Job syndrome): IgE is normal and there is no eczema or retained teeth.
- F (IL-12 receptor β1 deficiency): presents with mycobacteria or Salmonella, and the DHR is normal.
Next steps: if his mother is an X-linked carrier, her DHR will show two neutrophil populations. He needs TMP-SMX and itraconazole prophylaxis, interferon-γ, and an HSCT evaluation.
Key takeaways
- CGD = NADPH oxidase (NOX2) defect → no superoxide → failed respiratory burst; ingestion is normal, killing is not.
- Organisms: S. aureus, Burkholderia cepacia, Serratia, Nocardia and Aspergillus (the leading cause of death).
- About two-thirds are X-linked (CYBB, gp91phox); NCF1 (p47phox) is the main autosomal recessive form and has better survival.
- DHR flow cytometry is the test of choice; NBT (no blue formazan) is the classic alternative; MPO deficiency can give a false-abnormal DHR.
- Granulomas obstruct the gastric outlet and urinary tract, and Crohn-like colitis affects about 40–50%.
- Prophylaxis: TMP-SMX + itraconazole + interferon-γ; HSCT is the only established cure.
Sources
- Leiding JW, Holland SM. Chronic Granulomatous Disease — GeneReviews, NCBI Bookshelf (updated 2026)
- Chronic Granulomatous Disease (CGD) — Merck Manual Professional Edition
- Chronic granulomatous disease — MedlinePlus Genetics
- CYBB gene — MedlinePlus Genetics
- Yu JE, et al. Considerations in the Diagnosis of Chronic Granulomatous Disease — Journal of the Pediatric Infectious Diseases Society (2018)
- Kottilil S, et al. Infections with Haemophilus species in chronic granulomatous disease: insights into the interaction of bacterial catalase and H2O2 production — Clinical Immunology (2003)
- Nguyen GT, et al. Neutrophils to the ROScue: Mechanisms of NADPH Oxidase Activation and Bacterial Resistance — Frontiers in Cellular and Infection Microbiology (2017)
- ACTIMMUNE (interferon gamma-1b) prescribing information — DailyMed, US National Library of Medicine
- Practice Guidelines for the Diagnosis and Management of Aspergillosis: 2016 Update — Infectious Diseases Society of America
- Chronic granulomatous disease (CGD) and other phagocytic cell disorders — Immune Deficiency Foundation
- Leukocyte Adhesion Deficiency — Merck Manual Professional Edition
- Hyper-IgE Syndrome — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
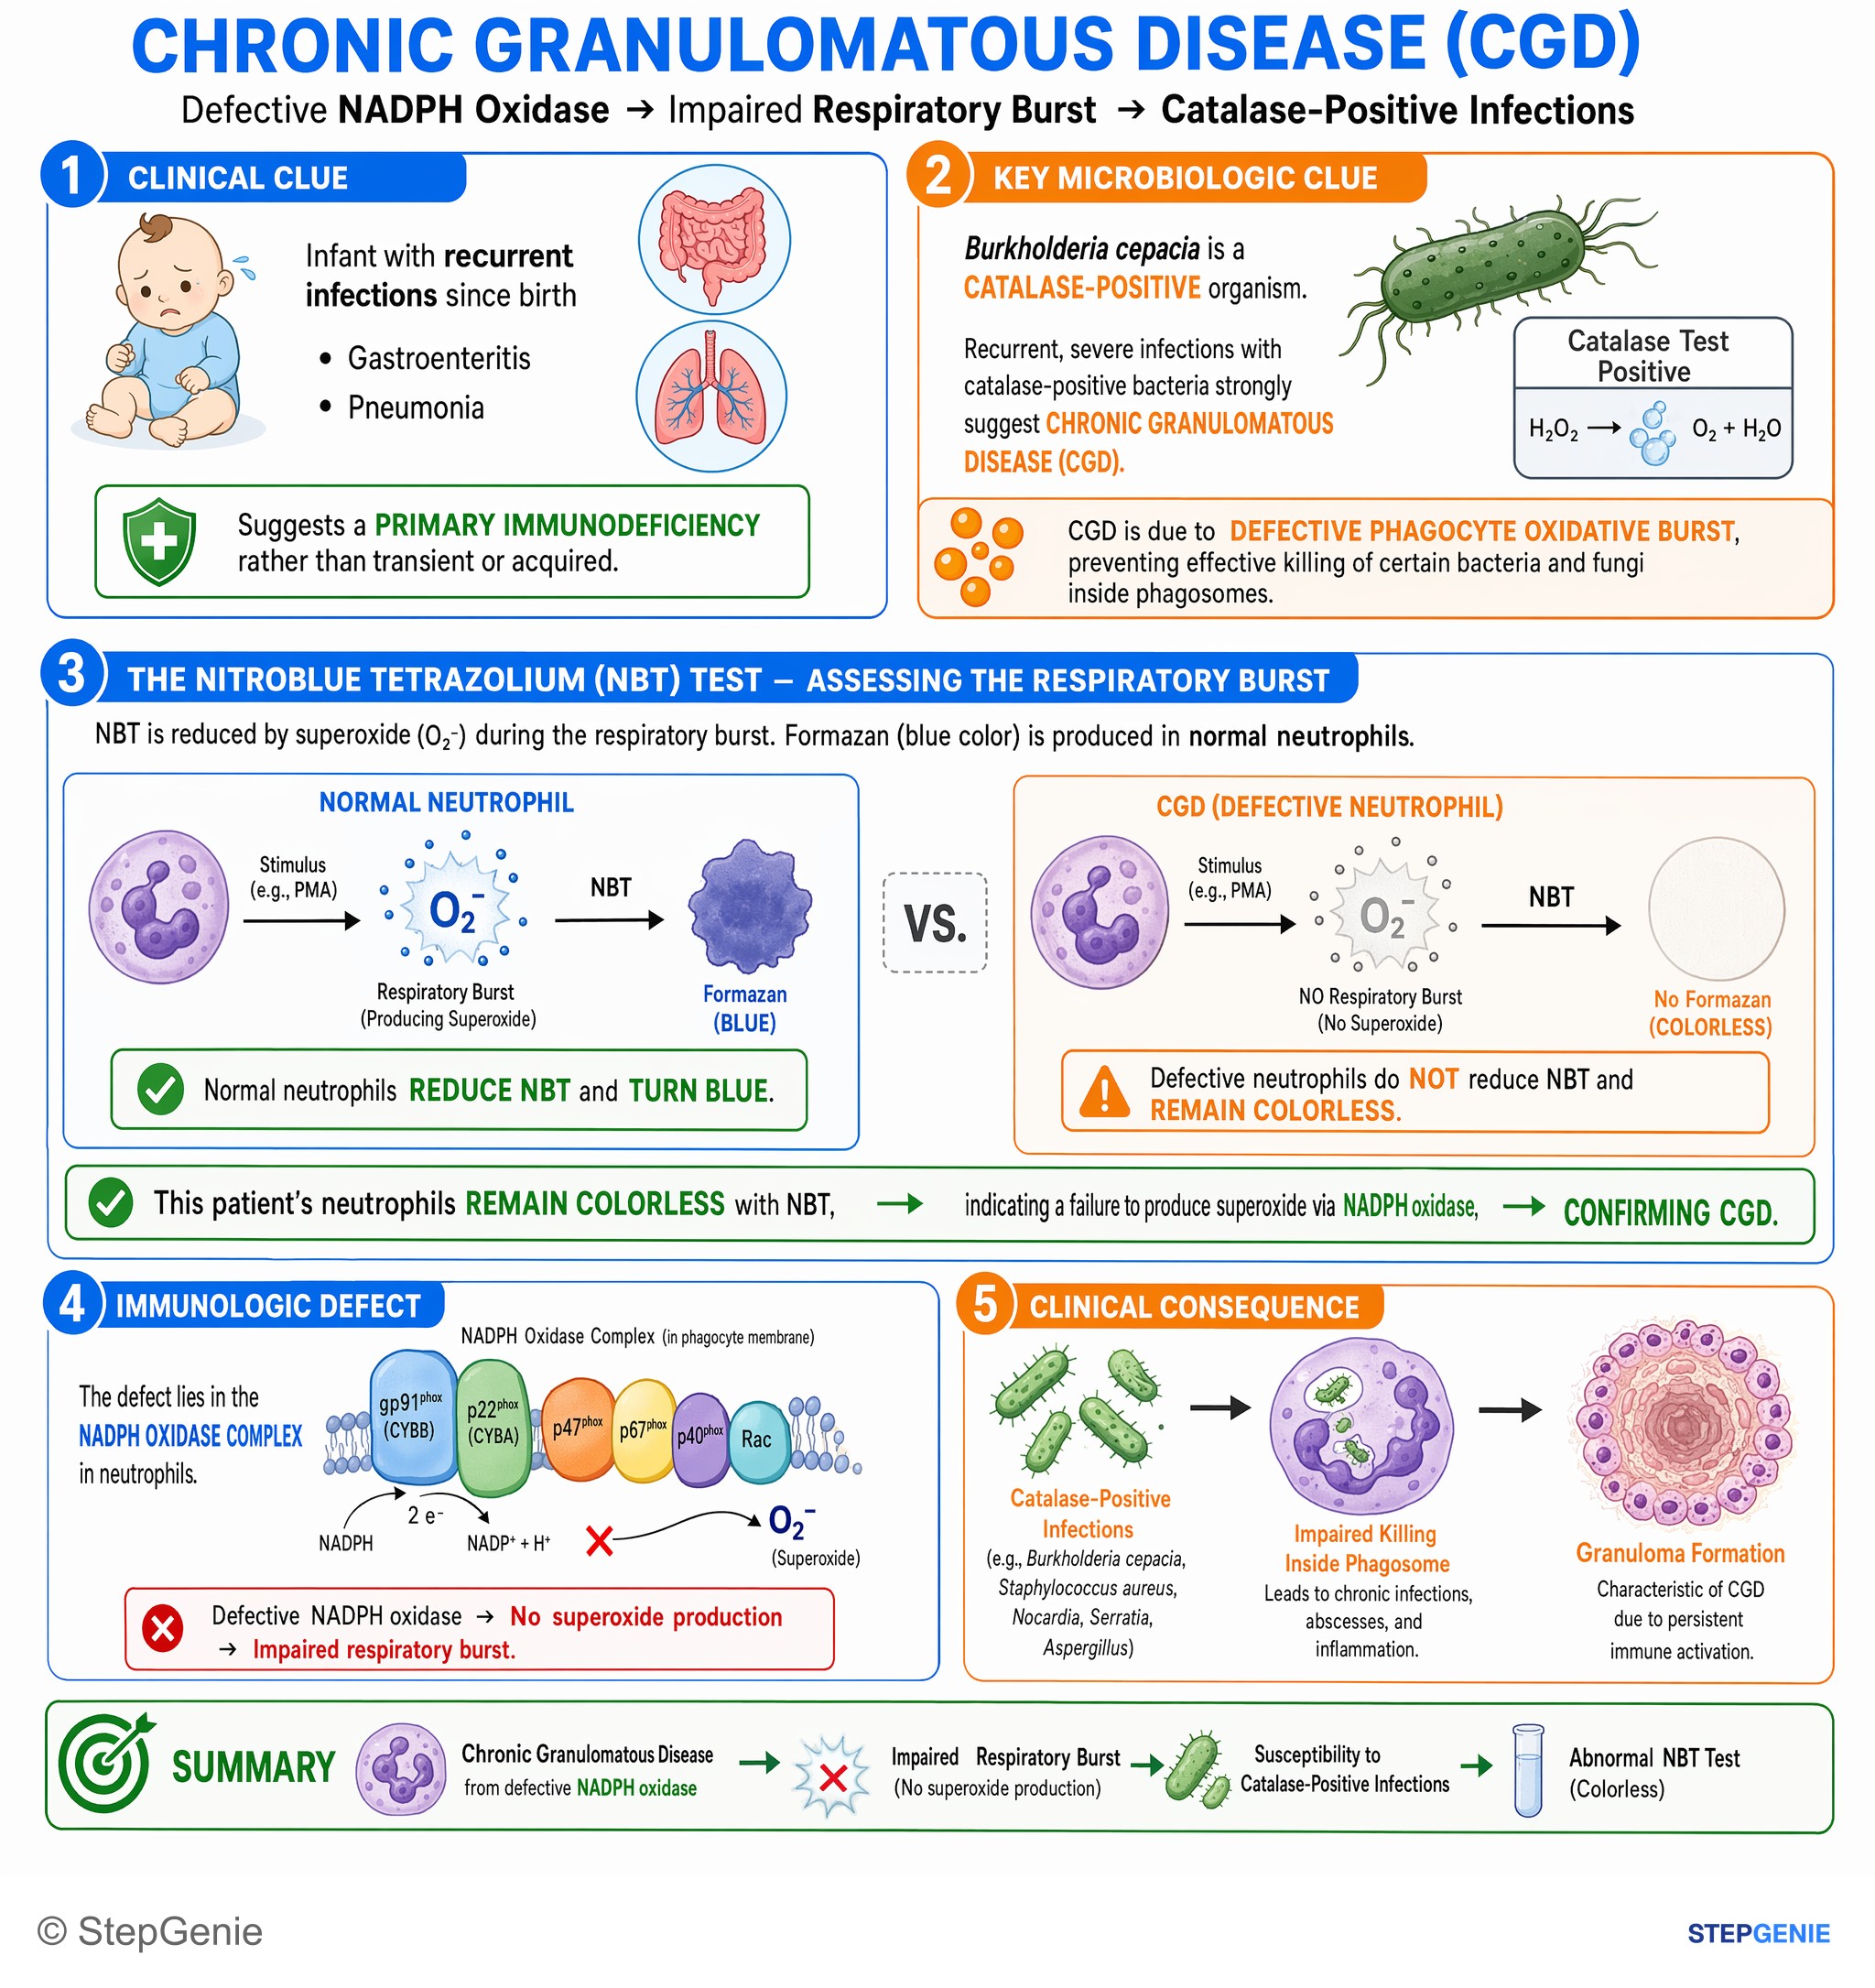
Chronic granulomatous disease from defective NADPH oxidase → impaired respiratory burst → catalase-positive infections (eg, Burkholderia…
USMLE Step 1Frequently Asked Questions
What is chronic granulomatous disease?
Chronic granulomatous disease (CGD) is an inherited immunodeficiency in which the NADPH oxidase of neutrophils and macrophages does not work, so these cells can engulf microbes but cannot make superoxide and the other oxidants of the respiratory burst. Patients have recurrent, deep bacterial and fungal infections and form granulomas that can obstruct the stomach outlet or urinary tract. About two-thirds of cases are X-linked, caused by CYBB variants affecting gp91phox; the rest are autosomal recessive.
What organisms cause infections in chronic granulomatous disease?
The classic organisms are Staphylococcus aureus, Burkholderia cepacia complex, Serratia marcescens, Nocardia and Aspergillus, and Aspergillus is the leading cause of death. They are traditionally explained as catalase-positive organisms that break down their own hydrogen peroxide, leaving the phagocyte with no oxidant to use against them. Catalase alone does not appear to be a major virulence factor in animal models, so it is best to memorize the specific list.
How is chronic granulomatous disease diagnosed?
The test of choice is dihydrorhodamine (DHR) flow cytometry, in which stimulated neutrophils from a patient with CGD show absent or greatly reduced fluorescence. In the older nitroblue tetrazolium (NBT) test, the cells fail to turn blue. An abnormal DHR should be confirmed with genetic testing, which also identifies the subtype. Myeloperoxidase deficiency can make the DHR look abnormal even though superoxide production and NBT staining are normal.
What is the treatment for chronic granulomatous disease?
Standard prevention is lifelong daily trimethoprim-sulfamethoxazole plus an antifungal such as itraconazole, and many centers add interferon gamma-1b injections three times weekly, which reduced serious infections in a placebo-controlled trial. Infections are treated aggressively with culture-directed antimicrobials and abscess drainage, and granulomatous complications often need corticosteroids. Allogeneic hematopoietic stem cell transplantation is the only established cure, and gene therapy is under study.
Is chronic granulomatous disease X-linked or autosomal recessive?
Both forms exist. About two-thirds of cases are X-linked recessive, caused by variants in CYBB, which encodes gp91phox, so they affect boys, and carrier mothers show two populations of neutrophils on DHR testing. The rest are autosomal recessive, most often from NCF1 variants affecting p47phox; these patients often have some residual oxidase activity and relatively good survival.
What is the life expectancy with chronic granulomatous disease?
Survival has improved greatly and is now about 90% at age 10, according to GeneReviews. With prophylaxis and treatment, most affected people live into mid- to late adulthood, and people with NCF1-related disease have relatively good survival, with more than 80% living beyond age 40. Hematopoietic stem cell transplantation can cure the disease.