You’re on rounds and a toddler keeps getting “just another ear infection.” Vaccines didn’t really “take,” tonsils look tiny, and the attending says: “Think Bruton.” Here’s a quick, shareable memory palace that locks in X-linked agammaglobulinemia (XLA) in under a minute—plus the USMLE-ready details that actually get tested.
The Memory Palace: “Bruton’s Locked B-Cell Boutique”
Picture a baby boy standing outside a fancy B-cell boutique. The sign says “B-KINASE (BTK) REQUIRED”, but the door is padlocked.
Inside, you can see racks labeled IgG, IgA, IgM, but the boy can’t enter—so he leaves with no antibodies and no B cells.
What each object means (and what to remember)
- Baby boy (X-linked) → XLA affects males
- Padlocked door labeled “BTK” → BTK mutation blocks B-cell maturation
- Empty shopping bags labeled IgG/IgA/IgM → all immunoglobulins low
- Tiny “tonsil display” + missing “lymph node mannequins” → absent/underdeveloped tonsils and lymph nodes
- A “No Live Shots” sticker on the door → avoid live vaccines in significant humoral immunodeficiency
- A “GI aisle” with a sign: “Enteroviruses welcome” → vulnerability to enteroviruses (e.g., polio/echo) and Giardia
One-Liner (the kind you can drop in a question stem explanation)
X-linked agammaglobulinemia (Bruton) = BTK defect → no B-cell maturation past pre-B stage → ↓ all Igs, ↓/absent B cells, recurrent bacterial + enteroviral infections after 6 months, small/absent tonsils/lymph nodes.
High-Yield Pathophys: What BTK actually does
BTK (Bruton tyrosine kinase) is required for pre–B cell receptor signaling in the bone marrow.
Result
- Arrest at pre-B stage
- No mature B cells in peripheral blood
- No plasma cells → very low immunoglobulins
USMLE phrasing: “Failure of B-cell maturation” and “absent germinal centers.”
Timeline Clue: Why symptoms start after ~6 months
Maternal IgG provides early protection; once it wanes (around 6 months), infections show up.
Classic pattern: recurrent infections beginning at ~6 months of age in a male infant.
What infections show up (testable list)
Think encapsulated bacteria + a couple of classic non-bacterial offenders:
Common offenders
- Encapsulated bacteria (opsonization problems with low IgG)
- Streptococcus pneumoniae
- Haemophilus influenzae
- Enteroviruses
- Polio, echovirus, coxsackie (humoral immunity is crucial)
- Giardia lamblia
- Especially with low IgA → chronic diarrhea, malabsorption
Physical Exam + Anatomy Clue: “Where are the tonsils?”
Because B cells populate follicles/germinal centers:
- Absent or small tonsils/adenoids
- No palpable lymph nodes
- Absent germinal centers on lymph node biopsy
These details are disproportionately high-yield in NBME-style stems.
Labs & Diagnosis: The “pattern recognition” table
| Feature | X-linked agammaglobulinemia (Bruton) |
|---|---|
| Gene/inheritance | BTK mutation, X-linked recessive |
| B cells (CD19/20) | ↓ or absent |
| Immunoglobulins | ↓ all (IgG, IgA, IgM) |
| Plasma cells | Absent |
| Germinal centers | Absent |
| Onset | After 6 months |
| Tonsils/lymph nodes | Small/absent |
Board-style phrasing: “Flow cytometry shows absent CD19+ B cells.”
Treatment & Prevention (what to choose on exam day)
- IVIG replacement (core therapy)
- Avoid live vaccines (risk depends on severity and vaccine type; for USMLE, the safe reflex is avoid live vaccines in major humoral immunodeficiency)
- Prompt treatment of infections; sometimes prophylactic antibiotics are used clinically
Rapid-fire differentiators (so you don’t confuse it)
- XLA vs CVID:
- XLA = boy, early, absent B cells
- CVID = later onset, B cells present but dysfunctional, low IgG ± IgA/IgM
- XLA vs Hyper-IgM:
- Hyper-IgM = high IgM, class-switch defect, often opportunistic infections
- XLA = low all Igs, absent B cells
Shareable “Memory Palace” Recap (screenshot-friendly)
Bruton’s Locked B-Cell Boutique:
- Boy outside a BTK-locked door
- Leaves with no Ig bags
- Tiny tonsils display inside
- “Enteroviruses welcome” sign in the GI aisle
- “No live shots” sticker on the door
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
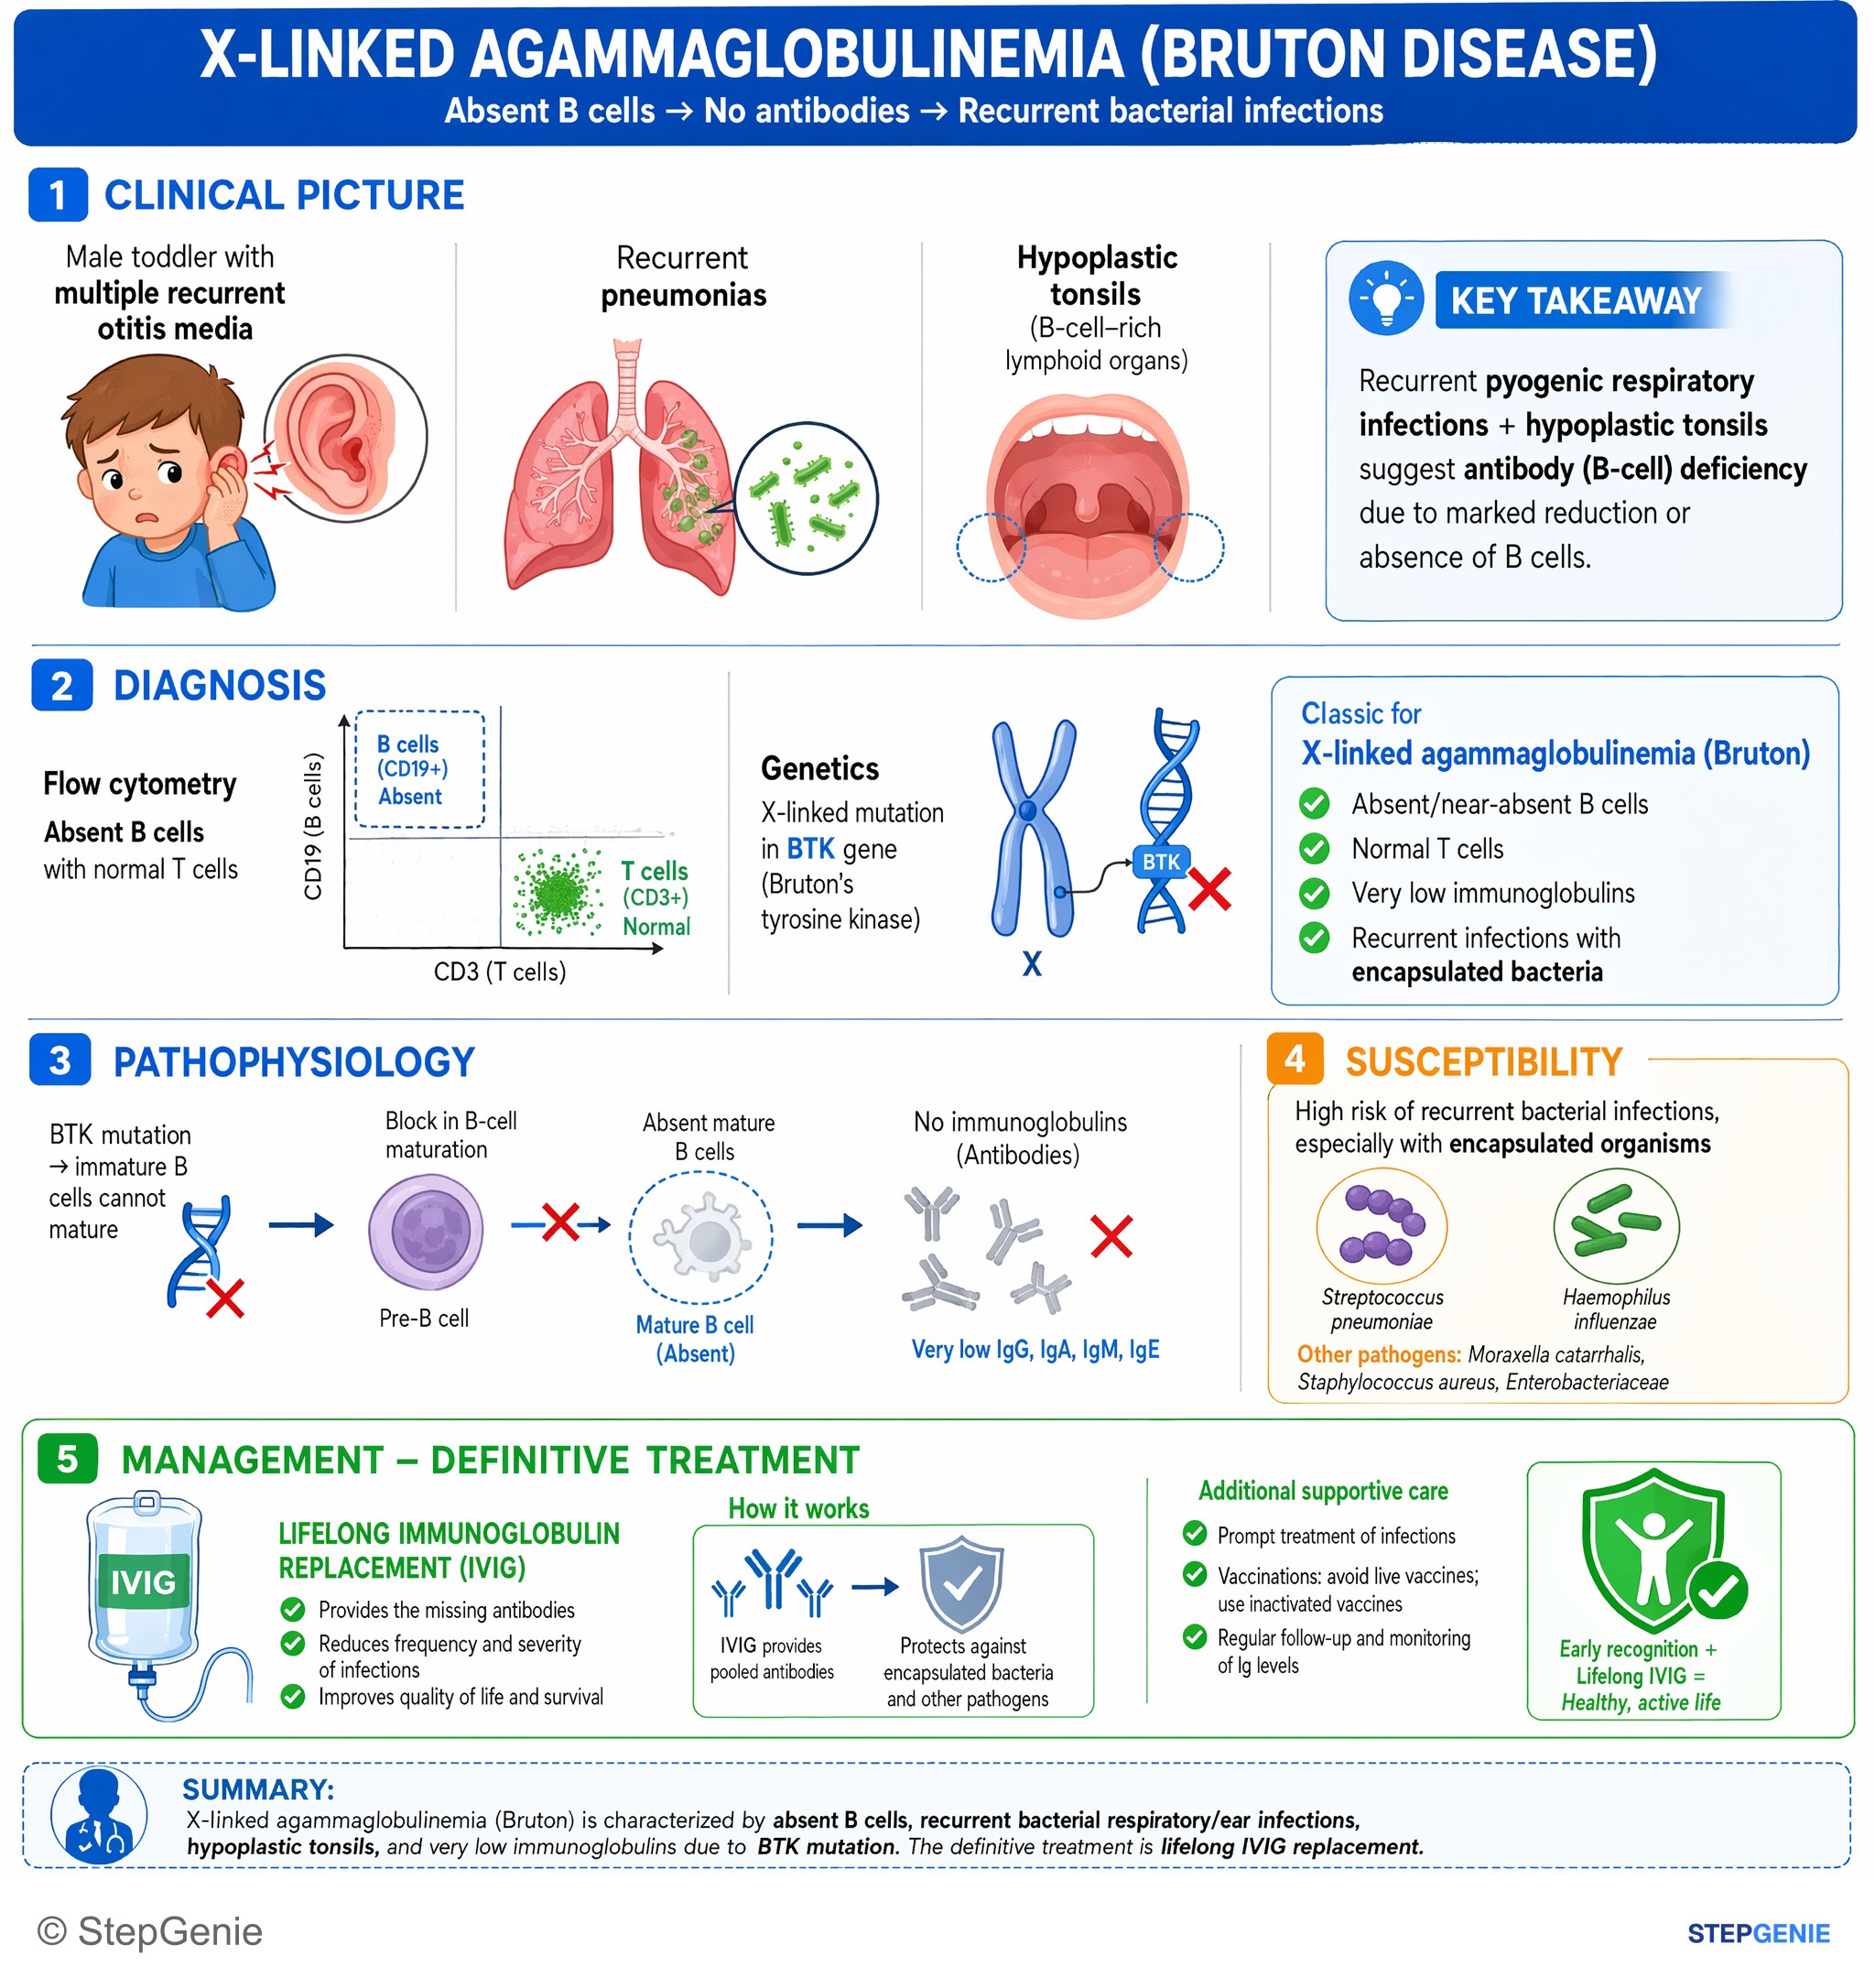
X-linked agammaglobulinemia (Bruton): absent B cells, recurrent bacterial respiratory/ear infections, hypoplastic tonsils → treat with…
USMLE Step 2Frequently Asked Questions
Why do symptoms of X-linked agammaglobulinemia usually start after 6 months?
Symptoms usually begin after about 6 months because maternal IgG protects the infant early on. Once that maternal antibody supply wanes, the child’s own humoral immune defect becomes apparent. In X-linked agammaglobulinemia, a BTK defect prevents B-cell maturation, so the infant cannot make normal immunoglobulins and then develops recurrent infections.
What is the mechanism of Bruton agammaglobulinemia?
Bruton agammaglobulinemia is caused by a BTK mutation that blocks B-cell maturation at the pre-B stage. BTK is required for pre-B cell receptor signaling in the bone marrow. The result is no mature B cells in peripheral blood, no plasma cells, and very low levels of all immunoglobulins, including IgG, IgA, and IgM.
How do you recognize X-linked agammaglobulinemia in a question stem?
A classic clue is a male infant with recurrent infections starting around 6 months, plus small or absent tonsils and lymph nodes. The lab pattern is decreased or absent B cells, such as absent CD19-positive cells on flow cytometry, with low levels of all immunoglobulins. Question stems may also mention absent germinal centers and recurrent bacterial or enteroviral infections.
What infections are classically seen in X-linked agammaglobulinemia?
The classic infections are recurrent infections with encapsulated bacteria, enteroviruses, and Giardia lamblia. Low IgG causes poor opsonization, which predisposes to organisms like Streptococcus pneumoniae and Haemophilus influenzae. Because humoral immunity is also important against enteroviruses, patients are vulnerable to polio, echovirus, and coxsackie, and low IgA can contribute to Giardia with chronic diarrhea and malabsorption.
How do you tell X-linked agammaglobulinemia from CVID or Hyper-IgM syndrome?
X-linked agammaglobulinemia is distinguished by early onset in a boy, absent B cells, and low levels of all immunoglobulins. CVID usually has later onset with B cells present but dysfunctional and low IgG with or without low IgA or IgM. Hyper-IgM syndrome instead has high IgM due to a class-switch defect and often presents with opportunistic infections.