Picture this: you’re cruising through your q-bank, feeling good… then a hepatitis question shows up and suddenly every virus feels the same. The trick is that hepatitis vignettes are built to make you mix up transmission, incubation, chronicity, and extrahepatic findings. This post walks through a classic clinical stem and then does what your review book can’t always do: make every answer choice teach you something.
Tag: Microbiology > Virology
The Clinical Vignette
A 24-year-old man presents with 4 days of fatigue, nausea, poor appetite, and right upper quadrant discomfort. He returned 3 weeks ago from a backpacking trip where he ate street food and drank untreated well water. Today he noticed dark urine and scleral icterus. He has no past medical history and takes no medications. He drinks alcohol socially.
Vitals are normal. Exam shows mild jaundice and RUQ tenderness without hepatosplenomegaly.
Labs:
- AST: 1,200 U/L
- ALT: 1,500 U/L
- Total bilirubin: 6.2 mg/dL
- ALP: mildly elevated
- INR: 1.1
Serology:
- Anti-HAV IgM: positive
- HBsAg: negative
- Anti-HBc IgM: negative
- Anti-HCV: negative
Question: Which of the following is the most likely cause of his illness?
A. Hepatitis A virus
B. Hepatitis B virus
C. Hepatitis C virus
D. Hepatitis D virus
E. Hepatitis E virus
Correct Answer: A. Hepatitis A virus (HAV)
Why HAV fits best
This is the “classic” acute hepatitis after fecal–oral exposure:
- Risk: travel + street food + untreated water
- Incubation: typically ~2–6 weeks (often memorized as ~4 weeks)
- Symptoms: abrupt onset, constitutional symptoms, then jaundice
- Serology: anti-HAV IgM positive = acute infection
- Course: does not become chronic
High-yield HAV facts (Step-friendly)
- Transmission: fecal–oral (contaminated food/water, daycare, close contacts)
- Chronicity: no chronic infection
- Severe disease: can cause fulminant hepatitis, especially older adults or underlying liver disease
- Prevention: inactivated vaccine; post-exposure prophylaxis with vaccine or immune globulin (timing-dependent)
Now, Why Each Distractor Is Wrong (and What It’s Trying to Teach You)
B. Hepatitis B virus (HBV)
Why it’s wrong here
- The stem screams fecal–oral travel exposure, not blood/sex/perinatal.
- Serologies are negative:
- HBsAg negative (no active infection marker)
- anti-HBc IgM negative (no acute HBV)
What HBV would look like instead (high-yield)
- Transmission: blood, sexual, perinatal
- Incubation: ~6 weeks to 6 months (often longer than HAV)
- Serologies to know cold:
- HBsAg = current infection (acute or chronic)
- anti-HBc IgM = acute infection / window period
- anti-HBs = immunity (vaccine or resolved infection)
- HBeAg = high infectivity (active replication)
The classic trap: the “window period”
- HBsAg negative and anti-HBs negative, but anti-HBc IgM positive.
C. Hepatitis C virus (HCV)
Why it’s wrong here
- HCV is less about “abrupt travel gastro illness” and more about:
- often asymptomatic acute infection
- high chronicity
- parenteral exposures (IV drug use, transfusions pre-1992, needlestick)
- Serology: anti-HCV negative in the vignette.
What HCV is really testing
- Transmission: blood > sex (IV drug use is #1)
- Chronicity: very high (major cause of cirrhosis, HCC)
- Extrahepatic associations (Step gold):
- Mixed cryoglobulinemia (palpable purpura, arthralgias, neuropathy, MPGN)
- Porphyria cutanea tarda
- Lichen planus
- Best test for active infection: HCV RNA (PCR)
- Anti-HCV can lag; PCR detects early infection.
D. Hepatitis D virus (HDV)
Why it’s wrong here
- HDV can’t infect you unless HBV is present (it’s a defective virus that requires HBsAg).
- This patient’s HBsAg is negative, making HDV essentially a non-starter.
How HDV shows up on exams
- Transmission: parenteral/sexual (like HBV)
- Requires HBV:
- Coinfection: HBV + HDV at same time (can be severe)
- Superinfection: HDV infects someone with chronic HBV → highest risk of fulminant hepatitis and cirrhosis
- Virology nugget: HDV is a defective, enveloped, circular negative-sense RNA virus that uses HBsAg for its envelope.
E. Hepatitis E virus (HEV)
Why it’s wrong here (subtle!) HEV does match fecal–oral + travel + water exposure, so why not E?
Because the question handed you the clincher:
- Anti-HAV IgM is positive → that’s acute HAV, period.
What HEV is trying to remind you
- Transmission: fecal–oral (especially contaminated water)
- Geography: classically associated with developing regions; outbreaks after flooding, refugee camps, poor sanitation
- High-yield differentiator: severe disease in pregnancy
- Risk of fulminant hepatitis is notably higher in pregnant patients (especially 3rd trimester)
- Usually no chronic infection, though chronicity can occur in immunocompromised patients (less commonly tested on USMLE than the pregnancy association).
Rapid Comparison Table (Exam Mode)
| Virus | Genome | Envelope | Transmission | Chronic? | Hallmark High-Yield Clue |
|---|---|---|---|---|---|
| HAV | +ssRNA | No | Fecal–oral | No | Travel/daycare, abrupt onset; anti-HAV IgM |
| HBV | Partially dsDNA (reverse transcriptase) | Yes | Blood/sex/perinatal | Yes | HBsAg, window period = anti-HBc IgM |
| HCV | +ssRNA | Yes | Blood (IVDU) | Yes (very common) | Cryoglobulinemia, PCT; confirm with HCV RNA |
| HDV | -ssRNA (defective) | Yes (HBsAg) | Blood/sex | Depends on HBV | Requires HBsAg; superinfection severe |
| HEV | +ssRNA | No | Fecal–oral (water) | Usually no | Pregnancy → fulminant hepatitis |
Q-Bank “Answer Choice Autopsy”: What the Question Writer Wanted
When hepatitis shows up in a vignette, you can usually solve it by forcing yourself to answer four mini-questions:
-
Transmission route?
- Fecal–oral: HAV/HEV
- Blood/sex/perinatal: HBV/HCV/HDV
-
Acute vs chronic tendency?
- Chronic common: HBV, HCV (HDV depends on HBV)
- Chronic absent: HAV (and typically HEV)
-
What’s the signature association?
- HCV: cryoglobulinemia, MPGN, PCT
- HEV: pregnancy severe
- HDV: requires HBV (HBsAg)
- HBV: window period patterns
-
What does the serology actually say?
- If you’re given anti-HAV IgM positive, you don’t need to philosophize—it’s HAV.
Take-Home High-Yield Pearls
- Anti-HAV IgM = acute HAV (think food/water, travel, daycare).
- HBV window period: only anti-HBc IgM is positive.
- HCV: highest chronicity; think extrahepatic immune complex disease; confirm with HCV RNA.
- HDV requires HBV (HBsAg); superinfection is nastiest.
- HEV: fecal–oral waterborne; pregnancy → fulminant hepatitis is the board-style giveaway.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
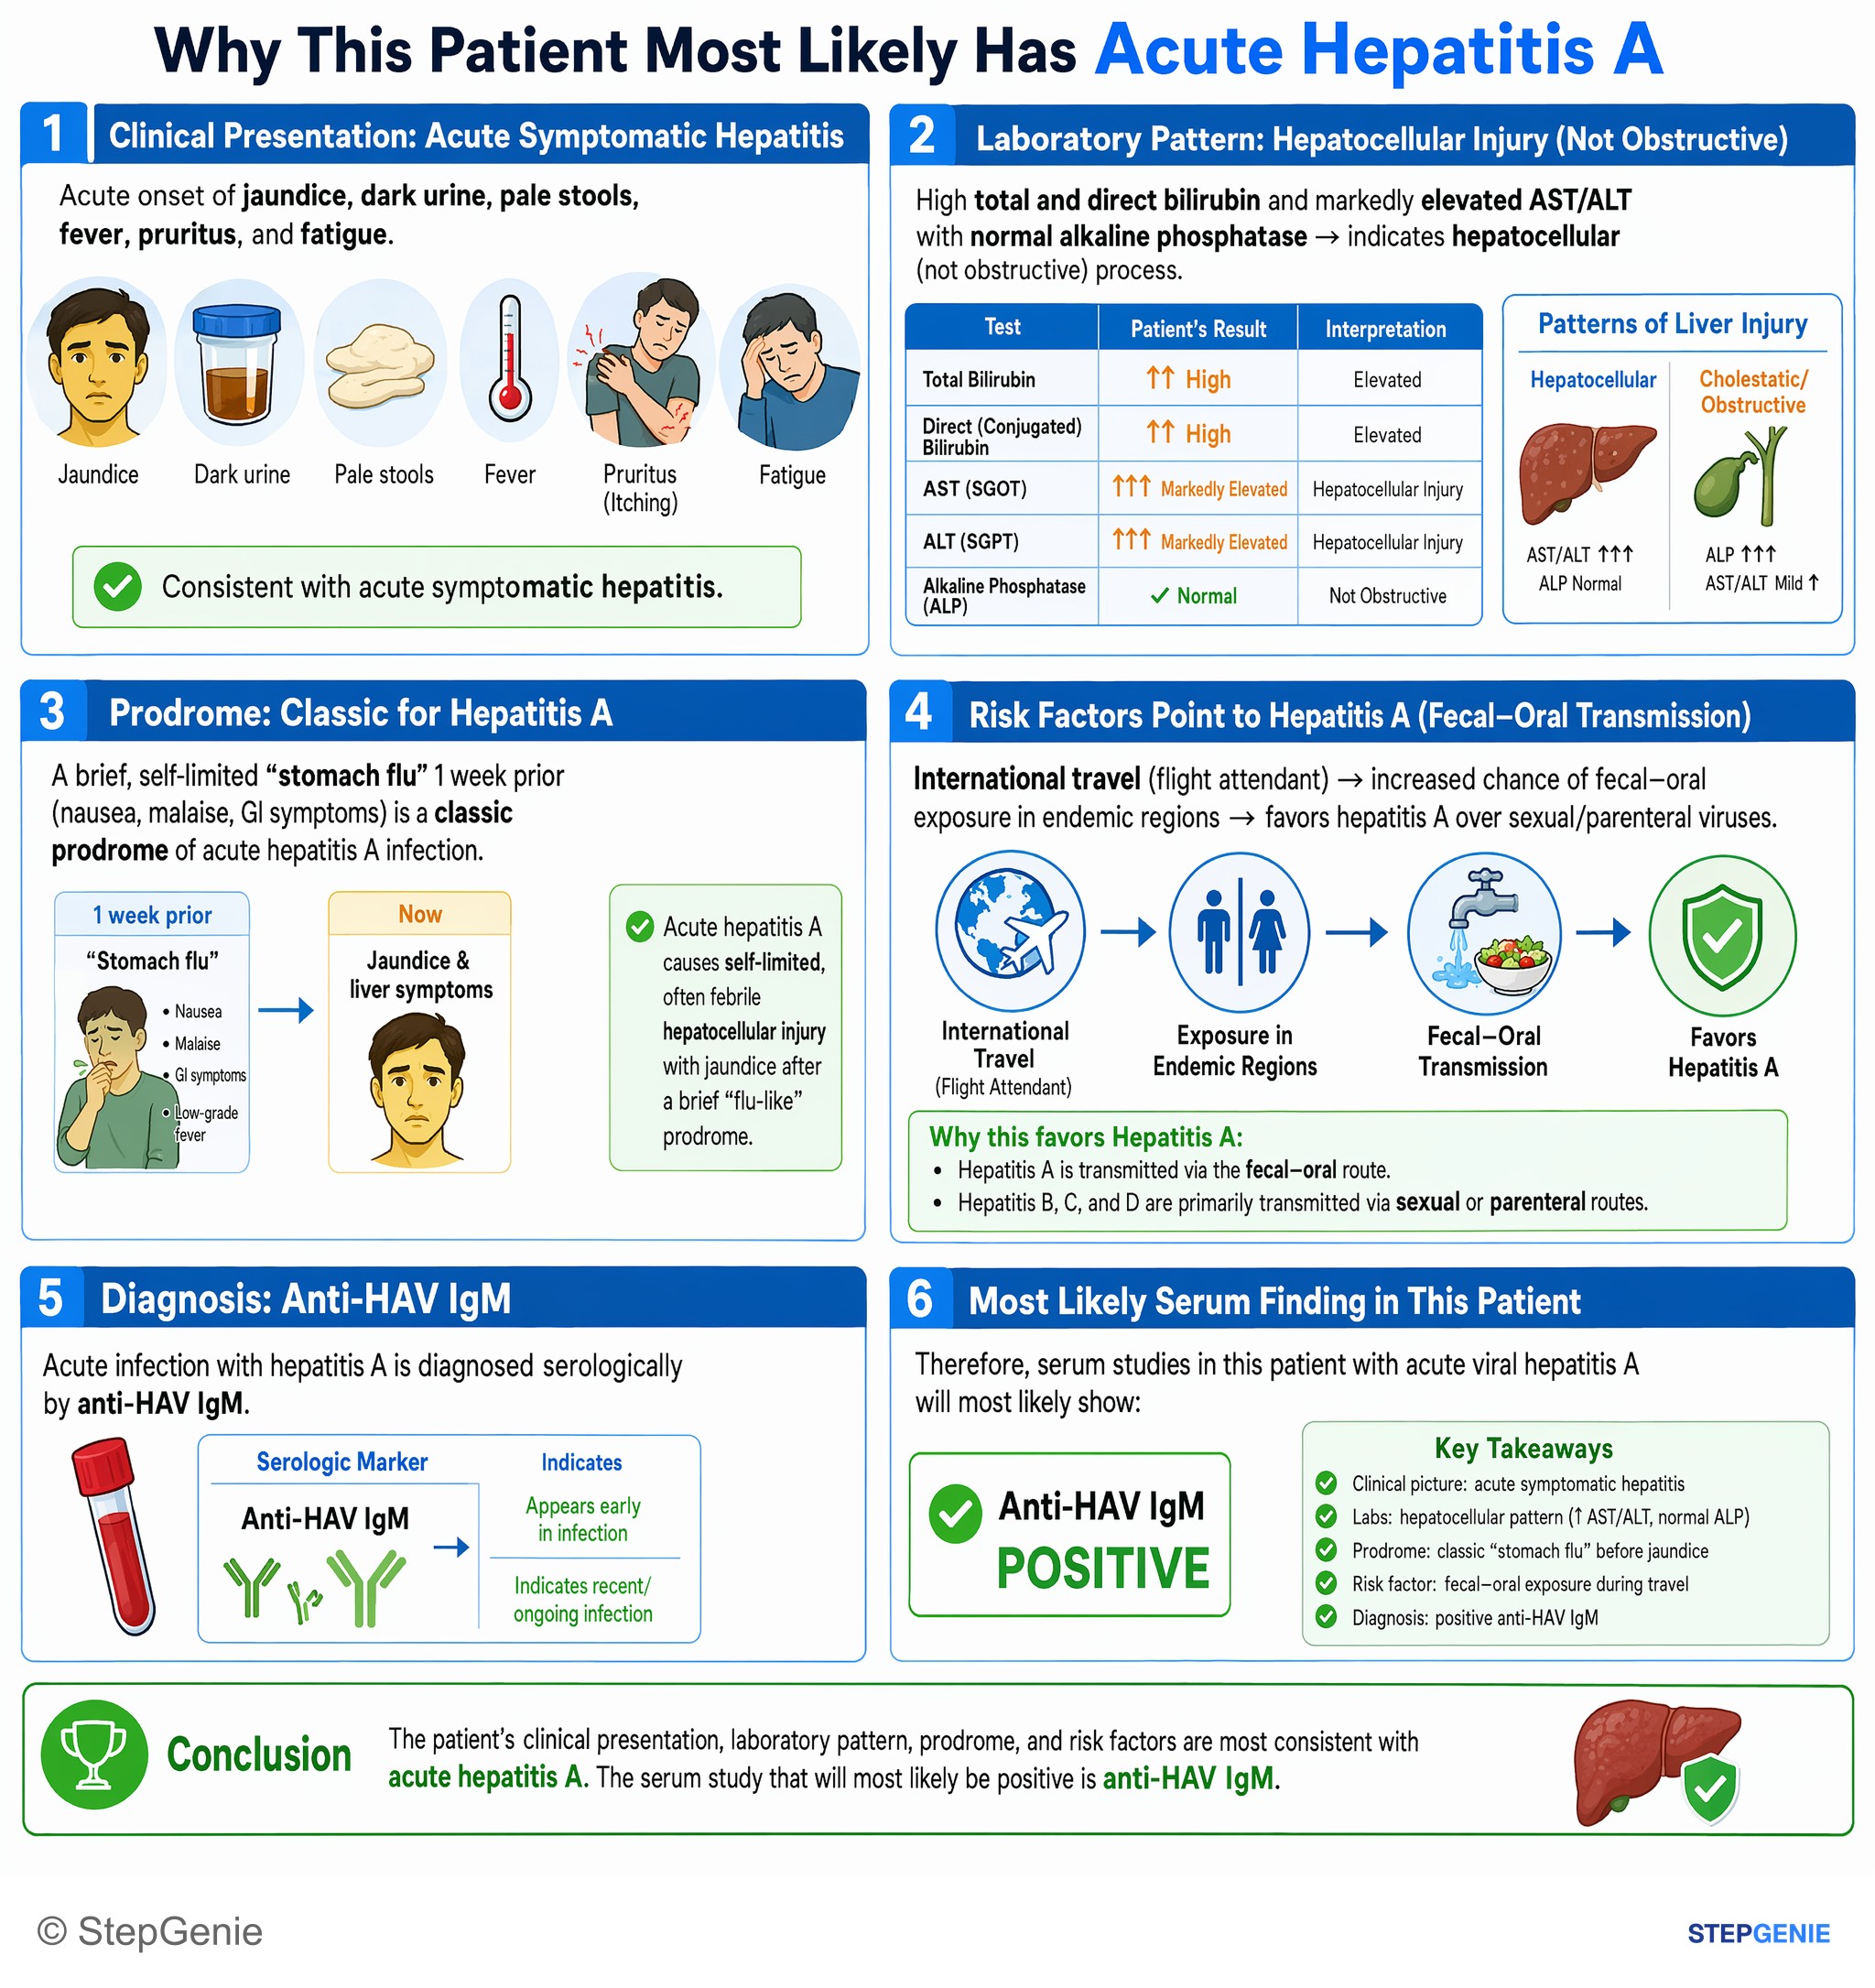
Acute hepatitis A causes self-limited, often febrile hepatocellular injury with jaundice after a brief “flu-like” prodrome; labs show…
USMLE Step 1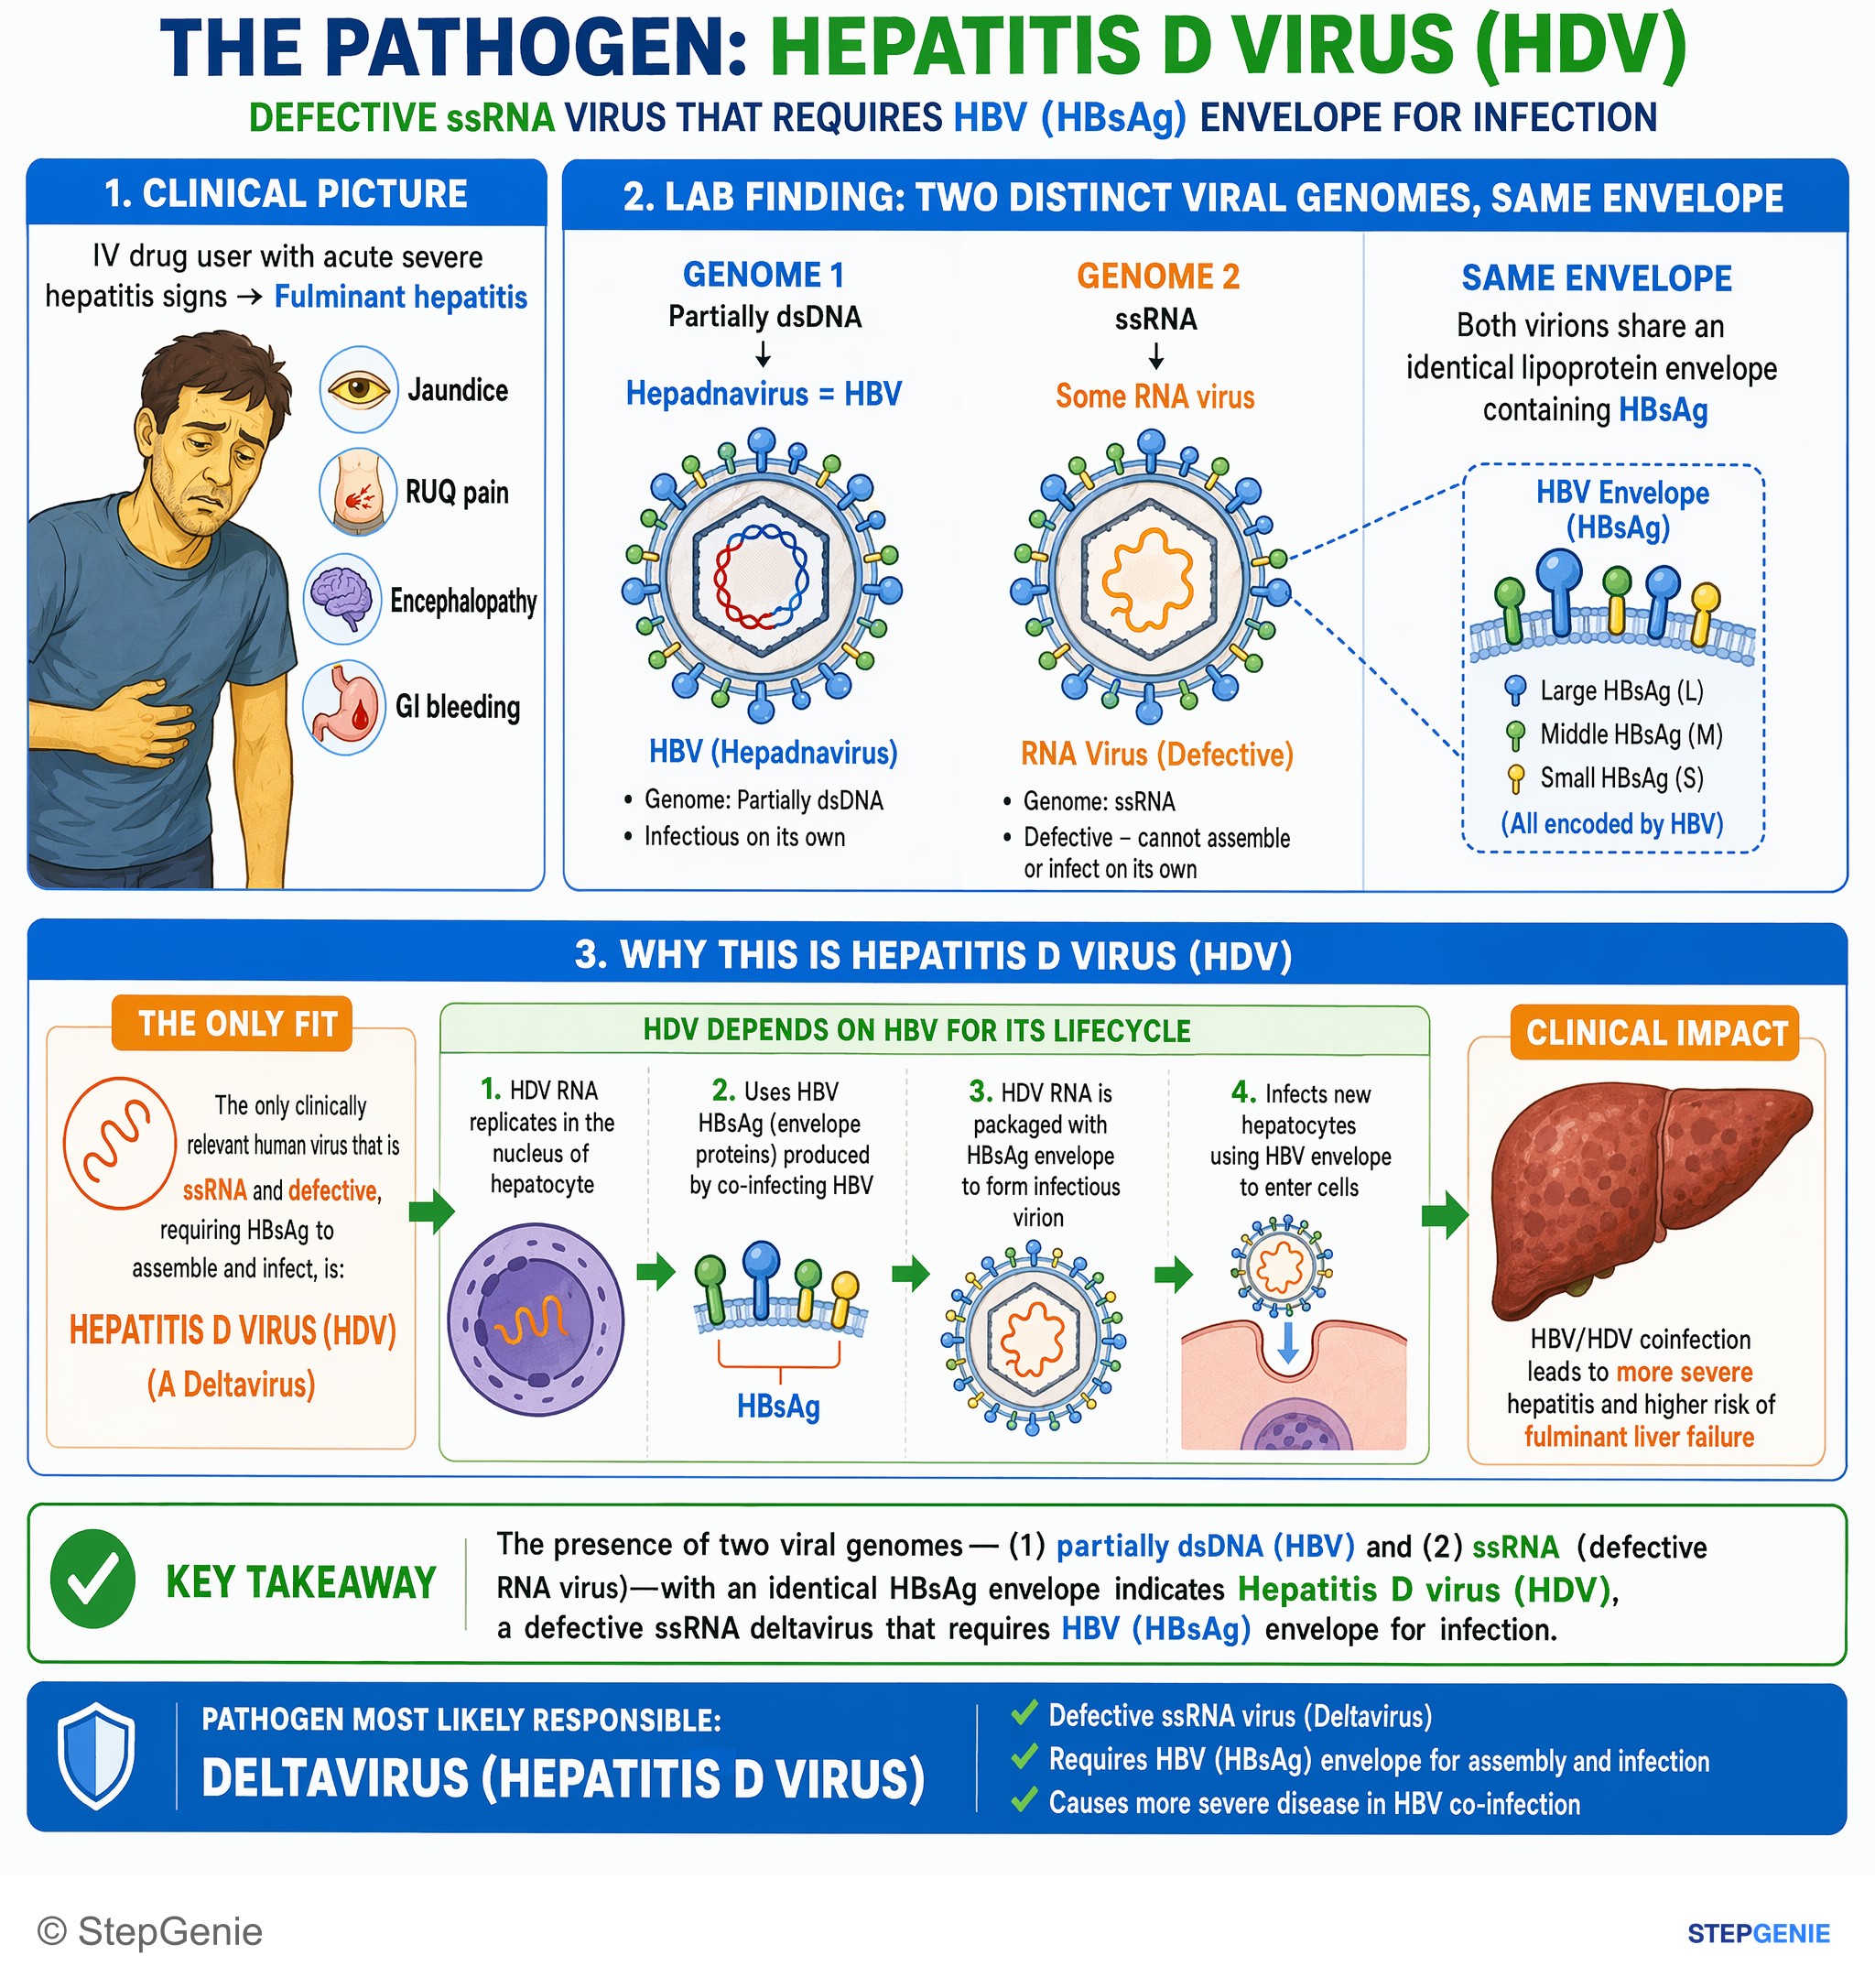
Hepatitis D virus is a defective ssRNA deltavirus that requires HBsAg envelope from HBV (partially dsDNA hepadnavirus) for infection…
USMLE Step 1Frequently Asked Questions
Why is hepatitis A the most likely cause in a traveler with jaundice after street food and untreated water?
Hepatitis A is the best answer because the exposure pattern and serology fit acute HAV. Fecal–oral transmission from contaminated food or water, a typical incubation of about 2 to 6 weeks, abrupt constitutional symptoms followed by jaundice, and a positive anti-HAV IgM all point to acute hepatitis A infection rather than the other hepatitis viruses.
How do you tell hepatitis A from hepatitis E on a vignette with travel and contaminated water exposure?
The key distinction here is serology. Both hepatitis A and hepatitis E can follow fecal–oral exposure during travel with contaminated water, but a positive anti-HAV IgM identifies acute hepatitis A. Hepatitis E is classically associated with contaminated water in developing regions and is especially high-yield because it can cause more severe fulminant hepatitis in pregnancy.
What serology pattern suggests acute hepatitis B or the HBV window period?
Acute hepatitis B is suggested by HBsAg positivity and anti-HBc IgM positivity, while the window period is identified by anti-HBc IgM positivity with both HBsAg and anti-HBs negative. These patterns matter because HBV is tested heavily through serologies, and anti-HBc IgM is the marker that helps catch acute infection even when surface antigen has disappeared.
Why is hepatitis D ruled out when HBsAg is negative?
Hepatitis D is ruled out because it cannot infect on its own and requires hepatitis B surface antigen to be present. HDV is a defective virus that uses HBsAg for its envelope, so a negative HBsAg makes HDV essentially impossible in this case. On exams, this is the core clue that excludes hepatitis D quickly.
What makes hepatitis C different from the other hepatitis viruses on exam questions?
Hepatitis C is distinguished by blood-borne transmission, very high chronicity, and classic extrahepatic associations. It is more linked to parenteral exposures such as IV drug use than to abrupt travel-related gastroenteric illness, and high-yield clues include mixed cryoglobulinemia, porphyria cutanea tarda, and lichen planus. The best test for active infection is HCV RNA by PCR.