You just missed a question on B-cell activation and class switching—and it felt unfair because “they all sounded kind of right.” That’s exactly why these vignettes are high-yield: they test whether you can map one clinical clue to the one immunologic step it points to. Let’s break down a classic scenario the way USMLE wants you to think: what’s happening mechanistically, what’s the correct answer, and why every distractor is tempting (but wrong).
Tag: Immunology > Innate & Adaptive Immunity
The Clinical Vignette (Q-bank style)
A 6-year-old boy has recurrent sinopulmonary infections with Streptococcus pneumoniae and Haemophilus influenzae. His labs show:
- Normal total B-cell count (CD19+ cells present)
- Increased IgM
- Decreased IgG, IgA, IgE
- Absent germinal centers on lymph node biopsy
Which process is most directly impaired?
A. Activation-induced cytidine deaminase (AID)–mediated somatic hypermutation
B. CD40–CD40L interaction between B cells and T helper cells
C. C3b opsonization of encapsulated organisms
D. Thymic negative selection of T cells
E. NADPH oxidase–dependent respiratory burst
Step 1: Identify the Pattern in One Sentence
This is Hyper-IgM syndrome due to defective class switching: high IgM + low other isotypes + absent germinal centers, often with recurrent pyogenic infections (and sometimes opportunistic infections depending on the subtype).
Correct Answer: B. CD40–CD40L interaction between B cells and T helper cells
Why this is correct
Most classic vignettes like this are pointing to defective T-dependent B-cell activation, specifically:
- CD40 (on B cell) binding CD40L/CD154 (on activated Th cells)
- This interaction is required for:
- Class switch recombination (CSR) (IgM → IgG/IgA/IgE)
- Germinal center formation
- High-affinity antibody responses (in conjunction with somatic hypermutation)
High-yield mechanism
- In T-dependent responses, the B cell presents antigen on MHC II to a Tfh/Th cell, receives:
- CD40–CD40L costimulation
- Cytokines that determine isotype (e.g., IL-4 → IgE; TGF-β → IgA)
Classic associations to remember
- X-linked Hyper-IgM: CD40L mutation (T cell problem)
- Can’t class switch → ↑ IgM, ↓ IgG/IgA/IgE
- Absent germinal centers
- Susceptible to opportunistic infections (because CD40L is also important for macrophage activation via Th1 signaling)
The Decision Tree: Where Does the Problem Live?
| Finding | Points to… | Why it matters |
|---|---|---|
| Normal B-cell count | Not a B-cell development failure | Rules out agammaglobulinemia patterns |
| ↑ IgM with ↓ IgG/IgA/IgE | Class switching defect | CSR is failing |
| Absent germinal centers | Failed T-dependent activation | Germinal centers require T cell help |
| Recurrent encapsulated infections | Poor opsonizing IgG | Encapsulated bacteria need IgG/C3b for clearance |
Now Kill the Distractors (One by One)
A. AID-mediated somatic hypermutation
Why it’s tempting: AID is famous for “maturation” of antibodies and is involved in germinal center processes.
Why it’s wrong here (most likely): This stem screams CD40L/CD40 (absent germinal centers + classic Hyper-IgM phenotype). That said, AID deficiency can also cause a Hyper-IgM picture—so the differentiator is what the question emphasizes.
Key distinction
- AID deficiency (autosomal recessive Hyper-IgM):
- Defect in class switch recombination and somatic hypermutation
- Typically no high-affinity antibodies
- But many exam items that want AID will explicitly mention failure of affinity maturation, lack of somatic hypermutation, or large germinal centers with nonfunctional hyperplasia depending on phrasing.
- CD40L/CD40 defect:
- T cell help is missing → germinal centers are absent/poorly formed
- More likely to include opportunistic infections (macrophage activation issues)
USMLE takeaway:
- CD40L/CD40 = can’t get T-dependent B-cell activation going.
- AID = can’t execute the DNA editing for switching/mutation even if activation happens.
C. C3b opsonization of encapsulated organisms
Why it’s tempting: Encapsulated organisms show up, and opsonization is crucial.
Why it’s wrong: Complement defects classically cause:
- Low C3 (or abnormal CH50/AH50 patterns)
- Recurrent infections, but not the signature “↑ IgM, ↓ IgG/IgA/IgE” pattern or absent germinal centers.
High-yield complement mini-map
- C3 deficiency → severe recurrent pyogenic infections + type III hypersensitivity
- C5–C9 deficiency → Neisseria
- C1 esterase inhibitor deficiency → hereditary angioedema
Here, the labs scream isotype problem, not complement.
D. Thymic negative selection of T cells
Why it’s tempting: You see “T cell” and think “central tolerance.”
Why it’s wrong: Negative selection failure → autoimmunity, not isolated inability to class switch.
Examples:
- AIRE mutation (APS-1): failure of negative selection in thymus due to impaired expression of peripheral antigens → chronic mucocutaneous candidiasis, hypoparathyroidism, adrenal insufficiency.
- FOXP3 mutation (IPEX): defective Tregs → severe autoimmunity, eczema, diarrhea.
This vignette is about humoral immunodeficiency, not tolerance.
E. NADPH oxidase–dependent respiratory burst
Why it’s tempting: Recurrent infections in a child can trigger the “phagocyte defects” reflex.
Why it’s wrong: NADPH oxidase deficiency = Chronic Granulomatous Disease (CGD):
- Catalase-positive organisms (e.g., S. aureus, Burkholderia, Serratia, Nocardia, Aspergillus)
- Abnormal DHR test (or NBT)
- Granulomas, deep-seated infections
- No characteristic “high IgM, low others” pattern
Here the organisms (S. pneumo, H. flu) and immunoglobulin profile point to opsonization problems from low IgG, not neutrophil oxidative burst failure.
High-Yield Core Concepts (USMLE Gold)
1) T-dependent vs T-independent antigen responses
T-dependent antigens (proteins):
- Require T cell help
- Produce class switching, affinity maturation, memory
- Occur in germinal centers
T-independent antigens (polysaccharides, LPS):
- Activate B cells without T-cell help (often via TLRs)
- Mostly IgM
- Minimal memory and class switching
This is why encapsulated bacteria (polysaccharide capsules) are a problem when your system can’t make strong IgG responses.
2) What actually triggers class switching?
Class switching requires:
- CD40–CD40L
- Cytokines to select isotype
- AID to do DNA recombination at switch regions
Cytokine → isotype associations (common USMLE)
- IL-4 → IgE (and IgG subclasses)
- IFN-γ → opsonizing IgG (macrophage activation vibe)
- TGF-β (± IL-5) → IgA
3) Why “absent germinal centers” is a major clue
Germinal centers are where B cells:
- proliferate (clonal expansion),
- undergo somatic hypermutation (affinity maturation),
- undergo class switch recombination,
- differentiate into plasma cells and memory B cells.
If germinal centers are absent, think: no effective T-dependent B-cell activation (often CD40L problems).
Rapid-Fire Exam Tips (What they love to ask)
-
Hyper-IgM (CD40L mutation):
- ↑ IgM, ↓ IgG/IgA/IgE
- Absent germinal centers
- Pyogenic infections + possible opportunistic infections (e.g., Pneumocystis, Cryptosporidium)
-
AID deficiency:
- Also hyper-IgM pattern
- Emphasis on no affinity maturation / defective somatic hypermutation
-
Common variable immunodeficiency (CVID):
- Low IgG and low IgA (sometimes low IgM)
- Usually later presentation (teens/adulthood)
- Normal/low B cells, poor plasma cell differentiation
-
X-linked agammaglobulinemia (Bruton):
- Low/absent B cells, low all Igs
- No tonsils/lymph nodes
One-Line Summary You Can Use on Test Day
High IgM + low IgG/IgA/IgE + absent germinal centers = failed T-dependent B-cell activation → think CD40–CD40L (Hyper-IgM).
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
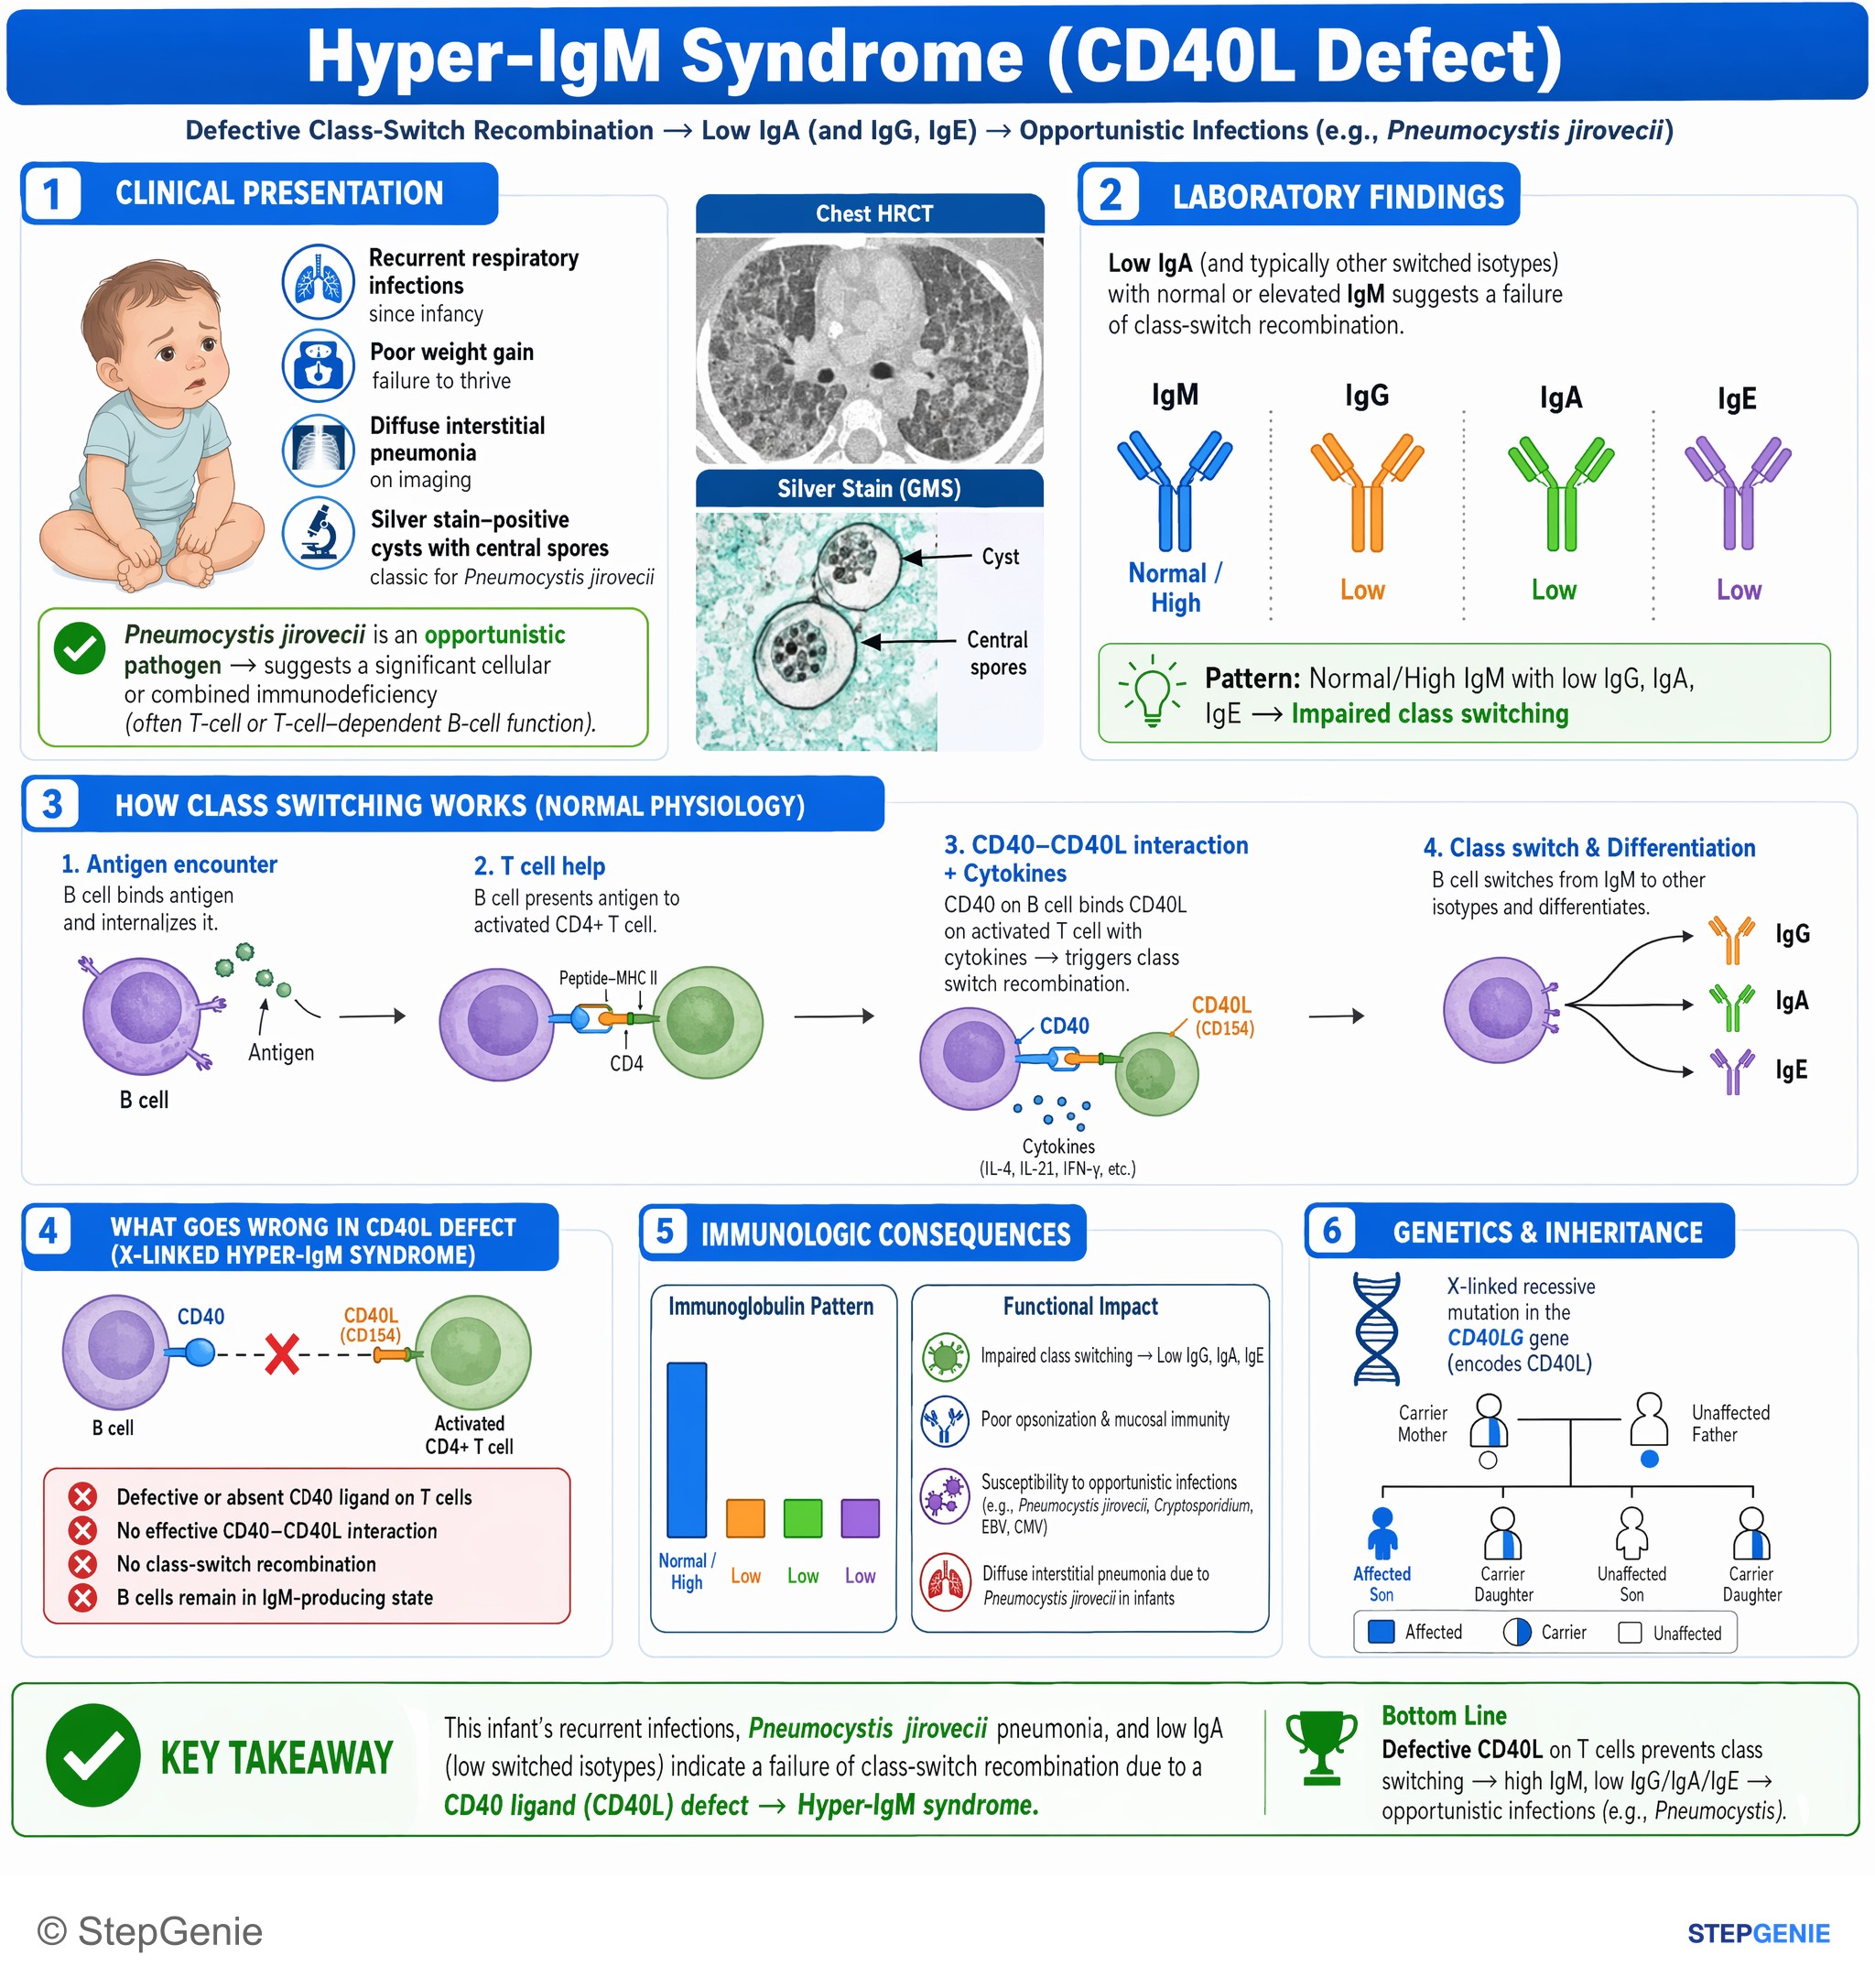
Hyper-IgM syndrome (CD40L defect) → impaired class switching, low IgA, opportunistic infections (e.g., Pneumocystis jirovecii) with…
USMLE Step 1Frequently Asked Questions
What immunodeficiency does high IgM with low IgG, IgA, and IgE plus absent germinal centers suggest?
This pattern suggests Hyper-IgM syndrome due to defective class switching. The key clues are increased IgM with decreased other isotypes, normal total B-cell count, and absent germinal centers. That combination points to a failure of T-dependent B-cell activation rather than a B-cell development problem, often presenting with recurrent pyogenic infections such as Streptococcus pneumoniae and Haemophilus influenzae.
Why does a CD40-CD40L defect cause absent germinal centers and failure of class switching?
A CD40-CD40L defect blocks the T-cell help B cells need for T-dependent activation. CD40 on B cells must bind CD40L on activated T helper cells to trigger class switch recombination, germinal center formation, and high-affinity antibody responses. Without that interaction, B cells remain stuck making IgM instead of switching to IgG, IgA, or IgE, and germinal centers are absent or poorly formed.
How do you tell CD40L deficiency from AID deficiency in a Hyper-IgM question?
The best way to distinguish them is by what the stem emphasizes. CD40L or CD40 defects point to failed T-dependent activation, so questions often highlight absent germinal centers and may include opportunistic infections. AID deficiency also causes a Hyper-IgM pattern, but stems that want AID usually emphasize failure of affinity maturation, lack of somatic hypermutation, or large germinal centers with nonfunctional hyperplasia.
Why are recurrent infections with encapsulated bacteria a clue to a class-switching defect?
Recurrent encapsulated bacterial infections are a clue because these organisms are cleared best with effective opsonization, especially by IgG and C3b. In a class-switching defect, IgG is low while IgM is high, so the patient has poor opsonizing antibody function. That makes organisms like Streptococcus pneumoniae and Haemophilus influenzae a classic clinical clue when paired with the immunoglobulin pattern.
Why is C3b opsonization not the best answer when the vignette includes encapsulated organisms?
C3b opsonization is not the best answer because the lab pattern points to an isotype-switching problem rather than a complement defect. Complement deficiencies can cause recurrent infections, but they do not give the classic combination of increased IgM, decreased IgG, IgA, and IgE, along with absent germinal centers. Those findings specifically support defective T-dependent B-cell activation and class switching.