You’re cruising through a Q-bank block and then it happens: a young patient with palpitations, a “weird” ECG, and answer choices that all sound kind of right. Wolff-Parkinson-White (WPW) is exactly the kind of topic where one clue flips the entire management plan, and where distractors are designed to punish pattern-matching. Let’s break it down the way test writers think—why the right answer is right, and why every wrong answer is wrong.
Tag
Cardiovascular > ECG Interpretation
The Vignette (Classic Q-bank Style)
A 23-year-old man comes to the ED for sudden-onset palpitations and lightheadedness. Episodes start and stop abruptly. No chest pain. Vitals: BP 118/74, HR 190/min, RR 16. He is anxious but alert. During one episode, ECG shows a narrow-complex tachycardia at 190/min, regular rhythm. After vagal maneuvers, he converts to sinus rhythm. Post-conversion ECG shows short PR interval and a slurred upstroke of the QRS.
Question: What is the underlying mechanism, and what medication should be avoided if he develops an irregular wide-complex tachycardia?
Step 1: Read the ECG Clues Like a Test Writer
Baseline (sinus rhythm) ECG findings in WPW
WPW = accessory pathway (Bundle of Kent) allowing atria → ventricles conduction outside the AV node.
Hallmark ECG triad (sinus rhythm):
- Short PR (< 120 ms): ventricles get activated early
- Delta wave: slurred upstroke of QRS (early ventricular depolarization)
- Wide QRS (often > 120 ms): fusion of early accessory + normal His-Purkinje conduction
Tachyarrhythmias associated with WPW
- AVRT (atrioventricular reentrant tachycardia): most common symptomatic tachyarrhythmia
- Often orthodromic AVRT → narrow-complex regular tachycardia (down AV node, up accessory)
- Atrial fibrillation with WPW: can become irregular wide-complex and dangerously fast
- Because the accessory pathway can conduct very rapidly to ventricles → risk of VF
The Correct Answer (What They Want)
Mechanism
Re-entrant tachycardia involving an accessory pathway (Bundle of Kent) that bypasses the AV node.
Why it matters: The AV node is normally a “rate limiter.” WPW creates a second highway with no toll booth.
Medication to avoid in irregular wide-complex tachycardia suspicious for AF + WPW
Avoid AV nodal blockers, because blocking the AV node forces more conduction through the accessory pathway → even faster ventricular rates → degeneration into ventricular fibrillation.
AV nodal blockers to avoid (high-yield list):
- Adenosine
- Beta-blockers
- Non-DHP calcium channel blockers (verapamil, diltiazem)
- Digoxin
- (Often also taught: amiodarone is controversial in pre-excited AF; many test resources prefer avoiding it and using procainamide/ibutilide instead.)
What to use instead (if stable):
- Procainamide or ibutilide for AF + WPW
If unstable: immediate synchronized cardioversion.
The Distractors: Why Each Wrong Answer Is Wrong (and When It Would Be Right)
Below is a “distractor autopsy.” Q-banks love these.
1) Adenosine
Why it’s tempting: Adenosine is first-line for regular narrow SVT (like AVNRT/orthodromic AVRT).
Why it’s wrong in the dangerous scenario: If the rhythm is irregular wide-complex (think AF + WPW), adenosine blocks the AV node and may accelerate conduction through the accessory pathway.
When adenosine is correct:
- Stable, regular, narrow-complex tachycardia (likely AVNRT or orthodromic AVRT)
- Can be used diagnostically/therapeutically after vagal maneuvers
USMLE pearl: Adenosine is “safe” in many SVTs—but not in pre-excited AF.
2) Verapamil / Diltiazem (Non-DHP CCBs)
Why it’s tempting: They slow AV nodal conduction and are common for SVT rate control.
Why it’s wrong here: Same AV nodal blocker problem—can precipitate VF in AF + WPW.
When they are correct:
- Rate control for atrial fibrillation without WPW
- Certain SVTs where AV node is the key player (in stable patients)
3) Beta-blockers
Why it’s tempting: “Rate control” reflex for tachycardias.
Why it’s wrong here: AV node suppression → preferential accessory pathway conduction in AF + WPW.
When they are correct:
- Rate control in typical AF/flutter (no WPW)
- Certain SVTs, symptomatic PVCs, hyperthyroid-related tachycardia
4) Digoxin
Why it’s tempting: Another AF rate-control drug.
Why it’s wrong here (high-yield):
- Digoxin increases vagal tone → slows AV node → can promote accessory conduction
- Classic board warning: digoxin is contraindicated in WPW with AF
When it’s correct:
- AF rate control in select patients with heart failure (not first-line in many acute settings)
- Symptomatic HFrEF (historically; now less common)
5) Amiodarone
Why it’s tempting: Broad “antiarrhythmic hammer.”
Why it’s often marked wrong: Many exam frameworks emphasize procainamide/ibutilide for AF + WPW. Amiodarone can have AV nodal blocking effects and has been associated with adverse outcomes in pre-excited AF in some settings.
In a test question, if procainamide is an option, it’s usually the intended answer.
When it may be used:
- Various ventricular and supraventricular arrhythmias depending on context/protocol
- But for pre-excited AF, boards typically push procainamide or cardioversion
6) Procainamide
Why it’s correct (if that’s the choice):
- Class IA: blocks Na channels and prolongs repolarization
- Slows conduction in accessory pathway
- Stabilizes pre-excited AF by preventing dangerously rapid ventricular rates
When to use:
- Stable AF with WPW (irregular wide-complex tachycardia)
- Some stable wide-complex tachycardias when WPW is suspected
7) Synchronized cardioversion
Why it’s correct in a different branch of the algorithm: If unstable (hypotension, altered mental status, shock, ischemic chest pain, acute heart failure), don’t overthink meds.
Indications (high-yield):
- Unstable SVT, AF/flutter with RVR, VT with a pulse (if unstable)
Quick ECG Pattern Table (Memorize This)
| Rhythm/ECG Pattern | Regular? | QRS Width | Think | Best Next Step (Stable) | Avoid |
|---|---|---|---|---|---|
| AVNRT / orthodromic AVRT | Regular | Narrow | SVT | Vagal → adenosine | — |
| Sinus rhythm with WPW | Regular | Often wide with delta | Pre-excitation | No acute tx unless symptomatic | — |
| AF with WPW (“pre-excited AF”) | Irregular | Wide (often varying) | Dangerous | Procainamide or ibutilide | AV nodal blockers |
| Unstable tachyarrhythmia | Variable | Variable | Hemodynamic compromise | Synchronized cardioversion | Delay |
High-Yield Facts USMLE Loves About WPW
1) The anatomy/mechanism
- Accessory pathway = Bundle of Kent
- Bypasses AV node → pre-excitation and re-entry circuits
2) The ECG
- Short PR, delta wave, wide QRS
- In tachycardia:
- Orthodromic AVRT = narrow regular
- Antidromic AVRT = wide regular (less common)
3) The dangerous scenario: AF + WPW
- Presents as irregular wide-complex tachycardia
- Ventricular rates can be extremely fast
- Risk: VF → sudden death
- Treat stable: procainamide/ibutilide
- Treat unstable: synchronized cardioversion
- Avoid: AV nodal blockers (adenosine, beta-blockers, non-DHP CCBs, digoxin)
4) Definitive management (when they ask “long-term”)
- Catheter ablation of the accessory pathway is curative and often recommended for symptomatic patients
How to Not Get Tricked: A 10-Second Test-Day Checklist
- Do you see delta wave + short PR on baseline ECG? → WPW pattern.
- Is the tachycardia irregular and wide? → Assume AF + WPW until proven otherwise.
- In AF + WPW: NO AV nodal blockers. Use procainamide (or cardiovert if unstable).
- If it’s regular narrow SVT and patient is stable: vagal → adenosine is reasonable.
Wrap-Up
WPW questions aren’t just “recognize the delta wave.” They’re really testing whether you understand the AV node’s protective role—and how blocking it can be lethal when an accessory pathway is present. Once you anchor on the rhythm description (regular vs irregular, narrow vs wide) the correct choice—and the reason each distractor is wrong—becomes much more predictable.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
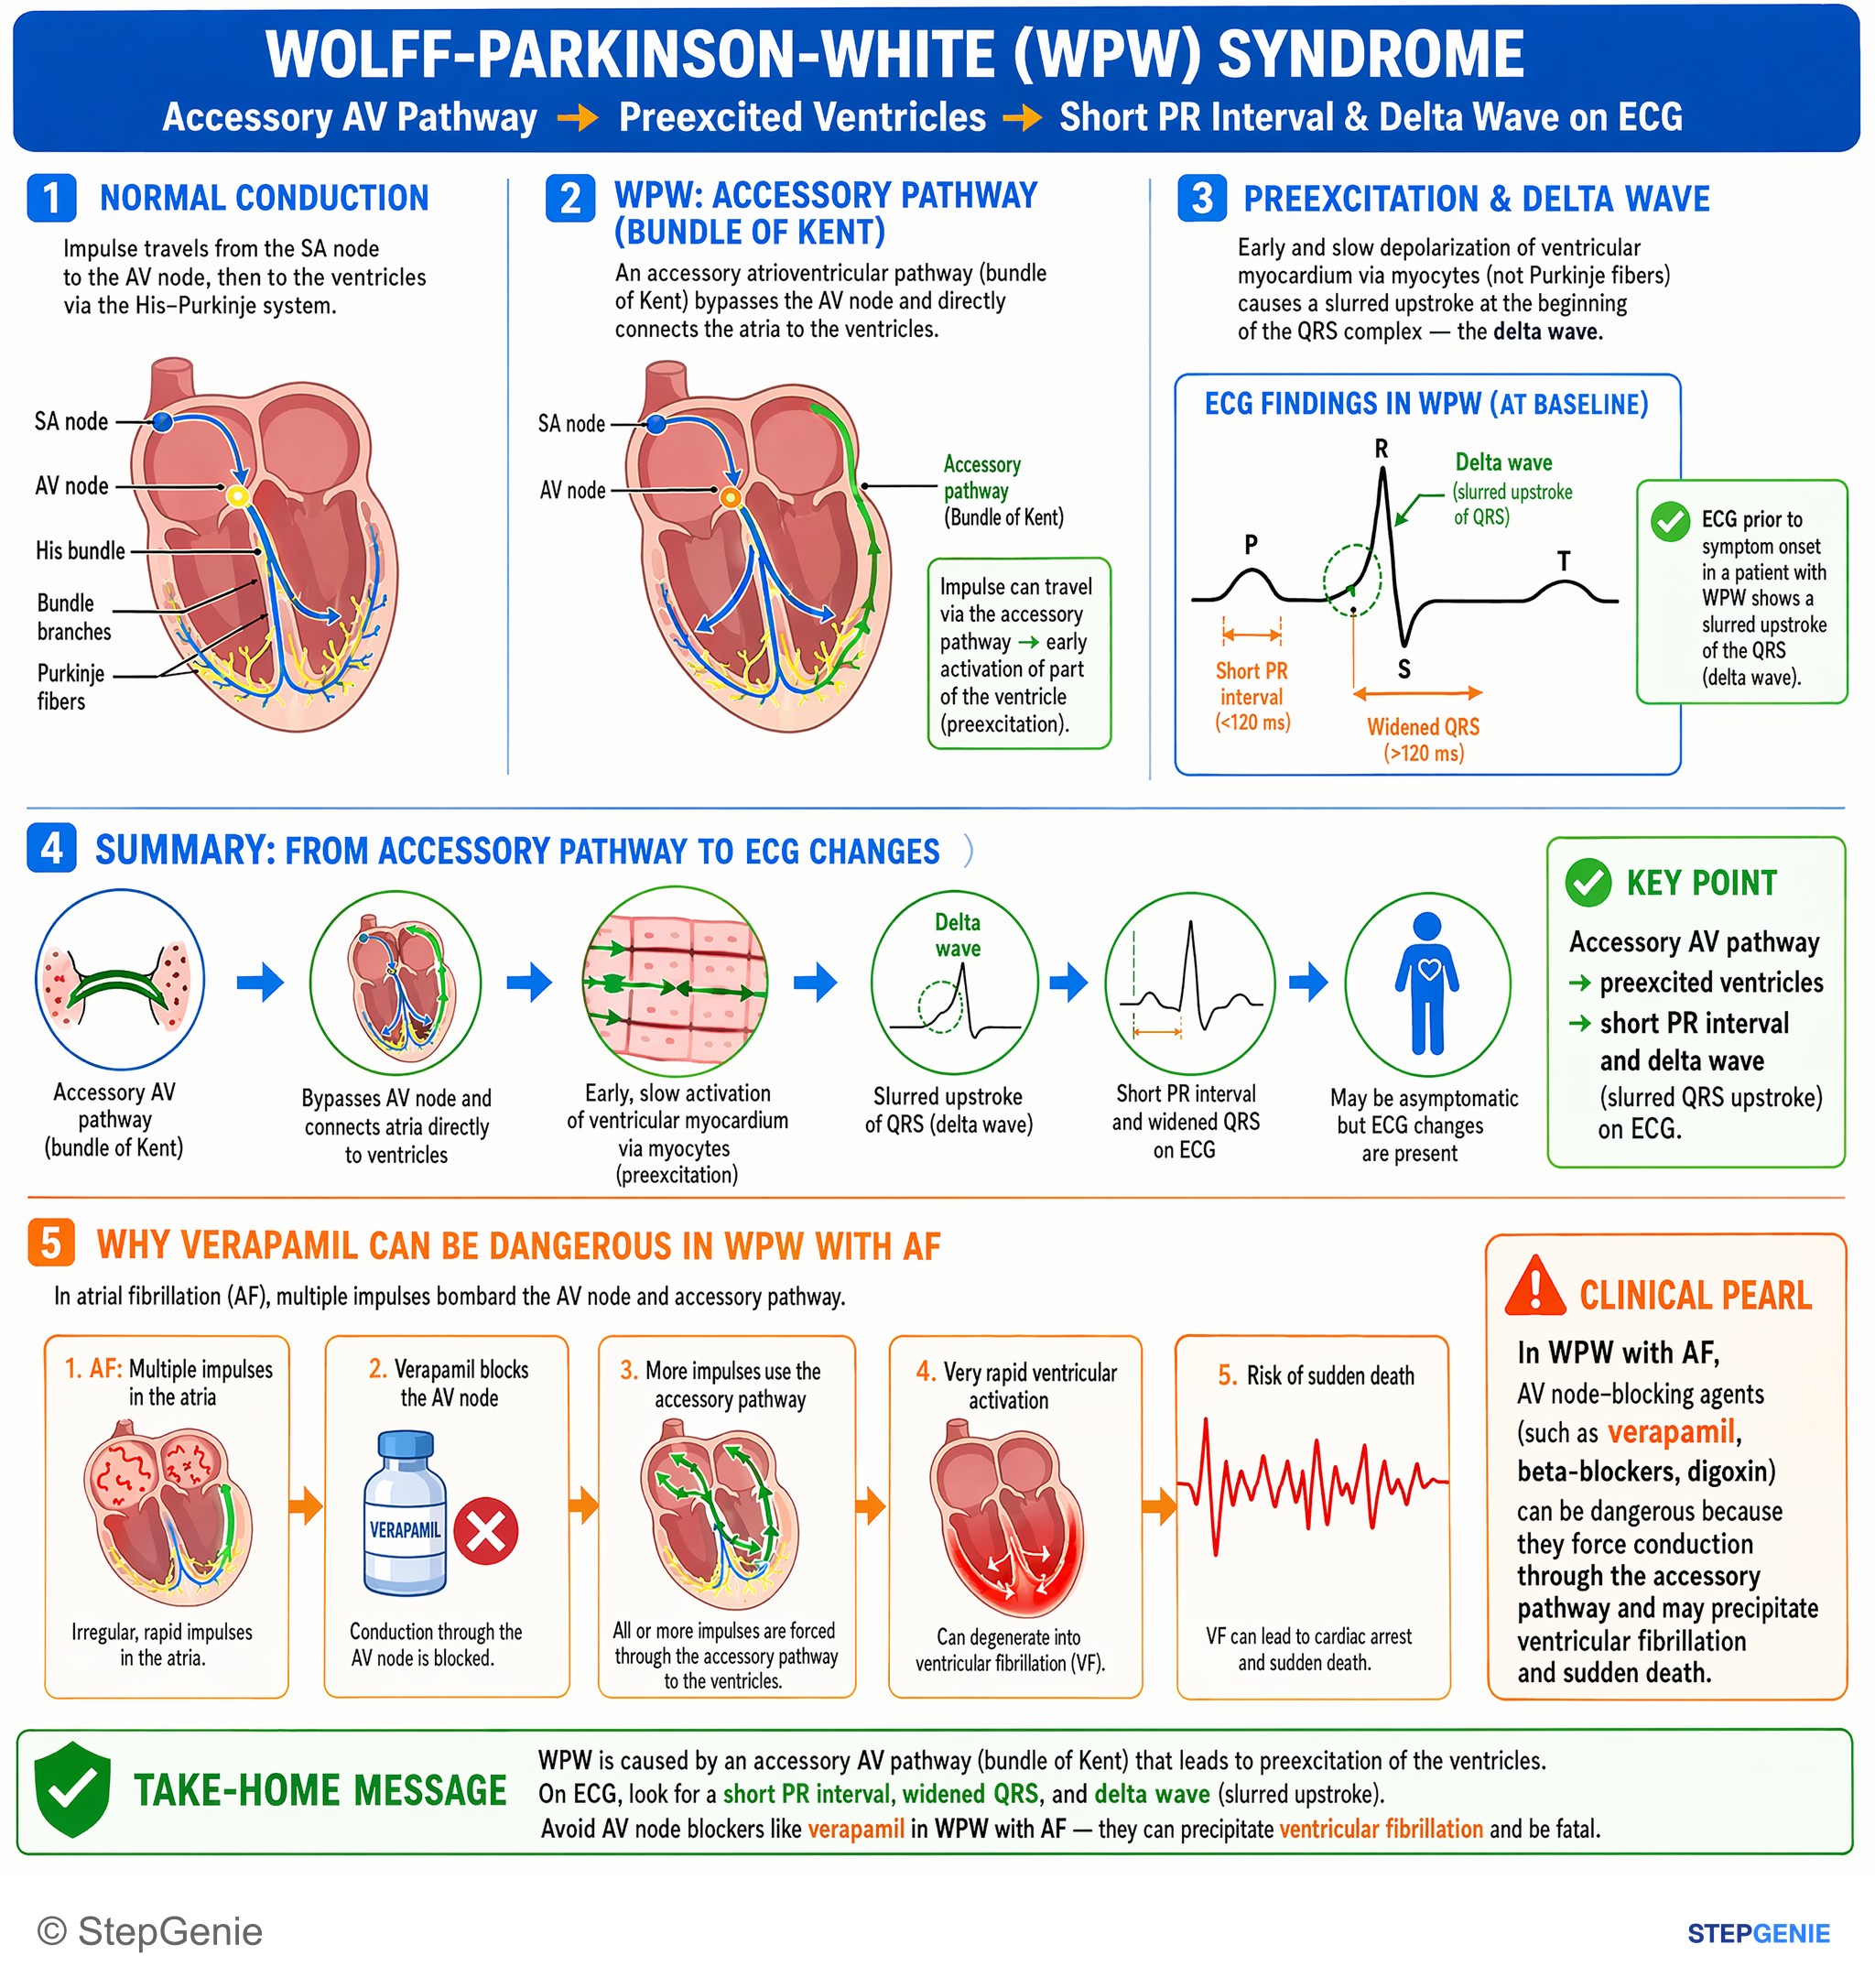
Wolff-Parkinson-White (WPW): accessory AV pathway → preexcited ventricles → short PR interval and delta wave (slurred QRS upstroke) on ECG.
USMLE Step 1Frequently Asked Questions
What is the underlying mechanism of Wolff-Parkinson-White syndrome?
Wolff-Parkinson-White is caused by an accessory pathway called the Bundle of Kent that conducts impulses from the atria to the ventricles outside the AV node. This creates pre-excitation and can support a re-entrant tachycardia. Because the AV node is bypassed, the normal rate-limiting function of the AV node is lost, which is why management changes dramatically in certain tachyarrhythmias.
What ECG findings should make you think of WPW in sinus rhythm?
The classic sinus-rhythm ECG pattern in WPW is a short PR interval, a delta wave, and often a wide QRS complex. The short PR reflects early ventricular activation, while the delta wave is the slurred upstroke of the QRS caused by early depolarization through the accessory pathway. The QRS may be widened because ventricular activation is a fusion of accessory-pathway and normal His-Purkinje conduction.
How do you tell orthodromic AVRT in WPW from atrial fibrillation with WPW on ECG?
Orthodromic AVRT in WPW is typically a regular narrow-complex tachycardia, whereas atrial fibrillation with WPW is classically an irregular wide-complex tachycardia. Orthodromic AVRT travels down the AV node and back up the accessory pathway, producing a narrow regular rhythm. In contrast, AF with WPW can conduct rapidly through the accessory pathway, creating an irregular wide rhythm and a risk of ventricular fibrillation.
Which drugs should be avoided in atrial fibrillation with WPW, and why?
AV nodal blockers should be avoided in atrial fibrillation with WPW because they can force more conduction through the accessory pathway and dangerously increase the ventricular rate. The drugs specifically listed are adenosine, beta-blockers, non-dihydropyridine calcium channel blockers such as verapamil and diltiazem, and digoxin. This pattern can degenerate into ventricular fibrillation, which is why recognizing the rhythm is high yield.
What is the first-line treatment for stable atrial fibrillation with WPW, and what if the patient is unstable?
For stable atrial fibrillation with WPW, the preferred treatments are procainamide or ibutilide. Procainamide is highlighted because it slows conduction in the accessory pathway and helps prevent dangerously rapid ventricular rates. If the patient is unstable, the correct treatment is immediate synchronized cardioversion. This distinction matters because common rate-control drugs that block the AV node are unsafe in pre-excited AF.