Prader-Willi syndrome (PWS) and Angelman syndrome (AS) are the classic “same chromosomal neighborhood, totally different vibe” Step 1 duo. They’re both imprinting disorders involving chromosome 15q11–q13, and the key test-day skill is figuring out which parent’s gene expression is missing—because that single detail flips the phenotype.
The Big Picture: Why These Two Get Tested Together
Both syndromes result from loss of expression of imprinted genes in 15q11–q13. In this region:
- Some genes are normally expressed only from the paternal allele
- Others are normally expressed only from the maternal allele
So the phenotype depends on which parent’s contribution is lost.
Core rule (memorize this)
- Prader-Willi = loss of paternal expression
- Angelman = loss of maternal expression
Genomic Imprinting Refresher (in Step-1 language)
Genomic imprinting = epigenetic silencing (often via DNA methylation) that is parent-of-origin–specific.
A good way to think of it:
- You inherit two copies of the DNA sequence (mom + dad)
- But in imprinted regions, one parent’s copy is “turned off”
- If the “on” copy is missing or disrupted → disease
First Aid cross-reference: Genetics → Genomic imprinting / Prader-Willi and Angelman syndromes (location varies by edition, often under chromosomal abnormalities/imprinting).
Side-by-Side High-Yield Comparison (Your Test-Day Anchor)
| Feature | Prader-Willi Syndrome | Angelman Syndrome |
|---|---|---|
| Missing expression | Paternal genes (15q11–q13) | Maternal genes (15q11–q13), classically UBE3A |
| Common mechanism | Paternal deletion OR maternal uniparental disomy | Maternal deletion OR paternal uniparental disomy |
| Signature phenotype | Hyperphagia → obesity, hypotonia, hypogonadism | Ataxia, seizures, inappropriate laughter (“happy puppet”) |
| Development | Mild–moderate intellectual disability | Severe intellectual disability, minimal speech |
| Early clues | Neonatal hypotonia, poor feeding → later hyperphagia | Microcephaly, developmental delay, seizures |
Mnemonic (classic Step 1):
- Prader-Willi: “P for Paternal loss; W for Weight gain”
- Angelman: “A for Ataxia/Awakening laughter; maternal loss of UBE3A”
Prader-Willi Syndrome (PWS)
Definition
An imprinting disorder due to loss of paternally expressed genes in 15q11–q13.
Pathophysiology (what’s actually happening)
Mechanisms you’ll see in questions:
- Deletion of paternal 15q11–q13 (most common)
- Maternal uniparental disomy (UPD): child inherits two maternal copies of chr 15 and no paternal copy
- Imprinting center defects (less common)
High-yield concept: In PWS, the child lacks the paternal “active” genes for this region → hypothalamic dysfunction is a major driver of the phenotype.
Clinical Presentation (classic timeline)
Neonatal/infancy
- Hypotonia (“floppy baby”)
- Poor feeding early (yes—then hyperphagia later)
- Developmental delay
Childhood and beyond
- Hyperphagia + food-seeking behavior → severe obesity
- Hypogonadism (e.g., cryptorchidism in males, delayed puberty)
- Mild–moderate intellectual disability / learning difficulties
- Short stature (often related to growth hormone axis issues)
Diagnosis (what NBME wants you to choose)
- DNA methylation testing is often the best screening test, because it can detect abnormal imprinting patterns (works regardless of deletion vs UPD).
- Follow-up tests can include:
- FISH or chromosomal microarray for deletions
- UPD studies if deletion not found
Exam tip: If the stem hints at imprinting and asks “best next step,” methylation analysis is frequently correct.
Treatment / Management (Step 2 flavor, still fair game for Step 1)
- Strict food supervision + diet/exercise structure (environmental control is huge)
- Growth hormone therapy (often used; improves body composition/linear growth)
- Manage hypogonadism (endocrinology)
- Developmental and behavioral support
High-Yield Associations (PWS)
- Hyperphagia → obesity
- Hypotonia
- Hypogonadism
- Often described with almond-shaped eyes and narrow bifrontal diameter (less tested than core triad)
Angelman Syndrome (AS)
Definition
An imprinting disorder due to loss of maternally expressed genes in 15q11–q13, classically involving UBE3A.
Pathophysiology (what’s actually happening)
Key mechanisms:
- Deletion of maternal 15q11–q13 (common)
- Paternal uniparental disomy: two paternal copies, no maternal copy
- UBE3A mutation (maternal allele) or imprinting defect
Why UBE3A matters (HY detail):
- In certain brain regions, UBE3A is primarily expressed from the maternal allele.
- Losing that maternal expression → prominent neurologic phenotype.
Clinical Presentation (the “happy puppet” cluster)
- Severe intellectual disability
- Speech impairment (often minimal verbal communication)
- Ataxia and movement disorder (jerky, puppet-like gait)
- Seizures (common; may be early)
- Inappropriate laughter, smiling, excitability (“happy demeanor”)
- Often microcephaly (postnatal onset)
Diagnosis
- Similar approach: DNA methylation analysis can identify abnormal imprinting/uniparental disomy patterns.
- If methylation is normal but suspicion remains, evaluate for UBE3A mutations.
Treatment / Management
- Seizure management (antiepileptic drugs tailored to patient)
- Physical/occupational/speech therapy
- Behavioral and sleep support
High-Yield Associations (AS)
- Ataxia + seizures + inappropriate laughter
- Severe developmental delay
- Microcephaly (often mentioned in stems)
How Question Writers Try to Trick You
Trick #1: “Deletion of chromosome 15” without saying maternal vs paternal
You must use the phenotype:
- Obesity/hyperphagia/hypotonia/hypogonadism → Prader-Willi
- Seizures/ataxia/laughter → Angelman
Trick #2: Uniparental disomy (UPD)
Know the direction:
- Maternal UPD (two maternal, no paternal) → Prader-Willi
- Paternal UPD (two paternal, no maternal) → Angelman
Trick #3: They’ll test imprinting conceptually
If asked why the phenotype differs even though it’s the same region:
- Because imprinted genes are expressed in a parent-of-origin–specific manner, so loss of maternal vs paternal expression affects different functional gene sets.
Rapid-Fire Step 1 High-Yield Summary (Last-Minute Review)
Prader-Willi
- Loss of paternal expression (15q11–q13)
- Paternal deletion or maternal UPD
- Hypotonia, hyperphagia → obesity, hypogonadism
Angelman
- Loss of maternal expression (15q11–q13), UBE3A
- Maternal deletion or paternal UPD
- Seizures, ataxia, inappropriate laughter, severe ID, speech impairment
Best initial lab concept
- DNA methylation testing for imprinting abnormalities (often the “best next test”)
First Aid Cross-References (Quick Map)
Look under:
- Genetics → Genomic imprinting
- Chromosomal disorders → Prader-Willi syndrome
- Chromosomal disorders → Angelman syndrome
- Often adjacent to other classic genetics HY: trisomies, microdeletions, UPD
(Exact page numbers vary by edition, but these are consistently grouped in the Genetics chapter.)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
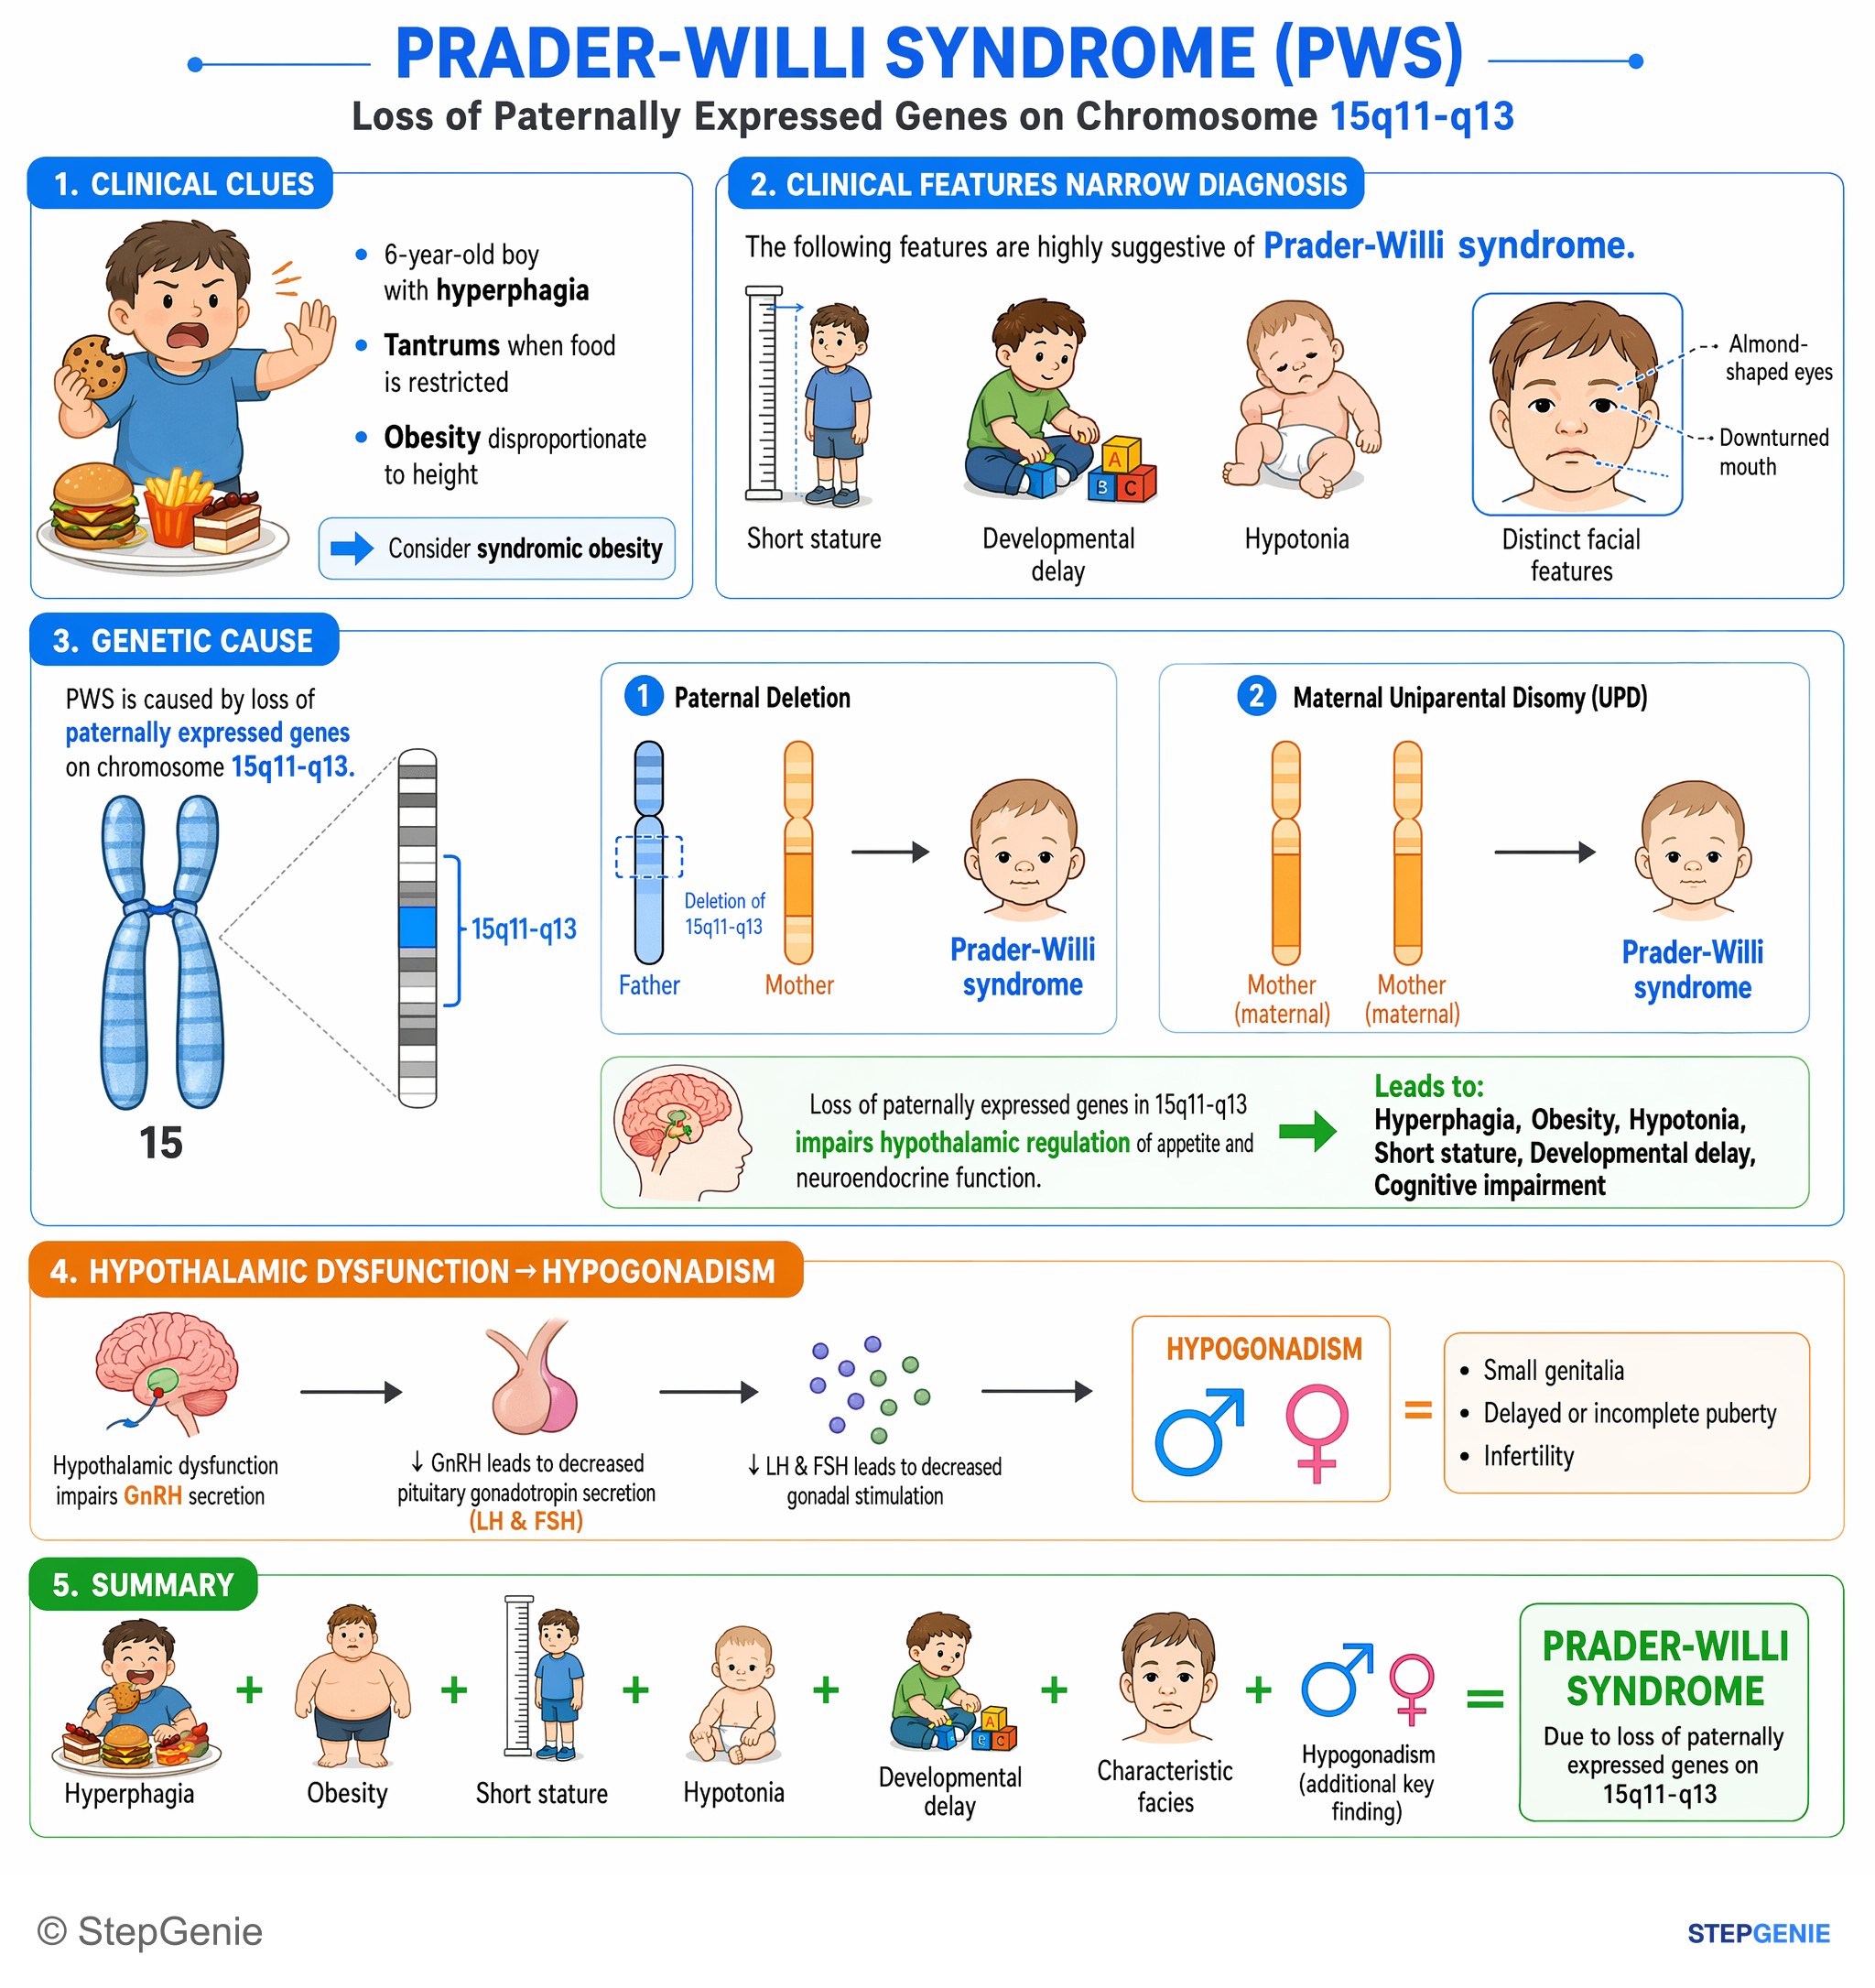
Prader-Willi syndrome due to paternal 15q11-q13 deletion → hyperphagia, obesity, short stature, hypotonia, developmental delay…
USMLE Step 1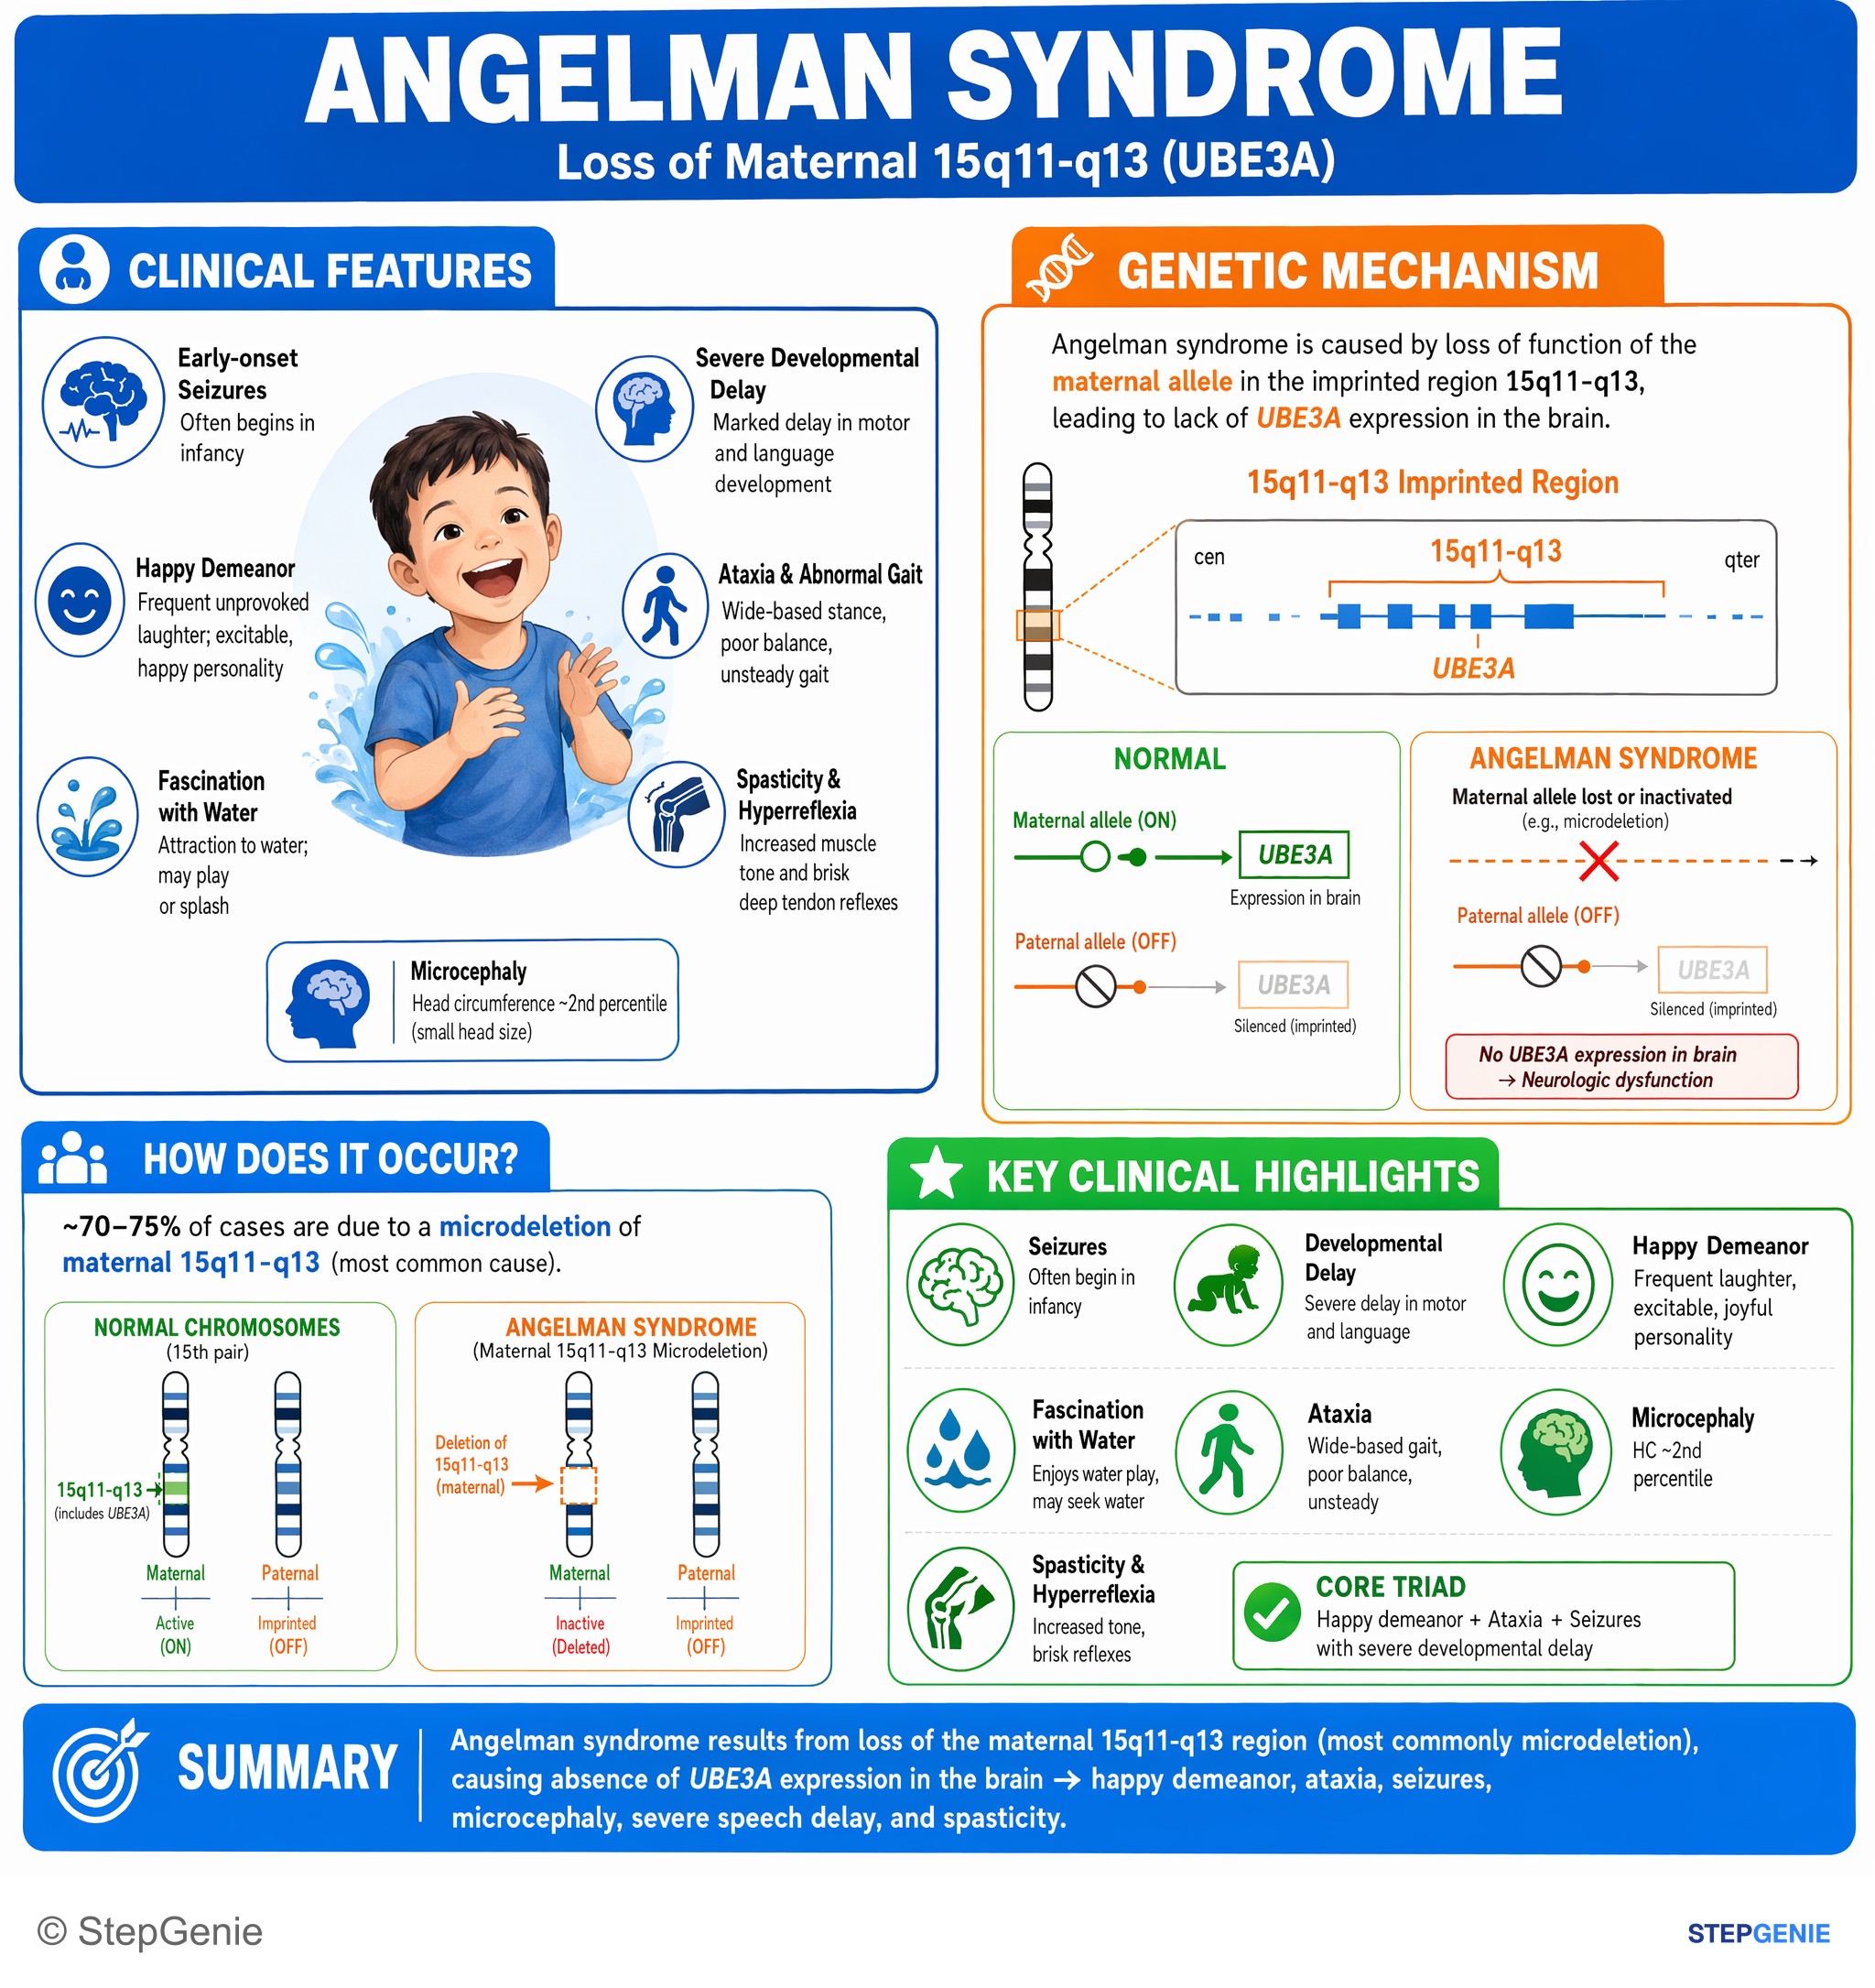
Angelman syndrome from loss of maternal 15q11-q13 (UBE3A) → happy demeanor, ataxia, seizures, microcephaly, severe speech delay, spasticity.
USMLE Step 1Frequently Asked Questions
How do you tell Prader-Willi syndrome from Angelman syndrome on Step 1?
The fastest way is to match the missing parent-specific expression with the hallmark phenotype. Prader-Willi syndrome is loss of paternal expression in 15q11–q13 and classically presents with neonatal hypotonia followed later by hyperphagia, obesity, and hypogonadism. Angelman syndrome is loss of maternal expression in the same region, classically involving UBE3A, and presents with ataxia, seizures, inappropriate laughter, severe intellectual disability, and minimal speech.
Why does the parent of origin matter in Prader-Willi and Angelman syndromes?
The parent of origin matters because these are imprinting disorders, so some genes in 15q11–q13 are normally expressed only from one parental allele. Genomic imprinting is parent-specific epigenetic silencing, often through DNA methylation. If the active copy from the relevant parent is missing or disrupted, disease occurs. Loss of paternal expression causes Prader-Willi syndrome, while loss of maternal expression causes Angelman syndrome.
What causes Prader-Willi syndrome genetically?
Prader-Willi syndrome is caused by loss of paternally expressed genes in chromosome 15q11–q13. The most common mechanism is deletion of the paternal 15q11–q13 region. It can also result from maternal uniparental disomy, where the child inherits two maternal copies of chromosome 15 and no paternal copy, or from less common imprinting center defects.
What causes Angelman syndrome genetically?
Angelman syndrome is caused by loss of maternally expressed genes in chromosome 15q11–q13, classically involving UBE3A. Common mechanisms include deletion of the maternal 15q11–q13 region and paternal uniparental disomy, which leaves the child with two paternal copies and no maternal copy. It can also result from a maternal UBE3A mutation or an imprinting defect.
What is the best screening test if a question stem suggests Prader-Willi or Angelman syndrome?
DNA methylation testing is often the best screening test when an imprinting disorder like Prader-Willi or Angelman syndrome is suspected. It can detect abnormal imprinting patterns and works across different mechanisms, including deletion and uniparental disomy. Follow-up testing may then include FISH or chromosomal microarray for deletions, and additional studies for uniparental disomy or UBE3A mutations when indicated.