Everything You Need to Know About Autosomal Dominant Inheritance for Step 1
Autosomal dominant (AD) inheritance is one of the most frequently tested genetics patterns on USMLE Step 1—and it’s not just memorization. Step questions often integrate pedigree interpretation, penetrance/expressivity, and classic AD diseases into clinical vignettes. This post is your high-yield, clinically oriented deep dive.
What Is Autosomal Dominant Inheritance?
Autosomal dominant inheritance means a single pathogenic variant (one mutant allele) on an autosome (non–sex chromosome) is sufficient to cause disease.
Core Rules (Step 1 Must-Knows)
- Vertical transmission: often seen in every generation.
- Males and females affected equally.
- Male-to-male transmission can occur (distinguishes from X-linked).
- Each child of an affected heterozygous parent has a 50% chance of inheriting the pathogenic allele.
- Unaffected individuals typically do not transmit the disorder (exceptions exist with reduced penetrance, germline mosaicism).
First Aid cross-reference: Genetics → Modes of inheritance (Autosomal dominant)
Pathophysiology: Why One Mutant Allele Can Be Enough
Autosomal dominant diseases usually result from mechanisms where 50% normal gene product is not sufficient or where the mutant product actively interferes.
1) Haploinsufficiency (Loss of Function)
One functional copy doesn’t make enough product to maintain normal function.
- Example patterns:
- Familial hypercholesterolemia (LDL receptor mutations)
- Hereditary spherocytosis (membrane proteins; classically AD)
- Some tumor suppressor disorders (e.g., RB1, TP53) behave as AD for predisposition (see “two-hit” below)
Testable clue: disease due to “reduced amount” of a protein.
2) Dominant Negative Effect
The mutant protein interferes with the normal protein—common in proteins that form multimers (e.g., collagen).
- Marfan syndrome (fibrillin-1; not a classic collagen multimer example, but dominant negative is often taught)
- Osteogenesis imperfecta (type I collagen; often dominant negative, sometimes haploinsufficiency depending on mutation)
Testable clue: mutant protein “poisons” the normal complex.
3) Gain of Function (Toxic/Constitutive Activity)
The mutant allele produces a protein with increased activity or new harmful function.
- Achondroplasia (FGFR3 gain-of-function)
- Huntington disease (CAG repeat expansion → toxic protein)
Testable clue: “constitutively active receptor” or “toxic accumulation.”
4) The Two-Hit Hypothesis (Important Nuance)
Some AD conditions involve inherited predisposition to cancer due to a germline mutation in a tumor suppressor gene. Disease manifests after loss of the second allele in somatic cells.
- Retinoblastoma (RB1)
- Li-Fraumeni syndrome (TP53)
- Familial adenomatous polyposis (APC) (polyposis predisposition; malignant transformation requires additional hits)
First Aid cross-reference: Genetics → Tumor suppressor genes; Two-hit hypothesis
Clinical Presentation: How AD Patterns Appear on Exams
Pedigree Hallmarks
- Multiple affected individuals in successive generations
- An affected parent often has affected children
- Equal sex distribution
- Male-to-male transmission present
Common Step 1 “Twists”
- Reduced penetrance: person carries mutation but has no phenotype → can make a generation “look skipped.”
- Variable expressivity: same mutation, different severity among family members.
- De novo mutations: child affected, parents unaffected (common in achondroplasia; associated with advanced paternal age).
- Anticipation: symptoms appear earlier/worse in successive generations due to repeat expansions (e.g., Huntington, myotonic dystrophy).
First Aid cross-reference: Genetics → Penetrance, variable expressivity, anticipation; Trinucleotide repeat disorders
High-Yield Autosomal Dominant Disorders (What to Recognize Fast)
Below are classic AD diseases that show up repeatedly in Step-style vignettes.
Connective Tissue / MSK
- Marfan syndrome (FBN1)
- Findings: tall, long limbs, arachnodactyly, hyperflexible joints, upward lens dislocation, aortic root dilation/dissection
- Ehlers-Danlos syndrome (some types AD)
- Hyperextensible skin, hypermobile joints, easy bruising; vascular type has rupture risk
- Osteogenesis imperfecta (COL1A1/COL1A2)
- Brittle bones, blue sclerae, hearing loss, dental imperfections
Neuro
- Huntington disease (CAG repeat, chromosome 4)
- Chorea, psychiatric changes, dementia; anticipation (often paternal transmission worsens)
- Neurofibromatosis type 1
- Café-au-lait spots, neurofibromas, Lisch nodules, optic gliomas
- Tuberous sclerosis
- Ash-leaf spots, seizures, renal angiomyolipomas, subependymal giant cell astrocytomas
Endocrine / Neoplasia Syndromes
- MEN 1 (menin): “3 P’s” (parathyroid, pancreas, pituitary)
- MEN 2 (RET proto-oncogene): medullary thyroid carcinoma ± pheochromocytoma
- Von Hippel–Lindau (VHL): hemangioblastomas, RCC, pheochromocytoma
Renal / Vascular
- ADPKD
- Enlarged kidneys, flank pain, hematuria; berry aneurysms, hepatic cysts, MVP
- Hereditary hemorrhagic telangiectasia
- Recurrent epistaxis, telangiectasias, AVMs
Metabolic / Other
- Familial hypercholesterolemia
- Tendon xanthomas, premature atherosclerosis, very high LDL
First Aid cross-reference: These are distributed across systems (CV, renal, neuro, endocrine). Most students find them listed under “Autosomal Dominant Disorders” in the Genetics chapter plus in organ-system chapters.
Diagnosis: How AD Inheritance Is Confirmed (and Tested)
Step 1 Level: Pedigree + Probability
- If one parent is affected with an AD condition (heterozygous), each child has a 50% risk.
- If neither parent is affected, think:
- De novo mutation
- Reduced penetrance
- Germline mosaicism (rare but testable)
Clinical Practice Angle (Step 2-Relevant Concepts)
- Genetic testing:
- Targeted mutation testing if known familial variant
- Gene panels for syndromic presentations
- Imaging/labs guided by suspected syndrome:
- Marfan: echocardiography (aortic root)
- ADPKD: renal ultrasound/CT
- MEN2: calcitonin, metanephrines; RET testing
Counseling Must-Knows
- Risk to offspring: typically 50% if an affected parent is heterozygous.
- Penetrance matters: genotype-positive but phenotype-negative can still pass on disease.
- Anticipation: repeat expansion disorders may worsen in subsequent generations.
Treatment and Management: The USMLE-Focused Approach
There’s no single “AD inheritance treatment”—management is disease-specific, but Step questions often test:
- Screening to prevent catastrophic complications
- Prophylactic interventions
- Family counseling
High-Yield Examples
- Marfan syndrome
- Reduce aortic shear stress: beta-blockers (classically) and/or ARBs; surveillance for aneurysm
- MEN2 (RET)
- Prophylactic thyroidectomy due to medullary thyroid cancer risk (timing depends on mutation risk level)
- ADPKD
- BP control; monitor for intracranial aneurysms in selected patients (e.g., family history)
- Familial hypercholesterolemia
- High-intensity statins, add-on lipid-lowering therapies as needed; early prevention
Genetic Counseling (Common Exam Target)
- Provide recurrence risk (often 50%).
- Discuss variable expressivity/penetrance—don’t overpromise phenotype severity.
- Consider testing at-risk relatives when early interventions or surveillance improves outcomes.
High-Yield Associations & Exam Traps (Rapid Review)
Pattern Recognition
- Every generation → think autosomal dominant
- Equal males/females + male-to-male transmission → supports autosomal (not X-linked)
- Appears to skip a generation → consider reduced penetrance
- Worse/earlier each generation → anticipation (trinucleotide repeats)
- Affected child, unaffected parents → de novo mutation (e.g., achondroplasia) or germline mosaicism
Quant Questions You Should Nail
- Affected heterozygous parent (Aa) × unaffected (aa) → 50% affected
- Two affected heterozygous parents (Aa × Aa) → 75% affected, 25% unaffected
- Note: AA may be more severe or lethal depending on disease (classic example: achondroplasia homozygous state is lethal).
First Aid Cross-References (Where to Review)
- Genetics chapter
- Modes of inheritance (AD vs AR vs X-linked)
- Penetrance/variable expressivity
- Anticipation + trinucleotide repeat disorders
- Tumor suppressors + two-hit hypothesis
- Organ-system chapters
- Marfan (CV/MSK)
- ADPKD (renal)
- MEN syndromes (endocrine)
- Neurocutaneous syndromes (neuro)
Quick Clinical Vignette Clues (Step-Style)
- Tall patient + lens up + aortic root dilation → Marfan (AD)
- Teen with multiple café-au-lait spots + neurofibromas → NF1 (AD)
- Adult with chorea + personality changes + family history → Huntington (AD, anticipation)
- Recurrent kidney cysts + berry aneurysm risk → ADPKD (AD)
- Hypercalcemia + pituitary tumor + pancreatic gastrinoma → MEN1 (AD)
- Medullary thyroid carcinoma + pheochromocytoma → MEN2 (AD)
Takeaway: The Step 1 Mental Model
If you can do three things quickly, you’ll ace most AD questions:
- Recognize the pedigree (vertical transmission; male-to-male possible).
- Apply the 50% rule (with penetrance/expressivity caveats).
- Attach the vignette to a classic AD syndrome and its hallmark complication.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
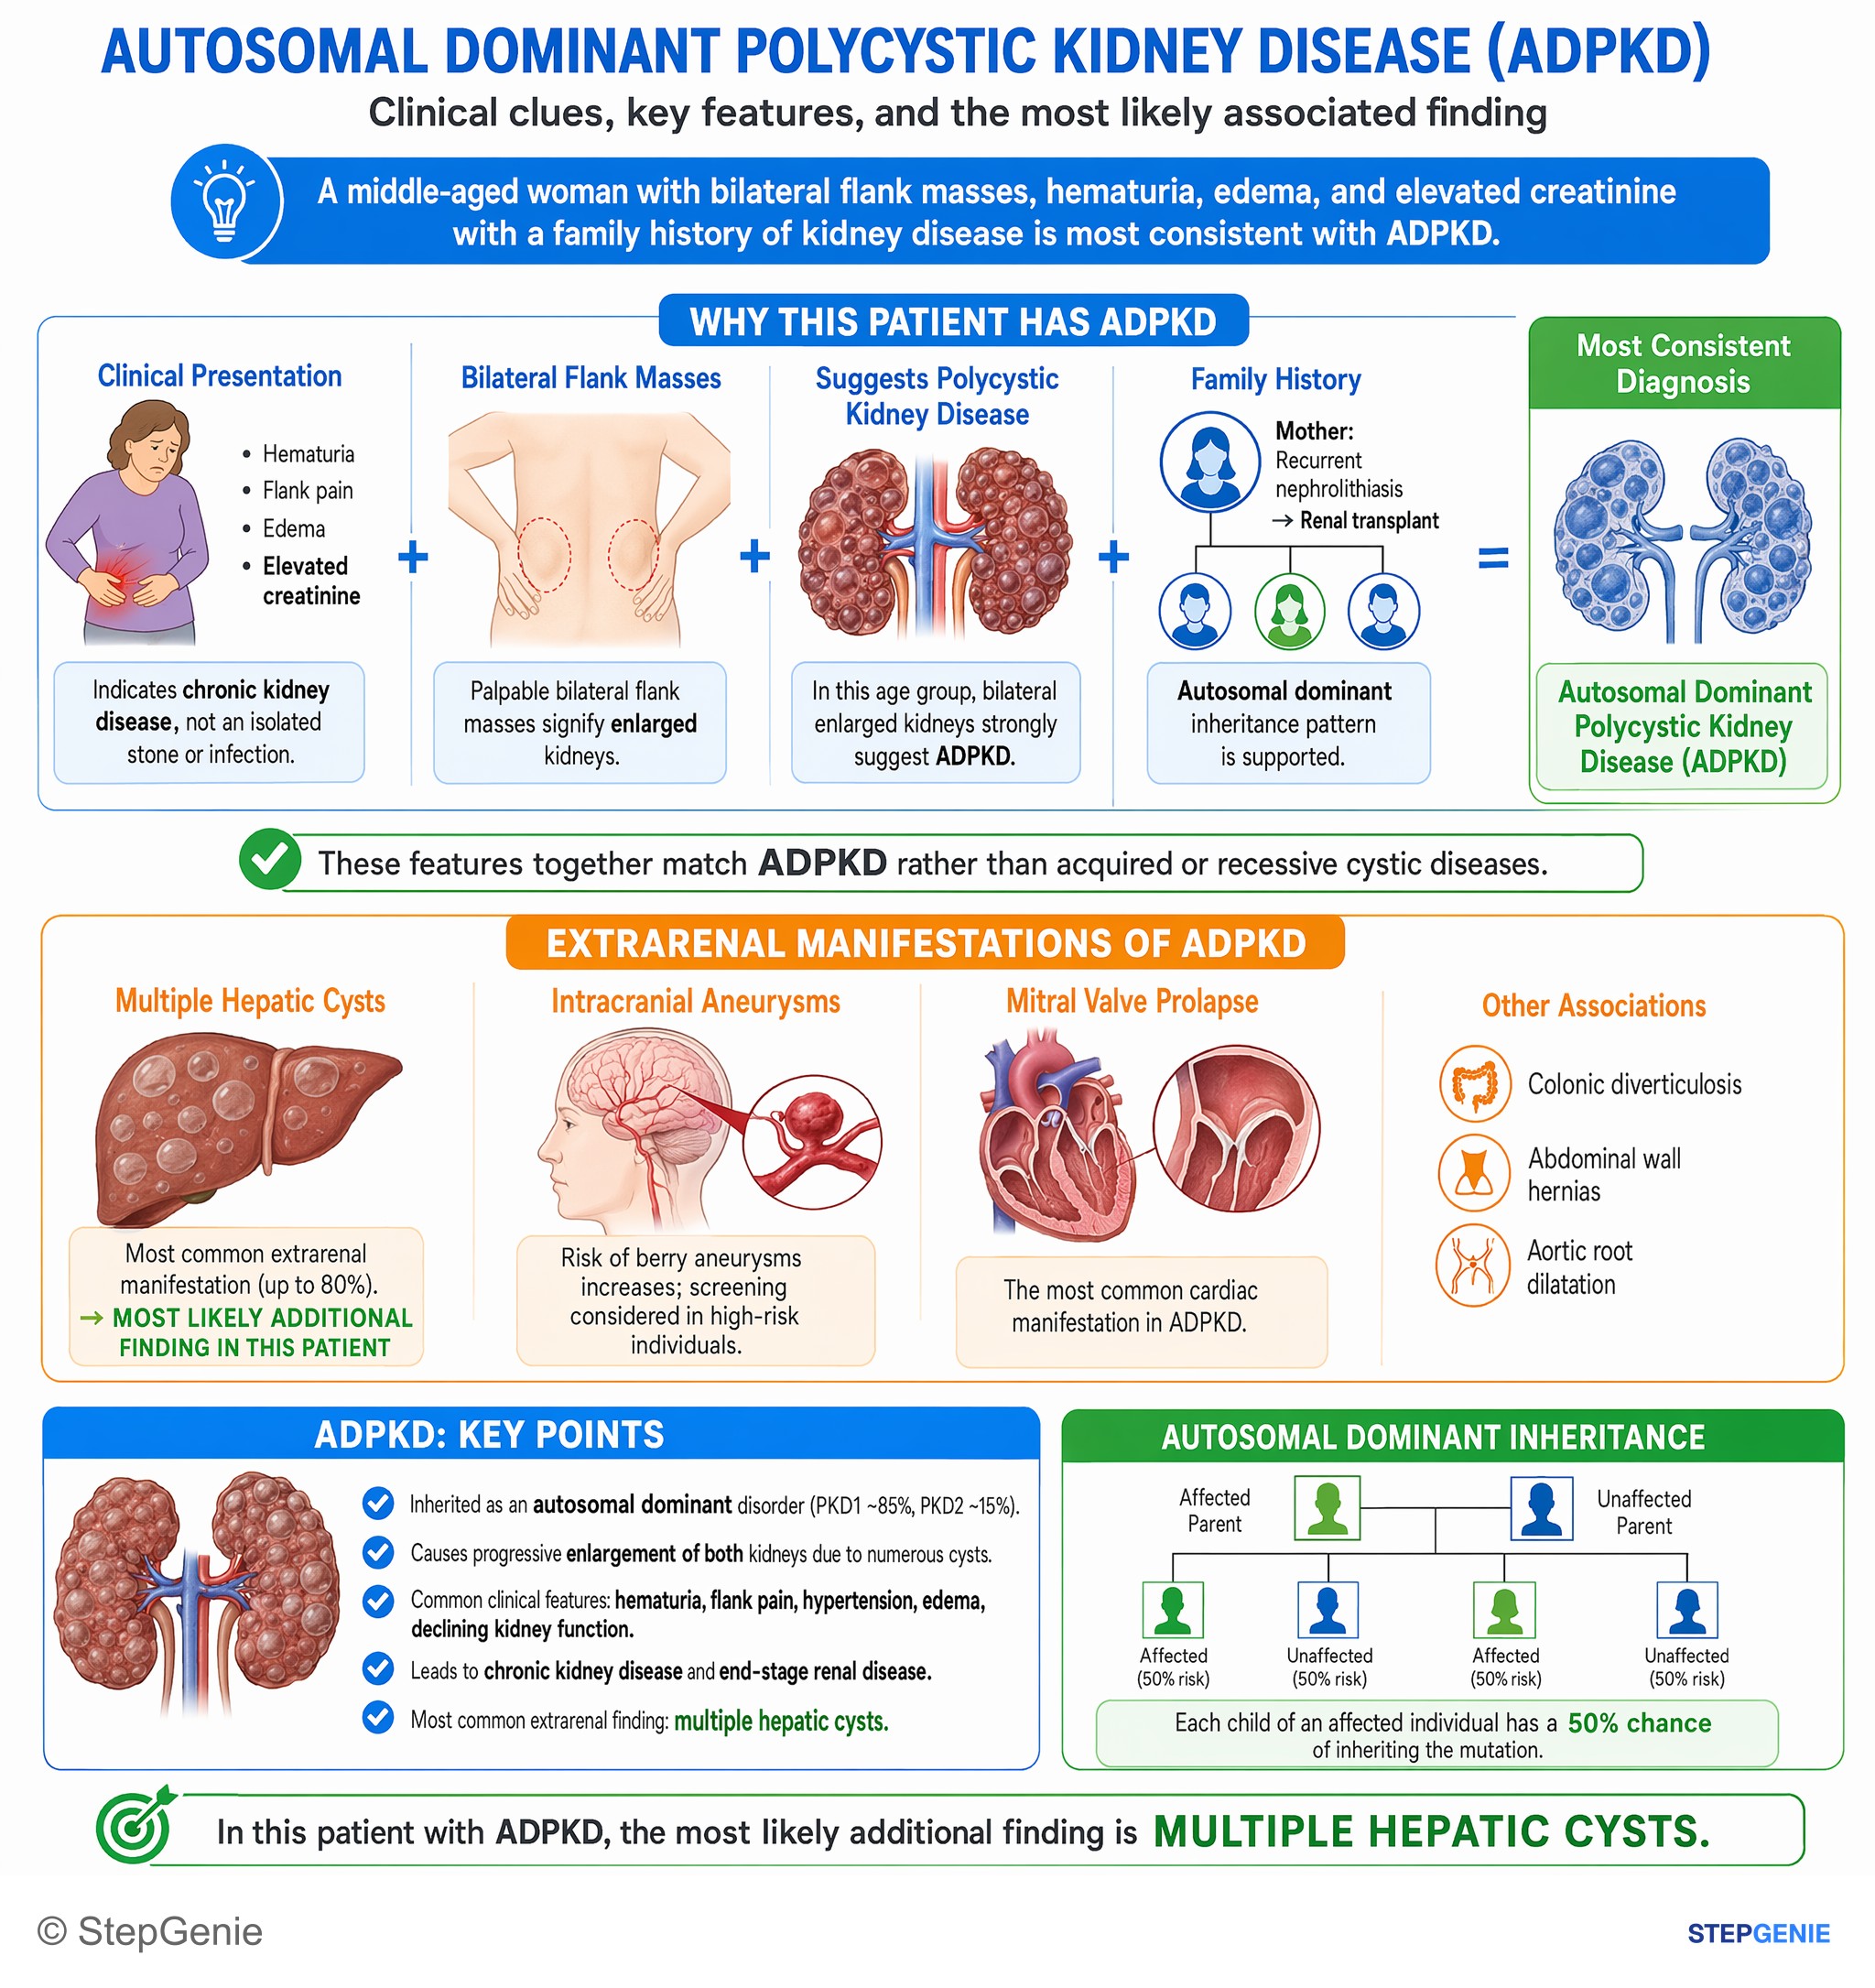
Autosomal dominant polycystic kidney disease causes bilateral renal enlargement, hematuria, renal failure, and is commonly associated with…
USMLE Step 1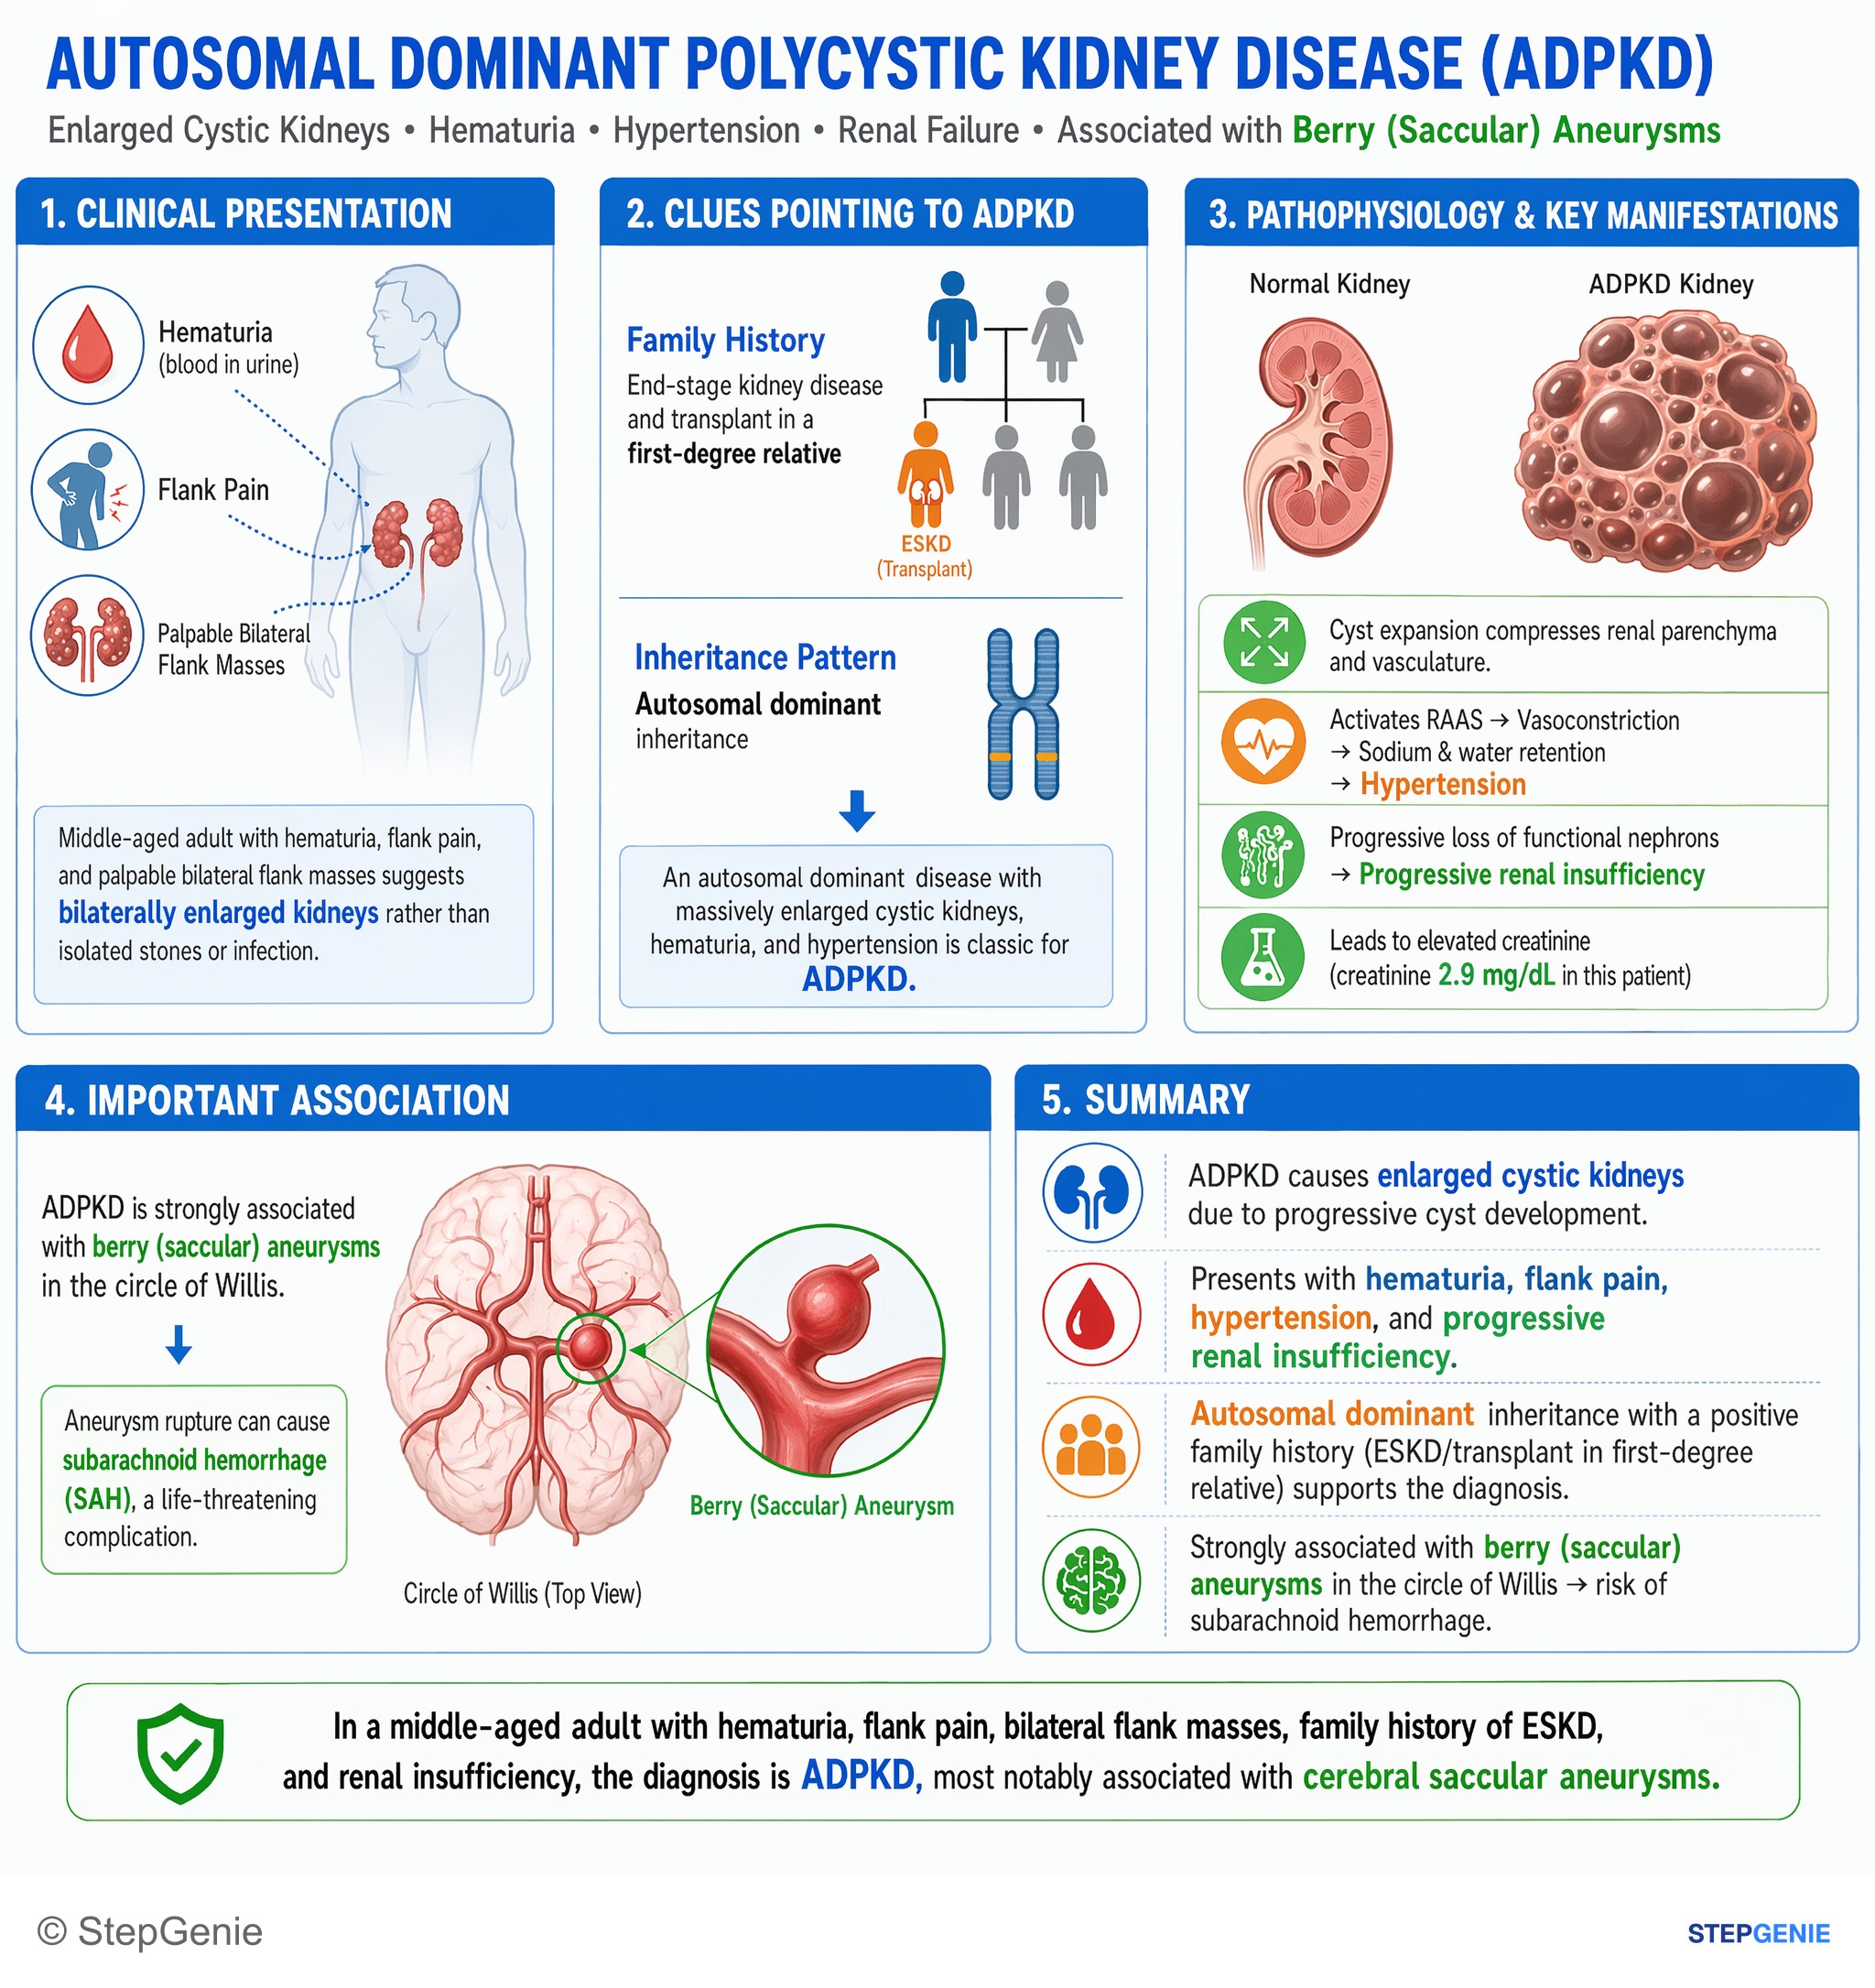
Autosomal dominant polycystic kidney disease (ADPKD) causes enlarged cystic kidneys, hematuria, HTN, renal failure, and is associated with…
USMLE Step 2Frequently Asked Questions
What are the classic pedigree clues for autosomal dominant inheritance?
Autosomal dominant inheritance classically shows vertical transmission with affected individuals in successive generations. Males and females are affected equally, and male-to-male transmission can occur, which helps distinguish it from X-linked inheritance. An affected parent often has affected children, and if the affected parent is heterozygous, each child has a 50% chance of inheriting the pathogenic allele.
Why can one mutant allele be enough to cause an autosomal dominant disease?
One mutant allele can be enough because many autosomal dominant disorders result from haploinsufficiency, dominant negative effects, or gain of function. In haploinsufficiency, one normal copy does not make enough protein for normal function. In dominant negative disease, the mutant protein interferes with the normal one. In gain-of-function disorders, the mutant allele produces increased or toxic activity.
How do you tell autosomal dominant inheritance from X-linked inheritance on a pedigree?
A key clue is that autosomal dominant disorders can show male-to-male transmission, while X-linked disorders do not. Autosomal dominant patterns also affect males and females equally and often appear in every generation. When a pedigree shows an affected father passing the condition to a son, that strongly supports an autosomal dominant pattern rather than an X-linked one.
Why can an autosomal dominant disorder look like it skips a generation?
An autosomal dominant disorder can appear to skip a generation because of reduced penetrance. In reduced penetrance, a person carries the mutation but does not show the phenotype, so the family history may look inconsistent with a dominant pattern. Germline mosaicism can also complicate the usual rule that unaffected individuals do not transmit the disorder.
What high-yield autosomal dominant diseases should you recognize quickly for Step 1?
High-yield autosomal dominant diseases include Marfan syndrome, osteogenesis imperfecta, Huntington disease, neurofibromatosis type 1, tuberous sclerosis, MEN 1, MEN 2, von Hippel–Lindau, ADPKD, hereditary hemorrhagic telangiectasia, and familial hypercholesterolemia. These are commonly recognized by classic clues such as Marfan features, Huntington anticipation, ADPKD with berry aneurysms, and familial hypercholesterolemia with tendon xanthomas and premature atherosclerosis.