Fragile X syndrome is one of those “classic genetics” topics that shows up everywhere on Step 1: trinucleotide repeats, X-linked inheritance patterns, intellectual disability, autism spectrum features, and that unmistakable phenotype (big ears + long face + macroorchidism). If you can connect the gene-level mechanism to the clinical picture and testing, you’ll pick up a lot of easy points.
What Is Fragile X Syndrome?
Fragile X syndrome (FXS) is the most common inherited cause of intellectual disability and a major genetic cause of autism spectrum disorder. It’s due to a trinucleotide repeat expansion in the FMR1 gene on the X chromosome.
Core idea:
- CGG repeat expansion in FMR1 → gene silencing → ↓ FMRP (Fragile X mental retardation protein) → abnormal synaptic development/plasticity → neurodevelopmental phenotype.
Genetics & Pathophysiology (The Mechanism Step 1 Loves)
The Mutation
- Gene: FMR1
- Chromosome: X
- Repeat: CGG
- Type of mutation: Dynamic mutation (repeat expansion), leading to anticipation
Full Mutation vs Premutation (High-Yield Distinction)
| Category | CGG Repeats | Methylation? | FMR1 Expression | Clinical Associations |
|---|---|---|---|---|
| Normal | < ~45 | No | Normal | None |
| Intermediate (“gray zone”) | ~45–54 | Usually no | Usually normal | Typically none |
| Premutation | ~55–200 | No (usually) | Often ↑ FMR1 mRNA (toxic gain-of-function) | FXTAS, FXPOI |
| Full mutation | >200 | Yes (hypermethylation) | ↓/absent FMRP | Fragile X syndrome |
Why the Phenotype Happens
FMRP helps regulate translation of synaptic proteins (especially at dendritic spines).
Loss of FMRP → abnormal dendritic spine morphology (often described as long/thin/immature) → impaired synaptic plasticity → learning and behavioral symptoms.
Anticipation & Maternal Transmission
- Fragile X shows anticipation (worsening severity / earlier onset in successive generations) due to repeat expansion during gametogenesis.
- Key Step 1 nuance: Expansion to full mutation is more likely during oogenesis, so transmission risk is classically emphasized through maternal carriers.
Inheritance Pattern: How It Presents on Pedigrees
Fragile X is X-linked dominant with variable penetrance and variable expressivity.
Testable pedigree clues
- No male-to-male transmission (because dads give sons a Y chromosome).
- Males are typically more severely affected (only one X).
- Female carriers can be symptomatic (due to X-inactivation skewing), often with milder cognitive/psychiatric findings.
Clinical Presentation (What to Recognize in a Vignette)
Neurodevelopmental/Behavioral
- Intellectual disability (often more severe in males)
- Autism spectrum disorder features
- ADHD, anxiety, social avoidance
- Language delay; learning difficulties
Characteristic Physical Features (Classic Board-Style)
- Long, narrow face
- Large, protruding ears
- Macroorchidism (postpubertal males)
- High-arched palate
- Hyperextensible joints
- Mitral valve prolapse (connective tissue–type finding)
When Features Become Obvious
- Many physical traits become more apparent with age; macroorchidism is typically noted after puberty.
Diagnosis (What Test Confirms It?)
Best Diagnostic Test
- DNA-based testing for CGG repeat number and methylation status:
- PCR (good for sizing smaller expansions)
- Southern blot (historically used; helps detect large expansions and methylation status—still conceptually testable)
Why karyotype isn’t enough:
The “fragile site” on X chromosome can be suggested cytogenetically, but modern diagnosis is by molecular testing.
What You Might See in the Stem (Clinical Clues)
- Male child with developmental delay + autistic behaviors + large ears/long face
- Family history of “learning problems” in maternal relatives
- Adult male relative with late-onset tremor/ataxia (points to premutation)
Treatment & Management (Step-Relevant)
There is no cure that reverses the genetic defect, so management is supportive and multidisciplinary:
- Early intervention: speech/language therapy, occupational therapy, individualized education plans
- Behavioral therapy for ASD/ADHD features
- Medications (symptom-targeted):
- Stimulants for ADHD
- SSRIs for anxiety
- Antipsychotics in select cases for severe irritability/aggression
- Genetic counseling:
- Carrier testing for family members
- Discussion of premutation/full mutation risks and anticipation
High-Yield Associations & Test Traps
1) Premutation Syndromes (Very Testable)
Premutation carriers (especially older adults and some women) can have distinct disorders due to toxic gain-of-function from increased FMR1 mRNA:
-
FXTAS (Fragile X–associated tremor/ataxia syndrome)
- Typically older males
- Intention tremor, ataxia, parkinsonism-like features, cognitive decline
-
FXPOI (Fragile X–associated primary ovarian insufficiency)
- In some female premutation carriers
- Infertility, irregular menses, early menopause
2) Fragile X vs Rett vs Angelman (Don’t Mix Them Up)
A fast discriminator table:
| Syndrome | Genetic Mechanism | Key Clues |
|---|---|---|
| Fragile X | CGG repeat expansion (FMR1) → hypermethylation → silencing | Long face, big ears, macroorchidism, ASD/ID |
| Rett | MECP2 mutation (X-linked dominant; usually lethal in males) | Normal early, then regression, hand-wringing, seizures |
| Angelman | Maternal deletion (15q) or imprinting defect; ↓ UBE3A | Happy demeanor, ataxia, seizures, inappropriate laughter |
3) “Autism + Macroorchidism” is a giveaway
If the question pairs ASD features with macroorchidism, think Fragile X first.
4) Connective tissue findings
Fragile X can show MVP and joint hypermobility—often used to tempt you toward Marfan/Ehlers-Danlos, but the neurodevelopmental phenotype and X-linked repeat expansion are the anchors.
First Aid Cross-References (Where This Lives in Your Head)
Use these as mental bookmarks rather than page numbers (since editions vary):
- Genetics → Trinucleotide repeat disorders
- Fragile X: CGG repeat, X-linked, anticipation
- Contrast with:
- Huntington: CAG
- Myotonic dystrophy: CTG
- Friedreich ataxia: GAA
- Neurodevelopmental disorders
- Intellectual disability, ASD associations
- Reproductive/endocrine associations
- Premutation → FXPOI
- Neurology (movement disorders in older adults)
- Premutation → FXTAS
Rapid-Fire Step 1 Review (High-Yield Checklist)
- Most common inherited cause of intellectual disability
- FMR1 on X chromosome
- CGG repeat expansion
- >200 repeats → hypermethylation → silenced gene → ↓ FMRP
- Anticipation, especially with maternal transmission
- Classic phenotype: long face, large ears, macroorchidism
- Behavioral: ASD, ADHD, anxiety
- Confirm with PCR/Southern blot repeat sizing (molecular testing)
- Premutation complications:
- FXTAS (older males: tremor/ataxia)
- FXPOI (female ovarian insufficiency)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
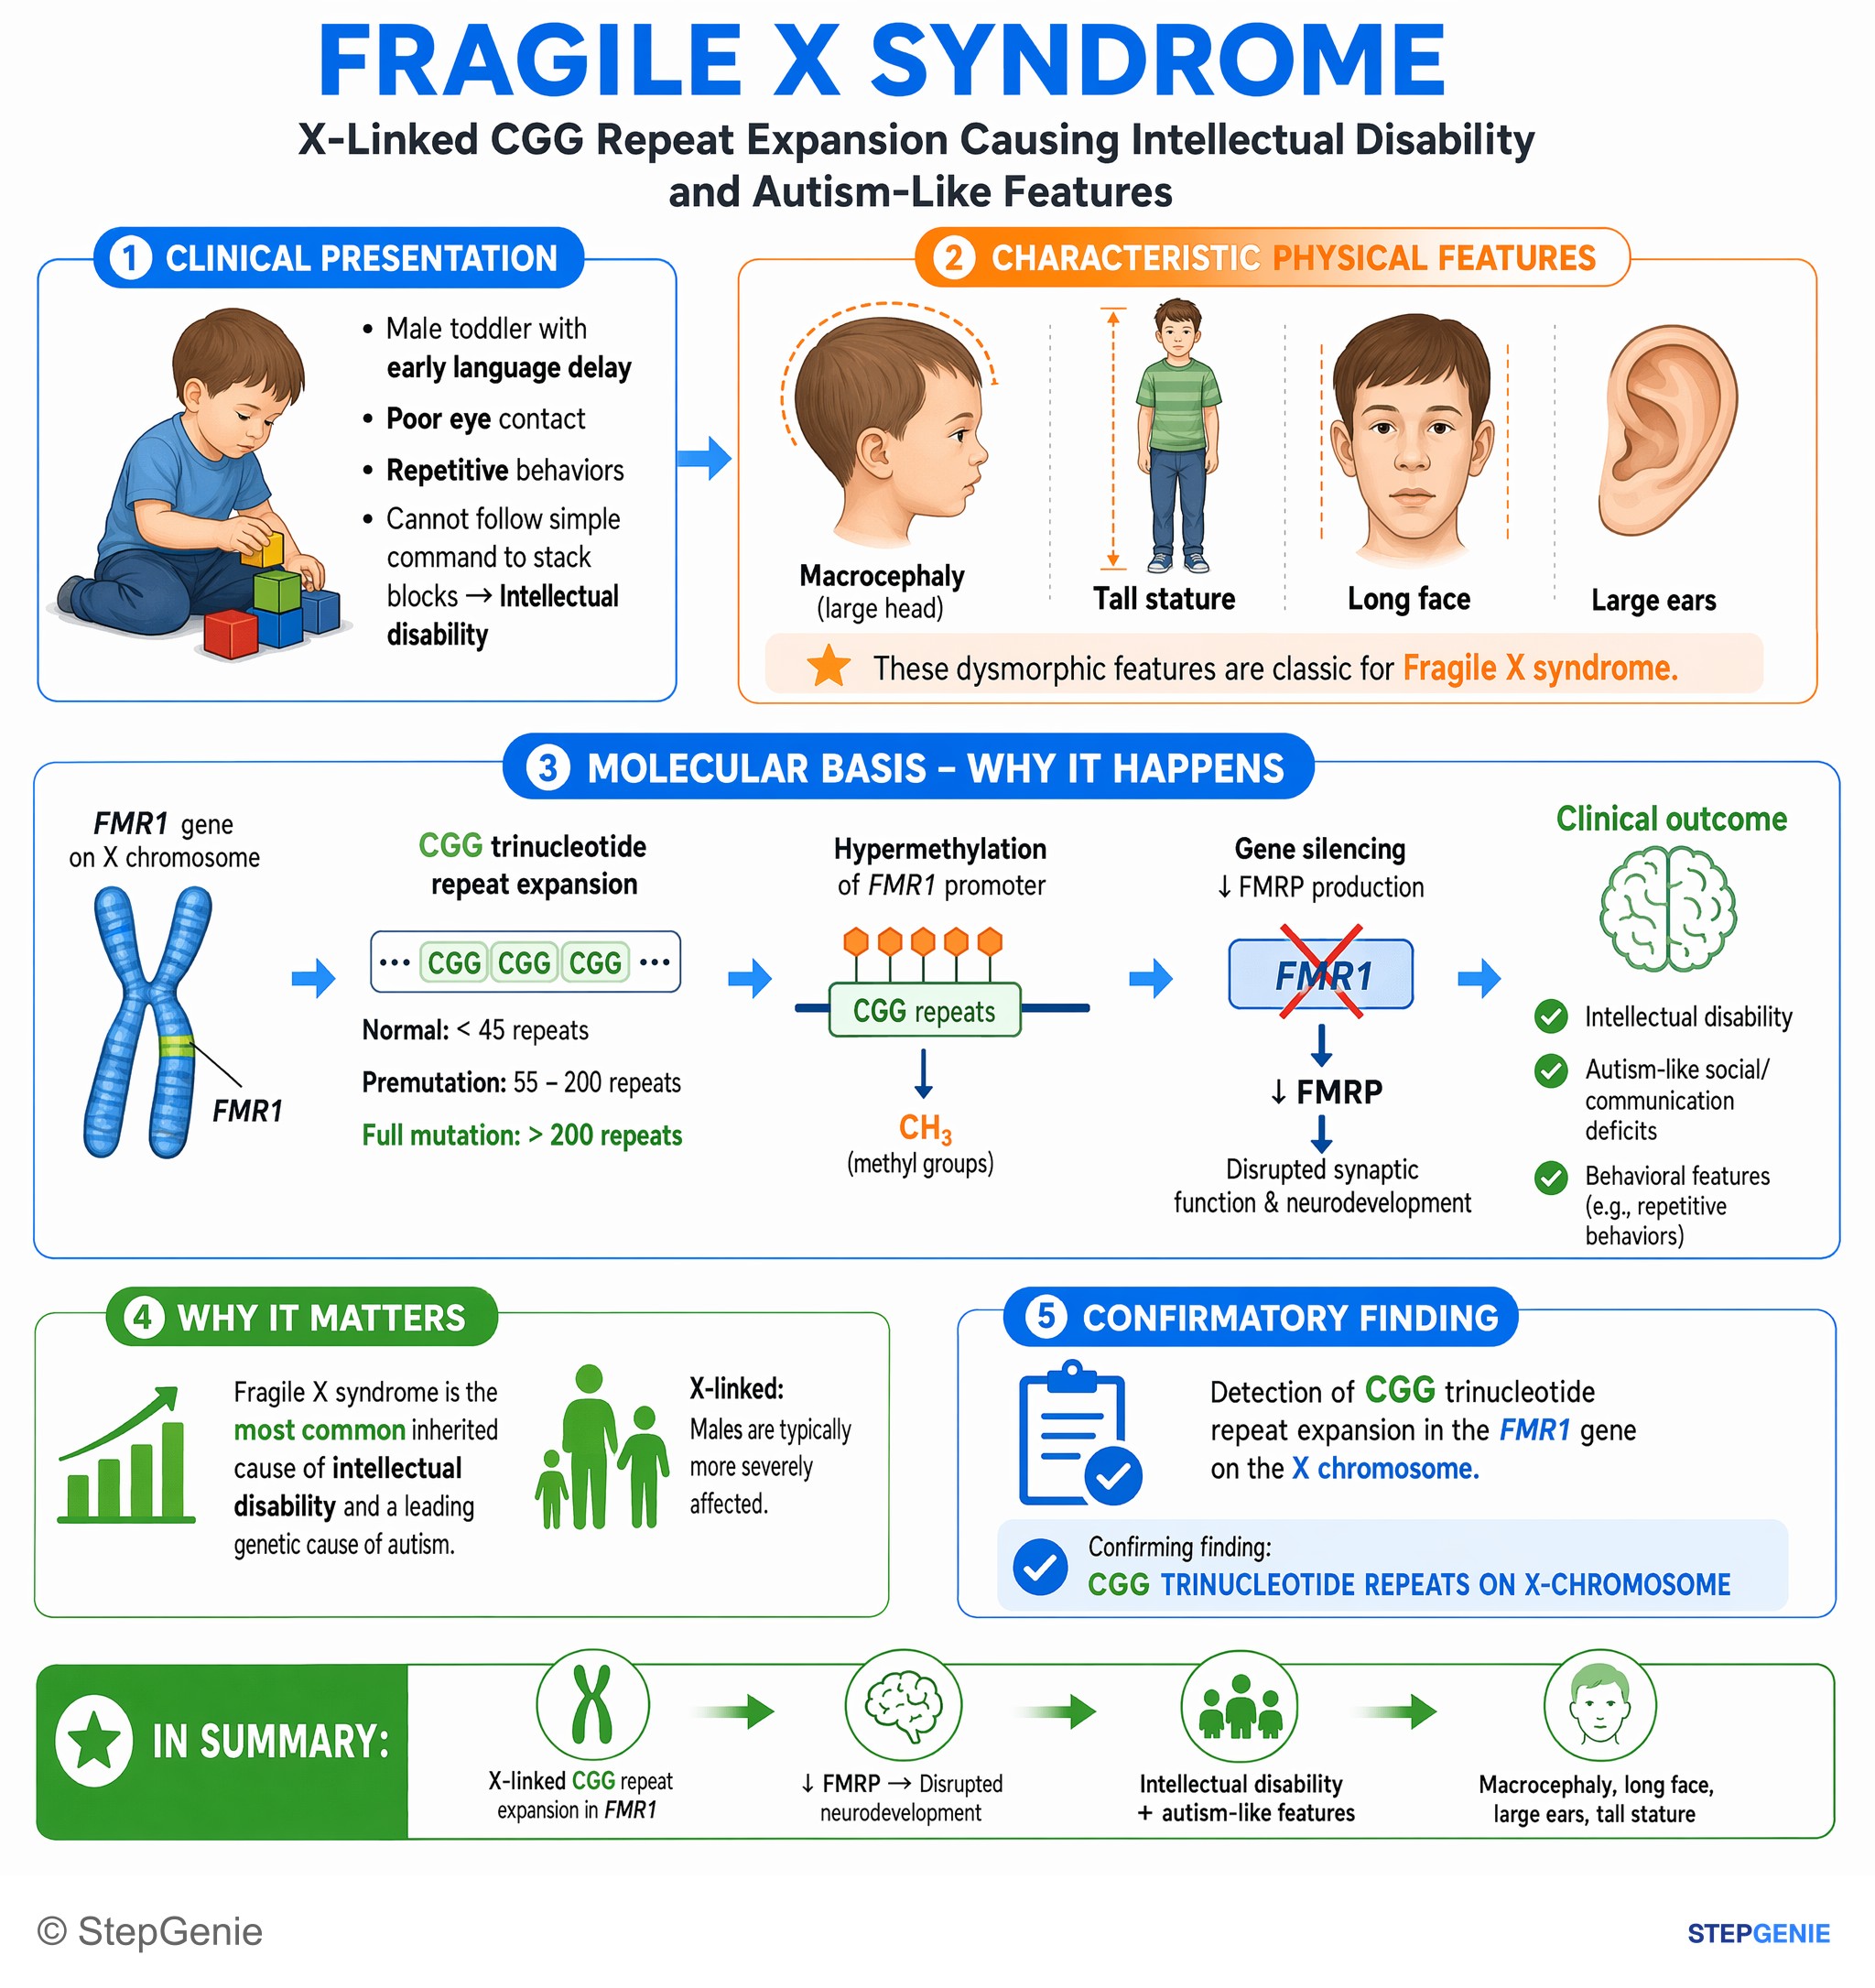
Fragile X syndrome: X-linked CGG repeat expansion → intellectual disability, macrocephaly, long face, large ears, autism-like…
USMLE Step 1Frequently Asked Questions
What causes Fragile X syndrome at the gene level?
Fragile X syndrome is caused by a CGG trinucleotide repeat expansion in the FMR1 gene on the X chromosome. In a full mutation, the repeat expansion leads to hypermethylation and silencing of FMR1, which lowers or eliminates FMRP. Because FMRP regulates translation of synaptic proteins, its loss disrupts synaptic development and plasticity, producing the neurodevelopmental and behavioral phenotype.
How do you tell a full Fragile X mutation from a premutation?
A full Fragile X mutation has more than 200 CGG repeats, is hypermethylated, and causes decreased or absent FMRP, leading to Fragile X syndrome. A premutation has about 55 to 200 repeats and is usually not methylated. Premutation carriers often have increased FMR1 mRNA with toxic gain-of-function effects and are associated with FXTAS and FXPOI rather than classic Fragile X syndrome.
What inheritance pattern and pedigree clues suggest Fragile X syndrome?
Fragile X syndrome is inherited in an X-linked dominant pattern with variable penetrance and expressivity. Classic pedigree clues include no male-to-male transmission, since fathers pass a Y chromosome to sons, and more severe disease in males because they have only one X chromosome. Female carriers can still be symptomatic, often more mildly, because of skewed X-inactivation.
What is the best confirmatory test for Fragile X syndrome?
The best confirmatory test is DNA-based molecular testing that measures CGG repeat number and methylation status in FMR1. PCR is useful for sizing smaller expansions, while Southern blot is historically used to detect larger expansions and methylation status. Although a fragile site on the X chromosome may be suggested cytogenetically, modern diagnosis is made with molecular testing rather than karyotype alone.
What clinical clues make Fragile X a likely diagnosis on a vignette?
Fragile X is especially likely when a male child has developmental delay or intellectual disability along with autism spectrum behaviors and the classic physical findings of a long narrow face, large protruding ears, and macroorchidism. Macroorchidism is typically seen after puberty. A family history of learning problems on the maternal side or an older male relative with tremor and ataxia also supports the diagnosis.