Q-Bank Breakdown: B-vitamin deficiencies — Why Every Answer Choice Matters
Tag: Biochemistry > Vitamins & Cofactors
B-vitamin questions are classic “one symptom = one vitamin” traps—until the test writer adds overlapping clues (neurologic + anemia + dermatitis), and suddenly every answer choice feels plausible. The key is to identify the pathognomonic anchor in the vignette, then use mechanism + associations to eliminate distractors.
Clinical Vignette (USMLE-Style)
A 46-year-old man with long-standing alcohol use presents with progressive difficulty walking and frequent falls. He reports numbness and tingling in both feet. Exam shows decreased vibration and proprioception, a wide-based gait, and mild weakness. Labs show macrocytic anemia. Methylmalonic acid level is elevated.
Which vitamin deficiency is most likely?
A. Thiamine (B1)
B. Riboflavin (B2)
C. Niacin (B3)
D. Pyridoxine (B6)
E. Cobalamin (B12)
F. Folate (B9)
Step-by-Step: Find the “Anchor Clues”
The vignette gives you multiple signals, but two are decisive:
- Posterior column findings: ↓ vibration/proprioception + gait instability
- ↑ Methylmalonic acid (MMA)
Those two together scream B12 deficiency (cobalamin). Alcohol use is common but not diagnostic—it’s there to distract you toward B1/folate.
Correct Answer: E. Cobalamin (Vitamin B12) Deficiency
Why it fits
B12 deficiency classically causes:
- Macrocytic (megaloblastic) anemia
- Neurologic deficits (unlike folate deficiency)
- Posterior column dysfunction → loss of vibration/proprioception, sensory ataxia
- Lateral corticospinal tract involvement → weakness/spasticity
- ↑ Methylmalonic acid and ↑ homocysteine
Pathophysiology (high yield)
Vitamin B12 is required for:
- Methylmalonyl-CoA → Succinyl-CoA (via methylmalonyl-CoA mutase)
- Deficiency → ↑ MMA → abnormal myelin → neurologic dysfunction
- Homocysteine → Methionine (via methionine synthase)
- Deficiency → ↑ homocysteine → endothelial dysfunction risk
Common etiologies you should recognize
- Pernicious anemia (anti–intrinsic factor antibodies; autoimmune gastritis)
- Terminal ileum disease/resection (Crohn disease)
- Dipylobothrium latum (fish tapeworm)
- Strict vegan diet (less common but testable)
USMLE favorite pitfall
Treating presumed folate deficiency can improve anemia while worsening neurologic injury if the true problem is B12 deficiency.
Rule: If macrocytosis is present and cause unclear → check B12 (or MMA) before folate-only therapy.
Why the Other Answer Choices Are Wrong (and When They’d Be Right)
A. Thiamine (B1)
What it’s for (cofactors):
- TPP cofactor for:
- Pyruvate dehydrogenase
- α-ketoglutarate dehydrogenase
- Branched-chain α-ketoacid dehydrogenase
- Transketolase (HMP shunt)
Clinical associations:
- Wernicke encephalopathy: confusion, ophthalmoplegia, ataxia
- Korsakoff syndrome: anterograde amnesia, confabulation
- Wet/dry beriberi (cardiomyopathy vs peripheral neuropathy)
Why it’s not B1 here
- This vignette’s neurologic findings are posterior column (vibration/proprioception loss), which is more consistent with subacute combined degeneration (B12).
- Elevated MMA points to B12, not thiamine.
- B1 deficiency can cause neuropathy/ataxia, especially in alcoholism—but the biochemical marker seals it: MMA.
B. Riboflavin (B2)
What it’s for:
- Precursor of FAD and FMN (redox reactions)
Classic presentation:
- Cheilosis (cracks at corners of mouth)
- Angular stomatitis
- Glossitis
- Corneal vascularization (occasionally referenced)
Why it’s not B2 here
- No mucocutaneous findings.
- Riboflavin deficiency does not cause elevated MMA or posterior column dysfunction.
C. Niacin (B3)
What it’s for:
- Precursor of NAD⁺/NADP⁺
Classic presentation: Pellagra
- Dermatitis, Diarrhea, Dementia (± Death)
- Can occur with Hartnup disease or carcinoid syndrome (tryptophan diverted to serotonin)
Why it’s not B3 here
- The vignette lacks the triad (especially dermatitis/diarrhea).
- Elevated MMA is not a niacin clue.
- “Dementia” in pellagra is cognitive/psychiatric—not posterior column sensory loss.
D. Pyridoxine (B6)
What it’s for (high yield list):
- PLP cofactor for:
- Transamination reactions (ALT/AST)
- Heme synthesis (ALA synthase)
- Neurotransmitters (GABA, dopamine, serotonin, norepinephrine)
- Homocysteine → cystathionine (cystathionine β-synthase)
Classic presentation:
- Peripheral neuropathy, seizures/irritability
- Sideroblastic anemia
- Can be caused by isoniazid, hydralazine, penicillamine, oral contraceptives
Why it’s not B6 here
- Anemia in B6 deficiency is typically microcytic sideroblastic, not macrocytic megaloblastic.
- B6 deficiency can cause neuropathy—but MMA elevation points away from B6 and toward B12.
F. Folate (B9)
What it’s for:
- DNA synthesis (thymidylate and purine synthesis)
Classic presentation:
- Megaloblastic anemia
- ↑ Homocysteine
- Normal MMA
- No neurologic deficits
- Pregnancy risk: neural tube defects
Why it’s not folate here
- The vignette explicitly gives elevated methylmalonic acid, which is not seen in folate deficiency.
- Neurologic deficits (posterior column signs) strongly favor B12 over folate.
USMLE elimination pearl
- B12 deficiency: ↑ homocysteine and ↑ MMA + neuro deficits
- Folate deficiency: ↑ homocysteine only (MMA normal) + no neuro deficits
Rapid-Fire High-Yield Table (B Vitamins)
| Vitamin | Active form | Big functions | Classic deficiency clues |
|---|---|---|---|
| B1 (Thiamine) | TPP | PDH, α-KGDH, BCKDH, transketolase | Wernicke-Korsakoff, beriberi |
| B2 (Riboflavin) | FAD, FMN | Redox reactions | Cheilosis, angular stomatitis, glossitis |
| B3 (Niacin) | NAD⁺/NADP⁺ | Redox reactions | Pellagra: dermatitis, diarrhea, dementia |
| B6 (Pyridoxine) | PLP | Transamination, heme, NT synthesis | Sideroblastic anemia, neuropathy; INH cause |
| B9 (Folate) | THF | DNA synthesis | Megaloblastic anemia; ↑ homocysteine; no neuro |
| B12 (Cobalamin) | (cofactor) | MMA→succinyl-CoA; homocysteine→methionine | Megaloblastic anemia + neuro; ↑ MMA, ↑ homocysteine |
Test-Day Strategy: “Correct Answer + One Sentence per Distractor”
When you review, force yourself to articulate:
- B12: macrocytosis + posterior column signs + ↑ MMA
- B9: macrocytosis but no neuro, MMA normal
- B1: confusion/ophthalmoplegia/ataxia or beriberi—no MMA clue
- B6: sideroblastic anemia + neuropathy (often INH)
- B3: pellagra triad
- B2: mouth/mucosa findings
This builds pattern recognition—and prevents you from missing “one lab value” that flips the answer.
Key Takeaways (High Yield)
- Elevated methylmalonic acid is a powerful discriminator: think B12.
- B12 deficiency causes neurologic deficits; folate deficiency does not.
- Alcohol use can point to several deficiencies—do not anchor on it without a specific clue.
- Treating folate alone can mask B12 deficiency and allow neurologic damage to progress.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
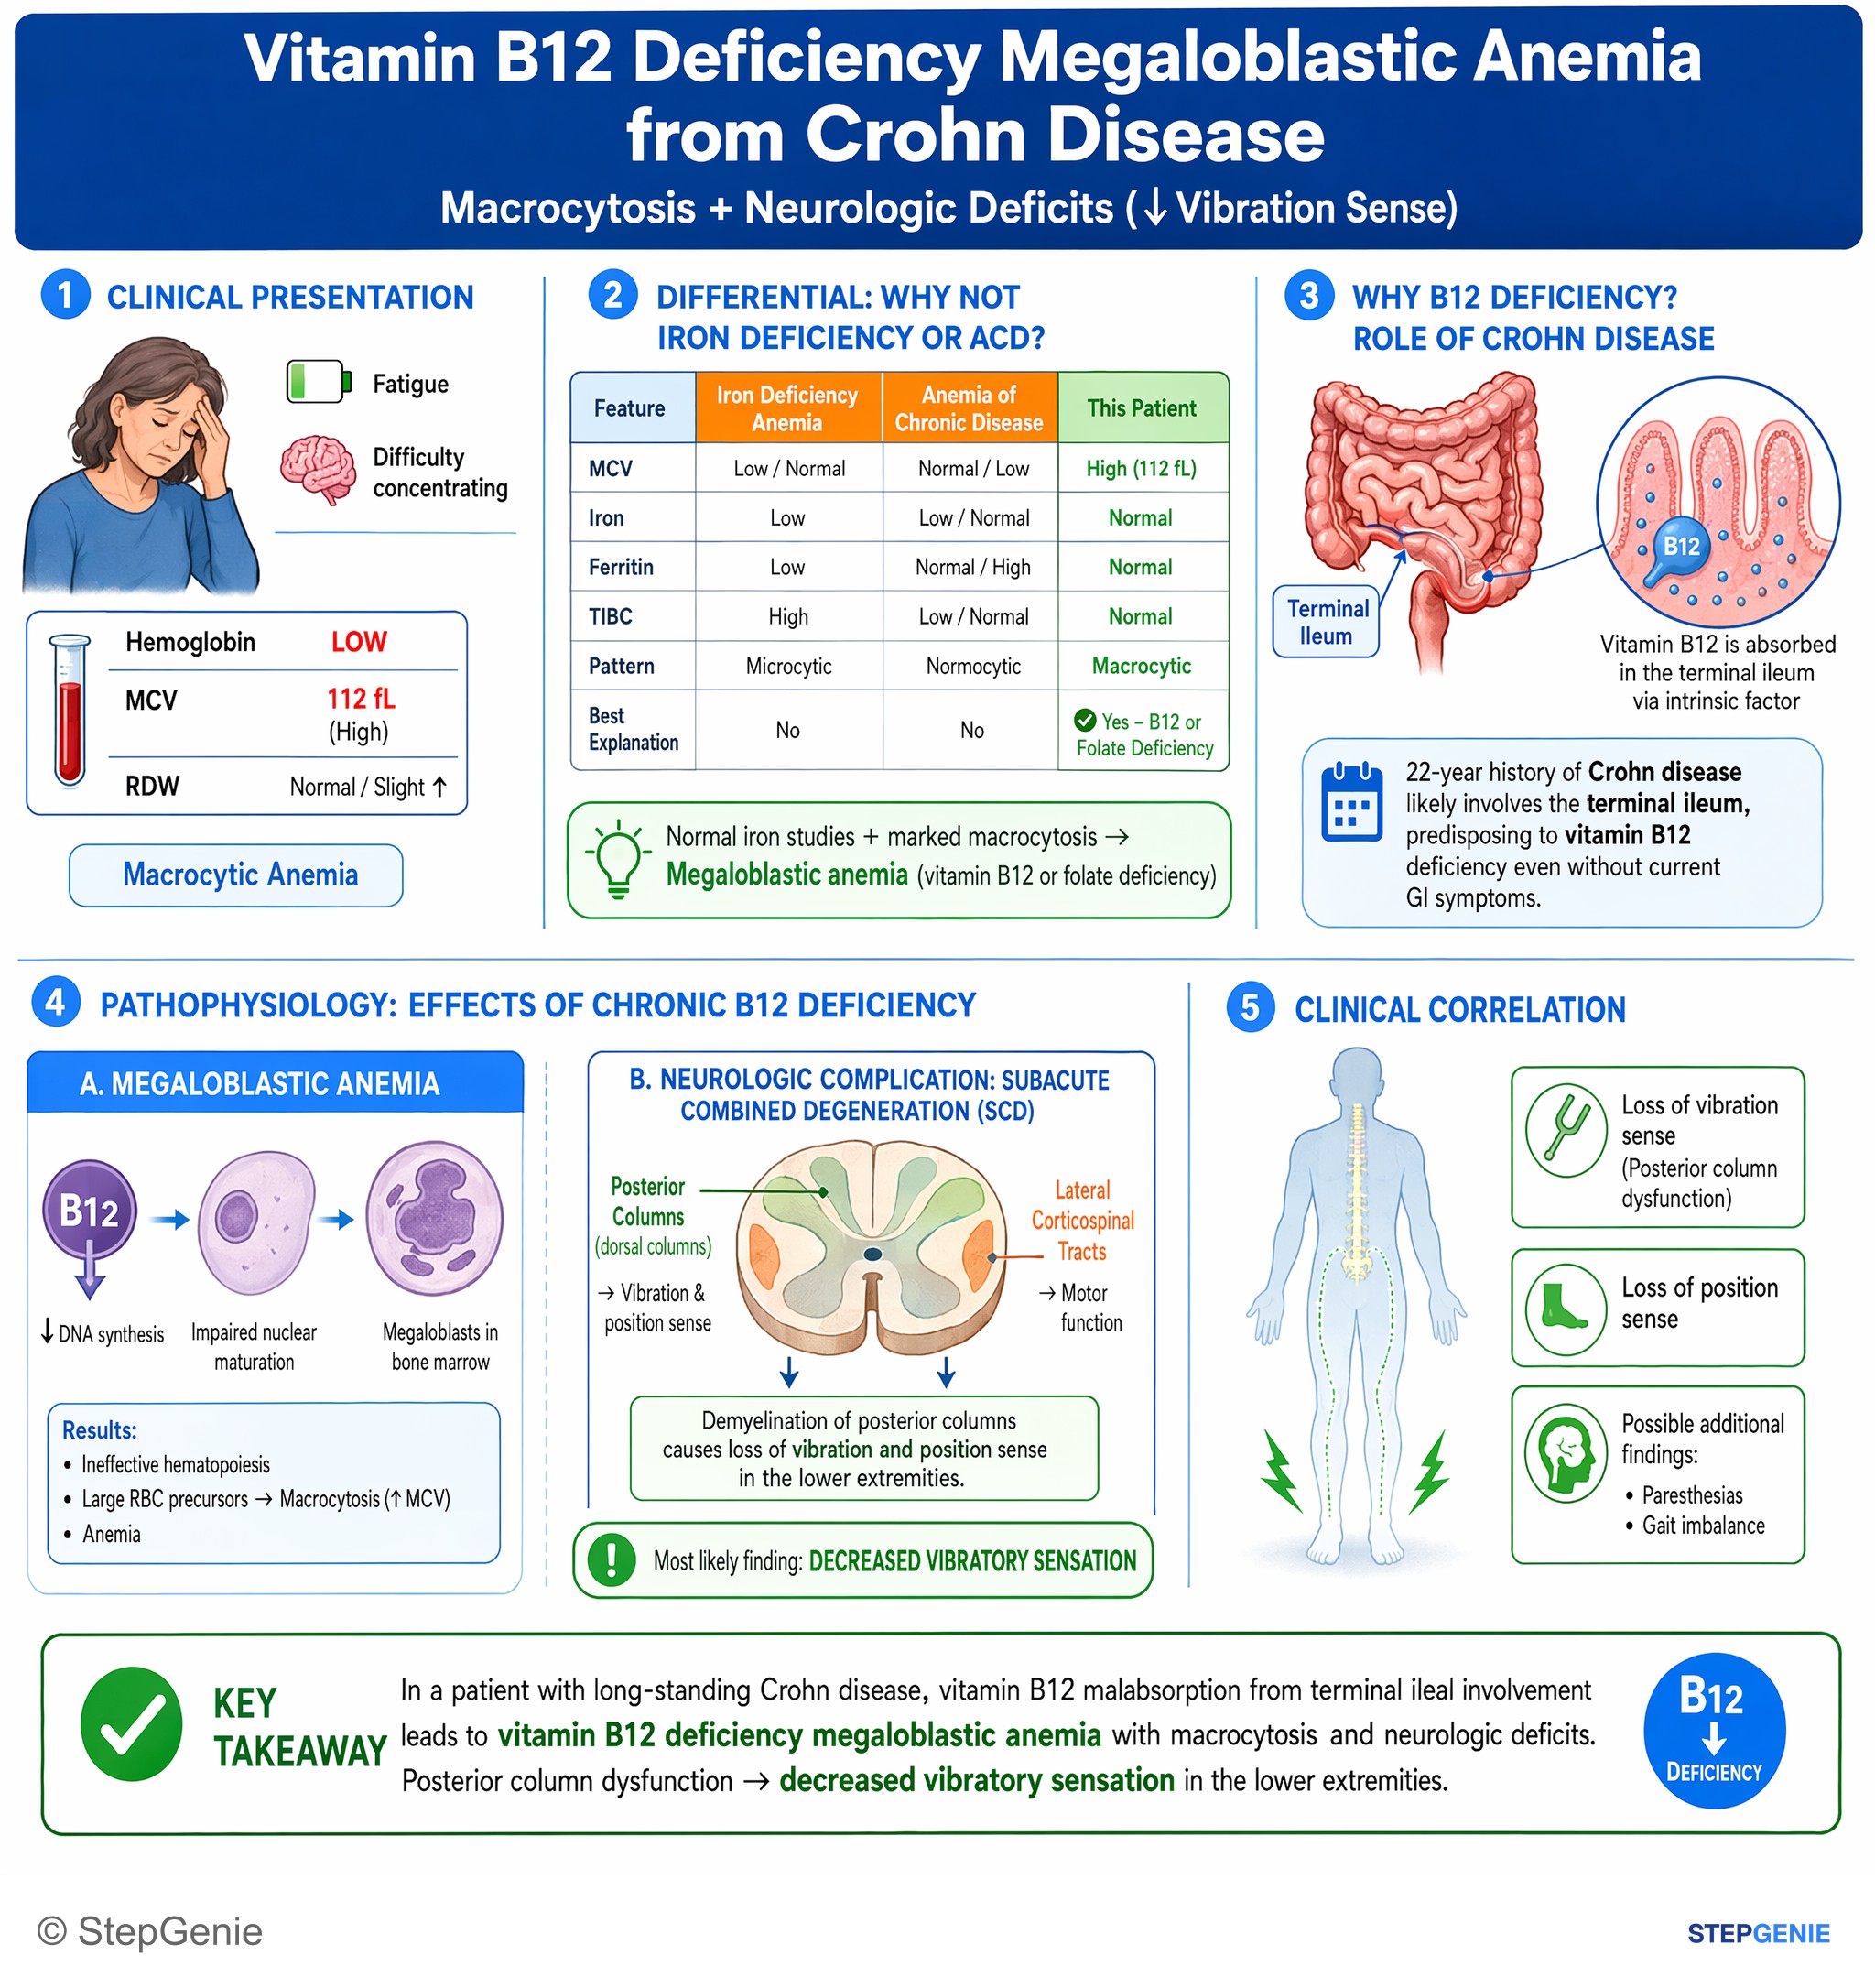
Vitamin B12 deficiency megaloblastic anemia from long-standing Crohn disease causes macrocytosis and neurologic deficits such as decreased…
USMLE Step 1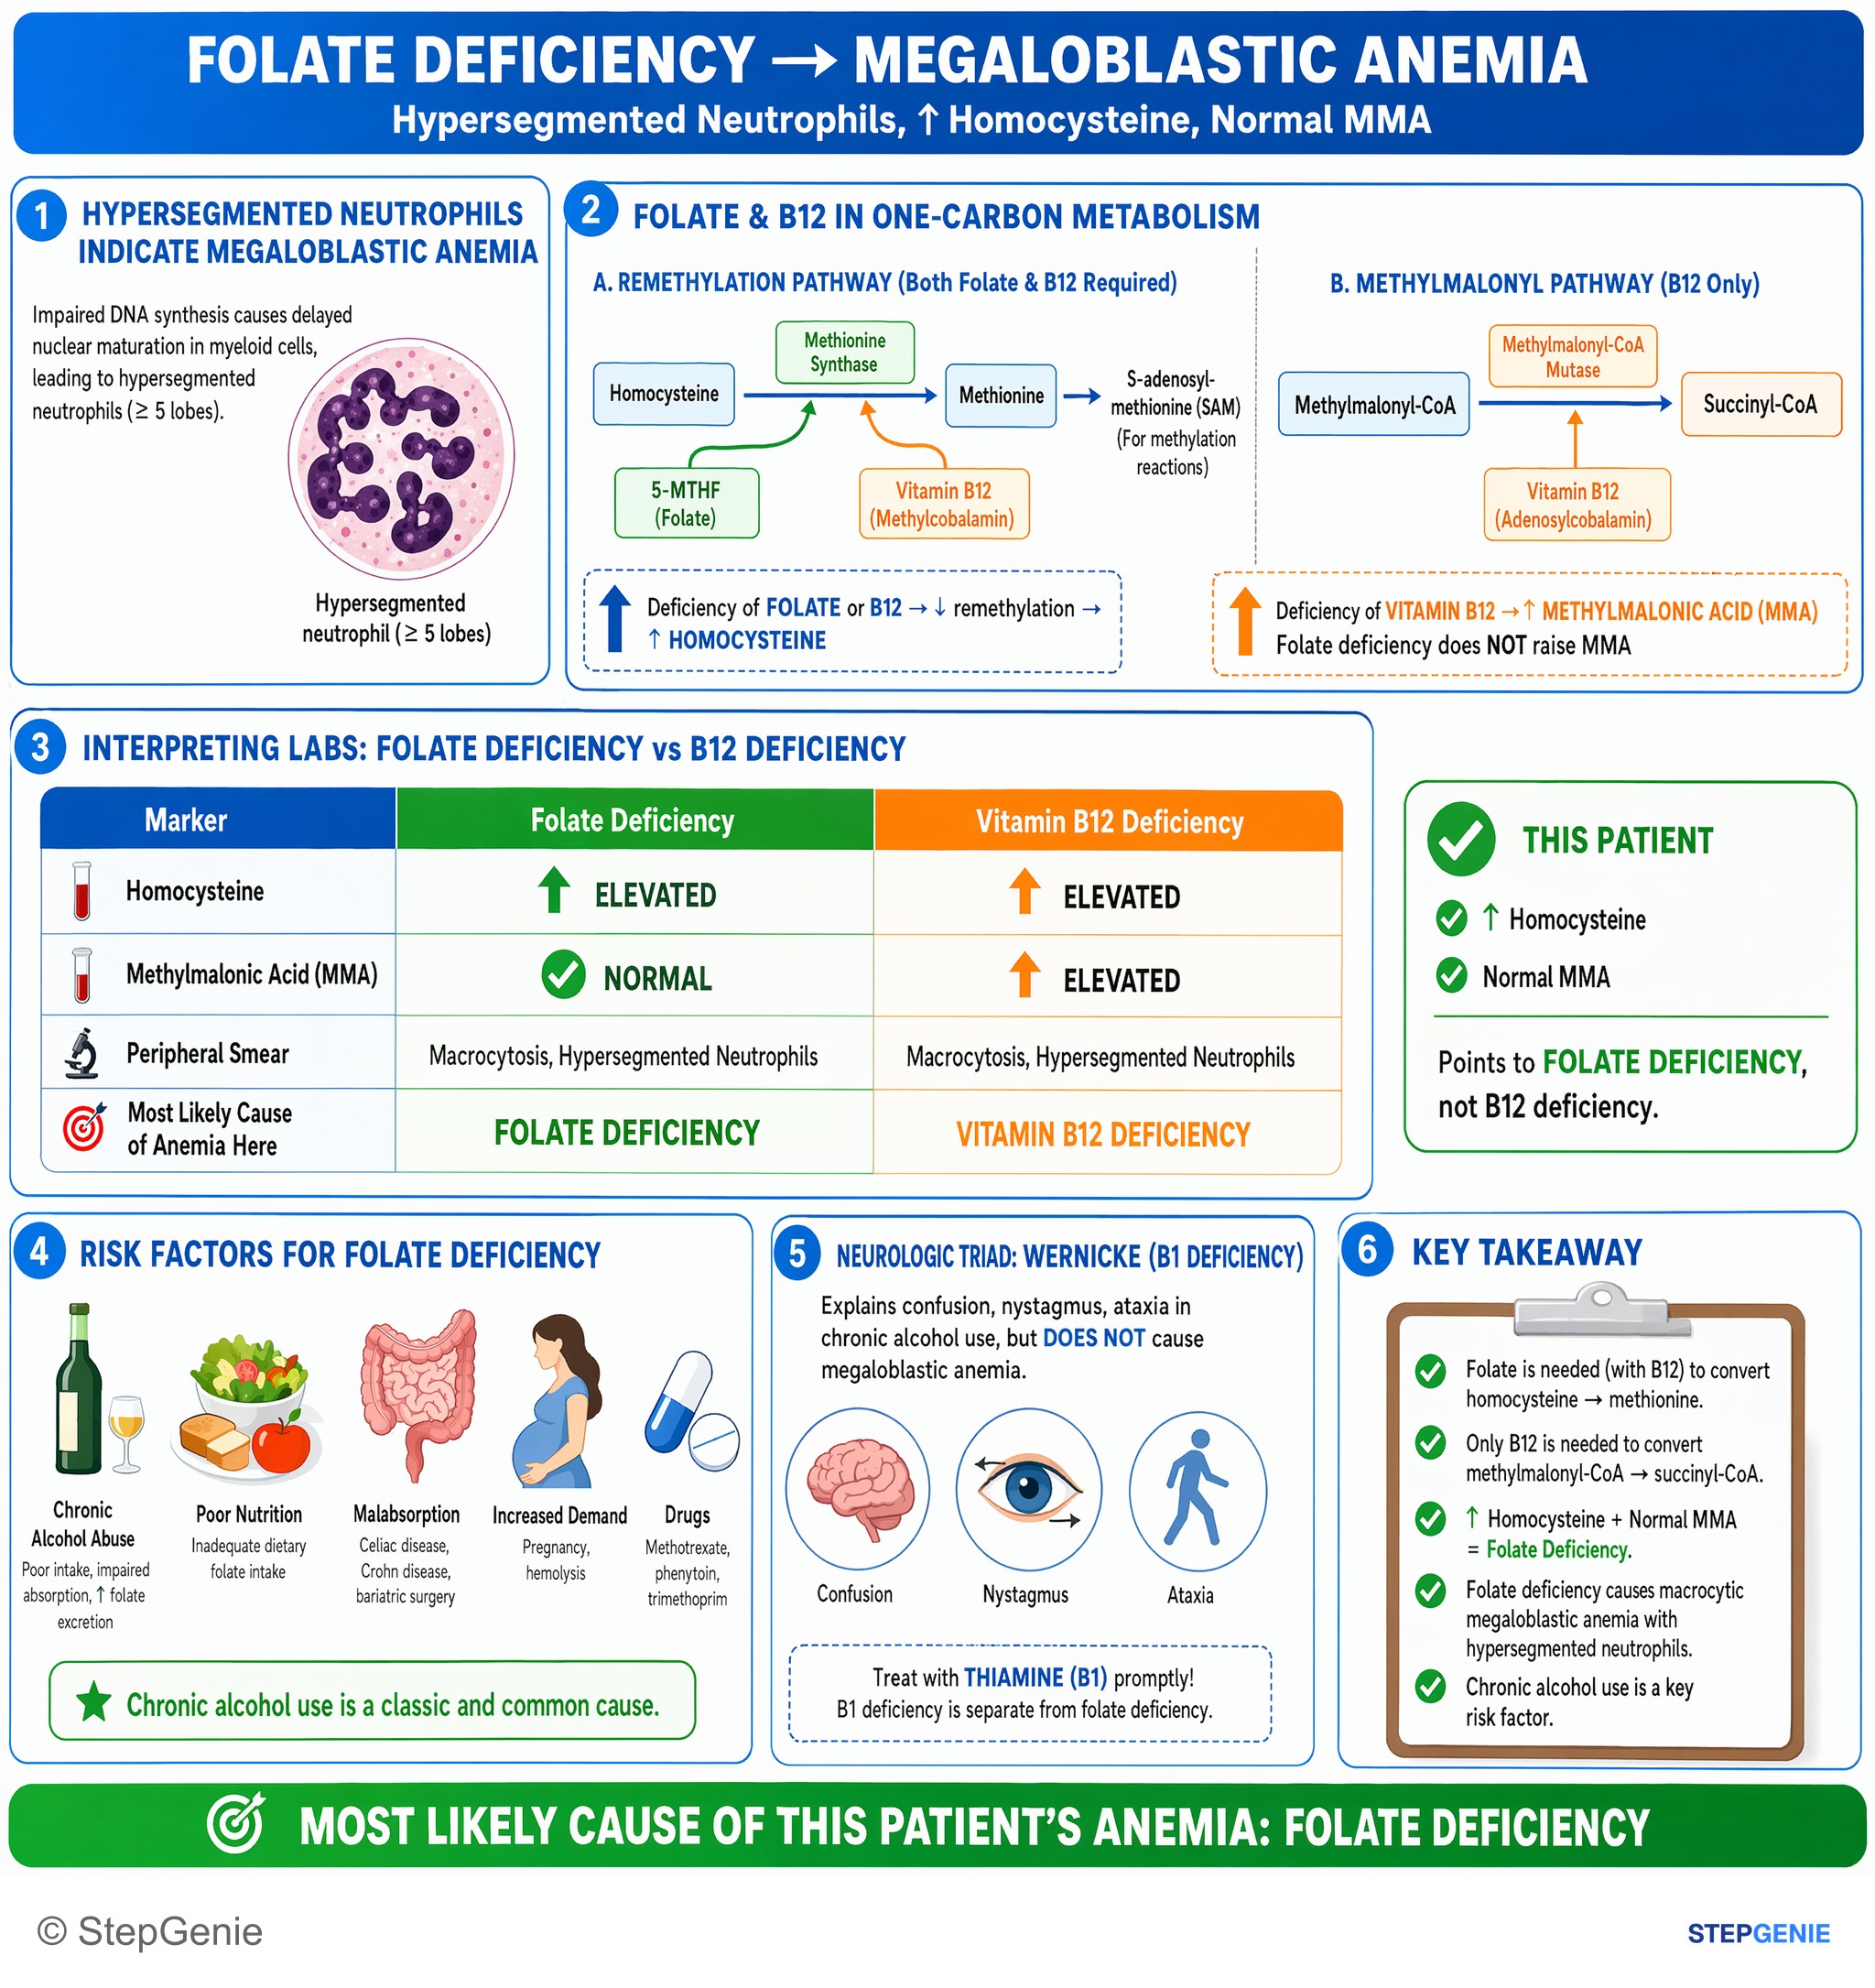
Folate deficiency causes macrocytic megaloblastic anemia with hypersegmented neutrophils, ↑homocysteine, normal methylmalonic acid…
USMLE Step 1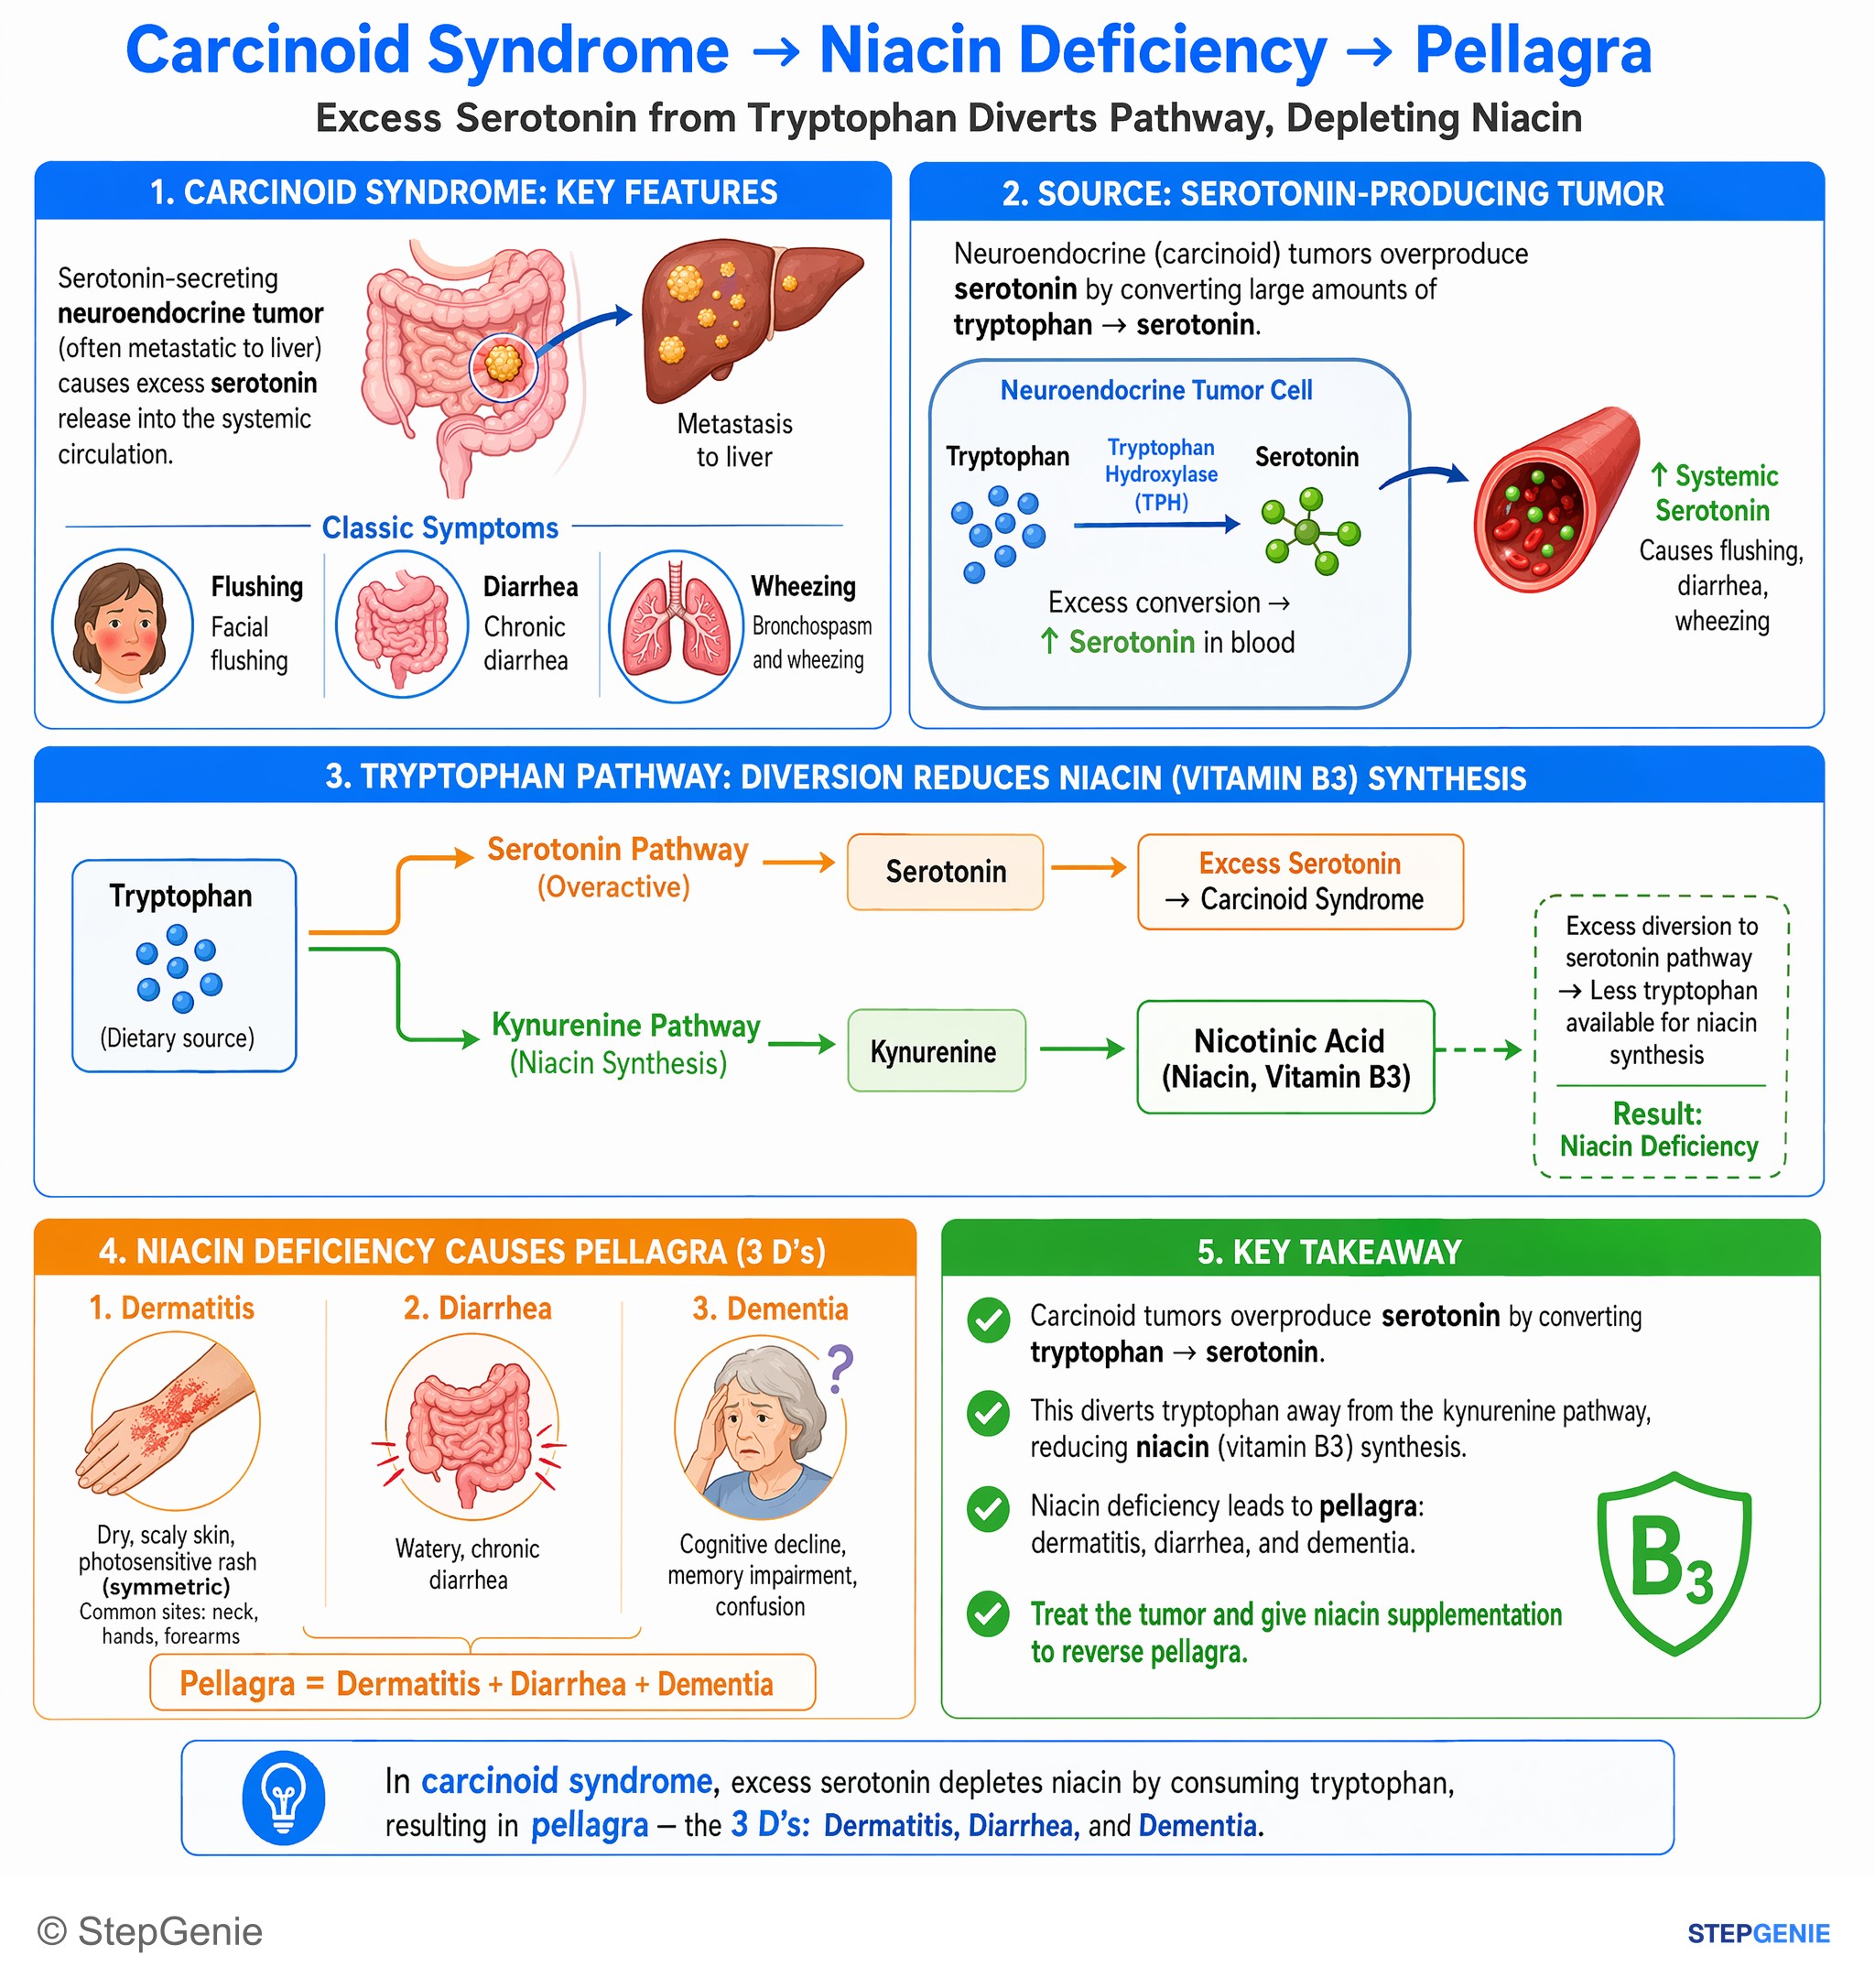
Carcinoid syndrome overproduces serotonin from tryptophan, depleting substrate for niacin synthesis → pellagra (diarrhea, dermatitis…
USMLE Step 1Frequently Asked Questions
How do you tell vitamin B12 deficiency from folate deficiency in a macrocytic anemia question?
Vitamin B12 deficiency is distinguished by neurologic deficits and elevated methylmalonic acid, while folate deficiency has no neurologic deficits and a normal methylmalonic acid level. Both can cause megaloblastic macrocytic anemia and elevated homocysteine, so the key separators are posterior column findings such as loss of vibration and proprioception and the presence of increased MMA, which strongly points to B12 deficiency.
Why does vitamin B12 deficiency cause loss of vibration and proprioception?
Vitamin B12 deficiency causes neurologic dysfunction because B12 is required for conversion of methylmalonyl-CoA to succinyl-CoA. When B12 is deficient, methylmalonic acid accumulates, which is associated with abnormal myelin and leads to neurologic injury. This commonly affects the posterior columns, producing decreased vibration and proprioception, sensory ataxia, and gait instability, and can also involve the lateral corticospinal tracts causing weakness or spasticity.
Why isn’t alcoholism alone enough to make thiamine or folate the best answer choice?
Alcohol use is a distractor unless the vignette’s anchor clues support thiamine or folate deficiency. In a patient with macrocytic anemia, posterior column findings, and elevated methylmalonic acid, the decisive diagnosis is vitamin B12 deficiency. Thiamine deficiency may cause ataxia or neuropathy in alcoholism, and folate deficiency may cause macrocytosis, but neither explains elevated MMA plus posterior column dysfunction.
What clinical clues make vitamin B12 deficiency the most likely diagnosis?
The strongest clues are macrocytic megaloblastic anemia, neurologic deficits, posterior column findings, and elevated methylmalonic acid. A patient with decreased vibration and proprioception, a wide-based gait, numbness and tingling, mild weakness, and macrocytic anemia fits classic B12 deficiency. Elevated MMA is especially helpful because it directly supports cobalamin deficiency and helps eliminate folate and other B-vitamin deficiencies.
Why is folate-only treatment dangerous if the real problem is vitamin B12 deficiency?
Folate-only treatment can improve the anemia while allowing neurologic injury from vitamin B12 deficiency to worsen. That is a classic pitfall in macrocytic anemia questions. Because B12 deficiency causes both megaloblastic anemia and neurologic deficits, the safer approach when the cause of macrocytosis is unclear is to check B12 status, or methylmalonic acid, before giving folate alone.