The fastest way to remember enzyme cofactors is by job: B1 (TPP) decarboxylates α-keto acids and powers transketolase, B2 (FAD/FMN) and B3 (NAD⁺/NADP⁺) carry electrons, B5 (coenzyme A) carries acyl groups, B6 (PLP) runs amino-acid chemistry, B7 (biotin) adds CO₂, B9 (THF) moves one-carbon units, and B12 serves just two enzymes. Use "The Rich Never Pay; Poor Beggars Find Cash" for the order of the B vitamins and "Tender Loving Care For Nancy" for the five cofactors of pyruvate dehydrogenase.
Cofactor vs coenzyme vs prosthetic group
A cofactor is any non-protein helper an enzyme needs: a metal ion or an organic molecule. A coenzyme is an organic cofactor, and a prosthetic group is a cofactor held tightly, sometimes covalently, so it stays on the protein. The protein alone is an inactive apoenzyme; protein plus cofactor is the active holoenzyme. Usage varies; IUPAC calls coenzymes loosely attached and prosthetic groups tightly attached.
| Term | What it means | Examples | Exam angle |
|---|---|---|---|
| Cofactor | Umbrella term: a metal ion or organic molecule an enzyme needs for activity | Zn²⁺ in carbonic anhydrase; Mg²⁺ for ATP-dependent reactions; TPP in pyruvate dehydrogenase | Metal ions are cofactors, not coenzymes |
| Coenzyme | Small, dissociable organic molecule that transfers chemical groups, hydrogen or electrons; many come from B vitamins | NAD⁺, coenzyme A, THF | NADH made in the TCA cycle carries its electrons to complex I |
| Prosthetic group | Tightly bound non-protein part of a protein | Heme in hemoglobin and cytochromes (covalently attached in cytochrome c); FMN in complex I; PLP in ALT and AST; biotin on a lysine of pyruvate carboxylase | ALT/AST assay methods are advised to add PLP, because coenzyme-free apoenzyme also circulates |
| Apoenzyme vs holoenzyme | Inactive protein alone vs protein plus cofactor | Biotin carboxylases are made as inactive apoenzymes | Holocarboxylase synthetase deficiency leaves the biotin carboxylases unactivated (multiple carboxylase deficiency) |
Enzyme cofactor cheat sheet: vitamin, coenzyme, enzymes, deficiency
| Vitamin | Active coenzyme | Classic enzymes and reactions | Deficiency clue |
|---|---|---|---|
| B1 (thiamine) | Thiamine pyrophosphate (TPP; thiamine diphosphate) | Pyruvate dehydrogenase, α-ketoglutarate dehydrogenase, branched-chain α-keto acid dehydrogenase; transketolase (nonoxidative pentose phosphate pathway) | Wernicke encephalopathy (confusion, ophthalmoplegia, ataxia), Korsakoff memory loss, dry beriberi (neuropathy), wet beriberi (high-output heart failure), lactic acidosis |
| B2 (riboflavin) | FAD, FMN | Succinate dehydrogenase (complex II, FAD), complex I (FMN), E3 of the α-keto acid dehydrogenases, MTHFR, glutathione reductase | Angular stomatitis, cheilosis, glossitis, seborrheic dermatitis, normocytic anemia, corneal vascularization |
| B3 (niacin) | NAD⁺, NADP⁺ | NAD⁺: lactate, isocitrate, malate and glyceraldehyde-3-phosphate dehydrogenases; NADPH: steroid and fatty acid synthesis, respiratory burst, glutathione reduction | Pellagra: photosensitive dermatitis (Casal necklace), diarrhea, dementia, then death |
| B5 (pantothenic acid) | Coenzyme A; 4′-phosphopantetheine in acyl carrier protein | Acyl-group transfer: CoA in pyruvate and α-ketoglutarate dehydrogenases; fatty acid synthesis | Rare; "burning feet" (numbness and burning of the hands and feet), headache, fatigue; review books add dermatitis, enteritis, alopecia and adrenal insufficiency, which are poorly documented in humans |
| B6 (pyridoxine) | Pyridoxal 5′-phosphate (PLP) | ALT and AST, glutamate decarboxylase (GABA), histidine decarboxylase (histamine), ALA synthase, cystathionine β-synthase, glycogen phosphorylase, kynureninase (tryptophan → niacin) | Peripheral neuropathy, seizures, microcytic (sideroblastic) anemia, cheilosis, glossitis, confusion |
| B7 (biotin) | Biotin, bound to a lysine of the carboxylase | Pyruvate carboxylase, acetyl-CoA carboxylases 1 and 2, propionyl-CoA carboxylase, 3-methylcrotonyl-CoA carboxylase | Alopecia, periorificial dermatitis, conjunctivitis, depression, hallucinations, paresthesias, organic aciduria |
| B9 (folate) | Tetrahydrofolate (THF) carrying one-carbon units | Thymidylate synthase (dUMP → dTMP), purine synthesis, serine hydroxymethyltransferase; N⁵-methyl-THF feeds methionine synthase | Megaloblastic anemia, hypersegmented neutrophils, glossitis, raised homocysteine with normal MMA; neural tube defects |
| B12 (cobalamin) | Methylcobalamin; adenosylcobalamin | Methionine synthase (homocysteine → methionine); methylmalonyl-CoA mutase (methylmalonyl-CoA → succinyl-CoA) | Megaloblastic anemia plus subacute combined degeneration; raised MMA and homocysteine |
| K | Reduced vitamin K (hydroquinone) | γ-Glutamyl carboxylase: glutamate → γ-carboxyglutamate on factors II, VII, IX and X and proteins C and S | Bleeding with a prolonged PT/INR; vitamin K deficiency bleeding in newborns who miss prophylaxis |
| C | Ascorbate | Prolyl and lysyl hydroxylases (collagen), dopamine → norepinephrine, carnitine synthesis; aids iron absorption | Scurvy: swollen, bleeding gums, perifollicular hemorrhages, corkscrew hairs, poor wound healing |
Tender Loving Care For Nancy: the three α-keto acid dehydrogenases
Pyruvate dehydrogenase (PDH), α-ketoglutarate dehydrogenase (α-KGDH) and branched-chain α-keto acid dehydrogenase (BCKDH) share one three-enzyme plan, so one mnemonic covers them: TPP (B1), Lipoic acid, CoA (B5), FAD (B2), NAD⁺ (B3). In PDH, E1 strips CO₂ from pyruvate and holds the two-carbon remnant on TPP; E2 (dihydrolipoyl transacetylase) passes it through lipoic acid to coenzyme A; and E3 (dihydrolipoyl dehydrogenase) reoxidizes lipoic acid with FAD and hands the electrons to NAD⁺. α-KGDH uses the same five cofactors, and so does BCKDH: a TPP-dependent E1, a lipoyl transacylase E2 that hands the acyl group to CoA, and the very same E3.
| Complex | Reaction | Pathway | When it fails |
|---|---|---|---|
| PDH | Pyruvate → acetyl-CoA + CO₂, with NADH | Links glycolysis to the TCA cycle | Lactic acidosis; inherited PDH deficiency (most often the X-linked E1α gene, PDHA1), thiamine deficiency, arsenic |
| α-KGDH | α-Ketoglutarate → succinyl-CoA + CO₂, with NADH | TCA cycle | Thiamine deficiency (together with PDH and transketolase, it underlies Wernicke's selective brain injury) |
| BCKDH | Oxidative decarboxylation of the α-keto acids made from leucine, isoleucine and valine | Branched-chain amino acid breakdown | Maple syrup urine disease: maple syrup odor in cerumen and urine, encephalopathy, raised alloisoleucine |
Three payoffs of the mnemonic:
- Lipoic acid is not a vitamin. It is synthesized in mitochondria, so its exam hook is poisoning rather than diet. Arsenite binds sulfhydryl groups, and PDH, which needs lipoic acid, is particularly affected; acute poisoning brings vomiting, "rice-water" diarrhea and QTc prolongation.
- E3 is shared. Biallelic DLD variants (dihydrolipoamide dehydrogenase deficiency) impair all three complexes at once, so lactic acidosis can come with raised leucine, isoleucine and valine and urinary α-ketoglutarate, although many patients lack these markers.
- Thiamine is worth a trial. It is routinely given in inherited PDH deficiency, although only a minority respond, and a thiamine trial is considered in maple syrup urine disease (whether truly thiamine-responsive MSUD exists is uncertain).
PDH regulation and the pyruvate carboxylase contrast are in pyruvate dehydrogenase cofactors and regulation.
Six more mnemonics for vitamin cofactors
- "TPN FAD CoA" for the five workhorse coenzymes: TPP (B1), PLP (B6), NAD⁺ (B3), FAD (B2) and CoA (B5).
- B-vitamin order: "The Rich Never Pay; Poor Beggars Find Cash." Thiamine (B1), Riboflavin (B2), Niacin (B3), Pantothenic acid (B5), Pyridoxine (B6), Biotin (B7), Folate (B9), Cobalamin (B12).
- TPP enzymes: "Be APT." Branched-chain α-keto acid dehydrogenase, α-ketoglutarate dehydrogenase, Pyruvate dehydrogenase, Transketolase.
- Biotin carboxylases: "PAP," then "ABC." Pyruvate carboxylase (pyruvate → oxaloacetate, for gluconeogenesis), Acetyl-CoA carboxylase (acetyl-CoA → malonyl-CoA, for fatty acid synthesis), Propionyl-CoA carboxylase (propionyl-CoA → methylmalonyl-CoA, for odd-chain fatty acids and some amino acids). Every biotin carboxylase uses the same recipe, ATP + Biotin + CO₂ (supplied as bicarbonate), and pyruvate carboxylase also needs magnesium.
- B12's two enzymes: "M and M." Methionine synthase (methylcobalamin) and methylmalonyl-CoA mutase (adenosylcobalamin). B12 deficiency raises both homocysteine and methylmalonic acid (MMA); folate deficiency raises homocysteine only.
- PLP: "B6 does amino acids." Transamination (ALT, AST), decarboxylation (GABA, histamine), heme synthesis (ALA synthase, the rate-limiting step), transsulfuration (cystathionine β-synthase), plus glycogen phosphorylase and the tryptophan → niacin pathway. Other control points are in the rate-limiting enzymes table.
Folate and B12: the one-carbon handoff
Folate and B12 meet at methionine synthase: N⁵-methyl-THF hands its methyl group to B12, and methylcobalamin passes it to homocysteine to make methionine, regenerating THF. Without B12, N⁵-methyl-THF cannot pass on its methyl group and accumulates (the "folate trap"), so DNA synthesis stalls and the anemia mimics folate deficiency. Thymidylate synthase uses N⁵,N¹⁰-methylene-THF to turn dUMP into dTMP and leaves dihydrofolate (DHF), which dihydrofolate reductase (DHFR) reduces back to THF with NADPH.
DHFR is where the drugs hit:
- Methotrexate inhibits DHFR. Leucovorin (folinic acid) is a reduced folate that does not need DHFR, so it rescues normal tissues.
- Trimethoprim competitively inhibits DHFR but binds the bacterial enzyme far more strongly than the human one, so folate-deficiency (megaloblastic) anemia from trimethoprim-sulfamethoxazole appears mainly with high doses, prolonged use or low folate stores, and becomes more likely when it is combined with methotrexate or pyrimethamine.
- Phenytoin and sulfasalazine also interfere with folate absorption or metabolism.
| Finding | B12 deficiency | Folate deficiency |
|---|---|---|
| Homocysteine | Raised | Raised |
| Methylmalonic acid | Raised | Normal |
| Neurologic signs (vibration and position loss, spastic weakness) | Typical (subacute combined degeneration) | Generally absent |
| Classic causes | Pernicious anemia, gastrectomy or gastric bypass, ileal resection, strict vegan diet, metformin, acid suppressants, nitrous oxide | Poor intake, alcohol, pregnancy (higher demand), methotrexate, trimethoprim, phenytoin, sulfasalazine |
Exclude B12 deficiency before treating a megaloblastic anemia with folate alone: folic acid or leucovorin can correct the anemia while the neurologic damage persists or worsens. The full workup is in megaloblastic anemia: B12 vs folate.
Metal cofactors that are high-yield
Zinc, copper, magnesium, molybdenum, iron and selenium each pair a signature enzyme with a signature deficiency or genetic disease.
| Metal | Enzymes or proteins that need it | Exam association |
|---|---|---|
| Zinc | Carbonic anhydrase, ALA dehydratase (heme synthesis), alkaline phosphatase, Cu/Zn superoxide dismutase; zinc-containing transcription factors | Acrodermatitis enteropathica (SLC39A4): periorificial and acral rash, alopecia, diarrhea; impaired taste and smell, poor wound healing, hypogonadism, low alkaline phosphatase; excess zinc causes copper deficiency |
| Copper | Cytochrome c oxidase (complex IV), lysyl oxidase, dopamine β-hydroxylase, tyrosinase, superoxide dismutase; ceruloplasmin (a ferroxidase) | Menkes disease (ATP7A, X-linked); acquired deficiency causes anemia or pancytopenia and a myelopathy that mimics B12 deficiency; Wilson disease (ATP7B) is the copper-overload counterpart |
| Magnesium | ATP-dependent reactions (over 300 reactions in all), pyruvate carboxylase, TPP-dependent enzymes | Low magnesium makes hypokalemia and hypocalcemia refractory (renal potassium wasting, less PTH release) |
| Molybdenum | Molybdopterin cofactor of xanthine oxidase, sulfite oxidase, aldehyde oxidase and mARC | Xanthine oxidase makes uric acid; inherited molybdenum cofactor deficiency causes neonatal encephalopathy and seizures; acquired deficiency has been reported once, on molybdenum-free parenteral nutrition |
| Iron | Heme in hemoglobin, myoglobin, cytochromes (including CYP450), catalase and nitric oxide synthase; iron–sulfur clusters in aconitase and complexes I–III | Microcytic iron-deficiency anemia; ring sideroblasts are iron-laden mitochondria in erythroid precursors when heme synthesis fails |
| Selenium | Selenocysteine in glutathione peroxidases, thioredoxin reductases and iodothyronine deiodinases (T4 → T3) | Keshan disease, a cardiomyopathy of selenium-poor regions |
Cofactors also stack. Each subunit of xanthine oxidase carries FAD, a molybdenum cofactor and two iron–sulfur clusters, and magnesium is needed by TPP-dependent enzymes, so low magnesium can blunt the response to thiamine in Wernicke encephalopathy.
Clinical links: what the stem is pointing to
| If the stem says… | Think… | Cofactor logic |
|---|---|---|
| Alcohol use disorder with confusion, ophthalmoplegia and ataxia, worse after IV dextrose | Thiamine (TPP) | PDH, α-KGDH and transketolase fail in high-demand brain regions |
| Isoniazid with numbness and tingling, or isoniazid overdose with seizures | Pyridoxine (PLP) | Isoniazid metabolites interfere with B6 metabolism; pyridoxine 25–50 mg/day prevents neuropathy; overdose seizures need pyridoxine gram for gram plus a benzodiazepine |
| Isoniazid, carcinoid syndrome or Hartnup disease with a sun-exposed rash and diarrhea | Niacin (NAD⁺) | Isoniazid lowers PLP-dependent kynureninase; carcinoid diverts tryptophan to serotonin; Hartnup disease impairs tryptophan absorption |
| Methotrexate, trimethoprim or phenytoin with macrocytic anemia | Folate (THF) | Methotrexate and trimethoprim inhibit DHFR; leucovorin bypasses it |
| Macrocytic anemia with raised MMA; metformin, acid suppressants, strict vegan diet, ileal resection or nitrous oxide | Vitamin B12 | The adenosylcobalamin-dependent mutase fails; nitrous oxide oxidizes the cobalt in cobalamin |
| Large amounts of raw egg white, long-term anticonvulsants or antibiotics, parenteral nutrition without biotin | Biotin | Avidin in raw egg white binds biotin; cooking denatures avidin |
| Exclusively breastfed newborn who missed vitamin K at birth; warfarin; malabsorption | Vitamin K | Clotting factors lack γ-carboxylation, so the PT rises |
Thiamine before glucose, current guidance: IV glucose given to a thiamine-deficient patient can trigger or worsen Wernicke encephalopathy, so give thiamine before or together with glucose, but do not delay treatment of significant hypoglycemia while waiting for it. Presentation and dosing are covered in thiamine deficiency: beriberi, Wernicke and TPP enzymes.
Classic exam traps
- Carboxylase or decarboxylase? Biotin adds CO₂; TPP removes it from α-keto acids; PLP removes it from amino acids (glutamate → GABA, histidine → histamine). γ-Carboxylation of clotting factors runs on vitamin K and is not one of the five biotin carboxylases.
- Warfarin doesn't block the carboxylase. It inhibits vitamin K epoxide reductase (VKORC1), so vitamin K can't be recycled to its active, reduced form.
- Riboflavin activates other vitamins. FMN is needed to make PLP, and FAD to make niacin from tryptophan and to run MTHFR, so B2 deficiency drags down B6, niacin and folate metabolism.
- Vitamin status tests are often enzyme assays. Red-cell transketolase (B1), erythrocyte glutathione reductase activation coefficient (EGRac, B2) and erythrocyte aminotransferase activity (B6); MMA is the most sensitive marker for B12.
- Biotin megadoses distort lab tests. Streptavidin–biotin immunoassays can read falsely high or low; the FDA reported a death after a falsely low troponin in a patient taking high-dose biotin.
- Big doses can rescue a weak cofactor site. X-linked sideroblastic anemia (ALAS2) can respond partly or fully to pyridoxine, and some cystathionine β-synthase homocystinuria is B6-responsive.
Worked examples
Vignette 1. A 38-year-old man started isoniazid for latent tuberculosis 3 months ago but skipped his prescribed pyridoxine. He now has numbness and tingling in both feet, diarrhea, poor concentration, and a scaly, darkened rash on his neck and forearms that worsens in the sun. Deficiency of which active cofactor best explains all of his findings?
Answer: Pyridoxal 5′-phosphate (PLP), the active form of vitamin B6.
Reasoning: Isoniazid metabolites interfere with B6 metabolism, causing the neuropathy, and PLP-dependent kynureninase is needed to make niacin from tryptophan, so the same deficiency produces pellagra's dermatitis, diarrhea and dementia. PLP is the best single answer because it is the upstream defect: it causes the neuropathy directly and the pellagra indirectly, whereas NAD⁺ deficiency could explain the rash and diarrhea but not why skipping pyridoxine matters.
Vignette 2. A 64-year-old woman who has taken metformin for type 2 diabetes for 9 years reports fatigue and unsteadiness. She has reduced vibration and position sense in both feet and a positive Romberg sign. Hemoglobin is 9.6 g/dL, MCV is 112 fL and the smear shows hypersegmented neutrophils. Homocysteine and methylmalonic acid are both elevated. Which enzyme, using which form of its cofactor, explains the raised methylmalonic acid?
Answer: Methylmalonyl-CoA mutase, which needs adenosylcobalamin (vitamin B12).
Reasoning: Metformin can reduce B12 absorption. Homocysteine rises in both B12 and folate deficiency because methionine synthase stalls, but only B12 deficiency raises MMA, and the dorsal-column signs fit subacute combined degeneration. Folic acid alone could improve the anemia while the neurologic damage progresses.
Key takeaways
- Learn cofactors by job: TPP decarboxylates, FAD/FMN and NAD(P)⁺ carry electrons, CoA carries acyl groups, PLP handles amino acids, biotin adds CO₂ and THF moves one-carbon units.
- Cofactor is the umbrella term, coenzyme means organic and dissociable, and prosthetic group means tightly bound (heme, biotin on its carboxylase).
- "Tender Loving Care For Nancy" = TPP, lipoic acid, CoA, FAD and NAD⁺ for PDH, α-KGDH and BCKDH, which share one E3.
- B12 vs folate: both raise homocysteine; only B12 deficiency raises MMA.
- Drug links: isoniazid → B6 (neuropathy, pellagra, sideroblastic anemia); methotrexate and trimethoprim → DHFR; warfarin → VKORC1; raw egg whites → biotin.
- Metals: zinc (carbonic anhydrase), copper (cytochrome c oxidase, lysyl oxidase), magnesium (ATP), molybdenum (xanthine oxidase), iron (heme, iron–sulfur clusters), selenium (glutathione peroxidase).
More biochemistry reviews are collected on the biochemistry topic hub.
Sources
- Biochemistry, Water Soluble Vitamins — StatPearls, NCBI Bookshelf
- Cofactors — IUPAC Compendium of Chemical Terminology (Gold Book)
- Biochemistry, Citric Acid Cycle — StatPearls, NCBI Bookshelf
- Maple Syrup Urine Disease — GeneReviews, NCBI Bookshelf
- Dihydrolipoamide Dehydrogenase Deficiency — GeneReviews, NCBI Bookshelf
- EC 1.8.1.4, dihydrolipoyl dehydrogenase — IUBMB Enzyme Nomenclature
- Vitamin B1 (Thiamine) Deficiency — StatPearls, NCBI Bookshelf
- Wernicke-Korsakoff Syndrome — StatPearls, NCBI Bookshelf
- Riboflavin Deficiency — StatPearls, NCBI Bookshelf
- Niacin Deficiency — StatPearls, NCBI Bookshelf
- Vitamin B6 (Pyridoxine) — StatPearls, NCBI Bookshelf
- Biotin Deficiency — StatPearls, NCBI Bookshelf
- Biochemistry, Tetrahydrofolate — StatPearls, NCBI Bookshelf
- Vitamin B12 (Cobalamin) — StatPearls, NCBI Bookshelf
- Vitamin K — StatPearls, NCBI Bookshelf
- Arsenic Toxicity — StatPearls, NCBI Bookshelf
- Pantothenic Acid: Fact Sheet for Health Professionals — NIH Office of Dietary Supplements
- Vitamin B12: Fact Sheet for Health Professionals — NIH Office of Dietary Supplements
- Biotin: Fact Sheet for Health Professionals — NIH Office of Dietary Supplements
- Molybdenum: Fact Sheet for Health Professionals — NIH Office of Dietary Supplements
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
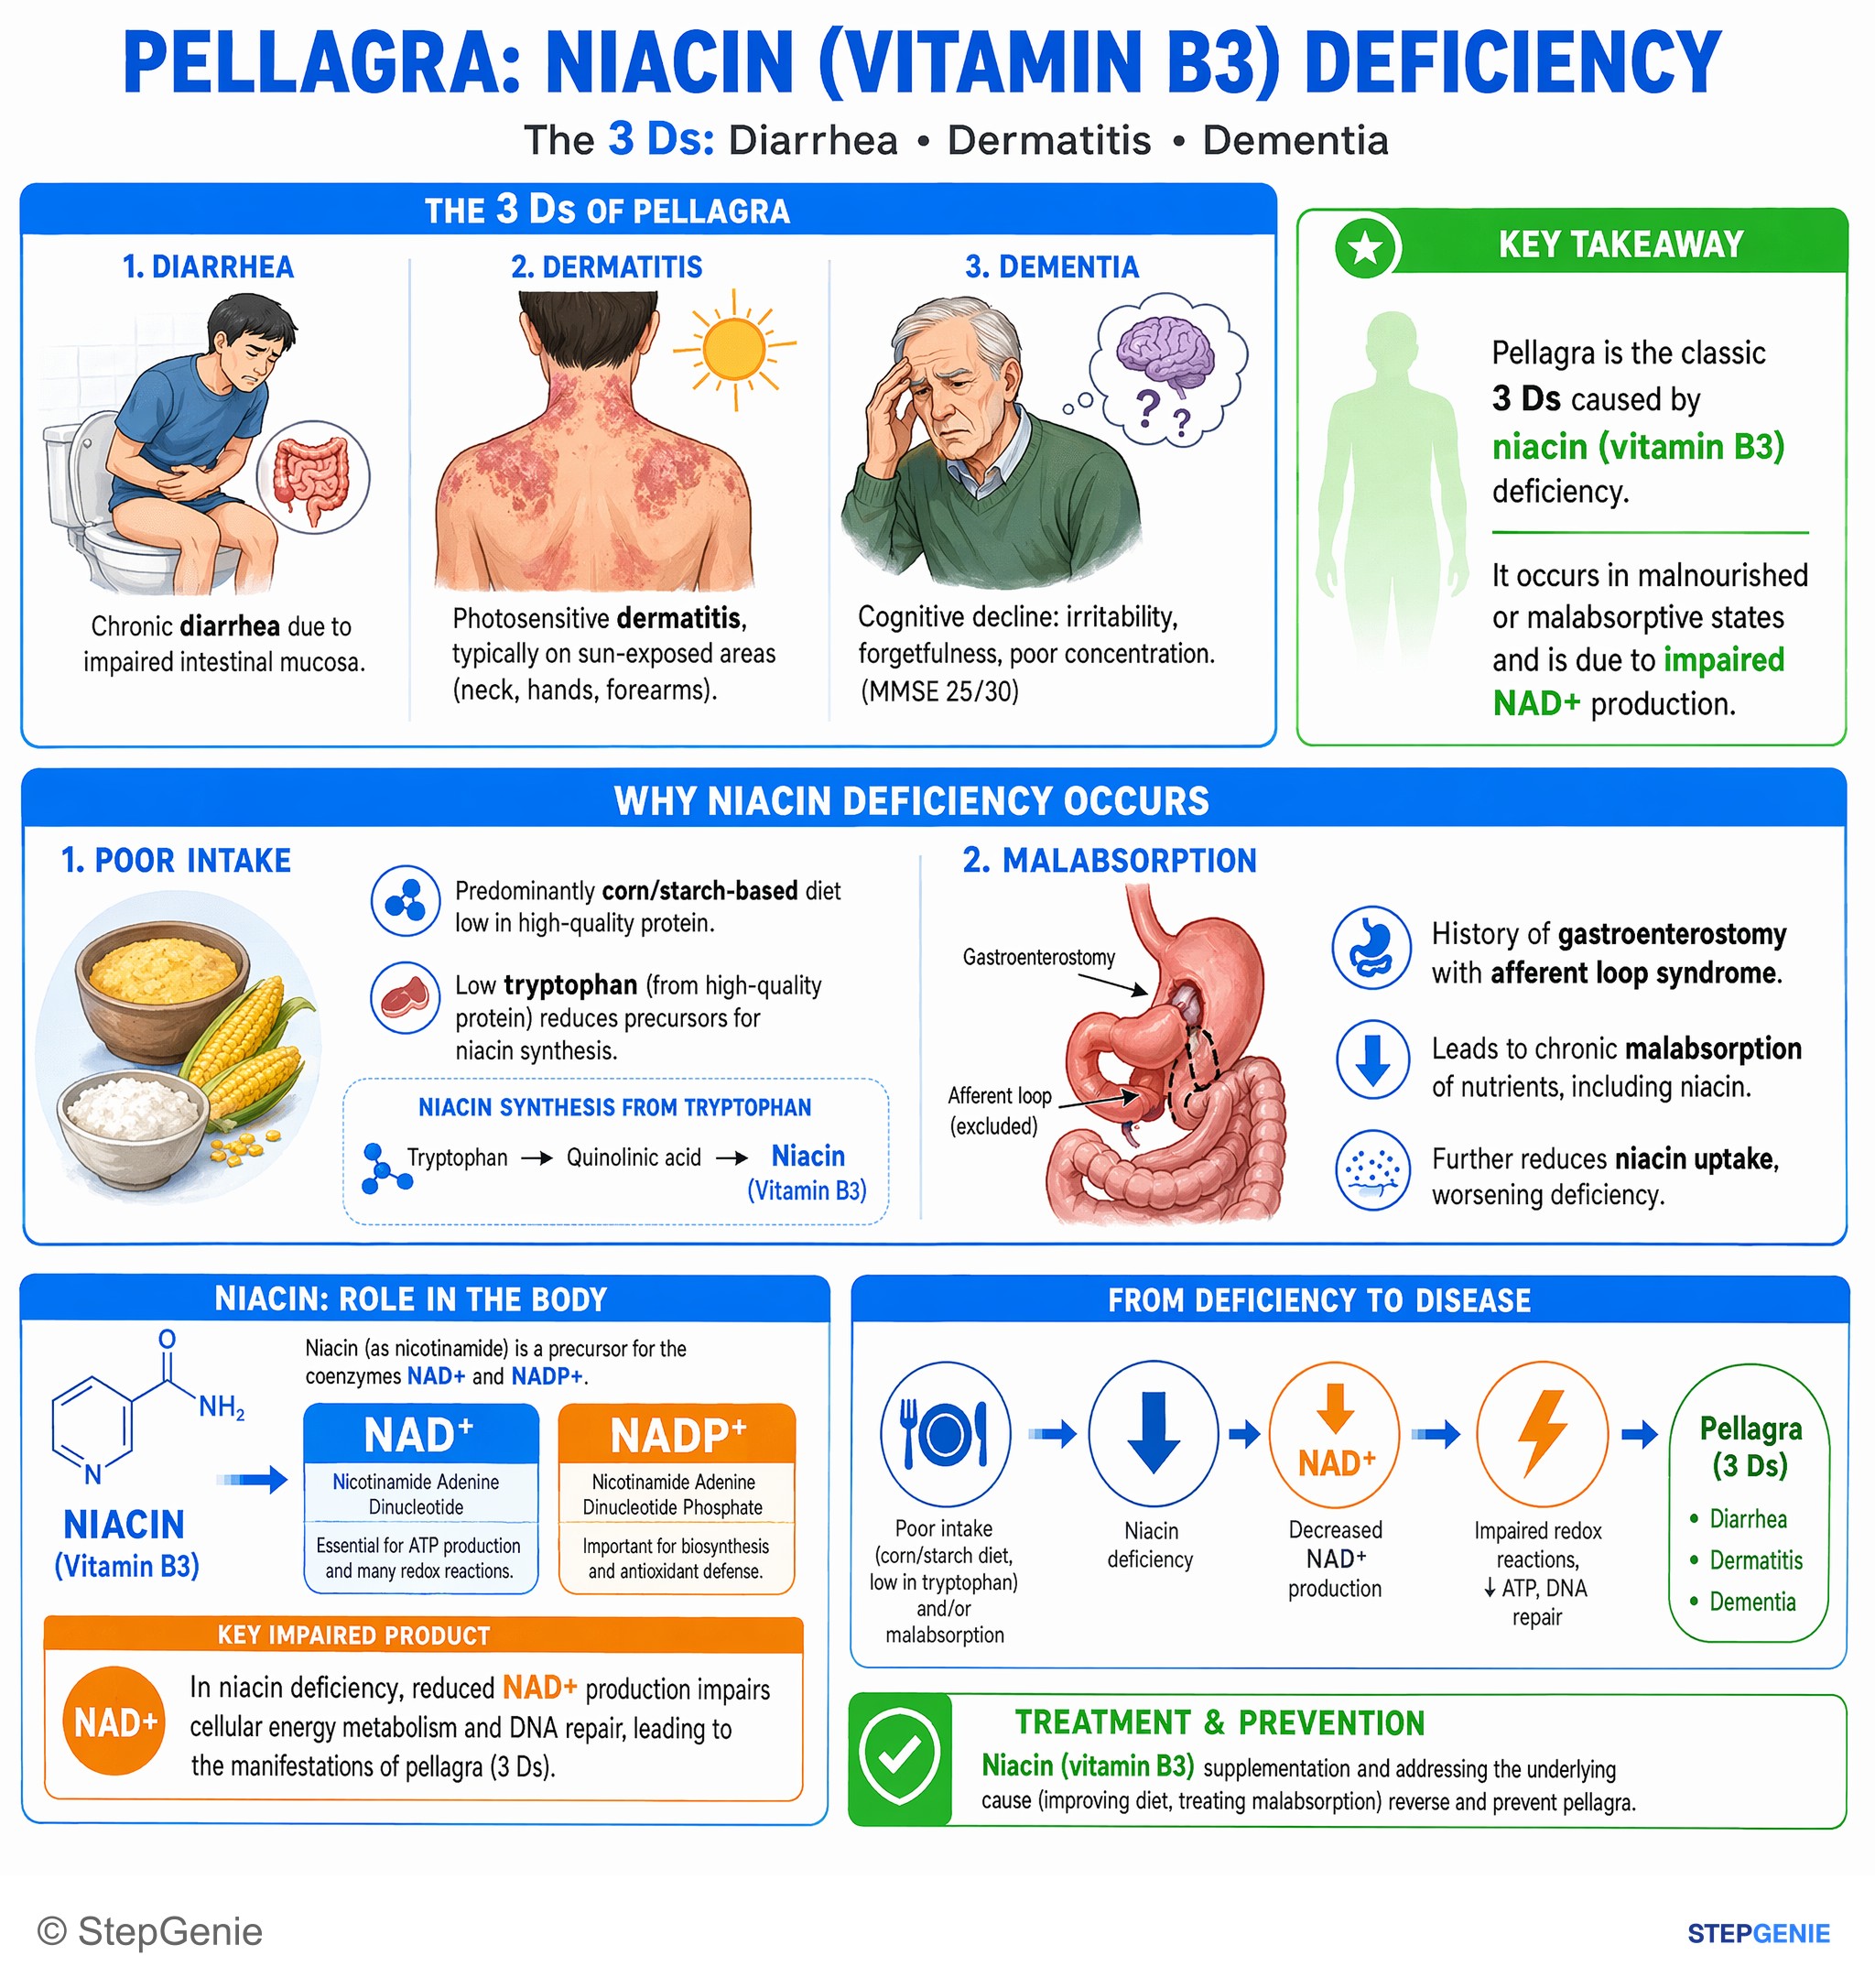
Pellagra from niacin (vitamin B3) deficiency → impaired NAD+ production, causing dermatitis, diarrhea, and dementia in malnourished or…
USMLE Step 1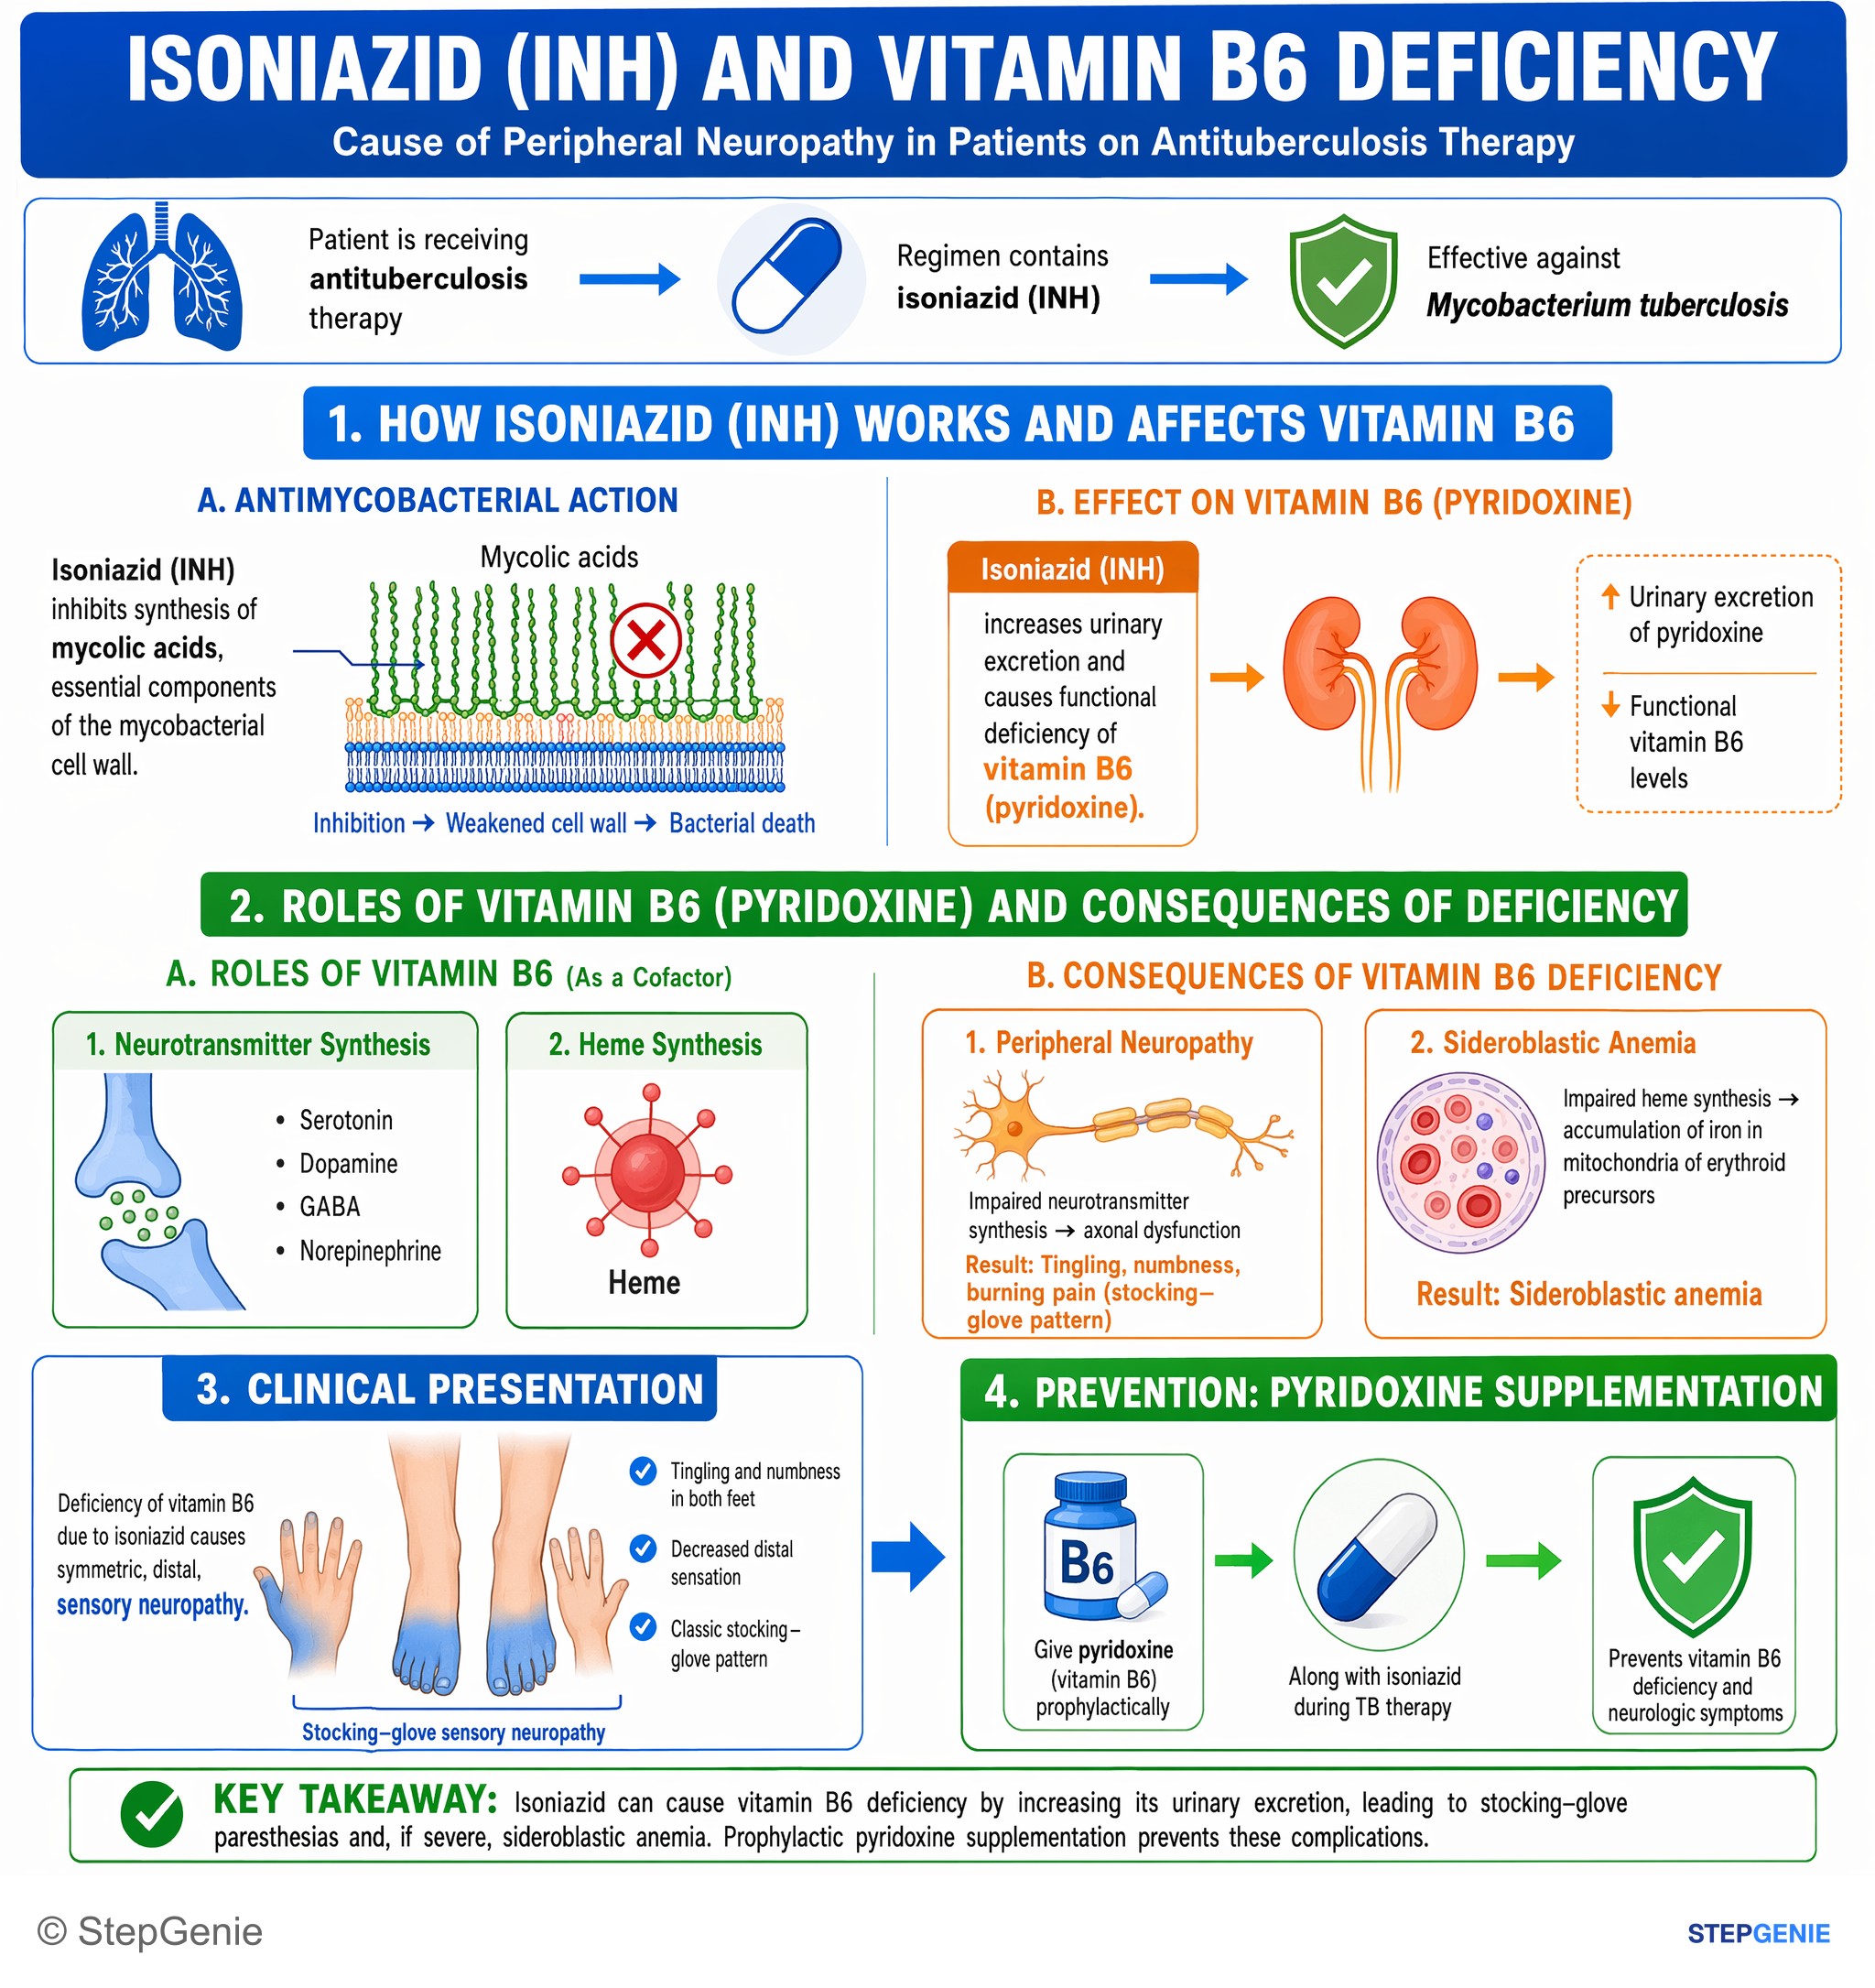
Isoniazid-induced peripheral neuropathy from vitamin B6 (pyridoxine) deficiency causes stocking–glove paresthesias; prevented with…
USMLE Step 1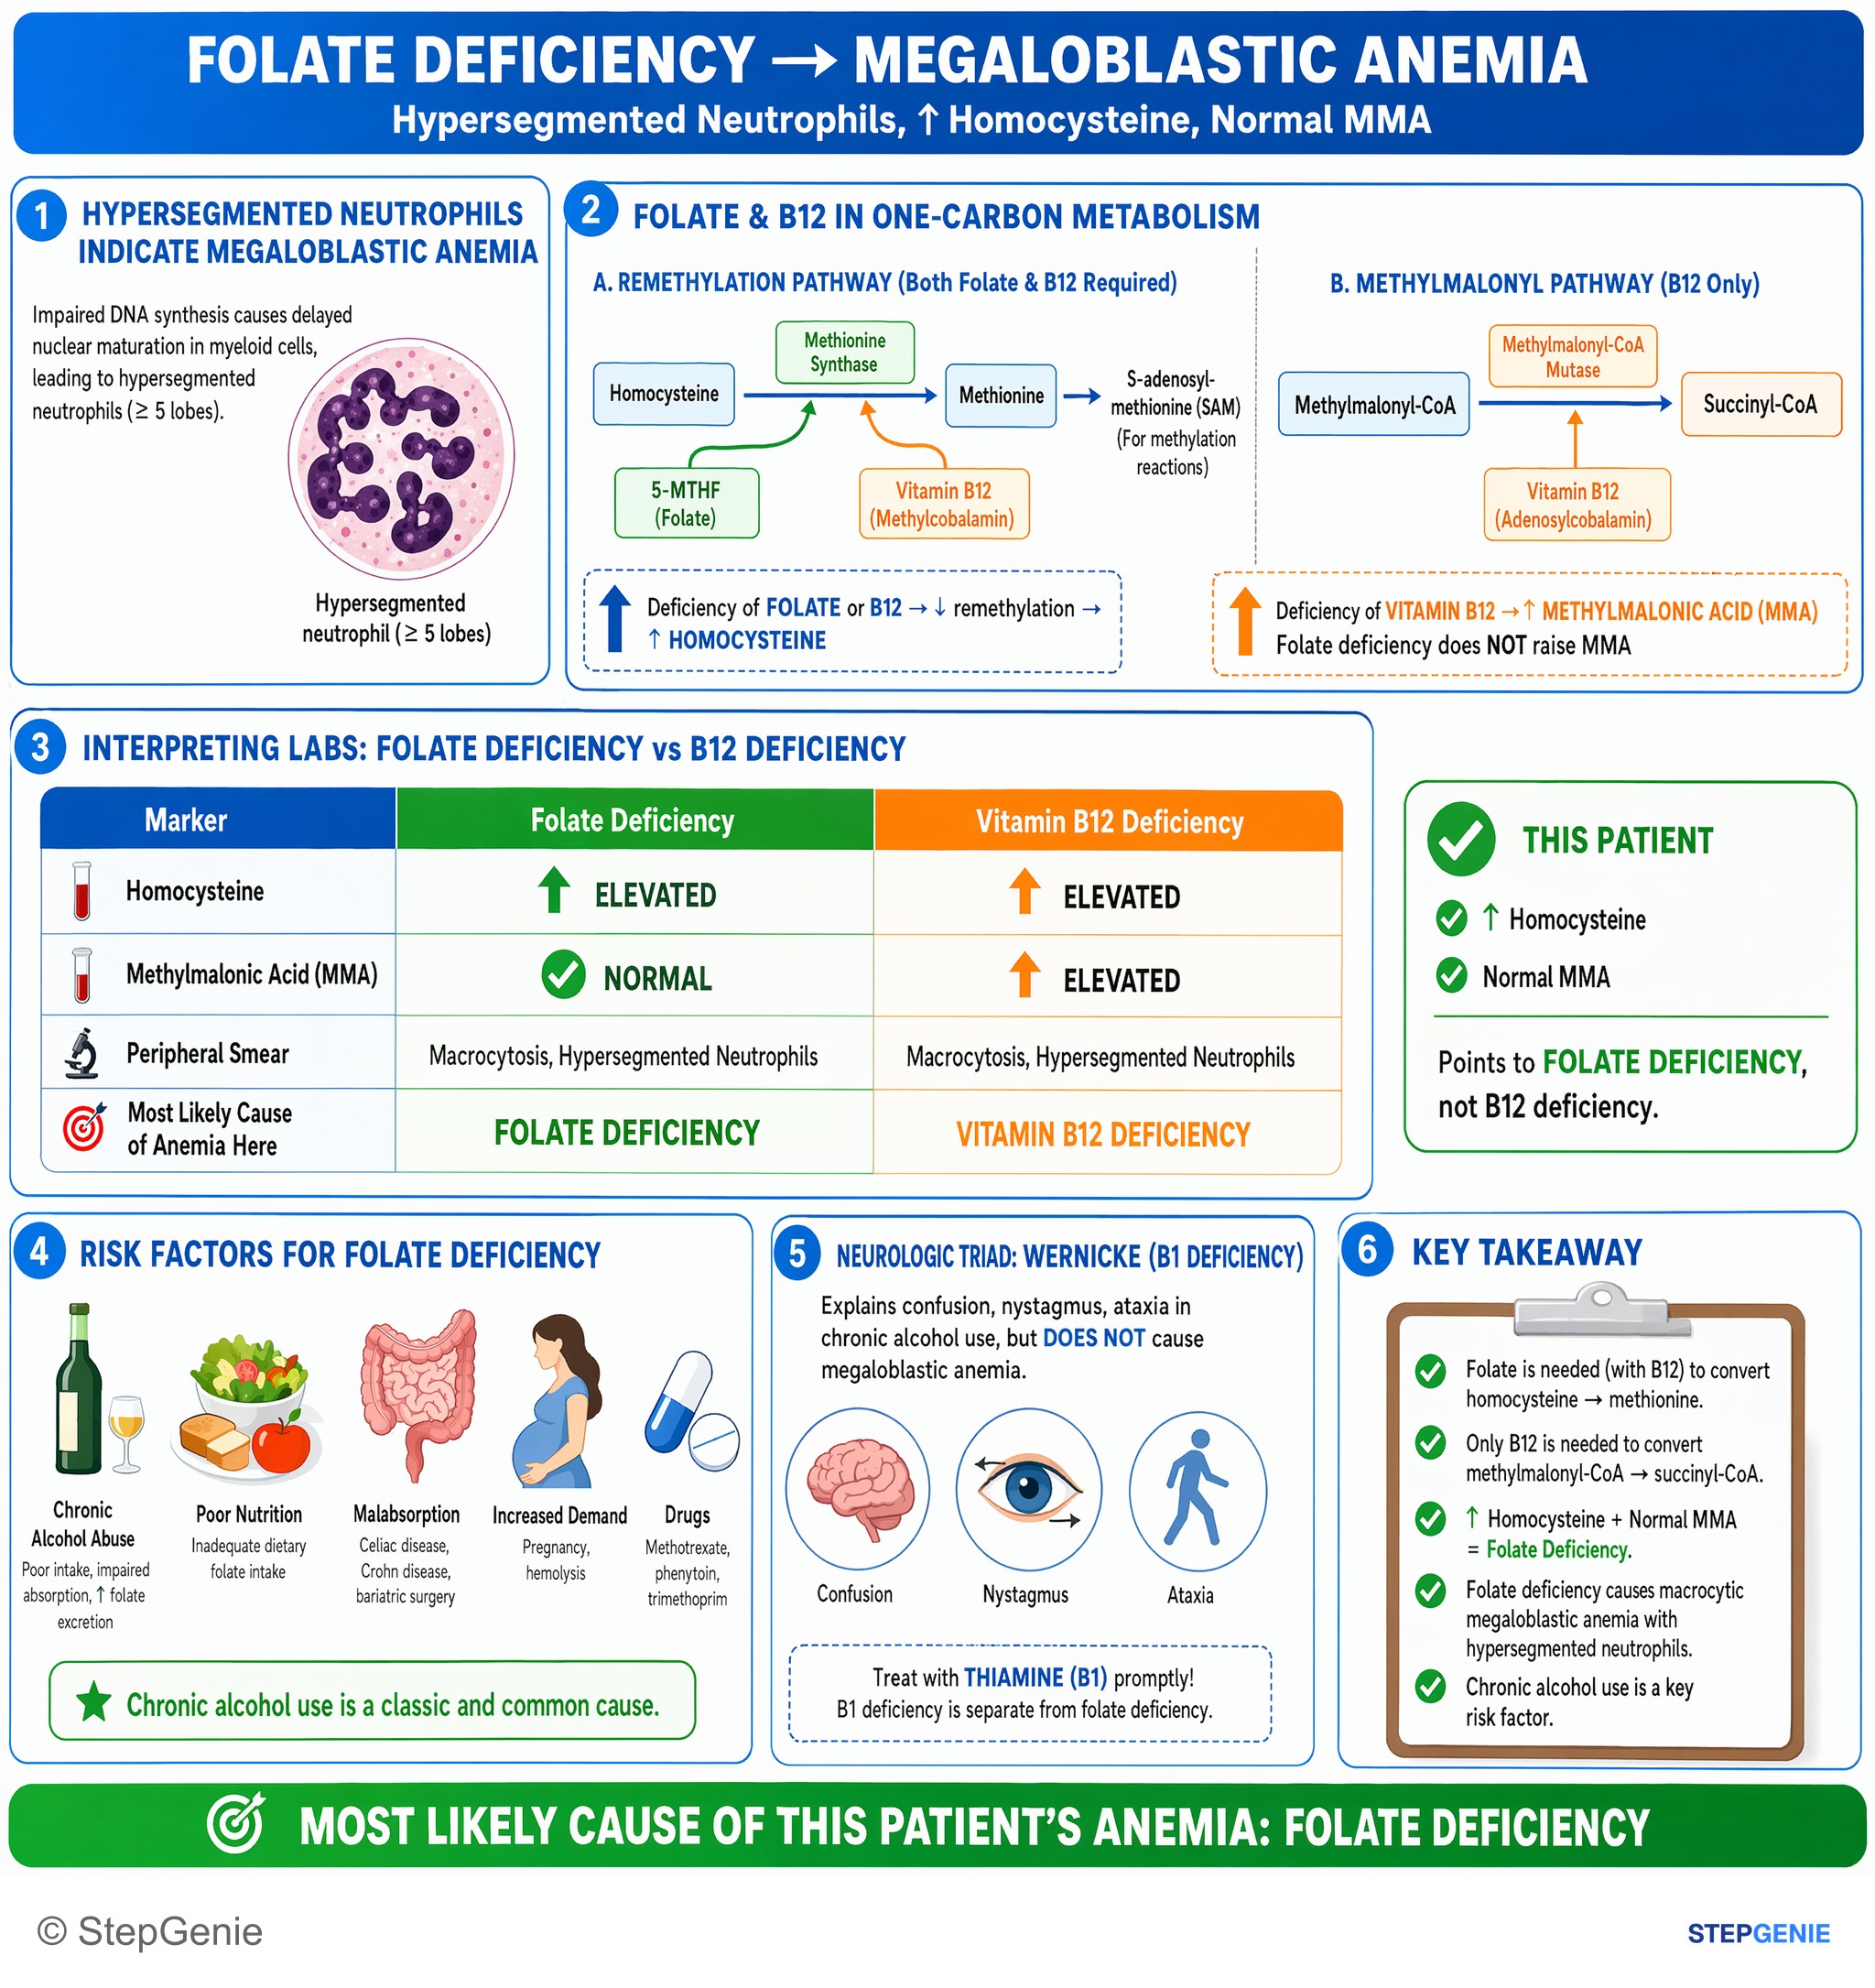
Folate deficiency causes macrocytic megaloblastic anemia with hypersegmented neutrophils, ↑homocysteine, normal methylmalonic acid…
USMLE Step 1Frequently Asked Questions
What is the difference between a cofactor, a coenzyme and a prosthetic group?
A cofactor is any non-protein helper an enzyme needs, either a metal ion such as zinc or magnesium or an organic molecule. Organic cofactors are coenzymes, and many come from B vitamins, such as TPP from thiamine or PLP from pyridoxine. A prosthetic group is a cofactor held tightly, sometimes covalently, such as heme in cytochromes or biotin bound to a lysine of pyruvate carboxylase. The protein alone is an inactive apoenzyme; with its cofactor it becomes the active holoenzyme.
What are the five cofactors of pyruvate dehydrogenase?
Pyruvate dehydrogenase needs thiamine pyrophosphate (B1), lipoic acid, coenzyme A (B5), FAD (B2) and NAD+ (B3), remembered as 'Tender Loving Care For Nancy.' TPP works on E1, lipoic acid and CoA on E2, and FAD and NAD+ on E3. Alpha-ketoglutarate dehydrogenase and branched-chain alpha-keto acid dehydrogenase use the same five and share the same E3. Lipoic acid is made in the body, and arsenite, which binds sulfhydryl groups, particularly affects pyruvate dehydrogenase.
Which enzymes require thiamine (vitamin B1)?
Thiamine pyrophosphate is the cofactor for pyruvate dehydrogenase, alpha-ketoglutarate dehydrogenase, branched-chain alpha-keto acid dehydrogenase and transketolase, remembered as 'Be APT.' The three dehydrogenases decarboxylate alpha-keto acids, and transketolase works in the nonoxidative pentose phosphate pathway. Deficiency causes lactic acidosis and injures energy-hungry brain regions, as in Wernicke encephalopathy. Red-cell transketolase activity, measured before and after adding TPP, is a functional test of thiamine status.
Which enzymes use biotin?
Humans have five biotin-dependent carboxylases: pyruvate carboxylase (gluconeogenesis), acetyl-CoA carboxylases 1 and 2 (malonyl-CoA for fatty acid synthesis and control of fat oxidation), propionyl-CoA carboxylase (odd-chain fatty acids and some amino acids) and 3-methylcrotonyl-CoA carboxylase (leucine breakdown). Deficiency is rare but can follow heavy intake of raw egg whites, whose avidin binds biotin, long-term anticonvulsants or antibiotics, parenteral nutrition without biotin, or inherited biotinidase deficiency.
Which vitamin is required for transamination reactions?
Vitamin B6, as pyridoxal 5'-phosphate (PLP), is the coenzyme for the aminotransferases ALT and AST, where it is bound as a true prosthetic group. PLP also drives amino-acid decarboxylation (glutamate to GABA, histidine to histamine), ALA synthase in heme synthesis, cystathionine beta-synthase, glycogen phosphorylase and the tryptophan-to-niacin pathway. That range explains why B6 deficiency, for example from isoniazid, can cause neuropathy, seizures, microcytic anemia and even pellagra.
How do you tell vitamin B12 deficiency from folate deficiency?
Measure methylmalonic acid (MMA) and homocysteine. B12 is the cofactor for methionine synthase (as methylcobalamin) and methylmalonyl-CoA mutase (as adenosylcobalamin), so B12 deficiency raises both homocysteine and MMA, while folate deficiency raises homocysteine but leaves MMA normal. B12 deficiency also tends to cause neurologic signs such as loss of vibration and position sense, which isolated folate deficiency generally lacks. Exclude B12 deficiency before treating a megaloblastic anemia with folate alone.