The basal ganglia control movement through two opposing pathways that both start in the striatum and end on the GPi/SNr, the inhibitory (GABA) "brake" on the VA/VL thalamus. The direct pathway (striatum → GPi/SNr) releases that brake and promotes movement; the indirect pathway (striatum → GPe → subthalamic nucleus → GPi/SNr) tightens it and suppresses movement. Dopamine from the substantia nigra pars compacta (SNc) excites direct-pathway neurons through D1 receptors and inhibits indirect-pathway neurons through D2 receptors, so both actions favor movement. Lose that dopamine (Parkinson disease) and GPi/SNr output is too high, giving bradykinesia; lose indirect-pathway striatal neurons (Huntington disease) or the subthalamic nucleus (hemiballismus) and output is too low, giving chorea or flinging.
The question
A 66-year-old man has had 18 months of slowness and stiffness, and he now struggles to get up from a chair. His wife says his voice has become soft and his handwriting has shrunk. He takes no medications. He has a slow, pill-rolling tremor of the right hand at rest that lessens when he reaches for a cup, cogwheel rigidity worse on the right, finger tapping that becomes slower and smaller with repetition, reduced facial expression, and a shuffling gait with less arm swing on the right. Which change in basal ganglia circuitry best explains his bradykinesia?
A. Increased activity of D1-receptor striatal neurons that project to the GPi B. Loss of GABAergic striatal neurons that project to the GPe C. Increased GABAergic output from the GPi/SNr to the VA/VL thalamus after loss of nigrostriatal dopamine D. Infarction of the contralateral subthalamic nucleus E. Blockade of striatal D2 receptors by a dopamine antagonist
Answer: C. This is Parkinson disease: asymmetric resting tremor, rigidity, bradykinesia, a soft voice (hypophonia), small handwriting (micrographia) and a shuffling gait in a man in his 60s (mean age at onset is about 60). Degeneration of pigmented dopaminergic neurons in the SNc depletes dopamine in the dorsal putamen. With less dopamine, D1 direct-pathway neurons lose their excitation (less "go") and D2 indirect-pathway neurons lose their inhibition (more "stop"). The GPe is suppressed, the subthalamic nucleus is released, and the GPi/SNr fires harder onto the VA/VL thalamus, so the thalamus drives the motor cortex less. In the classic textbook phrasing, the inhibitory outflow of the basal ganglia becomes abnormally high.
Why every other answer choice is wrong
- A (more D1 direct-pathway activity): wrong direction. The direct pathway is underactive in Parkinson disease. More D1 drive would release the thalamus and increase movement, which is what dopamine replacement tries to restore.
- B (loss of striatal neurons that project to the GPe): this is Huntington disease. Losing these indirect-pathway medium spiny neurons disinhibits the GPe, which then suppresses the subthalamic nucleus; GPi/SNr output falls and the result is chorea, not bradykinesia.
- D (contralateral subthalamic nucleus infarct): this causes hemiballismus, sudden wild flinging of the proximal arm or leg on the opposite side. Without the subthalamic nucleus's excitatory drive, GPi/SNr output drops and the thalamus is released: too little brake, not too much.
- E (D2 blockade): this produces a similar circuit change (an overactive indirect pathway and high GPi/SNr output) and is the mechanism of drug-induced parkinsonism from antipsychotics or metoclopramide. It is wrong here because he takes no dopamine-blocking drug, and his slowly progressive, asymmetric course fits Parkinson disease.
The circuit in one table
| Projection | Transmitter | Effect | Pathway |
|---|---|---|---|
| Cortex → striatum | Glutamate | Excites | Input to both |
| Striatum (D1 neurons) → GPi/SNr | GABA | Inhibits | Direct |
| Striatum (D2 neurons) → GPe | GABA | Inhibits | Indirect |
| GPe → subthalamic nucleus | GABA | Inhibits | Indirect |
| Subthalamic nucleus → GPi/SNr | Glutamate | Excites | Indirect |
| GPi/SNr → VA/VL thalamus | GABA | Inhibits | Final output (the brake) |
| Thalamus → motor cortex | Glutamate | Excites | Output of both |
| SNc → striatum | Dopamine | D1 excites direct neurons; D2 inhibits indirect neurons | Modulates both |
Count the inhibitory steps. From striatum to thalamus, the direct pathway has two inhibitory synapses (striatum inhibits GPi/SNr, GPi/SNr inhibits thalamus). Two negatives make a positive, so the thalamus is released and movement increases. The indirect pathway has three (striatum inhibits GPe, GPe inhibits the subthalamic nucleus, and GPi/SNr inhibits the thalamus, with the excitatory subthalamic step in between). An odd number nets out as inhibition, so movement decreases. Even = go, odd = stop.
Disorders sorted by GPi/SNr output
| Disorder | Lesion | Circuit change | GPi/SNr output | Movements | Classic stem |
|---|---|---|---|---|---|
| Parkinson disease | SNc dopaminergic neurons; synuclein-filled Lewy bodies | Direct ↓, indirect ↑ | ↑ | Hypokinetic: bradykinesia, rigidity, rest tremor | Asymmetric pill-rolling tremor, micrographia, shuffling gait |
| Drug-induced parkinsonism | Striatal D2 receptors blocked (antipsychotics, metoclopramide) | Indirect ↑ | ↑ | Hypokinetic | Parkinsonism after starting a dopamine antagonist |
| Huntington disease | Striatal medium spiny neurons; caudate atrophy | Indirect ↓ | ↓ | Hyperkinetic: chorea | Chorea, psychiatric change and dementia, usually starting in the 30s or 40s; autosomal dominant |
| Hemiballismus | Contralateral subthalamic nucleus, usually an infarct | Subthalamic drive lost | ↓ | Hyperkinetic: proximal limb flinging | Sudden violent flinging of one arm or leg |
Parkinson disease: the tested facts
- Pathology: loss of pigmented SNc neurons with synuclein-filled Lewy bodies in the nigrostriatal system; dopamine loss is greatest in the dorsal putamen.
- Signs: a 3-6 Hz "pill-rolling" resting tremor that fades with movement, cogwheel rigidity, bradykinesia with shrinking amplitude, hypomimia, hypophonia, micrographia and a shuffling gait; postural instability comes later. Onset is usually asymmetric, and tremor can be subtle or absent in rigid-akinetic forms.
- Diagnosis is clinical. A large, sustained response to levodopa strongly supports it.
- Treatment logic: carbidopa-levodopa is the most effective drug (carbidopa blocks peripheral decarboxylation of levodopa). MAO-B inhibitors, dopamine agonists and amantadine can be used alone in early, mild disease or added later; COMT inhibitors are add-ons when levodopa starts wearing off, and amantadine also eases levodopa-induced dyskinesias. Anticholinergics help tremor most but cause confusion and delirium in older adults.
- Deep brain stimulation targets the subthalamic nucleus or GPi, the nodes the circuit model says are overactive.
- Workup and drug choices step by step: Parkinson disease flowchart.
Huntington disease and hemiballismus
- Huntington genetics: autosomal dominant CAG repeat expansion in HTT on chromosome 4. 40 or more repeats almost always cause disease; 36-39 may or may not. Large expansions occur almost exclusively through paternal transmission, so anticipation is seen mainly when the father passes it on.
- Huntington pathology and signs: caudate atrophy and degeneration of inhibitory medium spiny neurons (less GABA and substance P); onset usually in the 30s or 40s, with chorea plus depression, apathy, irritability and dementia. Chorea is later replaced by akinetic-rigid features.
- Huntington treatment: VMAT2 inhibitors deplete dopamine and suppress chorea: tetrabenazine and deutetrabenazine, and valbenazine is also FDA-labeled for Huntington chorea. VMAT2 inhibitors can increase depression and suicidality in Huntington disease; antipsychotics are the alternative. More in the Huntington disease cheat sheet.
- Hemiballismus: a lesion, usually an infarct, in or around the contralateral subthalamic nucleus. It is usually self-limited over 6-8 weeks; severe cases get an antipsychotic for 1-2 months, and deep brain stimulation if that fails. Most of the basal ganglia are supplied by the lenticulostriate branches of the middle cerebral artery, but most of the subthalamic nucleus is fed by posteromedial branches of the posterior cerebral artery (P1 segment); map other deep infarcts with stroke localization by artery.
- Other causes of chorea: Sydenham chorea (it can be the first sign of rheumatic fever), hyperthyroidism, hyperglycemia, drugs such as levodopa and phenytoin, tardive dyskinesia, and pregnancy.
How USMLE tests it
- Hypokinetic = too much brake; hyperkinetic = too little. Bradykinesia and rigidity mean high GPi/SNr output; chorea and ballismus mean low output.
- Dopamine is not simply excitatory. It excites D1 (direct) neurons and inhibits D2 (indirect) neurons, and both effects increase movement.
- The subthalamic nucleus is the excitatory node. Its glutamate projection to the GPi/SNr is the only glutamatergic output among the basal ganglia nuclei; striatal, GPe and GPi/SNr outputs are all GABA, and nigral dopamine is modulatory.
- Signs are contralateral to the lesion, as in hemiballismus from a contralateral subthalamic infarct.
- Tell the tremors apart: parkinsonian rest tremor fades with action; an intention tremor builds as the hand nears its target and points to the cerebellum (see cerebellum lesions); essential tremor (4-12 Hz) is usually symmetric in both arms, sometimes with head and voice tremor, can be suppressed by low-dose alcohol, and is treated with propranolol or primidone.
- The output target is the VA/VL thalamus, a favorite of thalamic nuclei questions.
- New parkinsonism on an antipsychotic or metoclopramide means blocked D2 receptors, not a degenerating nigra; review extrapyramidal effects by drug in typical vs atypical antipsychotics.
Key takeaways
- Direct pathway = go: striatal D1 neurons inhibit the GPi/SNr, releasing the VA/VL thalamus.
- Indirect pathway = stop: striatal D2 neurons inhibit the GPe, freeing the subthalamic nucleus to excite the GPi/SNr, which inhibits the thalamus.
- Dopamine from the SNc excites D1 and inhibits D2 neurons; both favor movement.
- Parkinson disease: SNc loss → GPi/SNr output ↑ → bradykinesia, rigidity, 3-6 Hz rest tremor; deep brain stimulation targets the subthalamic nucleus or GPi.
- Huntington disease: CAG repeats in HTT, caudate atrophy, loss of indirect-pathway striatal neurons → GPi/SNr output ↓ → chorea.
- Hemiballismus: contralateral subthalamic infarct → GPi/SNr output ↓ → flinging that usually settles in 6-8 weeks.
- D2 blockers (antipsychotics, metoclopramide) reproduce the Parkinson circuit.
Sources
- Neuroanatomy, Basal Ganglia — StatPearls, NCBI Bookshelf (2023)
- Circuits within the Basal Ganglia System — Neuroscience, 2nd ed., NCBI Bookshelf (2001)
- Neuroanatomy, Subthalamic Nucleus — StatPearls, NCBI Bookshelf (2022)
- Parkinson Disease — Merck Manual Professional Edition (2026)
- Huntington Disease — Merck Manual Professional Edition (2026)
- Chorea, Athetosis, and Hemiballismus — Merck Manual Professional Edition (2026)
- Tremor — Merck Manual Professional Edition (2026)
- Huntington Disease — GeneReviews, NCBI Bookshelf (2026)
- Huntington's disease — MedlinePlus Genetics (2020)
- INGREZZA (valbenazine) prescribing information — DailyMed (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
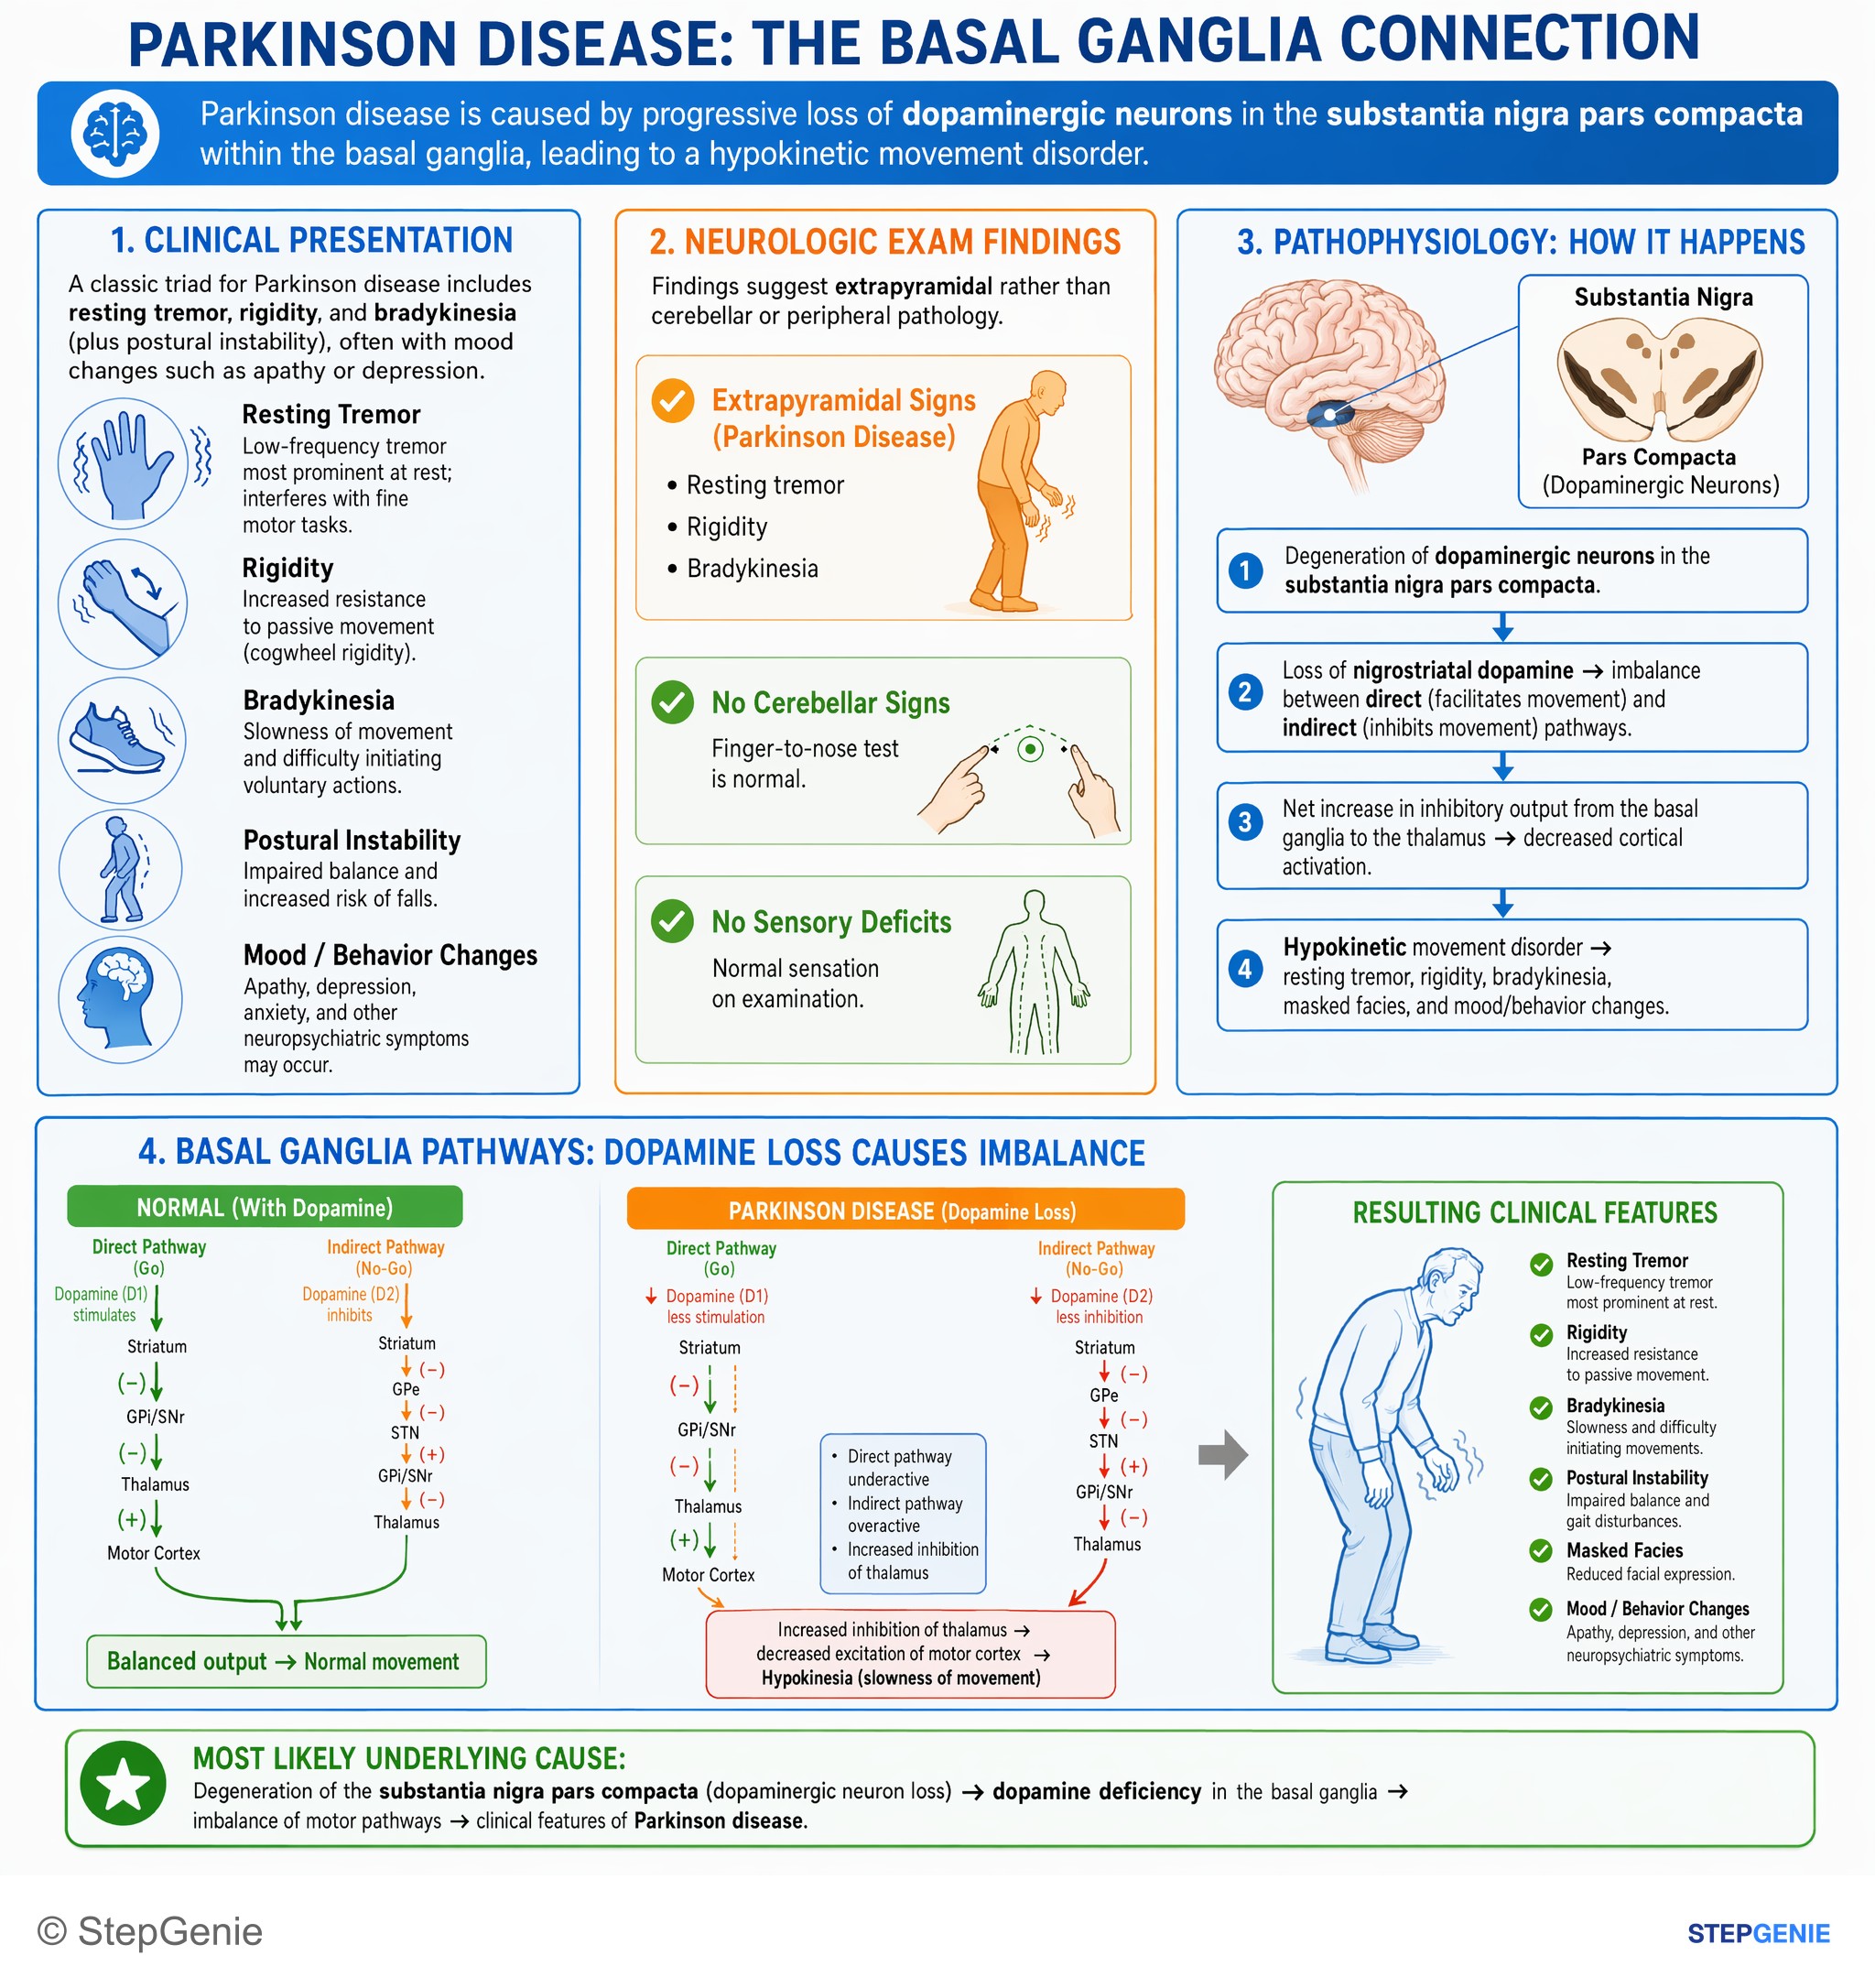
Parkinson disease from dopaminergic neuron loss in substantia nigra pars compacta → resting tremor, rigidity, bradykinesia, masked facies…
USMLE Step 1Frequently Asked Questions
What is the difference between the direct and indirect basal ganglia pathways?
Both start with GABAergic neurons in the striatum and end at the GPi/SNr, which inhibits the VA/VL thalamus. The direct pathway inhibits the GPi/SNr itself, releasing the thalamus so movement increases. The indirect pathway inhibits the GPe instead, which frees the subthalamic nucleus to excite the GPi/SNr, so thalamic inhibition rises and movement decreases. A quick check: two inhibitory steps (direct) net out as go, three (indirect) as stop.
How does dopamine affect the direct and indirect pathways?
Dopamine from the substantia nigra pars compacta acts on two kinds of striatal neurons. It excites direct-pathway neurons through D1 receptors and inhibits indirect-pathway neurons through D2 receptors. Both actions lower GPi/SNr output to the thalamus, so the net effect of dopamine is more movement. That is why losing dopamine in Parkinson disease, or blocking D2 receptors with antipsychotics or metoclopramide, causes slow, stiff, reduced movement.
Why does Parkinson disease cause bradykinesia?
Parkinson disease destroys dopaminergic neurons in the substantia nigra pars compacta, depleting dopamine in the striatum, especially the dorsal putamen. The direct pathway loses its D1 excitation and the indirect pathway loses its D2 inhibition. Both changes raise GABAergic output from the GPi/SNr onto the VA/VL thalamus, which then drives the motor cortex less. The result is bradykinesia, rigidity and difficulty initiating movement, usually with a 3 to 6 Hz resting tremor.
Why does a subthalamic nucleus lesion cause hemiballismus?
The subthalamic nucleus is the excitatory, glutamate-releasing node of the indirect pathway; it drives the GPi/SNr to inhibit the thalamus. When a lesion, usually an infarct, destroys it, GPi/SNr output falls and the thalamus is released. The result is hemiballismus: sudden, wild flinging movements of the proximal arm or leg on the side opposite the lesion. It usually settles within 6 to 8 weeks, and severe cases are treated with an antipsychotic.
Which basal ganglia pathway is affected in Huntington disease?
Huntington disease mainly disrupts the indirect pathway. Inhibitory medium spiny neurons in the striatum degenerate, including those that project to the GPe, and the caudate atrophies. The GPe is then disinhibited and suppresses the subthalamic nucleus, so GPi/SNr output falls and the thalamus is released, producing chorea. The disease is autosomal dominant, caused by a CAG repeat expansion in HTT on chromosome 4, with onset usually in a person's 30s or 40s.
Which neurotransmitters does the basal ganglia circuit use?
The cortex-to-striatum and thalamus-to-cortex projections use glutamate. Striatal outputs to the GPi/SNr and GPe, the GPe output to the subthalamic nucleus, and the GPi/SNr output to the thalamus all use GABA. The subthalamic nucleus is the excitatory exception among the basal ganglia nuclei, sending glutamate to the GPi/SNr. Dopamine from the substantia nigra pars compacta modulates the striatum, exciting D1 neurons and inhibiting D2 neurons.