The highest-yield brainstem mnemonic is the Rule of 4. Four structures near the midline start with M (Motor pathway, Medial lemniscus, MLF, Motor nucleus of CN III, IV, VI or XII), four lateral structures start with S (Spinocerebellar, Spinothalamic, Sensory nucleus of V, Sympathetic), and the cranial nerves stack four per level: I–IV above the pons (only III and IV in the midbrain), V–VIII in the pons, IX–XII in the medulla. Use the cranial nerve to find the level and the M's or S's to decide medial versus lateral; an ipsilateral cranial nerve deficit with contralateral body signs points to the brainstem.
Brainstem stroke syndromes at a glance
Most named brainstem syndromes pair a cranial nerve sign (which sets the level) with one or more long-tract signs (which set medial versus lateral); Parinaud, a supranuclear vertical gaze palsy without long-tract signs, is the exception.
| Syndrome | Level and territory | Usual artery | Same side as lesion | Opposite side | Hook |
|---|---|---|---|---|---|
| Weber | Ventral (medial) midbrain | Paramedian branches of the PCA | CN III palsy: ptosis, eye down and out, dilated pupil | Hemiparesis including the lower face | Weber = Weak |
| Claude | Midbrain tegmentum (dentatorubrothalamic fibers) | PCA branches | CN III palsy | Ataxia | Claude = Clumsy |
| Benedikt | Tegmentum plus peduncle (red nucleus, substantia nigra) | Peduncular branches of the proximal PCA | CN III palsy | Hemiparesis plus ataxia, tremor or choreoathetosis | Benedikt = Both |
| Parinaud | Dorsal midbrain (tectum) | Classically compression by a pineal tumor (young patients); infarct or hemorrhage in older adults | Bilateral: upgaze palsy, light-near dissociation, convergence-retraction nystagmus, lid retraction | — | Can't look uP |
| Raymond | Ventral caudal pons | Paramedian basilar perforators | CN VI palsy (eye can't abduct) | Hemiparesis | VI + motor |
| Millard-Gubler | Ventral caudal pons | Paramedian basilar perforators | CN VI palsy and whole-face CN VII palsy | Hemiparesis | VI + VII + motor |
| Foville | Inferior medial pons | Basilar branches | Horizontal gaze palsy toward the lesion, facial palsy | Hemiparesis | Millard-Gubler + gaze palsy |
| Lateral pontine (AICA) | Lateral caudal pons | AICA or long circumferential basilar branches | Facial palsy, hearing loss, Horner, facial pain/temperature loss, limb ataxia | Body pain/temperature loss | AICA = Audition |
| Locked-in | Ventral pons, both sides | Basilar artery | — | Quadriplegia, bilateral facial and horizontal gaze palsy; awake, vertical gaze and blinking spared | Only the eyes move |
| Medial medullary (Dejerine) | Medial medulla | Anterior spinal artery / vertebral paramedian branches | CN XII: tongue deviates toward the lesion | Hemiparesis sparing the face; vibration and proprioception loss | Tongue points to the lesion |
| Lateral medullary (Wallenberg) | Lateral medulla | Vertebral artery (most cases) or PICA | Dysphagia, hoarseness, facial pain/temperature loss, Horner, ataxia, vertigo | Body pain/temperature loss | Can't swallow, can't feel pain |
| Babinski-Nageotte | Lateral plus medial medulla | Vertebral artery and PICA branches | Wallenberg findings | Body pain/temperature loss plus hemiparesis | Wallenberg + weakness |
The Rule of 4 of the brainstem
Neurologist Peter Gates published this shortcut in 2005 as four rules:
- Four M's run down the midline (medial brainstem).
- Four S's sit to the side (lateral brainstem).
- Four cranial nerves per level: medulla IX–XII, pons V–VIII, above the pons I–IV (only III and IV are in the midbrain).
- The midline motor nuclei are the numbers that divide evenly into 12, excluding 1 and 2: III, IV, VI, XII. The other brainstem nerves (V, VII, VIII, IX, X, XI) are lateral.
| Structure | Location | Deficit when damaged | Side |
|---|---|---|---|
| Motor pathway (corticospinal) | Medial | Arm and leg weakness (UMN) | Contralateral |
| Medial lemniscus | Medial | Loss of vibration and proprioception | Contralateral |
| Medial longitudinal fasciculus | Medial | Internuclear ophthalmoplegia (INO) | Ipsilateral |
| Motor nucleus of III, IV, VI or XII | Medial | That cranial nerve's palsy | Ipsilateral |
| Spinocerebellar tracts | Lateral | Limb ataxia | Ipsilateral |
| Spinothalamic tract | Lateral | Pain and temperature loss in arm and leg | Contralateral |
| Sensory nucleus of V (spinal trigeminal) | Lateral | Pain and temperature loss on the face | Ipsilateral |
| Sympathetic pathway | Lateral | Horner syndrome (ptosis, miosis, anhidrosis) | Ipsilateral |
Why the sides split: in the brainstem, the long tracts serving the body all represent the opposite side (the corticospinal tract crosses below, in the lower medulla; the medial lemniscus and spinothalamic tract have already crossed), while cranial nerve nuclei, the MLF, spinocerebellar fibers and sympathetics serve the same side. Hence crossed findings. One exception: trochlear fibers cross before they exit, so a CN IV nucleus lesion weakens the opposite superior oblique.
Brainstem nuclei mnemonic: cranial nerves by level
| Level | Nuclei | Where the nerve exits | Localizing sign |
|---|---|---|---|
| Midbrain | III (oculomotor + Edinger–Westphal), IV | III: interpeduncular fossa; IV: dorsal surface (the only one) | Eye "down and out," ptosis, dilated pupil; vertical diplopia |
| Pons | V (motor, main sensory), VI, VII, VIII | V: lateral pons; VI–VIII: pontomedullary junction | Jaw deviation, failed abduction, whole-face facial palsy, hearing loss or vertigo |
| Medulla | IX, X, XII; XI's spinal accessory nucleus (SCM, trapezius) is in the upper cervical cord (C1–C5) | XII: between pyramid and olive; IX–XI: behind the olive | Dysphagia, hoarseness, uvula deviation, tongue deviation |
Two caveats explain classic stroke findings: the trigeminal nuclei span the whole brainstem (down to the upper cervical cord), so a lateral medullary stroke still numbs the ipsilateral face, and the vestibular nuclei extend into the medulla, so it also causes vertigo. CN I and II are forebrain structures, not brainstem nuclei.
Cranial nerve nuclei and columns mnemonic: motor medial, sensory lateral
In the embryo the sulcus limitans separates the basal plate (motor) from the alar plate (sensory). In the brainstem the motor nuclei end up nearer the midline and the sensory nuclei more lateral and posterior, so cranial nerve nuclei line up in functional columns.
| Column (motor first, then sensory) | Job | Nuclei |
|---|---|---|
| GSE, somatic motor | Eye and tongue muscles | III, IV, VI, XII |
| SVE, branchial motor | Pharyngeal arch muscles | Motor V, facial nucleus (VII), nucleus ambiguus (IX, X) |
| GVE, parasympathetic | Glands and smooth muscle | Edinger–Westphal (III), superior salivatory (VII), inferior salivatory (IX), dorsal motor nucleus of X |
| GVA and SVA, visceral sensory | Gut, baroreceptors, taste | Nucleus solitarius (VII, IX, X) |
| GSA, somatic sensory | Face touch, pain, temperature | Trigeminal nuclei (V) |
| SSA, special sensory | Hearing and balance | Cochlear and vestibular nuclei (VIII) |
The sulcus limitans divides the three motor (efferent) columns from the three sensory (afferent) columns. Hook: eye and tongue muscles, arch muscles, glands, then guts and taste, face, ears. The nucleus ambiguus sits in the lateral part of the rostral medulla, which is why it is hit in lateral (PICA or vertebral) strokes while XII stays medial.
Midbrain syndromes mnemonic: Weber, Claude, Benedikt, Parinaud
The ventral and tegmental midbrain syndromes all start with an ipsilateral CN III palsy; the second finding names the syndrome.
- Weber = Weakness: CN III fascicles plus the cerebral peduncle, giving contralateral hemiparesis that includes the lower face and tongue.
- Claude = Clumsy: CN III fascicles plus dentatorubrothalamic fibers near the red nucleus, giving contralateral ataxia.
- Benedikt = Both: CN III plus red nucleus, substantia nigra and peduncle, giving contralateral hemiparesis together with ataxia, tremor (Holmes tremor) or choreoathetosis.
- Parinaud = can't look uP: a dorsal midbrain (pretectal) lesion, classically compression by a pineal tumor in a young patient, while vascular causes dominate in middle and older age. Upgaze palsy, convergence–retraction nystagmus, pupils that react to near but not light, and eyelid retraction (Collier sign). This one is a vertical gaze palsy, not a CN III palsy.
Pontine syndromes: abduction, the face and gaze
The pons holds CN VI, the facial nucleus, the horizontal gaze machinery (abducens nucleus, paramedian pontine reticular formation, MLF) and corticospinal fibers in its base.
- Raymond: ipsilateral CN VI palsy with contralateral hemiparesis, and no ipsilateral (LMN) facial palsy; a contralateral central facial paresis may accompany the hemiparesis.
- Millard-Gubler: Raymond's findings plus an ipsilateral facial (CN VII) palsy that involves the forehead, because the facial fascicle is hit within the pons.
- Foville: Millard-Gubler plus a conjugate horizontal gaze palsy toward the side of the lesion, because the abducens nucleus also drives the opposite medial rectus through the MLF.
- Lateral pontine (AICA): ipsilateral facial paralysis and hearing loss (the AICA gives off the labyrinthine artery), ipsilateral Horner syndrome, facial pain and temperature loss, and limb ataxia, with contralateral body pain and temperature loss. When the infarct also reaches the corticospinal fibers (described as Marie-Foix syndrome), contralateral hemiparesis is added.
- Locked-in syndrome: a ventral pontine infarct, usually from basilar artery occlusion, destroys both corticospinal and corticobulbar tracts. Expect quadriplegia, bilateral facial paralysis and horizontal gaze palsy with preserved consciousness, vertical eye movements and blinking.
INO and the one-and-a-half syndrome
An MLF lesion causes internuclear ophthalmoplegia: on looking away from the lesion, the eye on the side of the lesion fails to adduct and the abducting eye shows nystagmus, while convergence can be preserved. Stroke (usually unilateral, older patient) and multiple sclerosis (often bilateral, young adult) each account for about a third of cases. Add the PPRF on the same side and you get the one-and-a-half syndrome: no horizontal movement remains except abduction of the opposite eye.
Medullary syndrome mnemonic: Wallenberg vs Dejerine
Wallenberg (lateral medullary) is the most tested brainstem stroke. About 80% of cases come from vertebral artery occlusion, and vertebral artery dissection is the commonest cause in younger patients (neck trauma or manipulation, connective tissue disease). PICA remains the classic exam answer; a young patient with neck pain after manipulation points to dissection.
| Wallenberg finding | Structure hit | Side |
|---|---|---|
| Dysphagia, hoarseness, reduced gag | Nucleus ambiguus (IX, X) | Ipsilateral |
| Hiccups (can be intractable) | Lateral medulla | — |
| Vertigo, nausea, nystagmus | Vestibular nuclei | — |
| Facial pain and temperature loss | Spinal trigeminal nucleus and tract | Ipsilateral |
| Body pain and temperature loss | Spinothalamic tract | Contralateral |
| Ptosis, miosis, anhidrosis | Descending sympathetic fibers | Ipsilateral |
| Limb ataxia, falling toward the lesion | Inferior cerebellar peduncle | Ipsilateral |
| Little or no weakness | Pyramids are ventromedial and spared | — |
Mnemonic: "Don't pick a horse that can't eat": PICA, hoarse, can't eat (dysphagia). Prognosis is generally better than for most stroke syndromes; gait instability is the commonest residual problem.
Dejerine (medial medullary) accounts for only about 1% of cerebral infarctions: paramedian branches of the anterior spinal artery or vertebral artery, usually atherothrombotic. The triad is the tongue deviating toward the lesion (CN XII), contralateral hemiparesis that spares the face (pyramid) and contralateral loss of vibration and proprioception (medial lemniscus), although only a minority show all three. Babinski-Nageotte combines Wallenberg features with contralateral hemiparesis.
Localize any brainstem lesion in four steps
- Confirm it is the brainstem. Crossed findings (cranial nerve on one side, body on the other) mean brainstem; face and body weak on the same side, with no crossed cranial nerve sign, usually point above the brainstem (cortex or internal capsule), although a ventral pontine lacune can do the same.
- Find the level from the cranial nerve. III or IV = midbrain; V, VI, VII or VIII = pons; IX, X or XII = medulla.
- Decide medial or lateral. Weakness, proprioception loss, INO or a midline motor nerve (III, IV, VI, XII) = medial. Ataxia, crossed pain/temperature loss, Horner or a lateral nerve (V, VII, VIII, IX, X) = lateral. Exception: in the midbrain, contralateral ataxia with a CN III palsy (Claude, Benedikt) comes from the paramedian red nucleus region, so it is a medial (PCA paramedian) syndrome.
- Name the artery. Medial = paramedian branches (PCA, basilar, anterior spinal or vertebral); lateral = circumferential branches (AICA in the pons, PICA or vertebral in the medulla).
For cortical, subcortical and lacunar territories, use stroke localization by artery; for the posterior circulation as a whole, see anterior vs posterior circulation stroke.
Brainstem reflexes mnemonic: which reflex tests which level
| Reflex | Afferent → efferent | Level tested |
|---|---|---|
| Pupillary light | II → III | Midbrain |
| Corneal (blink) | V1 → VII | Pons |
| Jaw jerk | V3 → V3 | Pons (motor V nucleus; afferent cell bodies in the midbrain) |
| Oculocephalic / cold caloric | VIII → III and VI (via MLF) | Pons to midbrain |
| Gag | IX → X | Medulla |
| Cough | X → X | Medulla |
Hook: the nerve pairs climb as you descend (2→3, 5→7, 9→10), so pupil, blink and gag test midbrain, pons and medulla. Loss of all brainstem reflexes, together with apnea, is part of the brain death examination.
Acute brainstem stroke on Step 2 CK
- How it presents: vertebrobasilar ischemia causes roughly 20% of strokes and TIAs, and the pons is the commonest brainstem site. "Top of the basilar" embolism causes vertical gaze palsy, pupillary changes, hypersomnolence and hallucinations with little motor or sensory loss.
- Imaging: noncontrast CT first to exclude hemorrhage, accepting that CT is often normal early; MRI with diffusion-weighted imaging is highly sensitive in the hyperacute phase, although early DWI can miss small brainstem infarcts. CTA or MRA of the head and neck looks for vertebrobasilar occlusion, stenosis or dissection.
- Thrombolysis: IV alteplase or tenecteplase within 4.5 hours of last known well, if eligible; the 2026 AHA/ASA guideline adds that IV thrombolysis may be reasonable at 4.5–9 hours (or within 9 hours of the midpoint of sleep in wake-up stroke) when automated perfusion imaging shows salvageable penumbra.
- Thrombectomy: the 2026 AHA/ASA acute ischemic stroke guideline recommends endovascular thrombectomy within 24 hours for basilar artery occlusion in patients with a prestroke modified Rankin Scale score of 0–1, an NIHSS of 10 or more and a posterior circulation ASPECTS of 6 or more. Untreated basilar occlusion carries a poor outcome in most cohorts.
Exam traps and look-alikes
- Which way does it deviate? Tongue toward a CN XII lesion; uvula away from a CN X lesion; jaw toward a CN V motor lesion.
- UMN vs LMN face. A facial nucleus or nerve lesion in the pons paralyzes the whole ipsilateral face, forehead included. A corticobulbar lesion (cortex, internal capsule, or the peduncle in Weber) weakens only the contralateral lower face.
- Nerve vs nucleus for CN VI. One eye that can't abduct = CN VI nerve or fascicle. Neither eye can look toward the lesion = abducens nucleus or PPRF (horizontal gaze palsy).
- PICA vs AICA. Both give crossed pain/temperature loss, Horner and ataxia; hoarseness and dysphagia mean medulla (PICA or vertebral), facial paralysis and hearing loss mean pons (AICA).
Worked examples
Vignette 1. A 64-year-old man with diabetes wakes with weakness of his left arm and leg. His face is symmetric. On protrusion, his tongue deviates to the right. Vibration and joint-position sense are lost in the left limbs, but pinprick is normal everywhere. Where is the lesion?
Answer: Right medial medullary syndrome, from occlusion of paramedian branches of the right anterior spinal or vertebral artery.
Reasoning: CN XII (a "divides into 12" motor nucleus) puts the lesion in the medulla. Two more M's (pyramid → left weakness, medial lemniscus → left vibration loss) with no S's make it medial, and the tongue points toward the lesion.
Vignette 2. A 41-year-old woman develops neck pain two days after a chiropractic adjustment, then sudden vertigo, hoarseness and hiccups. Her right pupil is small with mild ptosis, pinprick is reduced on the right face and the left arm and leg, and she falls to the right. Strength is normal. What is the most likely cause?
Answer: Right vertebral artery dissection causing a right lateral medullary (Wallenberg) infarct.
Reasoning: Hoarseness (nucleus ambiguus), hiccups, ipsilateral Horner, crossed pain/temperature loss and ipsilateral ataxia without weakness are lateral medullary findings; in a young patient after neck manipulation, dissection is the most likely mechanism.
Key takeaways
- Rule of 4: four M's medial, four S's lateral, four cranial nerves per level; midline motor nuclei are III, IV, VI, XII.
- Level first, then side: the cranial nerve sets the level; M versus S findings decide medial versus lateral; then name the artery.
- Midbrain: Weber weak, Claude clumsy, Benedikt both, Parinaud can't look up.
- Pons: Raymond (VI + motor), Millard-Gubler (VI + VII + motor), Foville (adds a gaze palsy), AICA (face and hearing), locked-in (only the eyes move).
- Medulla: Wallenberg = hoarseness, dysphagia, crossed pain/temperature loss and Horner without weakness; Dejerine = tongue toward the lesion plus contralateral weakness.
- Reflex levels: pupil = midbrain, corneal = pons, gag = medulla.
Browse the rest of the neurology topic hub for spinal cord, cerebellar and cortical localization.
Sources
- Gates P. The rule of 4 of the brainstem: a simplified method for understanding brainstem anatomy and brainstem vascular syndromes for the non-neurologist. Intern Med J. 2005 (PubMed)
- Brainstem Stroke — StatPearls, NCBI Bookshelf
- Vertebrobasilar Stroke — StatPearls, NCBI Bookshelf
- Pontine Infarction (archived chapter) — StatPearls, NCBI Bookshelf
- Wallenberg Syndrome (archived chapter) — StatPearls, NCBI Bookshelf
- Medial Medullary Syndrome — StatPearls, NCBI Bookshelf
- Benedikt Syndrome — StatPearls, NCBI Bookshelf
- Parinaud Syndrome — StatPearls, NCBI Bookshelf
- Internuclear Ophthalmoplegia — StatPearls, NCBI Bookshelf
- Prabhakaran S, et al. 2026 Guideline for the Early Management of Patients With Acute Ischemic Stroke (AHA/ASA). Stroke. 2026 (PubMed)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
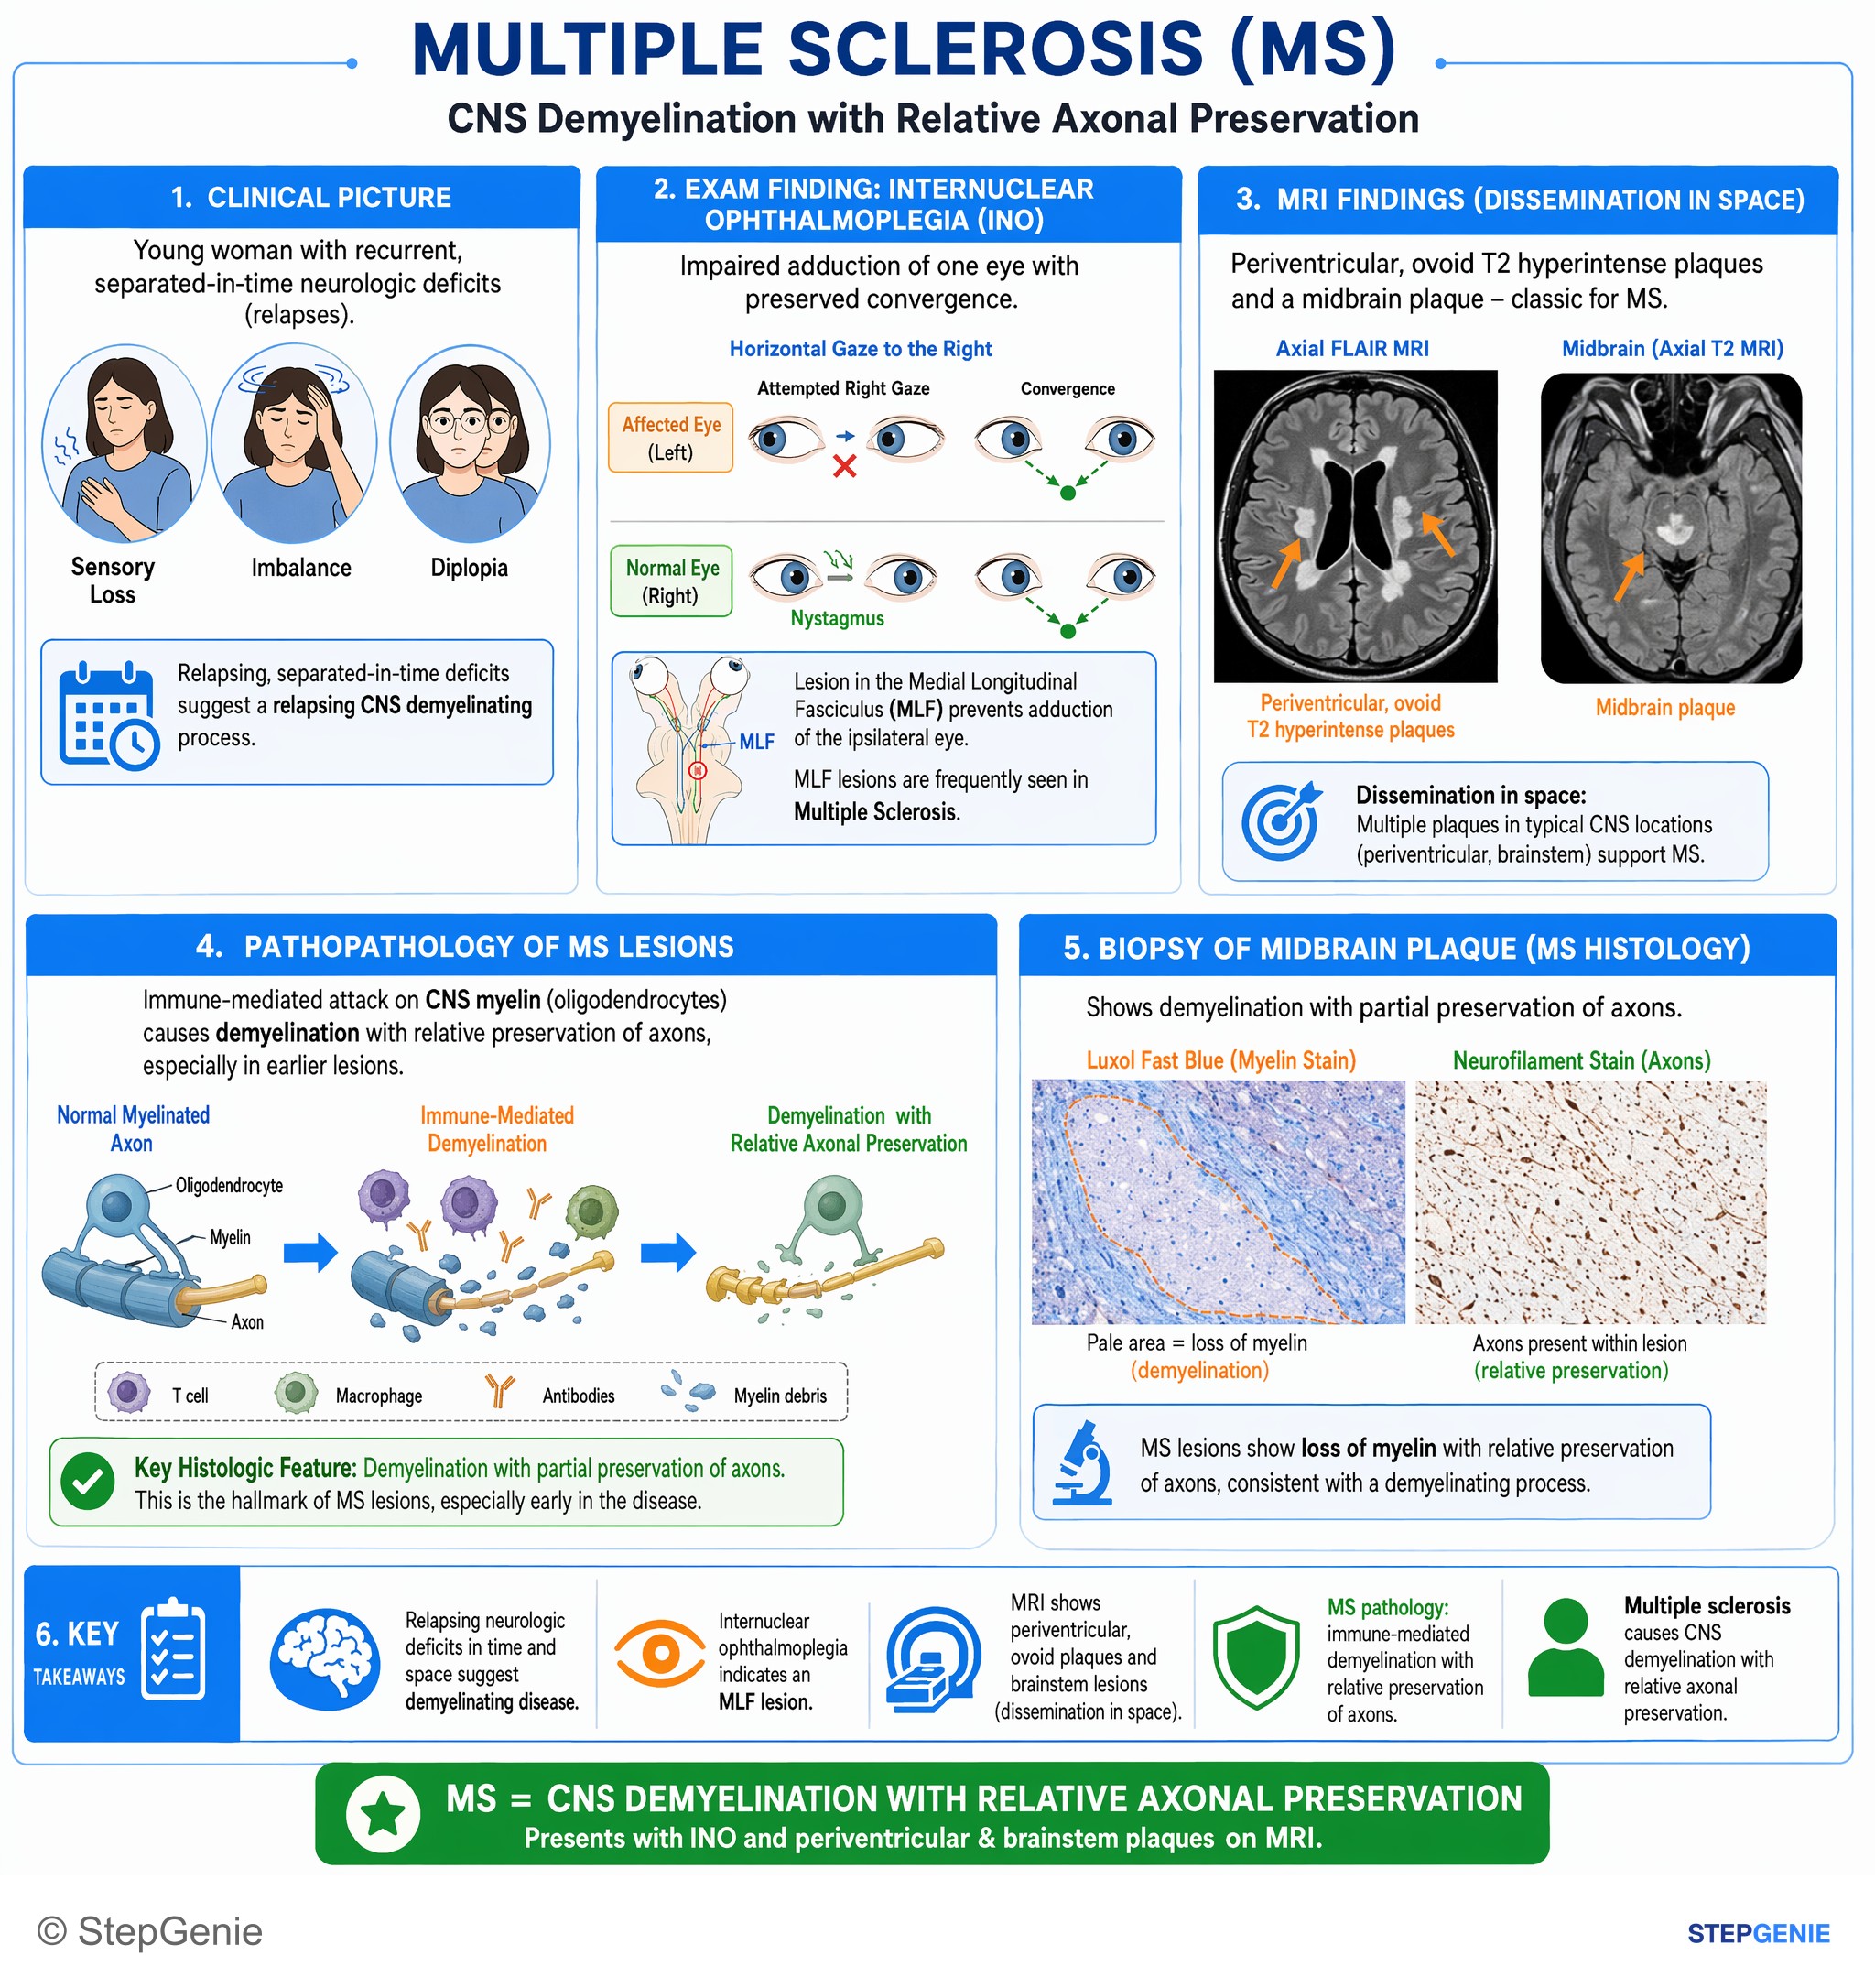
Multiple sclerosis causes CNS demyelination with relative axonal preservation, presenting with internuclear ophthalmoplegia and…
USMLE Step 1Frequently Asked Questions
What is the Rule of 4 of the brainstem?
It is a localization shortcut published by neurologist Peter Gates in 2005. Four medial structures begin with M (motor pathway, medial lemniscus, medial longitudinal fasciculus, and the motor nuclei of III, IV, VI and XII), four lateral structures begin with S (spinocerebellar, spinothalamic, sensory nucleus of V, sympathetic), and there are four cranial nerves in the medulla, four in the pons and four above the pons. Matching a patient's deficits to the M's and S's tells you whether a brainstem stroke is medial or lateral.
Which cranial nerve nuclei are in the midbrain, pons and medulla?
The midbrain contains the nuclei of CN III (including the Edinger-Westphal nucleus) and CN IV. The pons contains the motor and main sensory nuclei of CN V plus the nuclei of VI, VII and VIII, and the medulla contains IX, X and XII (the spinal accessory nucleus of XI, which drives SCM and trapezius, sits in the upper cervical cord, C1–C5). The trigeminal and vestibular nuclei also extend into the medulla, which is why a medullary stroke can still cause facial numbness and vertigo.
How do you tell lateral medullary (Wallenberg) syndrome from medial medullary syndrome?
Lateral medullary syndrome causes hoarseness, dysphagia and hiccups, pain and temperature loss on the ipsilateral face and contralateral body, an ipsilateral Horner syndrome, ataxia and vertigo, usually without significant weakness. Medial medullary syndrome instead causes contralateral hemiparesis that spares the face and contralateral loss of vibration and proprioception, with the tongue deviating toward the side of the lesion. Lateral is usually a vertebral artery or PICA stroke, while medial involves the anterior spinal artery or vertebral paramedian branches.
What is the mnemonic for midbrain syndromes?
Weber, Claude and Benedikt syndromes all share an ipsilateral oculomotor (CN III) palsy, so let the first letter name the second finding: Weber means weakness (contralateral hemiparesis), Claude means clumsy (contralateral ataxia) and Benedikt means both (hemiparesis plus ataxia, tremor or choreoathetosis). Parinaud syndrome is the odd one out: a dorsal midbrain lesion, often compression by a pineal tumor, that causes upgaze palsy, convergence-retraction nystagmus and light-near dissociation.
Which artery causes lateral medullary (Wallenberg) syndrome?
Wallenberg syndrome is classically taught as a PICA stroke, but about 80% of cases are caused by occlusion of the vertebral artery, which feeds the lateral medulla and the PICA territory. In younger patients the commonest cause is vertebral artery dissection, which can follow neck trauma or manipulation. The clinical picture is the same either way: hoarseness, dysphagia, crossed pain and temperature loss, Horner syndrome and ataxia.
Which brainstem reflexes test the midbrain, pons and medulla?
The pupillary light reflex (CN II in, CN III out) tests the midbrain. The corneal reflex (V1 in, VII out) and jaw jerk (V3 in and out) test the pons, while the gag (IX in, X out) and cough (X in and out) reflexes test the medulla. The pupillary, corneal, oculocephalic, caloric, gag and cough reflexes are all tested, along with an apnea test, when a comatose patient is evaluated for brain death.