Vitamin D questions on Step 1 love to look “simple” (sunlight → strong bones) and then test you on the one enzyme, organ, or regulator that breaks the chain. If you can trace vitamin D from skin → liver → kidney → intestine/bone and map what PTH, phosphate, FGF23, and kidney disease do to that pathway, you’ll crush most calcium/bone metabolism stems.
Big Picture: What Vitamin D Does (and Why Step 1 Cares)
Vitamin D (calcitriol, ) is a steroid hormone that primarily:
- Increases intestinal absorption of calcium and phosphate
- Promotes bone mineralization when Ca/Phos supply is adequate
- Can increase bone resorption (via RANKL) in certain contexts to maintain serum calcium
On exams, vitamin D is often tested in the context of:
- Rickets/osteomalacia
- CKD (renal osteodystrophy)
- Hypo/hyperparathyroidism
- Malabsorption
- Granulomatous disease → hypercalcemia
Vitamin D Metabolism: The High-Yield Pathway
Stepwise conversion (know the organs + enzymes)
| Step | Substrate → Product | Where | Enzyme | Regulation (HY) |
|---|---|---|---|---|
| 1 | 7-dehydrocholesterol → Cholecalciferol (D3) | Skin | UVB | ↓ with sunscreen, darker skin, low sun exposure |
| 2 | D3 → 25-hydroxyvitamin D (calcidiol) | Liver | 25-hydroxylase | Mostly substrate-driven; best measure of body stores |
| 3 | 25(OH)D → 1,25-dihydroxyvitamin D (calcitriol) | Kidney (proximal tubule) | 1α-hydroxylase | ↑ by PTH, ↓ by phosphate, ↓ by FGF23 |
Two lab values that Step 1 loves to trick you with
- 25(OH)D (calcidiol) = storage form and best test for vitamin D deficiency
- 1,25(OH)D (calcitriol) = active form and can be normal or even high in deficiency (because PTH upregulates 1α-hydroxylase)
Regulation: Who Turns Calcitriol Up or Down?
Parathyroid hormone (PTH): the “kidney activator”
Low calcium → ↑ PTH → kidney:
- ↑ 1α-hydroxylase → ↑ calcitriol
- ↑ Ca reabsorption (DCT)
- ↓ phosphate reabsorption (PCT) → phosphaturia
- ↑ bone resorption (via osteoblast RANKL → osteoclast activation)
Net: raises serum calcium; lowers serum phosphate.
Phosphate & FGF23: the “calcitriol brakes”
- High phosphate stimulates FGF23 (made by osteocytes)
- FGF23:
- ↓ 1α-hydroxylase → ↓ calcitriol
- ↓ phosphate reabsorption in PCT (phosphaturia)
Classic teaching: FGF23 is the body’s “anti-phosphate” hormone and reduces active vitamin D.
Mechanism of Action: How Vitamin D Works at Target Tissues
Intestine (highest yield)
Calcitriol increases:
- Calcium absorption (via ↑ TRPV6 channels, ↑ calbindin)
- Phosphate absorption
Bone
Vitamin D:
- Supports mineralization by providing Ca/Phos availability
- In conjunction with PTH, can promote resorption (upregulates RANKL via osteoblasts)
Kidney
Calcitriol modestly:
- Increases Ca/Phos reabsorption, but its major “exam effect” is through the gut.
Deficiency: Pathophysiology You’ll Actually See in Questions
Common causes
- Low sunlight exposure (institutionalized, high latitude)
- Darker skin (melanin blocks UVB)
- Malabsorption (celiac, Crohn, pancreatic insufficiency, bariatric surgery)
- Liver disease (↓ 25-hydroxylation)
- CKD (↓ 1α-hydroxylation → low calcitriol)
- Medications: enzyme inducers like phenytoin, phenobarbital (increase vitamin D catabolism)
What deficiency does to labs (pattern recognition)
Low vitamin D → ↓ intestinal Ca/Phos absorption → low calcium (or low-normal) → secondary hyperparathyroidism → phosphate wasting.
Typical deficiency labs:
- ↓ 25(OH)D
- ↓ Ca (may be low-normal early)
- ↓ phosphate (because PTH wastes phosphate)
- ↑ PTH
- ↑ alkaline phosphatase (high bone turnover/osteoblast activity)
HY nuance: In early deficiency, calcium may be normal due to compensatory PTH—so the giveaway becomes low phosphate + high PTH + high ALP + low 25(OH)D.
Clinical Presentations (Step-Style)
Rickets (kids)
Think: failure of mineralization at growth plates.
- Bone deformities: bowed legs (genu varum), knock-knees
- Rachitic rosary (enlarged costochondral junctions)
- Craniotabes, delayed closure of fontanelle
- Delayed growth, delayed tooth eruption
Osteomalacia (adults)
Think: poorly mineralized osteoid.
- Diffuse bone pain, tenderness
- Proximal muscle weakness
- ↑ fracture risk (especially insufficiency fractures)
Diagnosis: What to Order and How to Interpret It
Best initial test for vitamin D status
- Serum 25(OH)D
Helpful add-ons (often tested together)
- Calcium, phosphate, PTH, alkaline phosphatase
- Consider celiac testing or malabsorption workup if persistent
Imaging clues (less common but very Step 1)
- Rickets: metaphyseal cupping/fraying on X-ray
- Osteomalacia: Looser zones/pseudofractures
Treatment (and Exam-Relevant “Which Form Do I Give?”)
Nutritional deficiency (most common)
- Vitamin D3 (cholecalciferol) supplementation
- Ensure adequate calcium intake
Malabsorption or severe deficiency
- Higher-dose vitamin D regimens; sometimes calcidiol/calcitriol depending on context
- Treat underlying cause (celiac, pancreatic insufficiency, etc.)
CKD: key twist
- Kidney can’t do 1α-hydroxylation → low calcitriol even if 25(OH)D is okay
- Treat with active vitamin D:
- Calcitriol (1,25(OH)D) or analogs (e.g., paricalcitol)
- Also manage hyperphosphatemia (dietary phosphate restriction, phosphate binders)
Hypervitaminosis D and Hypercalcemia: The “Overdose” Pattern
Excess vitamin D (supplements) → hypercalcemia + hyperphosphatemia because intestinal absorption of both rises.
Findings:
- Nausea, constipation, polyuria, confusion
- Nephrolithiasis
- Shortened QT (hypercalcemia)
Labs:
- ↑ Ca, ↑ phosphate, ↓ PTH
Management is cause-dependent (stop supplements; IV fluids; consider bisphosphonates/calcitonin if significant hypercalcemia).
High-Yield Associations & Classic Vignettes
1) Chronic kidney disease → low calcitriol → secondary hyperparathyroidism
Mechanism: ↓ 1α-hydroxylase + phosphate retention → ↓ Ca → ↑ PTH
Labs: ↓ Ca, ↑ phosphate, ↑ PTH, ↑ ALP
Buzzwords: “renal osteodystrophy,” bone pain, pruritus, vascular calcifications.
2) Granulomatous disease (sarcoid, TB) → hypercalcemia
Macrophages express 1α-hydroxylase outside kidney → ↑ calcitriol independent of PTH.
Labs: ↑ Ca, ↓ PTH, ↑ 1,25(OH)D
Clue: hypercalcemia in sarcoidosis with hilar adenopathy.
3) Anticonvulsants (phenytoin/phenobarbital) → vitamin D deficiency
Induce CYP450 → ↑ vitamin D breakdown → osteomalacia/rickets risk.
4) Liver disease affects 25-hydroxylation
Leads to low 25(OH)D and downstream effects.
Rapid-Fire Step 1 “If You See X, Think Y”
- Best indicator of vitamin D stores → 25(OH)D
- PTH increases calcitriol → stimulates 1α-hydroxylase
- FGF23 decreases calcitriol and increases phosphate wasting
- CKD → can’t activate vitamin D → treat with calcitriol
- Sarcoidosis/TB → ectopic 1α-hydroxylase → hypercalcemia with low PTH
- Vitamin D deficiency → ↑ PTH, ↑ ALP, often ↓ phosphate
First Aid Cross-References (Where This Lives in FA)
Use these as your quick “flip-to” anchors (edition-dependent headings may shift slightly):
- Endocrine → Calcium homeostasis: PTH vs vitamin D actions (bone, kidney, gut)
- Renal → Chronic kidney disease: secondary hyperparathyroidism / renal osteodystrophy
- Musculoskeletal → Bone disorders: rickets, osteomalacia, osteoporosis differentiation
- Endocrine pharmacology: vitamin D preparations (cholecalciferol, ergocalciferol, calcitriol)
(Exact page numbers vary by edition; search within FA for “1α-hydroxylase,” “FGF23,” “rickets,” and “renal osteodystrophy.”)
Mini Table: Differentiate Bone Conditions Fast
| Condition | Primary problem | Calcium | Phosphate | PTH | ALP |
|---|---|---|---|---|---|
| Vitamin D deficiency (rickets/osteomalacia) | Low mineralization (low Vit D) | ↓ / low-normal | ↓ | ↑ | ↑ |
| CKD bone disease | ↓ calcitriol + phosphate retention | ↓ | ↑ | ↑ | ↑ |
| Primary hyperparathyroidism | Excess PTH | ↑ | ↓ | ↑ | ↑ |
| Vitamin D toxicity | Excess absorption | ↑ | ↑ | ↓ | variable |
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
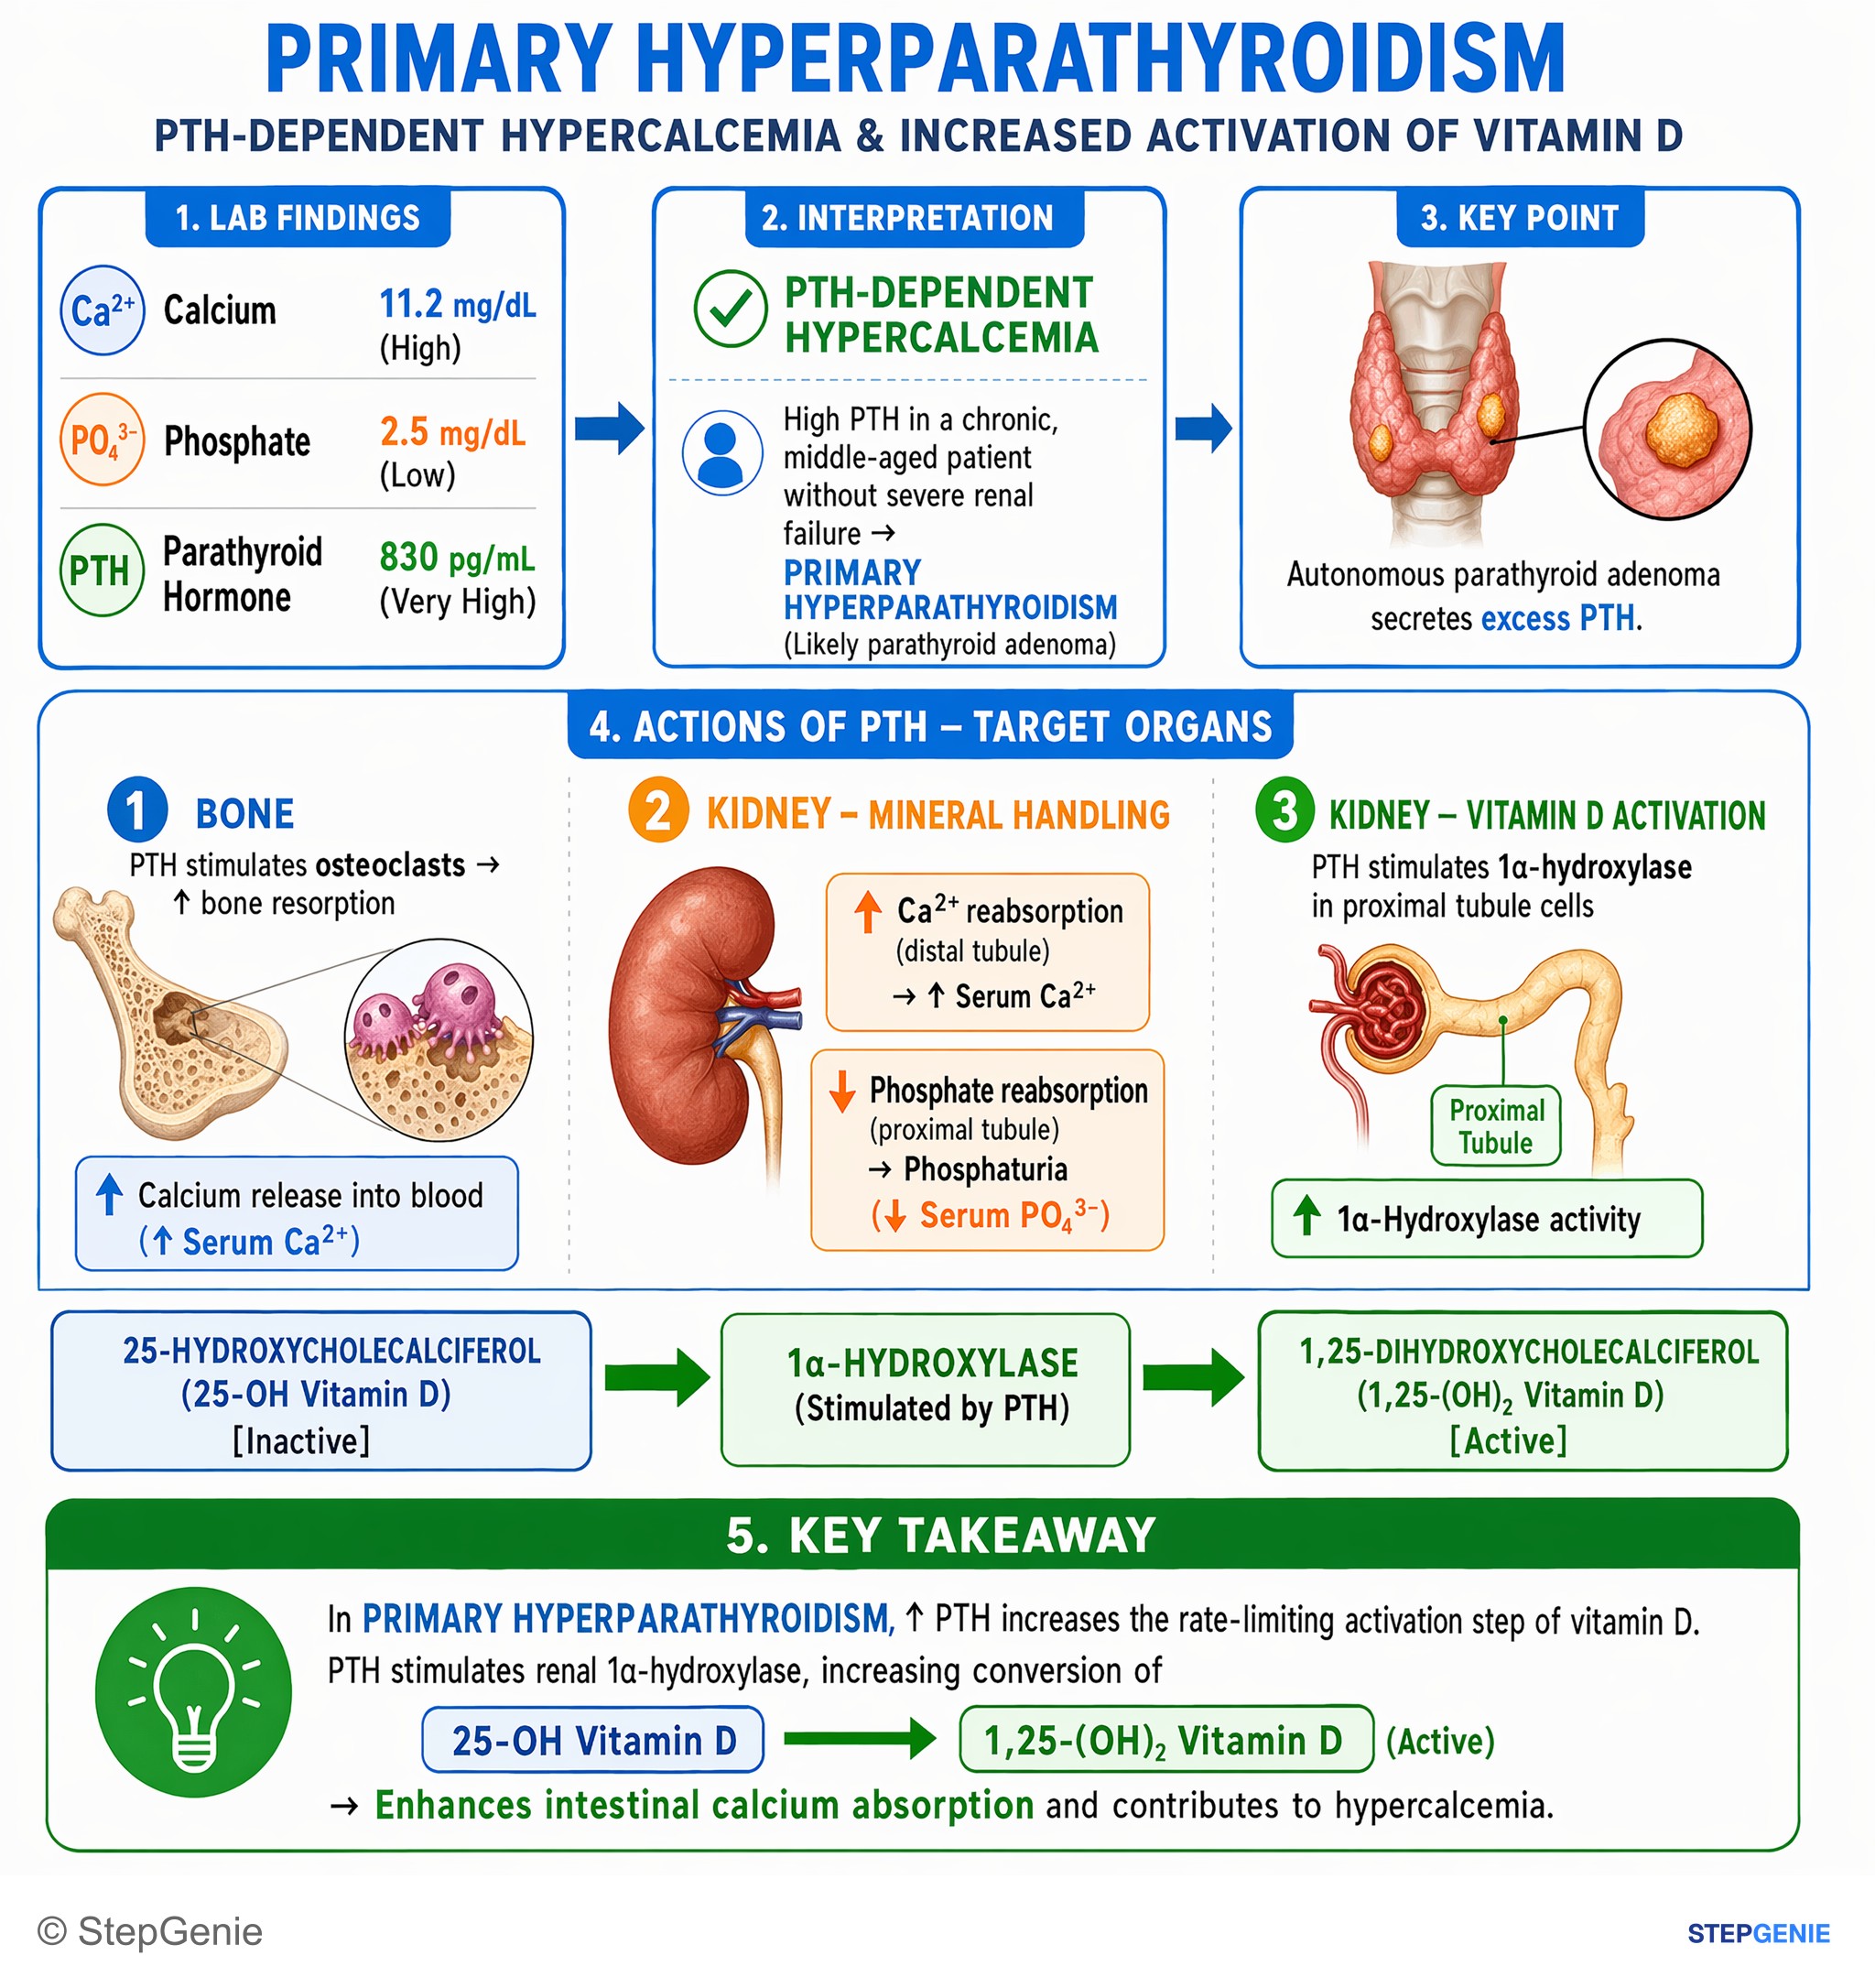
Primary hyperparathyroidism causes ↑PTH, which stimulates renal 1α-hydroxylase, increasing conversion of 25-OH vitamin D to active…
USMLE Step 1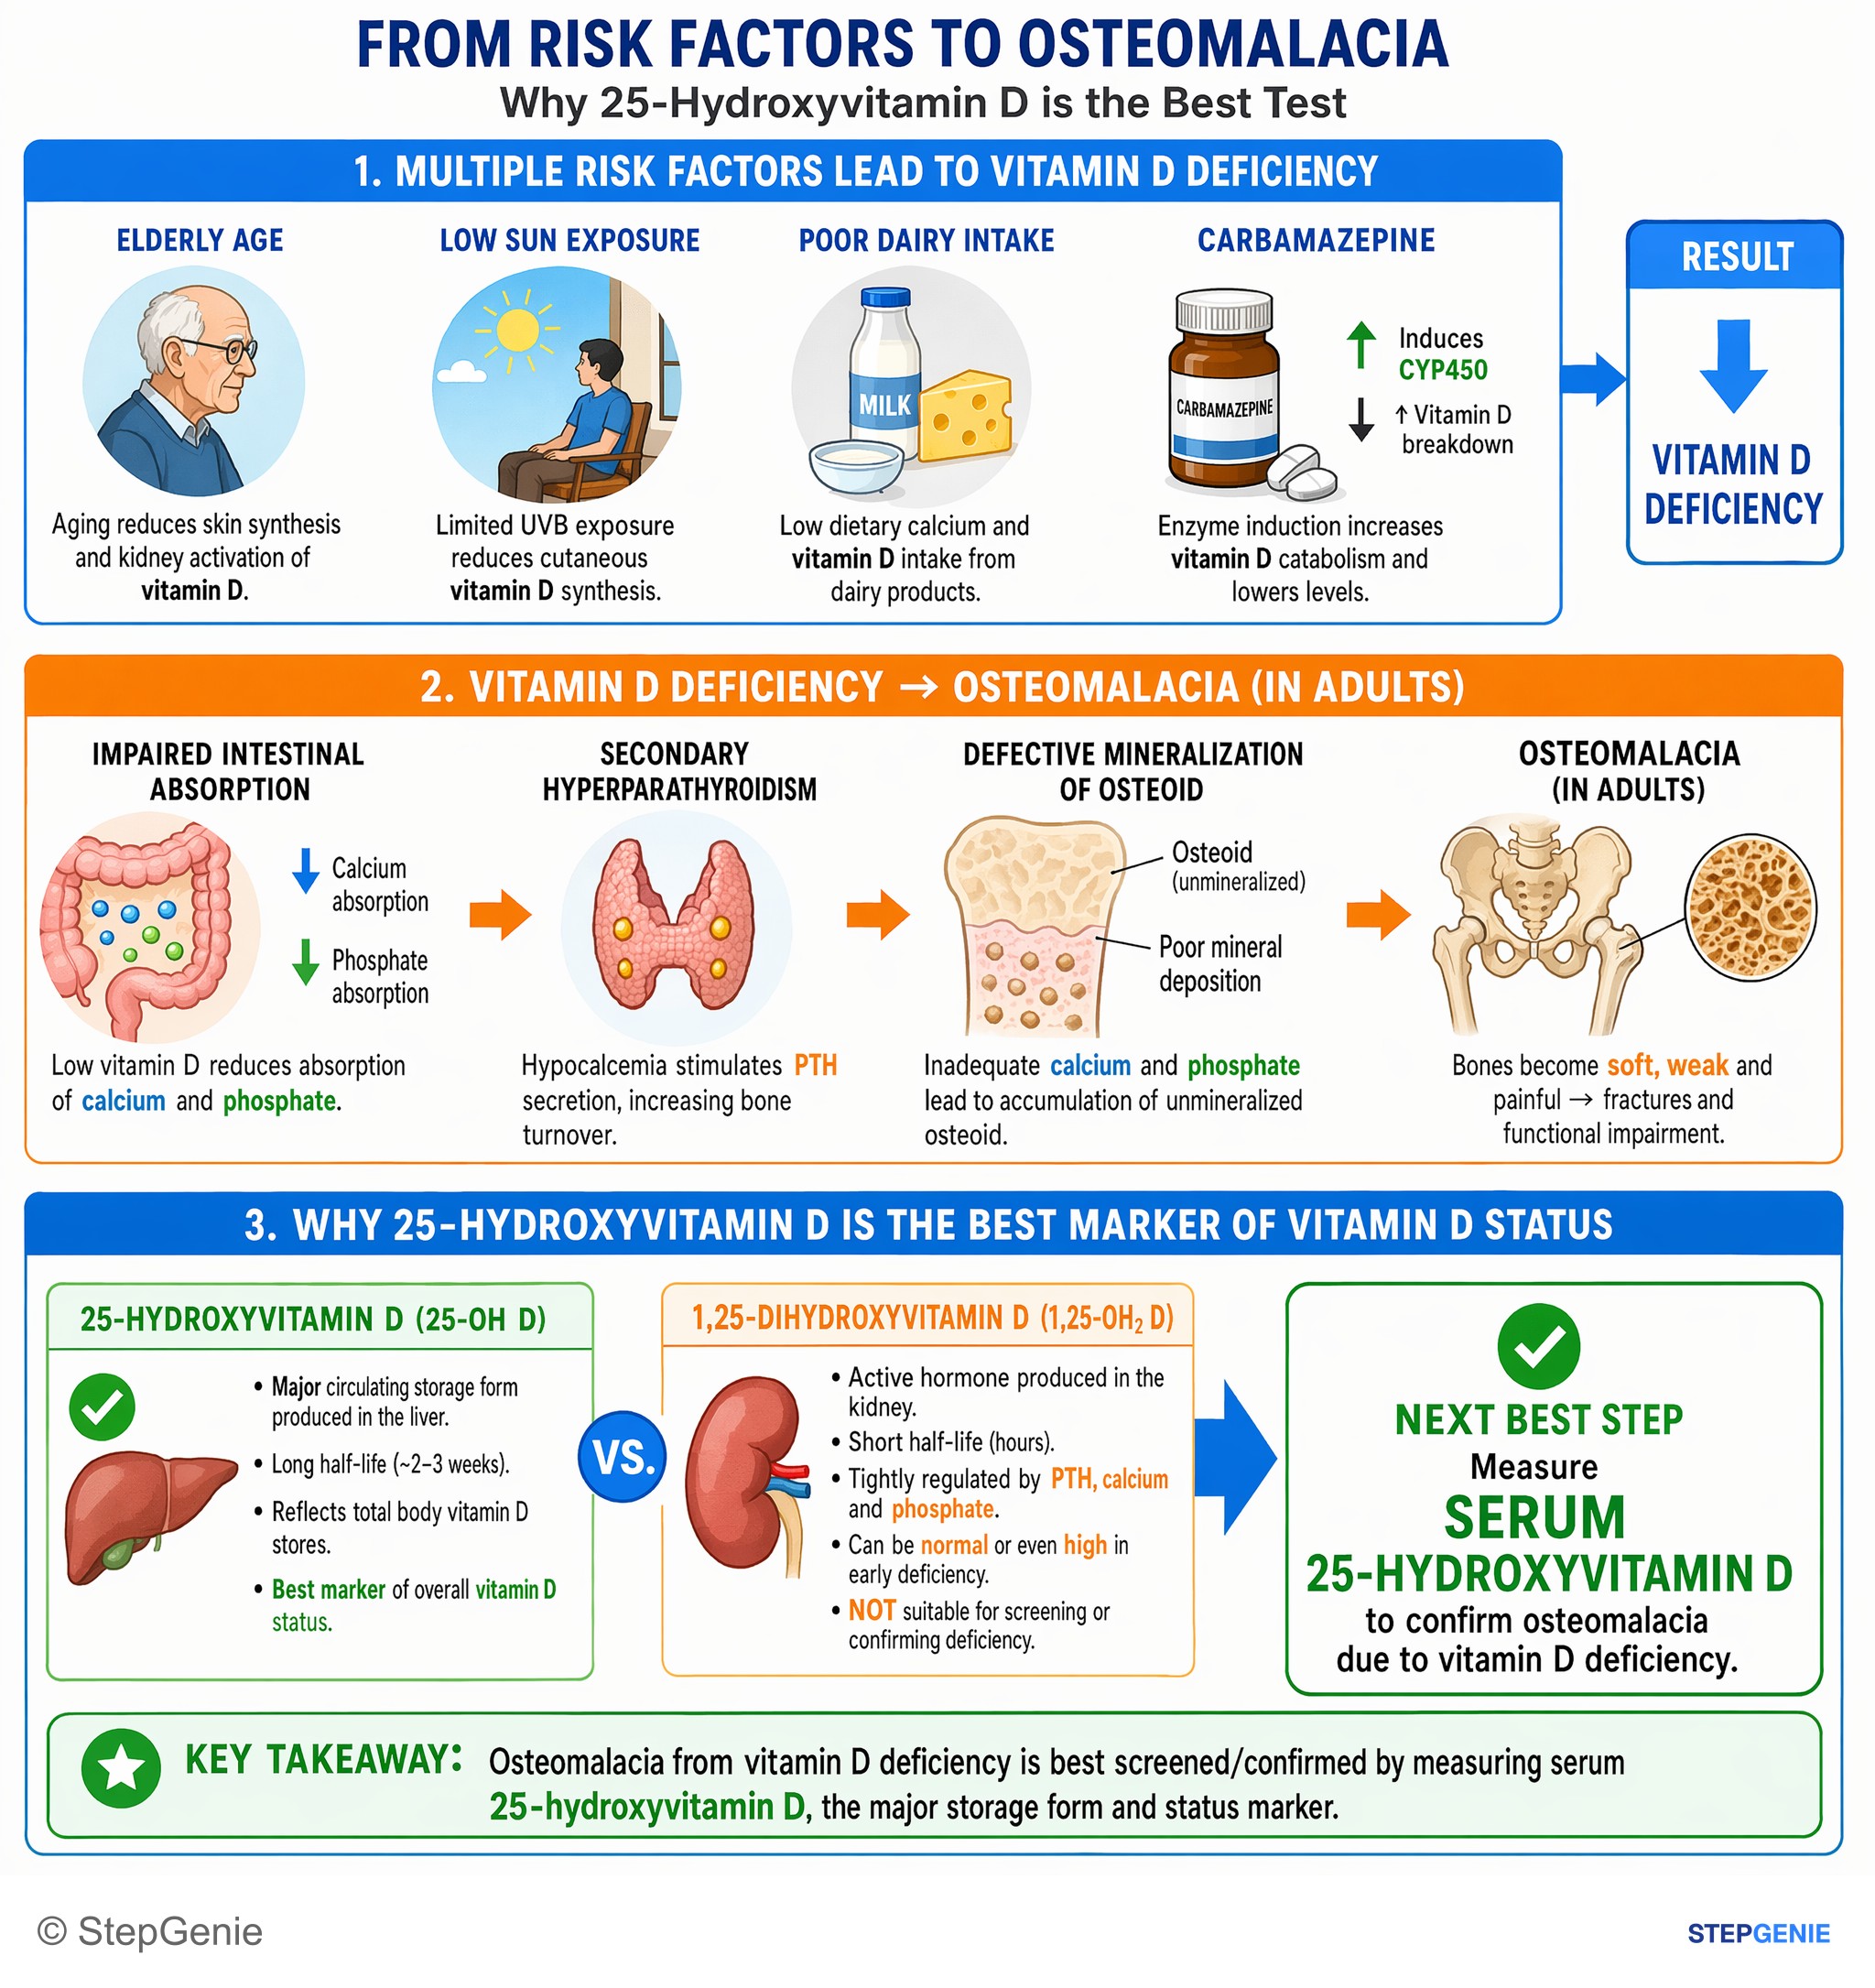
Osteomalacia from vitamin D deficiency is best screened/confirmed by measuring serum 25‑hydroxyvitamin D, the major storage form and…
USMLE Step 2Frequently Asked Questions
What is the best lab test for vitamin D deficiency on Step 1?
The best test for vitamin D deficiency is serum 25-hydroxyvitamin D, also called calcidiol. It is the storage form and best reflects body vitamin D stores. Step 1 often tries to distract with 1,25-dihydroxyvitamin D, but that active form can be normal or even elevated in deficiency because secondary hyperparathyroidism upregulates renal 1α-hydroxylase.
Why can 1,25-dihydroxyvitamin D be normal or high in vitamin D deficiency?
It can be normal or high because vitamin D deficiency lowers calcium absorption, which raises PTH. Increased PTH stimulates renal 1α-hydroxylase, increasing conversion of 25-hydroxyvitamin D to 1,25-dihydroxyvitamin D. That means the active form may not look low early on, even though total vitamin D stores are depleted and the 25-hydroxyvitamin D level is low.
How do you recognize the typical lab pattern of vitamin D deficiency?
The classic pattern is low 25-hydroxyvitamin D, low calcium or low-normal calcium, low phosphate, high PTH, and high alkaline phosphatase. The mechanism is decreased intestinal calcium and phosphate absorption, followed by secondary hyperparathyroidism. PTH then causes phosphate wasting, so early deficiency may be recognized by low phosphate, elevated PTH, elevated alkaline phosphatase, and low 25-hydroxyvitamin D even if calcium is still normal.
Why does chronic kidney disease cause low calcitriol?
Chronic kidney disease causes low calcitriol because the kidney normally performs the 1α-hydroxylation step that activates vitamin D. This conversion happens in the proximal tubule, turning 25-hydroxyvitamin D into 1,25-dihydroxyvitamin D. In CKD, that activation is impaired, so calcitriol falls even if 25-hydroxyvitamin D is still adequate, which is why CKD is a classic setup for renal osteodystrophy questions.
What vitamin D form do you give in chronic kidney disease versus nutritional deficiency?
Nutritional deficiency is treated with vitamin D3, or cholecalciferol, along with adequate calcium intake. Chronic kidney disease is different because the kidney cannot perform 1α-hydroxylation, so patients need active vitamin D such as calcitriol or an analog like paricalcitol. The treatment choice depends on whether the problem is lack of substrate or failure of renal activation.