Secondary and tertiary hyperparathyroidism are classic “renal physiology meets endocrine” topics that show up on Step 1 because they force you to connect PTH, vitamin D, phosphate, and bone—and then predict what happens to labs, bones, and vessels. If you can explain why PTH rises in CKD and how that can evolve into autonomous parathyroid hyperplasia, you’ll crush most question stems.
Big-Picture Definitions (Know These Cold)
Secondary hyperparathyroidism
Appropriately elevated PTH due to a chronic low-calcium stimulus (most commonly chronic kidney disease).
- Parathyroid glands are responding to hypocalcemia / low calcitriol / hyperphosphatemia.
- PTH is elevated, but it’s not autonomous.
Tertiary hyperparathyroidism
Inappropriately elevated PTH due to autonomous parathyroid hyperplasia after longstanding secondary hyperparathyroidism.
- Parathyroid glands “learn” to over-secrete PTH and stop listening to feedback.
- Typically in end-stage renal disease, often after kidney transplant (because the glands remain hyperplastic and autonomous).
Pathophysiology: The Step 1 “Chain Reaction”
Secondary hyperparathyroidism in CKD (the classic)
CKD triggers multiple hits that converge on low effective calcium and high phosphate, driving PTH up:
- ↓ GFR → phosphate retention
- ↑ PO₄³⁻ binds free calcium → ↓ free Ca²⁺
- Diseased kidney has ↓ 1α-hydroxylase activity
- ↓ calcitriol (1,25-(OH)₂ vitamin D) → ↓ GI calcium absorption
- Low calcium + low calcitriol + high phosphate → ↑ PTH
- Chronic stimulation → parathyroid hyperplasia and bone remodeling changes
High-yield concept: PTH tries to “fix” calcium, but in CKD the kidney can’t execute the usual plan well (can’t dump phosphate effectively; impaired vitamin D activation).
Tertiary hyperparathyroidism (how secondary becomes autonomous)
Longstanding secondary hyperPTH → sustained parathyroid hyperplasia → glands become autonomous:
- PTH stays high even if the original trigger improves (e.g., post-transplant normalization of phosphate handling).
- Result: hypercalcemia + high PTH.
Lab Patterns (This Is Where Points Are)
Quick table: Secondary vs Tertiary (CKD context)
| Condition | PTH | Calcium | Phosphate | Calcitriol (1,25) | Classic setting |
|---|---|---|---|---|---|
| Secondary hyperPTH (CKD) | ↑ | ↓ or normal | ↑ | ↓ | CKD/ESRD |
| Tertiary hyperPTH | ↑↑ | ↑ | ↑ (often) or variable | variable | Longstanding ESRD; sometimes after transplant |
Test-taking tip:
- If CKD + high PTH + low/normal Ca → think secondary.
- If long CKD (or post-transplant) + high PTH + high Ca → think tertiary.
Clinical Presentation: What You’ll See in Stems
Secondary hyperparathyroidism (CKD-related)
Common clues:
- History of chronic kidney disease, dialysis, diabetes/HTN nephropathy
- Bone pain, fractures, proximal muscle weakness
- Pruritus (uremia), vascular disease
- Labs: ↑ PTH, ↑ phosphate, ↓ calcitriol, Ca low or normal
Bone disease association:
- Renal osteodystrophy (a spectrum) with prominent osteitis fibrosa cystica due to high PTH.
Tertiary hyperparathyroidism
Clues:
- Longstanding ESRD with persistent hyperPTH
- Or patient after kidney transplant who now has hypercalcemia with high PTH
- Symptoms tilt toward hypercalcemia:
- Constipation, polyuria/polydipsia, nephrolithiasis (less classic in ESRD), confusion
- Subperiosteal bone resorption and bone pain can persist
Bone Pathology You Should Recognize
Osteitis fibrosa cystica (high PTH bone changes)
- Increased osteoclast activity (via osteoblast-mediated RANKL signaling)
- Subperiosteal bone resorption
- “Brown tumors” (collections of osteoclasts + hemorrhage)
Step pearl: PTH increases bone resorption overall (even though intermittent PTH can be anabolic—think teriparatide).
Diagnosis: How Questions Want You to Reason
Stepwise approach
- Confirm PTH is elevated
- Decide whether the elevation is appropriate (secondary) or autonomous (tertiary):
- Check calcium and clinical context
- In CKD patients, also look at:
- Phosphate (often ↑)
- Calcitriol (often ↓)
- Alkaline phosphatase (often ↑ due to high bone turnover)
- Imaging is not first-line for diagnosis:
- Parathyroid imaging (sestamibi/US) is generally for surgical planning, not Step 1 diagnosis.
Treatment: High-Yield Management Moves
Secondary hyperparathyroidism (CKD)
Core goals: control phosphate, restore vitamin D signaling, reduce PTH.
- Dietary phosphate restriction
- Phosphate binders
- Calcium-based: calcium carbonate, calcium acetate (watch hypercalcemia)
- Non-calcium: sevelamer, lanthanum (helpful if Ca is high)
- Vitamin D supplementation / activated vitamin D
- Calcitriol (active form) is key in CKD because 1α-hydroxylation is impaired
- Calcimimetics (increase Ca-sensing receptor sensitivity)
- Cinacalcet → ↓ PTH (commonly used in dialysis patients)
Step tie-in: If the stem emphasizes low calcitriol and high phosphate, you’re in CKD secondary hyperPTH territory—think phosphate binders + calcitriol ± cinacalcet.
Tertiary hyperparathyroidism
- Medical therapy may help (calcimimetics), but definitive management is often:
- Parathyroidectomy (especially if severe hypercalcemia, symptoms, or refractory disease)
Step pearl: Tertiary = autonomous gland hyperplasia → often needs surgery.
High-Yield Associations & Differentials (Common Traps)
Secondary hyperPTH causes (beyond CKD)
- Vitamin D deficiency (malabsorption, low sun exposure)
- Usually: low Ca → ↑ PTH; phosphate often low/normal (depends)
- Calcium malabsorption
- Chronic liver disease (↓ 25-hydroxylation → functional vitamin D deficiency)
Distinguish from primary hyperparathyroidism (for comparison)
Primary hyperPTH (adenoma/hyperplasia) typically:
- ↑ PTH
- ↑ Ca
- ↓ phosphate
- Kidney stones, bone pain, psychiatric symptoms
Fast differentiation in one line:
- Primary: PTH high causes hypercalcemia.
- Secondary: PTH high responds to hypocalcemia (often CKD).
- Tertiary: PTH high becomes autonomous → hypercalcemia.
First Aid Cross-References (Where to Anchor This)
In First Aid for the USMLE Step 1, connect this topic to:
- Endocrine → Parathyroid disorders (PTH regulation, primary vs secondary vs tertiary patterns)
- Renal → CKD/ESRD complications
- Endocrine/Renal → Vitamin D metabolism (1α-hydroxylase in kidney; calcitriol effects)
- Musculoskeletal → Bone remodeling (PTH effects; osteitis fibrosa cystica)
- Pharm:
- Cinacalcet (calcimimetic)
- Sevelamer (phosphate binder)
- Calcitriol
(Section titles and page numbers vary by edition, but these are the consistent placement “neighborhoods” in First Aid.)
USMLE-Style Rapid Review (What to Memorize)
Secondary hyperparathyroidism (CKD): the signature
- ↑ PO₄³⁻, ↓ calcitriol, ↓/normal Ca²⁺, ↑ PTH
- Leads to renal osteodystrophy / high-turnover bone disease
- Treat: phosphate binders + calcitriol ± cinacalcet
Tertiary hyperparathyroidism: the punchline
- After chronic secondary hyperPTH, glands become autonomous
- ↑↑ PTH + ↑ Ca²⁺ (often in ESRD; may persist post-transplant)
- Often needs parathyroidectomy
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
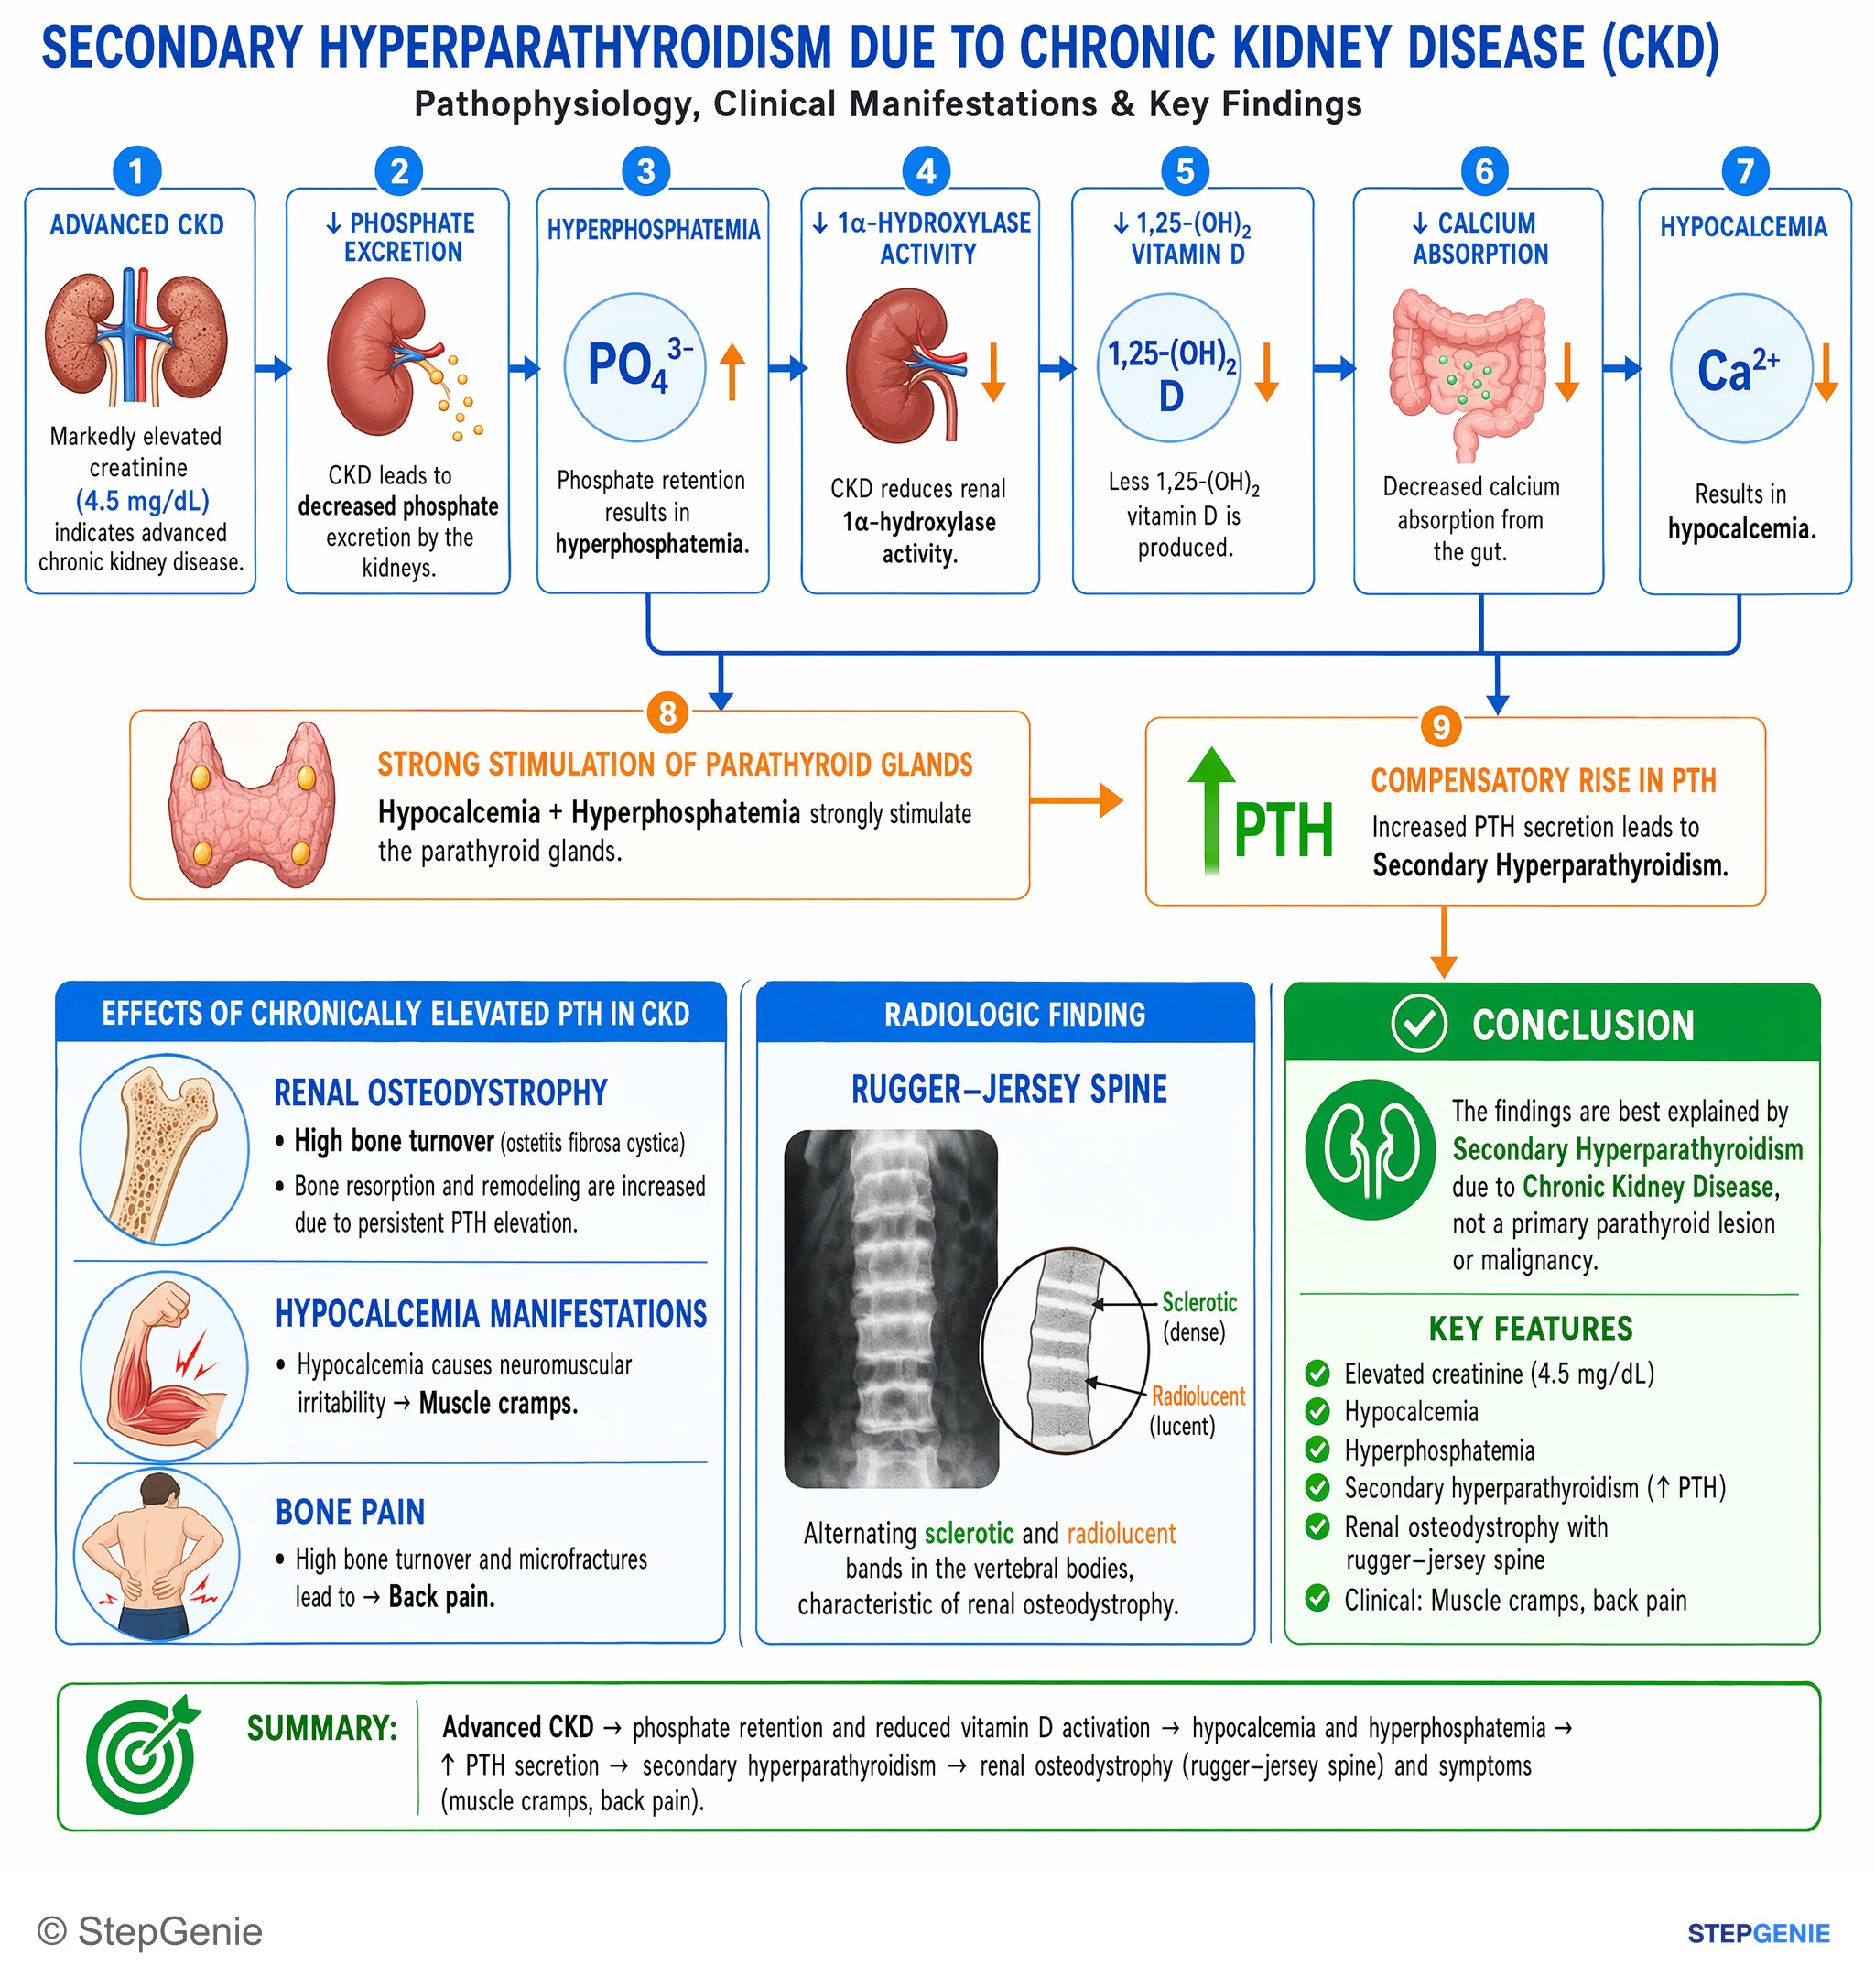
Secondary hyperparathyroidism due to chronic kidney disease → hypocalcemia, hyperphosphatemia, renal osteodystrophy with alternating…
USMLE Step 1Frequently Asked Questions
Why does chronic kidney disease cause secondary hyperparathyroidism?
Chronic kidney disease causes secondary hyperparathyroidism because it creates a chronic low-calcium stimulus that appropriately drives PTH upward. Reduced GFR causes phosphate retention, and the extra phosphate binds free calcium. At the same time, diseased kidneys have decreased 1α-hydroxylase activity, so calcitriol falls and gastrointestinal calcium absorption drops. Low calcium, low calcitriol, and high phosphate together stimulate sustained PTH secretion.
How do you tell secondary from tertiary hyperparathyroidism in a CKD patient?
The key difference is whether the elevated PTH is still an appropriate response or has become autonomous. In secondary hyperparathyroidism from CKD, PTH is high but calcium is usually low or normal, with high phosphate and low calcitriol. In tertiary hyperparathyroidism, longstanding secondary stimulation leads to autonomous parathyroid hyperplasia, so PTH remains high and calcium becomes high, especially in long ESRD or after kidney transplant.
Why can tertiary hyperparathyroidism cause hypercalcemia even after a kidney transplant?
Tertiary hyperparathyroidism causes hypercalcemia after kidney transplant because the parathyroid glands may stay hyperplastic and autonomous even when the original renal trigger improves. After longstanding secondary hyperparathyroidism, the glands effectively stop responding to normal feedback and continue over-secreting PTH. The result is persistently elevated PTH with hypercalcemia despite improved phosphate handling after transplant.
What bone findings are associated with secondary or tertiary hyperparathyroidism?
Both forms can produce high-PTH bone disease, especially osteitis fibrosa cystica. PTH increases overall bone resorption through osteoblast-mediated RANKL signaling, which raises osteoclast activity. Classic findings include subperiosteal bone resorption, bone pain, and brown tumors made of osteoclast collections and hemorrhage. In CKD-related disease, these changes are part of the broader spectrum of renal osteodystrophy.
What is the first-line treatment approach for secondary hyperparathyroidism in CKD?
The first-line approach is to control phosphate, restore vitamin D signaling, and reduce PTH. Treatment includes dietary phosphate restriction and phosphate binders such as calcium carbonate, calcium acetate, sevelamer, or lanthanum. Because kidney 1α-hydroxylation is impaired, calcitriol is important in CKD. Cinacalcet, a calcimimetic that increases calcium-sensing receptor sensitivity, is also commonly used, especially in dialysis patients.