Hypoparathyroidism is one of those Step 1 topics that looks “small” until it shows up as a post-thyroidectomy patient with tingling, a prolonged QT, and a calcium level that’s tanked. If you can quickly connect low PTH → low calcium + high phosphate and recognize classic neuromuscular irritability signs, you’ll grab easy points on both Step 1 and Step 2.
Big Picture: What Hypoparathyroidism Is
Hypoparathyroidism = inappropriately low parathyroid hormone (PTH) leading to hypocalcemia and hyperphosphatemia.
High-yield definition (Step-ready)
- Low PTH → ↓ serum Ca, ↑ serum phosphate
- Often presents with tetany and neuromuscular irritability
PTH Physiology Refresher (Because the Path Makes the Questions Easy)
PTH normally raises serum calcium and lowers serum phosphate via:
- Bone: stimulates osteoblasts to express RANKL → activates osteoclasts → ↑ bone resorption → ↑ Ca (and phosphate release too)
- Kidney:
- ↑ Ca reabsorption (distal tubule)
- ↓ phosphate reabsorption (proximal tubule) → phosphaturia
- ↑ 1-hydroxylase → ↑ 1,25-(OH) vitamin D (calcitriol) → ↑ GI absorption of Ca and phosphate
So if PTH is low:
- Less calcitriol → ↓ GI calcium absorption
- Less renal Ca reabsorption → more calcium lost
- More phosphate retained (no phosphaturia) → ↑ serum phosphate
- Net: hypocalcemia + hyperphosphatemia
Pathophysiology: The High-Yield Lab Pattern
Core lab signature
| Parameter | Hypoparathyroidism |
|---|---|
| PTH | Low |
| Calcium | Low |
| Phosphate | High |
| 1,25-(OH) vitamin D (calcitriol) | Low (often) |
| QT interval | Prolonged (from hypocalcemia) |
Classic Step contrast:
- Pseudohypoparathyroidism = PTH high (end-organ resistance), but Ca low and phos high. (More on this below.)
Etiologies: What Causes Low PTH?
1) Post-surgical (most commonly tested)
- Accidental removal or devascularization of parathyroids during:
- Thyroidectomy
- Neck surgery (parathyroid surgery, laryngectomy)
- Step vignette: “After thyroid surgery, patient has perioral tingling and carpopedal spasm.”
2) Autoimmune destruction
- Can be part of autoimmune polyglandular syndromes (less commonly tested than surgery, but fair game)
3) DiGeorge syndrome (22q11 deletion)
- Failure of 3rd/4th pharyngeal pouches → absent thymus + absent parathyroids
- Leads to:
- Hypocalcemia (low PTH)
- Recurrent infections (T-cell deficiency)
- Conotruncal cardiac defects
4) Severe hypomagnesemia (functional hypoparathyroidism)
- Low Mg impairs PTH secretion and can cause PTH resistance
- High-yield clinical move: if hypocalcemia won’t correct, check Mg
Clinical Presentation: How It Shows Up
Hypocalcemia increases neuronal excitability → tetany and irritability.
Symptoms (commonly tested)
- Perioral numbness/tingling
- Muscle cramps
- Tetany
- Seizures (severe hypocalcemia)
- Anxiety/irritability
Physical exam signs (must-know)
- Chvostek sign: facial muscle spasm with tapping facial nerve
- Trousseau sign: carpopedal spasm with BP cuff inflation (ischemia-induced tetany)
Cardiac findings
- Prolonged QT interval → risk of arrhythmias
(Think: hypocalcemia = long QT)
Diagnosis: A Practical Stepwise Approach
1) Confirm hypocalcemia
- Measure total calcium and/or ionized calcium
- Always interpret total calcium with albumin in mind (Step-style pitfall):
- Low albumin can lower total Ca without true hypocalcemia (ionized Ca may be normal)
2) Check PTH
- Low Ca + low PTH → points to hypoparathyroidism
3) Check phosphate and magnesium
- Phosphate: typically high
- Magnesium: rule out hypomagnesemia as a reversible cause
4) Consider vitamin D metabolites if needed
- Low PTH → low renal activation of vitamin D → ↓ calcitriol
Treatment: Acute vs Chronic (What You’d Actually Do + What They Test)
Acute symptomatic hypocalcemia (tetany, seizures, arrhythmias)
- IV calcium gluconate
- Also correct:
- Mg if low (critical to actually fix the problem)
- Monitor ECG (QT interval)
Chronic management
- Oral calcium supplementation
- Calcitriol (active vitamin D) is typically used because low PTH reduces ability to activate vitamin D
- Sometimes:
- Thiazide diuretics (to reduce urinary calcium losses) in select chronic cases (more Step 2–ish nuance)
Clinical pearl: Regular vitamin D (cholecalciferol/ergocalciferol) may not be sufficient alone because the bottleneck is 1-hydroxylation, which is PTH-dependent.
High-Yield Associations & “Classic Vignettes”
Post-thyroidectomy hypocalcemia
- Time course: can occur within hours to days after surgery
- Symptoms: tingling, cramps, tetany
- Labs: ↓ PTH, ↓ Ca, ↑ phosphate
- ECG: prolonged QT
DiGeorge syndrome
- Infant with hypocalcemic seizures + infections + cardiac defects
Hypomagnesemia masquerade
- Alcohol use disorder, diarrhea, diuretics → low Mg → low PTH effect
- Hypocalcemia refractory to calcium until magnesium corrected
The Must-Not-Confuse Differential (Rapid Comparison Table)
| Condition | PTH | Ca | Phosphate | Key clue |
|---|---|---|---|---|
| Hypoparathyroidism | ↓ | ↓ | ↑ | Post-thyroidectomy, autoimmune, DiGeorge |
| Pseudohypoparathyroidism (Albright hereditary osteodystrophy) | ↑ | ↓ | ↑ | End-organ resistance to PTH; short 4th/5th metacarpals |
| Secondary hyperparathyroidism (CKD) | ↑ | ↓/N | ↑ | CKD → phosphate retention + low calcitriol |
| Primary hyperparathyroidism | ↑ | ↑ | ↓ | Stones, bones, groans; adenoma most common |
First Aid Cross-References (Where This Lives in Your Memory Palace)
You’ll find hypoparathyroidism concepts integrated in First Aid under:
- Endocrine → Parathyroid disorders (hypo vs hyperparathyroidism)
- Calcium regulation + vitamin D physiology
- DiGeorge syndrome (immunology + congenital)
- Electrolytes/ECG changes (hypocalcemia → prolonged QT)
- Pseudohypoparathyroidism / Albright hereditary osteodystrophy (often near parathyroid disorders)
(Section titles can vary slightly by edition, but these are the consistent “anchors.”)
USMLE High-Yield Takeaways (Burn These In)
- Hypoparathyroidism labs: ↓ PTH, ↓ Ca, ↑ phosphate
- Symptoms/signs: perioral tingling, tetany, Chvostek, Trousseau
- ECG: prolonged QT
- Top cause tested: post-thyroidectomy
- If hypocalcemia won’t fix: check magnesium
- Chronic therapy often needs calcitriol (active vitamin D) + oral calcium
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
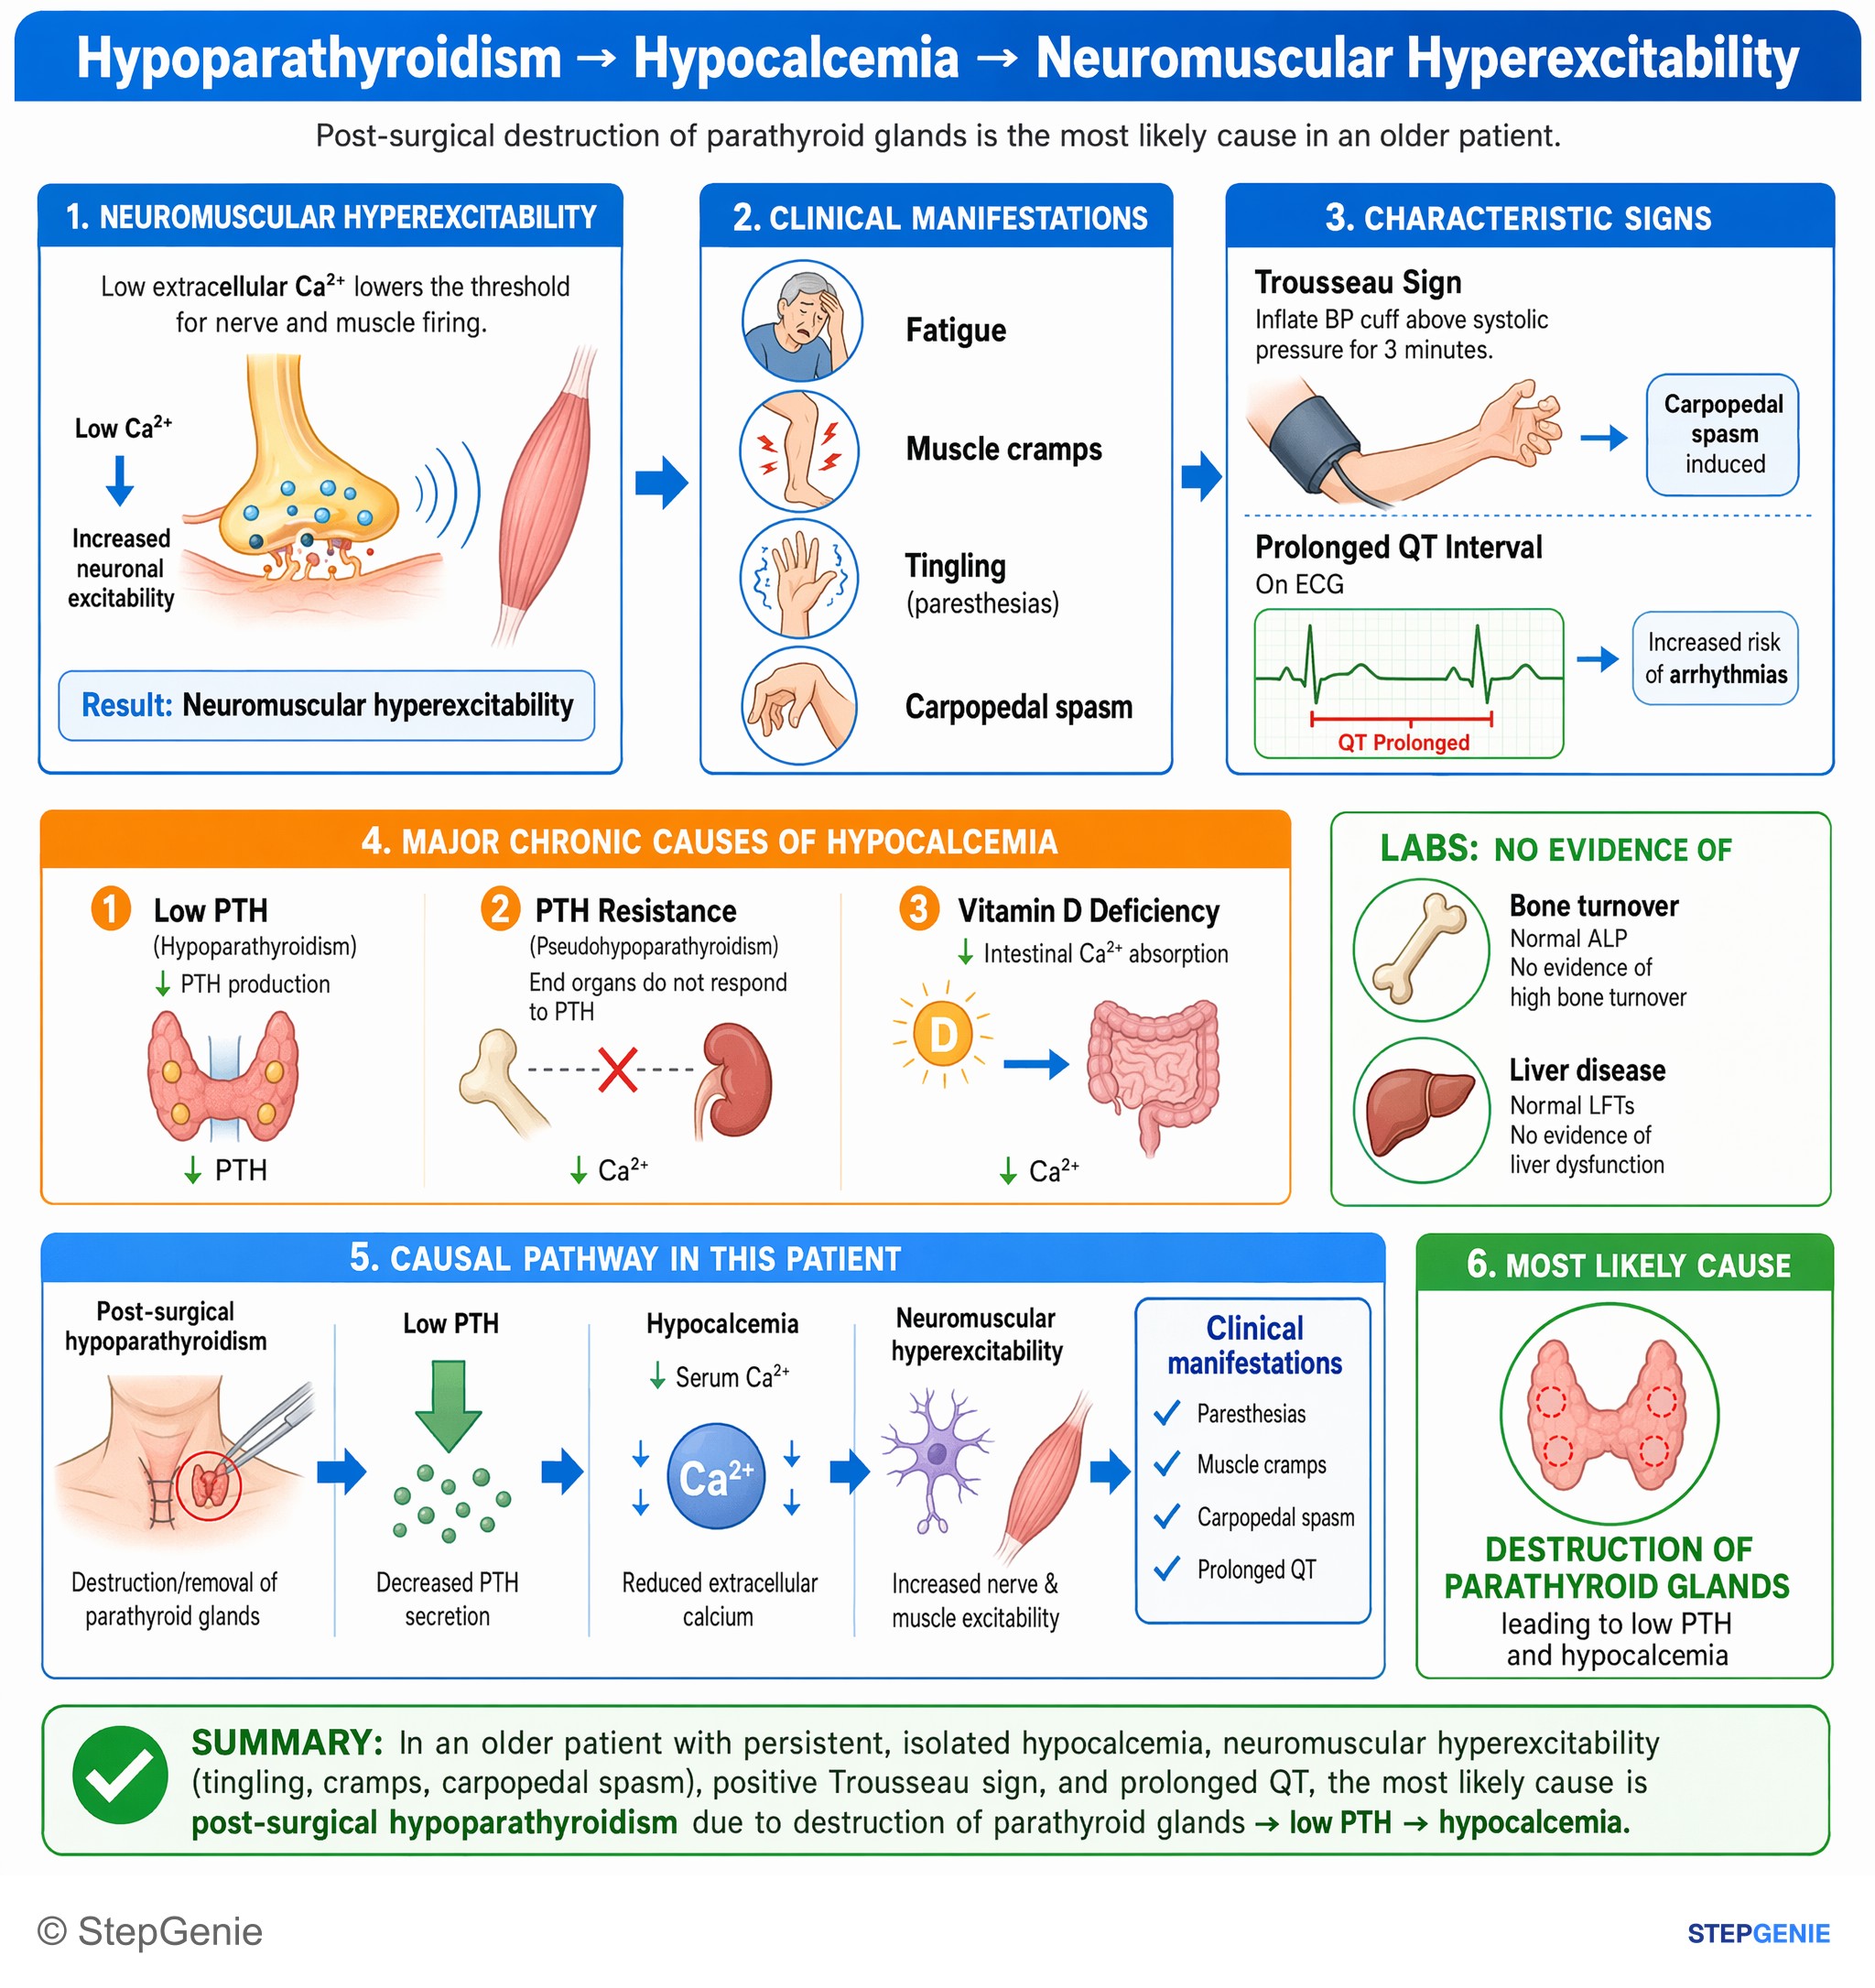
Post-surgical hypoparathyroidism → low PTH → hypocalcemia causing paresthesias, carpopedal spasm, prolonged QT in an older patient.
USMLE Step 1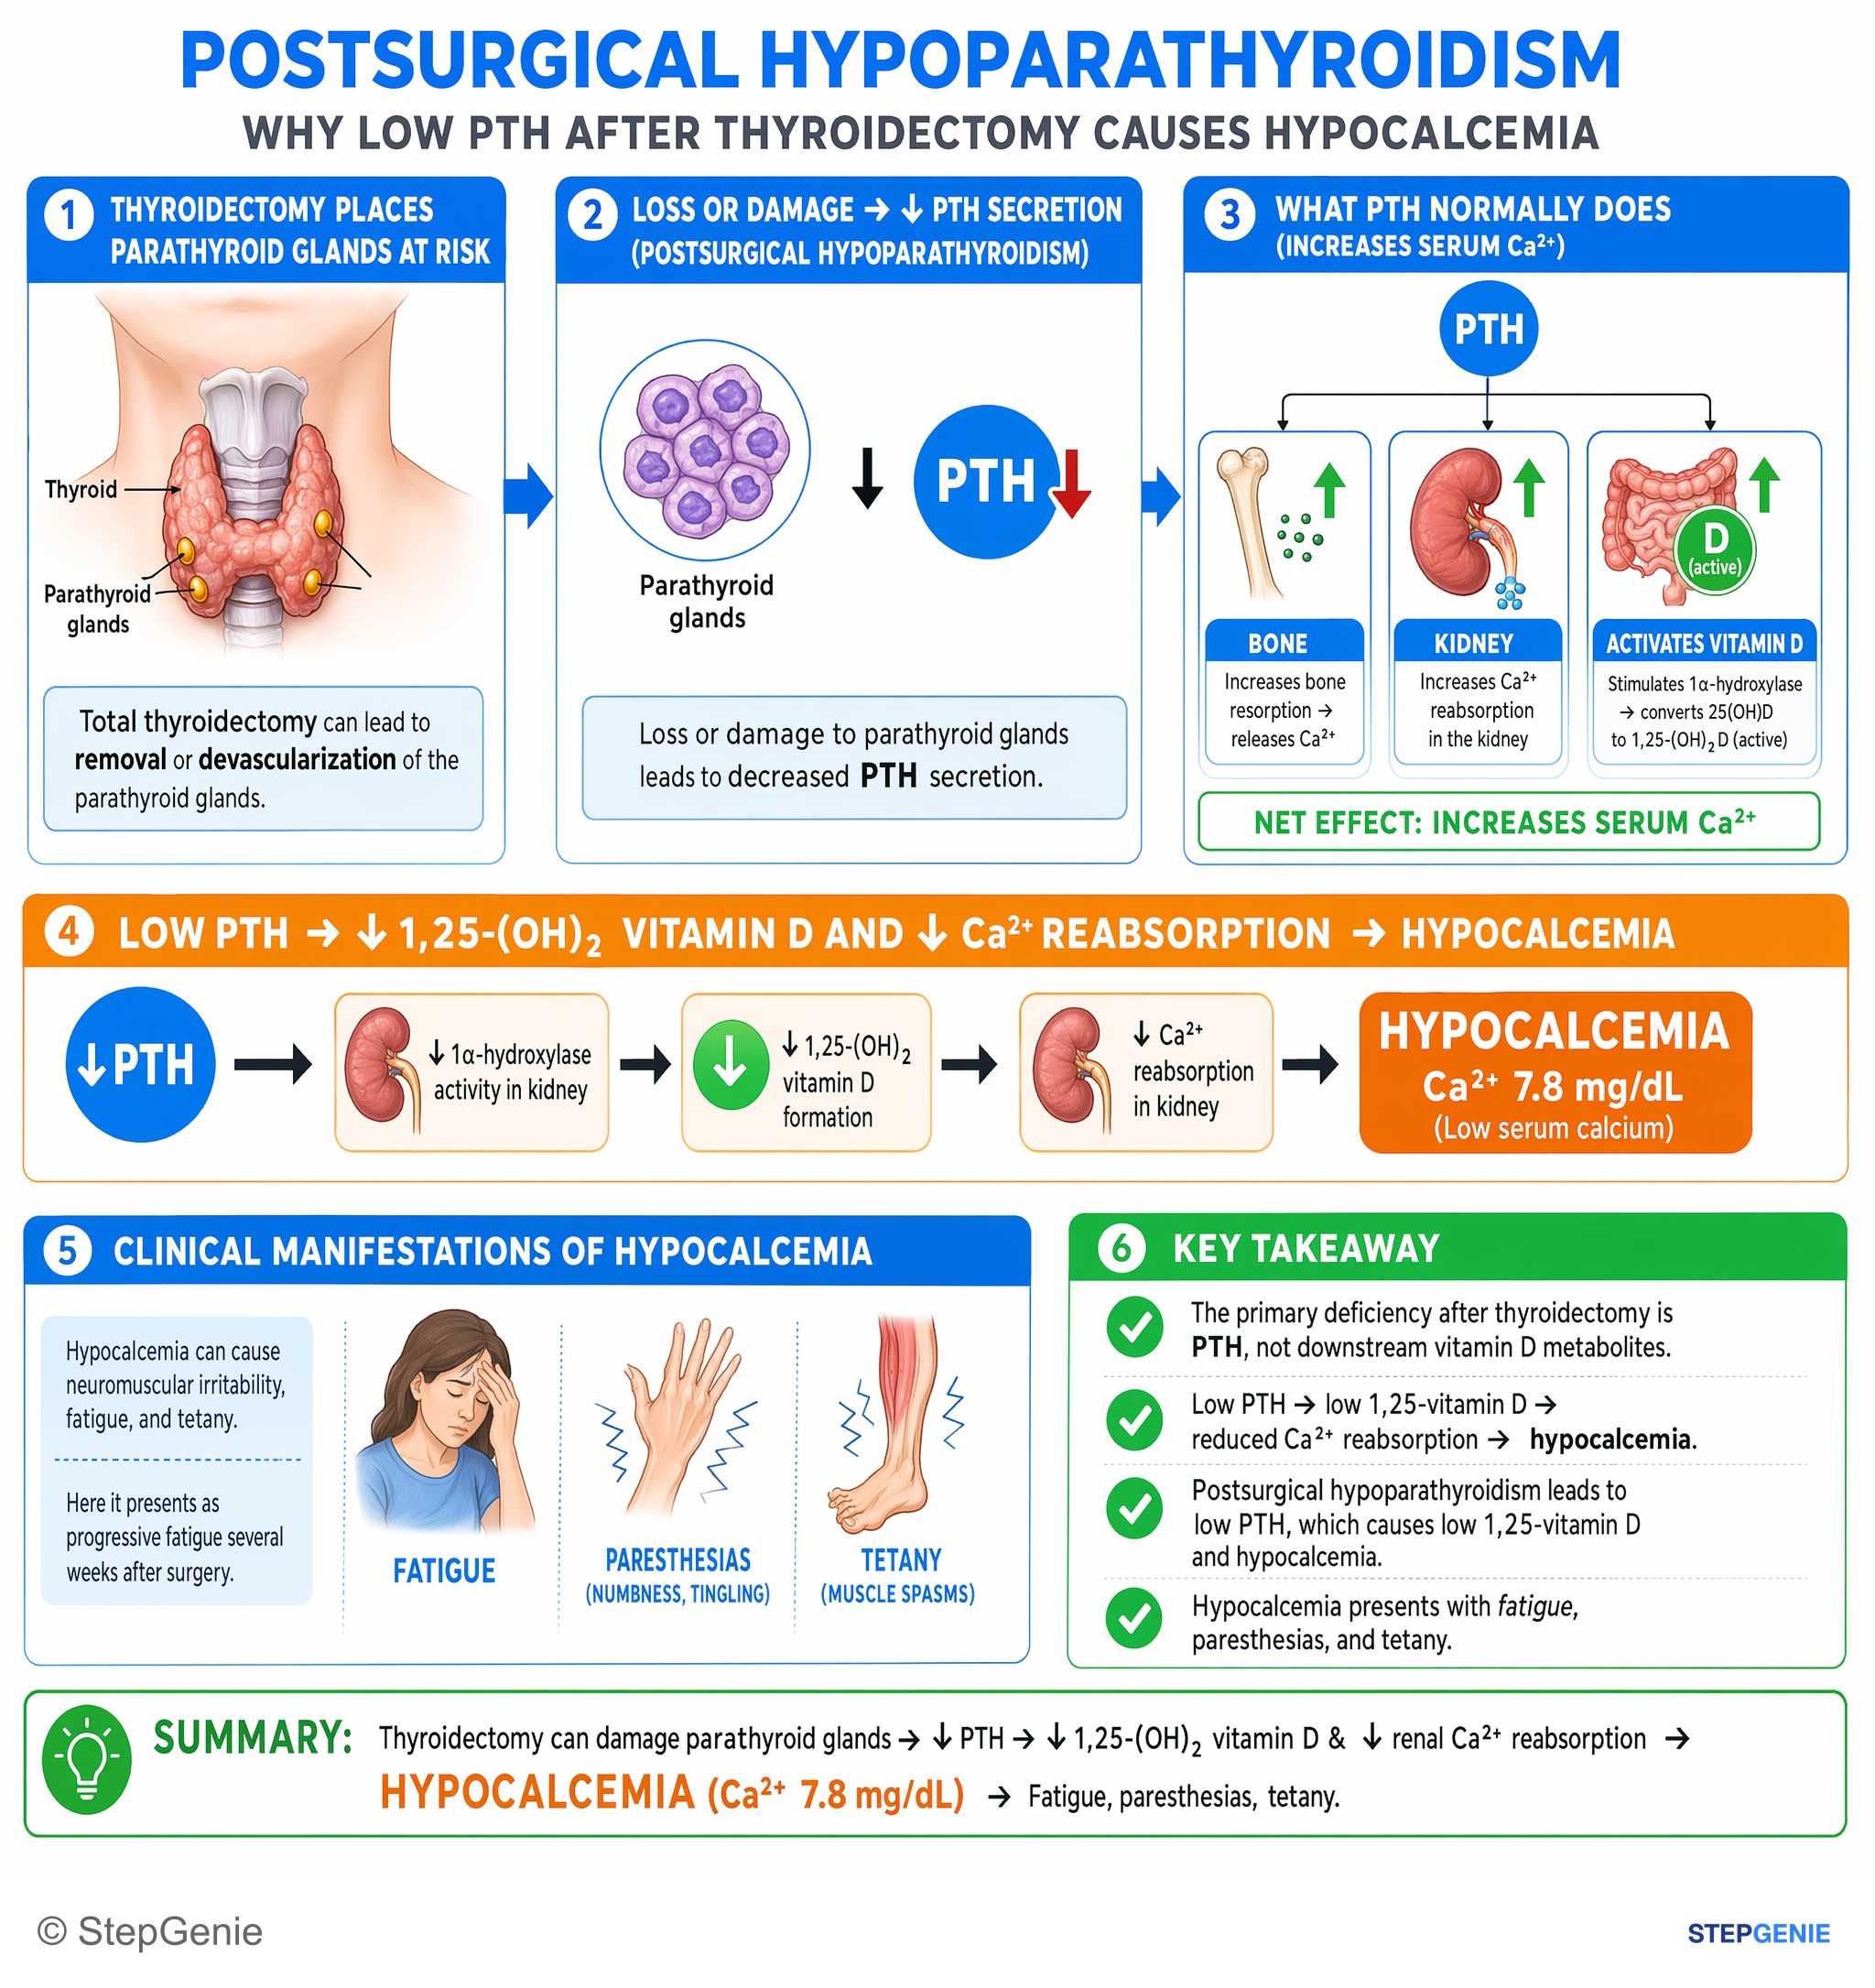
Postsurgical hypoparathyroidism after thyroidectomy → low PTH → low 1,25-vitamin D and hypocalcemia presenting with fatigue, paresthesias…
USMLE Step 1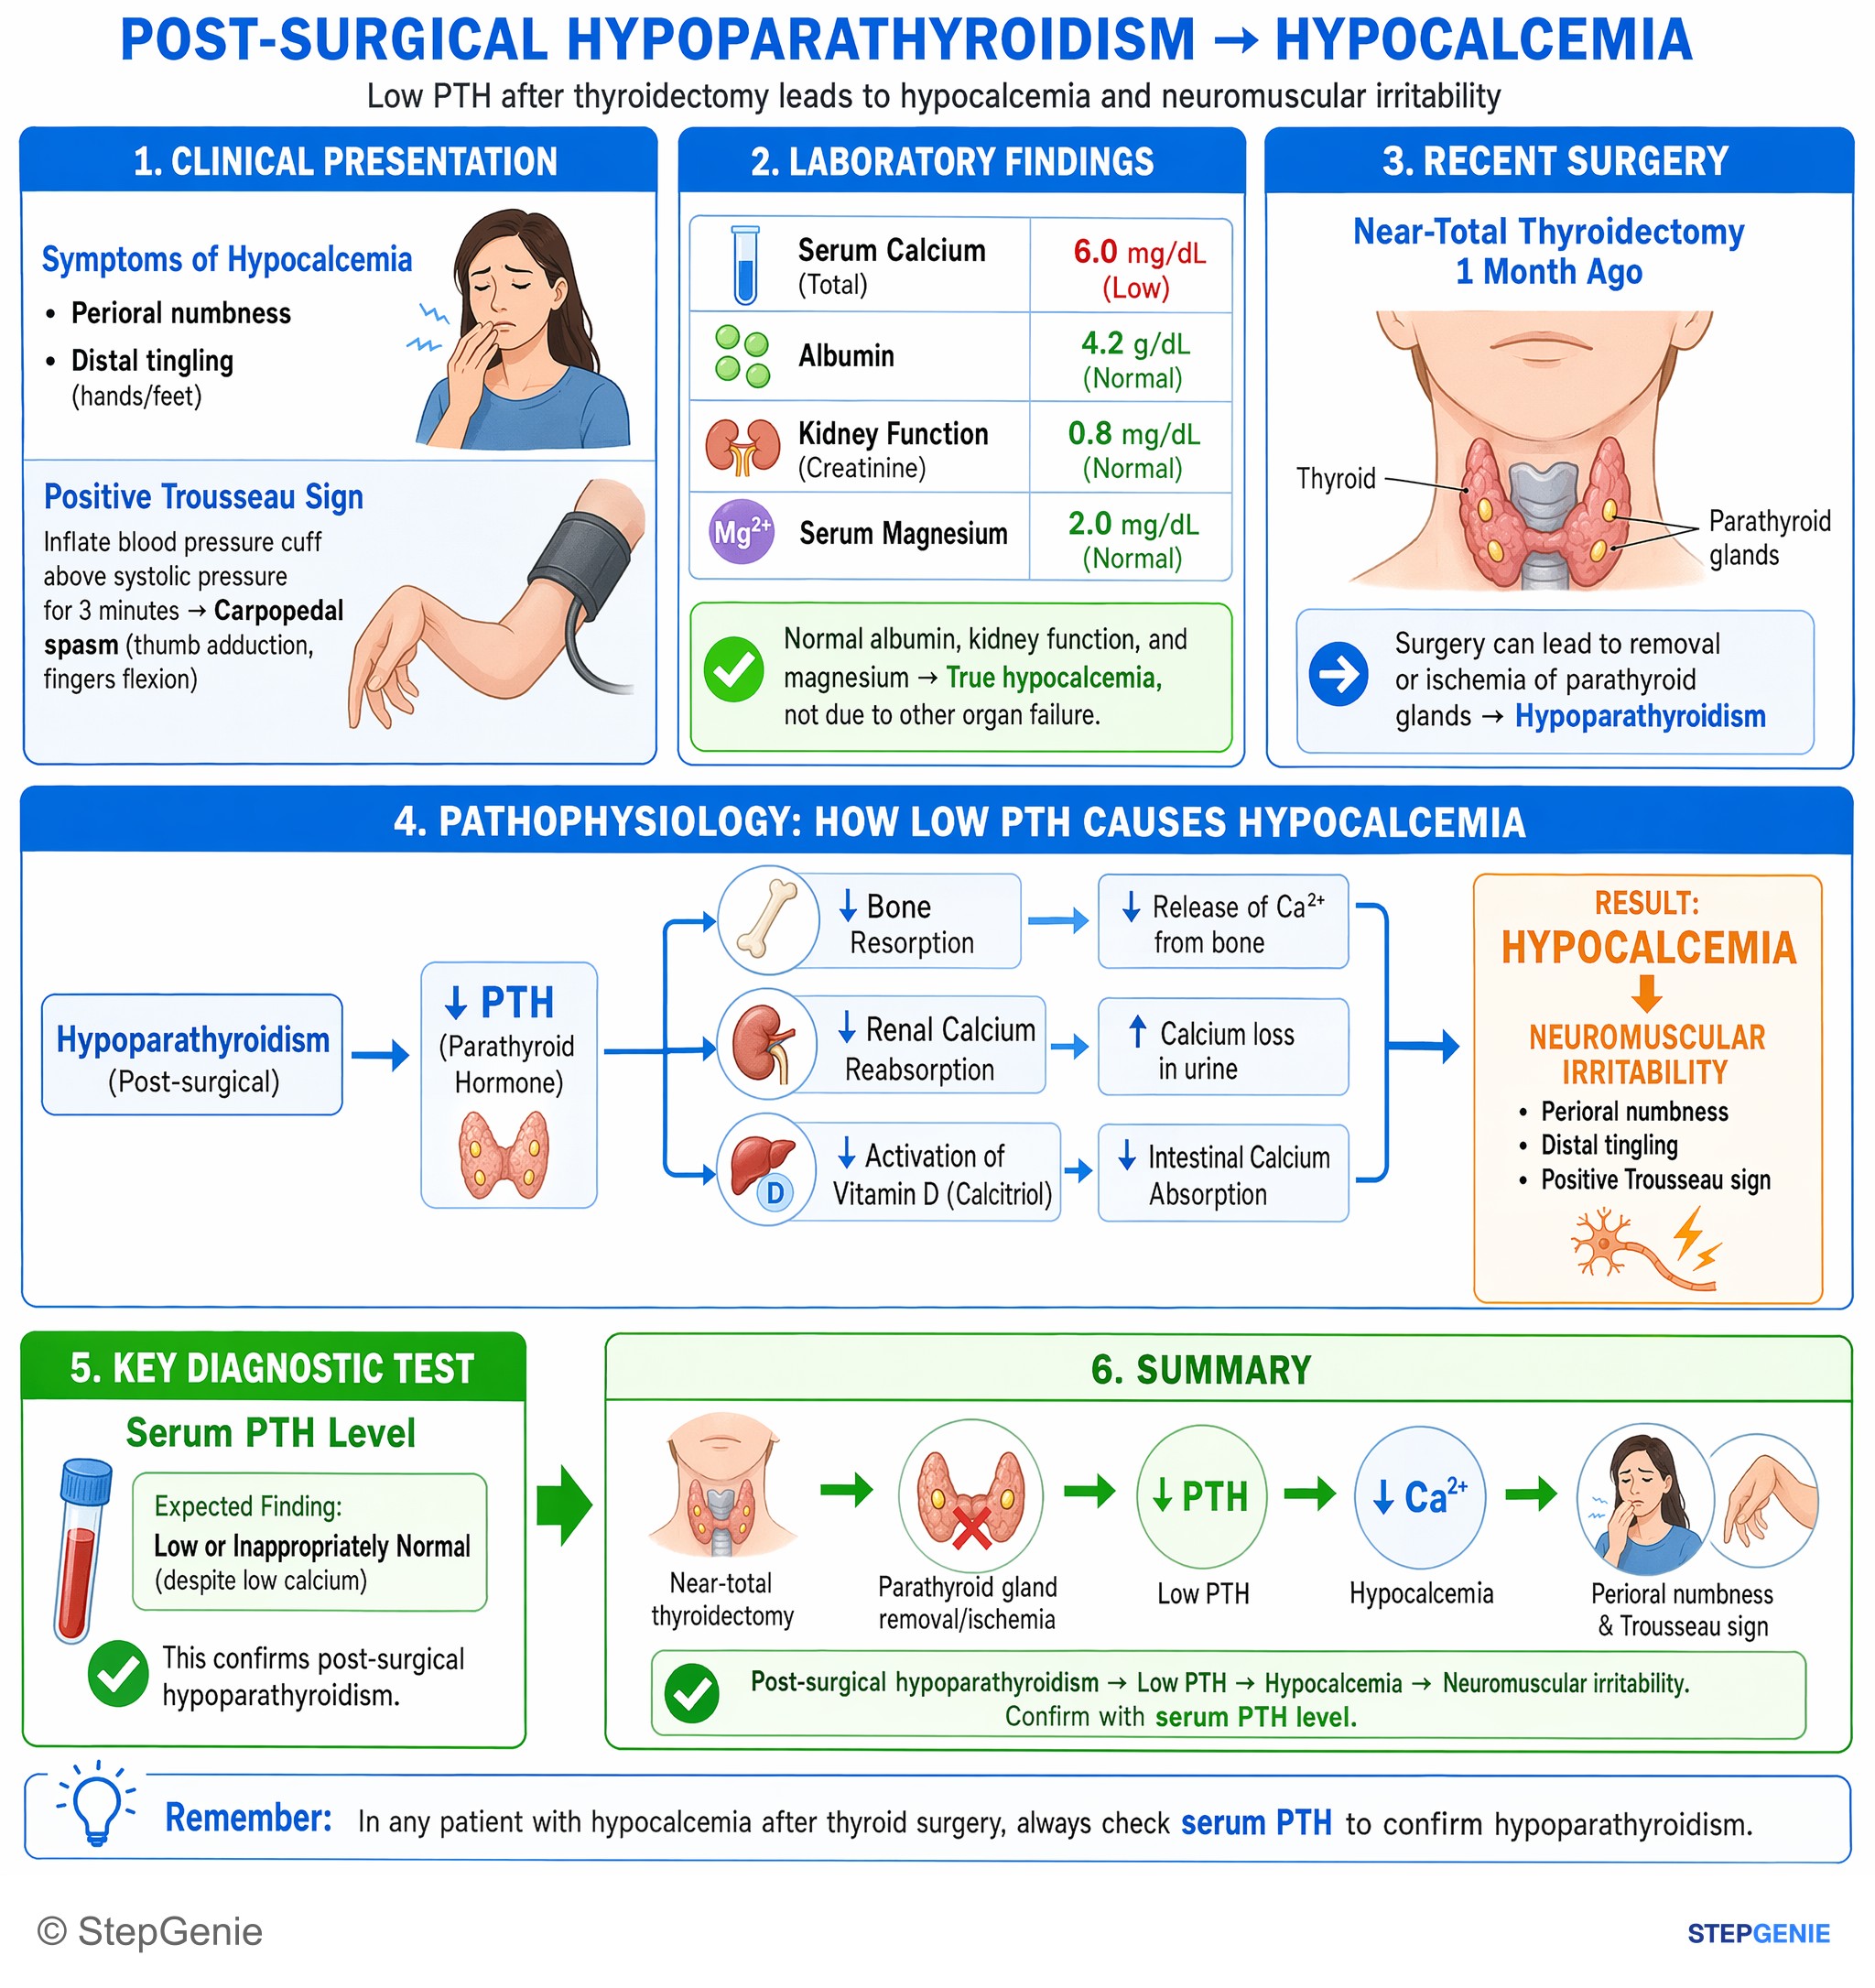
Post-surgical hypoparathyroidism after thyroidectomy → low PTH → hypocalcemia with perioral numbness, Trousseau sign; confirm with serum…
USMLE Step 2Frequently Asked Questions
What is the classic lab pattern in hypoparathyroidism?
The classic pattern is low PTH, low calcium, and high phosphate. This happens because PTH normally raises serum calcium, promotes phosphate excretion in the kidney, and increases calcitriol formation. When PTH is inappropriately low, calcium absorption and reabsorption fall, phosphate is retained, and calcitriol is often low as well.
Why does low PTH cause hypocalcemia and hyperphosphatemia?
Low PTH causes hypocalcemia and hyperphosphatemia because PTH normally increases calcium and lowers phosphate. Without enough PTH, the kidney reabsorbs less calcium, the proximal tubule no longer wastes phosphate, and renal 1α-hydroxylase activity falls. That lowers calcitriol, which reduces gastrointestinal calcium absorption, producing the net pattern of low calcium and high phosphate.
What are the most important clinical signs of hypoparathyroidism to recognize?
The key signs are neuromuscular irritability from hypocalcemia, especially tetany, Chvostek sign, and Trousseau sign. Patients may also have perioral tingling, muscle cramps, seizures if hypocalcemia is severe, and anxiety or irritability. A prolonged QT interval is another major clue, particularly in a post-thyroidectomy patient with low calcium symptoms.
How do you tell hypoparathyroidism from pseudohypoparathyroidism?
The main difference is the PTH level. In hypoparathyroidism, PTH is low, while in pseudohypoparathyroidism, PTH is high because the tissues are resistant to it. Both can show low calcium and high phosphate, so the distinction comes from recognizing whether the problem is true hormone deficiency or end-organ resistance.
What is the first-line treatment for symptomatic hypocalcemia in hypoparathyroidism?
Acute symptomatic hypocalcemia is treated first with IV calcium gluconate. This is used when patients have tetany, seizures, or arrhythmias. Magnesium should also be corrected if it is low, because severe hypomagnesemia can impair PTH secretion and cause resistance to PTH, making hypocalcemia hard to correct until magnesium is fixed.