You’re cruising through a question block and suddenly get hit with a child in shock, a scary rash, and labs that don’t make sense unless you remember one thing: sometimes the adrenal glands can catastrophically fail in a matter of hours. Waterhouse–Friderichsen syndrome is one of those “if you know it, you can’t miss it” diagnoses—and it’s a classic setup for distractors that look almost right.
Tag: Endocrine > Adrenal Disorders
The Clinical Vignette (Classic Q-bank Style)
A 7-year-old boy is brought to the ED with fever, vomiting, and lethargy. He became acutely worse over the last several hours. On exam, he is hypotensive, tachycardic, and confused. He has nonblanching petechiae and purpura on the trunk and lower extremities. Labs show:
- Na⁺: low
- K⁺: high
- Glucose: low
- Metabolic acidosis
Despite IV fluids, he remains hypotensive.
Question: What is the most likely underlying pathophysiology?
The Correct Answer: Waterhouse–Friderichsen Syndrome (WFS)
What it is
Waterhouse–Friderichsen syndrome = acute adrenal hemorrhage → acute primary adrenal insufficiency, most classically due to meningococcemia (Neisseria meningitidis) causing fulminant sepsis and disseminated intravascular coagulation (DIC).
Why it fits this vignette
This stem is screaming:
- Septic shock + petechiae/purpura → meningococcemia with DIC
- Persistent hypotension despite fluids → vasoplegic shock + loss of cortisol/aldosterone support
- Hyponatremia + hyperkalemia + hypoglycemia → primary adrenal insufficiency
- Acute deterioration → hemorrhagic infarction of adrenals (not a slow autoimmune process)
High-yield mechanism
In WFS, you get:
- DIC → hemorrhagic necrosis of adrenal glands
- Loss of:
- Cortisol → ↓ vascular responsiveness to catecholamines, hypoglycemia
- Aldosterone → salt wasting (↓ Na⁺), hyperkalemia, volume depletion
- Often accompanied by purpura fulminans (rapidly progressive thrombosis/skin necrosis) in severe meningococcemia.
Expected endocrine lab pattern (primary adrenal insufficiency)
| Hormone/Lab | Direction | Why |
|---|---|---|
| Cortisol | ↓ | adrenal destruction |
| Aldosterone | ↓ | adrenal cortex failure |
| ACTH | ↑ | loss of negative feedback |
| Renin | ↑ | hypovolemia/low perfusion |
| Na⁺ | ↓ | salt wasting |
| K⁺ | ↑ | impaired K⁺ secretion |
| Glucose | ↓ | impaired gluconeogenesis |
Immediate management (Step-relevant)
- Empiric IV antibiotics for meningococcemia (e.g., ceftriaxone/cefotaxime)
- Stress-dose steroids: IV hydrocortisone (covers glucocorticoid + some mineralocorticoid effect)
- Aggressive fluids, pressors as needed
- Manage DIC supportively
USMLE pearl: In shock refractory to fluids and pressors, think adrenal crisis and give steroids—don’t wait for confirmatory testing.
Why Every Answer Choice Matters: Systematic Distractor Breakdown
Below are the “usual suspects” you’ll see as alternatives. The key is to separate similar presentations (shock, hyperpigmentation, electrolyte changes, fever) by timing, rash, electrolytes, and hormone patterns.
Distractor 1: Autoimmune Addison Disease (21-hydroxylase autoantibodies)
Why it tempts you: Also causes primary adrenal insufficiency → hyponatremia, hyperkalemia, hypotension.
Why it’s wrong here:
- Time course is typically chronic/insidious, not hours.
- Often has hyperpigmentation (high ACTH → MSH activity) and nonspecific symptoms (weight loss, fatigue, abdominal pain).
- No classic association with purpura fulminans or meningococcemia.
When it’s right: Middle-aged patient with chronic fatigue, weight loss, hypotension, hyperpigmentation, and autoimmune history (e.g., thyroid disease, T1DM).
Distractor 2: Secondary Adrenal Insufficiency (pituitary failure, chronic steroids)
Why it tempts you: Hypotension, fatigue, low cortisol.
Why it’s wrong here (high-yield difference):
- Secondary AI has low ACTH → no hyperpigmentation
- Aldosterone is usually normal (regulated mainly by RAAS, not ACTH)
- So hyperkalemia is not typical
- Rash and meningococcemia picture doesn’t fit.
Quick rule:
- Primary AI → ↓ cortisol, ↓ aldosterone → ↑ K⁺
- Secondary/Tertiary AI → ↓ cortisol only → K⁺ usually normal
Distractor 3: Congenital Adrenal Hyperplasia (21-hydroxylase deficiency)
Why it tempts you: Can cause salt wasting → hypotension, hyponatremia, hyperkalemia.
Why it’s wrong here:
- Usually presents in infancy with vomiting, dehydration, and possibly ambiguous genitalia in XX or precocious virilization.
- Not associated with petechiae/purpura or septic shock.
- Hypoglycemia is less central than in adrenal crisis from hemorrhage; fever/rash points away.
High-yield tie-in:
21-hydroxylase deficiency → ↓ cortisol, ↓ aldosterone, ↑ androgens → hypertension is NOT present (that’s 11β-hydroxylase).
Distractor 4: Pheochromocytoma
Why it tempts you: “Adrenal” diagnosis + can cause severe symptoms.
Why it’s wrong here:
- Pheo causes episodic headaches, palpitations, diaphoresis, and hypertension (not hypotension).
- Electrolytes (Na⁺/K⁺) don’t match.
- Rash + DIC + fever points hard toward meningococcemia.
High-yield clue: Pheo classically associated with MEN2 (RET), VHL, NF1; diagnosed via plasma free metanephrines.
Distractor 5: Cushing Syndrome (excess cortisol)
Why it tempts you: Another adrenal buzzword.
Why it’s wrong here:
- Cushing causes hypertension, hyperglycemia, weight gain, proximal muscle weakness, easy bruising—but not acute shock.
- Cortisol excess does the opposite of hypoglycemia.
High-yield pearl: Exogenous steroids suppress ACTH → adrenal atrophy; stopping them abruptly can cause tertiary adrenal insufficiency, but still no hyperkalemia and no DIC rash.
Distractor 6: Central Diabetes Insipidus (pituitary/hypothalamus)
Why it tempts you: “Endocrine emergency” + altered mental status.
Why it’s wrong here:
- DI causes hypernatremia (free water loss), polyuria, polydipsia.
- This vignette is hyponatremia + hyperkalemia + shock + rash—not a water balance problem.
Distractor 7: Septic shock without adrenal hemorrhage
Why it tempts you: The patient is septic and hypotensive—fair.
Why it’s incomplete:
Sepsis alone can explain hypotension, but the vignette gives you primary adrenal insufficiency labs:
- Hyperkalemia is the big tell (points to aldosterone deficiency)
- Hypoglycemia and refractory hypotension strengthen adrenal crisis
Test-writer move: If they add electrolyte patterns of primary AI, they want you to connect sepsis → DIC → adrenal hemorrhage.
Rapid-Fire High-Yield Summary (What to Memorize)
Waterhouse–Friderichsen Syndrome
- Cause: Meningococcemia → DIC → bilateral adrenal hemorrhage
- Findings: Fever, shock, petechiae/purpura, refractory hypotension
- Labs: ↓ Na⁺, ↑ K⁺, ↓ glucose, metabolic acidosis; ↓ cortisol/aldosterone, ↑ ACTH/renin
- Tx: Immediate antibiotics + stress-dose hydrocortisone + resuscitation
Primary vs Secondary Adrenal Insufficiency (fast differentiator)
| Feature | Primary (Addison/WFS) | Secondary/Tertiary |
|---|---|---|
| ACTH | ↑ | ↓ |
| Aldosterone | ↓ | Normal |
| K⁺ | ↑ | Normal |
| Hyperpigmentation | Yes | No |
One Last Test-Day Tip
If you see shock + purpura and the question is in the Endocrine/Adrenal neighborhood, don’t overthink it: meningococcemia can destroy the adrenals fast, and the exam loves that connection.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
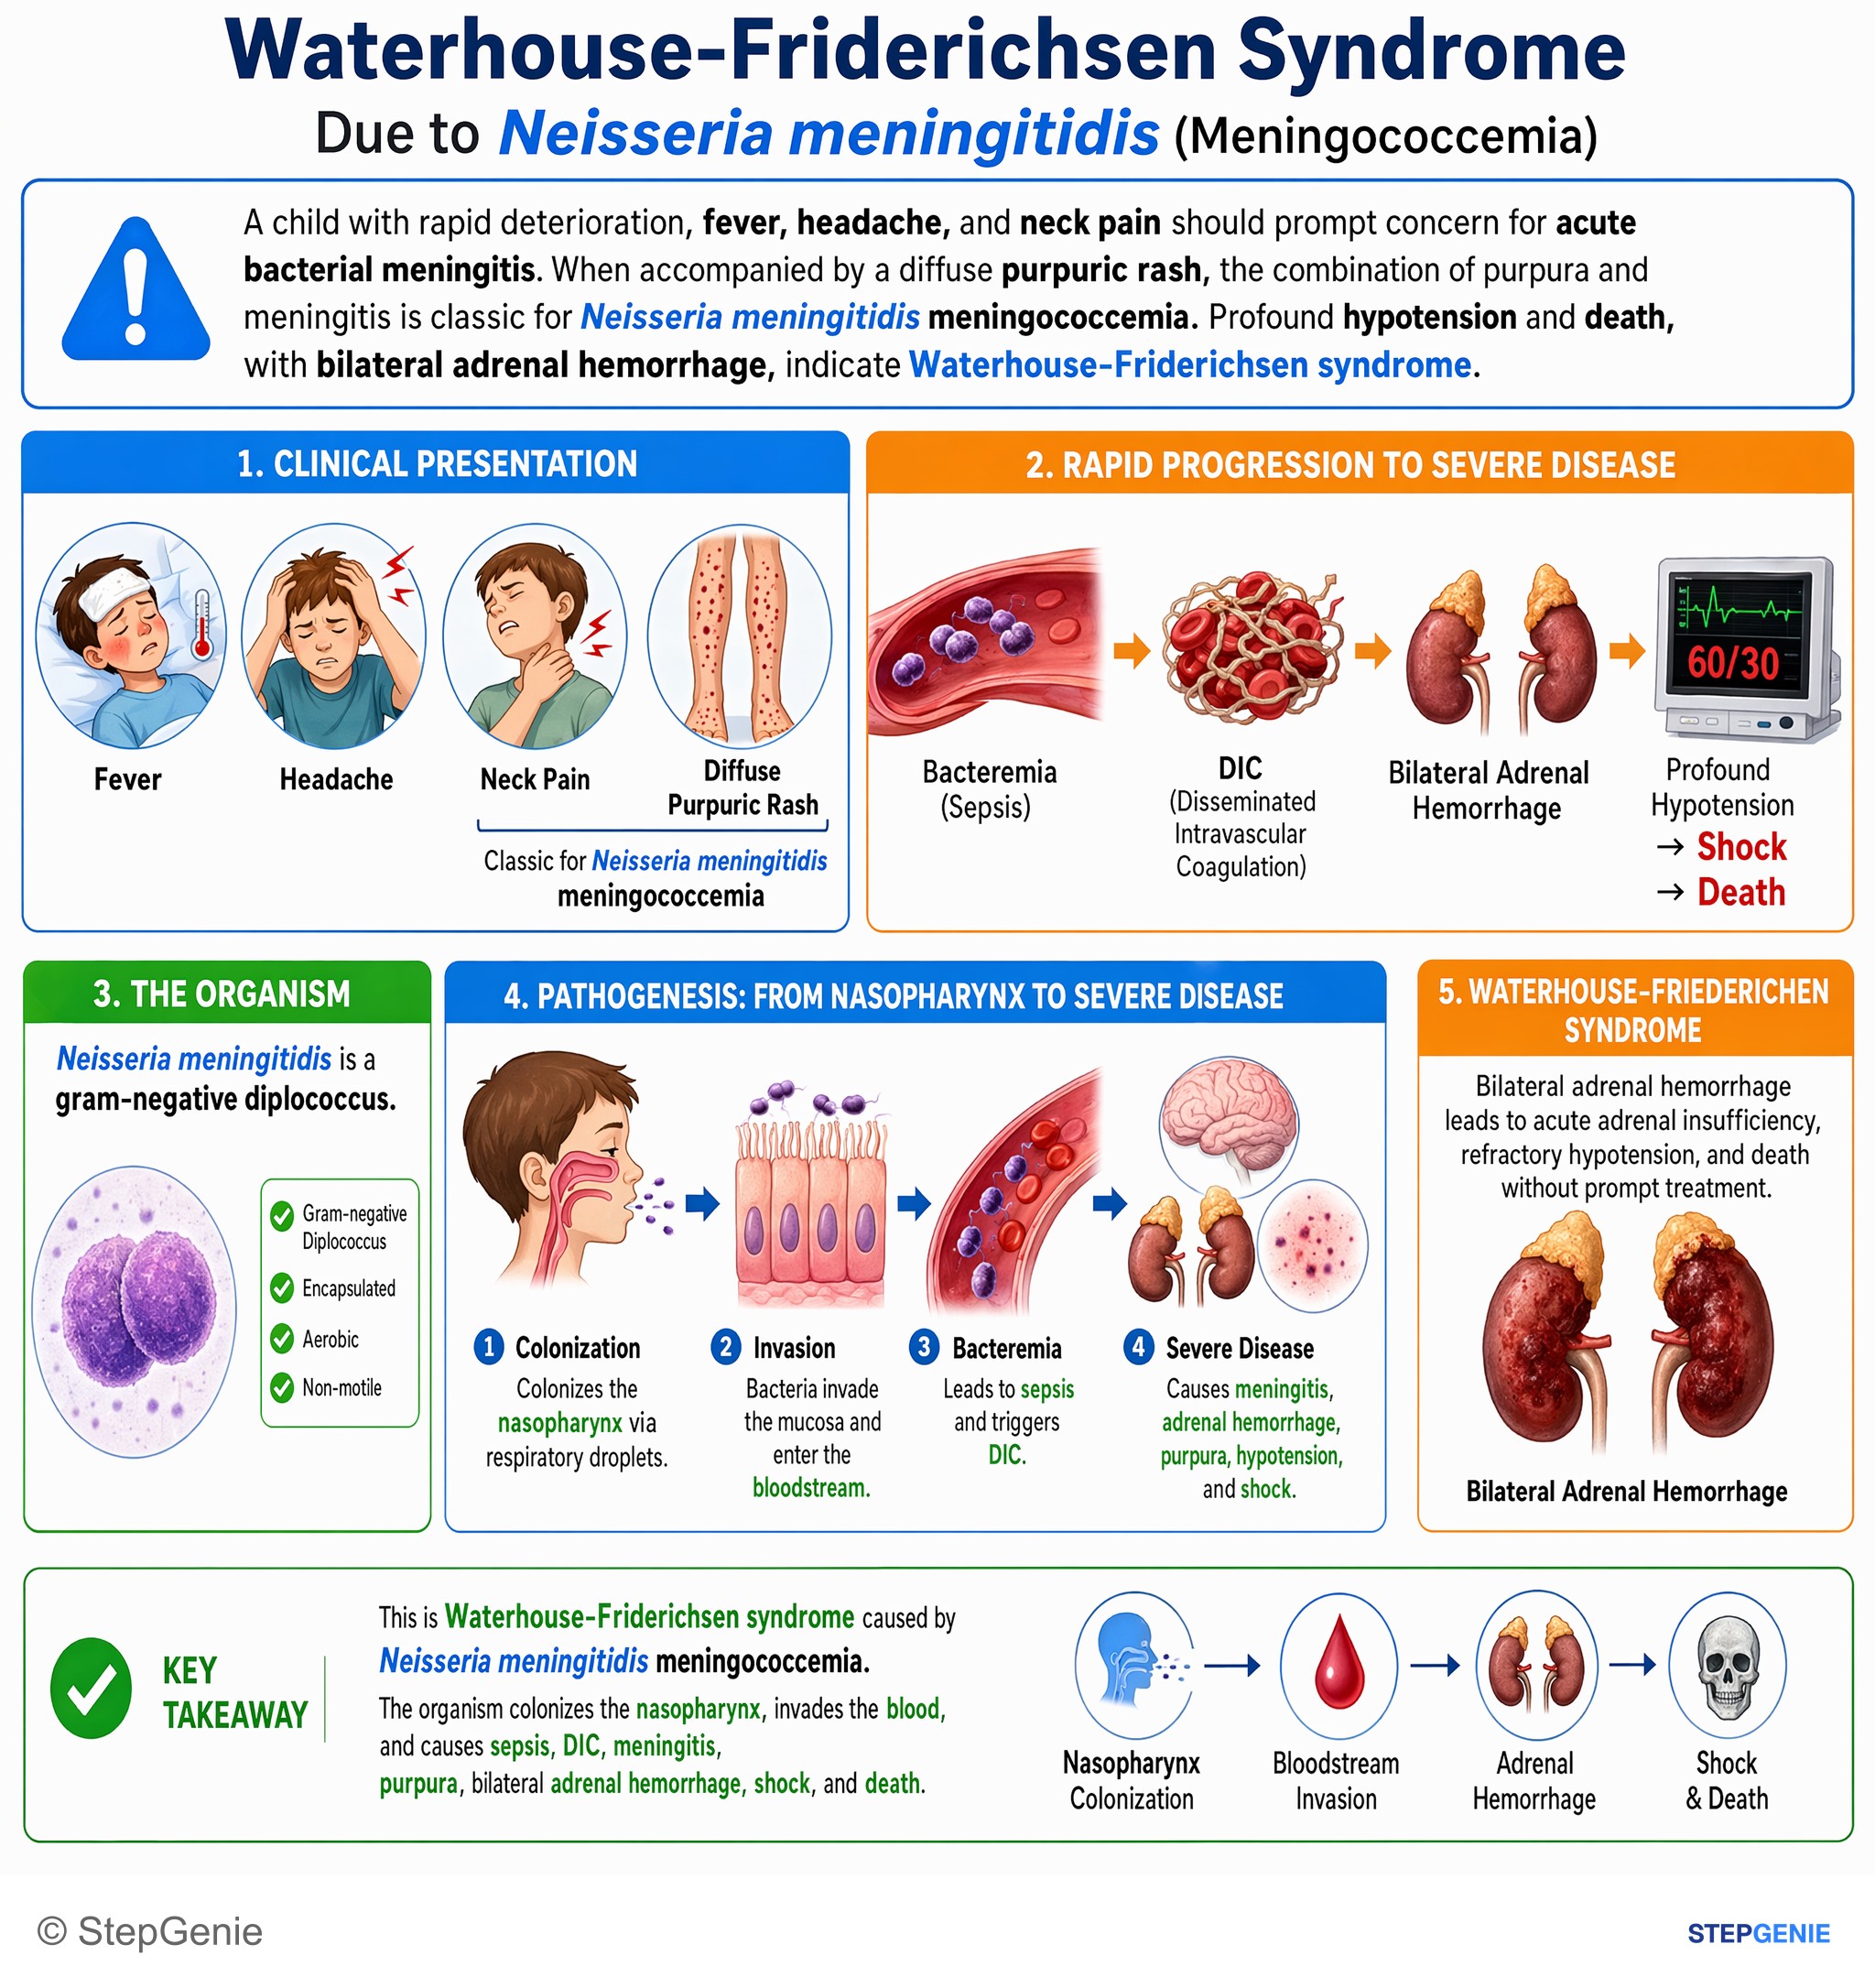
Waterhouse-Friderichsen syndrome from Neisseria meningitidis meningococcemia; organism colonizes nasopharynx, invades blood → adrenal…
USMLE Step 1Frequently Asked Questions
Why does Waterhouse-Friderichsen syndrome cause hyponatremia, hyperkalemia, and hypoglycemia?
It causes acute primary adrenal insufficiency from adrenal hemorrhage. Loss of aldosterone leads to salt wasting with low sodium, impaired potassium secretion with high potassium, and volume depletion. Loss of cortisol reduces gluconeogenesis, causing hypoglycemia, and also decreases vascular responsiveness to catecholamines, which contributes to severe hypotension.
How do you recognize Waterhouse-Friderichsen syndrome in a question stem?
Look for a child with fulminant sepsis, shock, and a nonblanching petechial or purpuric rash plus electrolyte findings of primary adrenal insufficiency. The classic picture is meningococcemia with disseminated intravascular coagulation, persistent hypotension despite fluids, acute deterioration over hours, and labs showing low sodium, high potassium, low glucose, and metabolic acidosis.
How do you tell Waterhouse-Friderichsen syndrome from autoimmune Addison disease?
The key difference is timing and clinical context. Waterhouse-Friderichsen syndrome presents abruptly over hours with septic shock, petechiae or purpura, and adrenal hemorrhagic infarction, classically from meningococcemia with DIC. Autoimmune Addison disease is typically chronic and insidious, often with fatigue, weight loss, abdominal pain, hypotension, hyperpigmentation, and autoimmune history rather than a fulminant rash.
How do you distinguish primary adrenal insufficiency from secondary adrenal insufficiency on labs?
Primary adrenal insufficiency shows low cortisol and low aldosterone, so hyperkalemia is typical along with hyponatremia and hypotension. Secondary adrenal insufficiency has low cortisol from low ACTH, but aldosterone is usually normal because it is mainly regulated by the renin-angiotensin-aldosterone system, so potassium is usually normal and hyperkalemia is not typical.
What is the immediate treatment for suspected Waterhouse-Friderichsen syndrome?
Start empiric IV antibiotics and give stress-dose IV hydrocortisone immediately, along with aggressive fluids and pressors as needed. The syndrome is classically linked to meningococcemia, so antibiotics such as ceftriaxone or cefotaxime are used, and hydrocortisone is important because it provides glucocorticoid effects plus some mineralocorticoid support in adrenal crisis.