You’re in the middle of a q-bank set, you see “polyuria, polydipsia,” and your brain auto-fills “diabetes.” But Step-style questions aren’t testing whether you can name the disease—they’re testing whether you can prove it, and (more importantly) eliminate every tempting distractor. Type 1 vs Type 2 diabetes mellitus is one of the highest-yield places where that skill pays off.
Tag: Endocrine > Diabetes Mellitus
The Vignette (Classic, But With Traps)
A 17-year-old boy is brought to the ED for 2 days of nausea and abdominal pain. Over the past 3 weeks, he has had increased thirst and frequent urination. His mother says he has been “losing weight despite eating all the time.” He is tachypneic with deep, rapid respirations. Labs:
- Glucose: 520 mg/dL
- Arterial pH: 7.18
- Serum bicarbonate: 10 mEq/L
- Serum ketones: positive
- Potassium: 5.6 mEq/L
- HbA1c: 11.2%
Question: Which of the following best explains the underlying pathophysiology?
Answer choices
A. Autoimmune destruction of pancreatic cells leading to absolute insulin deficiency
B. Peripheral insulin resistance with compensatory hyperinsulinemia early in disease course
C. Activating mutation of the insulin receptor causing increased glucose uptake
D. Destruction of pancreatic cells leading to decreased glucagon secretion
E. Excess cortisol causing increased hepatic gluconeogenesis
Step-by-Step: Identify the Diagnosis Before You Pick the Mechanism
This patient has diabetic ketoacidosis (DKA):
- Hyperglycemia (520)
- High anion gap metabolic acidosis (pH 7.18, HCO₃⁻ 10)
- Ketones positive
- Kussmaul respirations (deep, rapid breathing)
- Weight loss + teen + rapid onset → points hard toward Type 1 DM
So the correct mechanism should explain absolute insulin deficiency and unopposed counterregulatory hormones → ketogenesis.
Correct Answer: A — Autoimmune Destruction of Cells
Why A is correct
Type 1 DM is caused by autoimmune-mediated destruction of pancreatic cells, leading to absolute insulin deficiency.
High-yield T1DM facts (Step 1 + Step 2):
- Associated with HLA-DR3 and HLA-DR4
- Autoantibodies you should recognize:
- Anti-GAD65
- Anti-islet cell
- Anti-insulin
- Histology: insulitis (lymphocytic infiltration of islets)
- Low C-peptide (endogenous insulin production is low)
- Patients are prone to DKA because low insulin → increased lipolysis → ketone production
The core physiology
Insulin normally:
- Promotes glucose uptake (especially in muscle/adipose via GLUT4)
- Inhibits lipolysis and ketogenesis
In T1DM:
- No insulin → increased hormone-sensitive lipase activity → free fatty acids → hepatic ketogenesis
- Counterregulatory hormones (glucagon, epinephrine, cortisol, GH) amplify hyperglycemia and ketones
Why Each Distractor Is Wrong (And What It’s Trying to Test)
B. Peripheral insulin resistance with compensatory hyperinsulinemia early
This describes Type 2 DM, especially early on:
- Insulin resistance (muscle/adipose/liver) → pancreas compensates with increased insulin
- Over time: -cell dysfunction → relative insulin deficiency
Why it’s wrong here:
- The vignette screams DKA + lean teen + rapid onset → T1DM is far more likely
- DKA is uncommon in classic T2DM (though it can occur, especially with stress or SGLT2 inhibitors—more on that later)
High-yield contrast:
- T2DM: high/normal C-peptide early, acanthosis nigricans, metabolic syndrome, obesity, gradual onset
- T1DM: low C-peptide, autoimmune, acute onset, DKA risk
C. Activating mutation of the insulin receptor causing increased glucose uptake
An “activating mutation” would cause hypoglycemia, not hyperglycemia. If insulin signaling is enhanced, tissues take up more glucose and suppress hepatic glucose output.
What this distractor is testing:
- Directionality of insulin receptor signaling
- Recognizing that many receptor problems in real life are loss-of-function (insulin resistance), not activating
Related high-yield concept:
Rare syndromes of severe insulin resistance (e.g., insulin receptor abnormalities) cause hyperglycemia, not increased uptake.
D. Destruction of pancreatic cells leading to decreased glucagon secretion
Glucagon is elevated in DKA physiology (or functionally “unopposed”) and contributes to:
- Increased hepatic gluconeogenesis and glycogenolysis
- Increased ketogenesis (via promoting fatty acid oxidation)
Why it’s wrong here:
- DKA requires too much glucagon effect relative to insulin, not too little
- Decreased glucagon would generally make hypoglycemia more likely (and reduce ketone formation)
High-yield pairing:
DKA pathogenesis is often summarized as:
- insulin + glucagon → ketones
E. Excess cortisol causing increased hepatic gluconeogenesis
Cortisol increases gluconeogenesis and contributes to insulin resistance, so this can cause hyperglycemia (think Cushing syndrome or chronic steroid use).
Why it’s wrong here:
- Cortisol excess doesn’t typically cause DKA with positive ketones and severe metabolic acidosis
- The vignette’s age, rapid onset, weight loss, and Kussmaul breathing fits T1DM with DKA far better
How Step might test cortisol instead:
- Central obesity, proximal muscle weakness, purple striae, hypertension, osteoporosis
- Hyperglycemia without prominent ketosis
Rapid-Fire: Type 1 vs Type 2 — The “Prove It” Table
| Feature | Type 1 DM | Type 2 DM |
|---|---|---|
| Pathogenesis | Autoimmune -cell destruction | Insulin resistance + progressive -cell dysfunction |
| Insulin level | Low/absent | High early → low late |
| C-peptide | Low | Normal/high early |
| Body habitus | Often lean (not always) | Often overweight/obese |
| Onset | Abrupt | Gradual |
| DKA risk | High | Low (but possible) |
| Autoantibodies | Present (anti-GAD, etc.) | Absent |
| Typical acute crisis | DKA | HHS |
The Acid–Base + Potassium Pitfall (Classic USMLE Move)
This patient’s potassium is 5.6 mEq/L, which looks high—yet total body potassium is depleted in DKA.
Why serum K⁺ is high in DKA
- Insulin normally drives K⁺ into cells → without insulin, K⁺ shifts out
- Acidosis drives H⁺ into cells and K⁺ out (complex but testable)
Why you still replace K⁺ during treatment
Once you give insulin and fluids, K⁺ shifts back into cells → potassium can crash and cause arrhythmias.
High-yield treatment sequence (DKA):
- IV fluids
- Potassium assessment/repletion (if low, replete before insulin)
- Insulin
- Add dextrose to fluids once glucose falls (to keep insulin running and clear ketones)
Common “Twist” Facts That Show Up in Answer Choices
1) DKA vs HHS
- DKA: ketones + acidosis, more common in T1DM
- HHS: very high glucose (often >600), high serum osmolality, dehydration, minimal ketosis, typically T2DM
2) SGLT2 inhibitors can blur the picture
SGLT2 inhibitors (e.g., canagliflozin, empagliflozin) can cause euglycemic DKA:
- DKA physiology but glucose not as high as expected
If the stem mentions an SGLT2 inhibitor, don’t let “only mildly elevated glucose” throw you.
3) MODY and LADA as “third options”
- MODY: young, non-obese, strong family history, impaired insulin secretion (often glucokinase or transcription factor mutations), no autoantibodies
- LADA: autoimmune diabetes in adults → looks like T2DM initially but progresses to insulin dependence
Your Q-Bank Mindset: How to Eliminate Distractors Fast
When the question is Type 1 vs Type 2, ask:
-
Is there ketosis/acidosis?
- If yes, think “absolute insulin deficiency” until proven otherwise.
-
What is the tempo + body habitus + age?
- Rapid onset + weight loss + younger → T1DM
- Gradual + metabolic syndrome → T2DM
-
Does the answer choice match the mechanism and the presentation?
- Cortisol explains hyperglycemia, but not classic DKA
- “Increased glucose uptake” can’t cause hyperglycemia
Take-Home Points (High Yield)
- T1DM = autoimmune -cell destruction → absolute insulin deficiency → DKA risk
- T2DM = insulin resistance → hyperinsulinemia early; DKA uncommon
- In DKA, serum K⁺ may be high, but total body K⁺ is low
- Always match answer choices to both mechanism and clinical context—that’s where points come from
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
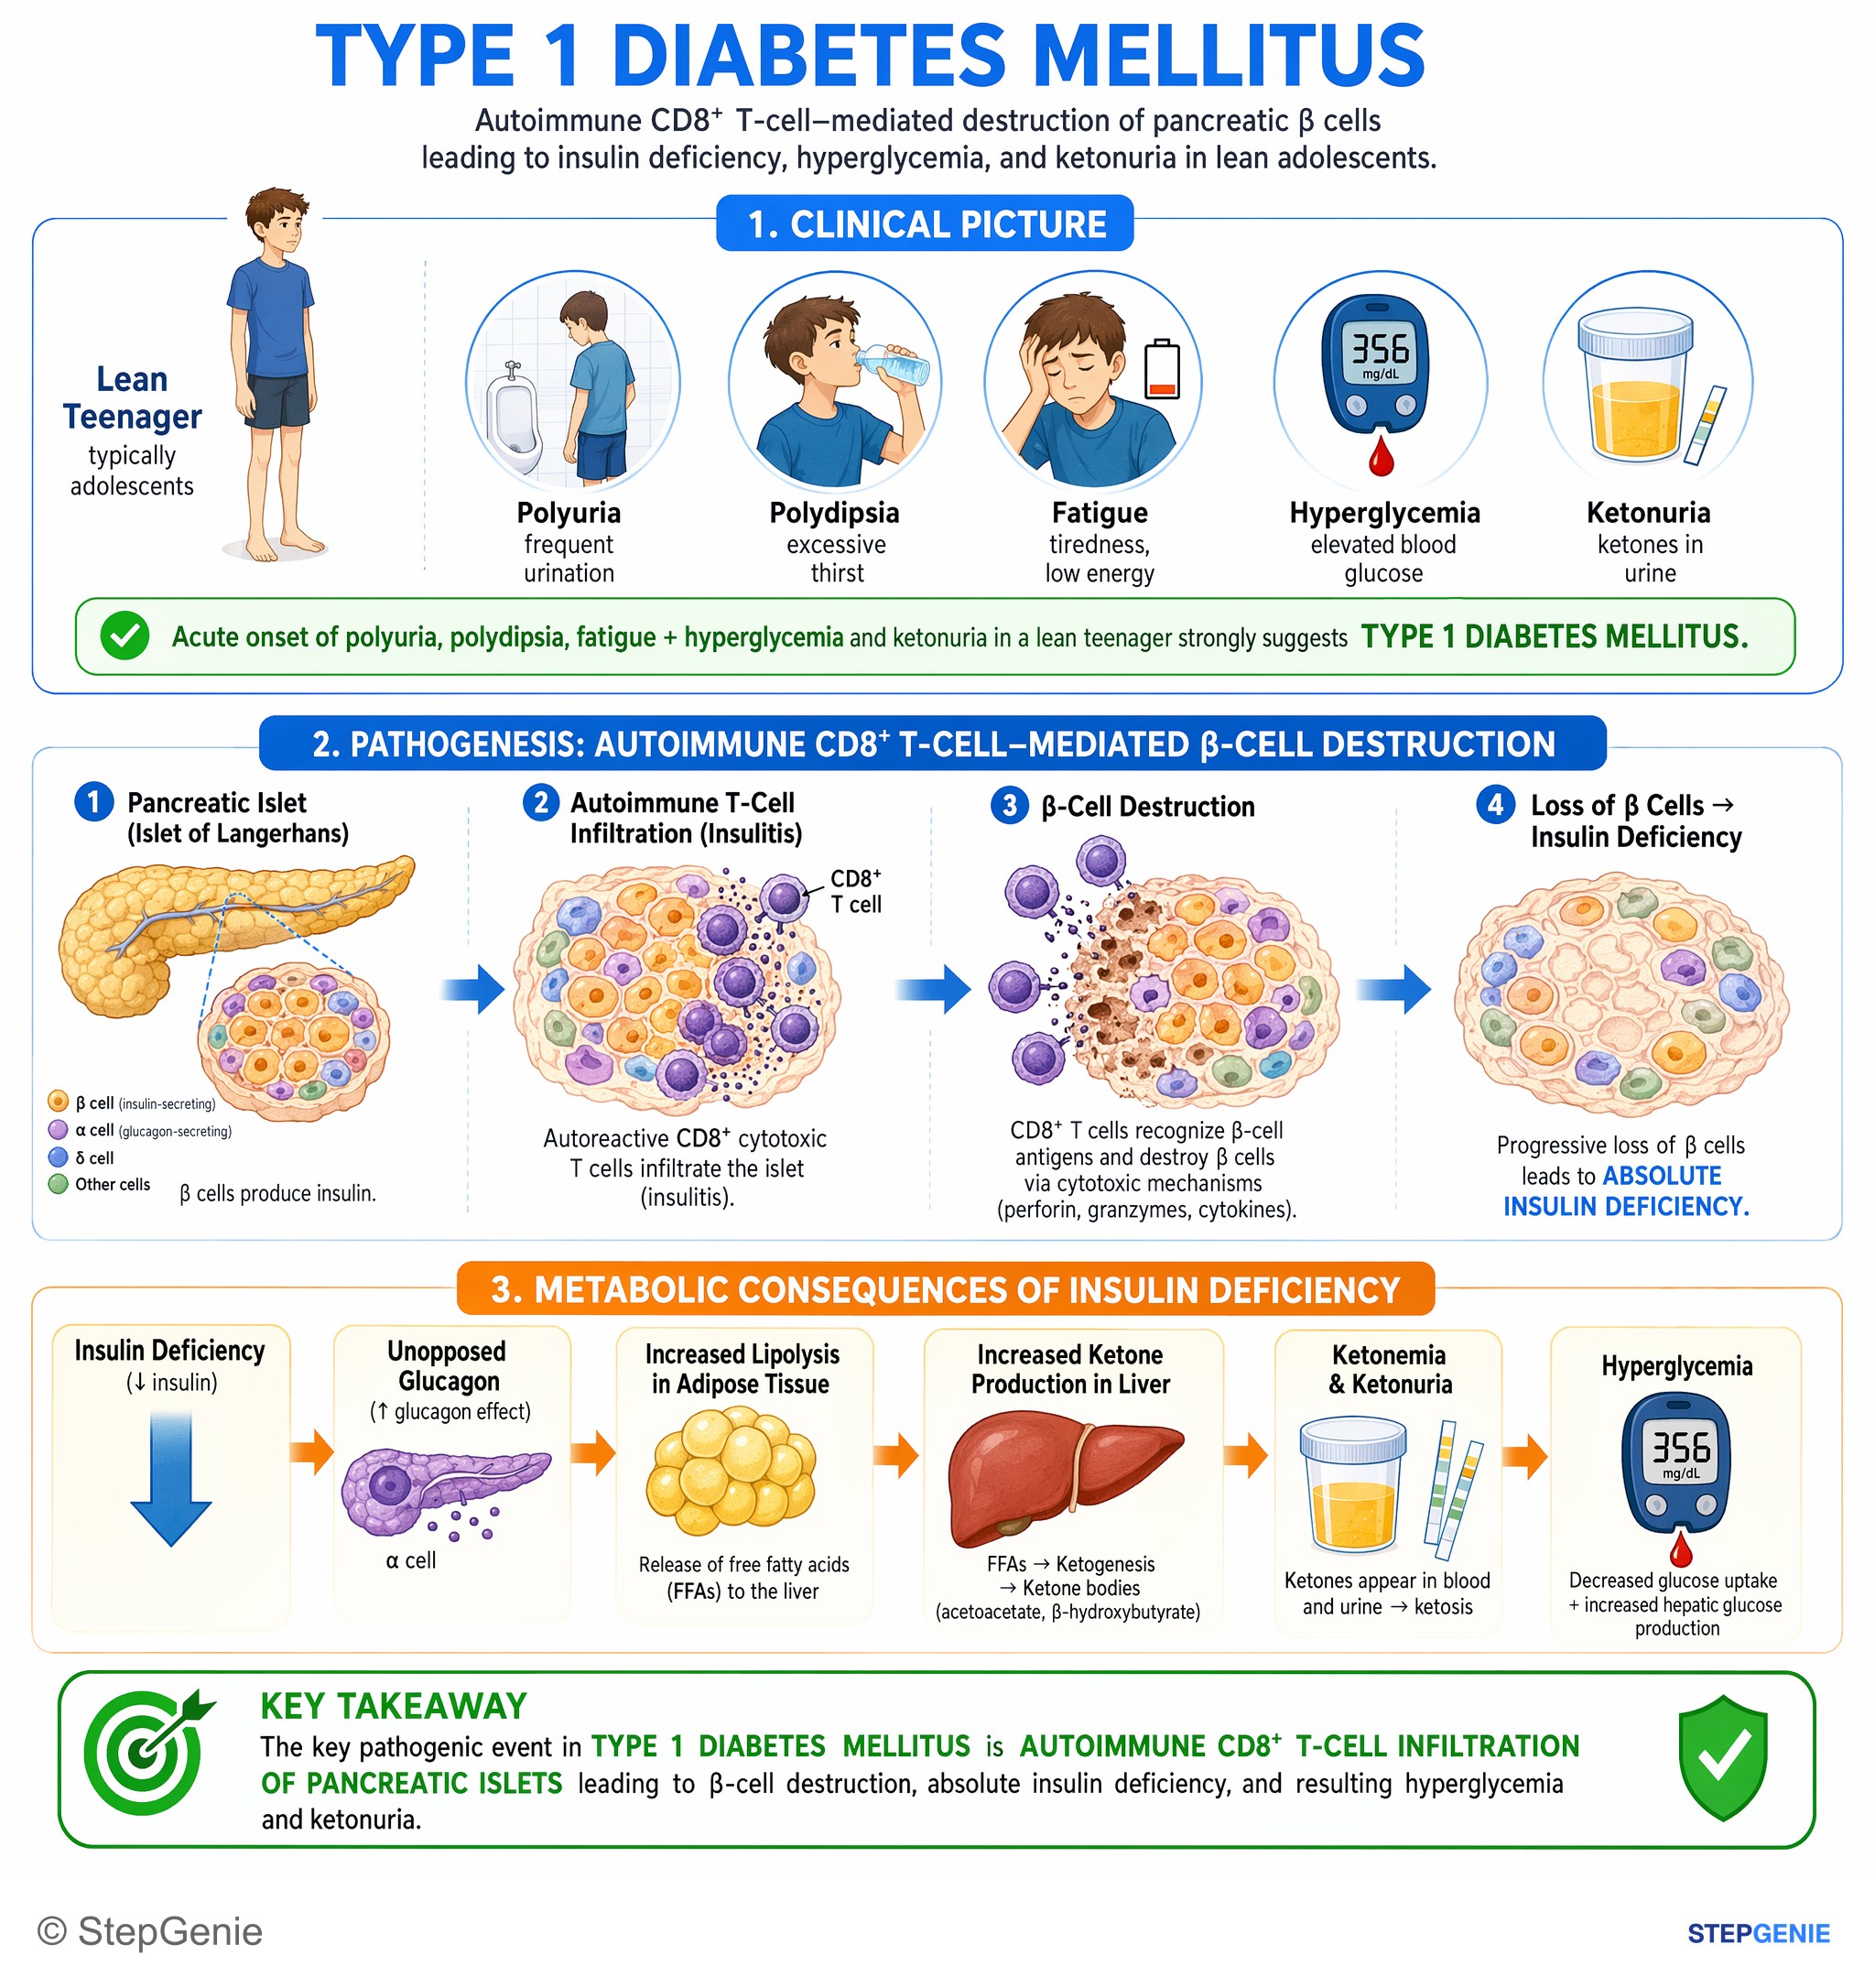
Type 1 diabetes mellitus: autoimmune CD8⁺ T-cell–mediated destruction of pancreatic β cells → insulin deficiency, hyperglycemia, ketonuria…
USMLE Step 1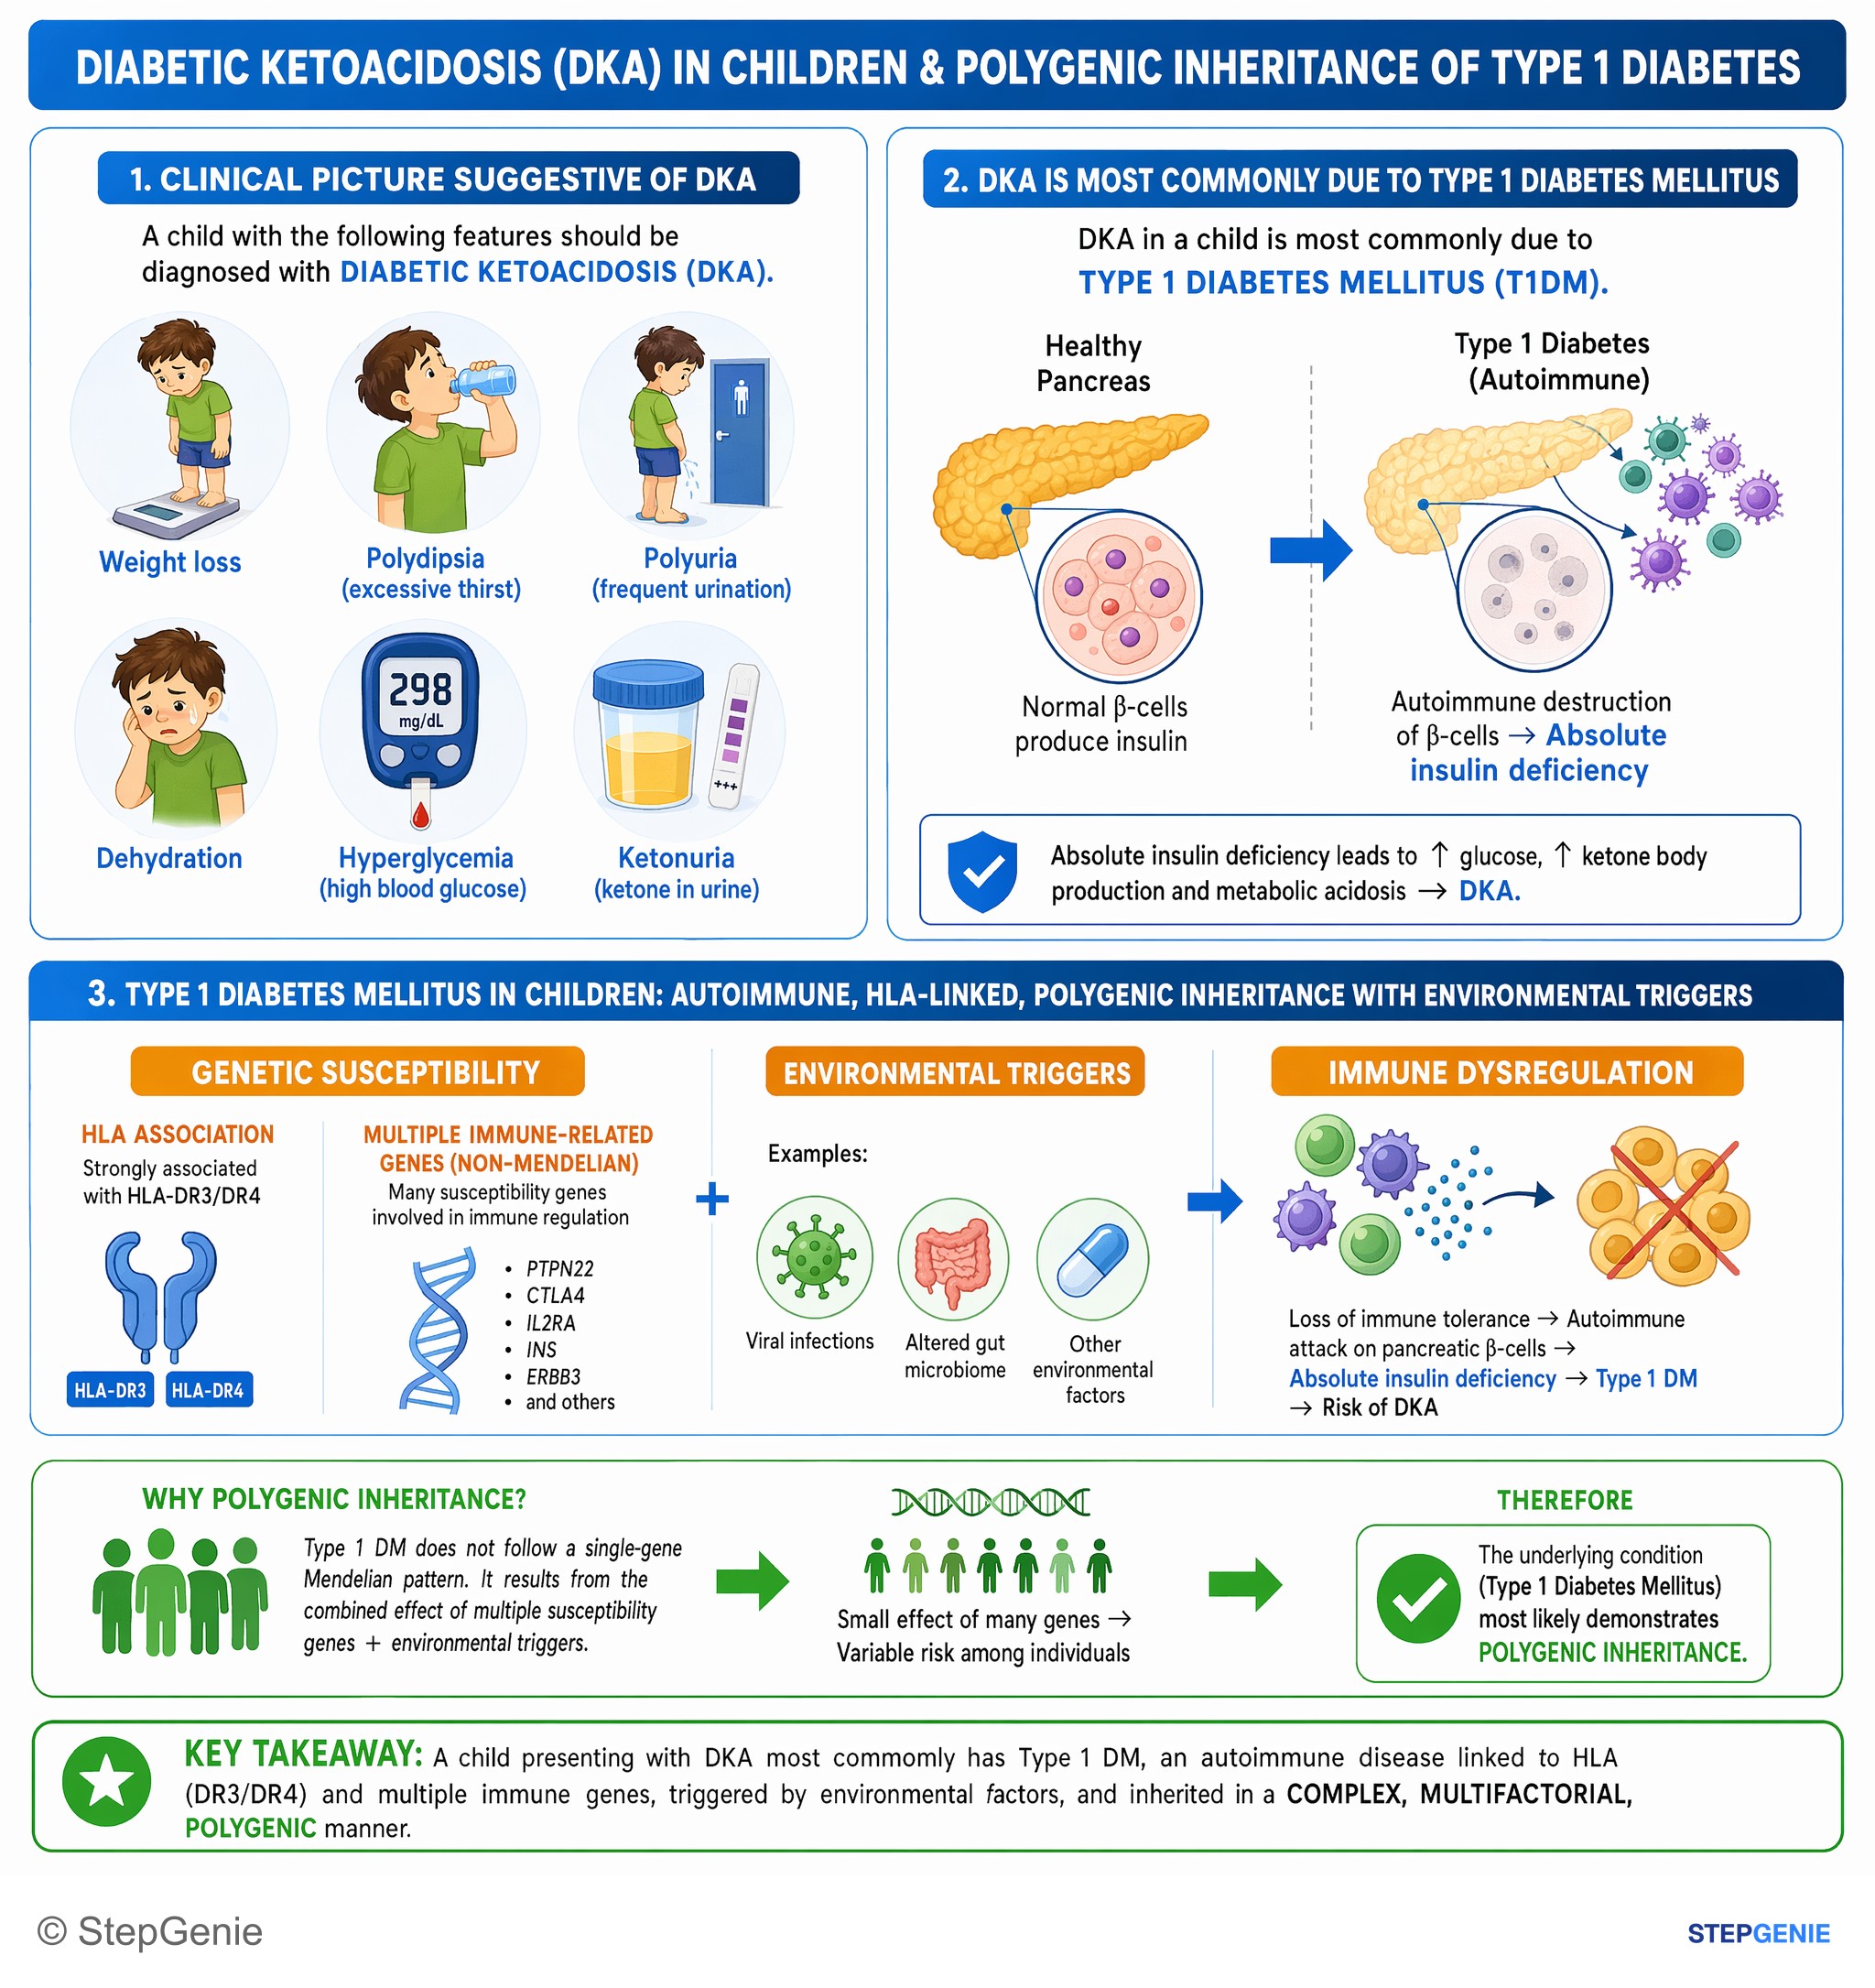
Type 1 diabetes mellitus in children is an autoimmune, HLA-linked disease with a polygenic inheritance pattern and environmental triggers…
USMLE Step 1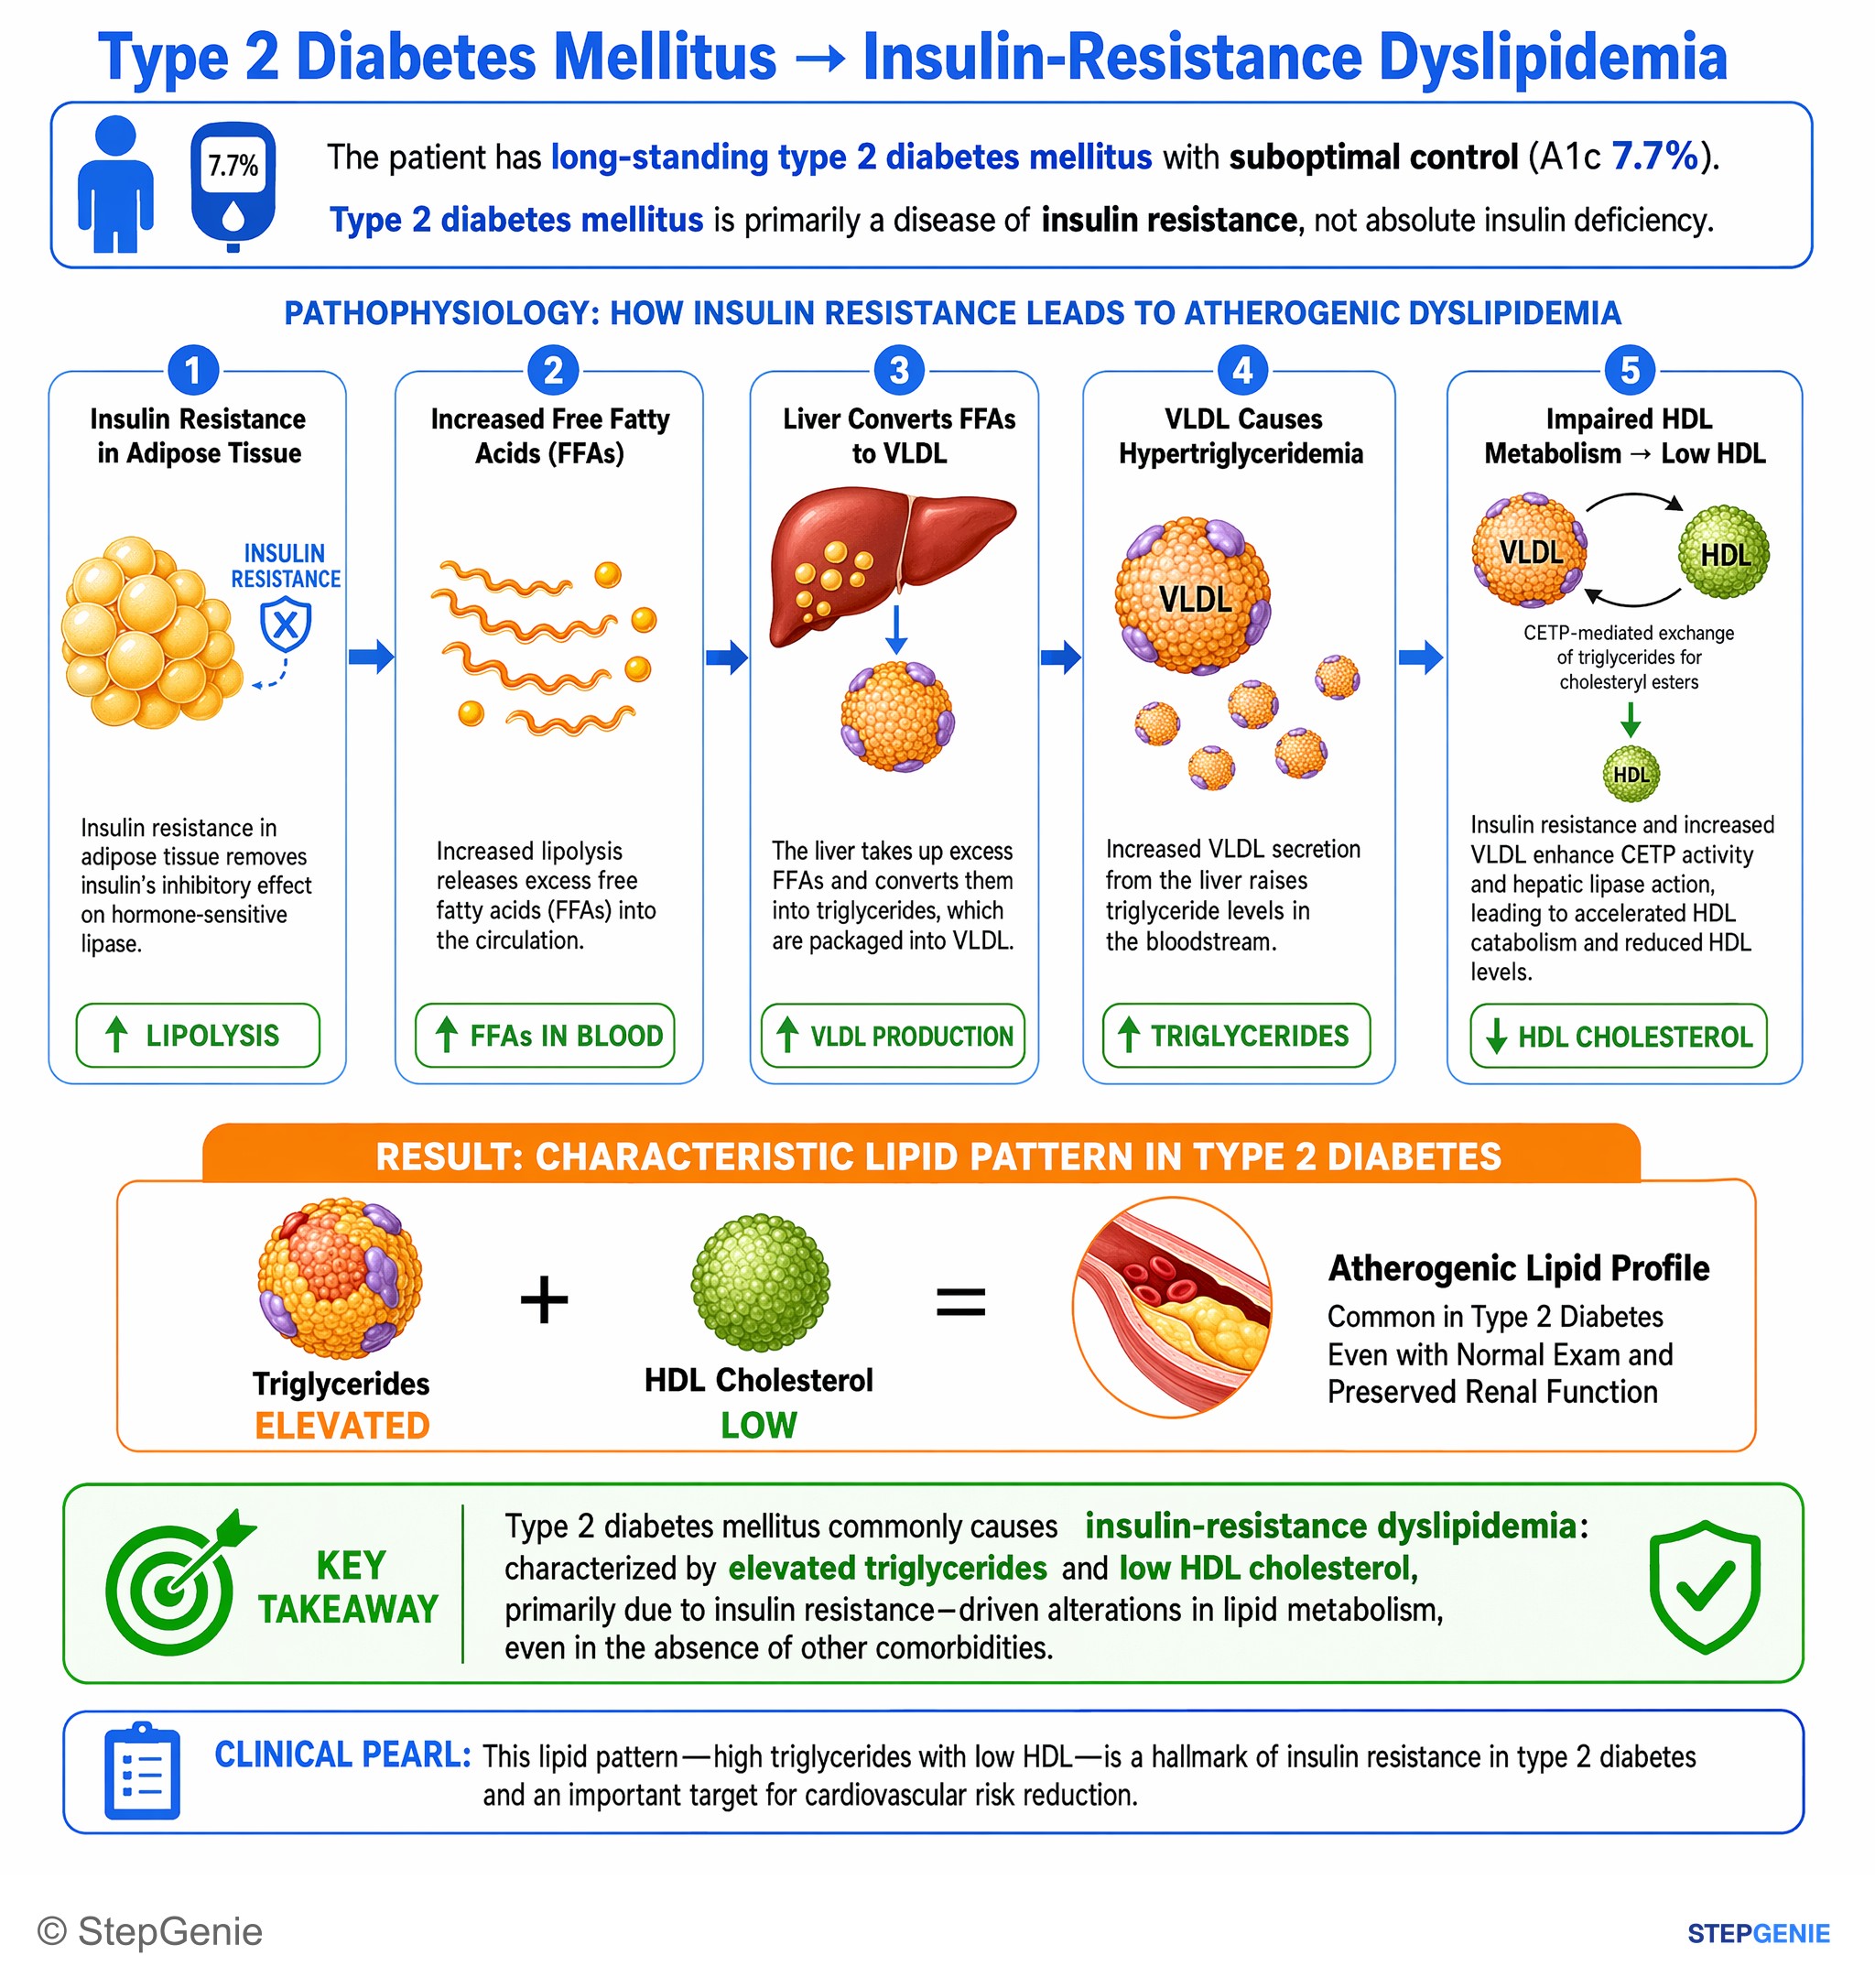
Type 2 diabetes mellitus commonly causes insulin-resistance dyslipidemia: elevated triglycerides and low HDL despite normal exam and…
USMLE Step 1Frequently Asked Questions
Why does type 1 diabetes cause diabetic ketoacidosis?
Type 1 diabetes causes diabetic ketoacidosis because autoimmune destruction of pancreatic beta cells creates absolute insulin deficiency. Without insulin, hormone-sensitive lipase activity increases, generating free fatty acids that the liver converts into ketones. At the same time, counterregulatory hormones such as glucagon, epinephrine, cortisol, and growth hormone are unopposed, which amplifies hyperglycemia and ketone production and leads to metabolic acidosis.
How do you tell type 1 diabetes from type 2 diabetes in a question stem?
Type 1 diabetes is suggested by a lean or younger patient with abrupt onset, weight loss, low C-peptide, and high risk of diabetic ketoacidosis, while type 2 diabetes more often has gradual onset, obesity or overweight body habitus, insulin resistance, and normal or high C-peptide early in the disease. In this vignette, the teen age, rapid onset, weight loss, and DKA point strongly to type 1 diabetes.
What clues in a vignette point to diabetic ketoacidosis?
The key clues for diabetic ketoacidosis are marked hyperglycemia, high anion gap metabolic acidosis, positive serum ketones, and Kussmaul respirations. This patient has glucose of 520 mg/dL, arterial pH of 7.18, bicarbonate of 10 mEq/L, positive ketones, and deep rapid breathing, which together identify DKA. Weight loss, polyuria, and polydipsia further support uncontrolled diabetes as the underlying cause.
Why is peripheral insulin resistance with compensatory hyperinsulinemia the wrong answer here?
Peripheral insulin resistance with compensatory hyperinsulinemia describes early type 2 diabetes, not classic type 1 diabetes with DKA. Early type 2 disease typically has increased insulin production and normal or high C-peptide, whereas this vignette shows a lean teen with rapid onset, weight loss, and diabetic ketoacidosis, which fits absolute insulin deficiency from autoimmune beta-cell destruction much better. DKA is uncommon in classic type 2 diabetes.
What autoimmune markers are high-yield for type 1 diabetes?
The high-yield autoimmune markers for type 1 diabetes are anti-GAD65, anti-islet cell, and anti-insulin antibodies. Type 1 diabetes is also associated with HLA-DR3 and HLA-DR4, and histology shows insulitis with lymphocytic infiltration of the islets. These findings support the core mechanism of autoimmune beta-cell destruction leading to absolute insulin deficiency and low C-peptide.