You just finished a diabetes question and thought, “DKA vs HHS—easy.” Then you look at the answer explanations and realize every option is basically a trap. This post is a step-by-step Q-bank style breakdown that doesn’t just tell you the right answer—it teaches you why each distractor is wrong (and when it would be right). Tag: Endocrine > Diabetes Mellitus.
The Vignette (Classic Step Style)
A 23-year-old man with type 1 diabetes mellitus is brought to the ED for confusion and abdominal pain. He stopped taking insulin 2 days ago because he “ran out.” He has nausea and vomiting.
Vitals: T 37.2°C, HR 118, BP 96/58, RR 28 (deep), SpO₂ 99% RA.
Exam: dry mucous membranes, diffuse abdominal tenderness.
Labs:
- Glucose: 420 mg/dL
- Na⁺: 130 mEq/L
- K⁺: 5.6 mEq/L
- HCO₃⁻: 10 mEq/L
- Anion gap: 24
- Serum ketones: positive
- ABG: pH 7.12, PaCO₂ 22 mmHg
Question: What is the best next step in management?
Answer choices
A. IV regular insulin infusion only
B. IV normal saline, then IV regular insulin infusion
C. Subcutaneous rapid-acting insulin and discharge after PO fluids
D. IV sodium bicarbonate
E. IV dextrose infusion immediately
Step 1: Identify the Syndrome (DKA vs HHS)
This vignette is DKA.
Why it’s DKA
- Type 1 DM + missed insulin
- High anion gap metabolic acidosis: HCO₃⁻ 10, AG 24, pH 7.12
- Ketones positive
- Kussmaul respirations (RR 28 deep) → compensatory respiratory alkalosis (low PaCO₂)
- Abdominal pain + vomiting are very DKA-coded
What would push you toward HHS instead?
Think older type 2, profound dehydration, neuro symptoms, very high glucose, and minimal ketones/acidosis.
| Feature | DKA | HHS |
|---|---|---|
| Typical patient | Type 1 (can occur in type 2) | Type 2 (older) |
| Glucose | Usually >250 (often 300–600) | Usually >600 (often 800–1200) |
| pH | <7.30 | >7.30 |
| HCO₃⁻ | <18 | >18 |
| Ketones | High | Minimal/absent |
| Osmolality | Variable | High (often >320 mOsm/kg) |
| Mental status | Variable | More prominent AMS |
| Main killer | Acidosis + electrolyte shifts | Dehydration + thrombosis |
High-yield trigger list
- DKA: missed insulin, infection, MI, stroke, pancreatitis, cocaine; SGLT2 inhibitors can cause euglycemic DKA
- HHS: infection, steroids, thiazides, dehydration/poor access to water
Correct Answer: B. IV normal saline, then IV regular insulin infusion
Why B is correct (the algorithm that always scores points)
In DKA/HHS, treat in this order:
- Fluids first (restore perfusion, lower catecholamines/cortisol, improve renal clearance of glucose/ketones)
- Potassium assessment/repletion
- Insulin infusion
- Add dextrose once glucose drops to target range (to allow insulin to continue closing the gap)
For this patient: hypotensive and dry → start 0.9% normal saline. Then insulin infusion (after confirming K⁺ is not dangerously low).
Now the Money Part: Why Each Distractor Is Wrong (and When It’s Right)
A. IV regular insulin infusion only ❌
Why it’s wrong here
Starting insulin before fluids can worsen hemodynamics because insulin drives glucose (and water) into cells, potentially dropping intravascular volume further in a patient who is already hypotensive.
Also, insulin drives K⁺ into cells → risk of hypokalemia-induced arrhythmia if K⁺ isn’t monitored and replaced.
When it might look tempting
If you’re overfocused on the acidosis/ketones. But on Step exams, fluids are the first move in both DKA and HHS unless there’s a very specific contraindication (rarely tested).
C. Subcutaneous rapid-acting insulin and discharge after PO fluids ❌
Why it’s wrong here
This patient has:
- pH 7.12 (severe acidemia)
- hypotension and tachycardia
- altered mental status
- ongoing vomiting
That’s ICU-level DKA until proven otherwise.
When subcutaneous insulin is appropriate
Some institutions use SQ rapid-acting insulin protocols for mild DKA in selected stable patients:
- pH typically >7.25–7.30
- able to tolerate PO
- no severe comorbidities
- close monitoring available
This vignette is not that.
D. IV sodium bicarbonate ❌ (usually)
Why it’s wrong here
Bicarb is not routinely indicated in DKA because it can:
- worsen hypokalemia once insulin is started
- cause paradoxical CNS acidosis
- reduce tissue oxygen release (left shift of hemoglobin dissociation curve)
- increase risk of cerebral edema (esp pediatrics)
When bicarbonate is indicated (high-yield thresholds)
Most testable indication:
- pH < 6.9 (some guidelines use <6.9; occasionally <7.0)
This patient’s pH is 7.12, so treat with fluids + insulin + potassium strategy.
E. IV dextrose infusion immediately ❌
Why it’s wrong here
Dextrose is used in DKA later, not upfront. The immediate problem is hyperglycemia, dehydration, and ketosis.
When dextrose becomes correct
Once glucose drops but the anion gap is still open (ketosis ongoing), you add dextrose to keep insulin running:
- In DKA, add dextrose when glucose is <200 mg/dL
- In HHS, add dextrose when glucose is <300 mg/dL
A common Step phrase: “Switch to D5-½NS when glucose hits goal and continue insulin until the gap closes.”
The High-Yield Physiology Behind the Labs (What Step Wants You to Say Out Loud)
1) Why potassium is high even though total body K⁺ is low
In DKA:
- insulin deficiency + acidosis → K⁺ shifts out of cells → serum K⁺ may be normal/high
- but osmotic diuresis → K⁺ losses in urine → total body K⁺ depletion
Translation: a “high” K⁺ (like 5.6) is not reassuring—once you give insulin, K⁺ can plummet.
Potassium rules that get tested
- If K⁺ <3.3: hold insulin, give K⁺ first
- If K⁺ 3.3–5.2: give K⁺ with insulin
- If K⁺ >5.2: start insulin, monitor closely, replace when it falls
2) Corrected sodium (hidden hypernatremia clue)
Hyperglycemia causes water shift into plasma → measured Na⁺ looks low.
A common correction:
Here, glucose 420:
- Add
- Corrected Na⁺ → not truly hyponatremic
Exam tip: corrected sodium helps you choose fluids later (e.g., switching to 0.45% saline if corrected Na⁺ is high/normal after initial resuscitation).
3) Why abdominal pain happens in DKA
Not appendicitis until proven otherwise:
- acidosis + electrolyte shifts + decreased perfusion can cause abdominal pain, ileus, and vomiting
- pain often improves as acidosis resolves
DKA vs HHS: The “What Kills Them” Memory Hook
DKA
- Faster onset (hours)
- “Acid problem”
- Risk: arrhythmias (K⁺ shifts), cerebral edema (esp kids), shock
HHS
- Slower onset (days)
- “Water problem”
- Risk: severe dehydration, thrombosis (stroke/MI/DVT/PE)
HHS high-yield add-on: consider VTE prophylaxis in hospitalized HHS because hyperviscosity + immobility increases clot risk.
One-Pass Management Algorithm (Exam-Friendly)
For both DKA and HHS
- 0.9% NS bolus (initial resuscitation)
- Check K⁺:
- If <3.3: K⁺ first, then insulin
- IV regular insulin infusion
- When glucose reaches goal:
- DKA: add dextrose at <200
- HHS: add dextrose at <300
- Stop insulin infusion only when:
- DKA: anion gap closed + HCO₃⁻ improved + clinically better
- HHS: osmolality improving + mental status improving
- Transition to subQ insulin with overlap (to prevent rebound):
- continue drip for ~1–2 hours after first long-acting dose
Rapid-Fire “Answer Choice Matters” Takeaways
- Fluids before insulin is the safe, testable default.
- Serum K⁺ can be high but total body K⁺ is low—monitor like a hawk.
- Bicarbonate is rarely indicated (think pH < 6.9).
- Dextrose is not for the beginning—it’s for the “gap still open but glucose is dropping” phase.
- HHS = dehydration + thrombosis risk, DKA = acidosis + ketosis.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
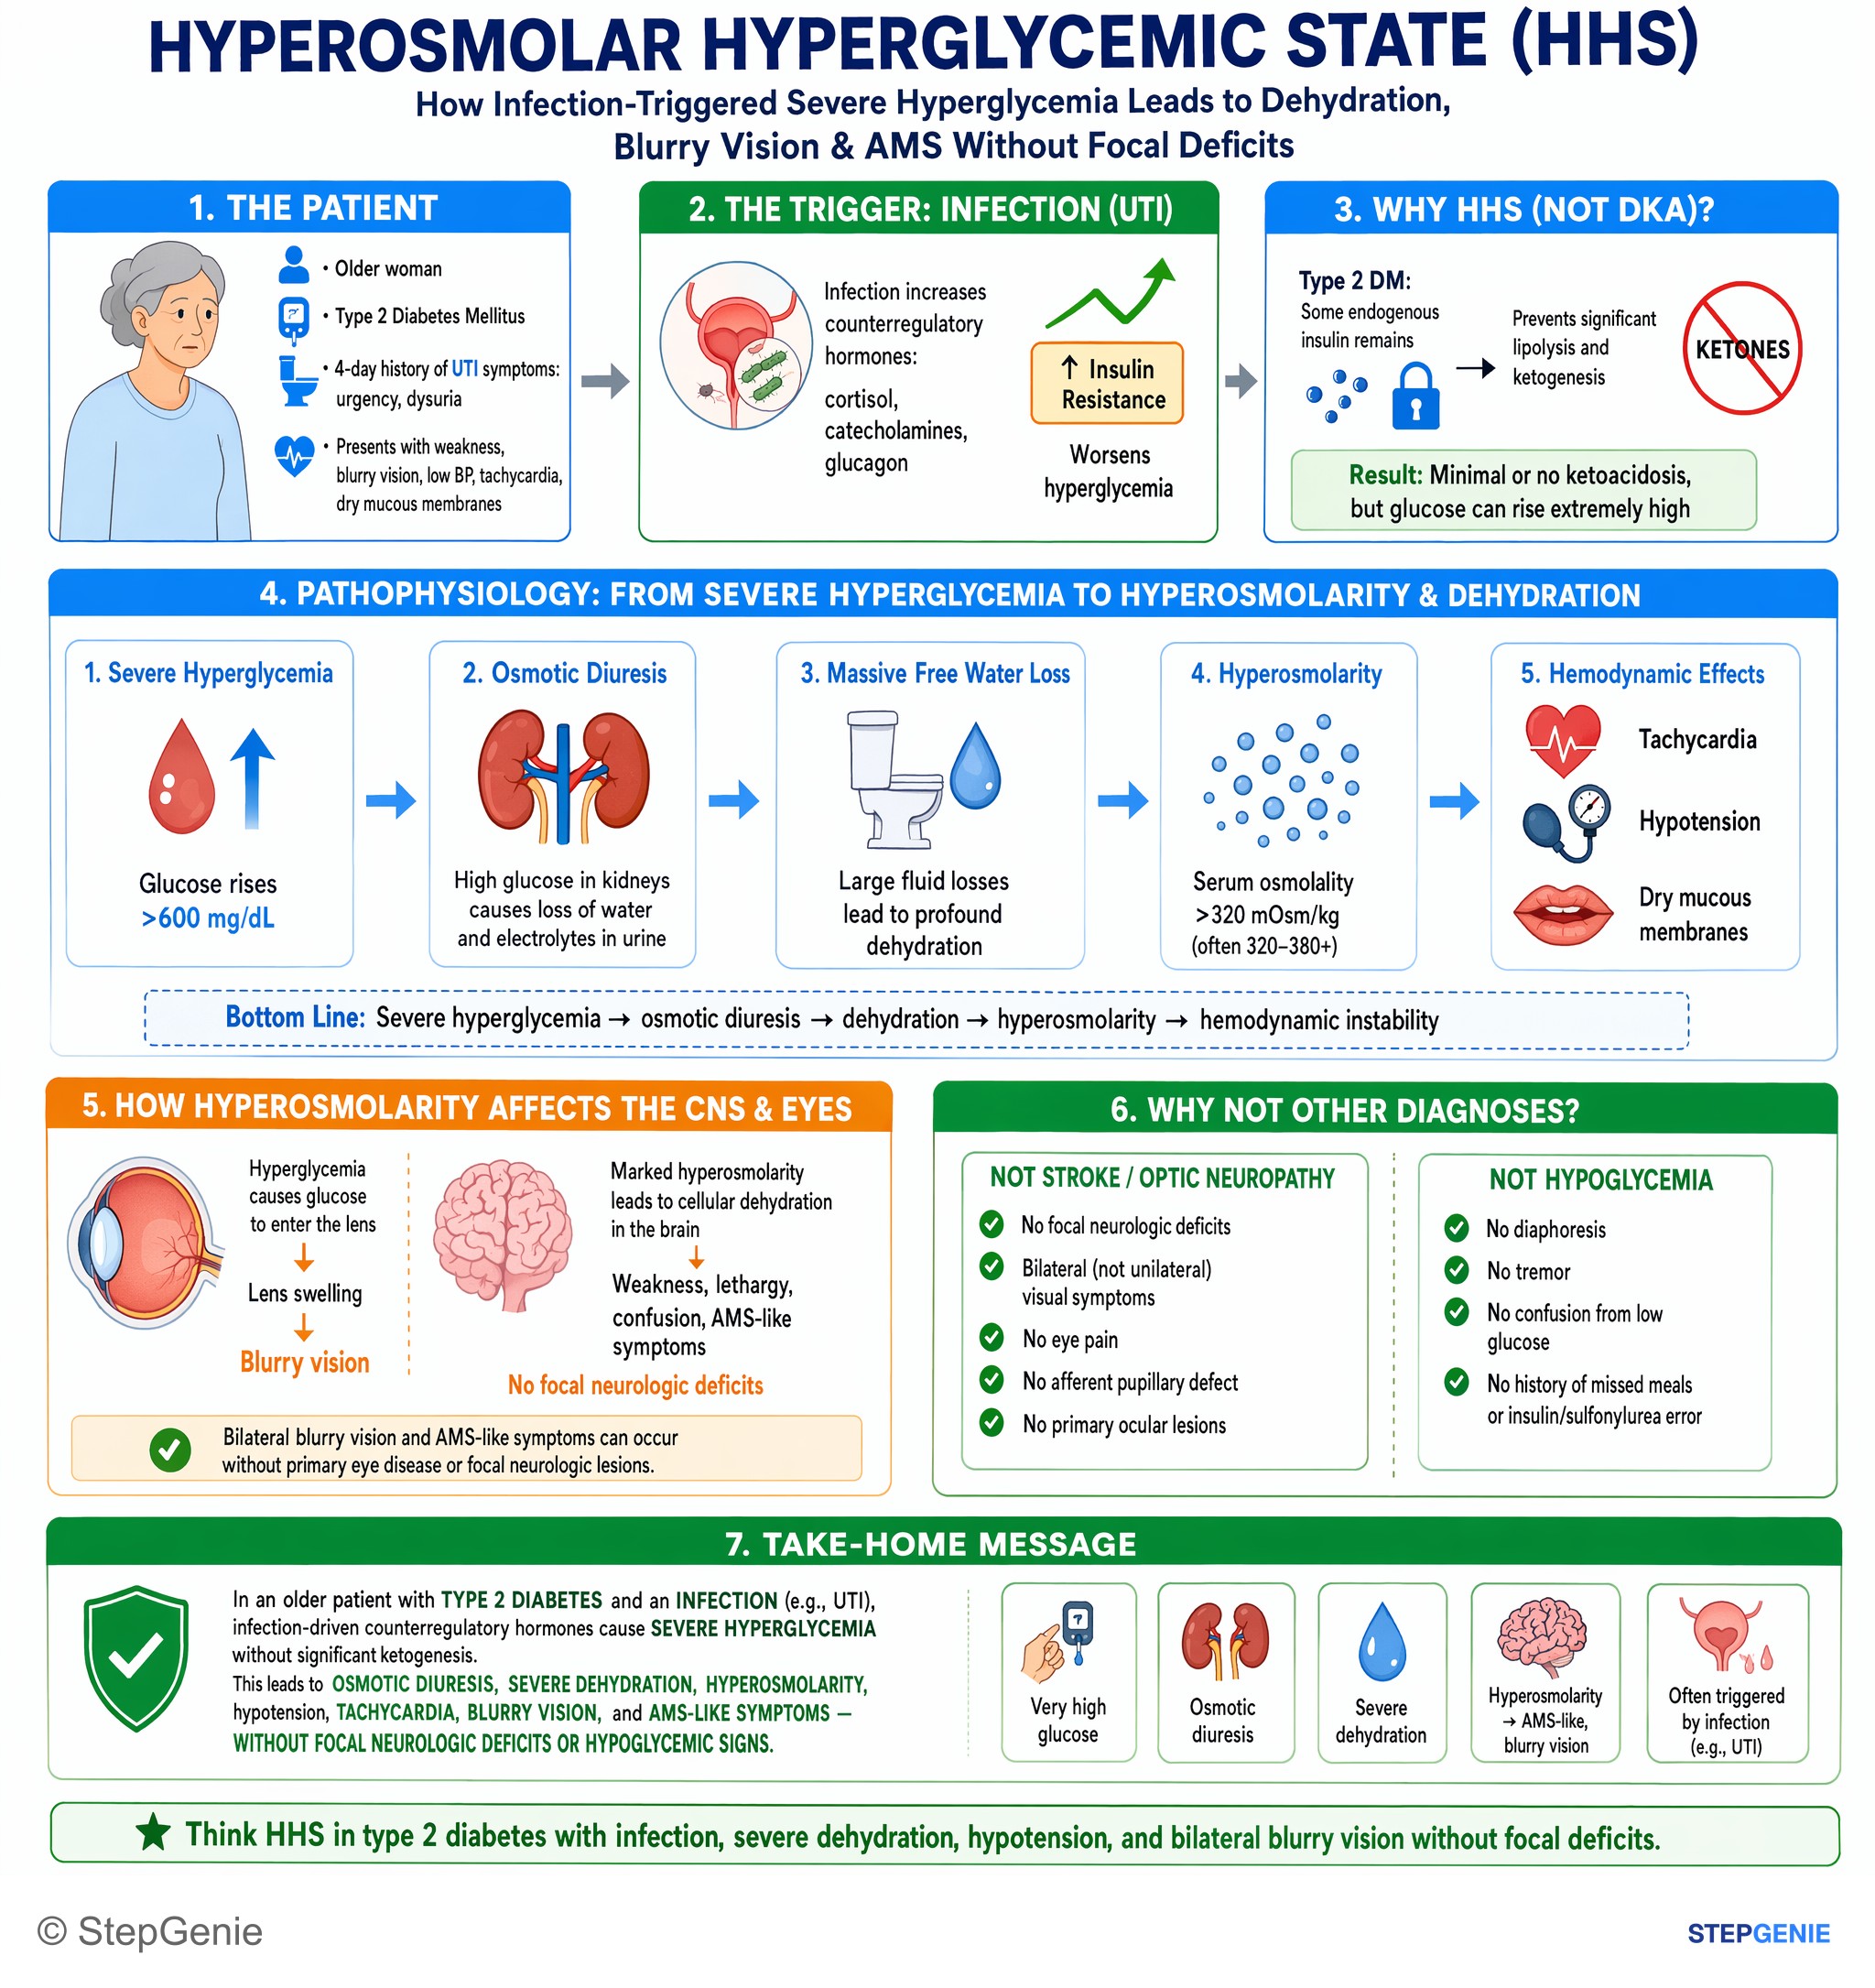
Hyperosmolar hyperglycemic state from infection-induced severe hyperglycemia: dehydration, hypotension, blurry vision, AMS symptoms, but…
USMLE Step 2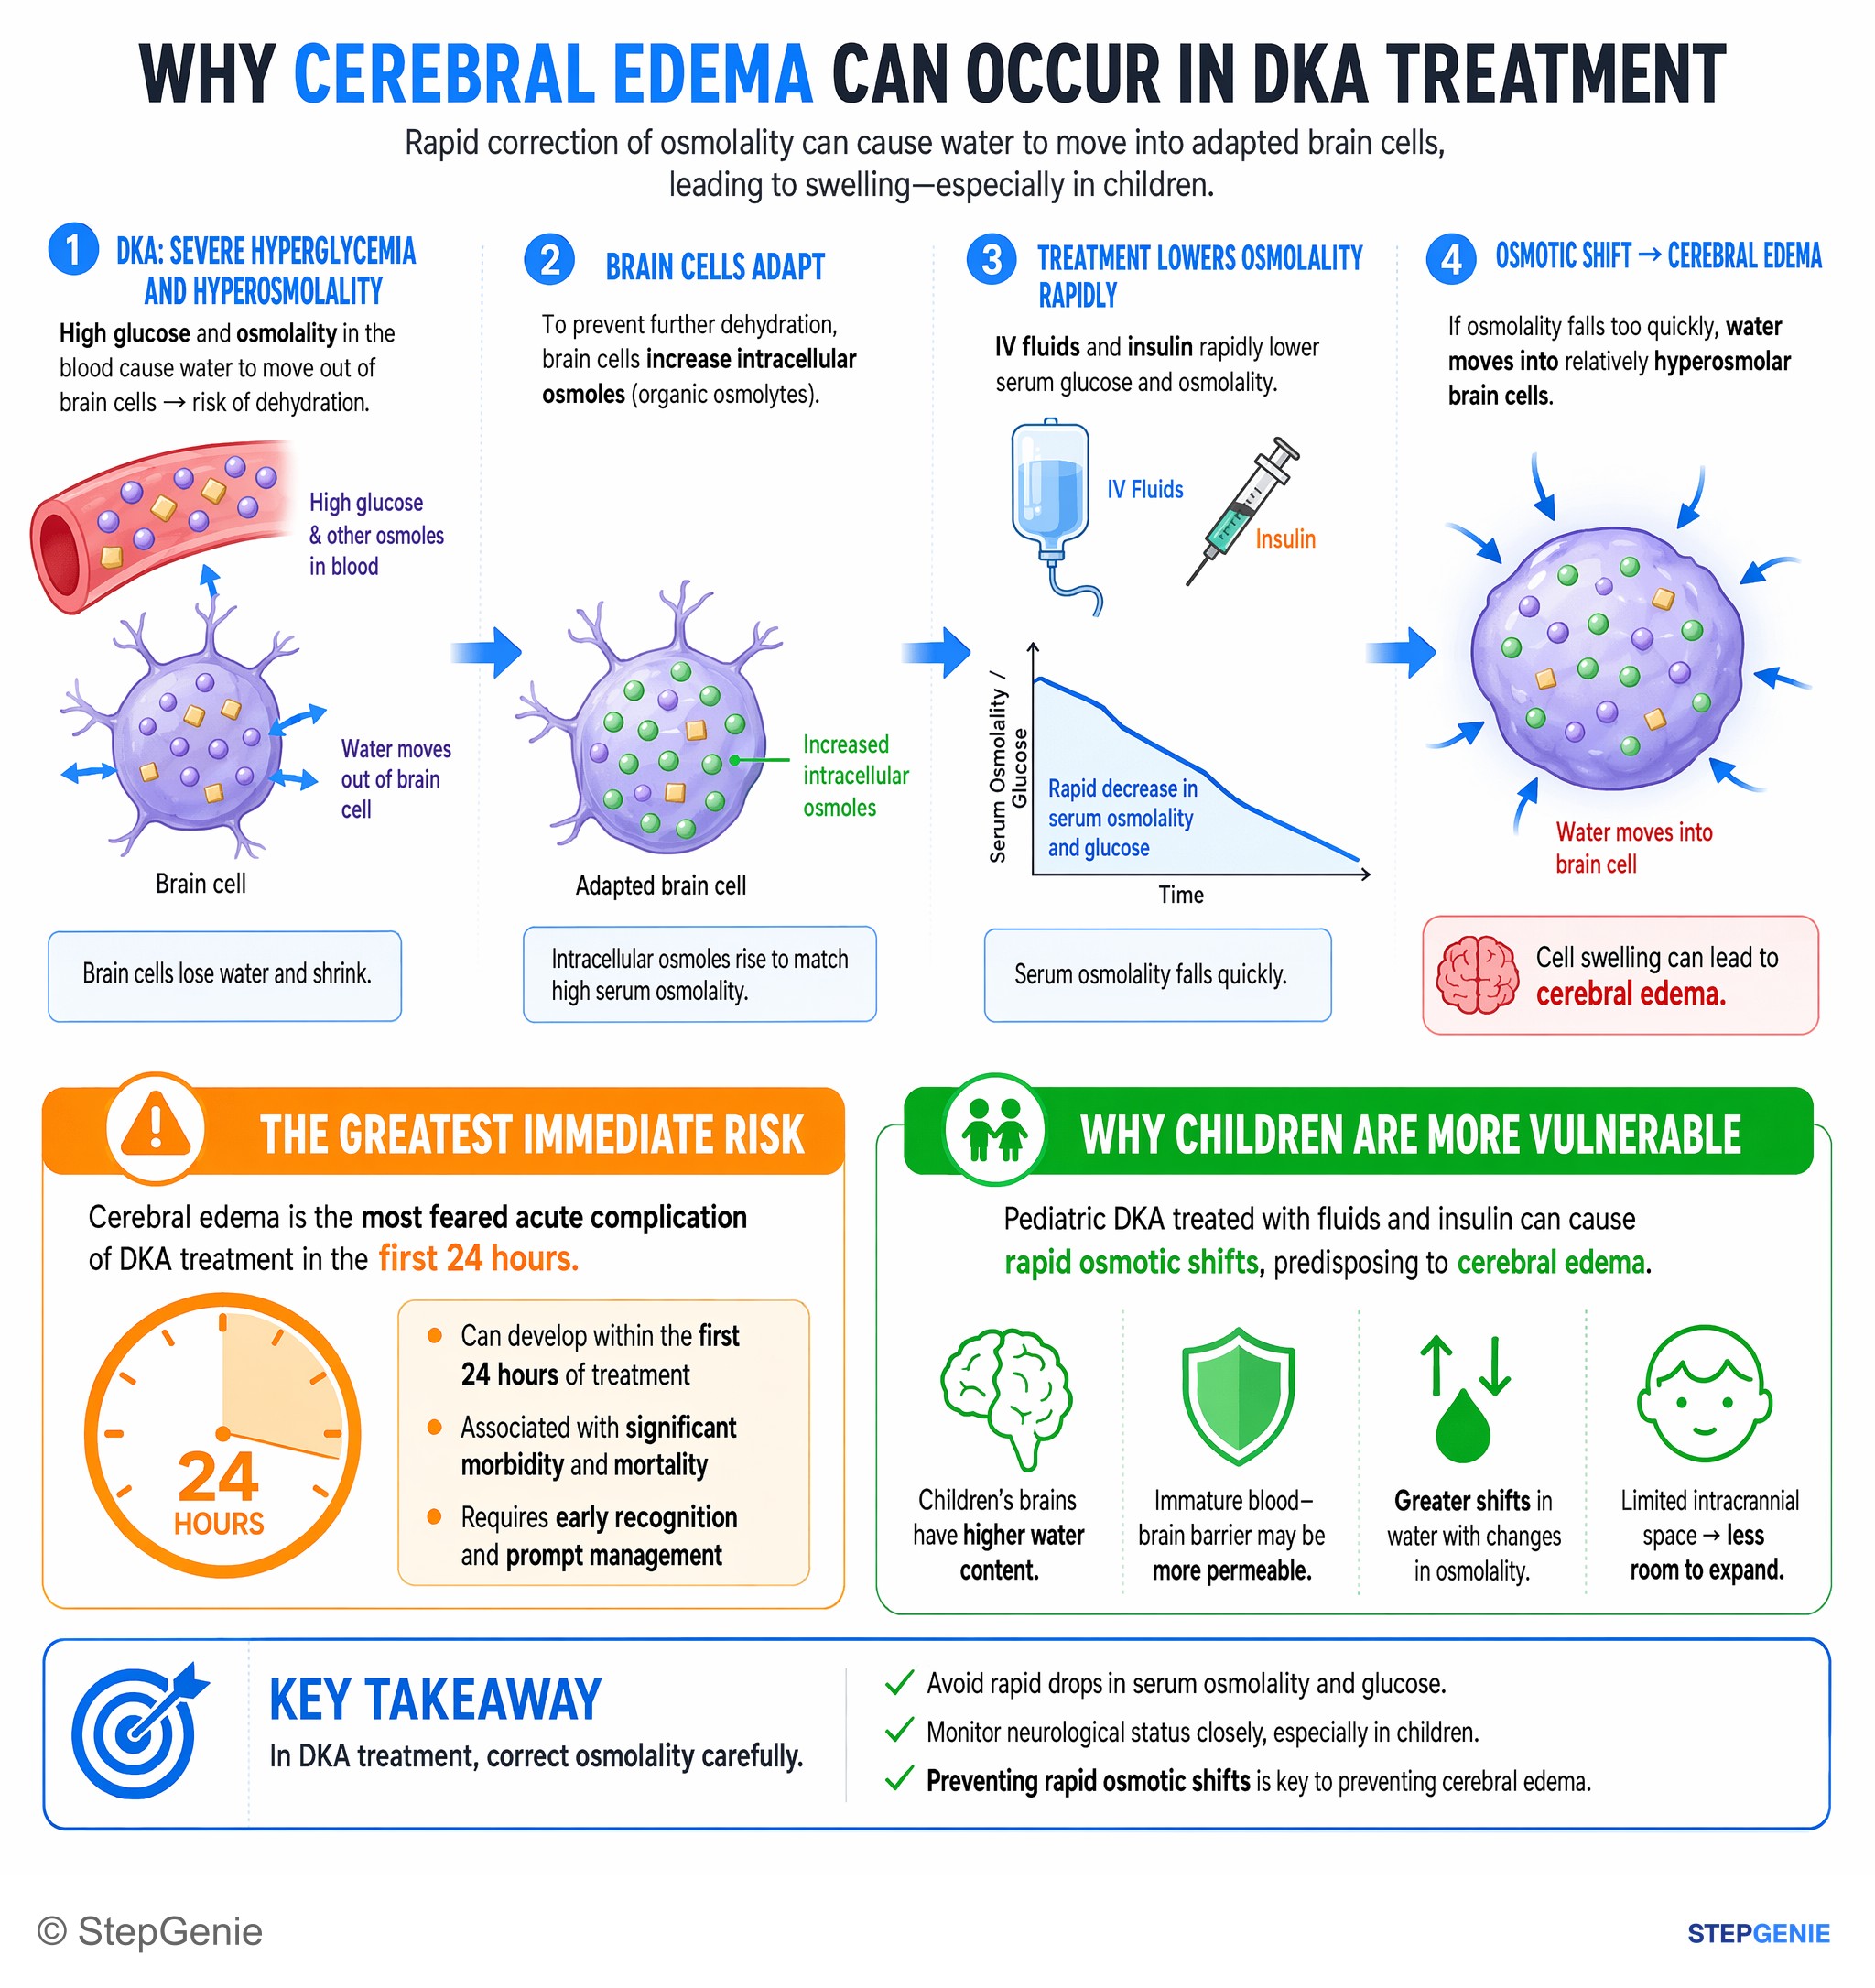
Pediatric DKA treated with fluids and insulin can cause rapid osmotic shifts, predisposing to cerebral edema within the first 24 hours.
USMLE Step 2Frequently Asked Questions
How do you tell DKA from HHS on a vignette?
DKA is suggested by type 1 diabetes, missed insulin, high anion gap metabolic acidosis, positive ketones, and symptoms like abdominal pain, vomiting, and Kussmaul respirations. HHS is more associated with older patients with type 2 diabetes, profound dehydration, more prominent altered mental status, very high glucose, and minimal ketones or acidosis. On labs, DKA has pH below 7.30 and bicarbonate below 18, while HHS usually does not.
What is the best next step in management for DKA?
The best next step is IV normal saline first, followed by IV regular insulin infusion. Initial fluids restore perfusion, lower stress hormones, and improve renal clearance of glucose and ketones. After that, insulin is started once potassium has been assessed and is not dangerously low. This sequence is emphasized for both DKA and HHS because treating dehydration first is the safest and most effective first move.
Why is insulin alone the wrong first treatment in DKA?
Insulin alone is the wrong first step because giving it before fluids can worsen hemodynamics in an already volume-depleted patient. Insulin moves glucose and water into cells, which can further reduce intravascular volume and worsen hypotension. It also shifts potassium into cells, creating a risk of sudden hypokalemia and arrhythmia if potassium is not monitored and managed appropriately first.
Why can potassium be high in DKA if total body potassium is low?
Serum potassium can be high in DKA because insulin deficiency and acidosis shift potassium out of cells into the blood. At the same time, osmotic diuresis causes urinary potassium losses, so total body potassium is actually depleted. This is why an elevated potassium level is not reassuring in DKA: once insulin is started, potassium can fall quickly and requires close monitoring and replacement strategy.
When do you give bicarbonate or dextrose in DKA?
Bicarbonate is usually not given in DKA unless the pH is below 6.9, because routine use can worsen hypokalemia, contribute to paradoxical CNS acidosis, reduce tissue oxygen release, and increase cerebral edema risk. Dextrose is added later, not immediately. In DKA, it is started once the glucose falls below 200 mg/dL so insulin can continue until the anion gap closes.