Adrenal insufficiency questions are sneaky because the “right” diagnosis is often less about memorizing one hallmark feature and more about weighing multiple small clues—BP, electrolytes, pigmentation, meds, and what the patient was doing right before they crashed. The payoff: once you learn to dissect these vignettes, you’ll start getting every answer choice for free.
The Clinical Vignette (Q-bank style)
A 38-year-old woman presents to the ED with 1 day of severe weakness, abdominal pain, nausea, and confusion. She recently had a “bad stomach bug” with vomiting and poor oral intake. PMH: autoimmune hypothyroidism. Meds: levothyroxine. Vitals: T 37.1°C, BP 82/48 mm Hg, HR 118/min. Exam: diffuse abdominal tenderness; hyperpigmentation in palmar creases. Labs:
| Lab | Value |
|---|---|
| Na⁺ | 124 mEq/L |
| K⁺ | 5.9 mEq/L |
| Glucose | 54 mg/dL |
| BUN/Cr | elevated |
| Eosinophils | mildly elevated |
Question: What is the most appropriate next step in management?
A. Cosyntropin stimulation test
B. IV hydrocortisone and IV normal saline
C. Fludrocortisone only
D. Metyrapone
E. IV levothyroxine
Step-by-Step: What’s Going On?
This patient is in adrenal crisis (acute adrenal insufficiency) due to primary adrenal insufficiency (Addison disease):
The “primary” clues
- Hyperpigmentation → high ACTH → increased POMC → increased melanocyte-stimulating activity
- Hyperkalemia → low aldosterone (primary AI; secondary AI usually has normal K⁺)
- Autoimmune history (thyroid disease) → think autoimmune polyglandular syndrome
The “crisis” clues
- Hypotension/shock
- GI symptoms (abdominal pain, nausea/vomiting)
- Hypoglycemia
- Trigger: acute illness with volume depletion (vomiting)
Correct Answer: B. IV hydrocortisone and IV normal saline
In suspected adrenal crisis, treat first—test later.
Why this is correct (management priorities)
- Steroids immediately
- Hydrocortisone is preferred because it has both glucocorticoid + mineralocorticoid activity at stress doses.
- Aggressive fluids
- Normal saline to correct hypovolemia and hypotension
- Add dextrose if hypoglycemic (often D5NS, depending on glucose)
- Labs can be drawn before steroids if it doesn’t delay treatment (cortisol/ACTH), but don’t wait for confirmatory testing.
High-yield one-liner: If the patient is crashing and adrenal crisis is on the table: give stress-dose steroids + fluids now.
Acute vs Chronic Adrenal Insufficiency (What Step Wants You to Distinguish)
Chronic primary adrenal insufficiency (Addison)
- Gradual fatigue, weight loss, salt craving
- Hyperpigmentation
- Hyponatremia + hyperkalemia
- Orthostatic hypotension
- Often autoimmune
Acute adrenal crisis
- Often precipitated by:
- Infection, surgery, trauma
- Abrupt steroid withdrawal
- Dehydration (vomiting/diarrhea)
- Severe hypotension/shock
- Abdominal pain, fever, delirium
- Hypoglycemia (especially in kids, or severe cases)
Now, Why the Other Answer Choices Are Wrong (and What They’re Testing)
A. Cosyntropin stimulation test
Cosyntropin (synthetic ACTH) is great for diagnosing adrenal insufficiency—but not as the first step in an unstable patient.
When it is appropriate:
- Stable patient with suspected chronic adrenal insufficiency
- Workup of unexplained fatigue, hyponatremia, weight loss, etc.
Testing pearl:
- Primary AI: low cortisol that fails to rise after cosyntropin + high ACTH
- Secondary/tertiary AI: low cortisol with low ACTH; cosyntropin response can be variable early but often improves if adrenals aren’t chronically atrophied.
Why it’s wrong here: the patient is hypotensive and altered—treat first.
C. Fludrocortisone only
Fludrocortisone replaces mineralocorticoid (aldosterone effect). It’s used in chronic primary adrenal insufficiency—but it will not rescue someone in crisis.
Why it’s wrong:
- In adrenal crisis, you need glucocorticoid urgently to support vascular tone, catecholamine responsiveness, and glucose homeostasis.
- Also, hydrocortisone at stress doses provides enough mineralocorticoid effect initially.
When fludrocortisone matters:
- Long-term outpatient management of primary AI (Addison), typically alongside oral hydrocortisone/prednisone.
D. Metyrapone
Metyrapone inhibits 11β-hydroxylase, decreasing cortisol synthesis. It’s relevant in:
- Diagnostic testing of the HPA axis (special contexts)
- Treatment of hypercortisolism (Cushing syndrome) in select cases
Why it’s wrong:
- This patient has too little cortisol, not too much.
- Giving metyrapone would worsen hypotension and shock.
Association to remember:
11β-hydroxylase deficiency CAH → HTN + hypokalemia + virilization (not this case)
E. IV levothyroxine
This choice is trying to bait you into thinking “myxedema coma.” But the vignette supports adrenal crisis more strongly.
How to tell apart:
- Myxedema coma: hypothermia, bradycardia, hypoventilation, hyponatremia, altered mental status (often older patient)
- Adrenal crisis: hypotension, tachycardia, abdominal pain, hyperkalemia, hypoglycemia, hyperpigmentation
Extra-high-yield endocrine integration:
If you suspect both hypothyroidism and adrenal insufficiency, replace steroids first. Thyroid hormone increases cortisol clearance and metabolic demand → can precipitate adrenal crisis in someone with undiagnosed AI.
So even if she needed thyroid support, IV levothyroxine is not step 1 here.
Mini-Table: Primary vs Secondary/Tertiary Adrenal Insufficiency
| Feature | Primary AI (Addison) | Secondary/Tertiary AI |
|---|---|---|
| ACTH | High | Low (or inappropriately normal) |
| Aldosterone | Low | Usually normal |
| Potassium | High | Usually normal |
| Pigmentation | Yes | No |
| Common causes | Autoimmune, TB, hemorrhage, metastasis | Chronic steroids, pituitary disease, hypothalamic disease |
| Crisis trigger | Illness, stress, missed steroids | Abrupt steroid withdrawal, stress |
USMLE High-Yield Pearls (The Stuff Q-banks Love)
- Adrenal crisis = shock + GI symptoms + electrolyte derangements → treat immediately with IV hydrocortisone + IV fluids (and dextrose if needed).
- Hyperpigmentation + hyperkalemia points to primary adrenal insufficiency.
- Secondary AI: no hyperpigmentation, usually no hyperkalemia (aldosterone preserved via RAAS).
- Autoimmune clustering: Addison + autoimmune thyroid disease ± type 1 diabetes → autoimmune polyglandular syndromes.
- If you’re going to test, draw cortisol/ACTH first only if it doesn’t delay treatment—then start steroids.
Quick “Answer Choice Autopsy” (1-liners)
- A Cosyntropin test: diagnostic, but not before stabilizing an unstable patient.
- B Hydrocortisone + NS: correct—resuscitate first.
- C Fludrocortisone only: chronic mineralocorticoid replacement, not crisis management.
- D Metyrapone: blocks cortisol synthesis—used for Cushing, not adrenal insufficiency.
- E IV levothyroxine: wrong priority; give steroids first if AI is possible.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
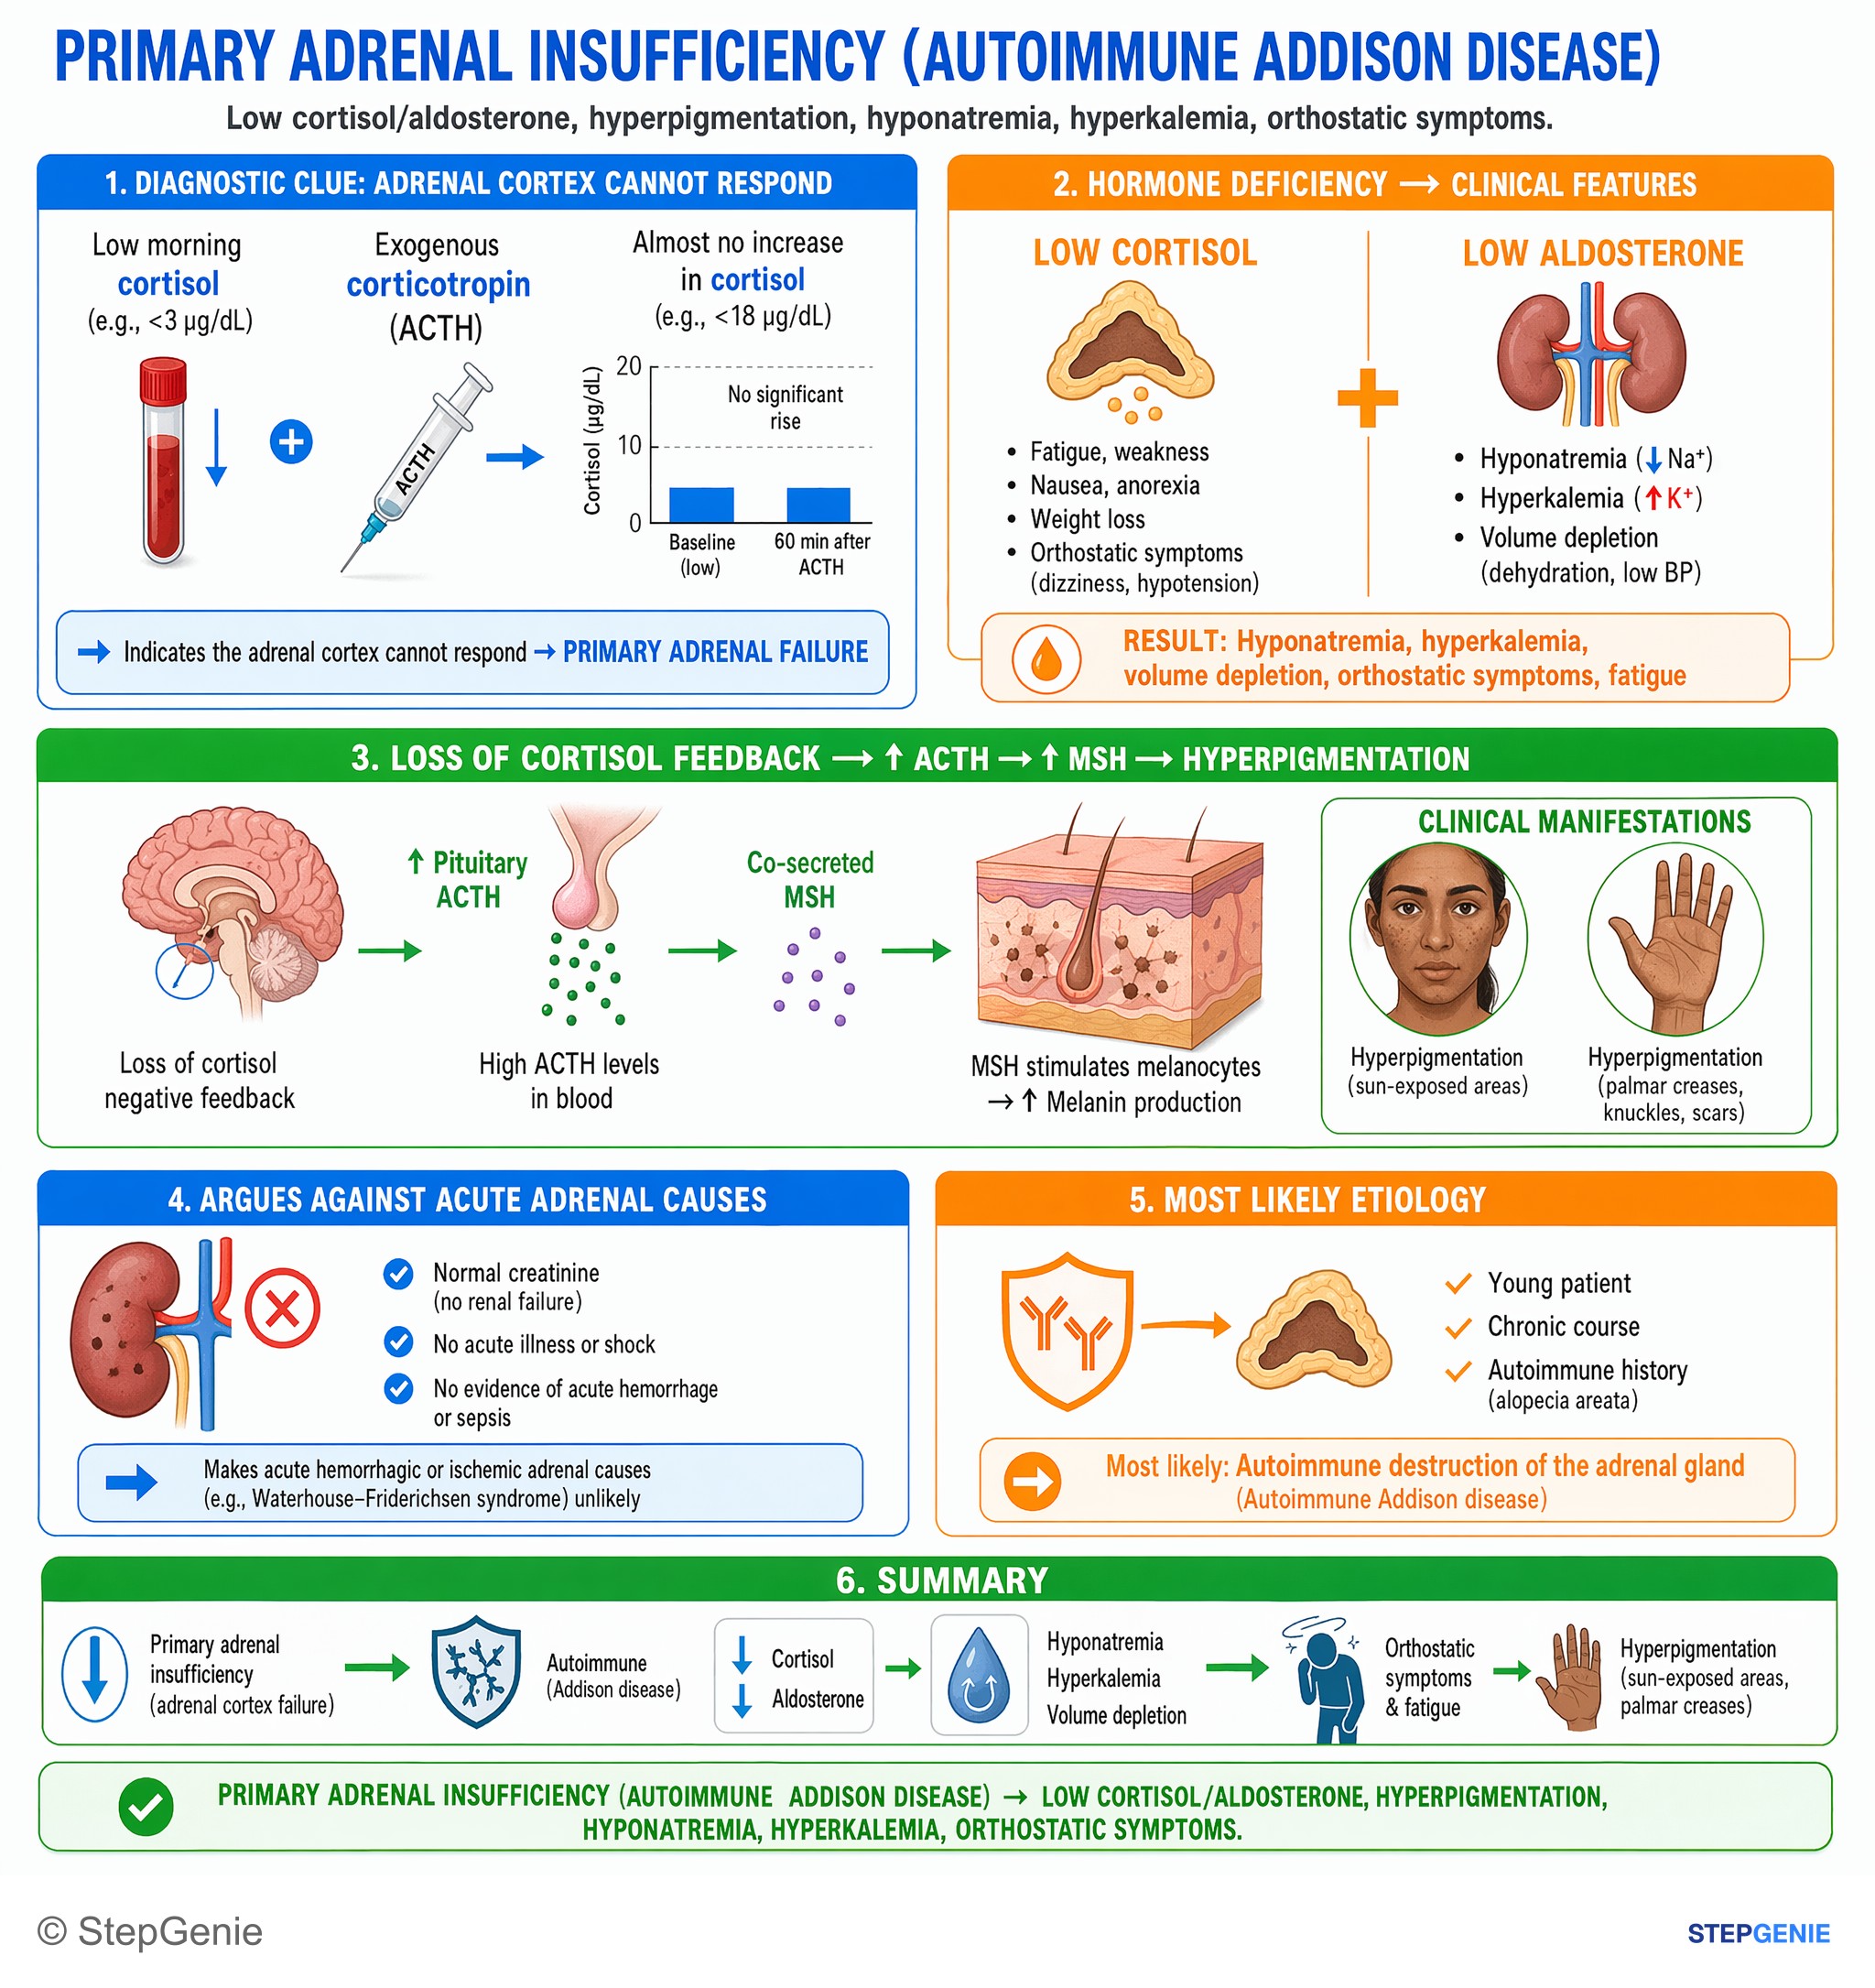
Primary adrenal insufficiency (autoimmune Addison disease) → low cortisol/aldosterone, hyperpigmentation, hyponatremia, hyperkalemia…
USMLE Step 1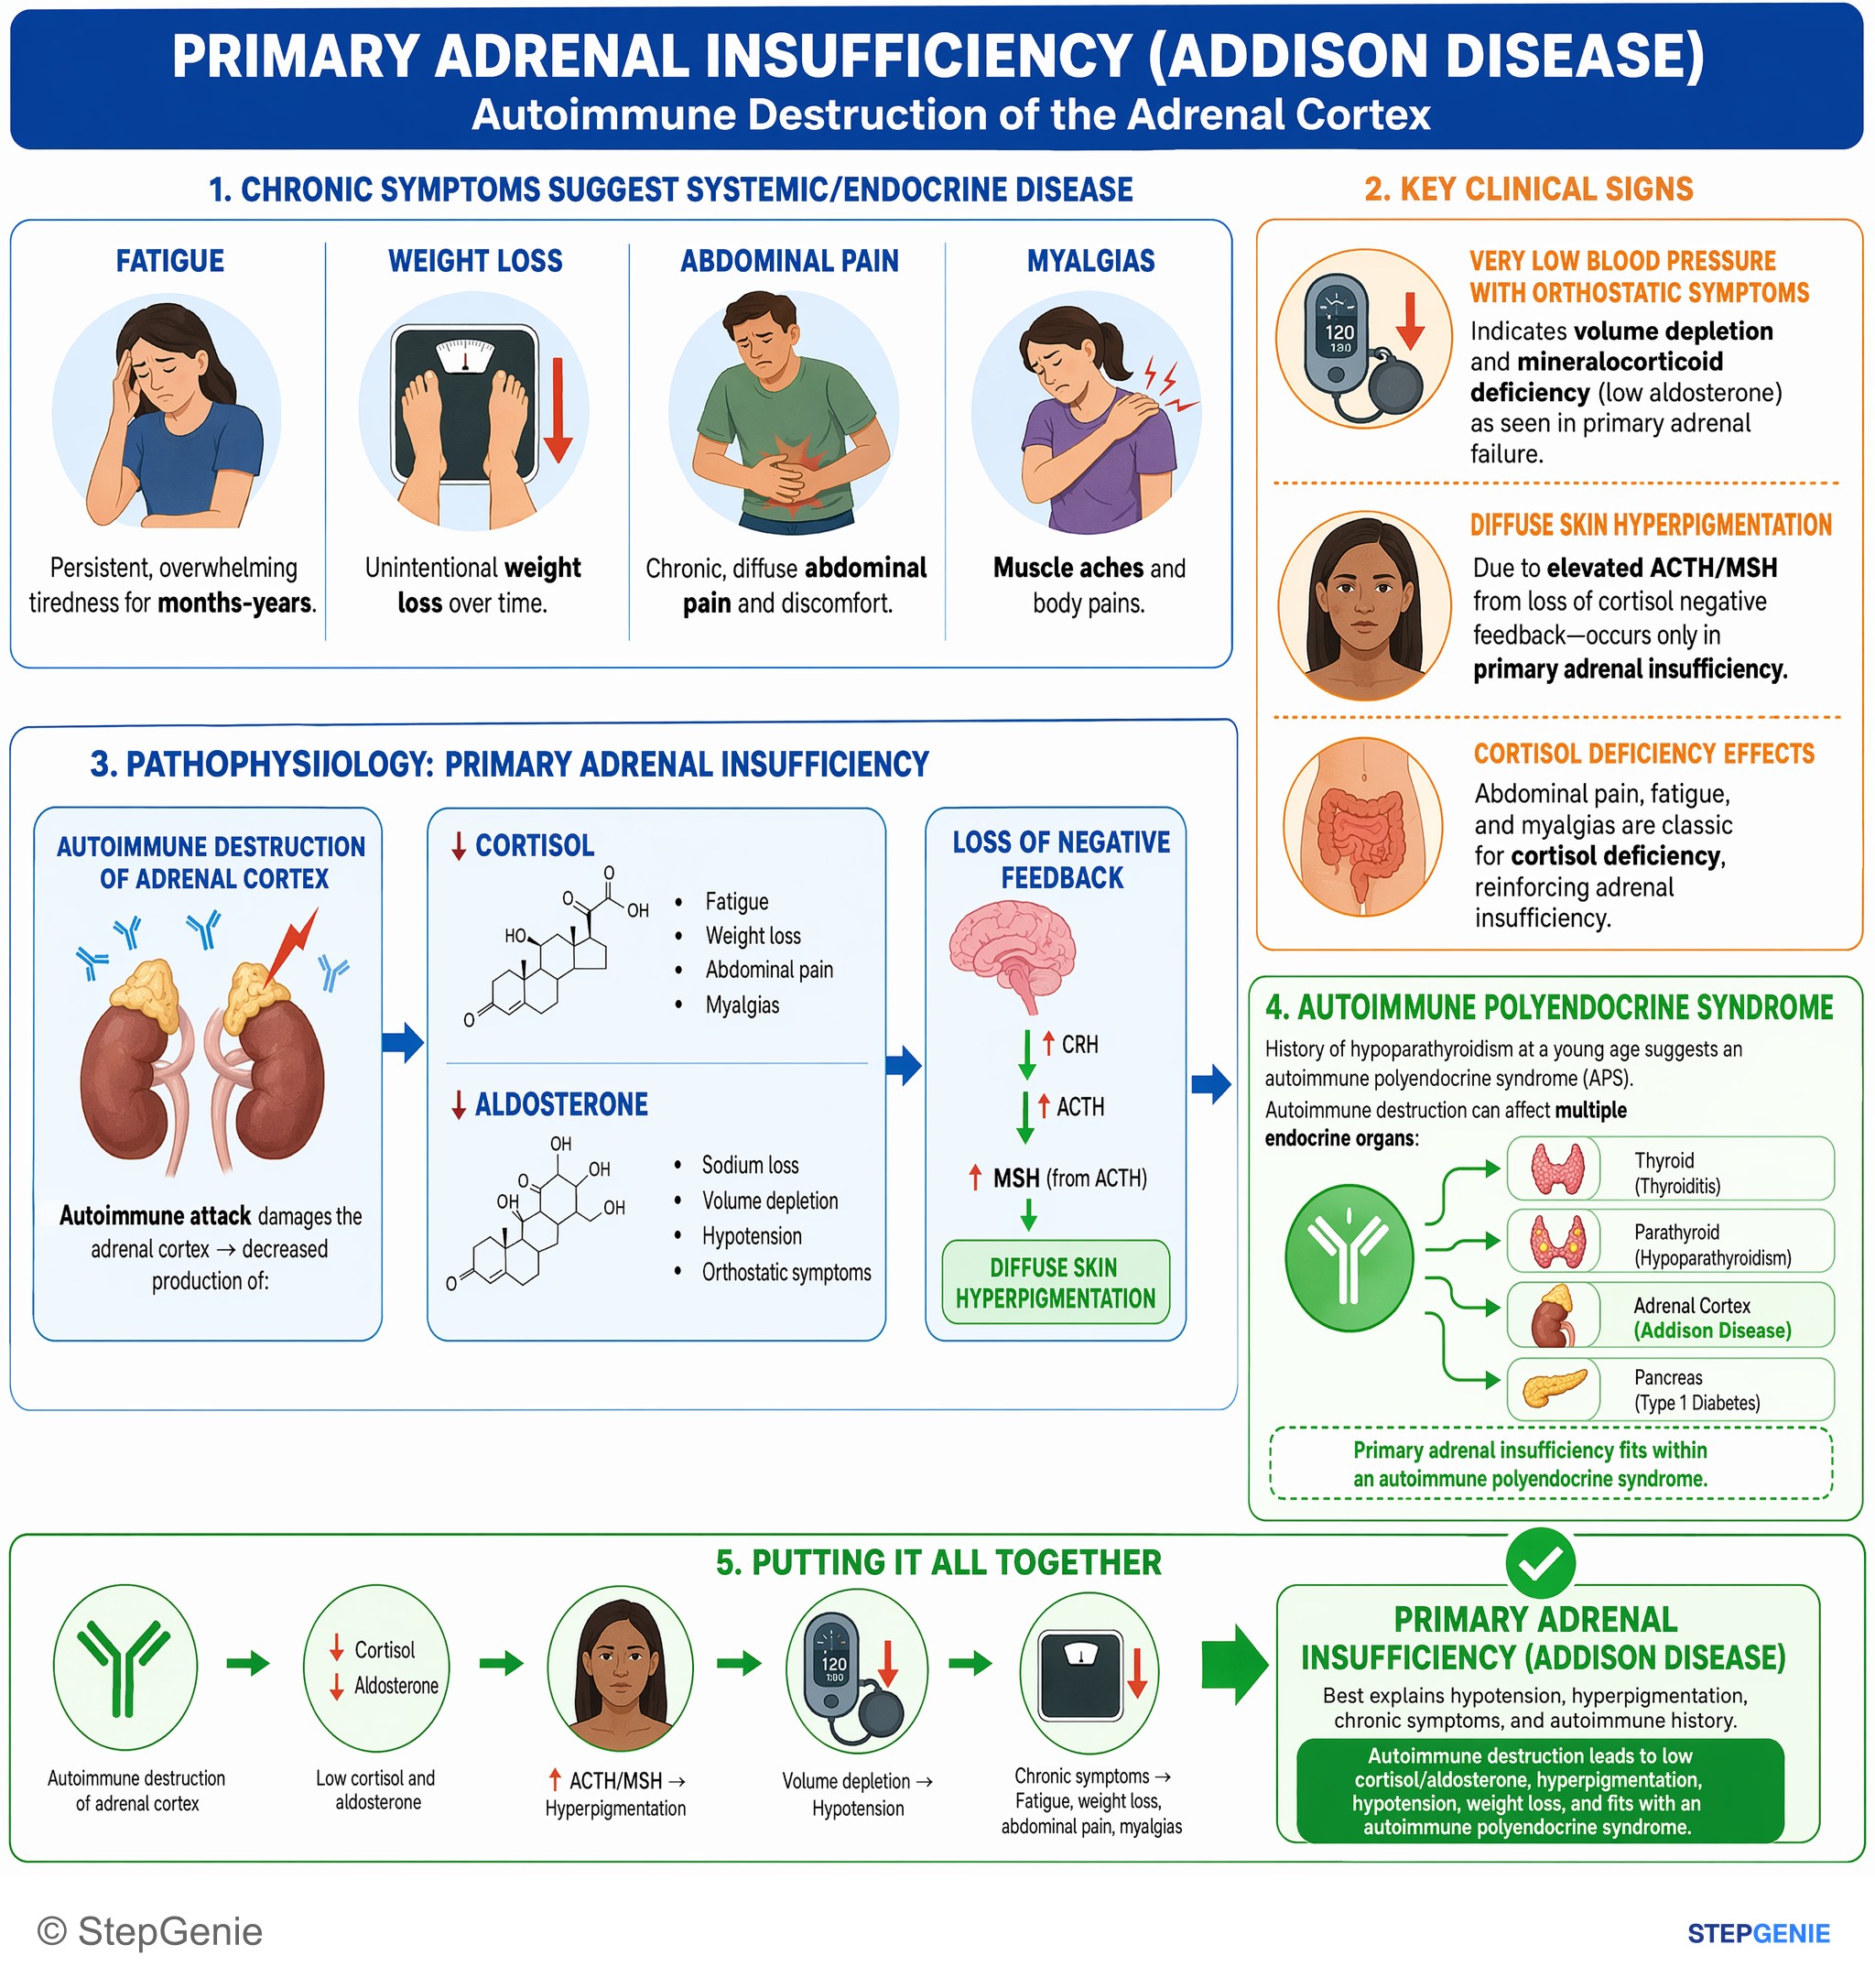
Primary adrenal insufficiency (Addison disease) from autoimmune destruction → low cortisol/aldosterone, hyperpigmentation, hypotension…
USMLE Step 1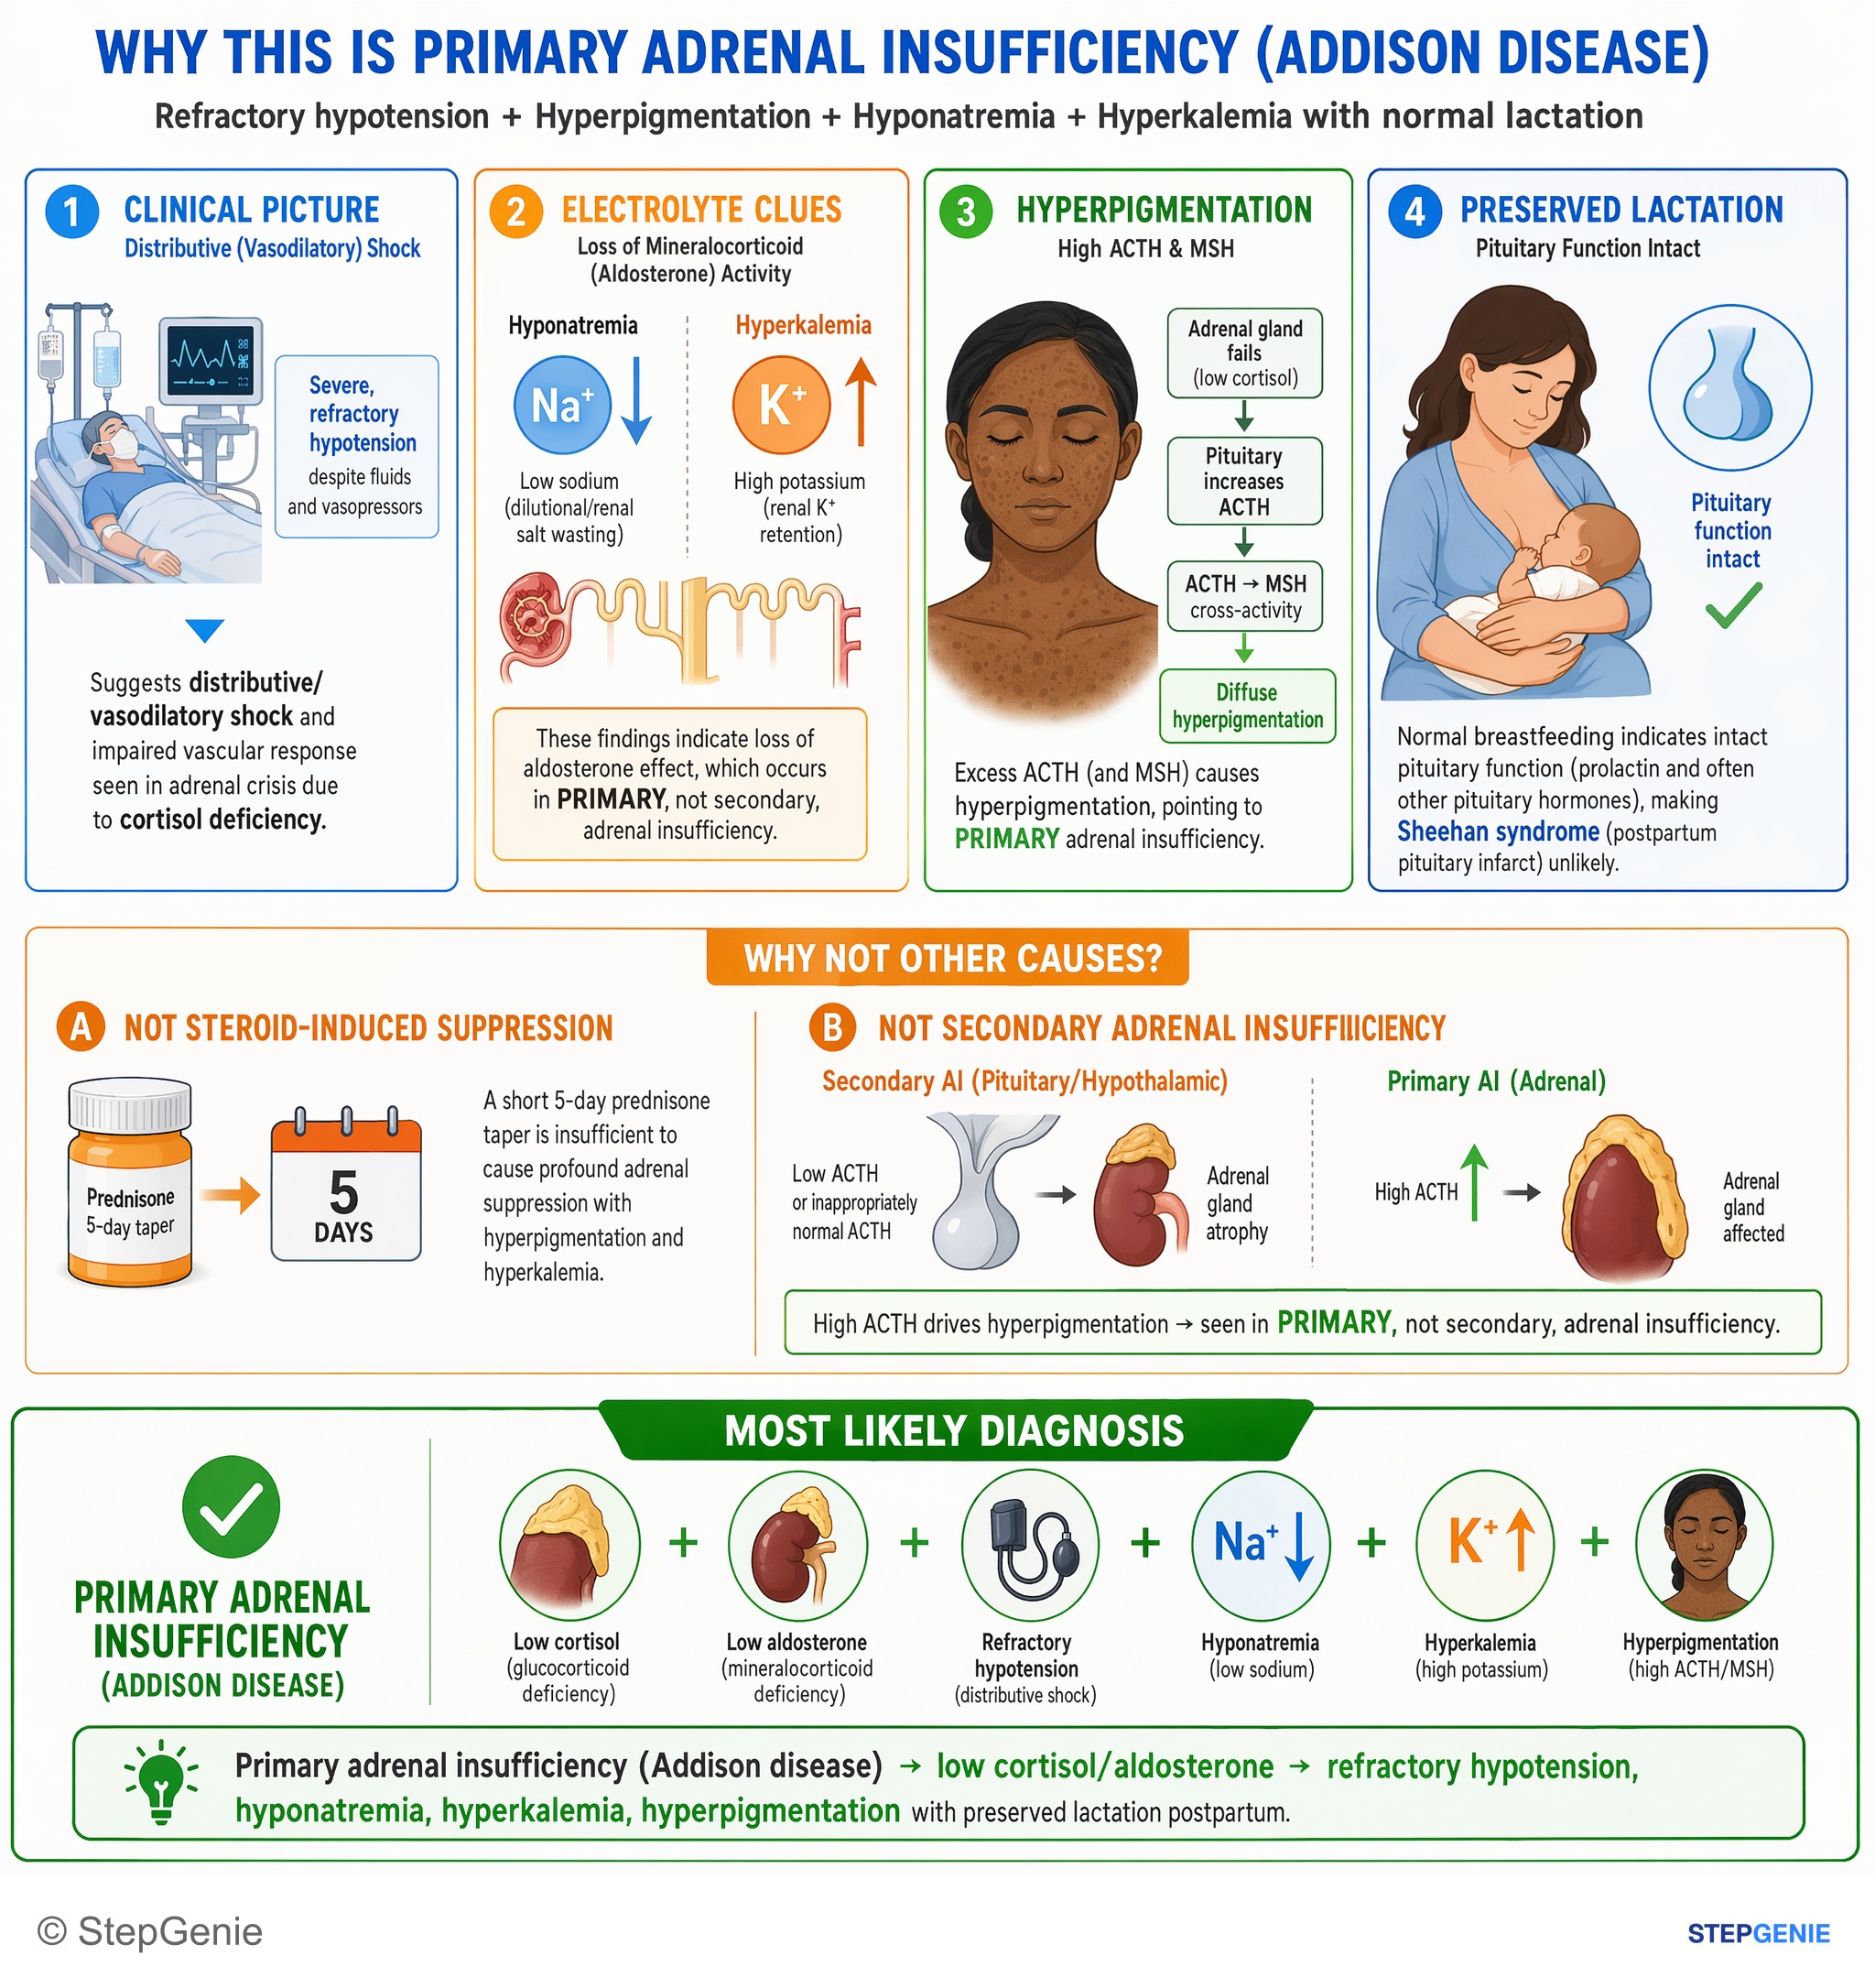
Primary adrenal insufficiency (Addison disease) → low cortisol/aldosterone → refractory hypotension, hyponatremia, hyperkalemia…
USMLE Step 2Frequently Asked Questions
What is the first-line treatment for suspected adrenal crisis in an unstable patient?
The first-line treatment is immediate IV hydrocortisone and IV normal saline. In suspected adrenal crisis, treatment comes before confirmatory testing because the patient can be hypotensive, hypoglycemic, and volume depleted. Hydrocortisone is preferred because stress doses provide both glucocorticoid and mineralocorticoid activity, and normal saline helps correct hypovolemia and shock. Dextrose is often added if hypoglycemia is present.
Why does primary adrenal insufficiency cause hyperpigmentation and hyperkalemia?
Primary adrenal insufficiency causes hyperpigmentation because low adrenal hormone output leads to high ACTH, which comes from POMC and increases melanocyte-stimulating activity. It causes hyperkalemia because aldosterone is low in primary adrenal insufficiency. That mineralocorticoid deficiency is a key clue favoring primary disease, whereas secondary adrenal insufficiency usually has a normal potassium level.
How do you tell adrenal crisis from myxedema coma on a vignette?
Adrenal crisis is suggested by hypotension, tachycardia, abdominal pain, hyperkalemia, hypoglycemia, and hyperpigmentation, while myxedema coma is suggested by hypothermia, bradycardia, hypoventilation, hyponatremia, and altered mental status. The distinction matters because adrenal crisis requires urgent steroids and fluids. If both hypothyroidism and adrenal insufficiency are possible, steroids should be given before thyroid hormone.
When should you do a cosyntropin stimulation test in adrenal insufficiency?
A cosyntropin stimulation test is appropriate in a stable patient with suspected chronic adrenal insufficiency, not as the first step in an unstable patient. It is useful for workup of symptoms like unexplained fatigue, hyponatremia, and weight loss. In primary adrenal insufficiency, cortisol is low and fails to rise after cosyntropin, with a high ACTH level.
What clues point to primary adrenal insufficiency with acute adrenal crisis instead of chronic Addison disease alone?
Primary adrenal insufficiency with acute adrenal crisis is suggested by shock or severe hypotension, GI symptoms such as abdominal pain and nausea, hypoglycemia, and a recent trigger like vomiting with poor oral intake. Chronic primary adrenal insufficiency more often presents gradually with fatigue, weight loss, salt craving, hyperpigmentation, orthostatic hypotension, and hyponatremia with hyperkalemia. Acute illness or volume depletion can precipitate the crisis.