Primary hyperaldosteronism (primary aldosteronism, also called Conn syndrome) is autonomous aldosterone secretion by the adrenal cortex, so aldosterone is high while renin is suppressed. The result is hypertension, sometimes with hypokalemia and metabolic alkalosis, but fewer than 30% of patients have a low potassium. About 60% of cases are bilateral adrenal hyperplasia and about 30% a unilateral aldosterone-producing adenoma (StatPearls). The 2025 Endocrine Society guideline suggests screening everyone with hypertension with plasma aldosterone and renin; unilateral disease is treated with adrenalectomy, and bilateral disease with a mineralocorticoid receptor antagonist, preferably spironolactone.
Why the labs look the way they do
Aldosterone is made in the zona glomerulosa. Its secretion is driven by the renin-angiotensin system and only to a lesser extent by ACTH (Merck); in primary disease it escapes that control.
| Aldosterone action | Where | Result |
|---|---|---|
| More ENaC channels and Na⁺/K⁺-ATPase | Principal cells | Na⁺ retention → volume expansion → hypertension |
| K⁺ leaves the cell into the lumen | Principal cells | Hypokalemia (when sodium intake is adequate) |
| More apical H⁺-ATPase | α-intercalated cells | H⁺ excretion → metabolic alkalosis |
| Volume expansion feeds back on the kidney | Juxtaglomerular cells | Suppressed renin, the hallmark of the diagnosis |
- Edema is uncommon despite sodium retention (Merck), so the picture is hypertension without swelling.
- Potassium is often normal. StatPearls: fewer than 30% of confirmed cases have a low potassium; it is more likely with a high salt intake, which delivers more sodium to the collecting duct for exchange with K⁺.
- The alkalosis is chloride-resistant: urine chloride is high, and saline does not correct it (see metabolic alkalosis and urine chloride). For the whole hormone cascade, see the RAAS breakdown.
How common it is, and its causes
- Prevalence (2025 guideline): 5-14% of people with hypertension seen in primary care and up to 30% in referral centers, with higher rates in resistant hypertension and in hypertension with hypokalemia. PA raises the risk of stroke, coronary artery disease, atrial fibrillation, heart failure and kidney disease (Endocrine Society).
- Bilateral adrenal hyperplasia: about 60% (treated medically).
- Unilateral aldosterone-producing adenoma: about 30% (potentially curable by surgery).
- Rare causes: aldosterone-producing adrenal carcinoma, ectopic secretion and familial forms. Familial hyperaldosteronism type I comes from a chimeric CYP11B1/CYP11B2 gene and is glucocorticoid-remediable; type III involves the KCNJ5 potassium channel gene (StatPearls). The guideline recommends genetic testing for patients diagnosed before age 20 and for first-degree relatives of people with familial disease.
Clinical picture
- Hypertension, often resistant to several drugs; Merck describes diastolic hypertension as common.
- Symptoms of hypokalemia, when present: fatigue, weakness, paresthesias, transient paralysis, tetany, and polyuria and polydipsia from hypokalemic nephropathy (nephrogenic diabetes insipidus).
- ECG in hypokalemia: ST-segment sagging, T-wave depression and prominent U waves (Merck; see hypokalemia vs hyperkalemia).
- Labs: ↑ aldosterone, ↓ renin, ↓ or normal K⁺, ↑ or normal HCO₃⁻.
Diagnosis: the 2025 Endocrine Society approach
The guideline (Adler et al., J Clin Endocrinol Metab, July 2025) replaced the 2016 version and widened screening.
1. Screen everyone with hypertension. Draw plasma aldosterone and renin (plasma renin activity, PRA, or direct renin concentration, DRC) in the morning with the patient seated, without dietary salt restriction in the days before. Measure potassium too: hypokalemia can falsely lower aldosterone, so a negative screen in a patient with hypokalemia is repeated after potassium is corrected. A positive screen needs suppressed renin plus aldosterone that is inappropriately high:
| Measure | Positive-screen threshold (2025) |
|---|---|
| Renin | PRA ≤ 1 ng/mL/h or DRC ≤ 8.2 mU/L |
| Aldosterone | ≥ 10 ng/dL by immunoassay (≥ 7.5 ng/dL by LC-MS/MS) |
| Aldosterone-to-renin ratio (ARR) | > 20 (aldosterone in ng/dL ÷ PRA in ng/mL/h), or > 70 (aldosterone in pmol/L ÷ DRC in mU/L); about 25% lower by LC-MS/MS |
Medications: the guideline outlines minimal-withdrawal and no-withdrawal strategies, chosen by safety and feasibility. Drugs that raise renin or lower aldosterone (MR antagonists, ENaC inhibitors such as amiloride and triamterene, other diuretics, ACE inhibitors, ARBs) can cause false negatives: if the screen is negative on them, repeat it on another day after stopping them if safe and feasible (4 weeks for MRAs, ENaC inhibitors and other diuretics; 2 weeks for ACE inhibitors and ARBs). Beta-blockers and central α₂-agonists (clonidine, methyldopa) lower renin and can cause false positives. Merck's ideal is still to stop renin-active drugs (thiazides, ACE inhibitors, ARBs, beta-blockers) for 4-6 weeks before testing.
2. Confirm only when it changes the plan. Suppression testing (IV saline infusion, oral salt loading, fludrocortisone or captopril challenge) shows that aldosterone fails to suppress. The 2025 guideline suggests it mainly when the probability of lateralizing disease is intermediate and the patient wants to pursue surgery. It can be skipped with overt renin-independent aldosterone excess, when the patient won't consider surgery, with familial hyperaldosteronism, or when lateralization is very unlikely.
3. Find the side, but only in surgical candidates. The guideline suggests CT plus adrenal venous sampling (AVS), which measures aldosterone and cortisol from each adrenal vein. Its example of when AVS may be unnecessary is a patient younger than 35 with marked PA, hypokalemia and a unilateral adenoma over 1 cm on CT. A CT nodule alone does not prove which gland is the source (see adrenal incidentaloma workup).
4. Check for cortisol too. If PA comes with an adrenal adenoma, the guideline suggests a dexamethasone suppression test, because some adenomas also secrete cortisol.
Treatment
- The 2025 guideline suggests PA-specific therapy for everyone with PA, medical or surgical, chosen by lateralization.
- Unilateral disease: total unilateral adrenalectomy, usually laparoscopic. After an adenoma is removed, potassium normalizes and blood pressure falls in all patients, and 50-70% need no antihypertensive drugs at all (Merck).
- Bilateral or unlateralized disease, or no surgery: lifelong MR antagonist. The guideline suggests spironolactone over other MRAs (low cost, wide availability; all MRAs work similarly at equivalent potency), MRAs rather than ENaC inhibitors, and raising the dose until renin rises if blood pressure stays high with suppressed renin.
- Spironolactone side effects: dose-related gynecomastia; eplerenone and amiloride have fewer of these sex-hormone effects (see potassium-sparing diuretics).
- Familial hyperaldosteronism type I is glucocorticoid-remediable.
Look-alikes: sort them by renin and aldosterone
| Condition | Renin | Aldosterone | Key clue | Treatment |
|---|---|---|---|---|
| Primary aldosteronism | ↓ | ↑ | Adrenal source; high ARR | Adrenalectomy or MR antagonist |
| Secondary aldosteronism | ↑ | ↑ | Renal artery stenosis or renin-secreting tumor (hypertensive); heart failure or cirrhosis with ascites (edematous) | Treat the cause |
| Liddle syndrome | ↓ | ↓ | Autosomal dominant ENaC gain of function; early-onset hypertension | Amiloride or triamterene; spironolactone is ineffective |
| Licorice (glycyrrhizin) | ↓ | ↓ | Blocks cortisol inactivation, so cortisol acts as a mineralocorticoid | Stop the licorice |
| Cushing syndrome | ↓ | ↓ | Cortisol excess features | Treat the cortisol source |
Merck: low renin with low aldosterone means a non-aldosterone mineralocorticoid excess (licorice, Cushing syndrome or Liddle syndrome). For the wider differential, see essential vs secondary hypertension.
Practice question
A 44-year-old man has a blood pressure of 164/98 mm Hg despite three antihypertensive drugs. Serum potassium is 3.0 mEq/L and bicarbonate 31 mEq/L. Morning plasma aldosterone is 28 ng/dL and plasma renin activity is below 0.2 ng/mL/h. CT shows a 1.6-cm left adrenal nodule and a normal right adrenal gland. He says he would choose surgery if it could cure his hypertension. Which is the most appropriate next step?
A. Adrenal venous sampling B. Laparoscopic left adrenalectomy C. Renal artery duplex ultrasonography D. Spironolactone with no further testing E. Saline infusion suppression test
Answer: A. Suppressed renin, an aldosterone well above 10 ng/dL and spontaneous hypokalemia make this overt primary aldosteronism. He is a surgical candidate, so the question is which gland is the source. The 2025 guideline suggests CT plus adrenal venous sampling for patients considering surgery; its example of a patient who might skip AVS is someone younger than 35 with marked PA, hypokalemia and a unilateral adenoma over 1 cm.
- B: at 44 he does not fit that exception, and a CT nodule does not prove the left gland makes the aldosterone; operating on CT alone risks removing the wrong gland or missing bilateral disease.
- C: renovascular disease causes secondary aldosteronism with high renin; his renin is suppressed.
- D: lifelong spironolactone is right for bilateral disease or for patients who decline surgery, but he wants a possible cure.
- E: confirmatory testing can be skipped when renin-independent aldosterone excess is overt, as here.
Key takeaways
- High aldosterone + low renin + hypertension = primary aldosteronism; hypokalemia is a bonus finding, present in fewer than 30%.
- About 60% bilateral hyperplasia (medical therapy), about 30% unilateral adenoma (surgery).
- 2025 Endocrine Society: screen everyone with hypertension; a positive screen is suppressed renin (PRA ≤ 1 ng/mL/h) with aldosterone ≥ 10 ng/dL and an ARR > 20.
- Confirmatory testing only when it changes management; CT + AVS before surgery (possible exception: age < 35 with marked PA, hypokalemia and a unilateral adenoma over 1 cm).
- Spironolactone is the preferred MRA; titrate until renin rises; gynecomastia → consider eplerenone.
- Low renin + low aldosterone = Liddle syndrome, licorice or Cushing syndrome; high renin + high aldosterone = secondary aldosteronism.
Sources
- Primary Aldosteronism: An Endocrine Society Clinical Practice Guideline — The Journal of Clinical Endocrinology & Metabolism (2025)
- Endocrine Society guideline calls for increased screening for common cause of high blood pressure — Endocrine Society (2025)
- Primary Aldosteronism — Merck Manual Professional Edition (2026)
- Hyperaldosteronism — StatPearls, NCBI Bookshelf (2025)
- Physiology, Aldosterone — StatPearls, NCBI Bookshelf (2023)
- Liddle Syndrome — Merck Manual Professional Edition (2026)
- Metabolic Alkalosis — Merck Manual Professional Edition (2025)
- Hypokalemia — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
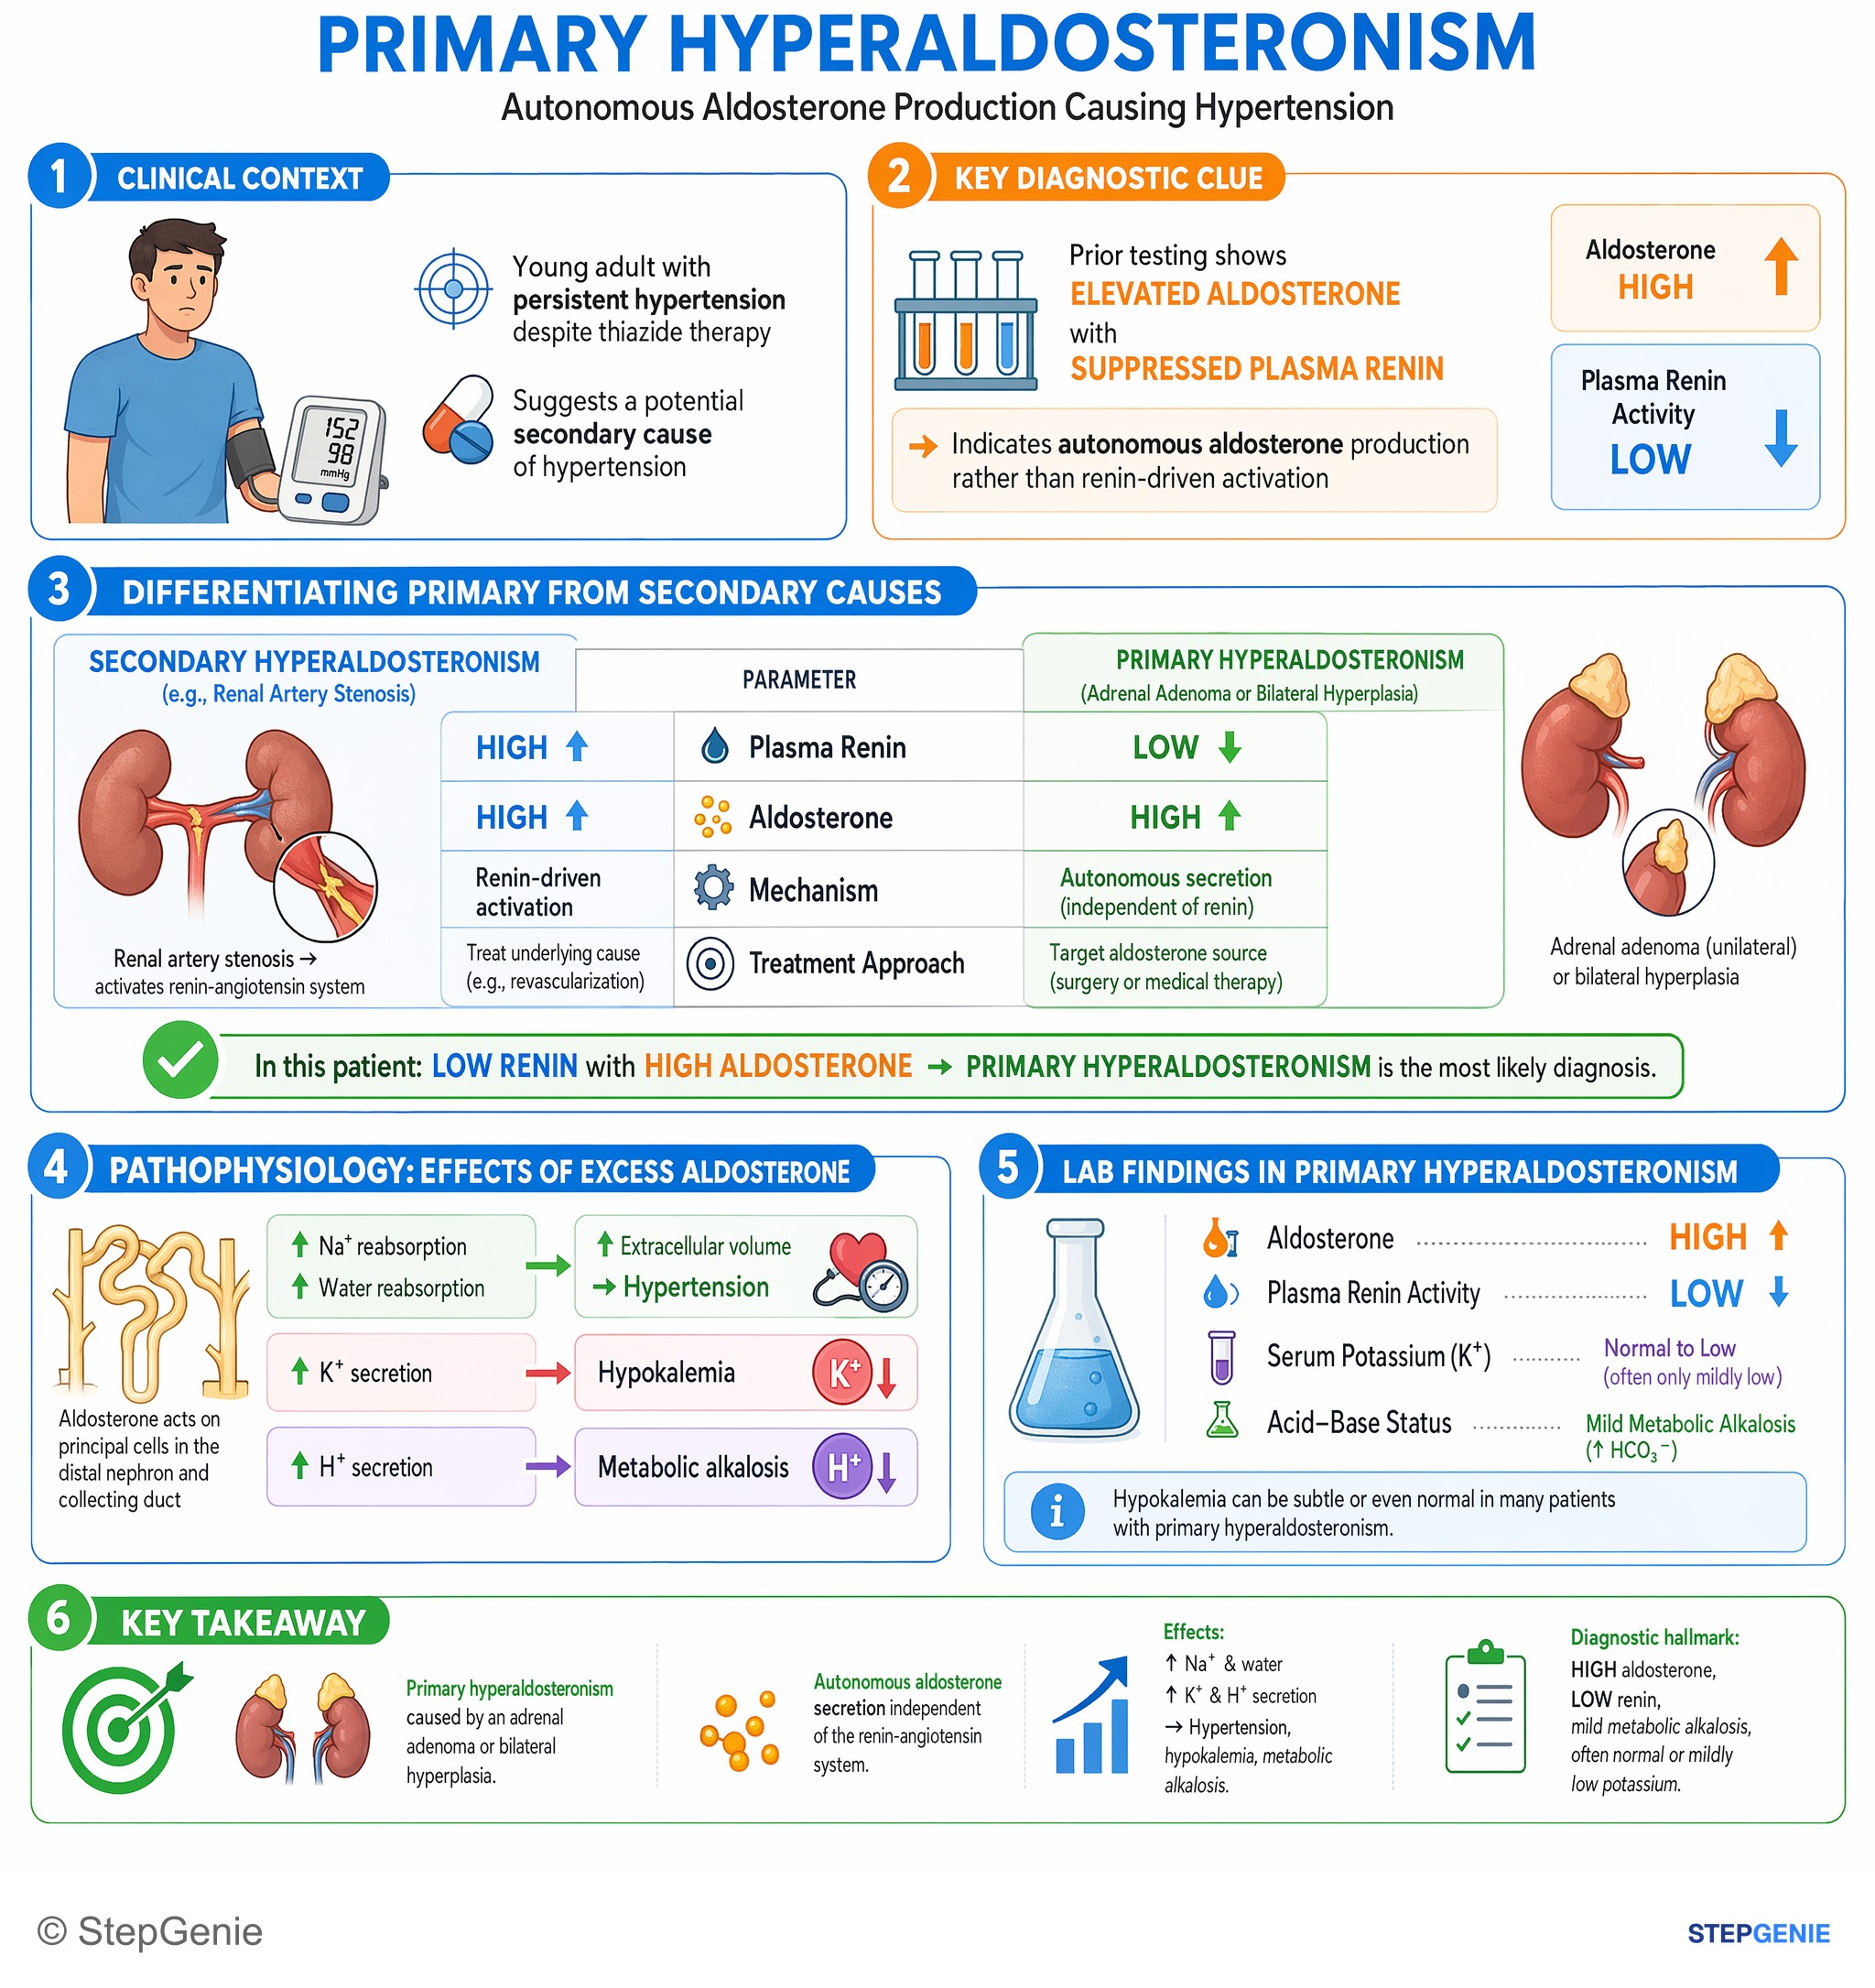
Primary hyperaldosteronism: autonomous aldosterone → hypertension with high aldosterone, low renin, mild metabolic alkalosis, often only…
USMLE Step 1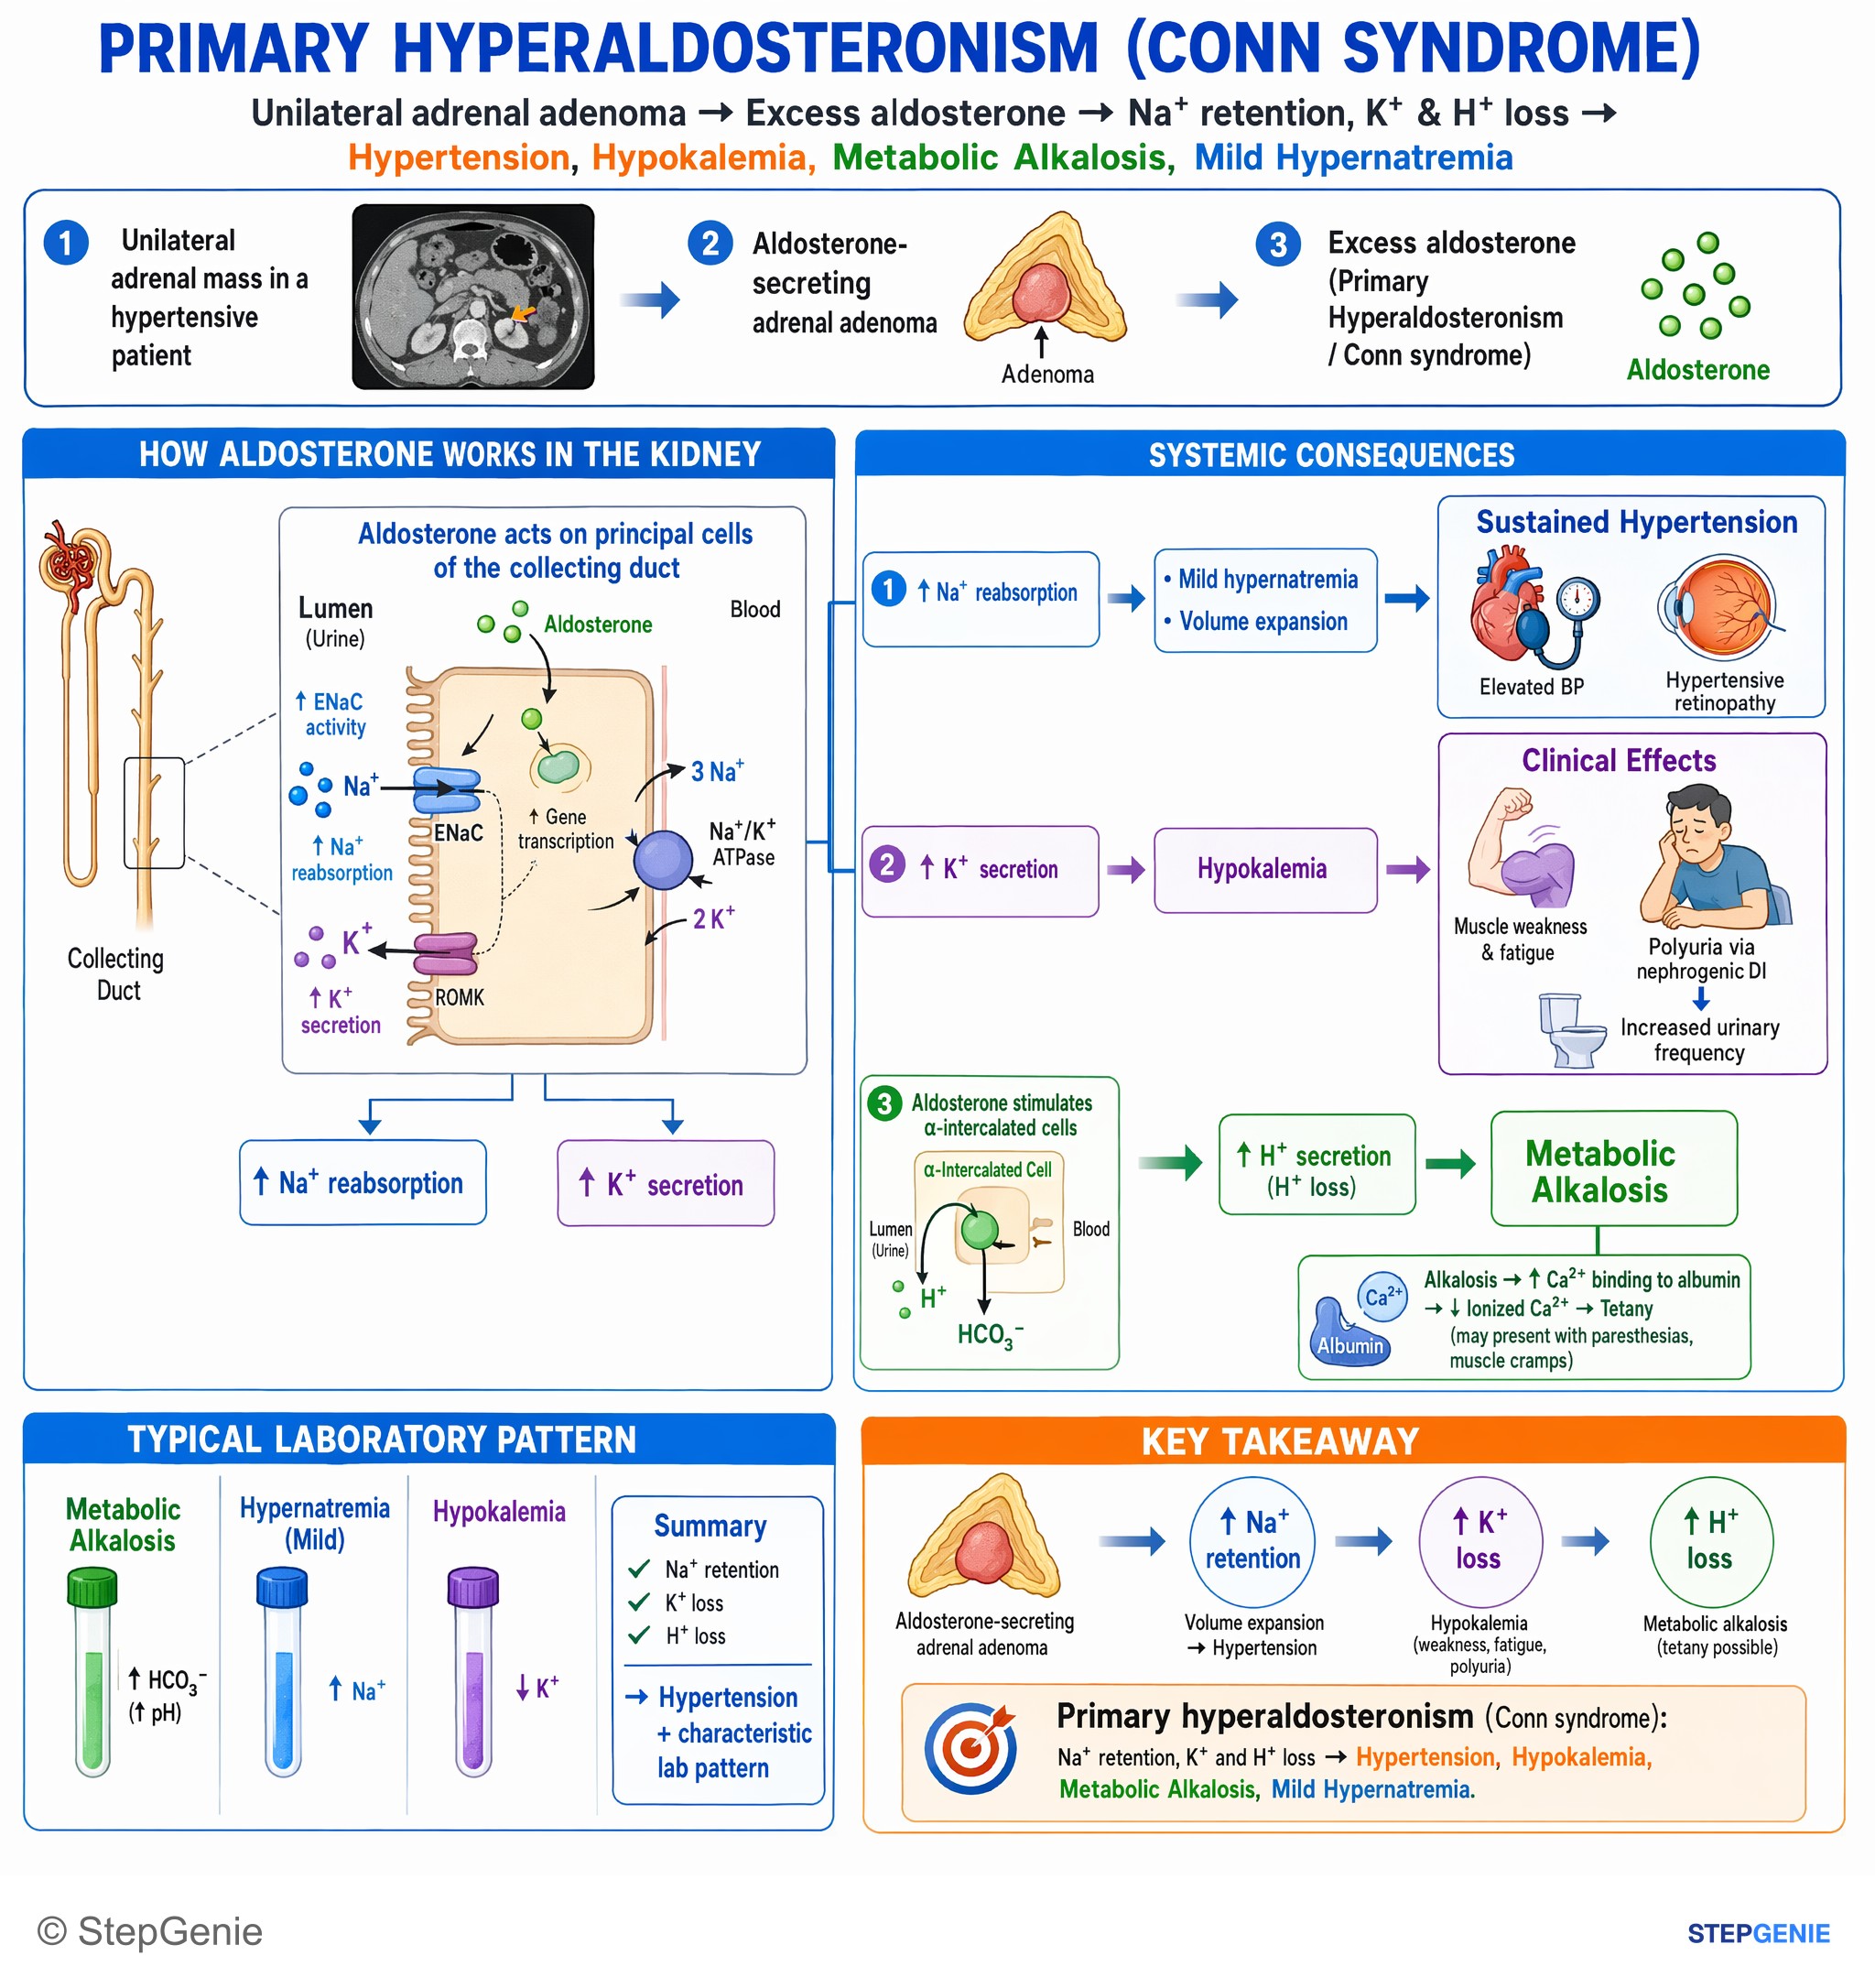
Primary hyperaldosteronism (Conn syndrome) from adrenal adenoma → Na⁺ retention, K⁺ and H⁺ loss → hypertension, hypokalemia, metabolic…
USMLE Step 1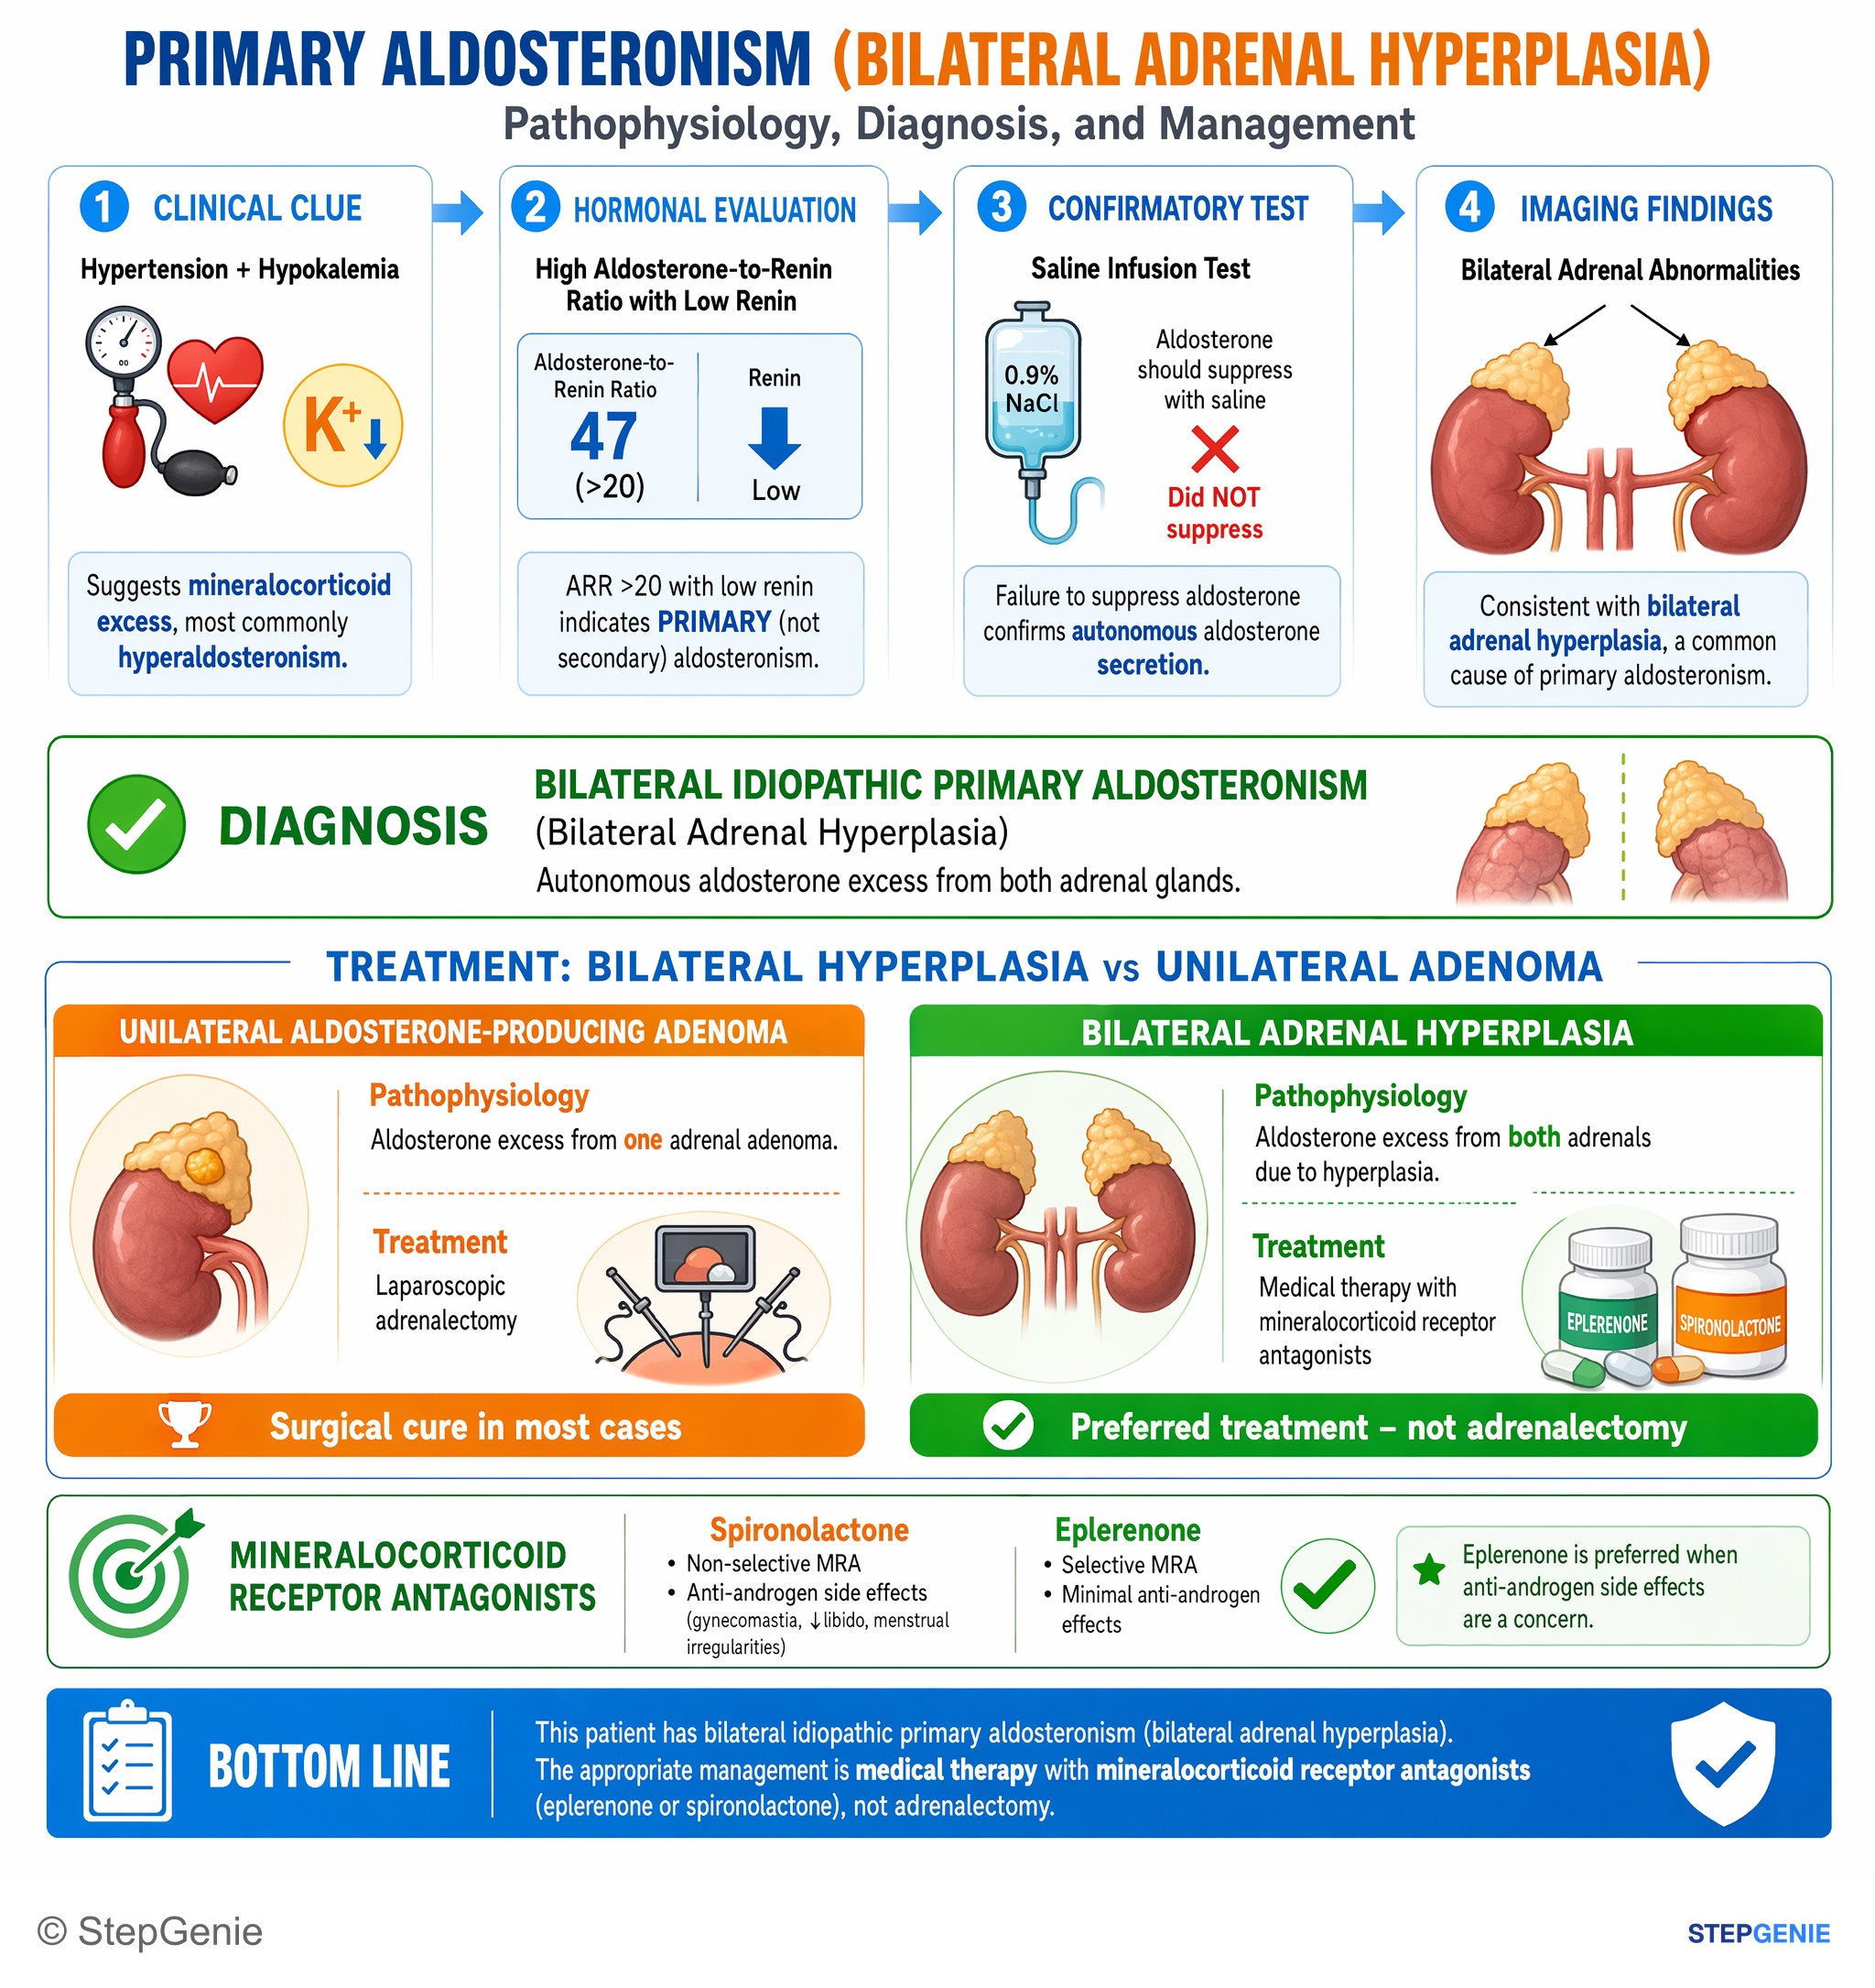
Bilateral idiopathic primary aldosteronism → treat with mineralocorticoid receptor antagonists (eplerenone/spironolactone), not…
USMLE Step 2Frequently Asked Questions
What is the difference between primary and secondary hyperaldosteronism?
In primary hyperaldosteronism the adrenal glands make aldosterone on their own, and the expanded volume suppresses renin, so aldosterone is high and renin is low. In secondary hyperaldosteronism something outside the adrenal raises renin first, such as renal artery stenosis, a renin-secreting tumor, heart failure or cirrhosis with ascites, so both renin and aldosterone are high. Both can cause hypokalemia, so the renin level is what separates them.
Who should be screened for primary aldosteronism?
The 2025 Endocrine Society guideline suggests screening everyone with hypertension, not only people with hypokalemia or resistant hypertension. Primary aldosteronism is found in an estimated 5 to 14% of people with high blood pressure seen in primary care and up to 30% in referral centers. Screening uses a morning plasma aldosterone and renin, with potassium measured alongside because a low potassium can falsely lower aldosterone; a positive screen shows suppressed renin with an inappropriately high aldosterone.
What aldosterone-to-renin ratio indicates primary aldosteronism?
In the 2025 Endocrine Society guideline, a positive screen has suppressed renin (plasma renin activity of 1 ng/mL/h or less, or direct renin concentration of 8.2 mU/L or less), aldosterone of at least 10 ng/dL by immunoassay, and an aldosterone-to-renin ratio above 20 when aldosterone is in ng/dL and renin activity in ng/mL/h. Some drugs shift the result: diuretics, MR antagonists, ACE inhibitors and ARBs can cause false negatives, and beta-blockers can cause false positives.
Can you have primary aldosteronism with normal potassium?
Yes. According to StatPearls, fewer than 30% of people with confirmed primary aldosteronism have a low potassium, so a normal potassium does not rule it out. Hypokalemia is more likely when salt intake is high, because more sodium reaches the collecting duct to be exchanged for potassium. Screening therefore relies on plasma aldosterone and renin rather than on the potassium level, and the 2025 guideline suggests it for everyone with hypertension.
How is primary aldosteronism treated?
Treatment depends on whether one or both adrenal glands are the source. A unilateral aldosterone-producing adenoma is removed by laparoscopic adrenalectomy; afterward potassium normalizes and blood pressure falls, and 50 to 70% of patients need no antihypertensive drugs (Merck). Bilateral disease, or disease in patients who decline surgery, is treated with a lifelong mineralocorticoid receptor antagonist; the 2025 guideline prefers spironolactone and suggests increasing the dose to raise renin if blood pressure stays high with renin still suppressed.
Why is adrenal venous sampling needed before surgery for primary aldosteronism?
CT can show an adrenal nodule, but a nodule does not prove that gland makes the excess aldosterone, and bilateral disease is treated with medication rather than surgery. Adrenal venous sampling measures aldosterone and cortisol in blood from each adrenal vein to show which side is the source. The 2025 Endocrine Society guideline suggests CT plus sampling for patients considering surgery; its example of when sampling may be unnecessary is a patient younger than 35 with marked disease, hypokalemia and a unilateral adenoma over 1 cm.