Cushing syndrome is the clinical picture of chronic glucocorticoid excess from any cause, and the most common cause overall is prescribed glucocorticoids. Cushing disease is one specific cause: an ACTH-secreting pituitary adenoma, which accounts for about 8 in 10 cases of endogenous Cushing syndrome. Prove hypercortisolism with two abnormal screening tests (late-night salivary cortisol, 24-hour urinary free cortisol, 1-mg overnight dexamethasone suppression test), then let plasma ACTH split ACTH-independent (adrenal) from ACTH-dependent (pituitary vs ectopic) disease. Pituitary MRI, stimulation tests and inferior petrosal sinus sampling (IPSS) localize the source, and surgery that removes it is first-line.
Syndrome vs disease at a glance
| Cushing syndrome | Cushing disease | |
|---|---|---|
| Meaning | Signs and symptoms of chronic cortisol (or glucocorticoid) excess, any cause | Cushing syndrome caused by a pituitary corticotroph adenoma secreting ACTH |
| Most common cause | Exogenous glucocorticoids | It is the most common endogenous cause |
| ACTH | Low with steroids or an adrenal tumor; high with pituitary or ectopic sources | Normal or high (not suppressed) |
| Adrenals | Atrophic, a unilateral mass, or bilateral hyperplasia, depending on cause | Bilateral hyperplasia |
| First-line treatment | Remove or stop the cause | Transsphenoidal adenomectomy |
Causes and their ACTH signature
| Group | Causes | ACTH |
|---|---|---|
| Exogenous (most common overall) | Glucocorticoid drugs | ↓, with bilateral adrenal atrophy |
| ACTH-dependent: 80-85% of endogenous cases | Cushing disease (most of these); ectopic ACTH from small cell lung cancer or neuroendocrine tumors such as bronchial carcinoid | Normal or ↑ in Cushing disease; ↑ or ↑↑ when ectopic |
| ACTH-independent: 15-20% of endogenous cases | Adrenal adenoma or carcinoma; bilateral macronodular hyperplasia (older adults); primary pigmented nodular adrenal disease (adolescents) | ↓ (suppressed by cortisol feedback) |
Endogenous Cushing syndrome is rare (about 40-70 per million), most often affects adults aged 30-50 and affects about three times as many women as men (NIDDK).
What cortisol excess does
- Body habitus: moon face with plethora, central obesity, buffalo hump, thin limbs.
- Skin: thin skin, easy bruising, poor wound healing, wide reddish-purple striae.
- Muscle and bone: proximal myopathy, osteoporosis, kidney stones.
- Metabolic and cardiovascular: glucose intolerance or diabetes (gluconeogenesis), hypertension, raised clot and infection risk.
- Brain: depression, irritability, psychosis, memory problems.
- Reproductive: menstrual irregularity; virilization in women with adrenal tumors (androgen co-secretion, classically carcinoma).
- Children: weight gain with falling growth velocity.
- ACTH-dependent clues: very high ACTH can cause hyperpigmentation (POMC also yields MSH), and the very high cortisol of ectopic ACTH overwhelms renal 11β-HSD2, activating mineralocorticoid receptors: hypokalemia, hypertension and metabolic alkalosis, often with rapid onset.
The Endocrine Society's best discriminators are easy bruising, facial plethora, proximal myopathy and striae (especially reddish-purple and over 1 cm wide), plus weight gain with slowing growth in children.
Step 1: prove hypercortisolism
First take a full drug history (oral, inhaled, topical, injected steroids). Then test; the Endocrine Society wants concordantly abnormal results on two different tests before hunting for a cause.
| Test | Abnormal result | Pitfalls |
|---|---|---|
| Late-night salivary cortisol (at least 2 nights) | Loss of the normal midnight nadir; cut-off assay-specific (e.g., > 145 ng/dL) | Collect at the patient's usual bedtime; immunoassays are less specific than LC-MS/MS |
| 24-hour urinary free cortisol (at least 2 collections) | Above the assay's upper limit; > 4 times normal nearly confirms it | Mild rises in depression, alcohol use disorder, severe obesity and poorly controlled diabetes; incomplete collections |
| 1-mg overnight dexamethasone suppression test (1 mg at 11 PM-midnight, cortisol at 8-9 AM) | Cortisol > 1.8 mcg/dL (50 nmol/L) | Oral estrogens raise cortisol-binding globulin (false positives in about half of women on the pill); CYP3A4 inducers (phenytoin, carbamazepine, rifampin) speed dexamethasone clearance |
Pseudo-Cushing states (depression and other psychiatric disorders, alcohol use disorder, obesity, poorly controlled diabetes) can cause mild hypercortisolism and abnormal screening tests without a tumor. Adrenal incidentalomas are screened with the dexamethasone test; see the adrenal incidentaloma workup.
Step 2: plasma ACTH splits the differential
- ACTH ≤ 10 pg/mL → ACTH-independent → adrenal CT for adenoma, carcinoma or bilateral nodular disease.
- ACTH ≥ 20 pg/mL → ACTH-dependent → pituitary vs ectopic.
- 10-20 pg/mL is a gray zone that needs further testing (cut-offs from a 2026 JCEM review).
Step 3: pituitary or ectopic?
The logic: a corticotroph adenoma still partly obeys the axis; an ectopic tumor ignores it.
| Clue | Cushing disease (pituitary) | Ectopic ACTH |
|---|---|---|
| ACTH level | Normal or ↑ | ↑ or ↑↑ |
| High-dose dexamethasone (2 mg every 6 h for 48 h) | Cortisol suppresses by > 50% | No suppression |
| CRH or desmopressin stimulation | ACTH and cortisol rise | Flat (a rise is rare) |
| IPSS gradient after desmopressin or CRH | Central-to-peripheral ACTH ratio > 3 | No gradient |
| Imaging | Pituitary MRI (gadolinium); adenomas are often tiny | CT of chest and abdomen; somatostatin receptor (gallium-68 dotatate) PET |
| Tempo | Gradual | Often rapid, with hypokalemia |
Current practice vs exam lore: the high-dose dexamethasone test is the classic USMLE discriminator, but Merck notes that most centers have abandoned it because of suboptimal sensitivity and specificity. CRH is now hard to obtain, so desmopressin is often used instead. When the MRI shows no clear adenoma or the tests disagree, IPSS decides: a gradient over 3 virtually excludes ectopic ACTH.
The classic lab-pattern table
| Condition | ACTH | Low-dose dex | High-dose dex | Adrenal glands |
|---|---|---|---|---|
| Cushing disease | N or ↑ | No suppression | Suppresses | Bilateral hyperplasia |
| Ectopic ACTH | ↑ or ↑↑ | No suppression | No suppression | Bilateral hyperplasia |
| Adrenal adenoma or carcinoma | ↓ | No suppression | No suppression | Unilateral mass, contralateral atrophy |
| Exogenous glucocorticoids | ↓ | Not needed | Not needed | Bilateral atrophy |
With exogenous steroids, measured cortisol depends on the drug and assay (some synthetic glucocorticoids cross-react with immunoassays); history plus suppressed ACTH is the key.
Treatment by cause
- Cushing disease: transsphenoidal adenomectomy by an experienced surgeon; remission is about 80% for microadenomas and 60% for macroadenomas (AAFP). Postoperative low cortisol signals success and needs glucocorticoid replacement and adrenal-insufficiency education until the axis recovers. If disease persists: repeat surgery, radiation (effect can take years), medical therapy or bilateral adrenalectomy.
- Bilateral adrenalectomy means lifelong glucocorticoid and mineralocorticoid replacement, and in Cushing disease it risks Nelson syndrome (about 20-25%, per Merck): the corticotroph tumor grows, ACTH soars and severe hyperpigmentation follows, so MRI and ACTH are monitored.
- Adrenal adenoma: laparoscopic adrenalectomy, with perioperative glucocorticoid cover because the other adrenal is suppressed.
- Ectopic ACTH: remove the tumor; if it can't be removed, control cortisol with drugs (IV etomidate in emergencies) or bilateral adrenalectomy.
- Exogenous: taper gradually; stopping suddenly after HPA-axis suppression risks adrenal crisis.
- Treat comorbidities: hypertension, diabetes, osteoporosis, potassium, clot prevention.
Drugs and their US status (October 2026)
| Drug | How it works | FDA status |
|---|---|---|
| Osilodrostat (Isturisa) | Inhibits 11β-hydroxylase (CYP11B1) | Approved for endogenous hypercortisolemia in adults with Cushing syndrome when surgery is not an option or not curative (broadened from Cushing disease in April 2025). Watch for hypocortisolism, QTc prolongation, and precursor build-up (hypokalemia, hirsutism) |
| Levoketoconazole (Recorlev) | Steroidogenesis inhibitor | Approved for the same indication; boxed warning: hepatotoxicity and QT prolongation |
| Ketoconazole (oral) | Steroidogenesis inhibitor | Not FDA-approved for Cushing syndrome (off-label) |
| Metyrapone (Metopirone) | Inhibits 11β-hydroxylase | US label is diagnostic only (adrenal insufficiency testing); treatment use is off-label in the US, approved in Europe |
| Pasireotide (Signifor, Signifor LAR) | Somatostatin analog targeting SSTR5 on corticotroph tumors | Approved for Cushing disease when pituitary surgery is not an option or not curative; hyperglycemia is very common |
| Mifepristone (Korlym) | Glucocorticoid receptor antagonist | Approved to control hyperglycemia from endogenous Cushing syndrome in adults with type 2 diabetes or glucose intolerance who failed or can't have surgery. Boxed warning: termination of pregnancy. Cortisol stays high or even rises, so cortisol levels can't guide dosing or detect adrenal insufficiency |
| Cabergoline, etomidate, mitotane | Dopamine agonist; IV cortisol-synthesis blocker; adrenolytic | Off-label for Cushing syndrome |
How USMLE tests it
- Iatrogenic first: cushingoid patient on chronic prednisone = low ACTH, atrophic adrenals; the answer is a slow taper, not imaging.
- Smoker with rapid weight loss, hypokalemia, hypertension and hyperpigmentation = ectopic ACTH from small cell lung cancer (see paraneoplastic syndromes). Hypokalemic hypertension with low renin and a normal cortisol is primary hyperaldosteronism instead.
- Woman on an oral contraceptive with a "failed" 1-mg dexamethasone test may simply have high cortisol-binding globulin.
- Virilization plus Cushing features with low ACTH = adrenal carcinoma.
- Headache or bitemporal hemianopia is unusual in Cushing disease, because the tumor is usually small; compare other pituitary adenomas.
Practice question
A 34-year-old woman has 9 months of weight gain, easy bruising, wide purple abdominal striae, proximal muscle weakness, new hypertension and irregular menses. She takes no medications. Late-night salivary cortisol is raised on two nights, and 24-hour urinary free cortisol is 3 times the upper limit of normal. Morning plasma ACTH is 48 pg/mL. Gadolinium-enhanced pituitary MRI shows no adenoma. Which is the most appropriate next step?
A. Bilateral inferior petrosal sinus sampling B. CT of the adrenal glands C. Transsphenoidal pituitary exploration D. 1-mg overnight dexamethasone suppression test E. Bilateral adrenalectomy
Answer: A. Two concordant abnormal tests confirm Cushing syndrome, and an ACTH of 48 pg/mL makes it ACTH-dependent. A young woman with gradual onset most likely has Cushing disease, but the MRI is negative, so IPSS is needed: a central-to-peripheral ACTH ratio above 3 after desmopressin or CRH confirms a pituitary source (then transsphenoidal surgery); no gradient sends the search to an ectopic tumor.
- B: adrenal imaging is for ACTH-independent disease (ACTH ≤ 10 pg/mL). Here it would show only hyperplasia or a misleading incidental nodule.
- C: operating before the pituitary is proven to be the source risks a negative exploration in a patient with ectopic ACTH.
- D: screening is finished; another screening test cannot localize the source.
- E: bilateral adrenalectomy is a last-line treatment that cures the hypercortisolism but leaves the tumor, with lifelong adrenal insufficiency and a risk of Nelson syndrome.
Key takeaways
- Syndrome = cortisol excess from any cause; disease = pituitary ACTH adenoma, the most common endogenous cause.
- Exogenous steroids are the most common cause overall: low ACTH, bilateral adrenal atrophy, taper slowly.
- Screen with late-night salivary cortisol, 24-hour urinary free cortisol or a 1-mg dexamethasone test (cortisol > 1.8 mcg/dL); act on two concordant abnormal tests.
- ACTH ≤ 10 pg/mL = adrenal; ACTH ≥ 20 pg/mL = pituitary or ectopic.
- Pituitary vs ectopic: suppression on high-dose dexamethasone and a CRH or desmopressin response favor pituitary; IPSS gradient > 3 is the decider when MRI is negative.
- Hypokalemia, hyperpigmentation and rapid onset suggest ectopic ACTH (small cell lung cancer).
- First-line treatment is surgery; osilodrostat and levoketoconazole are FDA-approved for Cushing syndrome, pasireotide for Cushing disease, mifepristone for its hyperglycemia, and metyrapone and ketoconazole are off-label in the US.
Sources
- Cushing Syndrome — Merck Manual Professional Edition (2026)
- The Diagnosis of Cushing's Syndrome: An Endocrine Society Clinical Practice Guideline — Journal of Clinical Endocrinology & Metabolism (2008)
- Treatment of Cushing's Syndrome: An Endocrine Society Clinical Practice Guideline — Journal of Clinical Endocrinology & Metabolism (2015)
- Measuring cortisol in Cushing syndrome: diagnosis, monitoring, and cortisol circadian rhythm improvement — Journal of Clinical Endocrinology & Metabolism (2026)
- Update and Practical Recommendations for the Use of Medical Treatment of Cushing Syndrome — Endocrine Reviews (2026)
- Cushing's Syndrome: Rapid Evidence Review — American Family Physician (2024)
- Cushing's Syndrome — NIDDK, National Institutes of Health (2018)
- Isturisa (osilodrostat) prescribing information — DailyMed (2025)
- Recorlev (levoketoconazole) prescribing information — DailyMed (2026)
- Signifor (pasireotide) prescribing information — DailyMed (2026)
- Korlym (mifepristone) prescribing information — DailyMed (2025)
- Metopirone (metyrapone) prescribing information — DailyMed (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
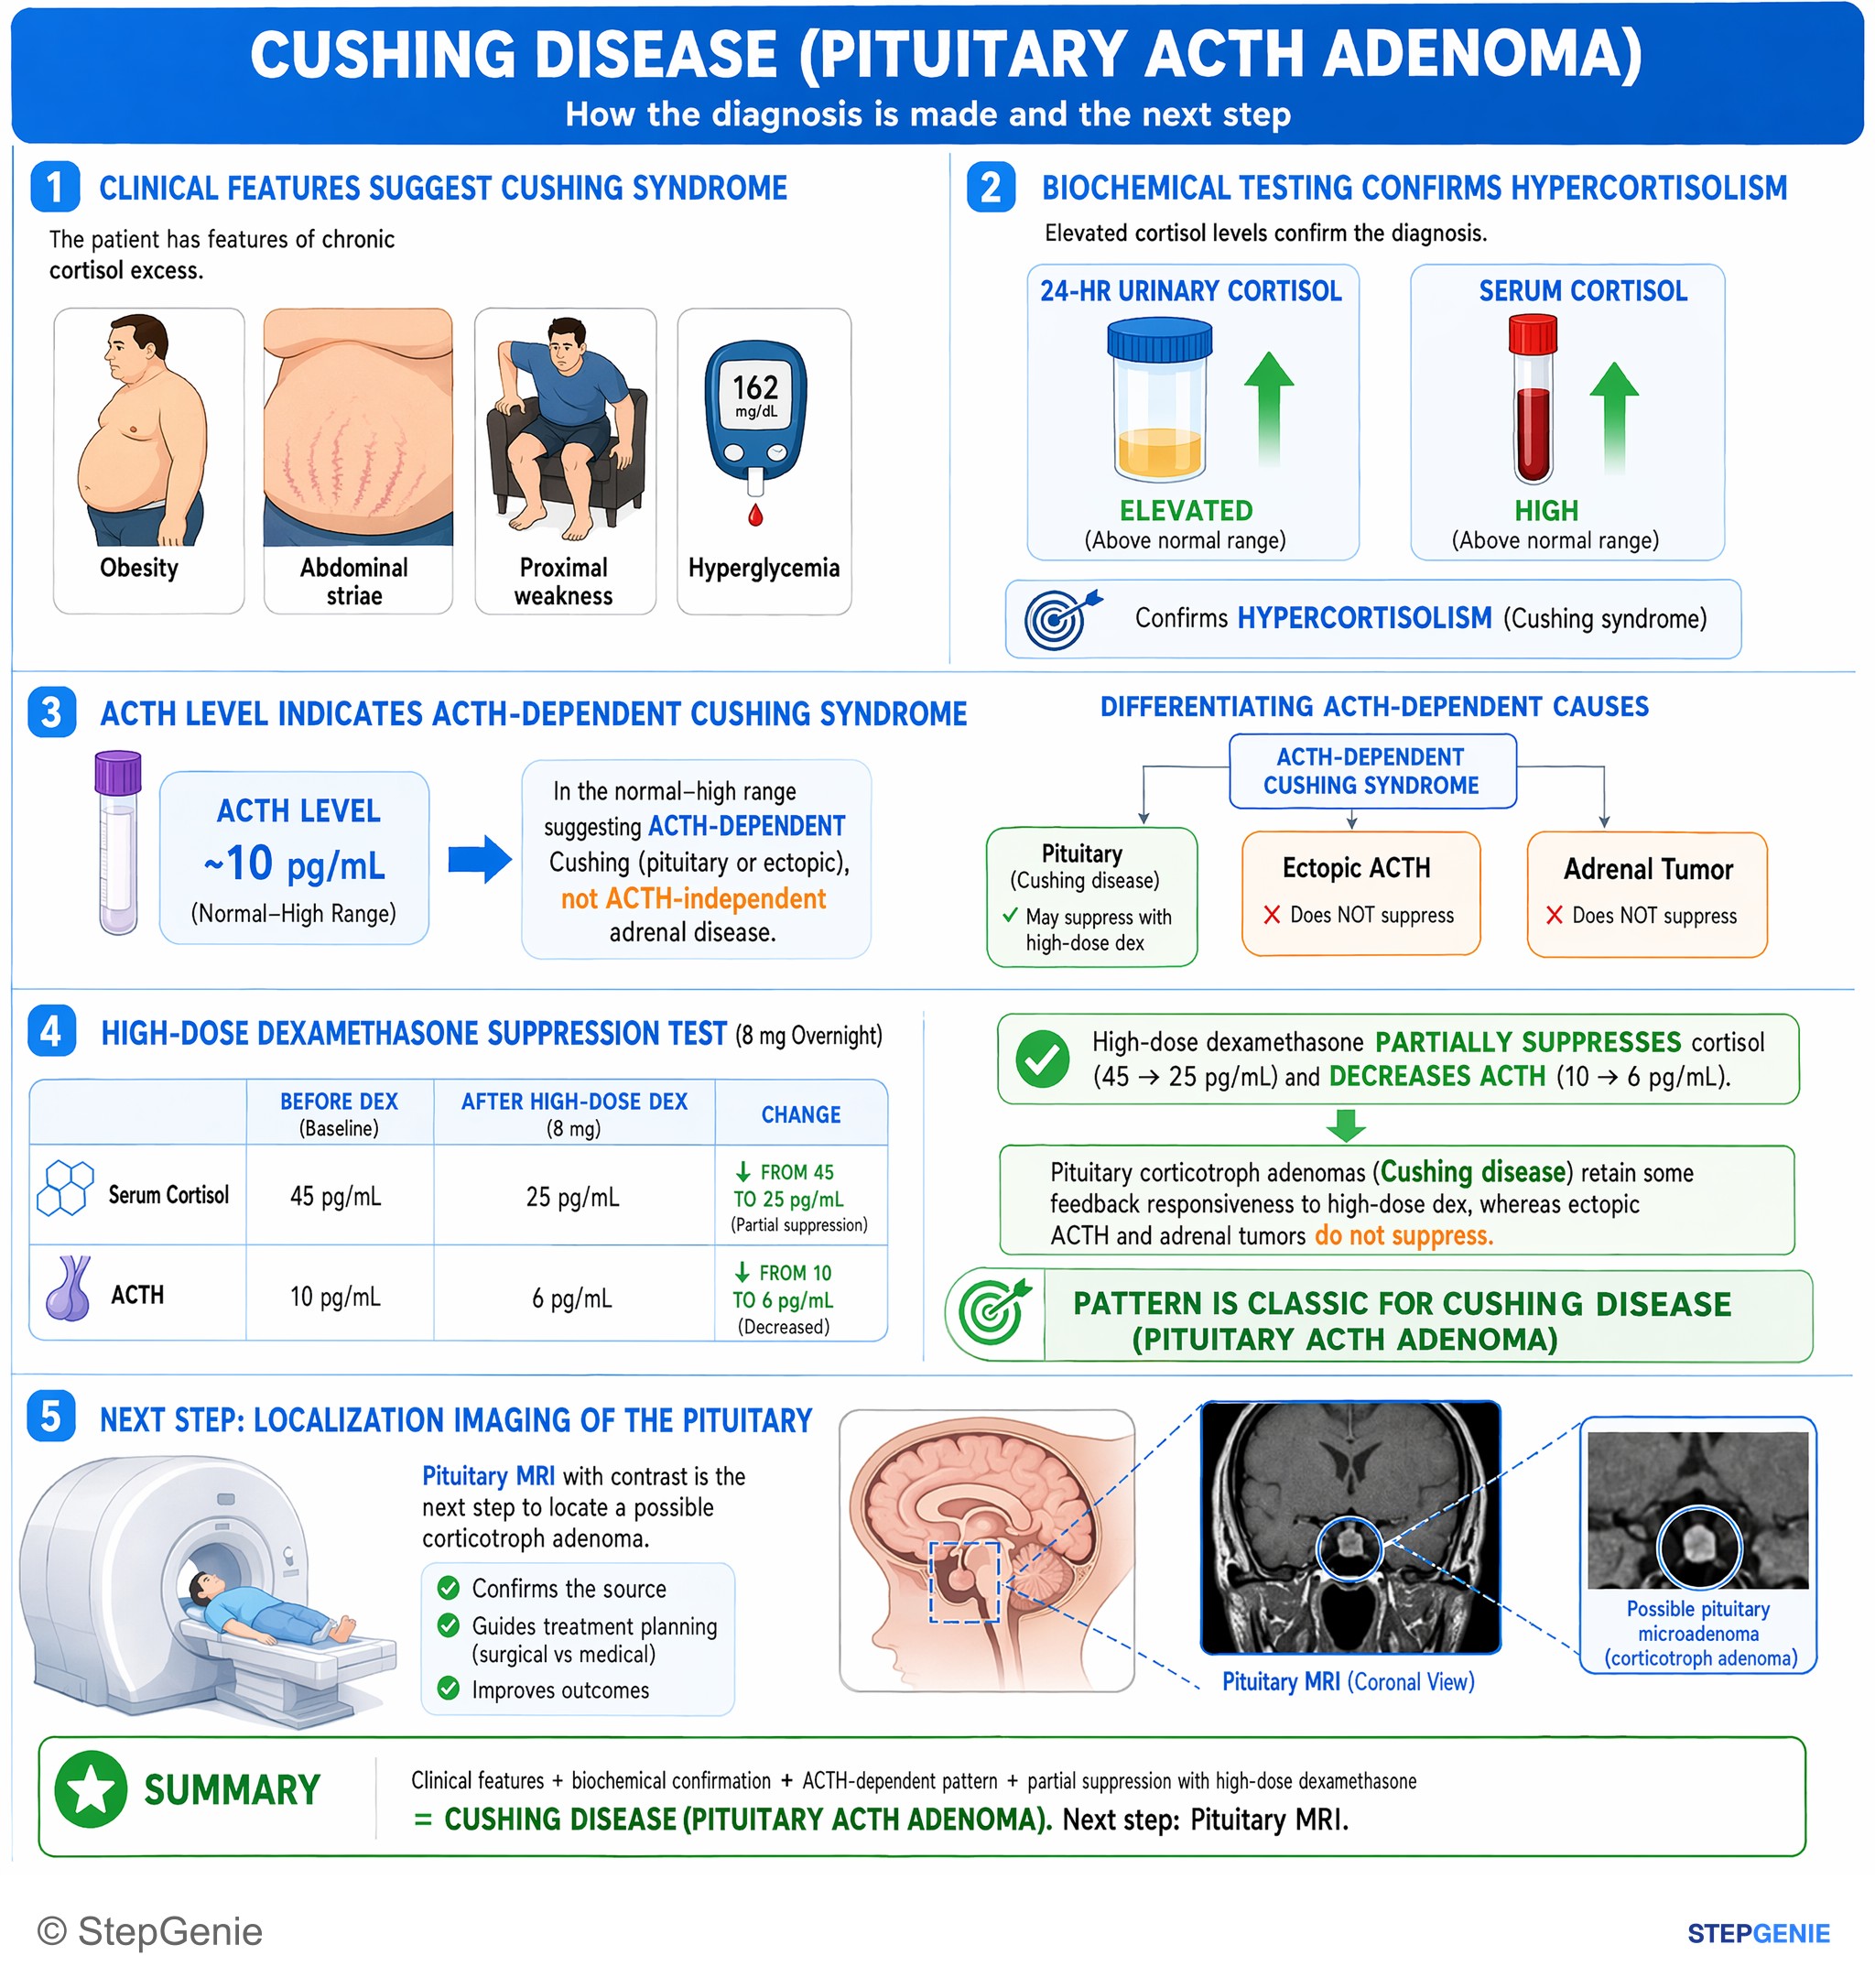
Cushing disease (pituitary ACTH adenoma) suspected after high-dose dex suppression with partial cortisol suppression and decreased ACTH…
USMLE Step 2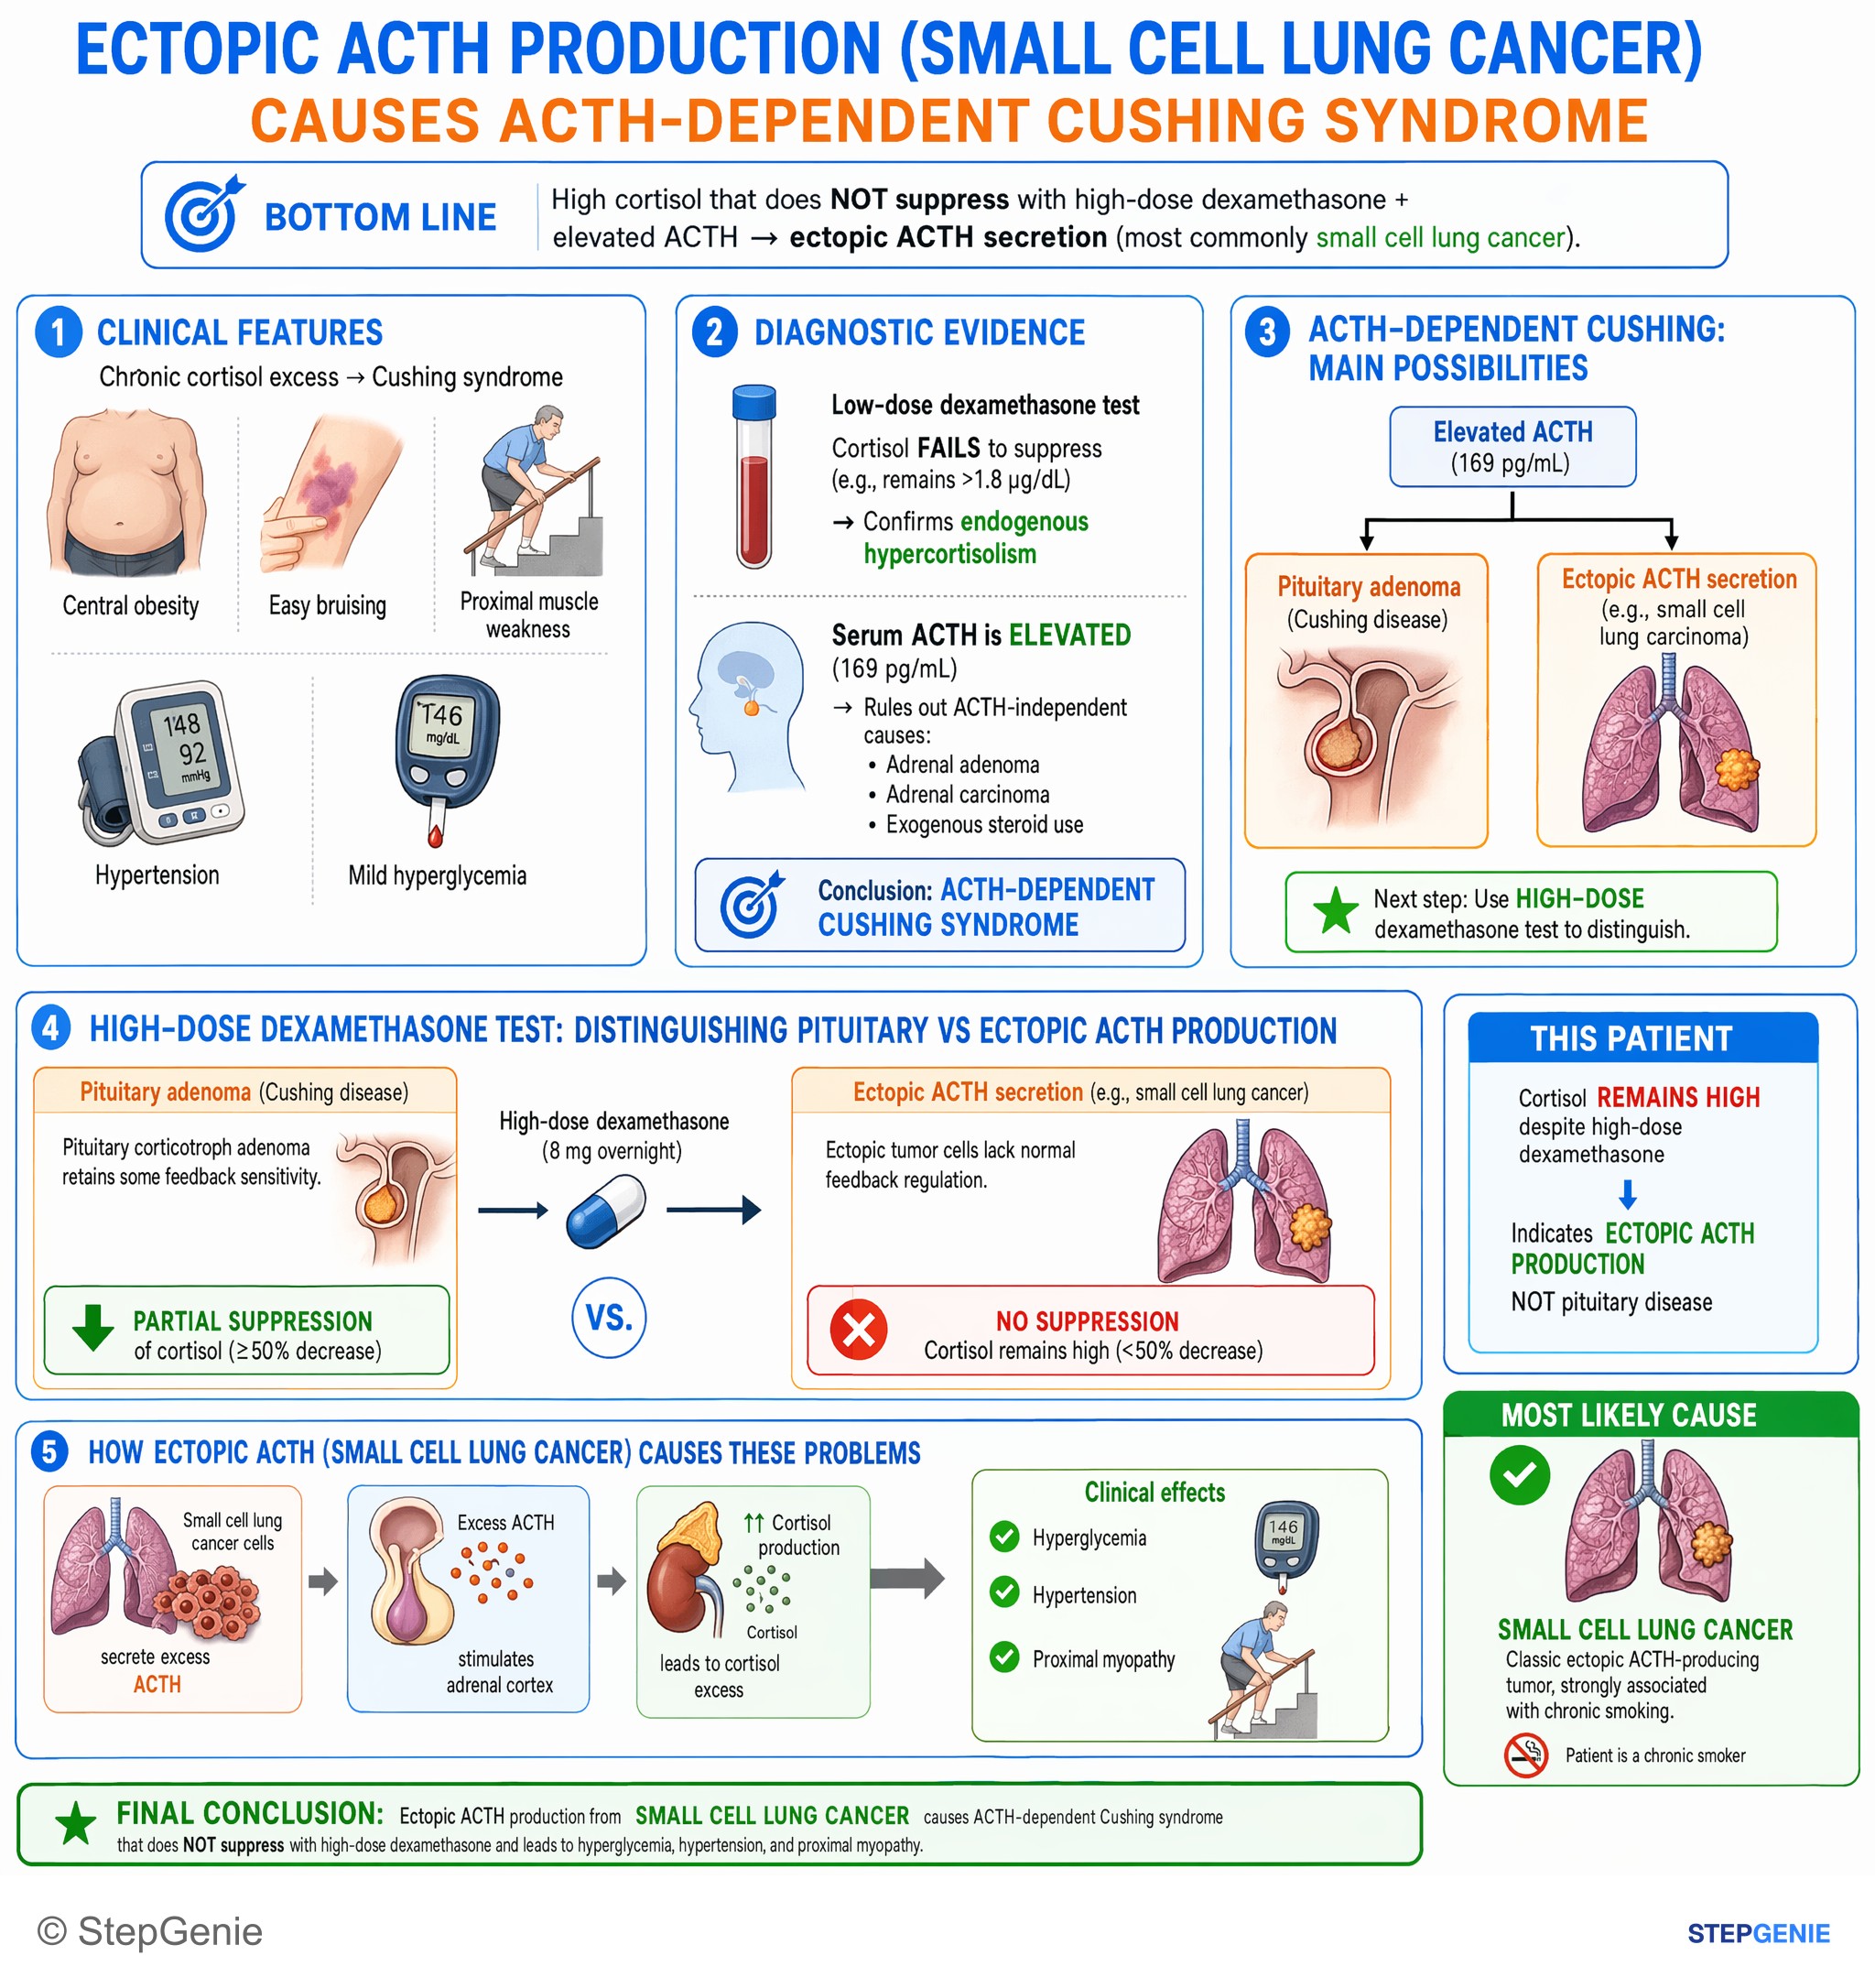
Ectopic ACTH production (small cell lung cancer) → ACTH-dependent Cushing syndrome that does not suppress with high-dose dexamethasone…
USMLE Step 1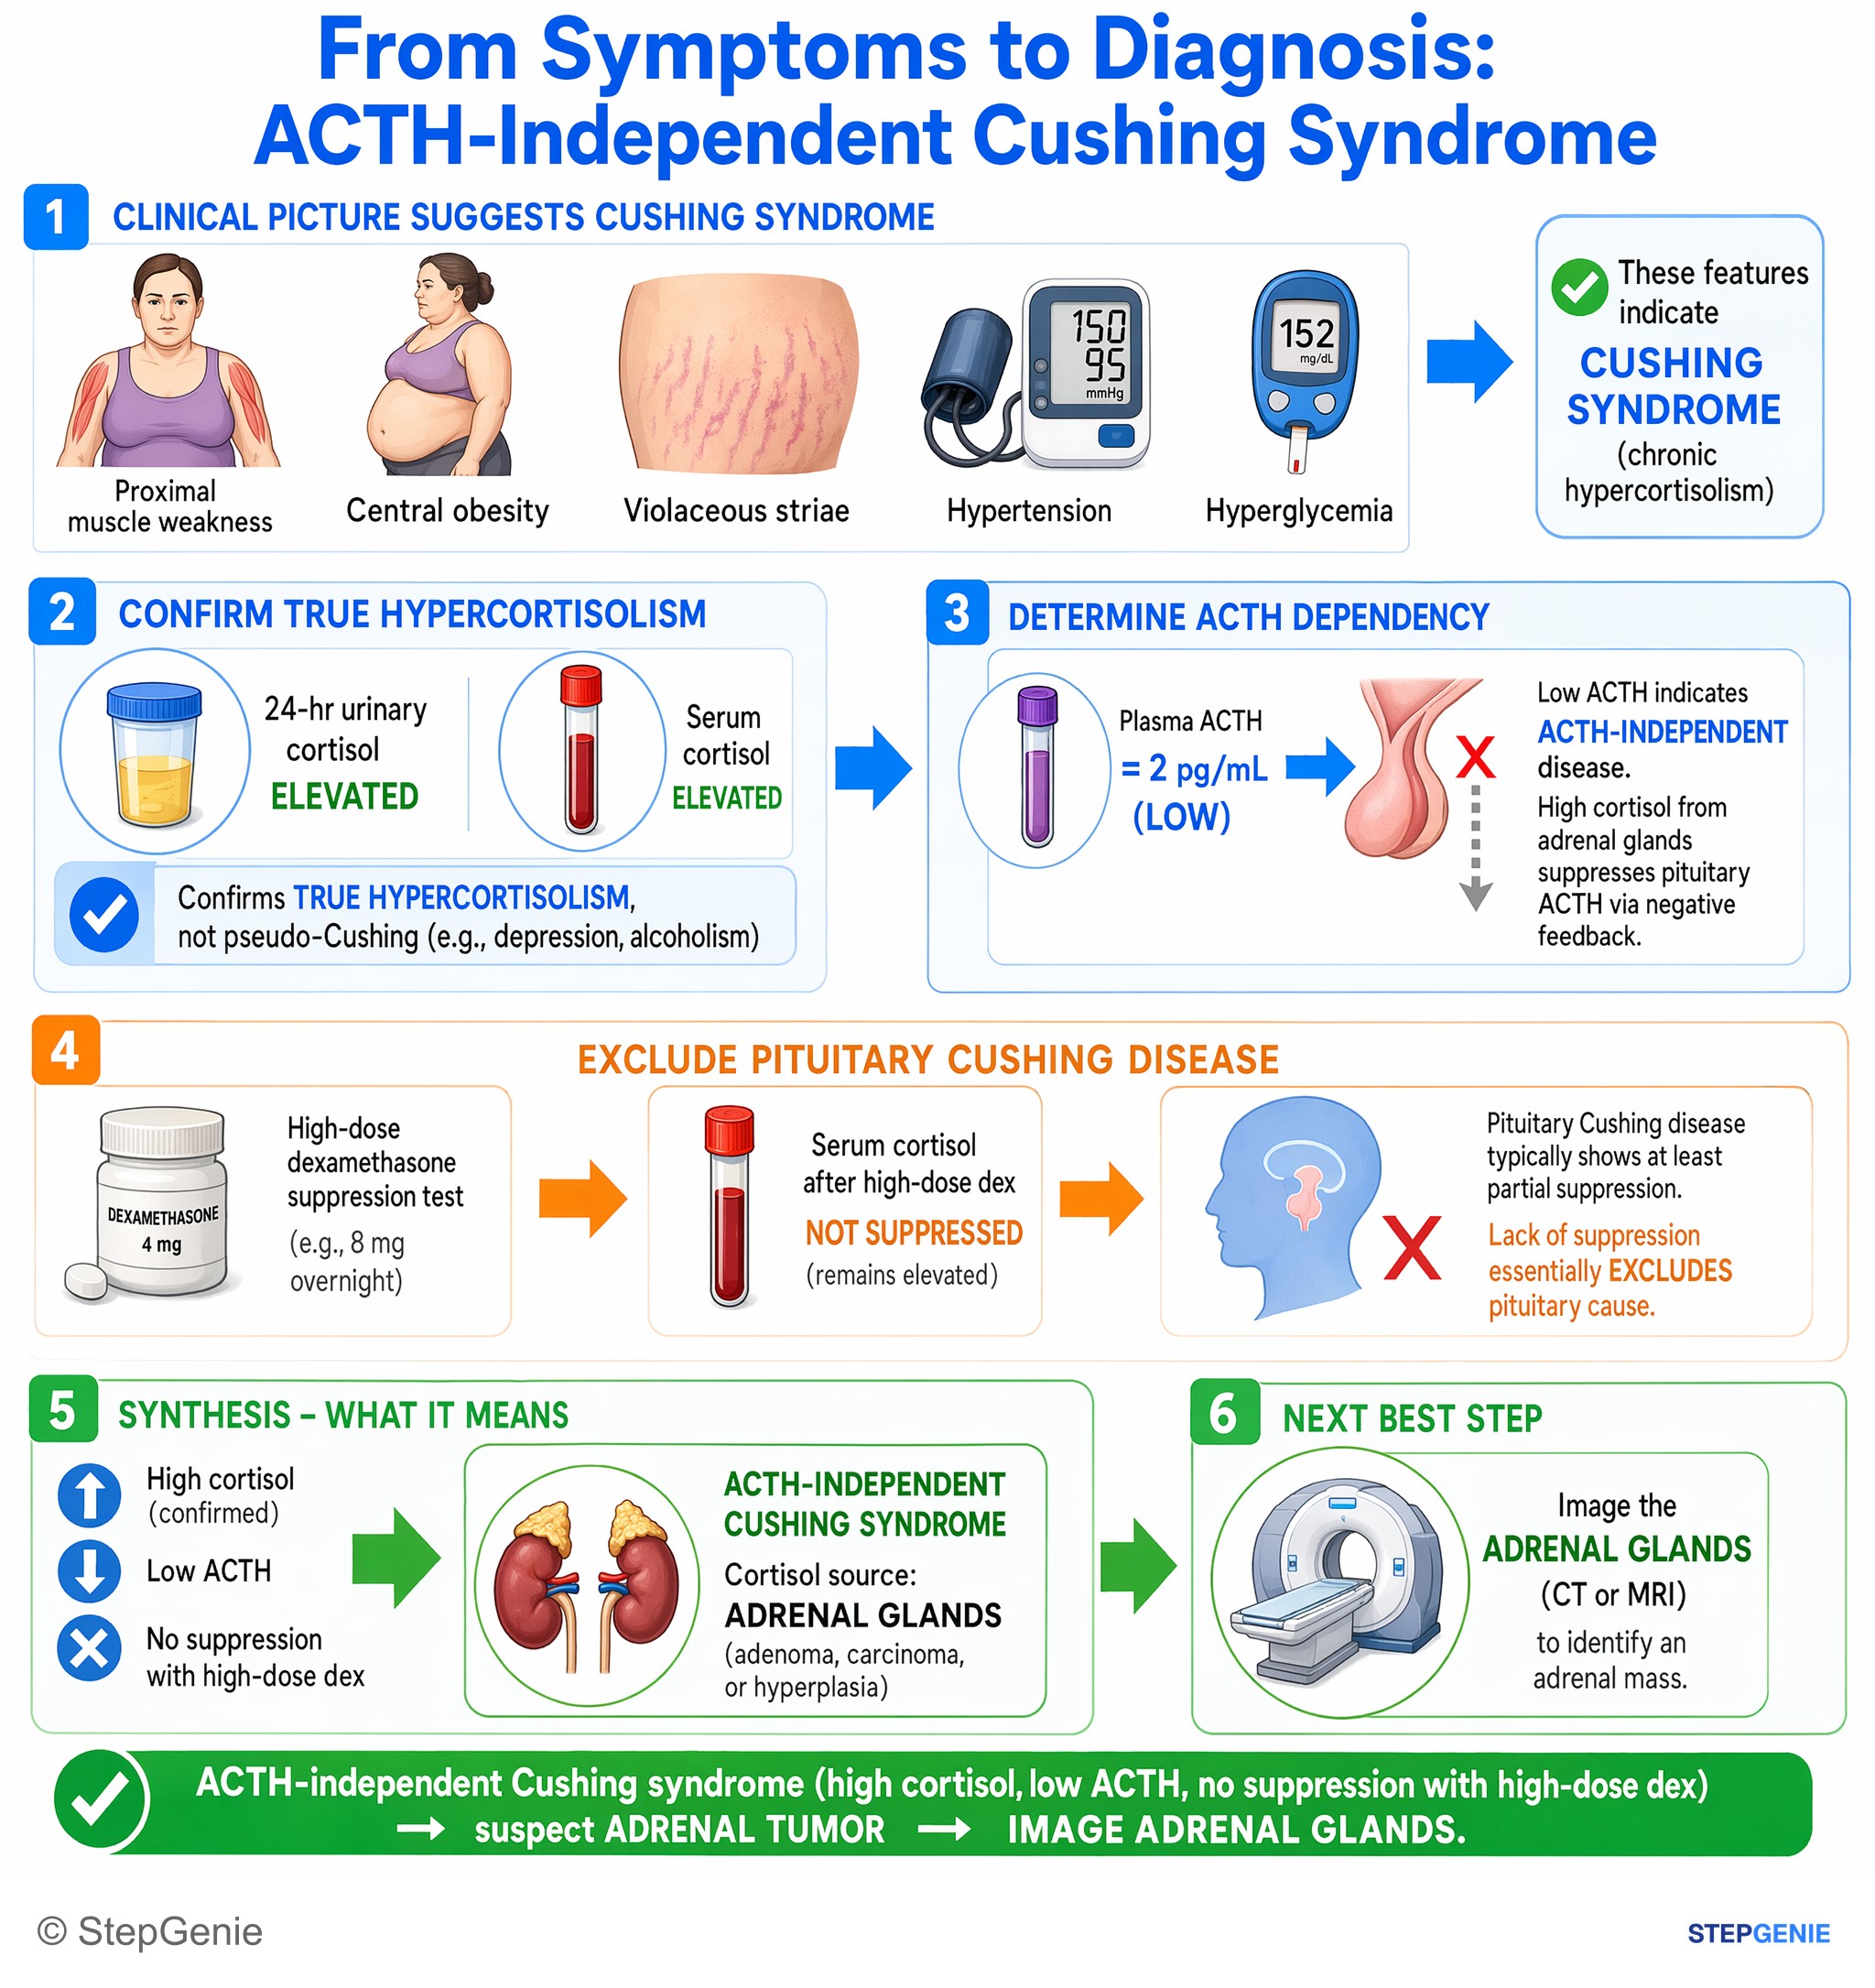
ACTH-independent Cushing syndrome (high cortisol, low ACTH, no suppression with high-dose dex) → suspect adrenal tumor → image adrenal…
USMLE Step 2Frequently Asked Questions
What is the difference between Cushing syndrome and Cushing disease?
Cushing syndrome is the set of signs and symptoms caused by chronic exposure to too much cortisol or another glucocorticoid, from any cause; prescribed steroids are the most common cause. Cushing disease is one cause of Cushing syndrome: an ACTH-secreting pituitary adenoma that drives both adrenal glands to make excess cortisol. It accounts for about 8 in 10 cases of endogenous Cushing syndrome, and its first-line treatment is transsphenoidal surgery.
What is the best screening test for Cushing syndrome?
After excluding prescribed glucocorticoids, the Endocrine Society recommends late-night salivary cortisol (at least two nights), 24-hour urinary free cortisol (at least two collections) or a 1-mg overnight dexamethasone suppression test, in which a morning cortisol above 1.8 mcg/dL (50 nmol/L) is abnormal. No single test is perfect, so the cause is investigated only after two different tests are concordantly abnormal. Oral estrogens, CYP3A4-inducing drugs and pseudo-Cushing states such as depression, alcohol use disorder and obesity can give false positives.
How do you tell Cushing disease from ectopic ACTH production?
First confirm the disease is ACTH-dependent (ACTH of 20 pg/mL or more). A pituitary adenoma keeps partial feedback, so cortisol classically suppresses by more than 50% on high-dose dexamethasone and ACTH rises after CRH or desmopressin, while an ectopic tumor usually does neither. Pituitary MRI may show the adenoma, but if it is negative or the tests disagree, inferior petrosal sinus sampling decides: a central-to-peripheral ACTH ratio above 3 after stimulation points to the pituitary. Rapid onset, hypokalemia and hyperpigmentation favor ectopic ACTH.
Is the high-dose dexamethasone suppression test still used?
It remains the classic exam discriminator: cortisol suppresses by more than 50% in Cushing disease but not with ectopic ACTH or adrenal tumors. In practice, Merck notes that most centers have abandoned it because its sensitivity and specificity are suboptimal. Current workups rely on plasma ACTH, pituitary MRI, CRH or desmopressin stimulation (CRH is now hard to obtain) and inferior petrosal sinus sampling when the MRI is negative or the results conflict.
Which drugs are FDA-approved to treat Cushing syndrome?
As of October 2026, osilodrostat (Isturisa, whose label was broadened from Cushing disease in April 2025) and levoketoconazole (Recorlev) are FDA-approved for endogenous hypercortisolemia in adults with Cushing syndrome when surgery is not an option or has not been curative; levoketoconazole carries a boxed warning for liver toxicity and QT prolongation. Pasireotide is approved for Cushing disease, and mifepristone is approved to control hyperglycemia caused by Cushing syndrome. In the US, metyrapone is labeled only as a diagnostic test, and oral ketoconazole is used off-label.
Why do patients taking long-term steroids need a slow taper?
Prescribed glucocorticoids suppress CRH and ACTH, so the adrenal glands atrophy and stop making cortisol. That is why exogenous Cushing syndrome shows low ACTH and bilateral adrenal atrophy. If the drug is stopped suddenly, the suppressed axis cannot respond and the patient can develop adrenal insufficiency or adrenal crisis. Tapering gradually gives the hypothalamus, pituitary and adrenals time to recover. The same suppression explains why glucocorticoid replacement is needed after successful removal of a cortisol-secreting tumor.