Congenital adrenal hyperplasia (CAH) is a group of autosomal recessive enzyme defects in adrenal steroid synthesis in which low cortisol raises ACTH, enlarging the adrenals and pushing precursors into whatever pathway is still open. 21-hydroxylase deficiency (about 95% of CAH) causes salt wasting and androgen excess, with a high 17-hydroxyprogesterone (17-OHP); 11β-hydroxylase deficiency causes androgen excess plus hypertension and hypokalemia from 11-deoxycorticosterone (DOC), with a high 11-deoxycortisol; and 17α-hydroxylase deficiency causes hypertension and hypokalemia with absent sex steroids. Sort every CAH question by two findings: blood pressure and androgens.
The pathway on one grid
Read down a column to follow each hormone track; the enzyme on the left does that row's step.
| Enzyme (gene) | Salt: mineralocorticoid track | Sugar: glucocorticoid track | Sex: androgen track |
|---|---|---|---|
| Top row (Δ5 steroids) | Pregnenolone | 17-OH pregnenolone | DHEA |
| 3β-HSD (HSD3B2) | Progesterone | 17-OHP | Androstenedione |
| 21-hydroxylase (CYP21A2) | DOC | 11-Deoxycortisol | — |
| 11β-hydroxylase (CYP11B1) | Corticosterone | Cortisol | — |
| Aldosterone synthase (CYP11B2) | Aldosterone (via 18-hydroxycorticosterone) | — | — |
The sideways steps belong to one enzyme, CYP17A1. Its 17α-hydroxylase activity converts pregnenolone to 17-OH pregnenolone and progesterone to 17-OHP; its 17,20-lyase activity converts 17-OH pregnenolone to DHEA. Upstream of everything, the StAR protein moves cholesterol into the inner mitochondrial membrane.
Rule of the grid: a block starves everything below it in that column, and the substrate piling up above it spills into any route still open.
The master comparison table
| Deficiency (gene) | Share of CAH | BP, K⁺ and renin | Sex steroids | Genitalia at birth | Signature lab |
|---|---|---|---|---|---|
| 21-hydroxylase, classic salt-wasting (CYP21A2) | All 21-hydroxylase forms: about 95% of CAH; salt-wasting is 75% of classic cases | Low BP, high K⁺, low Na⁺, acidosis, high renin | High androgens | 46,XX atypical (virilized); 46,XY typical male | High 17-OHP |
| 21-hydroxylase, simple virilizing | About 25% of classic cases | No salt loss | High androgens | 46,XX virilized; 46,XY typical male | High 17-OHP |
| 21-hydroxylase, nonclassic | About 1 in 1,000 people; more in some groups | Normal | Androgen excess after birth | Typical | 17-OHP high early in the morning or after cosyntropin |
| 11β-hydroxylase (CYP11B1) | 5–8% | High BP (about two-thirds of classic cases), low K⁺, alkalosis, low renin | High androgens | 46,XX atypical; 46,XY typical male | High 11-deoxycortisol and DOC |
| 17α-hydroxylase/17,20-lyase (CYP17A1) | About 1% | High BP, low K⁺, alkalosis, low renin | Low androgens and estrogens | 46,XY female-appearing; 46,XX typical female | High DOC and corticosterone, low sex steroids |
| 3β-HSD type 2 (HSD3B2) | Rare | Salt wasting in the salt-wasting type | Weak androgens only (DHEA) | 46,XY undervirilized; 46,XX mildly atypical | High pregnenolone, 17-OH pregnenolone, DHEA |
| Lipoid CAH (STAR) | Rare | All steroids low, including aldosterone | Low | Female or near-female in both | All steroids low |
21-hydroxylase deficiency (about 95%)
Block: 17-OHP → 11-deoxycortisol and progesterone → DOC. Cortisol and aldosterone fall, ACTH rises (causing hyperpigmentation), and 17-OHP piles up and is diverted into androgens. Classic CAH occurs in about 1 in 14,000 to 18,000 births. CYP21A2 sits next to a similar, nonfunctional pseudogene, CYP21A1P; gene conversion can copy its errors into the working gene.
- Classic salt-wasting (75% of classic cases): poor feeding, vomiting, weight loss and dehydration, with hyponatremia, hyperkalemia, acidosis, low aldosterone and high plasma renin activity. If undiagnosed, symptoms appear within days or weeks of birth, and adrenal crisis can be fatal. Girls are noticed at birth because of atypical genitalia (clitoral enlargement, fused labia majora, a urogenital sinus), but boys have typical genitalia, so without newborn screening their first sign may be a salt-wasting crisis.
- Simple virilizing (25%): no salt loss. Untreated boys have progressive penile enlargement with small testes, rapid growth and advanced bone age.
- Nonclassic: girls have typical genitalia at birth and develop signs of androgen excess later; in adolescent and adult women the picture can mimic polycystic ovary syndrome, with infertility (compare the PCOS Q-bank breakdown). Some people have no symptoms.
Diagnosis (Endocrine Society 2018 guideline):
- Newborn screening measures 17-OHP against gestational-age norms, with a second-tier liquid chromatography–tandem mass spectrometry (LC-MS/MS) test preferred. Premature, sick or stressed infants cause many false positives.
- Positive screens go to a pediatric endocrinologist, with cosyntropin (ACTH) stimulation testing as needed (17-OHP before and 60 minutes after).
- Symptomatic patients past infancy: an early-morning (before 8 am) 17-OHP by LC-MS/MS.
Treatment (Endocrine Society 2018 guideline):
- Hydrocortisone for growing children; avoid oral hydrocortisone suspension and chronic use of long-acting potent glucocorticoids such as dexamethasone.
- Fludrocortisone plus sodium chloride supplements in the newborn period and early infancy.
- Stress dosing for febrile illness (above 38.5 °C), gastroenteritis with dehydration, major surgery and major trauma; adrenal crisis is treated with IV stress-dose hydrocortisone.
- No glucocorticoids for asymptomatic, nonpregnant people with nonclassic CAH.
- Prenatal dexamethasone (to prevent virilization of a 46,XX fetus) is still experimental and should be given only through IRB-approved protocols.
- Long term: adults with classic CAH are usually shorter than family members, and males can develop benign testicular adrenal rest tumors that impair fertility, so the guideline recommends periodic testicular ultrasound.
11β-hydroxylase deficiency (5–8%)
Block: 11-deoxycortisol → cortisol and DOC → corticosterone (CYP11B1, chromosome 8). DOC accumulates and acts as a mineralocorticoid, so salt is retained: hypertension, hypokalemia and metabolic alkalosis with suppressed renin. The trapped precursors are also converted to androgens.
- About two-thirds of people with the classic form develop hypertension.
- 46,XX infants have atypical genitalia, and both sexes develop early pubic and facial hair, acne, a deep voice and an early growth spurt.
- Diagnosis: high 11-deoxycortisol and DOC with high androgens.
- Frequency: about 1 in 100,000–200,000 births overall, but about 1 in 5,000–7,000 among Moroccan Jews in Israel.
17α-hydroxylase deficiency (about 1%)
Block: CYP17A1 (chromosome 10) can't make 17-hydroxylated steroids or perform the 17,20-lyase step, so cortisol and all sex steroids are low. Precursors flow into the mineralocorticoid track instead: DOC and corticosterone rise, causing hypertension, hypokalemia and alkalosis with suppressed renin.
- 46,XY: in the complete form, female external genitalia, undescended (abdominal) testes and no uterus, with no female secondary sex characteristics and no periods; partial forms range from micropenis to hypospadias.
- 46,XX: typical external genitalia at birth, then no puberty (no breast development, little pubic hair, primary amenorrhea) and infertility.
- The usual presentation is an adolescent with absent puberty and hypertension. Labs show high DOC and corticosterone, a high progesterone-to-17-OHP ratio and low sex steroids.
- Treatment adds sex steroid replacement at puberty to glucocorticoid replacement. For where this fits among causes of primary amenorrhea, use the amenorrhea workup flowchart.
The rare forms
- 3β-HSD type 2 deficiency: the Δ5 steroids (pregnenolone, 17-OH pregnenolone, DHEA and DHEA sulfate) are high. DHEA is a weak androgen, so boys are undervirilized, from hypospadias to atypical genitalia, and girls may have slight genital changes; a salt-wasting type exists. The genital findings are reviewed in the hypospadias vs epispadias rule.
- Lipoid CAH (StAR deficiency): cholesterol can't reach the inner mitochondrial membrane, so all adrenal and gonadal steroids are low, and infants have female or near-female genitalia regardless of chromosomal sex.
- P450 oxidoreductase deficiency: combines features of 21- and 17α-hydroxylase defects and can include the skeletal anomalies of Antley-Bixler syndrome.
How CAH shows up in question stems
| Stem | Answer |
|---|---|
| Newborn girl with atypical genitalia, then vomiting, low Na⁺ and high K⁺ | Salt-wasting 21-hydroxylase deficiency |
| 2-week-old boy with typical genitalia in shock with hyperkalemia | Salt-wasting 21-hydroxylase deficiency (missed without screening) |
| 4-year-old boy with pubic hair, penile growth and advanced bone age, normal BP | Simple virilizing 21-hydroxylase deficiency |
| The same boy with hypertension and low K⁺ | 11β-hydroxylase deficiency |
| Young woman with hirsutism, irregular periods and a high early-morning 17-OHP | Nonclassic 21-hydroxylase deficiency |
| Teen with primary amenorrhea, no breasts, hypertension and low K⁺ | 17α-hydroxylase deficiency |
| Undervirilized 46,XY newborn with salt wasting and high DHEA | 3β-HSD deficiency |
Exam traps
- 11-deoxycortisol vs 11-deoxycorticosterone (DOC). The first is the glucocorticoid-track marker of 11β-hydroxylase deficiency; the second is the mineralocorticoid that drives the hypertension of 11β- and 17α-hydroxylase deficiency.
- CAH hypertension comes from DOC, and renin is suppressed. For low-renin hypertension caused by aldosterone itself, compare primary hyperaldosteronism.
- Androgens pick between the two hypertensive forms: virilization means 11β; absent puberty means 17α.
- A boy with salt-wasting CAH looks typical at birth.
- Isolated 17,20-lyase deficiency causes the sex-steroid problem without hypertension or hypokalemia.
- Don't give prenatal dexamethasone outside a research protocol, and don't treat asymptomatic nonclassic CAH.
Worked example
Vignette. A 16-year-old raised as a girl is evaluated for primary amenorrhea. She has no breast development and sparse pubic and axillary hair, and her external genitalia are female. Blood pressure is 158/100 mm Hg, potassium is 2.9 mEq/L with a metabolic alkalosis, and plasma renin activity is suppressed. Pelvic ultrasound shows no uterus, and the karyotype is 46,XY. Which enzyme is deficient?
Answer: 17α-hydroxylase (CYP17A1).
Reasoning: Without 17α-hydroxylation there is no cortisol and no sex steroid, so a 46,XY fetus develops female external genitalia and puberty never starts, while precursors diverted to DOC and corticosterone cause low-renin hypertension with hypokalemia.
- 11β-hydroxylase deficiency also causes hypertension, but with androgen excess and virilization, not absent puberty.
- 21-hydroxylase deficiency causes salt wasting and virilization, the opposite blood pressure and androgen pattern.
- Complete androgen insensitivity also gives a 46,XY person with female external genitalia, undescended testes and no uterus, but it doesn't cause hypertension or hypokalemia.
Key takeaways
- 21-hydroxylase: about 95% of CAH; salt wasting (75% of classic cases) plus virilization; high 17-OHP; boys missed without screening; symptoms within days or weeks of birth.
- 11β-hydroxylase: virilization plus hypertension and hypokalemia; high 11-deoxycortisol and DOC; low renin.
- 17α-hydroxylase: hypertension and hypokalemia with no sex steroids; 46,XY female phenotype; 46,XX absent puberty.
- 3β-HSD: high DHEA, undervirilized boys, salt wasting possible. Lipoid CAH: every steroid low.
- Treatment (Endocrine Society 2018): hydrocortisone in growing children, fludrocortisone and salt in infancy, stress dosing; prenatal dexamethasone is experimental.
Sources
- Speiser PW, et al. Congenital Adrenal Hyperplasia Due to Steroid 21-Hydroxylase Deficiency: An Endocrine Society Clinical Practice Guideline — J Clin Endocrinol Metab (2018)
- Congenital Adrenal Hyperplasia Caused by 21-Hydroxylase Deficiency — Merck Manual Professional Edition
- 21-hydroxylase deficiency — MedlinePlus Genetics
- What are the symptoms of congenital adrenal hyperplasia (CAH)? — NICHD, NIH
- CYP21A2 gene — MedlinePlus Genetics
- Congenital adrenal hyperplasia due to 11-beta-hydroxylase deficiency — MedlinePlus Genetics
- CYP11B1 gene — MedlinePlus Genetics
- 17α-hydroxylase/17,20-lyase deficiency — MedlinePlus Genetics
- CYP17A1 gene — MedlinePlus Genetics
- 3-beta-hydroxysteroid dehydrogenase deficiency — MedlinePlus Genetics
- Higa M, et al. Novel STAR gene variant in a patient with classic lipoid congenital adrenal hyperplasia and combined pituitary hormone deficiency — Human Genome Variation (2021)
- Androgen insensitivity syndrome — MedlinePlus Genetics
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
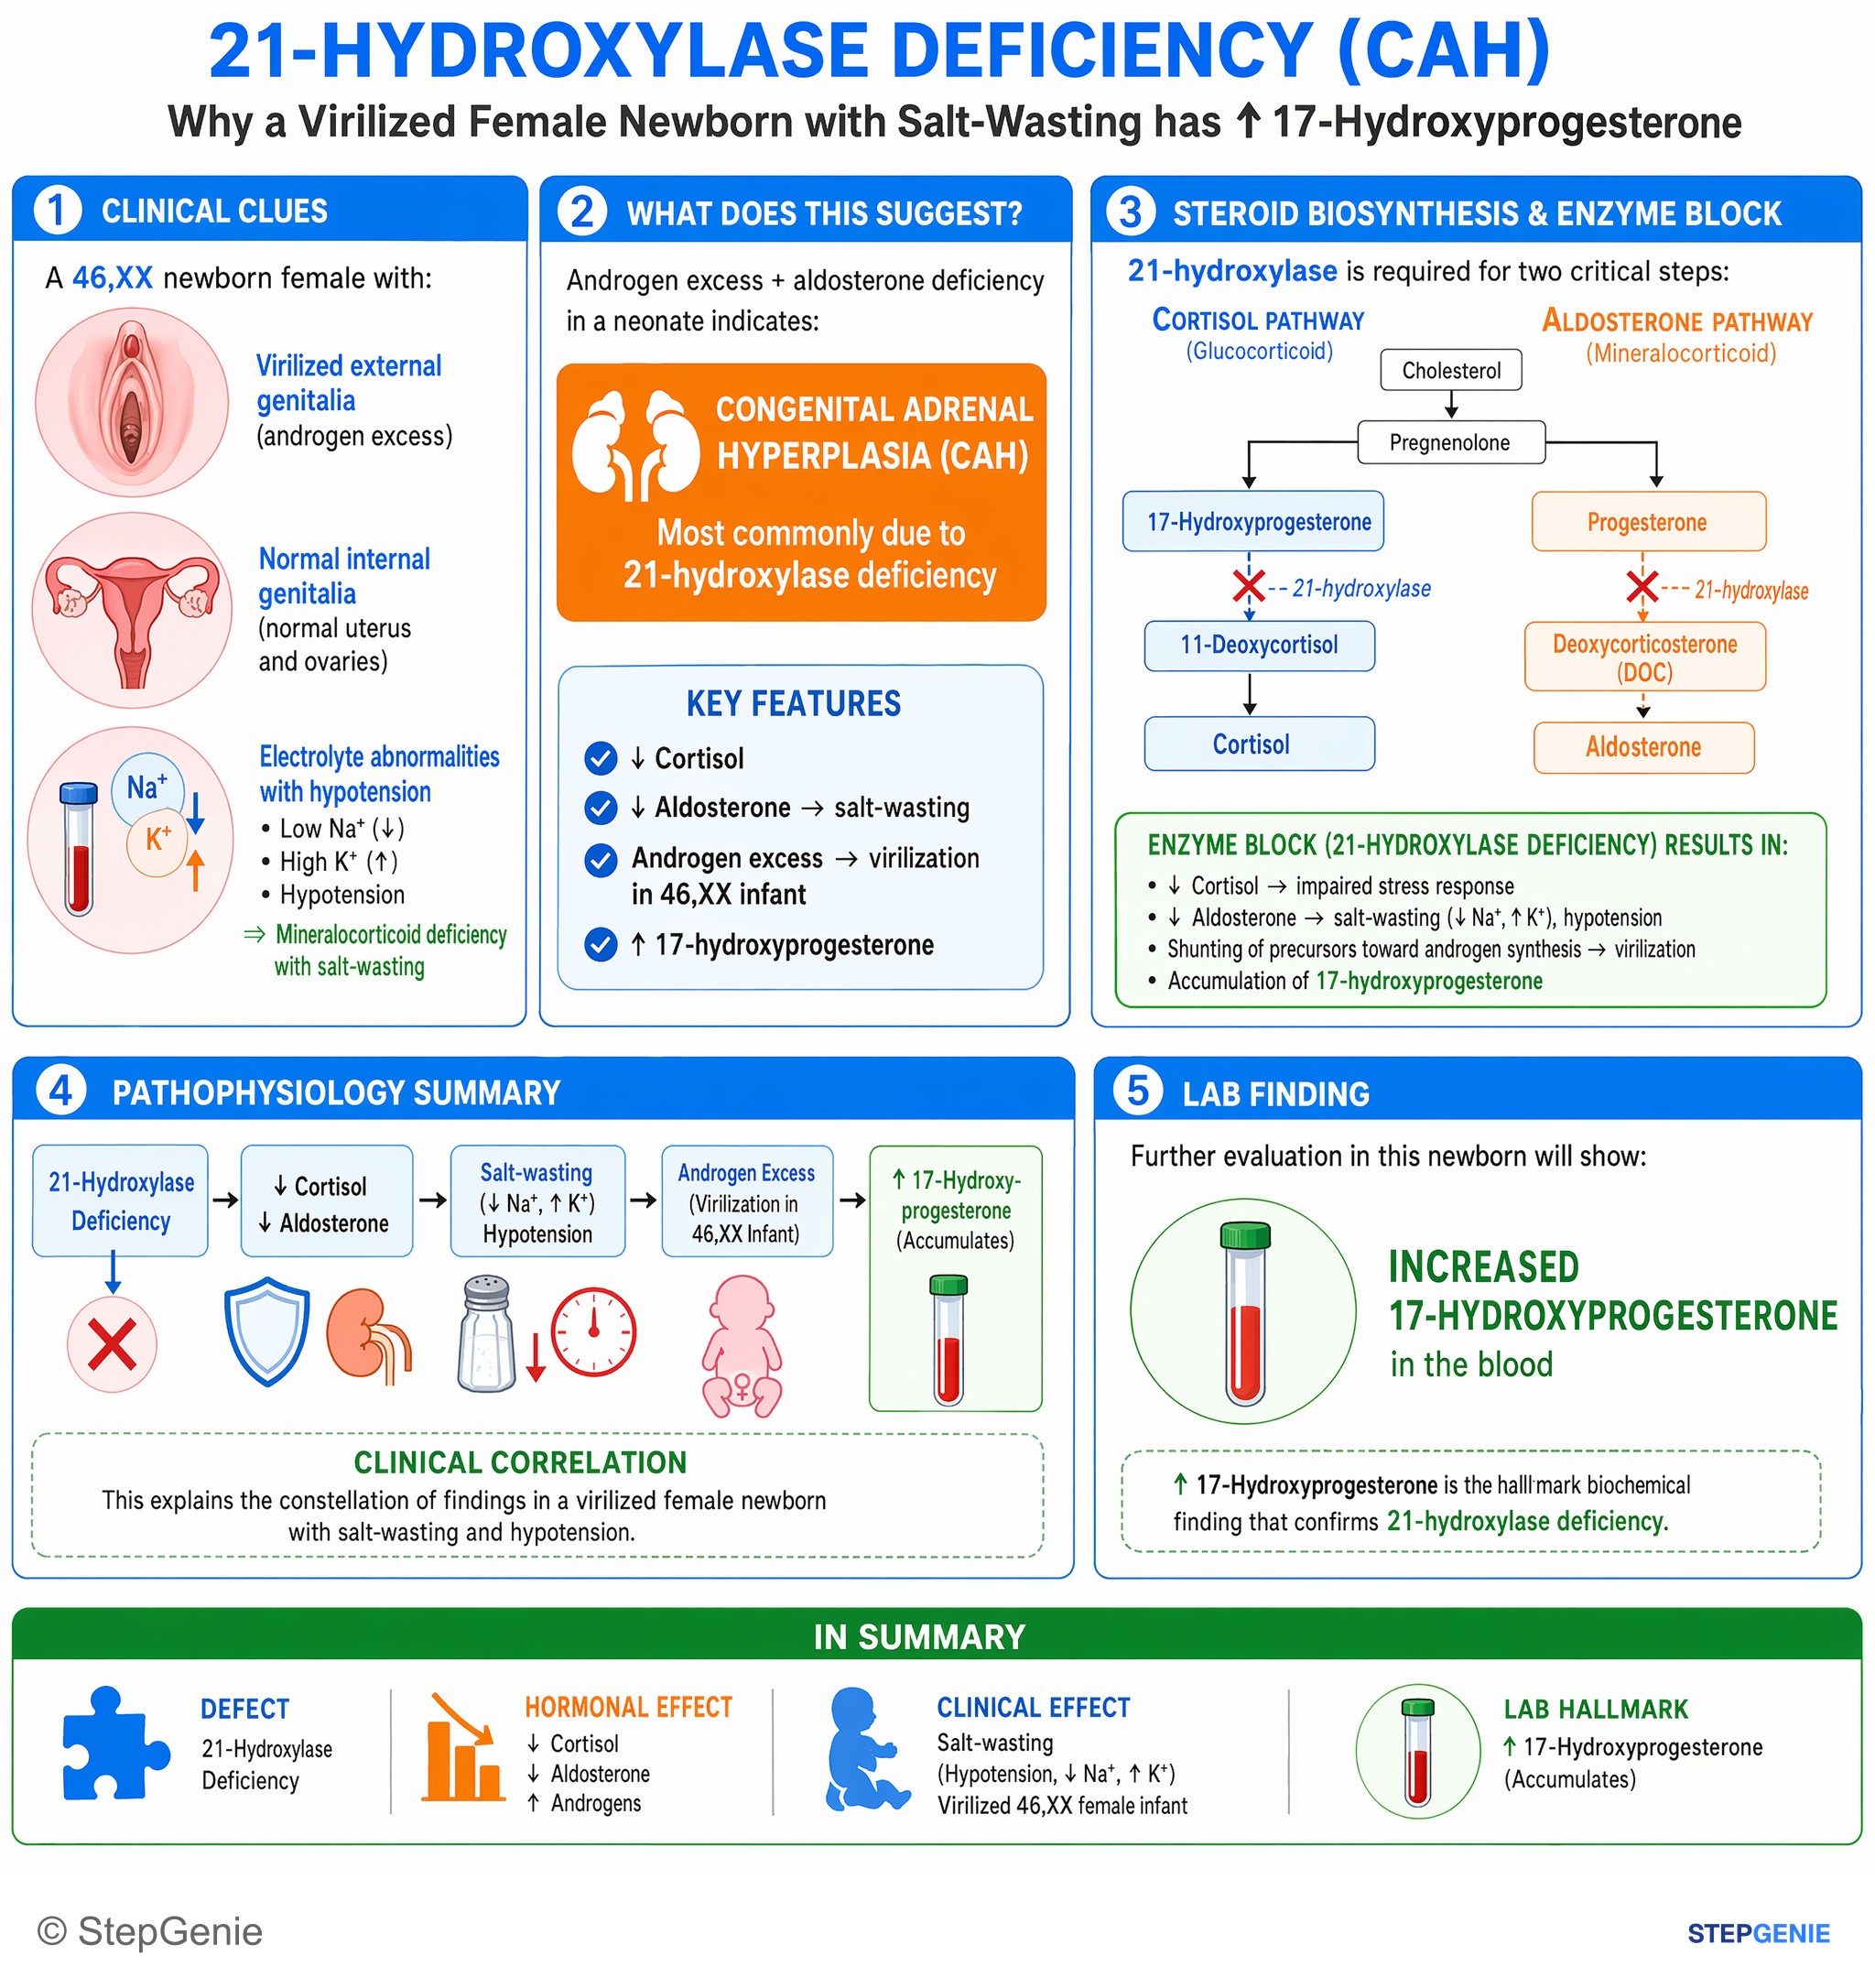
21-hydroxylase deficiency → ↓cortisol/aldosterone, salt-wasting, hypotension, virilized female infant, and ↑17-hydroxyprogesterone.
USMLE Step 1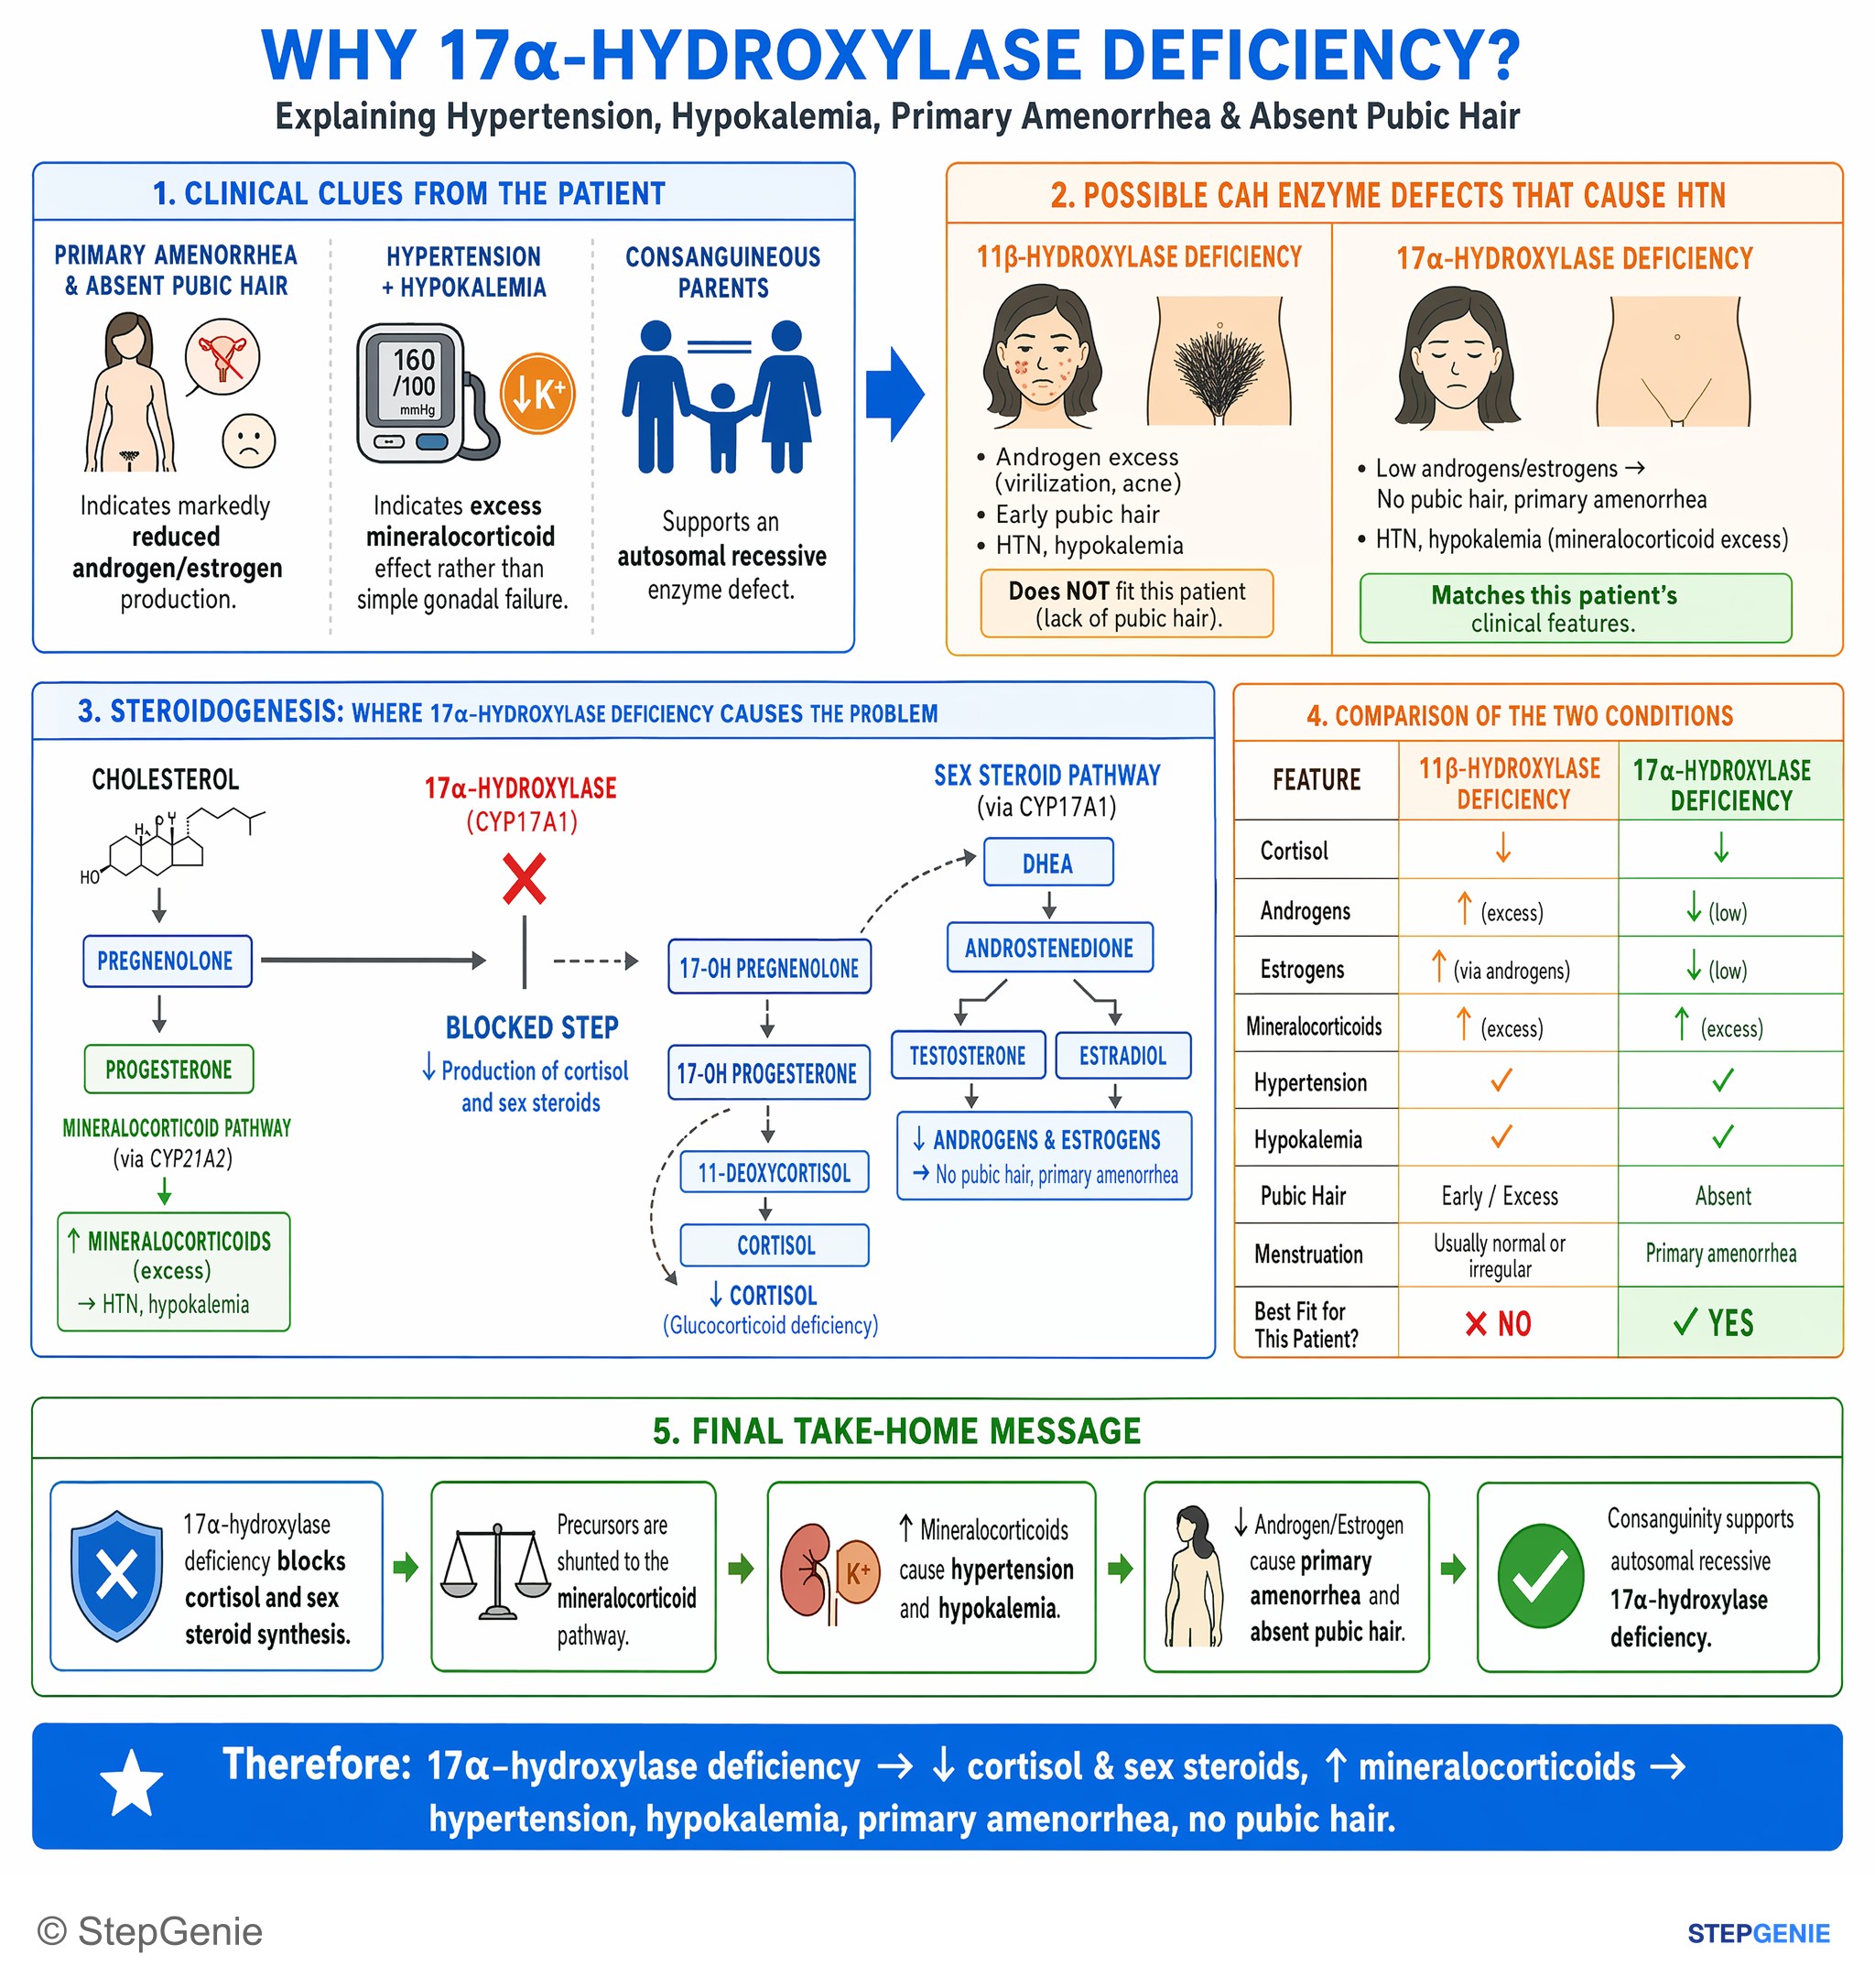
17α-hydroxylase deficiency → ↓ cortisol & sex steroids, ↑ mineralocorticoids → hypertension, hypokalemia, primary amenorrhea, no pubic hair.
USMLE Step 2Frequently Asked Questions
Which types of CAH cause hypertension?
11β-hydroxylase deficiency and 17α-hydroxylase deficiency both cause hypertension, because the enzyme block diverts precursors into 11-deoxycorticosterone (DOC), which acts as a mineralocorticoid. DOC retains salt, so patients have hypertension, hypokalemia and alkalosis with suppressed renin. The androgens separate them: 11β-hydroxylase deficiency causes virilization, while 17α-hydroxylase deficiency blocks sex steroid production and causes absent puberty.
How do you tell 21-hydroxylase from 11β-hydroxylase deficiency?
Both cause low cortisol, high ACTH and androgen excess, so both virilize 46,XX infants. The difference is the mineralocorticoid effect: 21-hydroxylase deficiency lowers aldosterone, causing salt wasting with hyponatremia, hyperkalemia and high renin, while 11β-hydroxylase deficiency raises DOC, causing hypertension and hypokalemia with low renin. The signature labs are a high 17-hydroxyprogesterone in 21-hydroxylase deficiency and a high 11-deoxycortisol in 11β-hydroxylase deficiency.
Why are boys with salt-wasting CAH often missed at birth?
Boys with classic 21-hydroxylase deficiency have typical male genitalia at birth, so nothing prompts clinicians to look for CAH. Without newborn screening for 17-hydroxyprogesterone, the first sign may be a salt-wasting adrenal crisis with vomiting, dehydration, hyponatremia and hyperkalemia, which can develop within days or weeks of birth. Affected girls are usually recognized sooner because of atypical genitalia.
What is nonclassic CAH?
Nonclassic CAH is the mild form of 21-hydroxylase deficiency, affecting about 1 in 1,000 people and more in some ethnic groups. Girls have typical genitalia at birth, and signs of androgen excess appear later; in women it can mimic polycystic ovary syndrome, with infertility. Symptomatic patients are screened with an early-morning 17-hydroxyprogesterone, and the Endocrine Society advises against glucocorticoids for asymptomatic nonpregnant people.
How is classic CAH treated?
Under the 2018 Endocrine Society guideline, growing children with classic CAH take hydrocortisone rather than long-acting potent glucocorticoids such as dexamethasone, and infants also receive fludrocortisone and sodium chloride supplements. Doses are increased for febrile illness, gastroenteritis with dehydration, major surgery or major trauma, and adrenal crisis is treated with IV stress-dose hydrocortisone. Prenatal dexamethasone remains experimental and should be used only in IRB-approved protocols.