Addison disease is primary adrenal insufficiency: the adrenal cortex itself fails, so cortisol and aldosterone (and adrenal androgens) fall while ACTH and renin rise. That combination explains the classic picture of fatigue, weight loss, salt craving, orthostatic hypotension, hyponatremia, hyperkalemia and hyperpigmentation; in the US and Europe up to 90% of cases are autoimmune (21-hydroxylase antibodies). Diagnosis is a low cortisol with a high ACTH, confirmed by a peak cortisol below 18 µg/dL (500 nmol/L) after 250 µg of cosyntropin. Treatment is lifelong hydrocortisone plus fludrocortisone with sick-day dosing; an adrenal crisis gets IV hydrocortisone 100 mg and isotonic saline at once, never delayed for testing.
Primary vs secondary vs tertiary adrenal insufficiency
| Primary (Addison) | Secondary | Tertiary | |
|---|---|---|---|
| Where it fails | Adrenal cortex | Pituitary (low ACTH) | Hypothalamus (low CRH); classically after long-term glucocorticoids are stopped abruptly |
| Cortisol | Low | Low | Low |
| ACTH | High | Low or inappropriately normal | Low or inappropriately normal |
| Aldosterone | Low (renin high) | Preserved (renin-angiotensin system intact) | Preserved |
| Potassium | High | Normal | Normal |
| Sodium | Low (aldosterone loss plus ADH) | Can be low (dilutional, from ADH) | Can be low |
| Skin | Hyperpigmented | Not hyperpigmented | Not hyperpigmented |
| Fludrocortisone needed? | Yes | No | No |
Hyperkalemia + hyperpigmentation = primary until proven otherwise. Both need a damaged adrenal: hyperkalemia because aldosterone is gone, hyperpigmentation because ACTH is high.
Pathophysiology: three missing hormones and one excess
- Cortisol deficiency: loss of the permissive effect on vascular tone (hypotension), less gluconeogenesis (hypoglycemia, more prominent in children), weakness and poor stress tolerance, which is why illness, surgery or trauma tips patients into crisis.
- Aldosterone deficiency: less sodium reabsorption and less potassium and hydrogen ion secretion in the collecting duct, giving salt wasting, hypovolemia, hyponatremia, hyperkalemia and a non-anion gap metabolic acidosis, the same physiology as type 4 renal tubular acidosis. Volume loss drives renin up.
- Adrenal androgen (DHEA) deficiency: matters mainly in women, in whom the adrenals are a major androgen source: low libido and energy.
- ACTH excess: low cortisol removes negative feedback, so the pituitary makes more pro-opiomelanocortin (POMC). Its products, ACTH and other melanocyte-stimulating peptides, darken the skin and mucous membranes.
Causes
| Cause | What to know |
|---|---|
| Autoimmune adrenalitis | Up to 90% in Western countries; 21-hydroxylase antibodies; small, atrophic adrenals on CT |
| APS type 2 (Schmidt syndrome) | Adrenal insufficiency + autoimmune thyroid disease ± type 1 diabetes; adults (peak around age 30); HLA-linked, polygenic |
| APS type 1 (APECED) | AIRE mutation, autosomal recessive; childhood; at least two of chronic mucocutaneous candidiasis, hypoparathyroidism and adrenal insufficiency |
| Infection | Tuberculosis and histoplasmosis (enlarged, often calcified adrenals), HIV, CMV, other fungi |
| Adrenal hemorrhage | Meningococcemia (Waterhouse-Friderichsen syndrome), DIC, trauma |
| Infiltration or tumor | Bilateral metastases, lymphoma, amyloidosis, sarcoidosis, hemochromatosis |
| Drugs | Ketoconazole and etomidate block cortisol synthesis |
| Genetic | Congenital adrenal hyperplasia is the most common cause in children; X-linked adrenoleukodystrophy (ABCD1, very long-chain fatty acids toxic to adrenal cortex and myelin) in boys and men |
The 2016 Endocrine Society guideline advises testing males with negative 21-hydroxylase antibodies for adrenoleukodystrophy with plasma very long-chain fatty acids. Meningococcal adrenal hemorrhage has its own Waterhouse-Friderichsen breakdown.
Presentation
- Symptoms are nonspecific and slow: weakness, fatigue, anorexia, weight loss, nausea, vomiting, abdominal pain, dizziness and orthostatic hypotension. Salt craving is the one specific symptom.
- Hyperpigmentation: diffuse darkening of exposed and unexposed skin, accentuated over skin folds such as the palmar creases, pressure points, extensor surfaces and scars, with bluish-black patches on the gums, lips and buccal mucosa and darker areolae.
- Labs: sodium below 135 mEq/L, potassium above 5 mEq/L, low bicarbonate, raised BUN (prerenal), fasting hypoglycemia, eosinophilia and relative lymphocytosis.
- Associated autoimmunity: thyroid disease, type 1 diabetes, premature ovarian failure, celiac disease and autoimmune gastritis with B12 deficiency (the guideline suggests periodic screening for these, for example yearly), plus vitiligo.
Diagnosis
- Morning cortisol and plasma ACTH together. When a cosyntropin test isn't feasible, the Endocrine Society treats a morning cortisol below 5 µg/dL (140 nmol/L), read with the ACTH, as a preliminary result suggesting adrenal insufficiency; once cortisol deficiency is confirmed, an ACTH more than twice the upper reference limit is consistent with primary disease. Merck treats ACTH of 50 pg/mL or more with cortisol below 5 µg/dL as diagnostic.
- Standard cosyntropin (ACTH) stimulation test, the preferred confirmatory test: 250 µg IV or IM, cortisol at 0, 30 and 60 minutes. A peak below 18 µg/dL (500 nmol/L) indicates adrenal insufficiency; the cut-off is assay dependent. The 1-µg test is suggested only when cosyntropin is in short supply.
- Plasma renin and aldosterone: high renin with low or inappropriately normal aldosterone confirms mineralocorticoid deficiency.
- Find the cause: 21-hydroxylase antibodies first; very long-chain fatty acids in antibody-negative males; adrenal CT if antibodies are negative (enlarged or calcified glands suggest TB, fungal infection, hemorrhage or metastases).
| Test | Primary | Secondary or tertiary |
|---|---|---|
| Baseline ACTH | High | Low or inappropriately normal |
| Standard cosyntropin test | No adequate rise | Often blunted too, because the unstimulated adrenals atrophy |
| Prolonged ACTH stimulation (over 24 hours) | Still no rise | Cortisol eventually rises |
| Renin and aldosterone | Renin high, aldosterone low | Normal |
The ACTH level, not the cosyntropin result alone, is what separates primary from secondary disease.
Treatment
- Glucocorticoid: hydrocortisone 15-25 mg/day in 2-3 doses, the largest on waking (for example 10 mg, 5 mg, 5 mg), avoiding a dose just before bed; prednisolone 3-5 mg/day is an alternative. Dexamethasone is avoided (hard to titrate, Cushingoid side effects).
- Mineralocorticoid: fludrocortisone once daily, starting at 50-100 µg (the label's usual dose is 0.1 mg), without salt restriction, titrated to blood pressure, potassium and the absence of orthostatic symptoms. Too much causes hypertension, edema and hypokalemia.
- DHEA: an optional 6-month trial for women with low libido, low mood or low energy despite optimal replacement.
- Sick-day rules: double the hydrocortisone dose for fever above 38°C and triple it above 39°C until recovery (usually 2-3 days); switch to injected hydrocortisone (a 100-mg emergency kit for IM or subcutaneous use) if vomiting. Every patient needs a steroid emergency card and medical alert ID.
- Thyroid trap: giving levothyroxine to someone with untreated adrenal insufficiency can precipitate an adrenal crisis, so replace cortisol first when both are deficient (APS type 2).
- Secondary adrenal insufficiency needs only the glucocorticoid: the intact adrenals still make aldosterone.
Adrenal crisis
- Triggers: infection, surgery, trauma, vomiting or missed doses, and abrupt withdrawal of long-term glucocorticoids.
- Picture: profound weakness, severe abdominal, low back or leg pain, vomiting, vascular collapse and fever or hypothermia, with hyponatremia, hyperkalemia, hypoglycemia and azotemia. In partial insufficiency, shock and fever may be the only signs.
- Treat first: draw cortisol and ACTH if it causes no delay, then give hydrocortisone 100 mg IV, followed by 200 mg per 24 hours (continuous infusion or 50 mg every 6 hours), plus 1 L of isotonic saline (or 5% dextrose in saline) within the first hour. Fludrocortisone is unnecessary while hydrocortisone doses are this high. Cosyntropin testing waits until the patient recovers.
- More on acute vs chronic presentations: adrenal insufficiency question breakdown.
How USMLE tests it
- Long-term prednisone stopped abruptly → tertiary (and secondary) insufficiency: low ACTH, no hyperpigmentation, normal potassium.
- Hyponatremia alone does not make it primary. Cortisol deficiency raises ADH, so secondary disease can cause hyponatremia too; hyperkalemia is the primary-only clue.
- Waterhouse-Friderichsen: meningococcemia with a petechial or purpuric rash and refractory shock = bilateral adrenal hemorrhage.
- Newborn with salt wasting (and ambiguous genitalia in a 46,XX infant) = 21-hydroxylase deficiency, a congenital cause of primary adrenal insufficiency rather than acquired (usually autoimmune) Addison disease; see the congenital adrenal hyperplasia chart.
- Mirror image: primary hyperaldosteronism gives hypertension, hypokalemia, metabolic alkalosis, low renin and high aldosterone.
Practice question
A 34-year-old woman has 5 months of fatigue, a 6-kg weight loss, nausea and light-headedness on standing. She has Hashimoto thyroiditis treated with levothyroxine and now craves salty food. Blood pressure is 96/60 mm Hg supine and 80/50 mm Hg standing. Her palmar creases, gums and a recent scar are darkly pigmented. Serum sodium is 128 mEq/L, potassium 5.9 mEq/L, bicarbonate 19 mEq/L and glucose 64 mg/dL, and her blood count shows eosinophilia. Which set of findings is most likely?
A. High ACTH, high renin, low aldosterone B. Low ACTH, normal renin, normal aldosterone C. Normal ACTH, low renin, high aldosterone D. High ACTH, low renin, low aldosterone E. High ACTH, high cortisol, normal renin
Answer: A. Hyperpigmentation, hyperkalemia, hyponatremia, hypoglycemia, eosinophilia and a personal history of autoimmune thyroid disease point to autoimmune primary adrenal insufficiency (APS type 2). A failed cortex means low cortisol (so ACTH rises) and low aldosterone (so volume depletion pushes renin up).
- B: secondary or tertiary adrenal insufficiency. Low ACTH cannot cause hyperpigmentation, and the intact renin-aldosterone axis prevents hyperkalemia.
- C: primary hyperaldosteronism: hypertension, hypokalemia and metabolic alkalosis, the opposite of this patient.
- D: 11β-hydroxylase deficiency (congenital adrenal hyperplasia): high ACTH drives the mineralocorticoid 11-deoxycorticosterone, causing hypertension and hypokalemia, and the mineralocorticoid excess suppresses renin and aldosterone.
- E: Cushing disease: an ACTH-secreting pituitary adenoma raises cortisol. She has every sign of cortisol deficiency instead.
Key takeaways
- Addison disease = primary adrenal insufficiency: low cortisol, low aldosterone, high ACTH, high renin.
- Hyperkalemia and hyperpigmentation separate primary from secondary or tertiary disease; salt craving is the only specific symptom.
- Autoimmune (21-hydroxylase antibodies) in up to 90% in Western countries; also TB, hemorrhage (Waterhouse-Friderichsen), metastases, ketoconazole or etomidate, adrenoleukodystrophy in males.
- Diagnose with morning cortisol plus ACTH, then the 250-µg cosyntropin test (peak below 18 µg/dL = insufficiency).
- Treat with hydrocortisone 15-25 mg/day in divided doses plus fludrocortisone; double or triple doses during febrile illness; replace cortisol before thyroid hormone.
- Adrenal crisis: hydrocortisone 100 mg IV and 1 L isotonic saline within the first hour, before any confirmatory test.
Sources
- Diagnosis and Treatment of Primary Adrenal Insufficiency: An Endocrine Society Clinical Practice Guideline — Journal of Clinical Endocrinology & Metabolism (2016)
- Primary Adrenal Insufficiency guideline summary — Endocrine Society (2016)
- Diagnosis and Therapy of Glucocorticoid-Induced Adrenal Insufficiency (ESE/Endocrine Society joint guideline) — Endocrine Society (2024)
- Addison Disease — Merck Manual Professional Edition (2026)
- Secondary Adrenal Insufficiency — Merck Manual Professional Edition (2026)
- Polyglandular Deficiency Syndromes — Merck Manual Professional Edition (2025)
- Congenital Adrenal Hyperplasia Caused by 11beta-Hydroxylase Deficiency — Merck Manual Professional Edition (2026)
- Addison Disease — StatPearls, NCBI Bookshelf (2024)
- Autoimmune Polyendocrinopathy-Candidiasis-Ectodermal Dystrophy — MedlinePlus Genetics (2020)
- X-Linked Adrenoleukodystrophy — MedlinePlus Genetics (2022)
- Fludrocortisone Acetate Tablets label — DailyMed (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
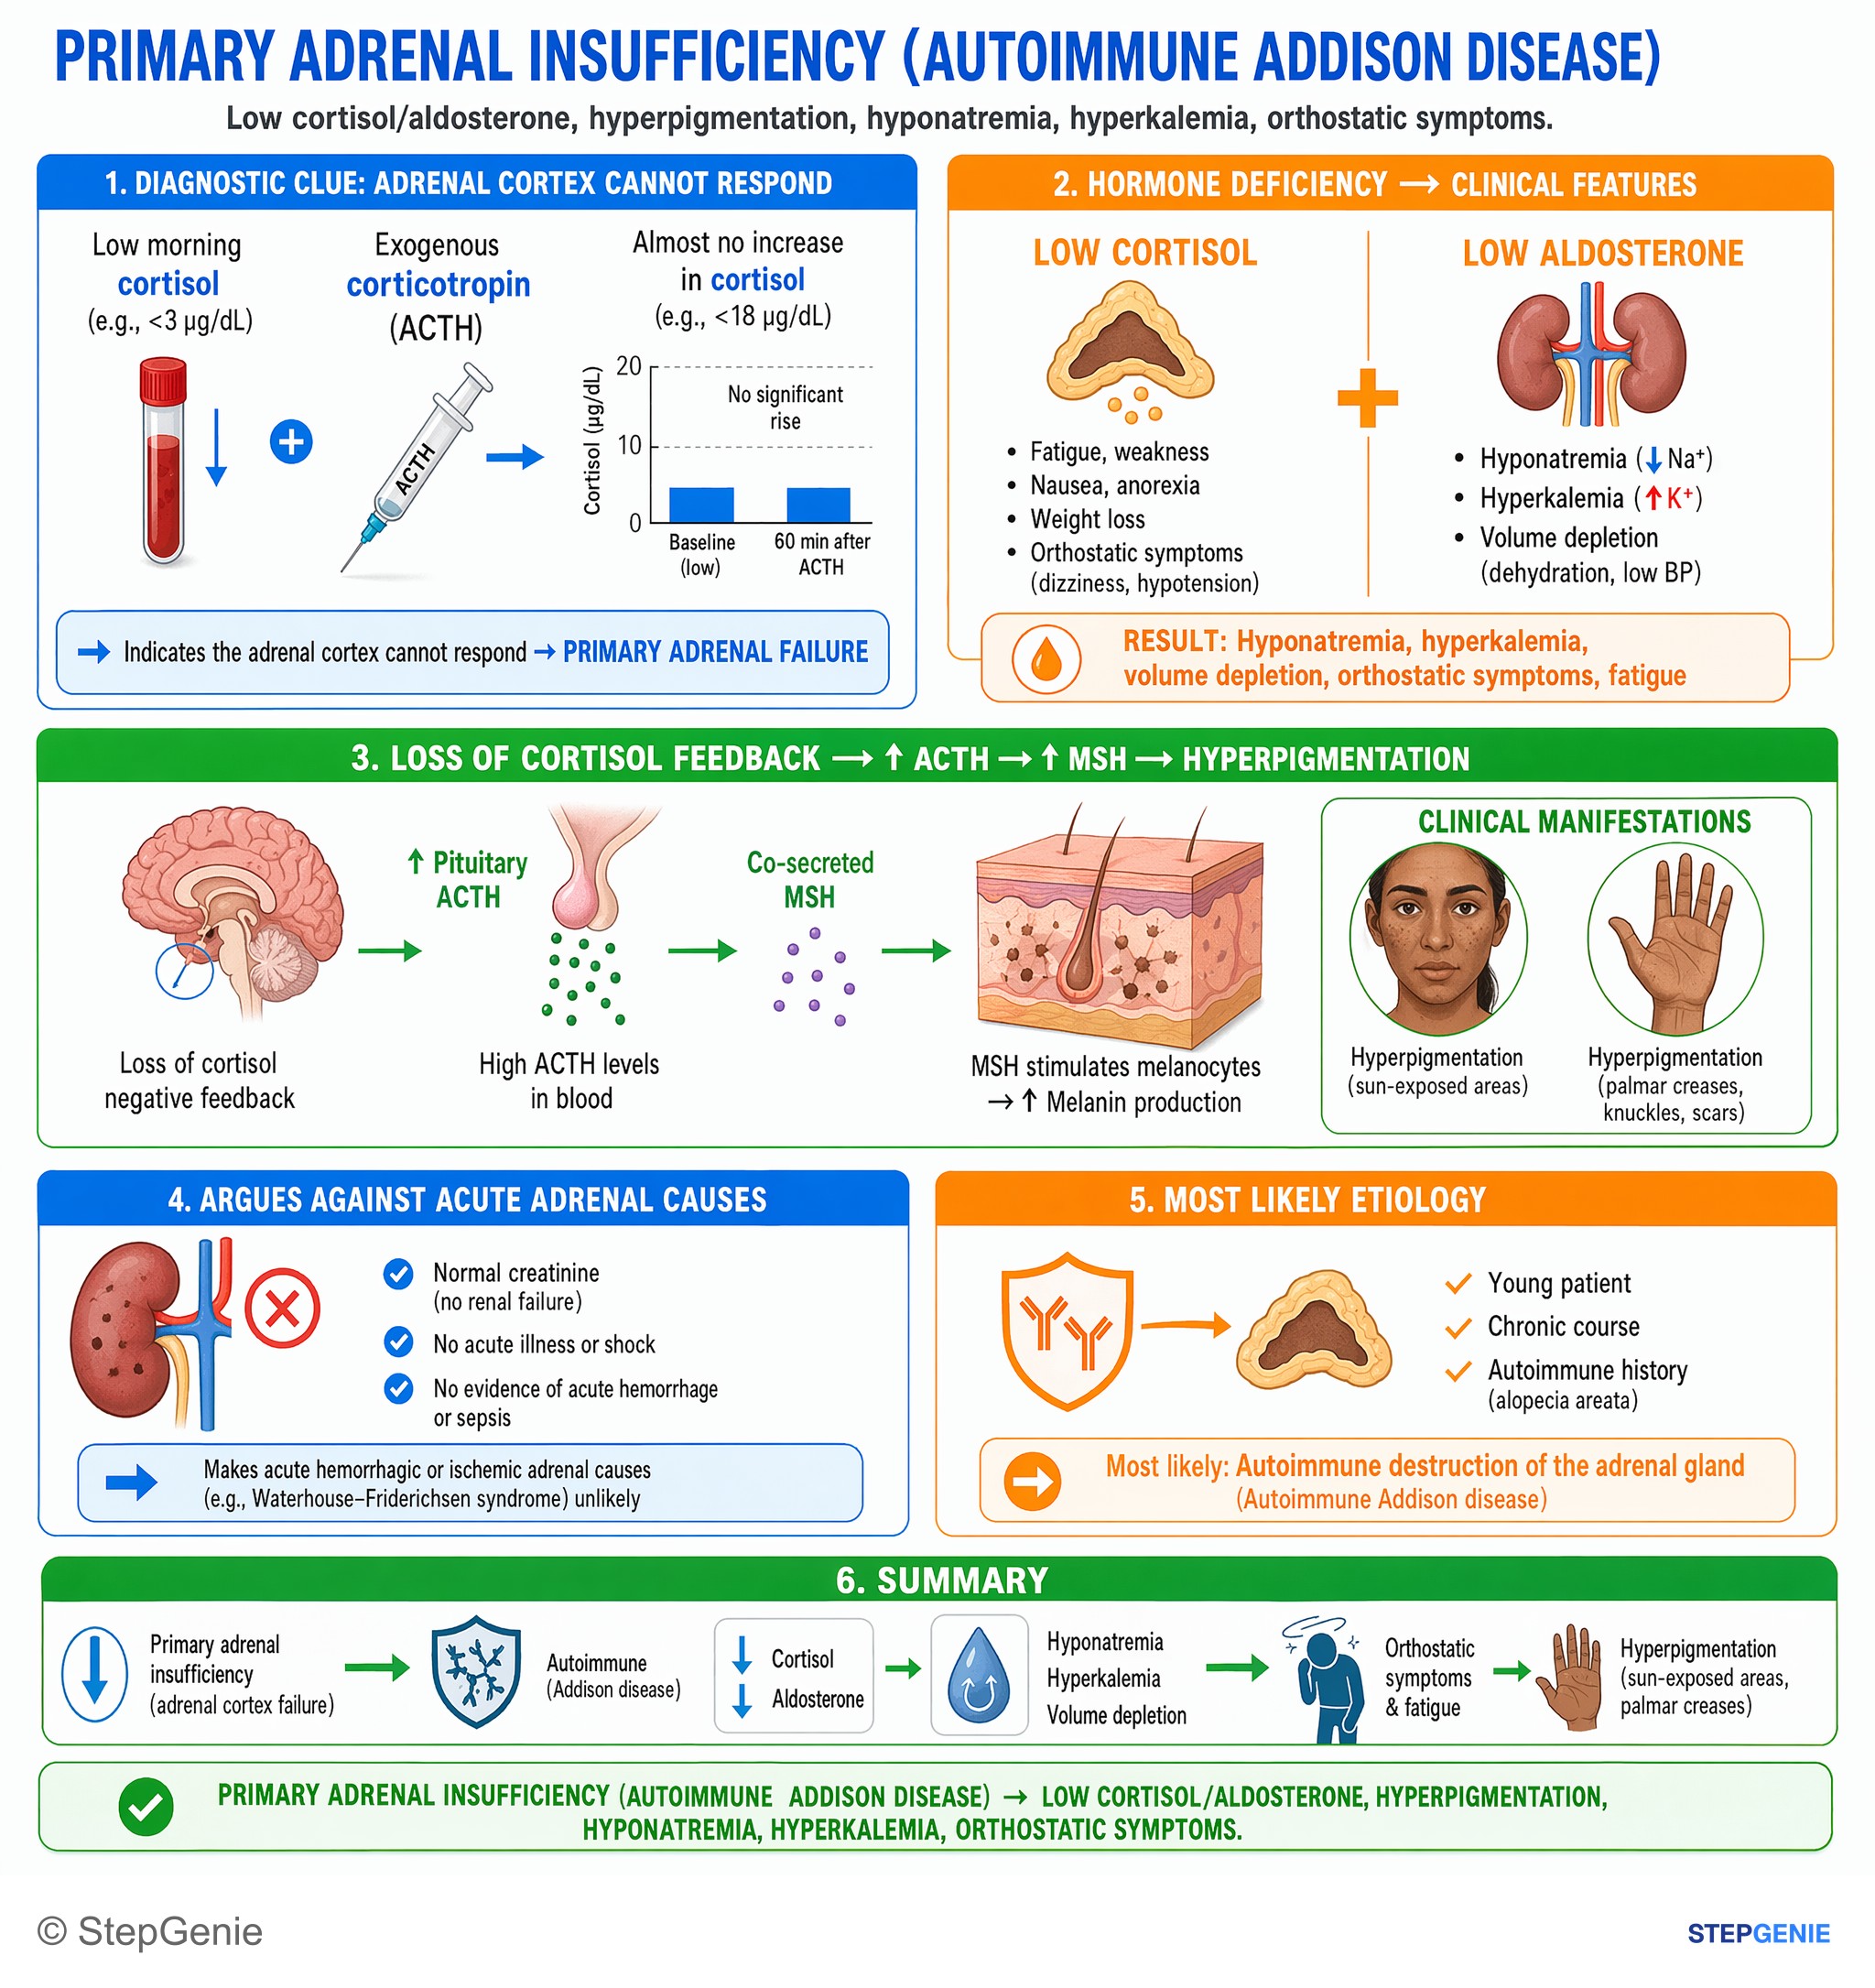
Primary adrenal insufficiency (autoimmune Addison disease) → low cortisol/aldosterone, hyperpigmentation, hyponatremia, hyperkalemia…
USMLE Step 1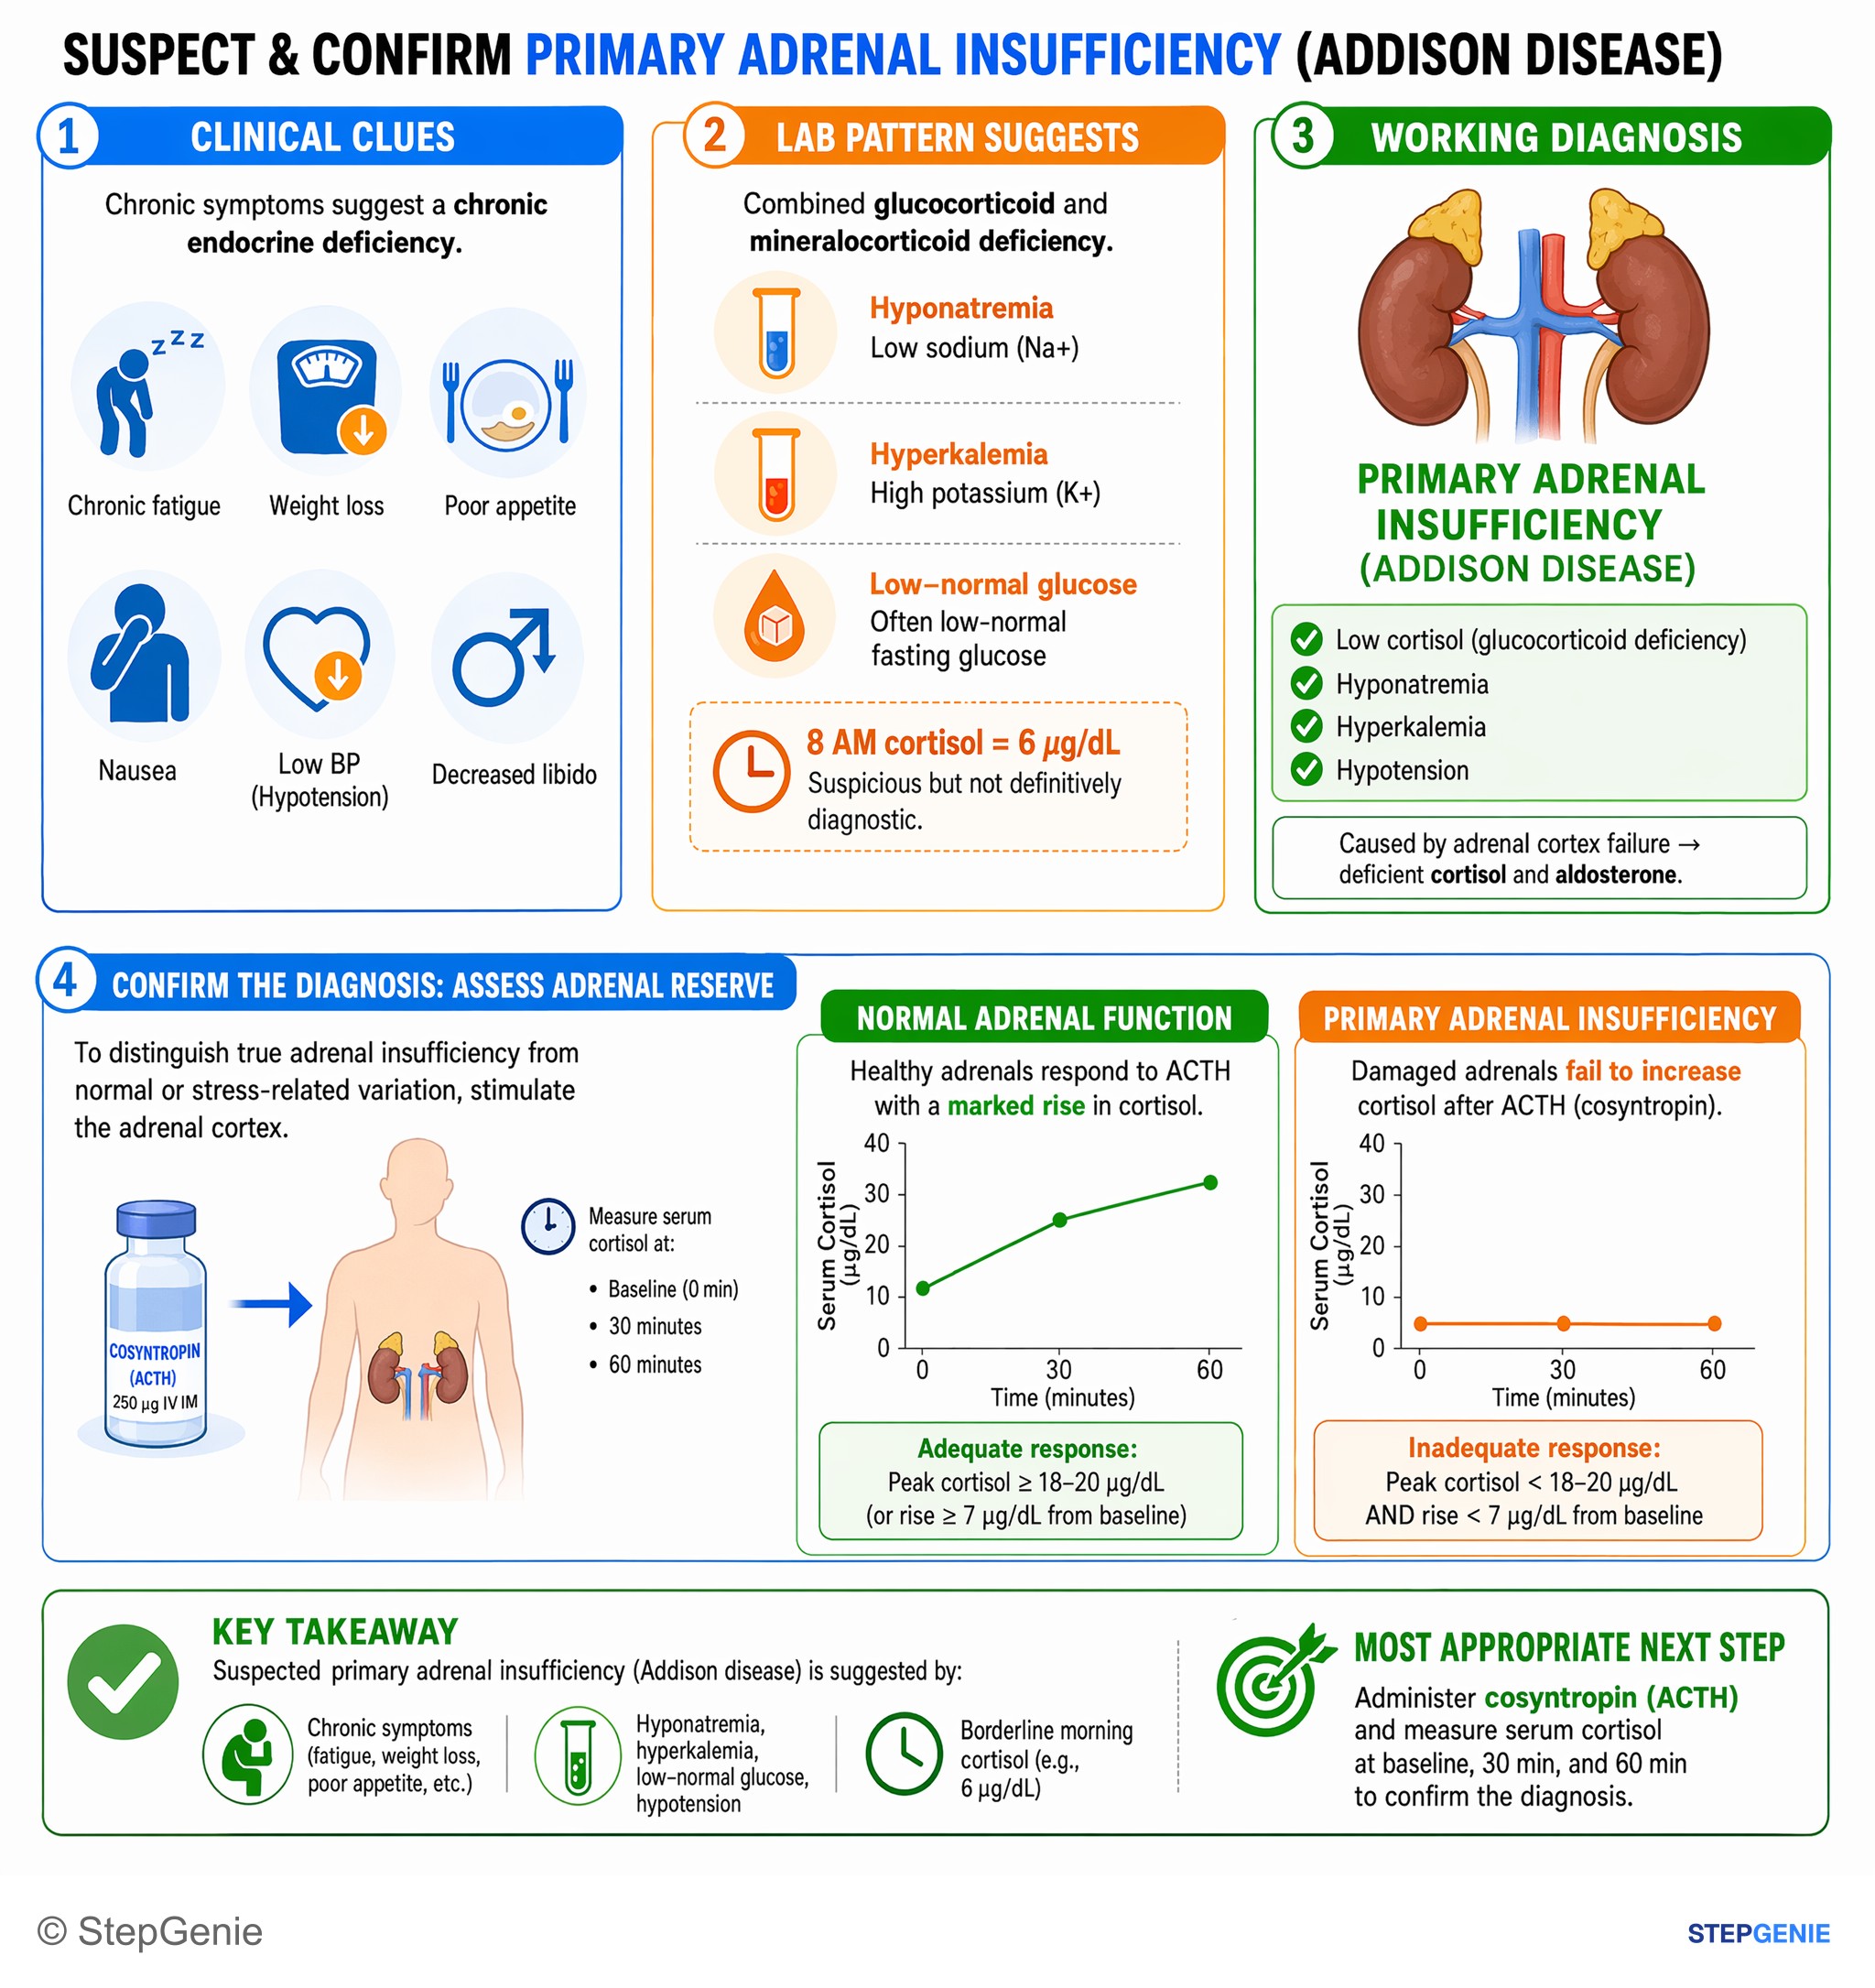
Primary adrenal insufficiency (Addison disease) → low cortisol, hyponatremia, hyperkalemia, hypotension; confirm with cosyntropin (ACTH)…
USMLE Step 2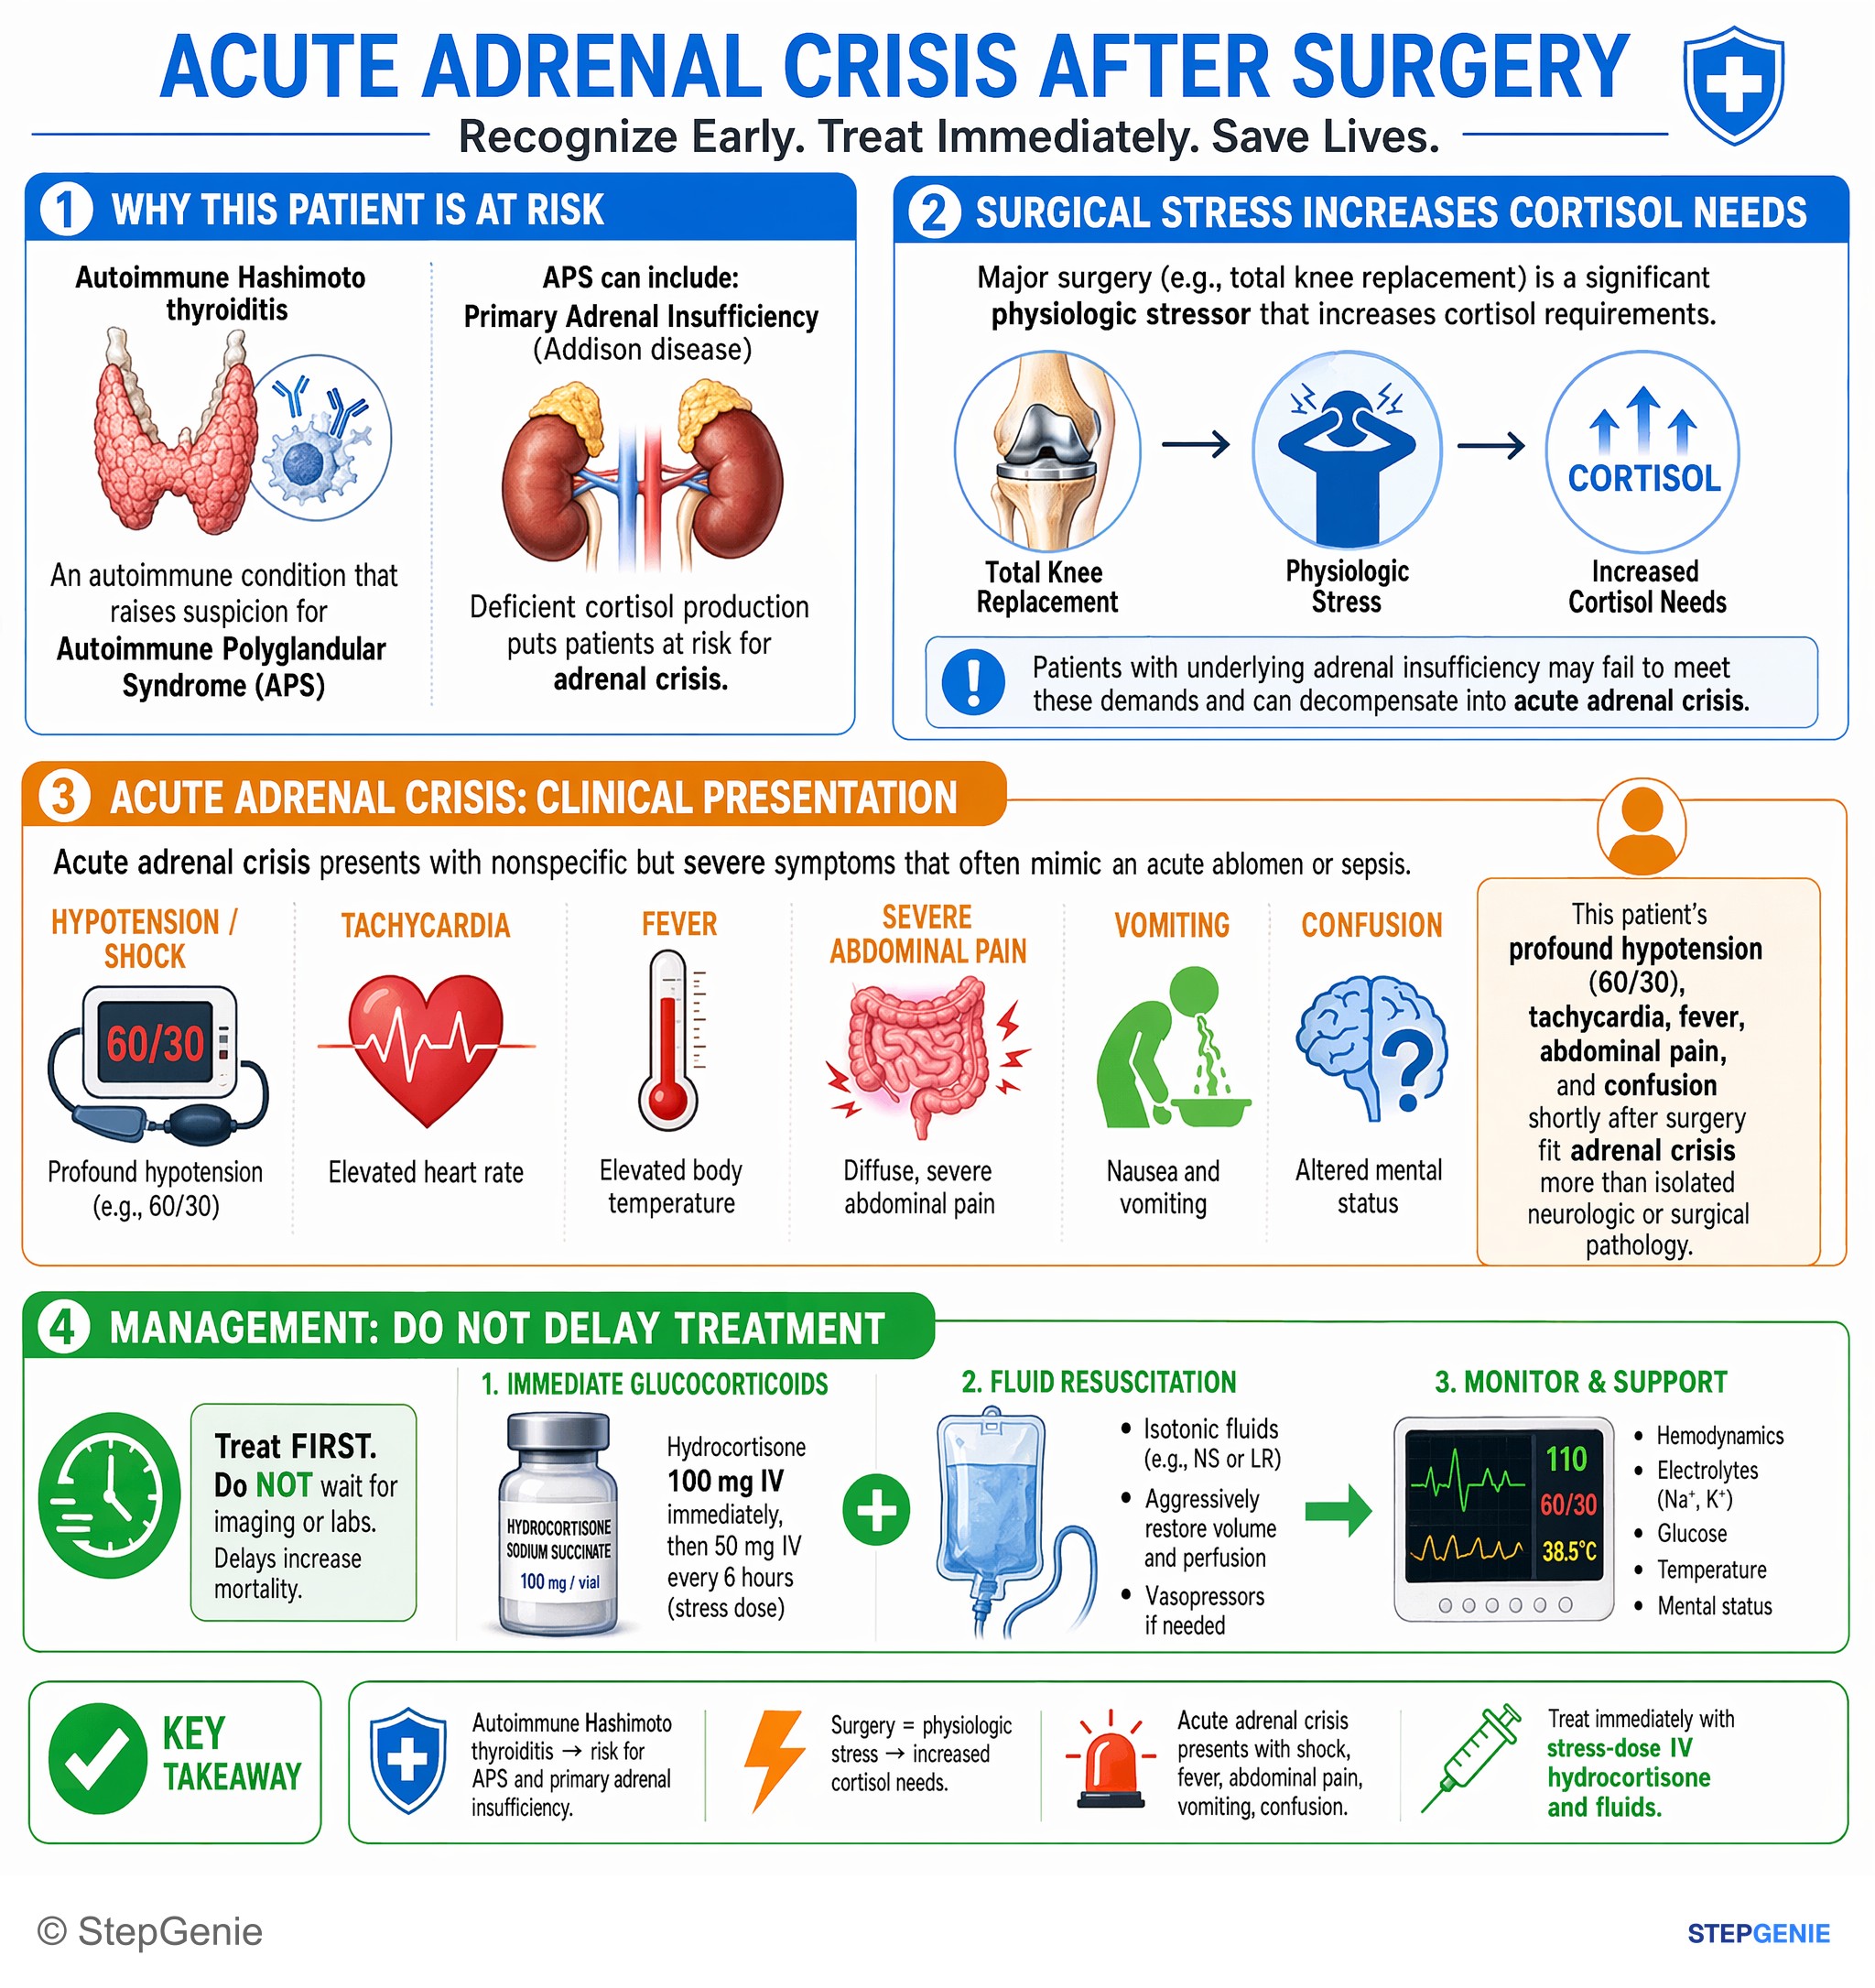
Acute adrenal crisis postoperatively presents with shock, fever, abdominal pain, and confusion; treat immediately with stress-dose IV…
USMLE Step 2Frequently Asked Questions
What is the difference between Addison disease and secondary adrenal insufficiency?
Addison disease is primary adrenal insufficiency: the adrenal cortex fails, so cortisol and aldosterone are both low while ACTH and renin are high. Secondary adrenal insufficiency comes from too little pituitary ACTH, so cortisol is low but aldosterone is preserved by the renin-angiotensin system. As a result, hyperkalemia and hyperpigmentation occur only in primary disease, and only primary disease needs fludrocortisone. Hyponatremia can occur in both.
Why does Addison disease cause hyperpigmentation?
Low cortisol removes negative feedback on the pituitary, which increases production of pro-opiomelanocortin (POMC). POMC is cleaved into ACTH and other melanocyte-stimulating peptides, and the excess stimulates melanocytes. The darkening is diffuse but most obvious in skin folds such as the palmar creases, pressure points, extensor surfaces, scars and the gums and buccal mucosa. Secondary adrenal insufficiency does not cause hyperpigmentation because ACTH is low.
Why does Addison disease cause hyperkalemia and hyponatremia?
Aldosterone normally makes the collecting duct reabsorb sodium and secrete potassium and hydrogen ions. In Addison disease aldosterone is lost along with cortisol, so the kidney wastes sodium and water and retains potassium and acid, giving hyponatremia, hyperkalemia, volume depletion and a non-anion gap metabolic acidosis. Cortisol deficiency also raises ADH, which adds to the hyponatremia. Volume depletion pushes renin up.
How is Addison disease diagnosed?
Start with a morning serum cortisol and plasma ACTH drawn together: a very low cortisol with a high ACTH points to primary adrenal insufficiency. The standard confirmatory test is the cosyntropin stimulation test, giving 250 micrograms of synthetic ACTH and measuring cortisol at 30 and 60 minutes; a peak below 18 µg/dL (500 nmol/L) indicates adrenal insufficiency. High renin with low aldosterone confirms mineralocorticoid deficiency, and 21-hydroxylase antibodies identify autoimmune disease.
What is the treatment for Addison disease?
Lifelong replacement of both missing hormones. Hydrocortisone 15 to 25 mg a day is split into two or three doses with the largest on waking, and fludrocortisone, usually started at 50 to 100 micrograms once daily, replaces aldosterone, without salt restriction. During febrile illness the hydrocortisone dose is doubled above 38°C and tripled above 39°C, and injected hydrocortisone is used if the patient is vomiting. Patients carry an emergency injection kit, a steroid emergency card and medical alert identification.
How is an adrenal crisis treated?
Treatment comes before confirmation. Give hydrocortisone 100 mg IV immediately, followed by 200 mg over 24 hours as an infusion or 50 mg every 6 hours, together with rapid isotonic saline, about 1 liter in the first hour, adding dextrose if the patient is hypoglycemic. Blood for cortisol and ACTH can be drawn first only if it causes no delay, and cosyntropin testing waits until the patient has recovered. The trigger, often an infection, is treated at the same time.