Primary hyperparathyroidism (PHPT) is one of those USMLE “free points” topics if you can draw the lab pattern fast: high calcium + high PTH + low phosphate—then connect it to stones, bones, groans, and psychiatric overtones. Let’s lock it in with a quick sketchable visual and the exact high-yield pivots Step loves.
The Draw-it-out Method (30-second sketch)
Grab a scrap paper and draw 3 boxes: Ca, PTH, Phos.
Step 1: Draw the lab triad
- Ca: ↑
- PTH: ↑
- Phosphate (PO): ↓
Step 2: Add the mechanism arrows
Under PTH, draw 3 arrows:
- Bone: ↑ resorption → Ca ↑
- Kidney:
- ↑ Ca reabsorption → Ca ↑
- ↓ phosphate reabsorption (proximal tubule) → Phos ↓
- ↑ 1-hydroxylase → ↑ 1,25-(OH) vitamin D
- Gut (via vitamin D): ↑ Ca absorption
That’s the whole disease in one doodle.
One-liner mnemonic (shareable)
“Primary hyperPTH: the gland is the problem—PTH is high on purpose, Ca follows, phosphate gets dumped.”
Or even tighter:
“PHPT = PTH ↑ → Ca ↑, PO ↓.”
High-yield causes (what Step expects)
Most common etiologies
- Parathyroid adenoma (single benign tumor) — most common
- Parathyroid hyperplasia (often all glands)
- Parathyroid carcinoma — rare but classic for very high Ca + palpable neck mass
Syndrome association
- MEN1: “3 P’s”
Pituitary, Pancreas, Parathyroid - MEN2A can have hyperparathyroidism too (less emphasized than MEN1)
Symptoms: translate the labs into clinical clues
Think hypercalcemia symptoms first:
- Stones: calcium oxalate/phosphate kidney stones
- Bones: bone pain, fractures (increased resorption)
- Groans: constipation, abdominal pain, pancreatitis
- Psychiatric overtones: fatigue, depression, confusion
Extra Step buzzwords:
- Polyuria/polydipsia (hypercalcemia causes nephrogenic DI-like picture)
- Short QT interval on EKG
The “bones” pathology Step likes
Osteitis fibrosa cystica (classic but less common)
Due to excess osteoclast activity (driven by osteoblast RANKL signaling under PTH influence).
Key findings
- Subperiosteal bone resorption
- Bone pain, fractures
- “Brown tumors” (hemorrhage + hemosiderin + fibrous tissue)
Lab pattern table (differentiate like a pro)
| Condition | Ca | PTH | Phosphate | Vitamin D | Notes |
|---|---|---|---|---|---|
| Primary hyperparathyroidism | ↑ | ↑ | ↓ | ↑/N | Adenoma most common |
| Secondary hyperparathyroidism (CKD) | ↓/N | ↑ | ↑ | ↓ | CKD: phosphate retention + low calcitriol |
| Tertiary hyperparathyroidism | ↑ | ↑↑ | ↑ | variable | Autonomous PTH after long-standing secondary (CKD) |
| Familial hypocalciuric hypercalcemia (FHH) | ↑ | N/↑ | N/↓ | N | Low urine Ca (CaSR mutation) |
| Malignancy (PTHrP) | ↑ | ↓ | ↓ | N | Squamous cell, RCC; PTH suppressed |
The classic Step trap: PHPT vs FHH
Both can have high calcium with non-low PTH, so the differentiator is urine calcium.
Draw this mini-box:
- PHPT → high urine calcium
- FHH → low urine calcium
Test to know:
- 24-hour urine calcium
- Calcium/creatinine clearance ratio (CaCrCR) is low in FHH (classically )
Imaging + management (Step 2 flavor, but Step 1 relevant)
Diagnosis basics
- Confirm labs (repeat Ca and PTH)
- Check:
- Phosphate
- 25-OH vitamin D (deficiency can coexist)
- Creatinine/eGFR
- DEXA scan (bone density)
- 24-hour urine calcium (esp. if considering FHH)
Localization (after biochemical diagnosis)
- Sestamibi scan and/or neck ultrasound for adenoma localization
(Don’t “diagnose” solely by imaging—USMLE likes that sequence.)
Treatment
- Definitive: parathyroidectomy (esp symptomatic, kidney stones, osteoporosis, very high Ca)
- If not surgical candidate:
- Cinacalcet (calcimimetic → activates CaSR → lowers PTH)
- Ensure hydration; manage bone density as indicated
Quick-hit memory anchors (what to recall in 5 seconds)
- Labs: Ca ↑, PTH ↑, PO ↓
- Most common cause: parathyroid adenoma
- EKG: short QT
- Differentiate from FHH: urine Ca high in PHPT, low in FHH
- Bone finding: subperiosteal resorption / osteitis fibrosa cystica
Mini self-check (1 question)
A patient has recurrent kidney stones, constipation, fatigue. Labs: Ca 11.6 (high), PTH high, phosphate low. What else is likely?
- Answer you should auto-say: Increased urine calcium and short QT.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
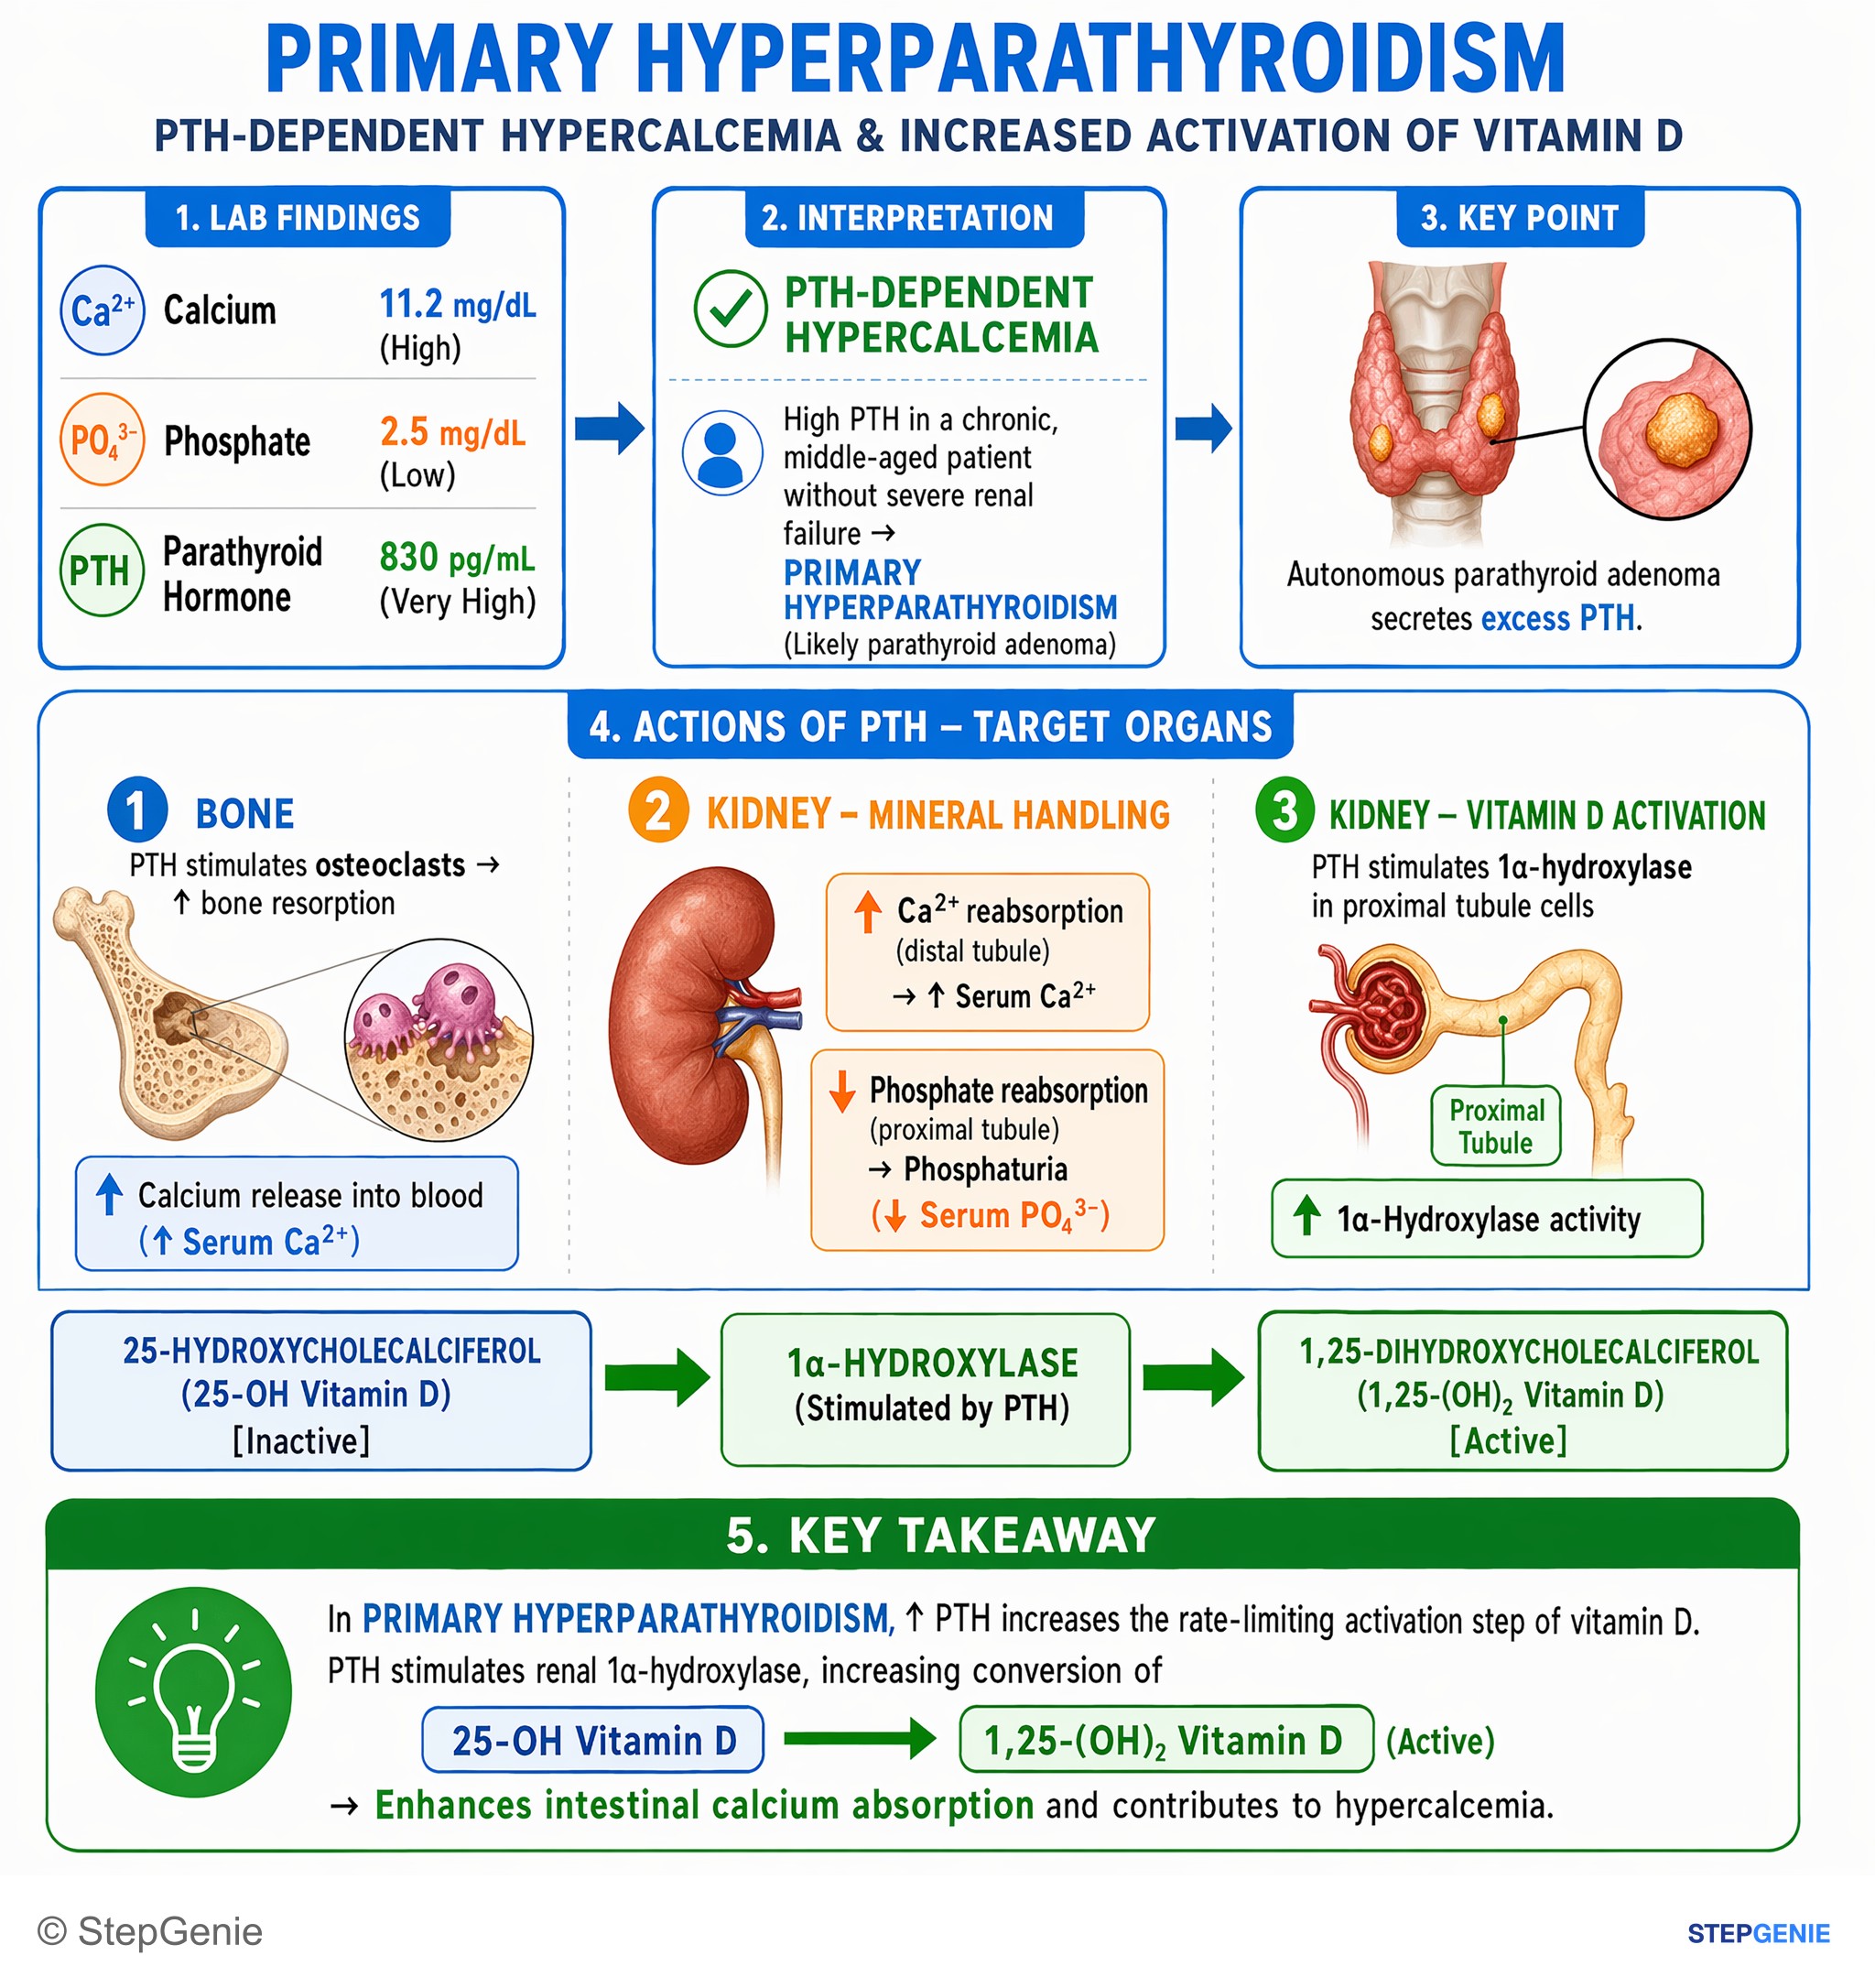
Primary hyperparathyroidism causes ↑PTH, which stimulates renal 1α-hydroxylase, increasing conversion of 25-OH vitamin D to active…
USMLE Step 1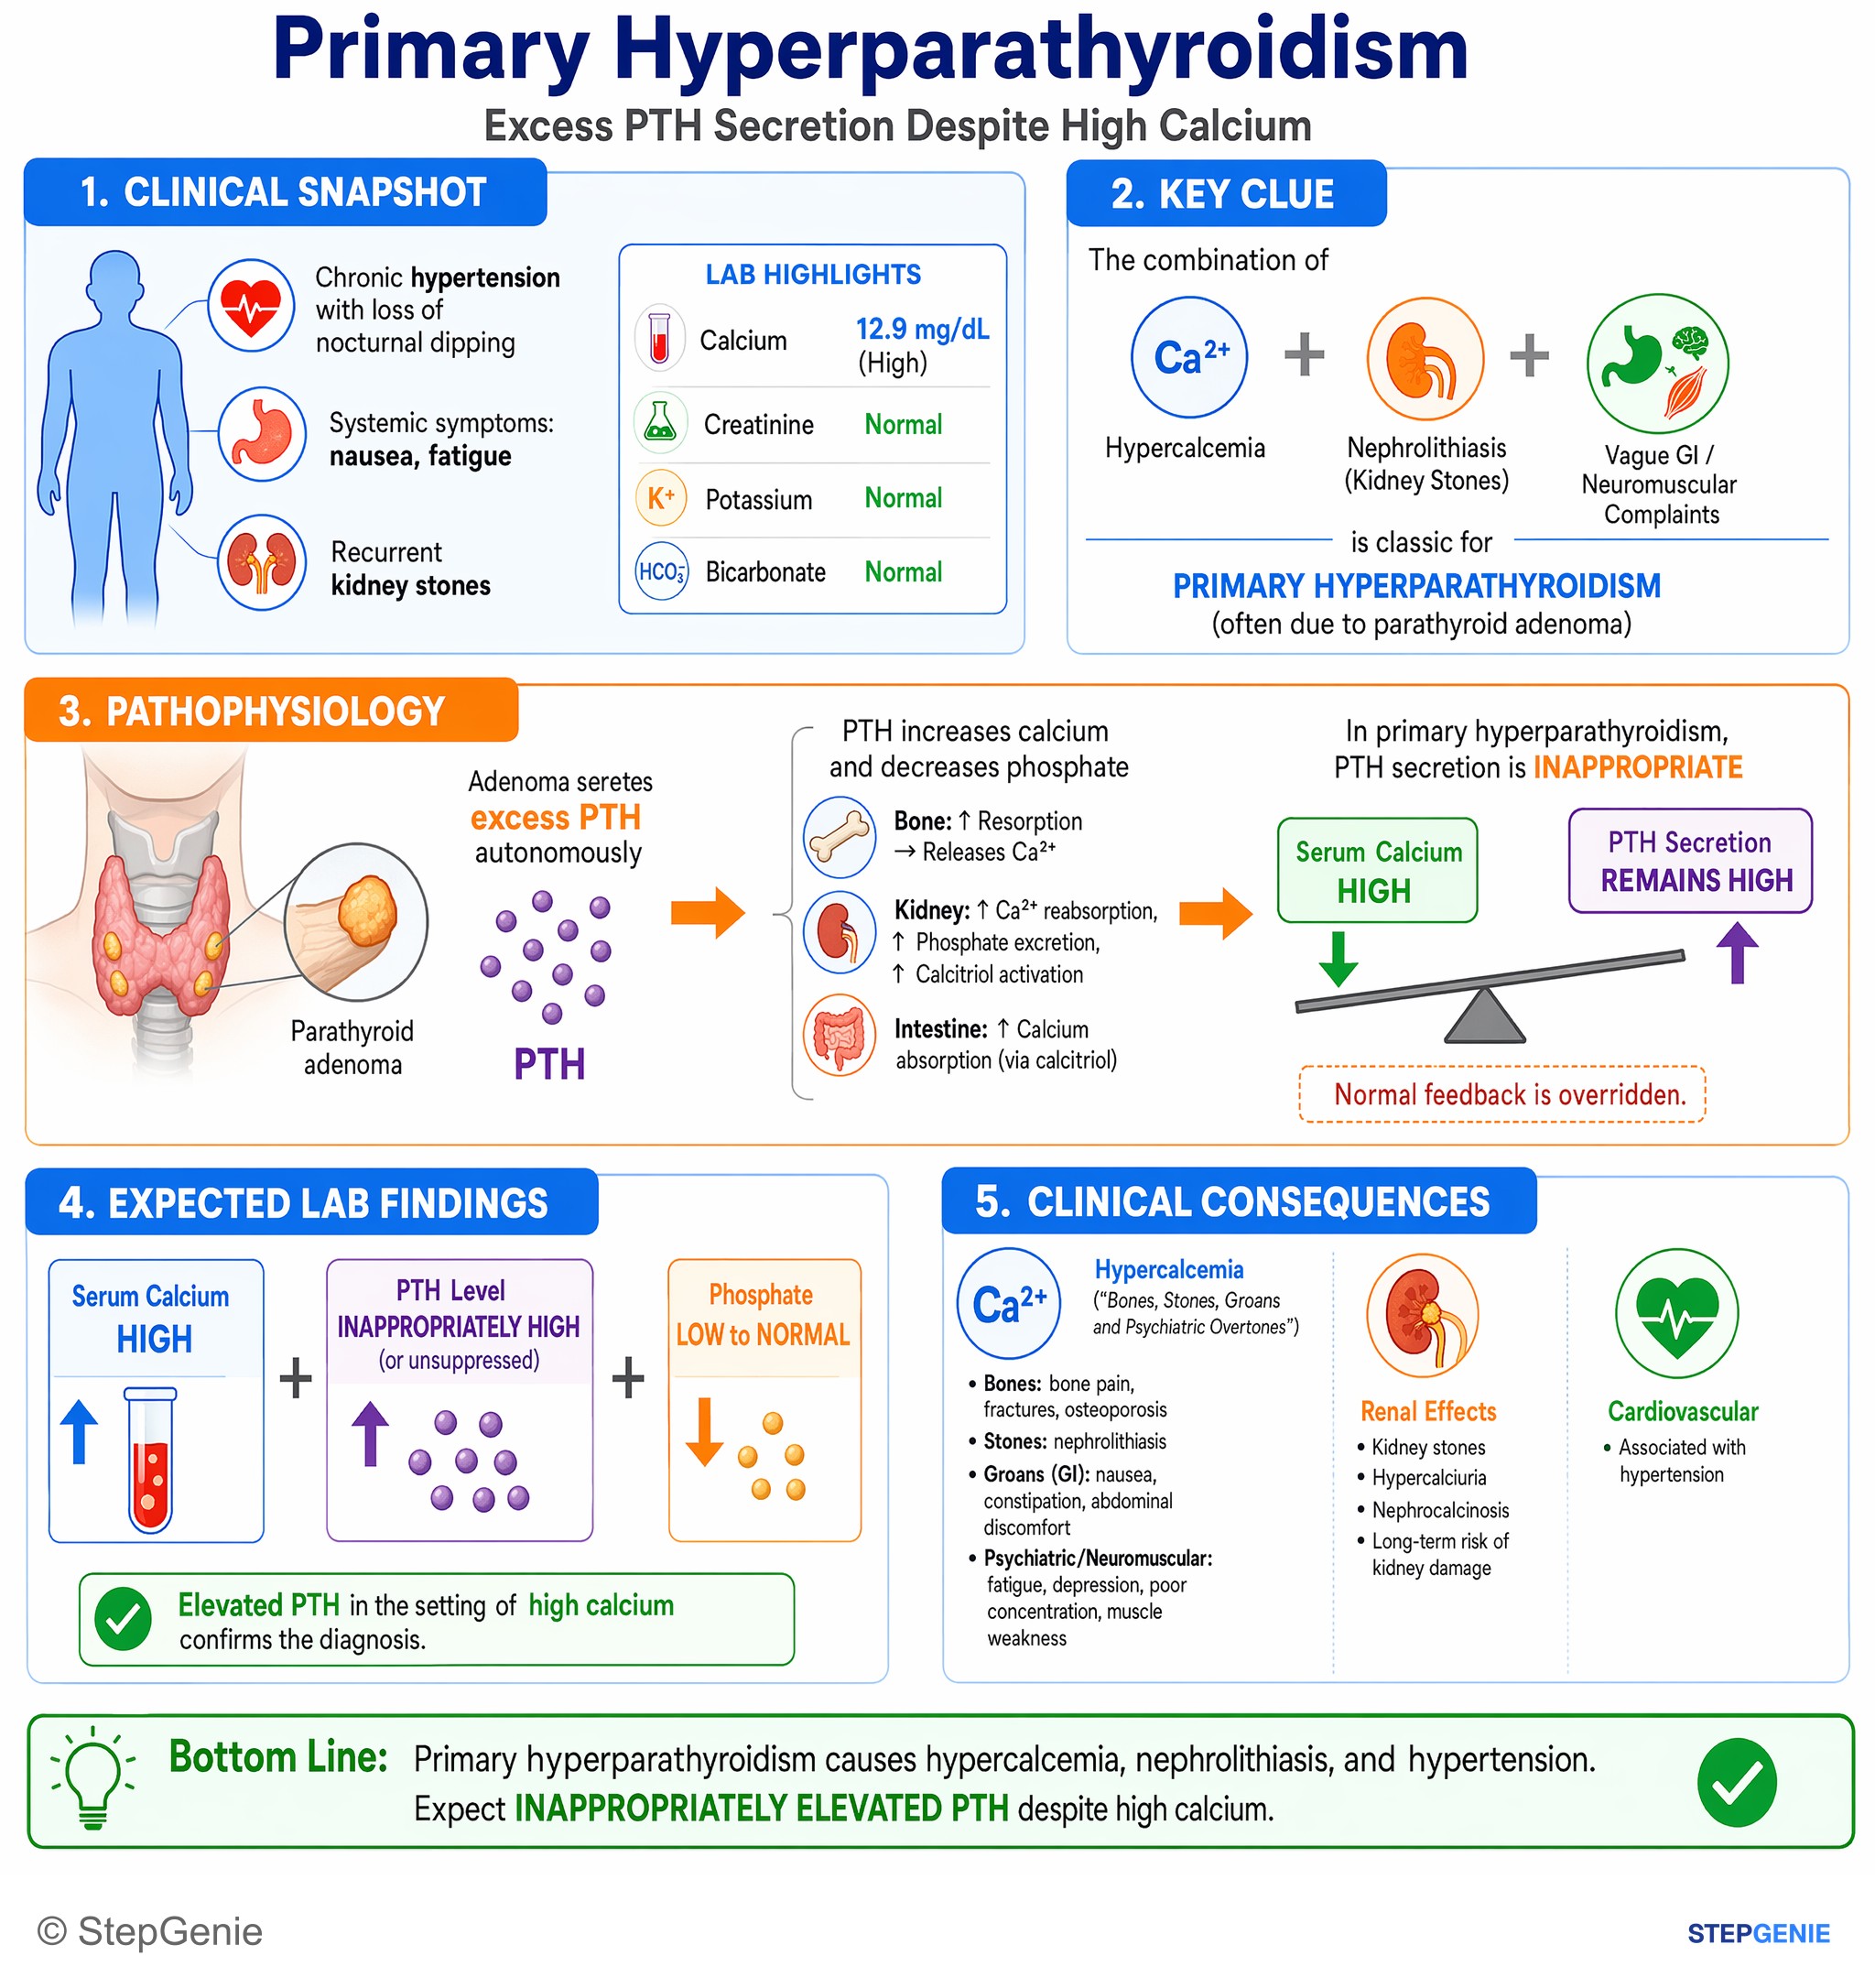
Primary hyperparathyroidism causes hypercalcemia, nephrolithiasis, and hypertension; expect elevated PTH despite high calcium.
USMLE Step 1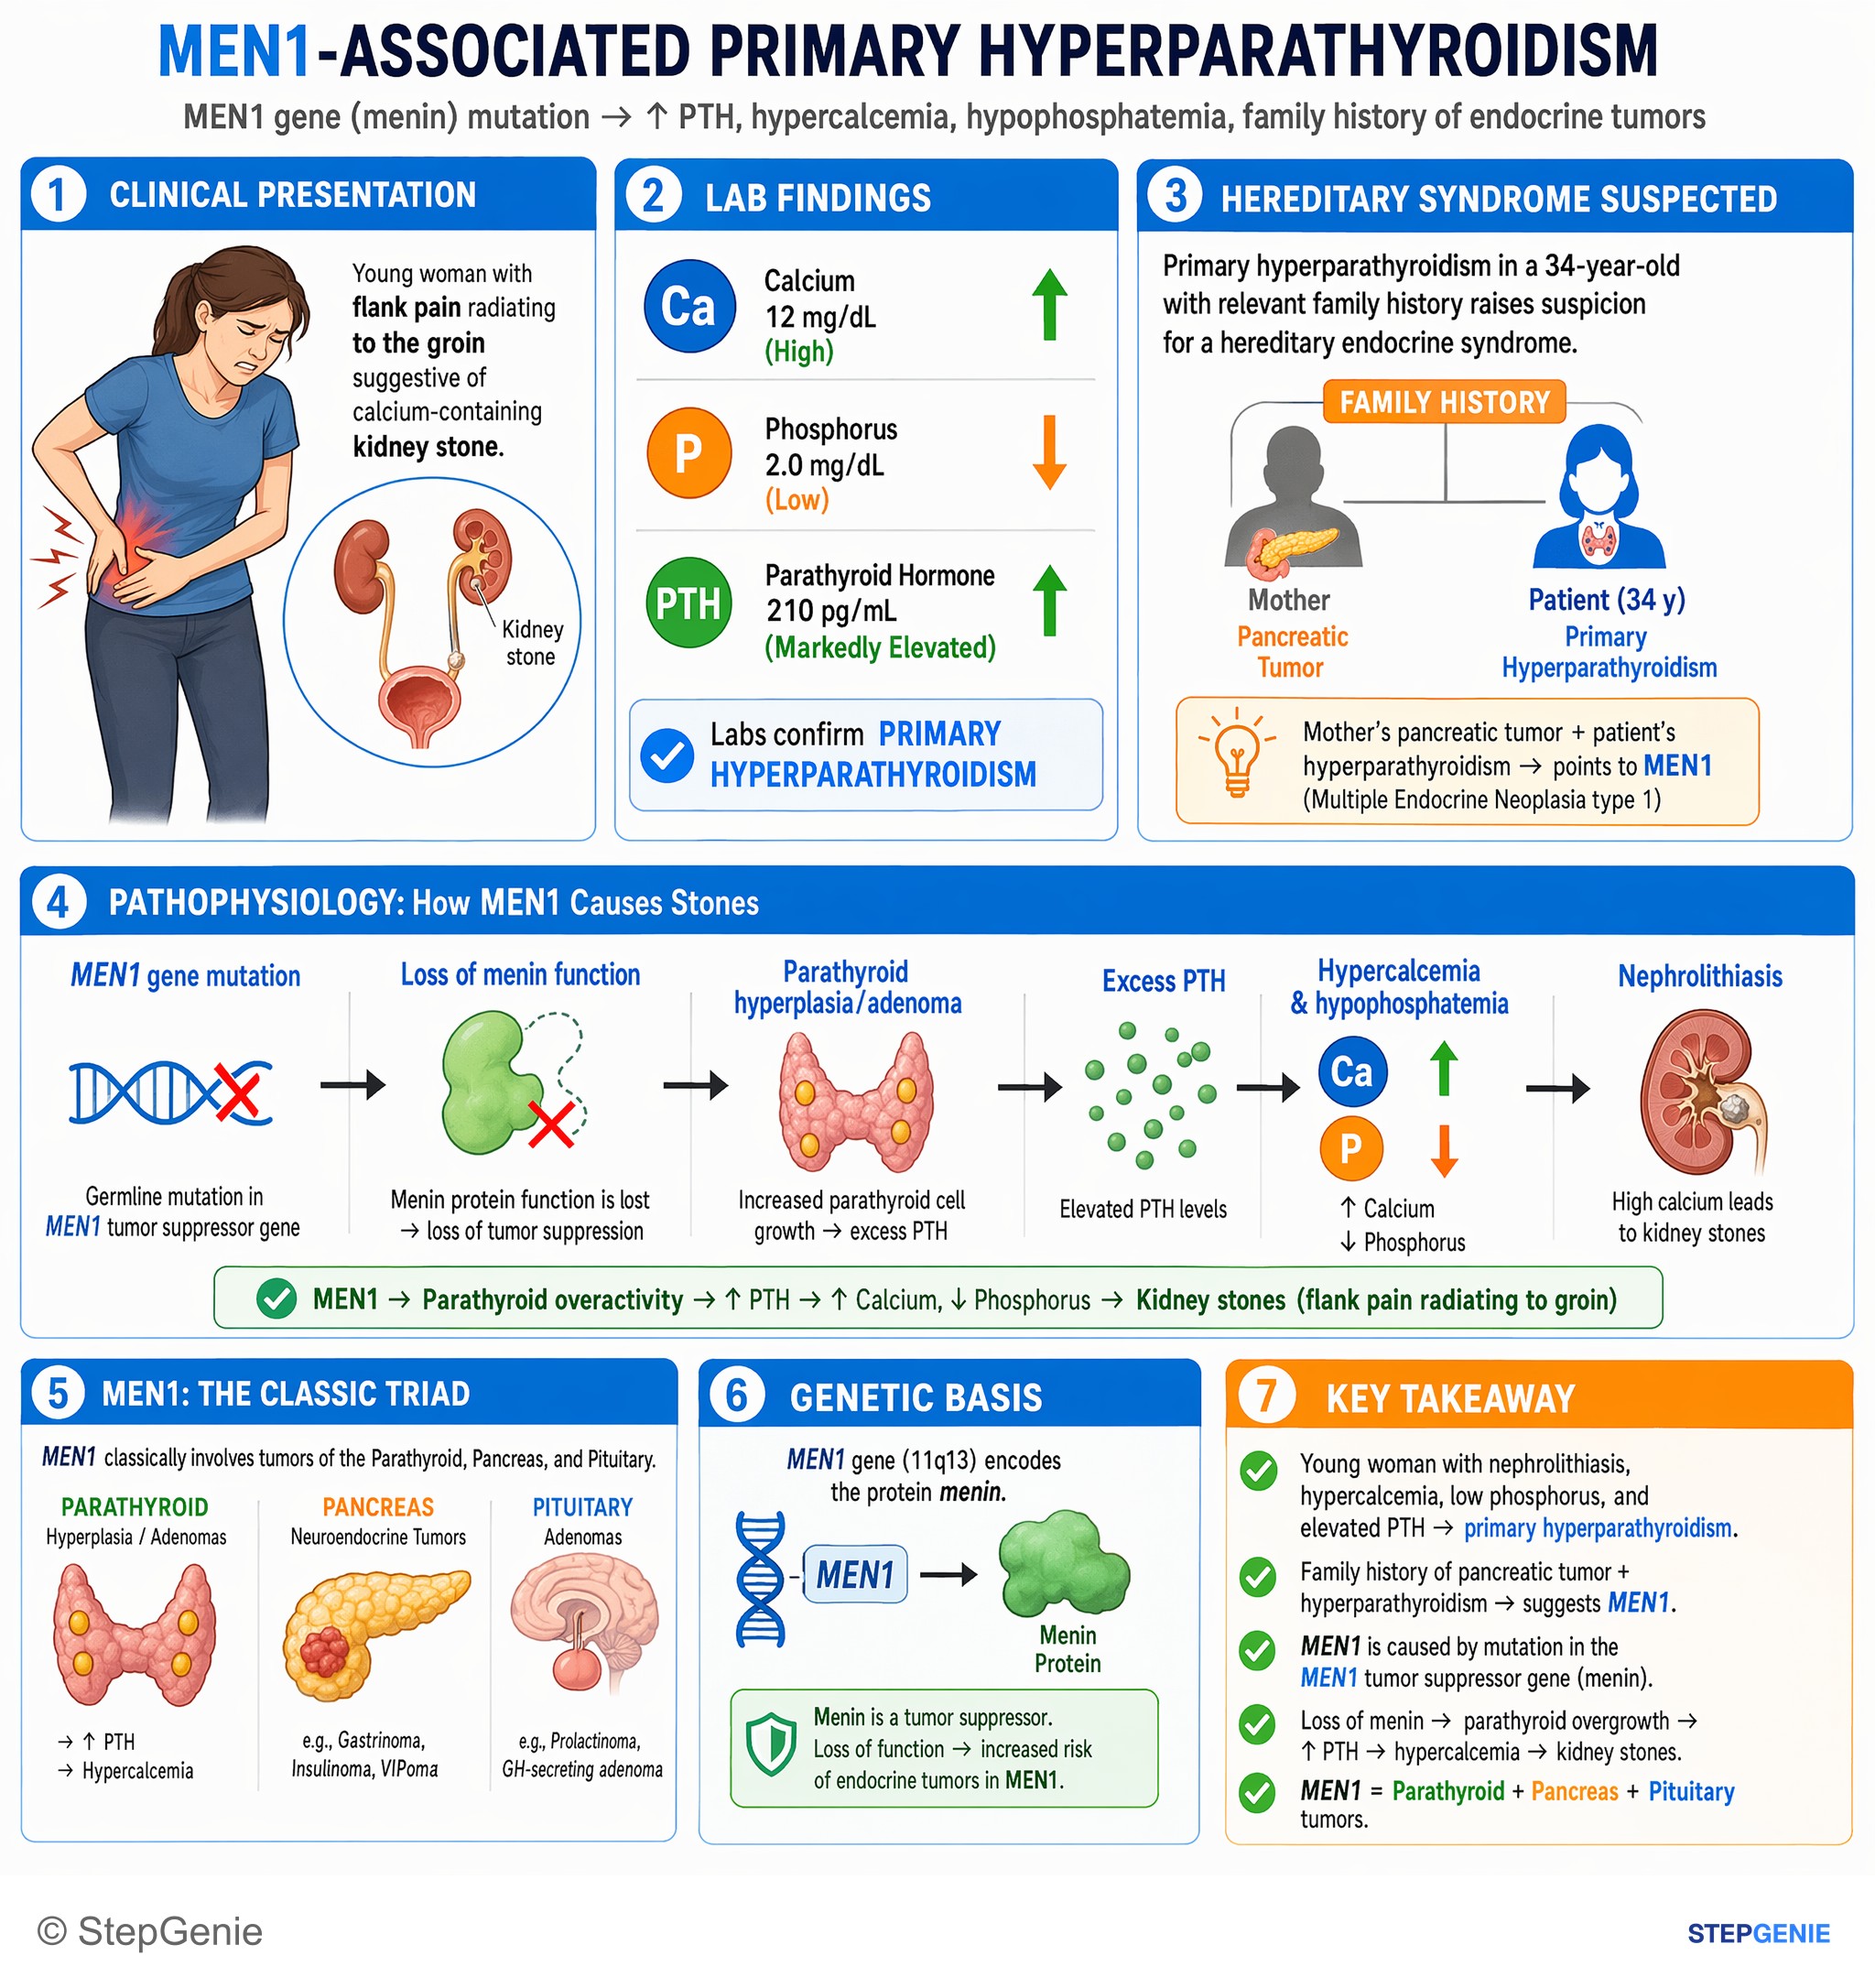
MEN1-associated primary hyperparathyroidism from MEN1 gene (menin) mutation → elevated PTH, hypercalcemia, hypophosphatemia, family…
USMLE Step 1Frequently Asked Questions
What lab pattern points to primary hyperparathyroidism?
Primary hyperparathyroidism classically shows high calcium, high PTH, and low phosphate. This pattern comes from excess PTH increasing bone resorption, increasing renal calcium reabsorption, decreasing phosphate reabsorption in the proximal tubule, and increasing 1-alpha-hydroxylase activity. The rise in active vitamin D then boosts gut calcium absorption, reinforcing the hypercalcemia.
Why does primary hyperparathyroidism cause low phosphate?
Primary hyperparathyroidism causes low phosphate because PTH decreases phosphate reabsorption in the kidney. The key renal effect is phosphate dumping from the proximal tubule, which lowers serum phosphate. At the same time, PTH increases calcium reabsorption, so the typical lab triad becomes high calcium, high PTH, and low phosphate.
How do you tell primary hyperparathyroidism from familial hypocalciuric hypercalcemia?
The main way to distinguish primary hyperparathyroidism from familial hypocalciuric hypercalcemia is urine calcium. Both can present with high calcium and a PTH that is not low, but primary hyperparathyroidism has high urine calcium, whereas familial hypocalciuric hypercalcemia has low urine calcium. A 24-hour urine calcium or a calcium/creatinine clearance ratio helps make the distinction.
What symptoms and exam clues should make you think of primary hyperparathyroidism?
Primary hyperparathyroidism should make you think of hypercalcemia symptoms such as kidney stones, bone pain or fractures, constipation, abdominal pain, pancreatitis, fatigue, depression, and confusion. Common clues also include polyuria and polydipsia from a nephrogenic DI-like effect of hypercalcemia. On EKG, a short QT interval is a classic association.
What is the most common cause and definitive treatment for primary hyperparathyroidism?
The most common cause of primary hyperparathyroidism is a parathyroid adenoma, and the definitive treatment is parathyroidectomy. Other causes include parathyroid hyperplasia and, more rarely, parathyroid carcinoma, which is classically associated with very high calcium and a palpable neck mass. If a patient is not a surgical candidate, cinacalcet can lower PTH by activating the calcium-sensing receptor.