Thyroid cancers come from two cell types, and that one fact sorts all four. Follicular cells give rise to papillary carcinoma (80–90% of cases in Merck's figures: Orphan Annie eye nuclei, psammoma bodies, spread to neck lymph nodes, BRAF V600E), follicular carcinoma (defined by capsular or vascular invasion, spreads through the blood to lung and bone, RAS) and anaplastic carcinoma (older patients, a neck mass that grows over weeks, the worst prognosis). Parafollicular C cells give rise to medullary carcinoma (3–4% per NCI: calcitonin, Congo red–positive amyloid, RET mutations, MEN2). Cancers that still behave like follicular cells keep making thyroglobulin and taking up iodine, so radioactive iodine works for them; anaplastic carcinoma has lost that ability, and medullary carcinoma never had it.
The visual hack: two factories, one ladder, three exits
Sketch this once and most thyroid cancer stems sort themselves.
- Factory 1, the follicular cell, makes thyroglobulin and traps iodine. Hang a ladder under it. The top rung holds the differentiated cancers, papillary and follicular; the middle rungs hold the high-grade (poorly differentiated) cancers; anaplastic sits at the bottom. Each step down loses thyroglobulin, iodine uptake and survival.
- Factory 2, the C cell, makes calcitonin. Its cancer, medullary carcinoma, is tracked with calcitonin and CEA, and its cells do not take up radioactive iodine.
- Three exits. Papillary (and medullary) leave by the lymph door to neck nodes. Follicular (and oncocytic) carcinoma takes the blood door to distant sites such as lung and bone. Anaplastic goes through the wall into the trachea, esophagus and recurrent laryngeal nerve.
Then give each tumor one picture:
| Tumor | Picture it | Hook |
|---|---|---|
| Papillary | Finger-like fronds with fibrovascular cores, pale "Orphan Annie eye" nuclei with grooves and pseudoinclusions, and grains of sand: psammoma bodies (laminated calcifications) | Psammoma bodies, Pale nuclei, Palpable neck nodes, Positive prognosis |
| Follicular | A ball of follicles breaking through its own capsule into a vein | Fence-breaker that travels Far by blood |
| Medullary | Nests of polygonal and spindle cells in amyloid that turns apple-green with Congo red under polarized light | C cell: Calcitonin, CEA, Congo red |
| Anaplastic | Wildly pleomorphic giant and spindle cells with many mitoses | Aged patient, Aggressive growth, Airway trouble |
The big four side by side
| Type | Cell of origin | Share of thyroid cancers | Classic stem clue | Spread |
|---|---|---|---|---|
| Papillary | Follicular cell | About 80–90% (Merck) or about 8 in 10 (American Cancer Society); the most common | Woman aged 30–60, prior neck radiation, palpable neck node | Lymphatic to cervical nodes (about a third of patients); sometimes lung |
| Follicular | Follicular cell | A small minority; estimates run from about 2–4% (Merck) to about 1 in 10 (American Cancer Society) | Older patient, iodine-deficient region; FNA reads "follicular neoplasm" | Hematogenous to lung and bone; nodes uncommon |
| Medullary | Parafollicular C cell | About 3–4% (NCI); under 5% (American Cancer Society) | Nodule with high calcitonin; family history of MEN2; diarrhea or flushing | Lymphatic to cervical and mediastinal nodes; sometimes liver, lung, bone |
| Anaplastic | Follicular cell (undifferentiated) | About 1% (Merck) to 2% (American Cancer Society) | Older adult, hard fixed mass growing over weeks; hoarseness, dysphagia, stridor | Direct invasion of neck structures; distant metastases common |
| Type | Driver genes | Tumor marker | Core treatment | Prognosis |
|---|---|---|---|---|
| Papillary | BRAF V600E (most common); RET/PTC and other fusions | Thyroglobulin (after thyroidectomy) | Surveillance, lobectomy or total thyroidectomy by size and risk; radioactive iodine and TSH suppression if intermediate or high risk | Excellent: 98.4% 5-year survival for papillary and follicular combined (Merck, citing SEER) |
| Follicular | RAS; PAX8::PPARG fusion | Thyroglobulin | Lobectomy for small tumors; total thyroidectomy plus radioactive iodine with extensive vascular invasion | Good, but less favorable than papillary |
| Medullary | RET gain of function (germline in hereditary cases, somatic in some sporadic ones) | Calcitonin, CEA | Exclude pheochromocytoma, then total thyroidectomy with central neck dissection; no radioactive iodine | Intermediate: 86% at 5 years, 65% at 10 years (NCI) |
| Anaplastic | TP53, TERT promoter, often BRAF V600E | None useful | Airway first; surgery if localized; radiation; dabrafenib plus trametinib if BRAF V600E | Worst: all stage IV; median survival historically about 5–6 months (PathologyOutlines) |
Papillary carcinoma: the common one
- Who: female-to-male ratio about 3:1; most present between 30 and 60, and older patients have more aggressive disease (Merck).
- Radiation: ionizing radiation, especially in childhood, is the best-established risk factor. After neck irradiation most new nodules are benign, but about 10% are papillary carcinomas, often multicentric and mostly driven by gene fusions (Merck); RET/PTC rearrangements are the classic papillary fusion.
- The nucleus makes the diagnosis: enlargement, chromatin clearing (Orphan Annie eye), longitudinal grooves and intranuclear pseudoinclusions. Ultrasound shows fine, stippled psammomatous microcalcifications.
- Spread: lymphatic; up to 50% are multifocal (NCI). Neck node metastases are common but rarely make it fatal.
- Treatment (Merck): active surveillance is an option for selected tumors under 1.5 cm, lobectomy for 1.5–4 cm, and total or near-total thyroidectomy for tumors over 4 cm or multifocal disease. Radioactive iodine is not recommended for low-risk disease; TSH-suppressive levothyroxine is for intermediate or high risk. Thyroglobulin, thyroglobulin antibodies and neck ultrasound detect recurrence.
Follicular carcinoma: defined by the break-out
- Who: older patients and regions of iodine deficiency (Merck).
- The invasion rule: the diagnosis needs capsular and/or vascular invasion. FNA samples cells, not the capsule, so a follicular-patterned nodule is reported as "follicular neoplasm" (Bethesda IV); on excision it may be an adenoma, NIFTP, a follicular-pattern papillary cancer or a carcinoma. Next step: diagnostic lobectomy or molecular testing.
- WHO risk groups: minimally invasive (capsular invasion only), encapsulated angioinvasive (extensive if 4 or more foci) and widely invasive.
- Radioiodine: metastases respond to repeated doses better than papillary metastases do (Merck).
- Oncocytic carcinoma (formerly Hürthle cell carcinoma) is now its own entity: mitochondria-packed cells, blood-borne spread outside the neck and, when widely invasive, weaker iodine uptake with FDG avidity on PET.
Medullary carcinoma: C cells, calcitonin and RET
- Markers: serum calcitonin is the best test and is greatly elevated; CEA is often high. Serum calcium stays normal because high calcitonin down-regulates its own receptors (Merck).
- Picture: calcitonin-derived amyloid in the stroma, Congo red–positive. Ultrasound may show dense, homogeneous calcification.
- Genetics: about 75% sporadic (usually unilateral) and 25% hereditary, from germline RET mutations that keep this receptor tyrosine kinase signaling without its growth factor. Hereditary tumors begin as C-cell hyperplasia and are bilateral and multicentric. Every patient gets germline RET testing, and carrier relatives are offered prophylactic thyroidectomy.
- Extra peptides: ectopic ACTH, VIP, prostaglandins, serotonin or kallikreins can cause Cushing syndrome, diarrhea or flushing.
- Treatment: screen for pheochromocytoma with plasma metanephrines and remove it first, because it can provoke a hypertensive crisis during thyroidectomy. Then total thyroidectomy with bilateral central neck dissection. Advanced disease: vandetanib, cabozantinib or the selective RET inhibitor selpercatinib (NCI).
| Feature | MEN2A | MEN2B |
|---|---|---|
| Medullary carcinoma | Almost all patients | Almost always present by age 1, and aggressive |
| Pheochromocytoma | 40–50% | Common; about half have neuromas, pheochromocytoma and medullary carcinoma together |
| Hyperparathyroidism | 10–20% | Does not occur |
| Other clues | Cutaneous lichen amyloidosis; Hirschsprung disease in 2–5% | Mucosal neuromas, intestinal ganglioneuromas, marfanoid habitus |
| RET mutation | Several codons | About 95% at codon 918 (M918T) |
| Prophylactic thyroidectomy | Timing set by the specific mutation | Before age 1 |
The whole MEN family, including MEN1, is compared in the MEN1 vs MEN2A vs MEN2B guide, and the "alpha before beta" rule is in the pheochromocytoma mnemonic.
Anaplastic carcinoma: the neck that doubles in weeks
- Presentation: mostly older adults, slightly more women; rapid, painful enlargement of a hard, fixed mass with hoarseness, dysphagia or dyspnea.
- Picture: undifferentiated pleomorphic, giant and spindle cells that no longer make thyroglobulin. It can arise from a differentiated cancer or de novo, with frequent TP53 and TERT promoter mutations.
- Outcome: every anaplastic cancer is stage IV, and death usually comes from uncontrolled disease in the neck (NCI). It is about 1% of thyroid cancers but about 20% of thyroid cancer deaths (Merck).
- Treatment: radioactive iodine is useless and tracheostomy is often needed. Test for BRAF V600E: dabrafenib plus trametinib is FDA-approved for unresectable or metastatic BRAF V600E disease. Estimates of the mutation's frequency vary (about 25% per NCI, about 45% per Merck).
- Mimic: a rapidly enlarging thyroid in a patient with Hashimoto thyroiditis should also raise primary thyroid lymphoma.
2022 WHO terms you may meet
- Hürthle cell → oncocytic cell; oncocytic carcinoma is a separate tumor type.
- "Variant" → "subtype" (for example, tall cell subtype of papillary carcinoma); "variant" now means a genetic change.
- NIFTP (noninvasive follicular thyroid neoplasm with papillary-like nuclear features), once called noninvasive encapsulated follicular variant of papillary carcinoma, is a low-risk neoplasm, not a carcinoma.
- High-grade follicular cell–derived carcinoma groups poorly differentiated carcinoma with the new differentiated high-grade carcinoma (5 or more mitoses per 2 mm² and/or necrosis).
- Squamous cell carcinoma of the thyroid is now a pattern of anaplastic carcinoma, and medullary carcinoma is graded (high grade: 5 or more mitoses per 2 mm², necrosis or Ki-67 of 5% or more).
- Molecular rule: most BRAF V600E-like tumors grow as papillae or infiltrate, while most encapsulated, follicular-patterned tumors are RAS-like.
Exam traps
- "Follicular neoplasm" on FNA is not a cancer diagnosis; only excision shows invasion.
- Radioactive iodine and thyroglobulin belong to follicular-cell cancers; medullary carcinoma is followed with calcitonin and CEA.
- High calcitonin, normal calcium: hypocalcemia is not a medullary clue.
- Age drives staging: under 55, stage II is the highest possible stage for papillary or follicular cancer, even with distant metastases (NCI).
- Amyloid stroma in a thyroid tumor points to medullary carcinoma (the amyloid is calcitonin-derived); Congo red and apple-green birefringence are reviewed in the amyloidosis flowchart.
Practice question
Vignette. A 31-year-old man has a firm 2-cm left thyroid nodule. His father died of "thyroid cancer" after surgery for an adrenal tumor. Fine-needle aspiration shows nests of polygonal and spindle cells beside extracellular material that is apple-green under polarized light after Congo red staining. His blood pressure is 162/98 mm Hg, and he reports episodes of pounding headache with sweating. Serum calcium is normal. What is the most appropriate next step?
Answer: Measure plasma free metanephrines. This is medullary carcinoma, and the family history plus paroxysmal hypertension point to MEN2A. A pheochromocytoma must be found and removed (after alpha-blockade) before thyroidectomy to avoid an intraoperative hypertensive crisis. Germline RET testing follows for him and his relatives.
Why not the others?
- Radioactive iodine ablation: medullary carcinoma cells do not take up iodine.
- Serum thyroglobulin: a marker for follicular-cell cancers after thyroidectomy; medullary carcinoma is followed with calcitonin and CEA.
- Start propranolol: beta-blockade before alpha-blockade can paradoxically raise blood pressure in pheochromocytoma.
- Left lobectomy now: the adrenal comes first, and medullary carcinoma needs total thyroidectomy with central neck dissection; hereditary tumors are bilateral.
Key takeaways
- Two cells: follicular cell → papillary, follicular, high-grade and anaplastic; C cell → medullary.
- Papillary: most common; Orphan Annie nuclei, grooves, psammoma bodies; lymph nodes; BRAF V600E; radiation.
- Follicular: capsular or vascular invasion (not diagnosable on FNA); blood to lung and bone; RAS, PAX8::PPARG.
- Medullary: calcitonin, CEA, calcitonin-derived amyloid; RET and MEN2; rule out pheochromocytoma first; no radioactive iodine.
- Anaplastic: older patient, rapidly enlarging compressive mass, always stage IV; test for BRAF V600E.
- Radioactive iodine and thyroglobulin work only while the tumor still acts like a follicular cell.
Sources
- Thyroid Cancers — Merck Manual Professional Edition (2026)
- Approach to the Patient With a Thyroid Nodule — Merck Manual Professional Edition (2026)
- Thyroid Cancer Treatment (PDQ), Health Professional Version — National Cancer Institute (2025)
- Jung CK et al. Update from the 2022 World Health Organization Classification of Thyroid Tumors — Endocrinology and Metabolism (2022)
- Multiple Endocrine Neoplasia, Type 2A (MEN 2A) — Merck Manual Professional Edition (2025)
- Multiple Endocrine Neoplasia, Type 2B (MEN 2B) — Merck Manual Professional Edition (2025)
- Papillary Thyroid Carcinoma, Classic — PathologyOutlines (2021)
- Medullary Carcinoma of the Thyroid — PathologyOutlines
- Anaplastic Thyroid Carcinoma — PathologyOutlines
- What Is Thyroid Cancer? — American Cancer Society (2024)
- Tests for Thyroid Cancer — American Cancer Society (2024)
- Bethesda System Diagnostic Categories — PathologyOutlines (2025)
- Pheochromocytoma — Merck Manual Professional Edition (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
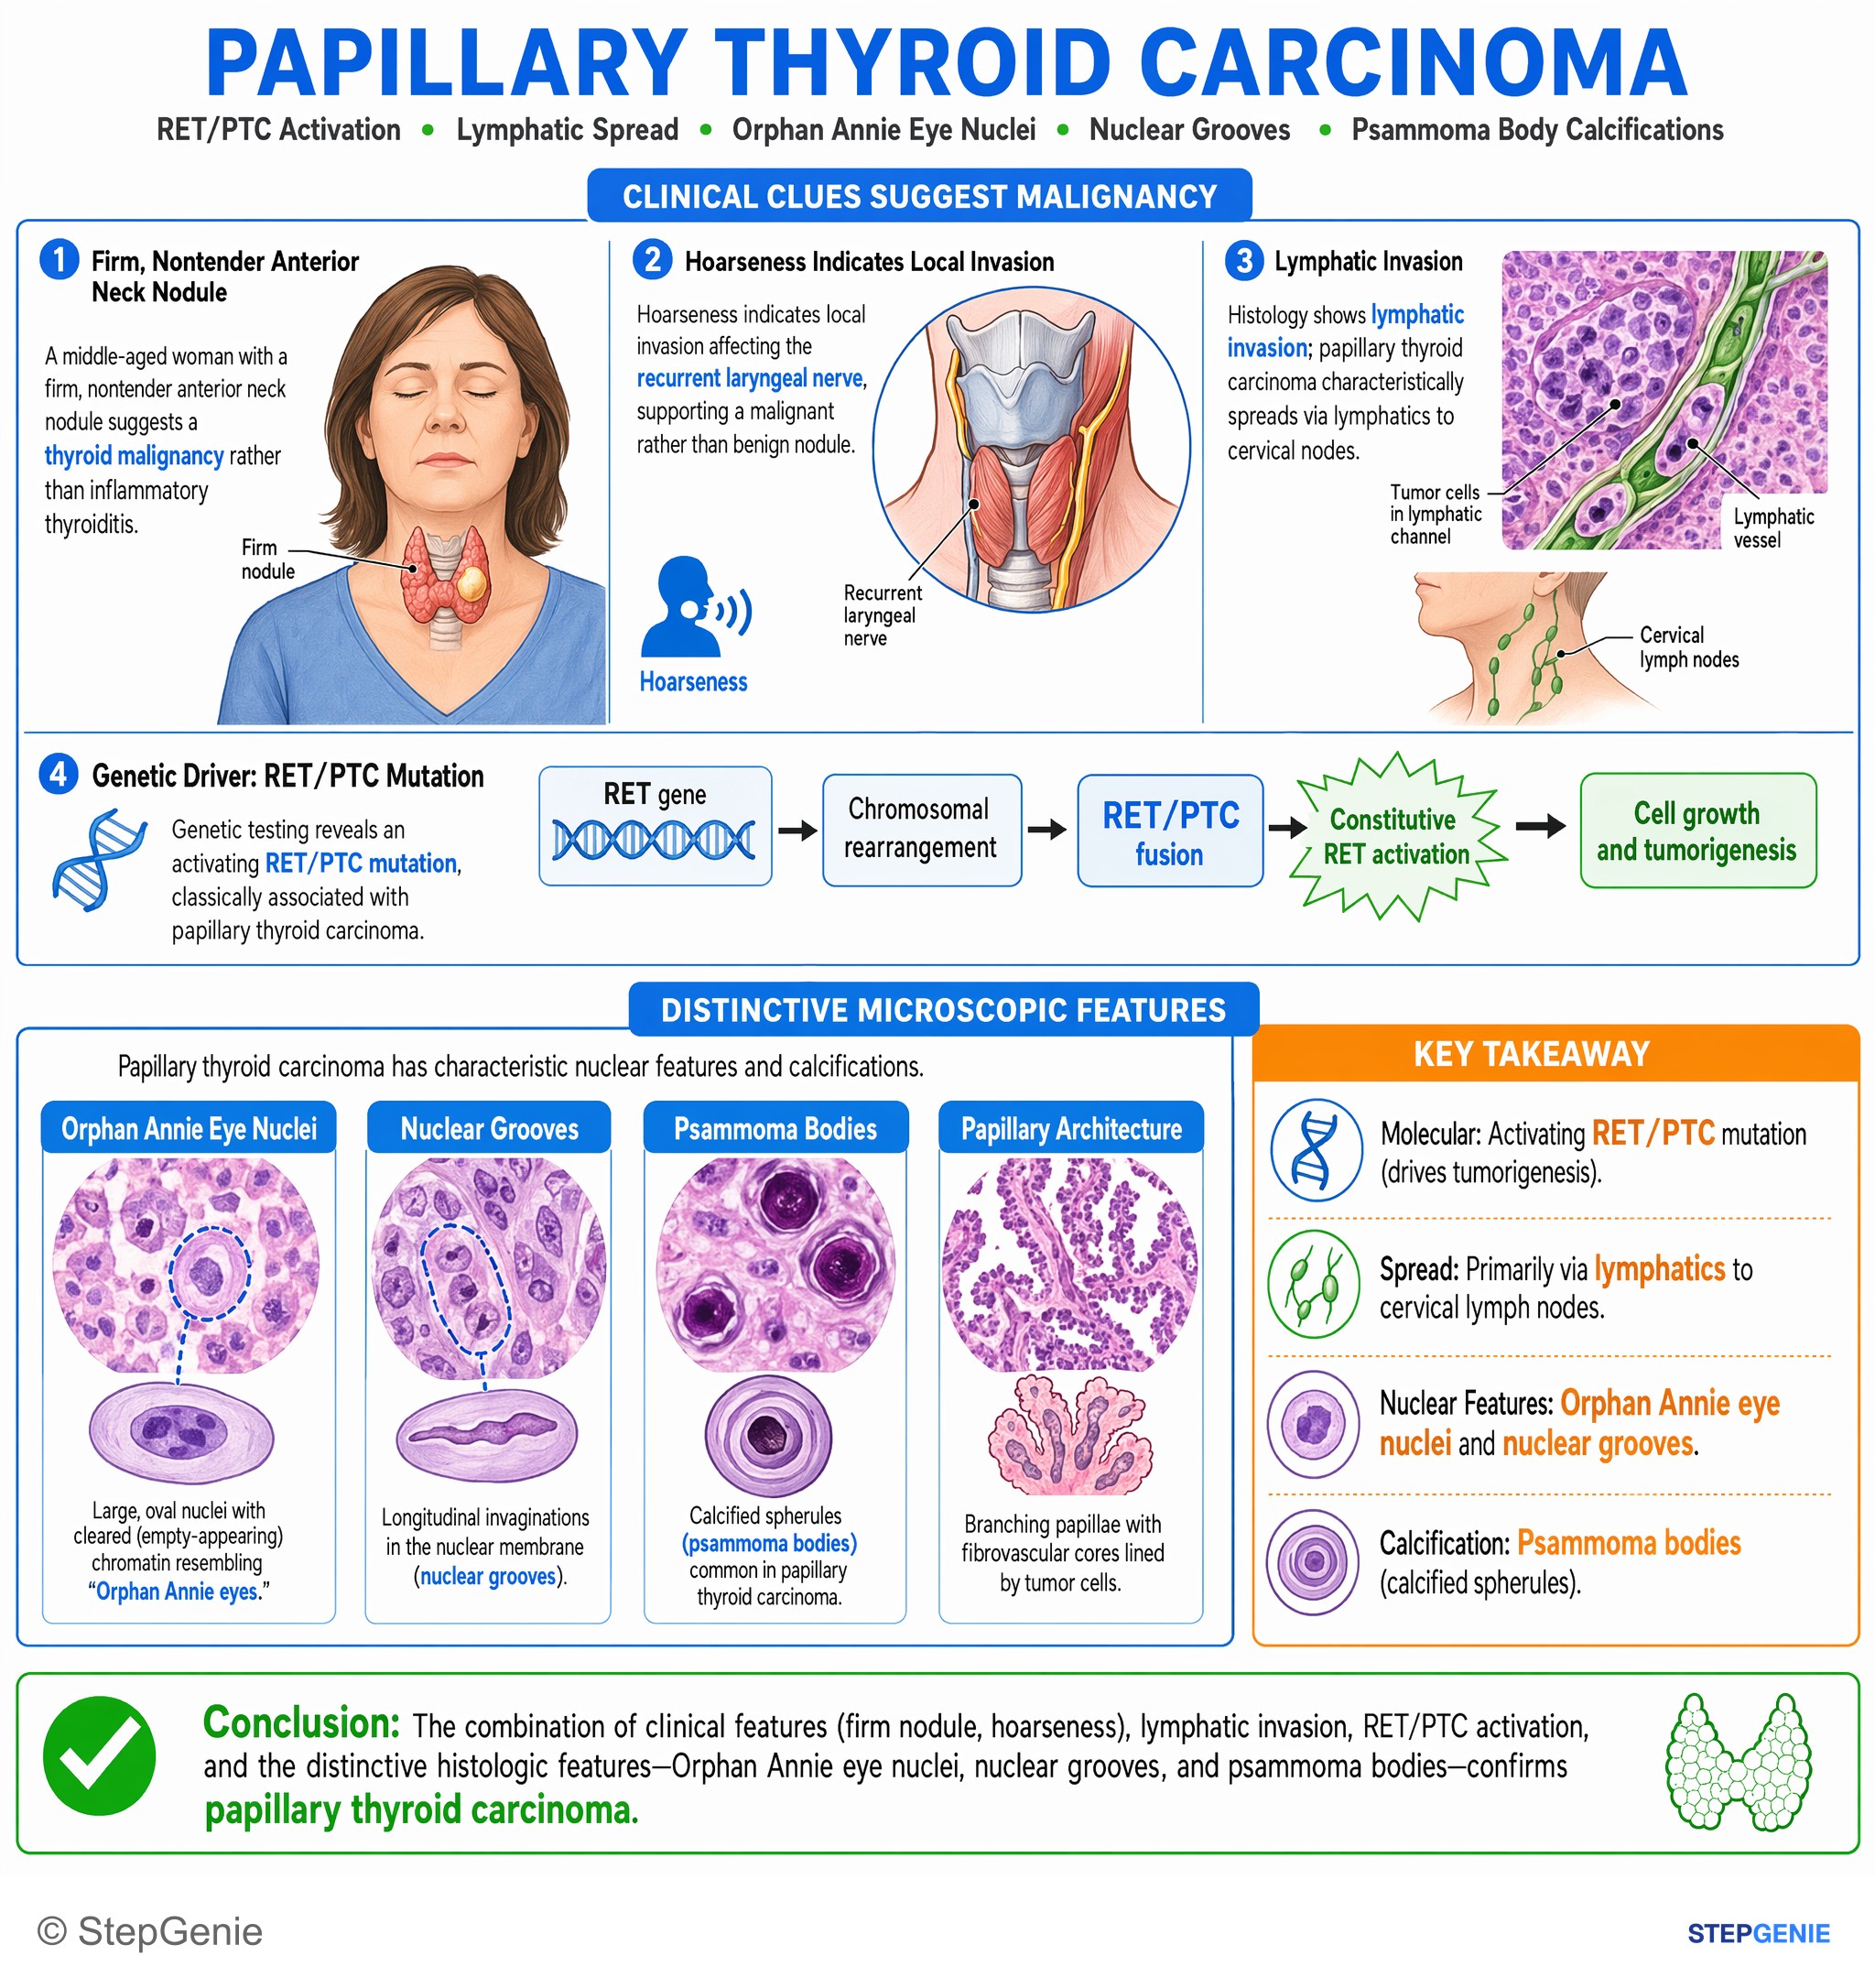
Papillary thyroid carcinoma: RET/PTC activation, lymphatic spread, orphan Annie eye nuclei, nuclear grooves, and psammoma body…
USMLE Step 1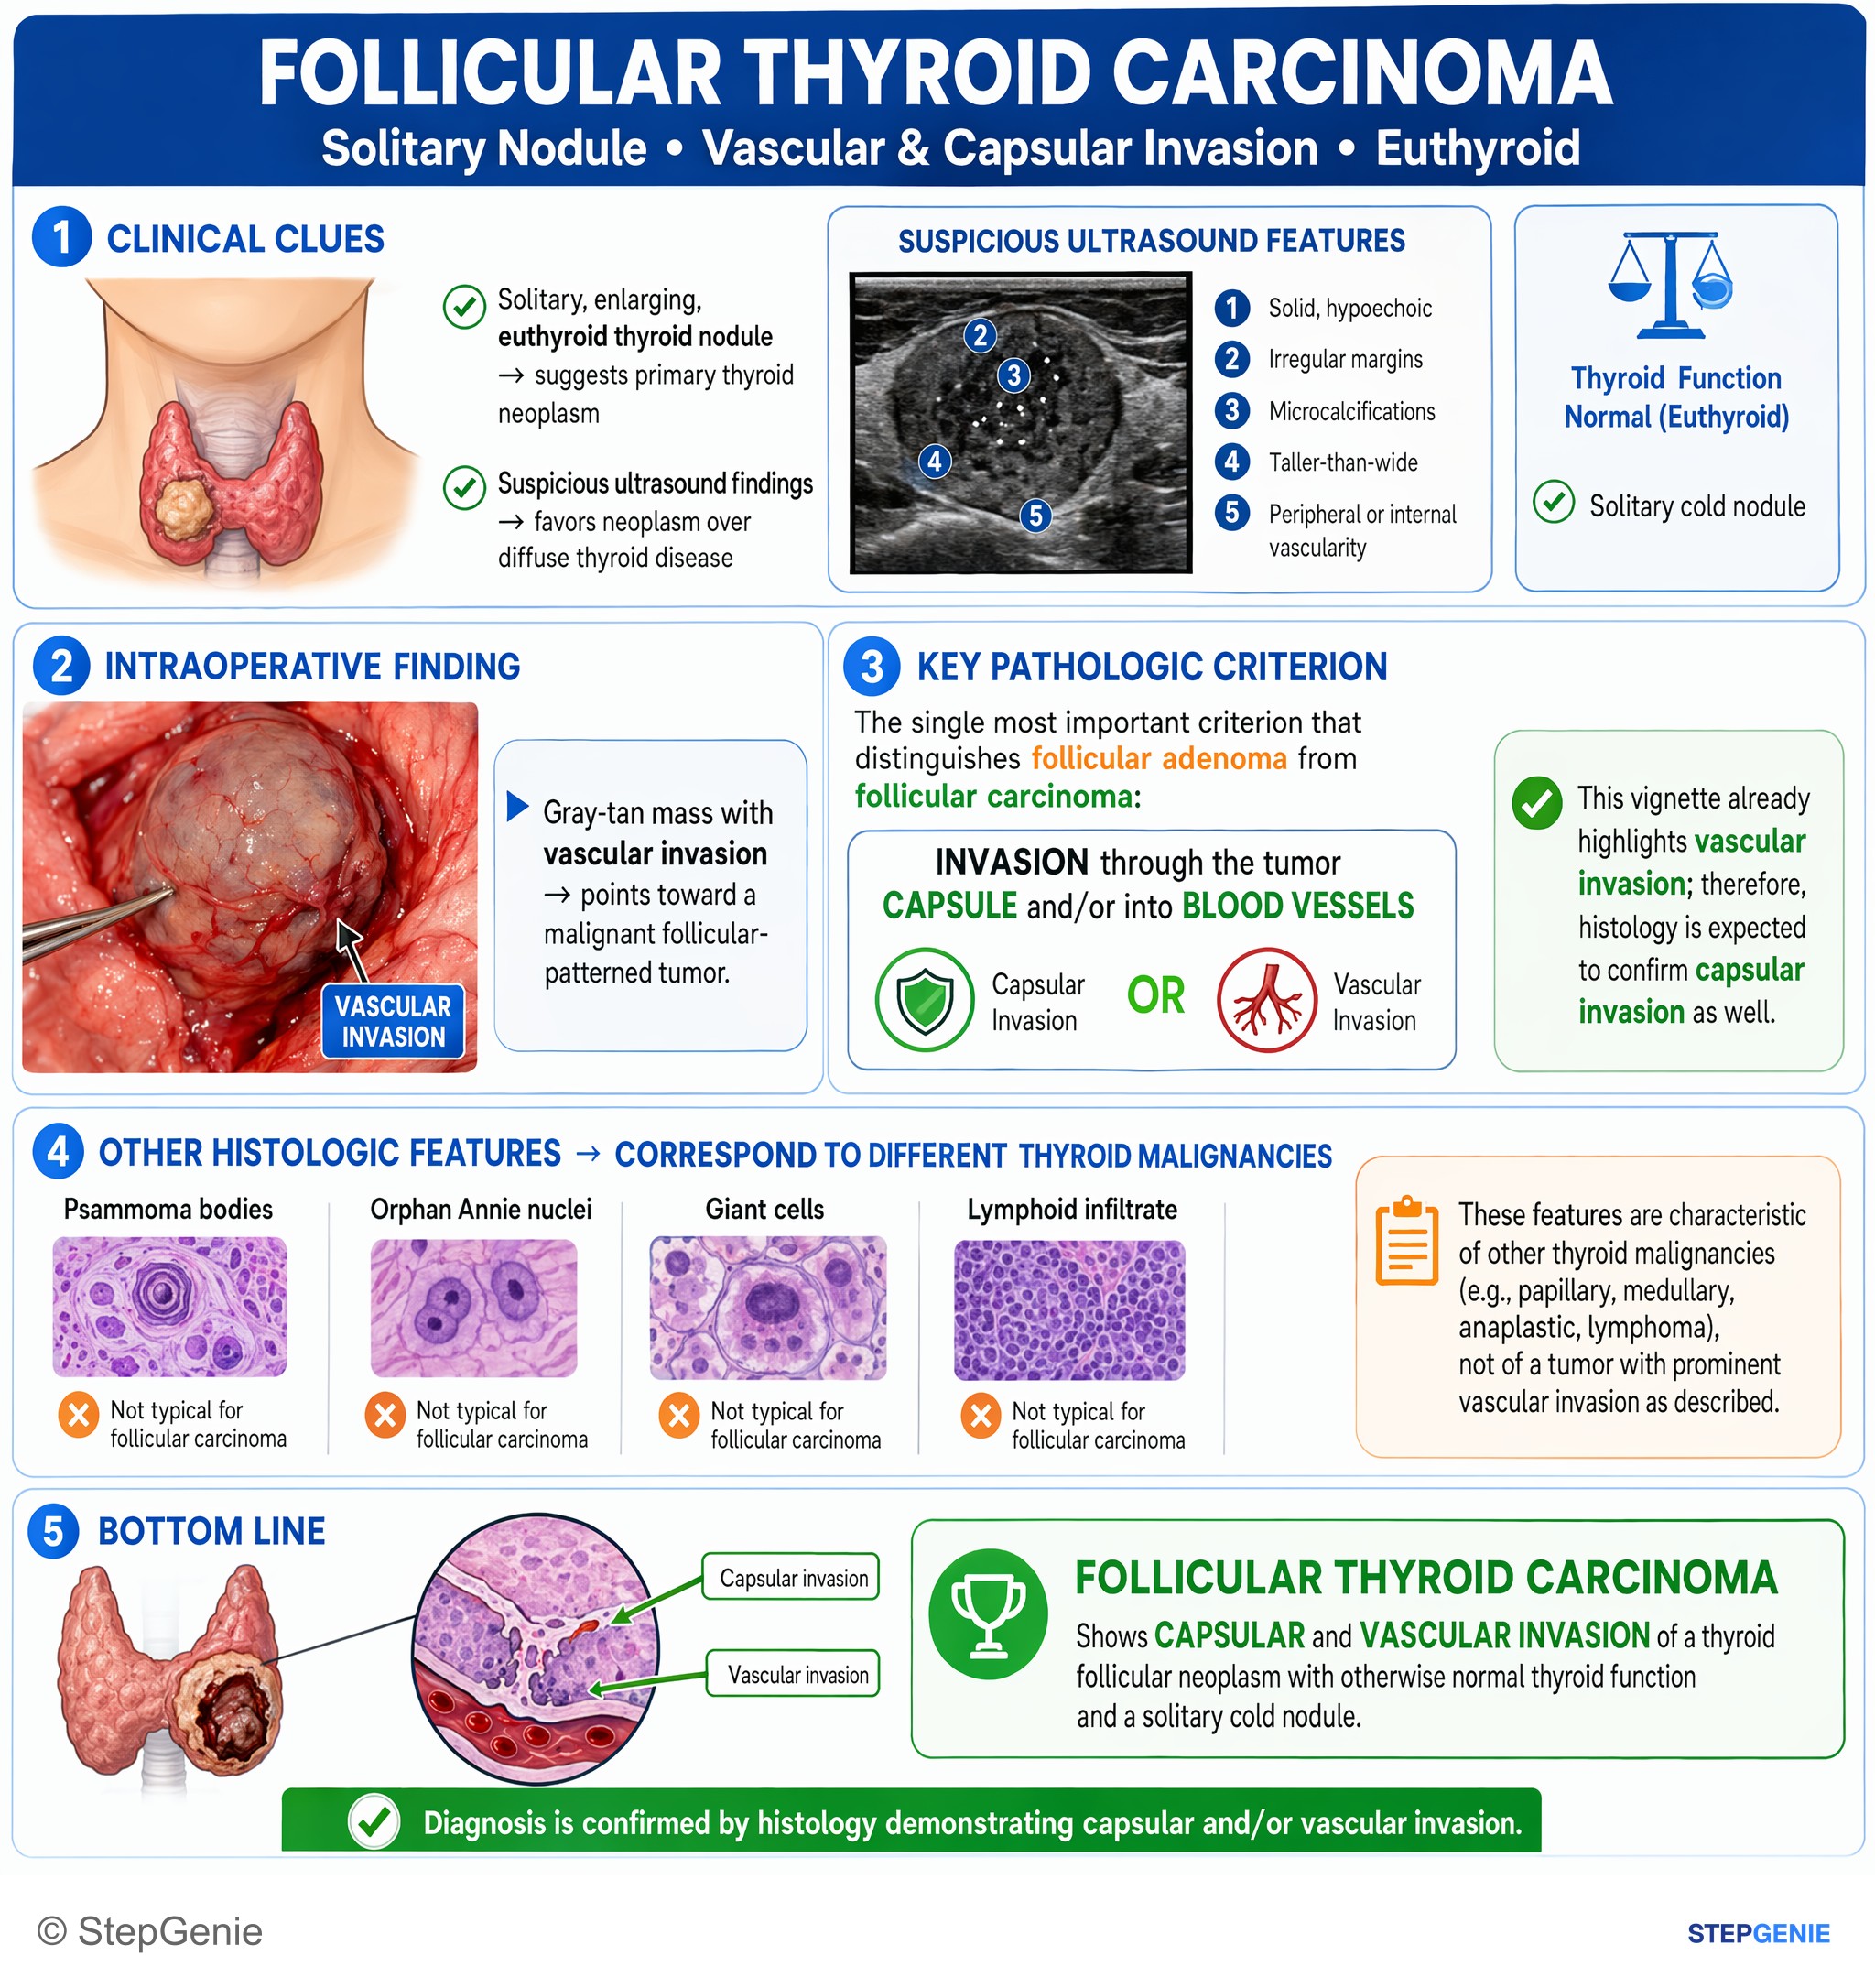
Follicular thyroid carcinoma shows capsular and vascular invasion of a thyroid follicular neoplasm with otherwise normal thyroid function…
USMLE Step 1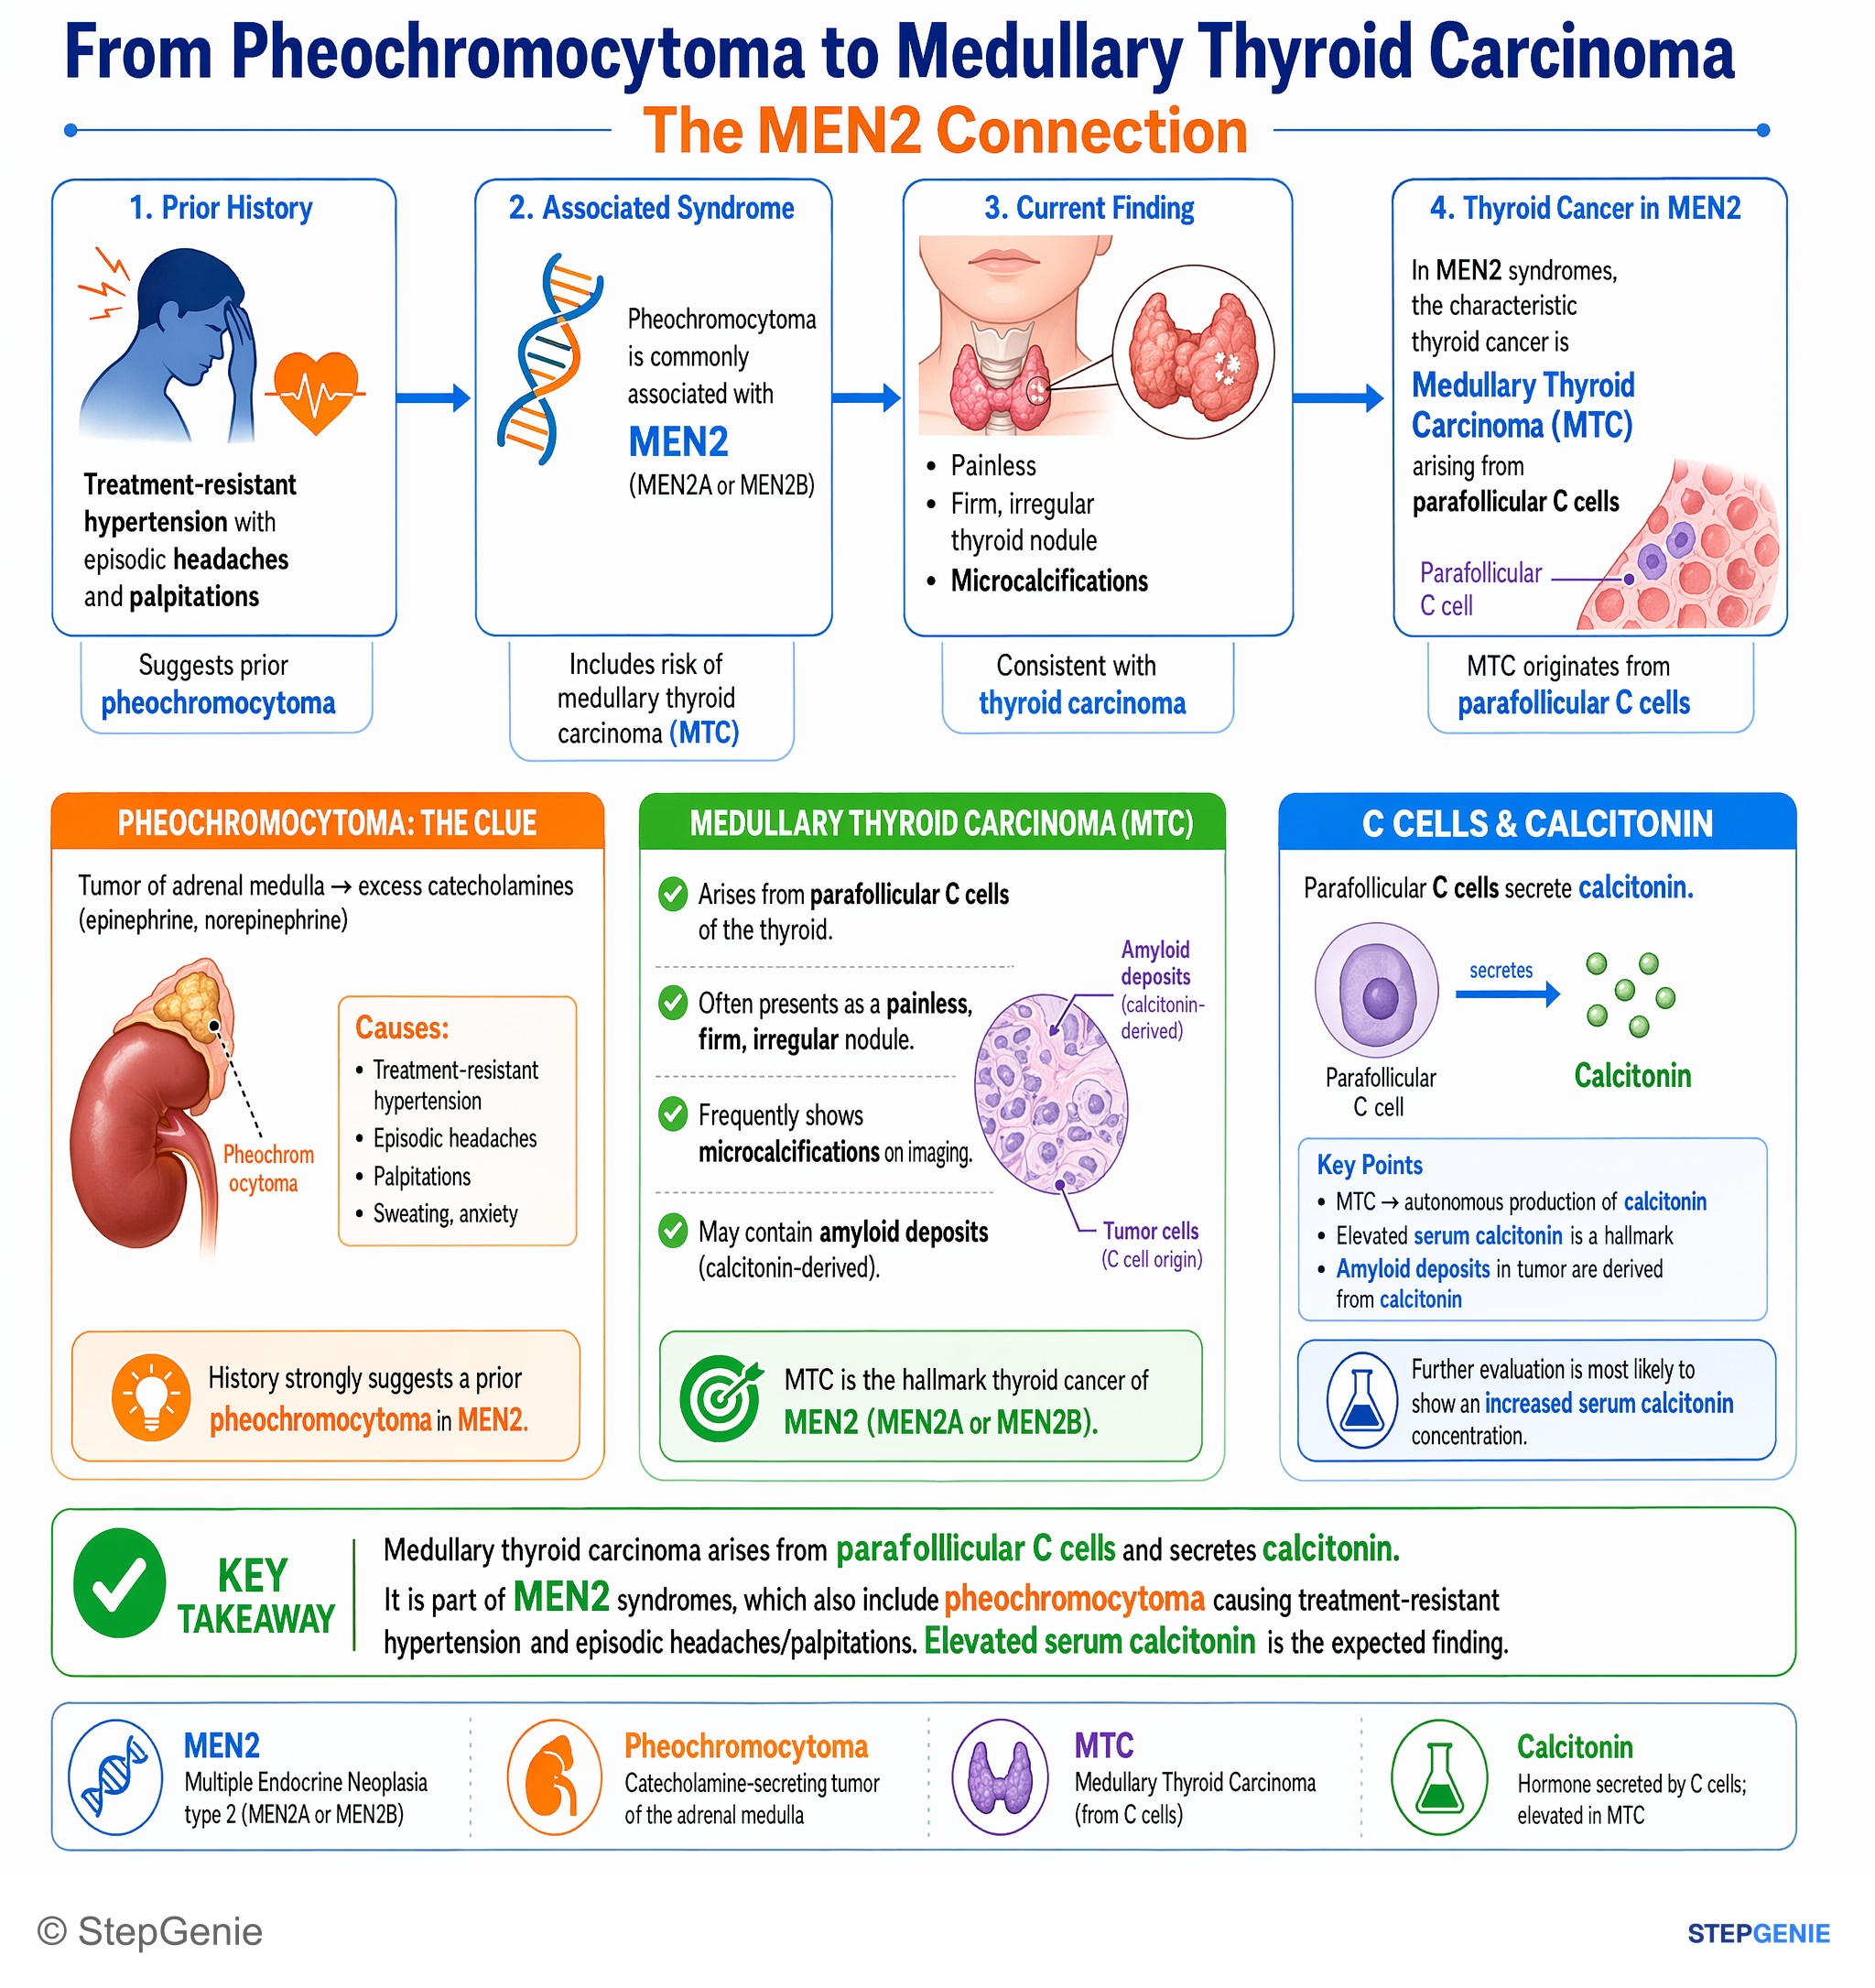
Medullary thyroid carcinoma from parafollicular C cells secretes calcitonin, often part of MEN2 with prior pheochromocytoma causing…
USMLE Step 1Frequently Asked Questions
What are the 4 main types of thyroid cancer?
The four classic types are papillary, follicular, medullary and anaplastic carcinoma. Papillary and follicular are differentiated cancers of the follicular cell, anaplastic is an undifferentiated follicular-cell cancer, and medullary comes from the calcitonin-making C cells. Papillary is by far the most common (80 to 90% of cases per Merck, about 8 in 10 per the American Cancer Society), medullary is about 3 to 4% (NCI), and anaplastic is only about 1 to 2% (Merck and the American Cancer Society) but causes a disproportionate share of deaths.
How do you tell papillary from follicular thyroid carcinoma?
Papillary carcinoma is diagnosed by its nuclei: enlarged, pale Orphan Annie eye nuclei with grooves and pseudoinclusions, often with psammoma bodies; it spreads through lymphatics to neck nodes and most often carries a BRAF V600E mutation. Follicular carcinoma lacks those nuclear features and is defined by invasion of its capsule or blood vessels; it spreads through the blood to lung and bone and most often carries a RAS mutation. Because invasion can only be seen in the removed nodule, fine-needle aspiration cannot tell a follicular adenoma from a follicular carcinoma.
Which type of thyroid cancer is the most aggressive?
Anaplastic thyroid carcinoma is the most aggressive. It usually affects older adults as a hard neck mass that enlarges over weeks and compresses the trachea, esophagus or recurrent laryngeal nerve, and every case is staged as stage IV. Median survival has historically been only about 5 to 6 months, although BRAF V600E-positive tumors can now be treated with dabrafenib plus trametinib.
Why is calcitonin high in medullary thyroid cancer, and is calcium low?
Medullary thyroid cancer arises from parafollicular C cells, whose normal product is calcitonin, so serum calcitonin is greatly elevated and is the best diagnostic and follow-up marker, along with CEA. Despite the high calcitonin, serum calcium is usually normal because the excess hormone down-regulates its receptors. The tumor stroma also contains calcitonin-derived amyloid that stains with Congo red.
Why must pheochromocytoma be ruled out before surgery for medullary thyroid cancer?
About a quarter of medullary thyroid cancers are hereditary, caused by germline RET mutations in MEN2A, MEN2B or familial medullary thyroid cancer, and MEN2 includes pheochromocytoma. An undiagnosed pheochromocytoma can trigger a hypertensive crisis during thyroid surgery. Plasma metanephrines are measured first, and any pheochromocytoma is removed after alpha-blockade before the thyroidectomy.
Does radioactive iodine work for all thyroid cancers?
No. Radioactive iodine works only for cancers that still take up iodine like follicular cells do, meaning papillary and follicular carcinoma, and it is not recommended for low-risk papillary cancer. Medullary carcinoma cells come from C cells and do not take up iodine, and anaplastic carcinoma has lost this ability, so radioactive iodine does not help either of them.