Thyroid nodule questions are classic USMLE “one-lab-away” traps: the stem feels like it’s testing cancer risk, but the first move is almost always about physiology—TSH determines the next diagnostic step. The best way to stop missing these is to treat every answer choice like it’s a mini-lesson: why it’s tempting, when it’s right, and why it’s wrong here.
Tag: Endocrine > Thyroid Disorders
The Clinical Vignette (Q-bank style)
A 43-year-old woman presents for evaluation of a thyroid “lump” found on a routine exam. She denies neck pain, dysphagia, or hoarseness. No family history of thyroid cancer. She has mild heat intolerance and palpitations. Exam shows a 2.5-cm right thyroid nodule; no cervical lymphadenopathy. Labs:
- TSH: 0.08 µIU/mL (low)
- Free T4: mildly elevated
What is the next best step in management?
Answer choices:
A. Fine-needle aspiration (FNA) biopsy
B. Thyroid ultrasound with Doppler
C. Radionuclide thyroid uptake scan
D. CT scan of the neck with contrast
E. Start levothyroxine suppression therapy
Step 1: Anchor on the Algorithm (the testable core)
The high-yield thyroid nodule workflow
- Check TSH
- Low TSH → nodule may be hyperfunctioning → radionuclide uptake scan
- Normal/high TSH → proceed to ultrasound ± FNA based on features/size
- If “hot” nodule (hyperfunctioning) → malignancy risk is very low → FNA usually not needed
- If “cold” nodule → evaluate malignancy risk using ultrasound patterns and size thresholds for FNA
This stem gives you a nodule + hyperthyroid symptoms + low TSH. That combination is an algorithmic slam dunk.
✅ Correct Answer: C. Radionuclide thyroid uptake scan
With a suppressed TSH, the key question is: Is this nodule autonomously producing thyroid hormone? A radionuclide scan (I-123 or technetium-99m) classifies nodules as:
- Hot (increased uptake): autonomous/hyperfunctioning
- Low malignancy risk
- Treat hyperthyroidism (radioiodine ablation, surgery, or meds depending on scenario)
- Cold (decreased uptake): nonfunctioning
- Higher malignancy risk relative to hot nodules
- Next step becomes ultrasound risk stratification and likely FNA
Why USMLE loves this
Because people jump straight to biopsy. But TSH first prevents unnecessary FNA and tests whether the nodule is the cause of hyperthyroidism.
High-yield pearl:
- Toxic (autonomous) adenoma = hot nodule + low TSH
- Path: follicular cells producing hormone independently
- Often causes hyperthyroid symptoms without Graves findings (no ophthalmopathy, no pretibial myxedema)
Distractor Breakdown (Why each answer choice matters)
A. Fine-needle aspiration (FNA) biopsy
Why it’s tempting: FNA is the go-to test for evaluating malignancy in thyroid nodules.
Why it’s wrong here: You don’t FNA first when TSH is low. Hyperfunctioning nodules are rarely malignant; you must identify “hot vs cold” with a radionuclide scan first.
When it would be correct:
- Normal/high TSH + ultrasound features meeting criteria for biopsy
- Cold nodule on scan with concerning US pattern (or large size)
High-yield FNA limitation: FNA cannot distinguish follicular adenoma vs follicular carcinoma (needs capsular/vascular invasion on histology after surgical excision).
B. Thyroid ultrasound with Doppler
Why it’s tempting: Ultrasound is central to nodule workup and helps choose which nodules get FNA.
Why it’s not the next step: With suppressed TSH, you need a radionuclide uptake scan first. Ultrasound is still useful—often obtained after the scan for anatomy and risk stratification—but it’s not the first move in a low TSH patient.
When it would be correct:
- TSH normal or high (most nodule cases)
- Screening cervical lymph nodes
- Risk stratification using suspicious sonographic features:
- hypoechoic
- irregular margins
- microcalcifications
- taller-than-wide shape
- extrathyroidal extension
D. CT scan of the neck with contrast
Why it’s tempting: “Look at the mass” logic, or concern about invasion.
Why it’s wrong here: CT is not first-line for thyroid nodules and doesn’t replace ultrasound/FNA algorithms. Also, iodinated contrast can:
- Interfere with subsequent radioiodine uptake/ablation
- Worsen hyperthyroidism in susceptible patients (Jod-Basedow phenomenon)—more relevant in toxic multinodular goiter or autonomous nodules
When it would be correct:
- Suspected large substernal goiter with compressive symptoms (airway/esophagus)
- Evaluating invasive disease when ultrasound is limited
E. Start levothyroxine suppression therapy
Why it’s tempting: Old-school idea: suppress TSH to shrink nodules.
Why it’s wrong (and risky):
- Not recommended as routine nodule therapy
- Can cause iatrogenic hyperthyroidism → atrial fibrillation, bone loss
- In this case, the patient is already hyperthyroid (low TSH, high T4)
When it might come up:
- Rarely in select benign nodules in iodine-deficient areas (not typical USMLE “best next step” today)
Quick Table: “Next step” patterns you should memorize
| Scenario | TSH | Best next step | Why |
|---|---|---|---|
| Thyroid nodule + hyperthyroid symptoms | Low | Radionuclide uptake scan | Determine hot vs cold |
| Thyroid nodule, euthyroid patient | Normal | Ultrasound ± FNA | US risk stratification |
| Thyroid nodule + hypothyroid labs | High | Ultrasound ± FNA | Higher suspicion; scan not first |
| Hot nodule on scan | Low | Treat hyperthyroidism; usually no FNA | Malignancy rare |
| Cold nodule + suspicious US | Any | FNA | Rule out malignancy |
Extra High-Yield Connections USMLE Loves
1) “Hot vs cold” is not just trivia
- Hot (hyperfunctioning): toxic adenoma, toxic multinodular goiter
- Cold (nonfunctioning): cyst, thyroiditis, benign adenoma, malignancy (papillary/follicular/medullary/anaplastic)
2) Thyroid cancer clues embedded in vignettes
- Papillary carcinoma (most common): “Orphan Annie eye” nuclei, psammoma bodies, lymphatic spread, prior radiation exposure
- Follicular carcinoma: hematogenous spread (bone, lungs); FNA cannot confirm carcinoma vs adenoma
- Medullary carcinoma: parafollicular C cells → calcitonin; associated with MEN 2 (RET mutation)
- Anaplastic carcinoma: older patient, rapidly enlarging neck mass, compressive symptoms
3) The single scariest symptom in nodule stems
- Hoarseness → possible recurrent laryngeal nerve involvement → raises concern for malignancy/invasive disease
Takeaway: The “one-line rule” to carry into test day
Thyroid nodule + low TSH = uptake scan first.
Don’t biopsy what might be an autonomous “hot” nodule until physiology tells you what you’re dealing with.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
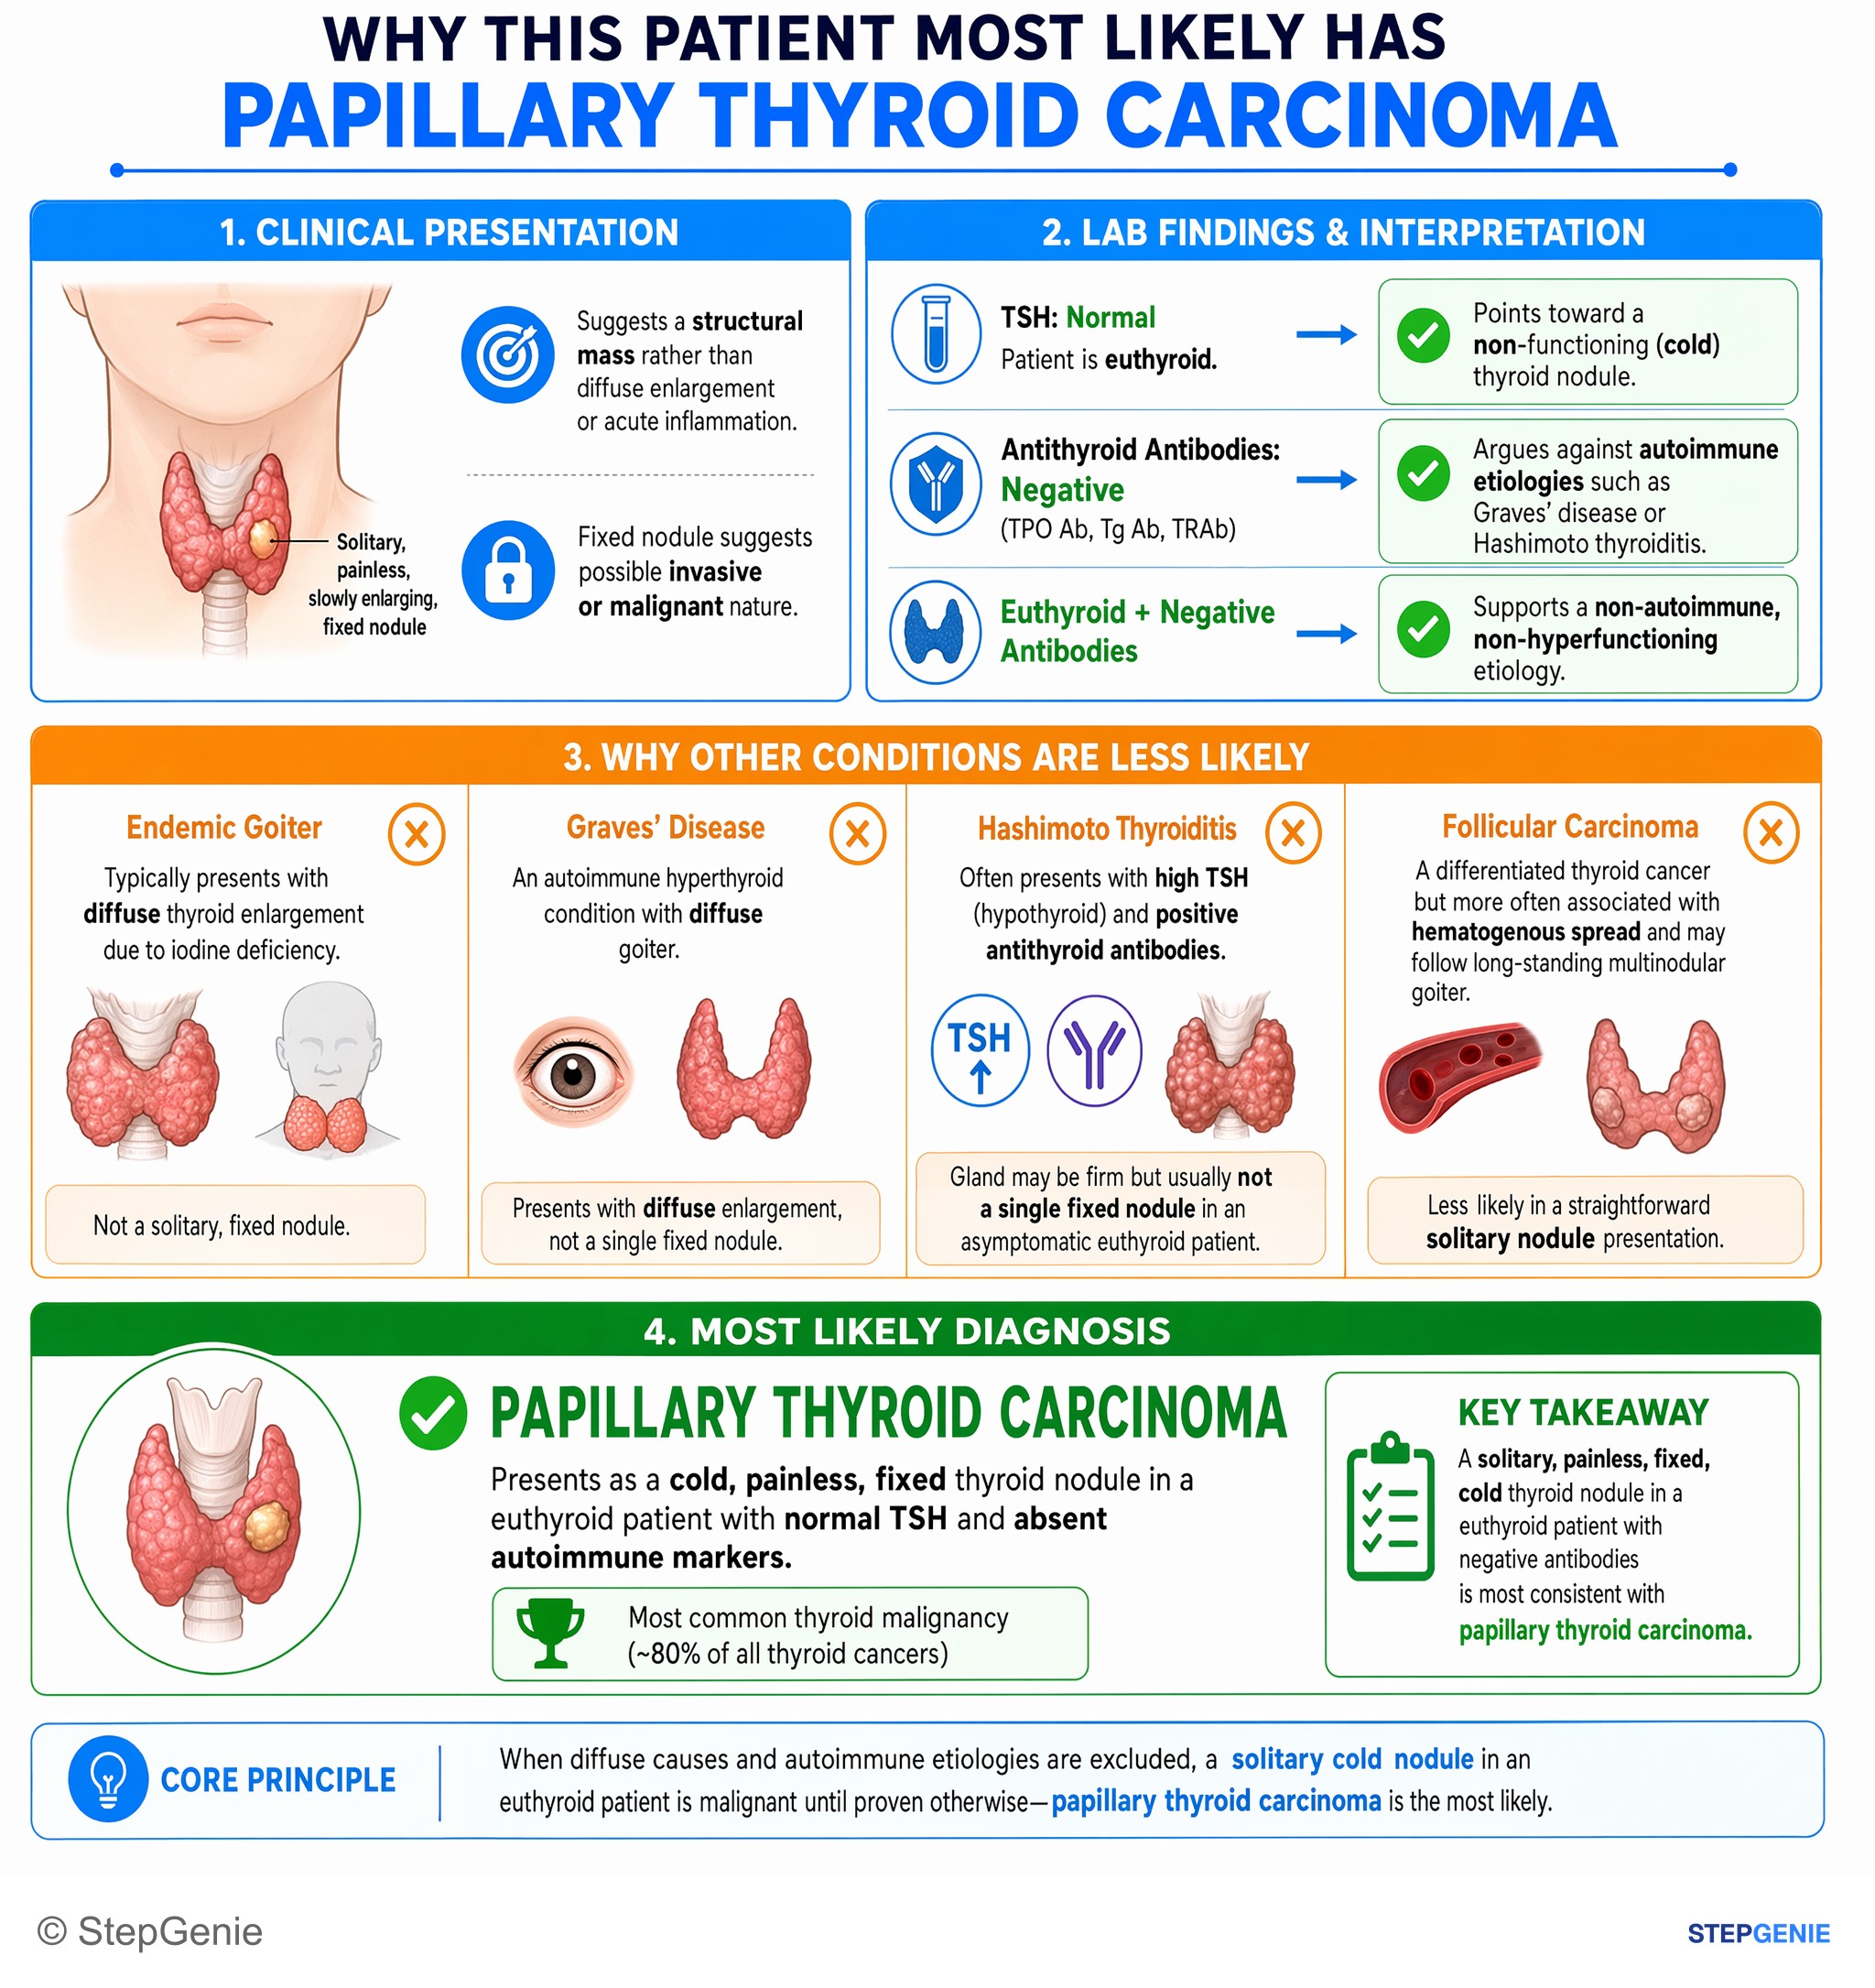
Papillary thyroid carcinoma presents as a cold, painless, fixed thyroid nodule with normal TSH and absent autoimmune markers; most common…
USMLE Step 1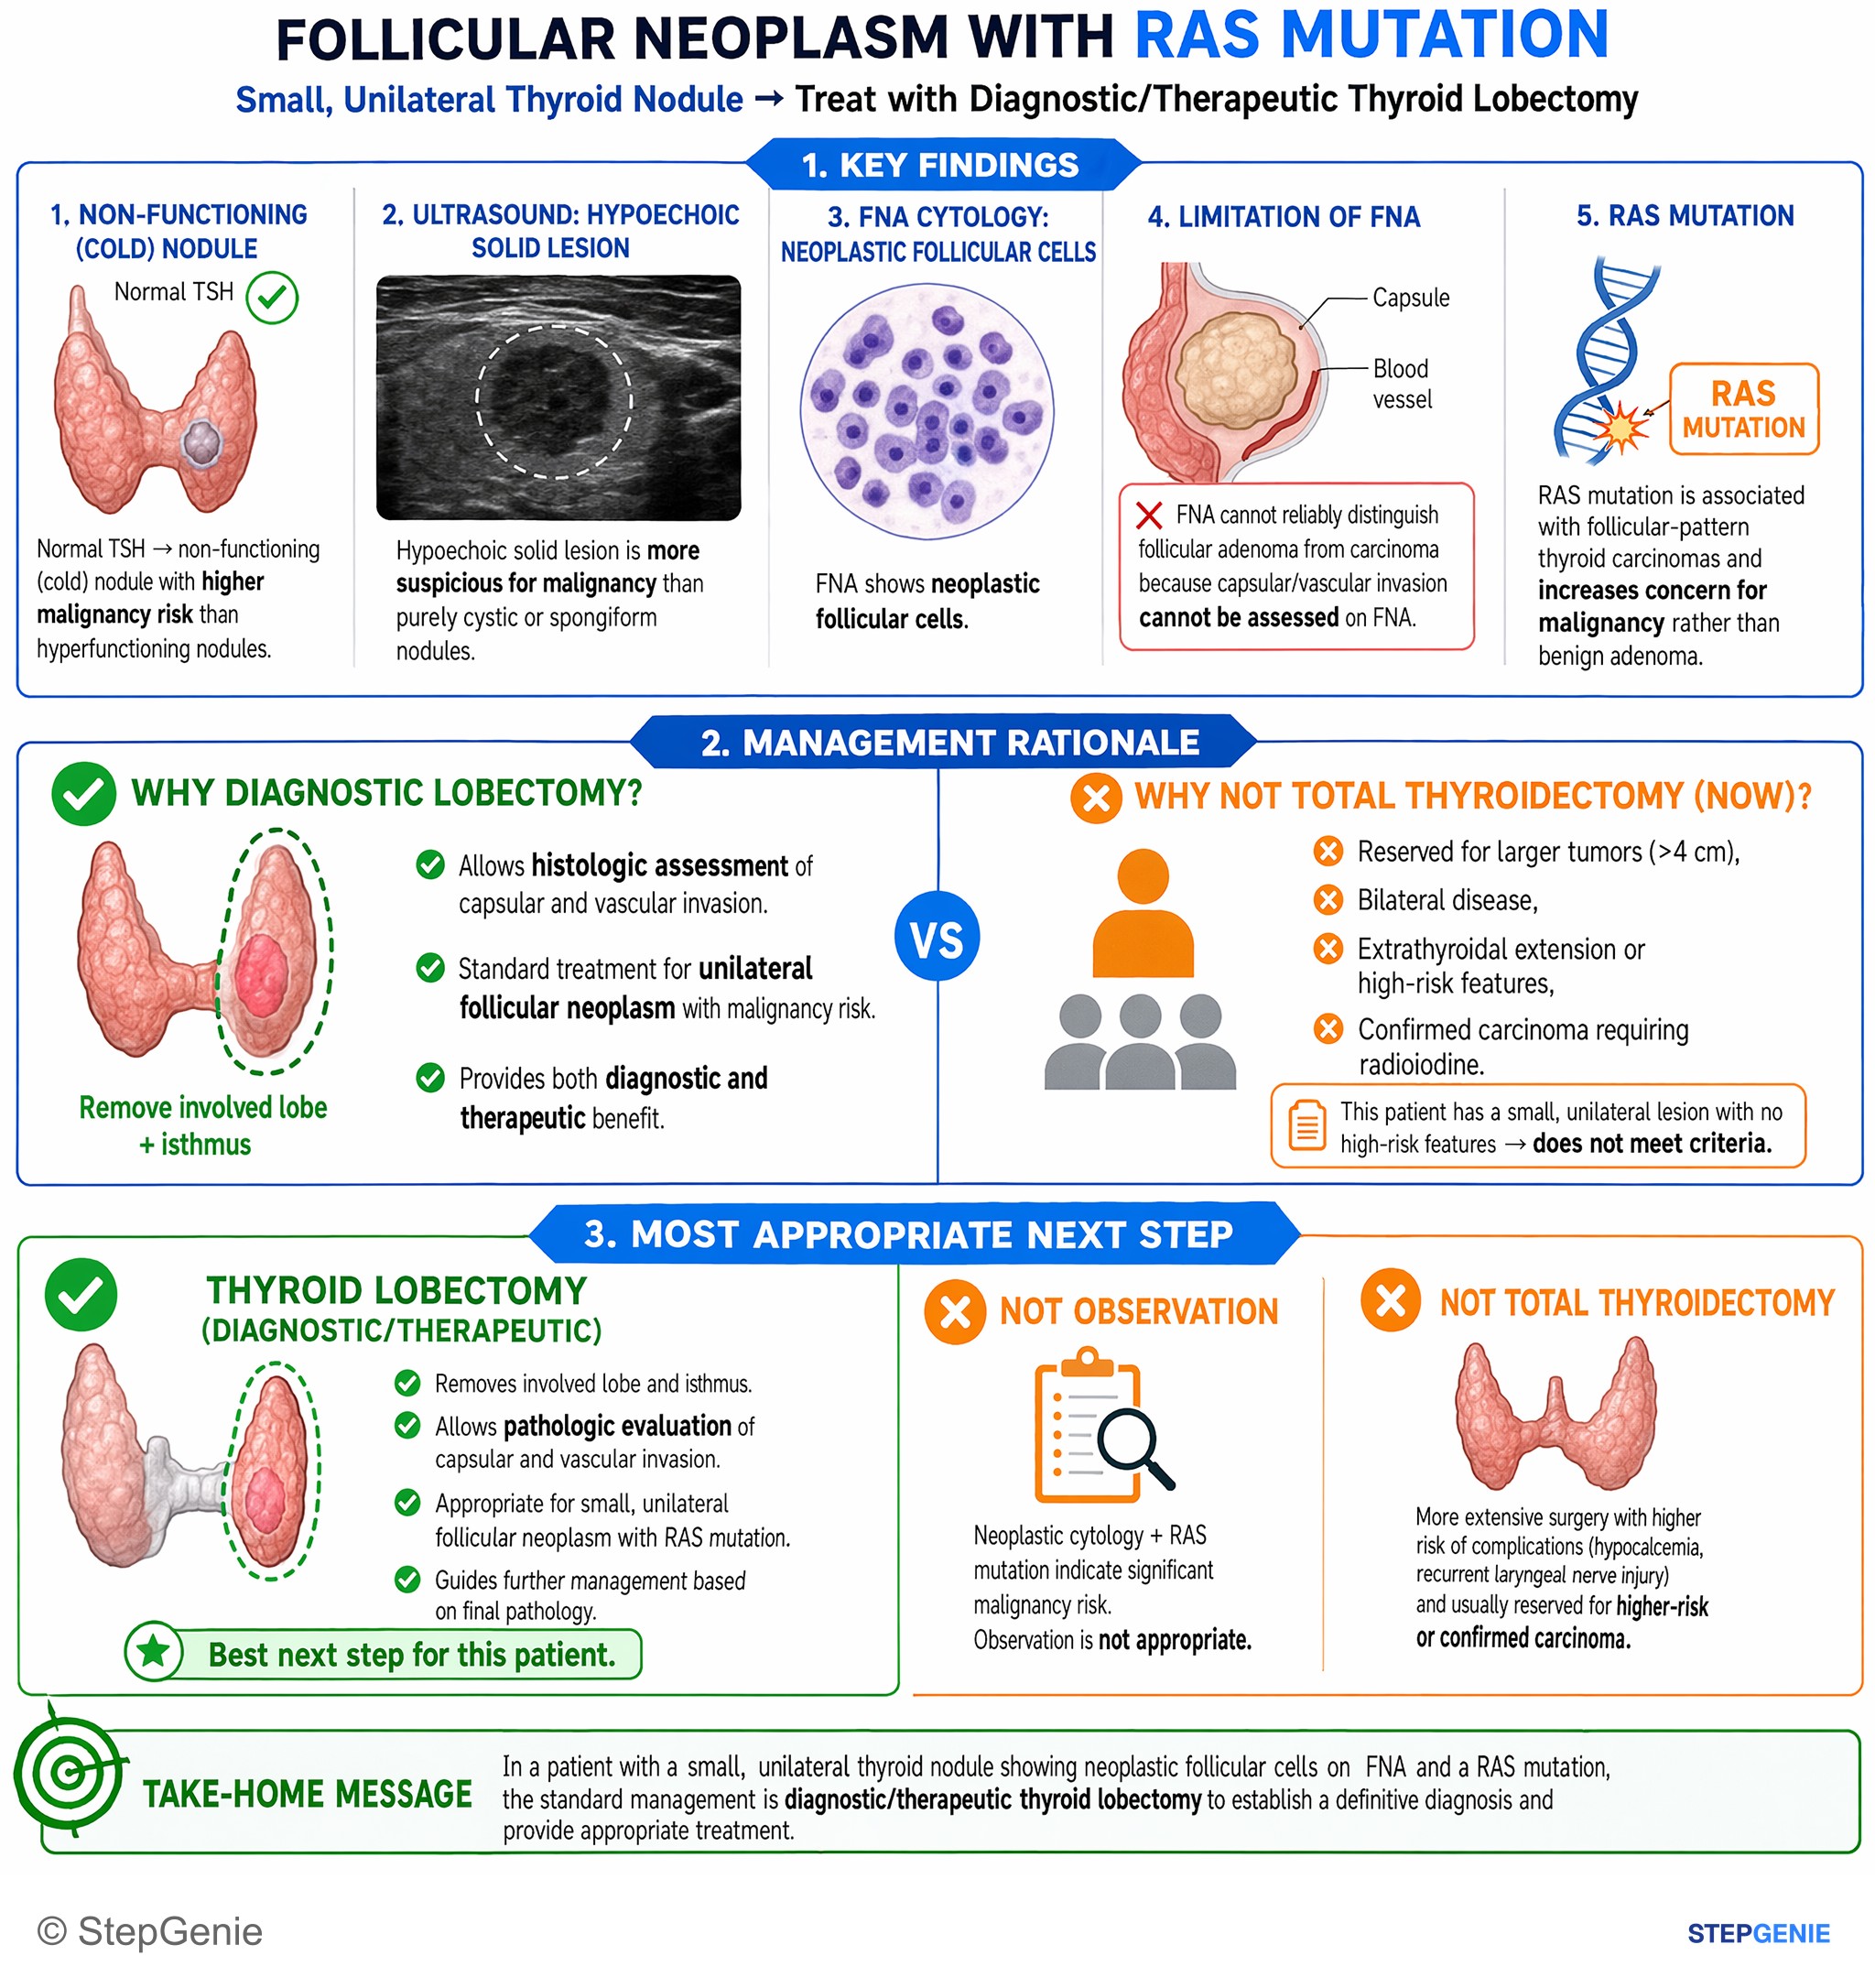
Follicular neoplasm with RAS mutation in a small, unilateral thyroid nodule → treat with diagnostic/therapeutic thyroid lobectomy, not…
USMLE Step 2Frequently Asked Questions
What is the next best step for a thyroid nodule when TSH is low?
The next best step is a radionuclide thyroid uptake scan. A suppressed TSH suggests the nodule may be autonomously producing thyroid hormone, so the key question is whether it is hot or cold. The scan classifies the nodule as hyperfunctioning or nonfunctioning and guides what comes next, including whether malignancy risk is low or whether ultrasound risk stratification and likely FNA are needed.
Why don’t you do FNA first in a patient with a thyroid nodule and low TSH?
You do not start with FNA because low TSH changes the algorithm. In a patient with a suppressed TSH, the priority is to determine whether the nodule is hyperfunctioning with a radionuclide uptake scan. Hot nodules have very low malignancy risk, so FNA is usually not needed. Biopsy becomes more appropriate after scan and ultrasound findings suggest a nonfunctioning or suspicious nodule.
How do you tell a toxic adenoma from Graves disease in a thyroid nodule question?
A toxic adenoma is suggested by a hot thyroid nodule with low TSH and hyperthyroid symptoms, often without classic Graves findings. Autonomous follicular cells produce hormone independently, causing symptoms like heat intolerance and palpitations. Unlike Graves disease, a toxic adenoma often lacks ophthalmopathy and pretibial myxedema, so the combination of a thyroid nodule and suppressed TSH is the key clue.
When is thyroid ultrasound the right next step for a thyroid nodule?
Thyroid ultrasound is the right next step when TSH is normal or high. In those patients, ultrasound is used for risk stratification and helps determine whether FNA is needed based on suspicious sonographic features and size. It is also useful for evaluating cervical lymph nodes, but in a patient with low TSH, radionuclide uptake scan comes first rather than ultrasound.
Why is CT neck with contrast a bad first test for a thyroid nodule?
CT of the neck with contrast is not first-line for thyroid nodule evaluation because it does not replace the standard ultrasound and FNA-based algorithm. In addition, iodinated contrast can interfere with later radioiodine uptake or ablation and may worsen hyperthyroidism in susceptible patients. CT is reserved for specific situations such as suspected large substernal goiter with compressive symptoms or invasive disease when ultrasound is limited.