Subacute (de Quervain) thyroiditis is a painful, probably viral, granulomatous inflammation of the thyroid: often after an upper respiratory infection, the gland becomes firm and exquisitely tender, the patient is febrile and thyrotoxic, the ESR is high and the radioactive iodine uptake (RAIU) is near zero. The hormone excess comes from destroyed follicles leaking stored T4 and T3, not from new synthesis, so the course is thyrotoxic, then hypothyroid, then usually back to normal within months. Treatment is a beta-blocker for symptoms and an NSAID for pain, with prednisone for severe or NSAID-resistant cases; methimazole, PTU and radioiodine have no role.
The Q-bank vignette
A 41-year-old woman has had 10 days of pain in the front of her neck that radiates to her right ear and jaw and has shifted from the right side to the left. Three weeks ago she had a sore throat and a runny nose. She now has palpitations, tremor and heat intolerance. Temperature is 38.2°C (100.8°F) and pulse 112/min. The thyroid is asymmetrically enlarged, firm and very tender, with no fluctuance, overlying redness or lymphadenopathy. There is no proptosis and no skin change over the shins. TSH is below 0.01 mU/L (suppressed), free T4 3.4 ng/dL (high), ESR 82 mm/h and leukocyte count 9,600/mm³. The 24-hour RAIU is 1% (low).
Which is the most likely diagnosis?
- A. Acute suppurative thyroiditis
- B. Factitious thyrotoxicosis
- C. Graves disease
- D. Hashimoto thyroiditis
- E. Painless (silent) thyroiditis
- F. Subacute granulomatous (de Quervain) thyroiditis
- G. Toxic multinodular goiter
Answer: F, subacute granulomatous (de Quervain) thyroiditis.
Why it is subacute thyroiditis
- Pain that moves: anterior neck pain that shifts from side to side and radiates to the jaw and ears, with fever and more lassitude than other thyroid disorders.
- Viral prologue: an antecedent upper respiratory infection is common; coxsackievirus, adenovirus, mumps and echovirus are implicated. Case reports and series also link it to SARS-CoV-2, with a classic presentation, although a 2021 systematic review judged it not a direct or frequent complication of COVID-19.
- Who: women are affected up to about four times as often as men, and HLA-B35 carriers appear predisposed.
- Exam: the gland is asymmetrically enlarged, firm and tender.
- Labs: suppressed TSH and high free T4 and T3 early; ESR is usually above 50 mm/h (ATA 2016); thyroid antibodies are absent or only weakly positive; thyroglobulin is not low, because it leaks from damaged follicles.
- Uptake: RAIU is low, often near zero, because a damaged, TSH-suppressed gland traps little iodine.
- Ultrasound: irregular hypoechoic areas with reduced blood flow on color Doppler, the opposite of the increased flow of Graves disease.
- Pathology: granulomas with multinucleated giant cells, epithelioid histiocytes and follicular disruption; how it compares with other granulomatous diseases is in the granulomatous inflammation table.
Why every other answer choice is wrong
A. Acute suppurative thyroiditis. Tempting because the thyroid is painful and the patient is febrile. It is a bacterial infection, usually Streptococcus pyogenes or Staphylococcus aureus, and is more common in children (mostly ages 5–15); a pyriform sinus fistula is the classic predisposing anomaly, and the abscess is more often in the left lobe. Expect a warm, red, sometimes fluctuant mass, pain on swallowing, leukocytosis and, in most patients, normal thyroid function. Ultrasound shows an abscess, and aspiration yields pus with neutrophils. Treatment is IV antibiotics plus drainage, then repair of any fistula.
B. Factitious thyrotoxicosis. The low RAIU fits, because exogenous hormone suppresses TSH and uptake. But the gland is not tender, the ESR is normal and serum thyroglobulin is low or low-normal, unlike every other cause of hyperthyroidism, because the patient's own gland is idle.
C. Graves disease. The classic trap: low TSH and high T4, but the goiter is painless and diffuse, often with a bruit, ophthalmopathy or pretibial myxedema. TSH receptor antibodies are positive, RAIU is high and diffuse, Doppler flow is increased, and a total T3 to total T4 ratio above 20 ng/µg (a cutoff the ATA cites from one study) favors Graves. Graves is the one that needs methimazole, radioiodine or surgery; the full breakdown is in the Graves disease Q-bank.
D. Hashimoto thyroiditis. Painless, firm, rubbery goiter with high-titer thyroid peroxidase (TPO) antibodies, lymphocytic infiltration with lymphoid follicles, and usually permanent hypothyroidism needing lifelong levothyroxine. A transient hyperthyroid phase can occur, but not a tender gland with fever and an ESR of 82 mm/h.
E. Painless (silent) thyroiditis. The closest cousin: also destructive, with the same thyrotoxic-hypothyroid-recovery course and a near-zero RAIU. But "silent" means no tenderness, the ESR and white count are normal, it typically appears postpartum (when TPO antibodies are almost always positive) and it recurs after later pregnancies. Its total T3 to total T4 ratio tends to be below 20 ng/µg.
G. Toxic multinodular goiter. Autonomous nodules in an older patient make new hormone, so RAIU is high and patchy (focal in a single toxic adenoma). The goiter is painless, there is no viral prologue and the ESR is normal.
Low-uptake vs high-uptake thyrotoxicosis
| Cause | Pain | Inflammatory markers | RAIU | Clincher | Treatment |
|---|---|---|---|---|---|
| Subacute (de Quervain) | Tender | High ESR | Near zero | Post-viral, fever, giant cells | Beta-blocker + NSAID; prednisone if severe |
| Painless or postpartum | None | Normal | Near zero | TPO antibodies, postpartum | Beta-blocker; levothyroxine if hypothyroid |
| Factitious | None | Normal | Near zero | Low thyroglobulin | Stop the hormone |
| Acute suppurative | Tender, red, fluctuant | High WBC, ESR and CRP | Not the key test; function usually normal | Child, fistula, abscess, pus | IV antibiotics + drainage |
| Graves | None | Normal | High, diffuse | TSH receptor antibodies, eye signs | Methimazole, radioiodine or surgery |
| Toxic nodular goiter | None | Normal | High, patchy or focal | Older patient, nodules | Radioiodine, surgery or methimazole |
Rule: thyrotoxicosis with a low RAIU means thyroiditis, an iodine load or ingested thyroid hormone; a high RAIU means the gland is overproducing hormone (Graves, toxic nodules). Then let pain, ESR, antibodies and thyroglobulin pick the cause.
Follow-up question: management
Propranolol and ibuprofen are started. Five days later her pain is still severe, she remains febrile and she cannot sleep. What is the most appropriate next step?
- A. Add methimazole
- B. Radioactive iodine ablation
- C. Start prednisone
- D. IV antibiotics and surgical drainage
- E. Start levothyroxine
- F. Total thyroidectomy
Answer: C, prednisone. NSAIDs or high-dose aspirin suit mild disease; the ATA advises switching to a glucocorticoid when symptoms fail to respond to full-dose NSAIDs over several days or when pain or thyrotoxic symptoms are moderate to severe at presentation. Merck gives prednisone 15–30 mg once daily, tapered over 3–4 weeks. Keep the beta-blocker: the ATA recommends beta-blockade for all patients with symptomatic thyrotoxicosis.
- Methimazole: blocks new hormone synthesis, but this gland is not synthesizing anything; it is leaking. For the same reason Merck calls antithyroid drugs, surgery and radioiodine contraindicated in silent thyroiditis. When each thionamide is used is in the antithyroid drugs flowchart.
- Radioactive iodine: an RAIU of 1% leaves nothing to target, and the gland will recover on its own.
- IV antibiotics and drainage: treatment for acute suppurative thyroiditis, an abscess with leukocytosis, not a granulomatous thyroiditis.
- Levothyroxine: adds hormone to a thyrotoxic patient; it belongs to a symptomatic or persistent hypothyroid phase.
- Total thyroidectomy: a permanent operation for a self-limited inflammation.
The triphasic course
| Phase | When | Labs | Management |
|---|---|---|---|
| Thyrotoxic | First several weeks | High free T4 and T3, suppressed TSH, high ESR, RAIU near zero | Beta-blocker; NSAID, or prednisone if severe |
| Hypothyroid | After stores are depleted, several weeks in | Low free T4, rising TSH | Levothyroxine if needed, then reassess |
| Recovery | Most are euthyroid within 6–12 months | Normal | Recheck TFTs; occasional recurrence or permanent hypothyroidism when destruction is extensive |
Exam traps
- "Hyperthyroid symptoms" does not mean increased synthesis. Check the RAIU before choosing a thionamide.
- Pain sorts the low-uptake causes: tender gland with a high ESR = de Quervain; painless with TPO antibodies after delivery = silent (postpartum) thyroiditis; low thyroglobulin = factitious.
- Pain is not always thyroiditis: Merck notes that a painful nodule can also mean hemorrhage into a cyst.
- Rapid, painful enlargement in an older adult raises anaplastic carcinoma, and rapid growth on a background of Hashimoto raises thyroid lymphoma; compare the cancers in the thyroid cancer types chart.
- Recovery is the rule: don't commit a patient to lifelong levothyroxine during the transient hypothyroid phase without rechecking.
Key takeaways
- De Quervain thyroiditis = painful, tender, post-viral granulomatous thyroiditis with fever, high ESR and a near-zero RAIU.
- Mechanism: release of preformed hormone from damaged follicles, so thionamides and radioiodine don't help.
- Course: thyrotoxic, then hypothyroid, then usually euthyroid within 6–12 months; permanent hypothyroidism occasionally.
- Treatment: beta-blocker plus NSAID; prednisone 15–30 mg a day, tapered over 3–4 weeks, for severe or NSAID-resistant pain.
- Mimics: painless thyroiditis (no pain, TPO antibodies, postpartum), Graves (high diffuse RAIU, TSH receptor antibodies), suppurative (abscess, leukocytosis, normal function), factitious (low thyroglobulin).
Sources
- Subacute Thyroiditis — Merck Manual Professional Edition (2026)
- Silent Lymphocytic Thyroiditis — Merck Manual Professional Edition (2026)
- Hyperthyroidism — Merck Manual Professional Edition (2026)
- Hashimoto Thyroiditis — Merck Manual Professional Edition (2026)
- 2016 American Thyroid Association Guidelines for Diagnosis and Management of Hyperthyroidism and Other Causes of Thyrotoxicosis — Thyroid (2016)
- Comparison of the therapeutic effects of 15 mg and 30 mg initial dosage of prednisolone daily in patients with subacute thyroiditis: protocol for a multicenter, randomized, open, parallel control study — Trials (2020)
- Acute Suppurative and Subacute Thyroiditis: From Diagnosis to Management — Journal of Clinical Medicine (2025)
- COVID-19-Associated Subacute Thyroiditis: Evidence-Based Data From a Systematic Review — Frontiers in Endocrinology (2021)
- Approach to the Patient With a Thyroid Nodule — Merck Manual Professional Edition (2026)
- Thyroid Cancers — Merck Manual Professional Edition (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
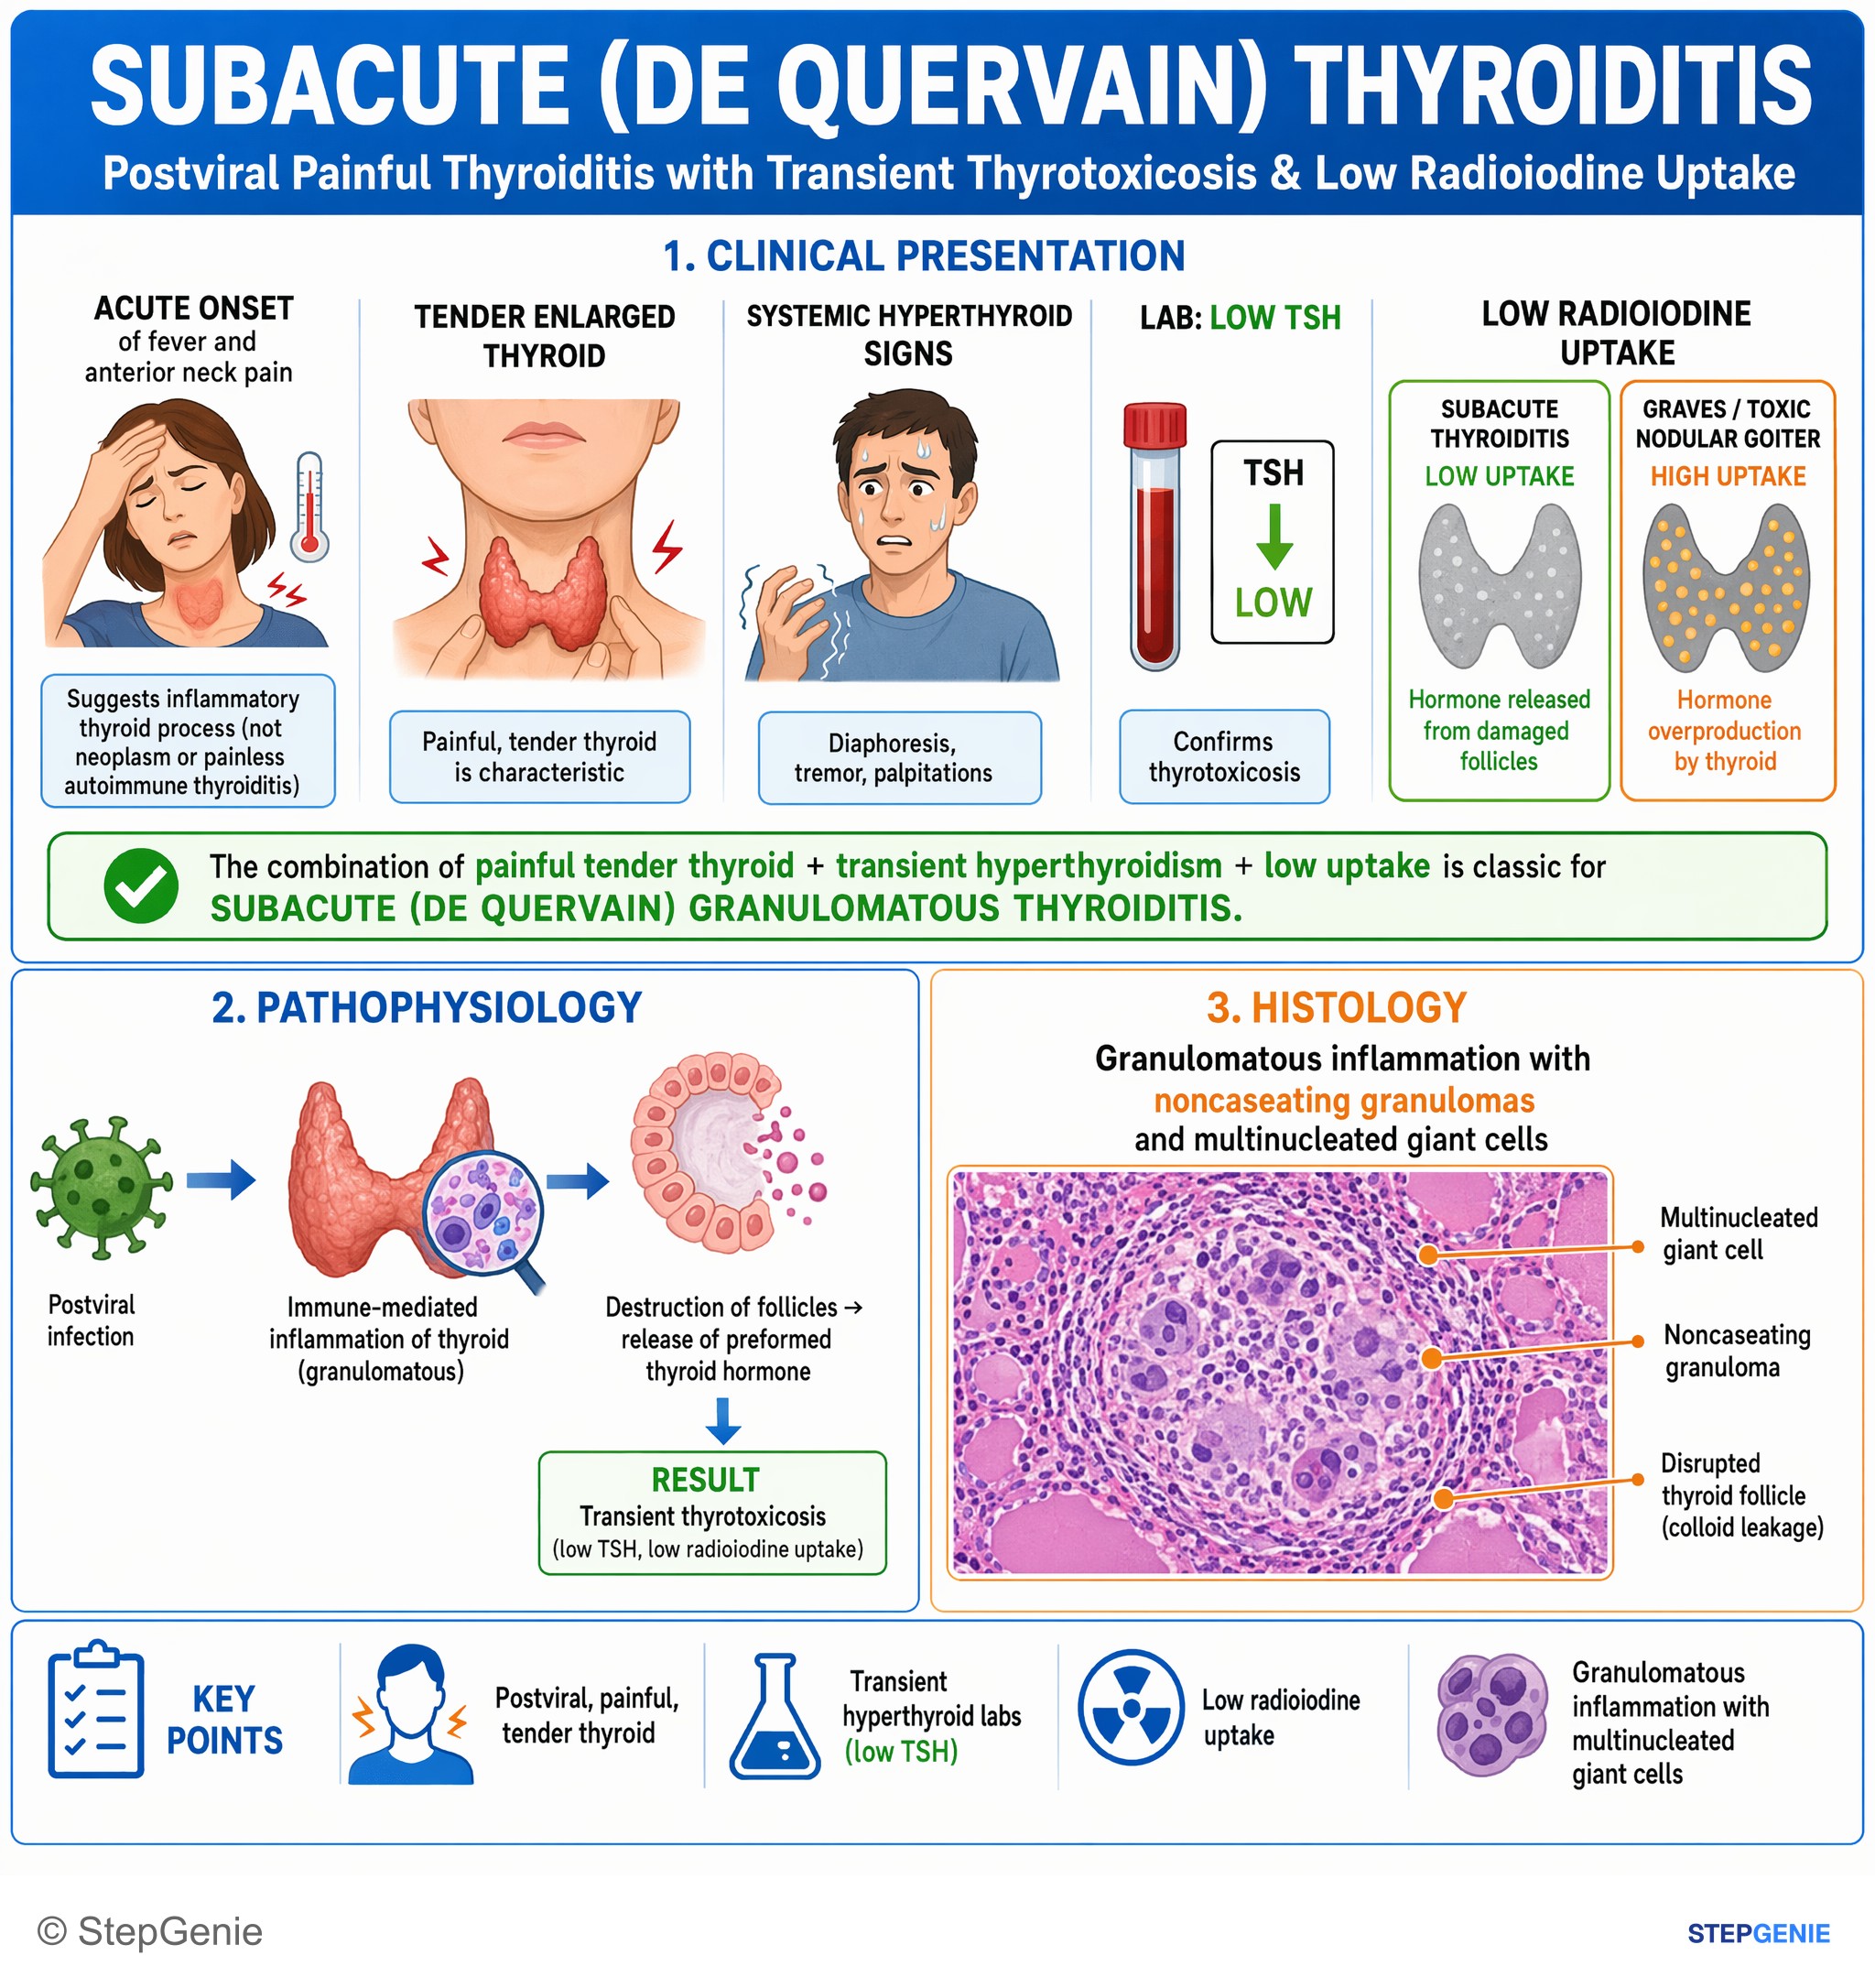
Subacute (de Quervain) thyroiditis: postviral painful tender thyroid, transient hyperthyroid labs, low radioiodine uptake, granulomatous…
USMLE Step 1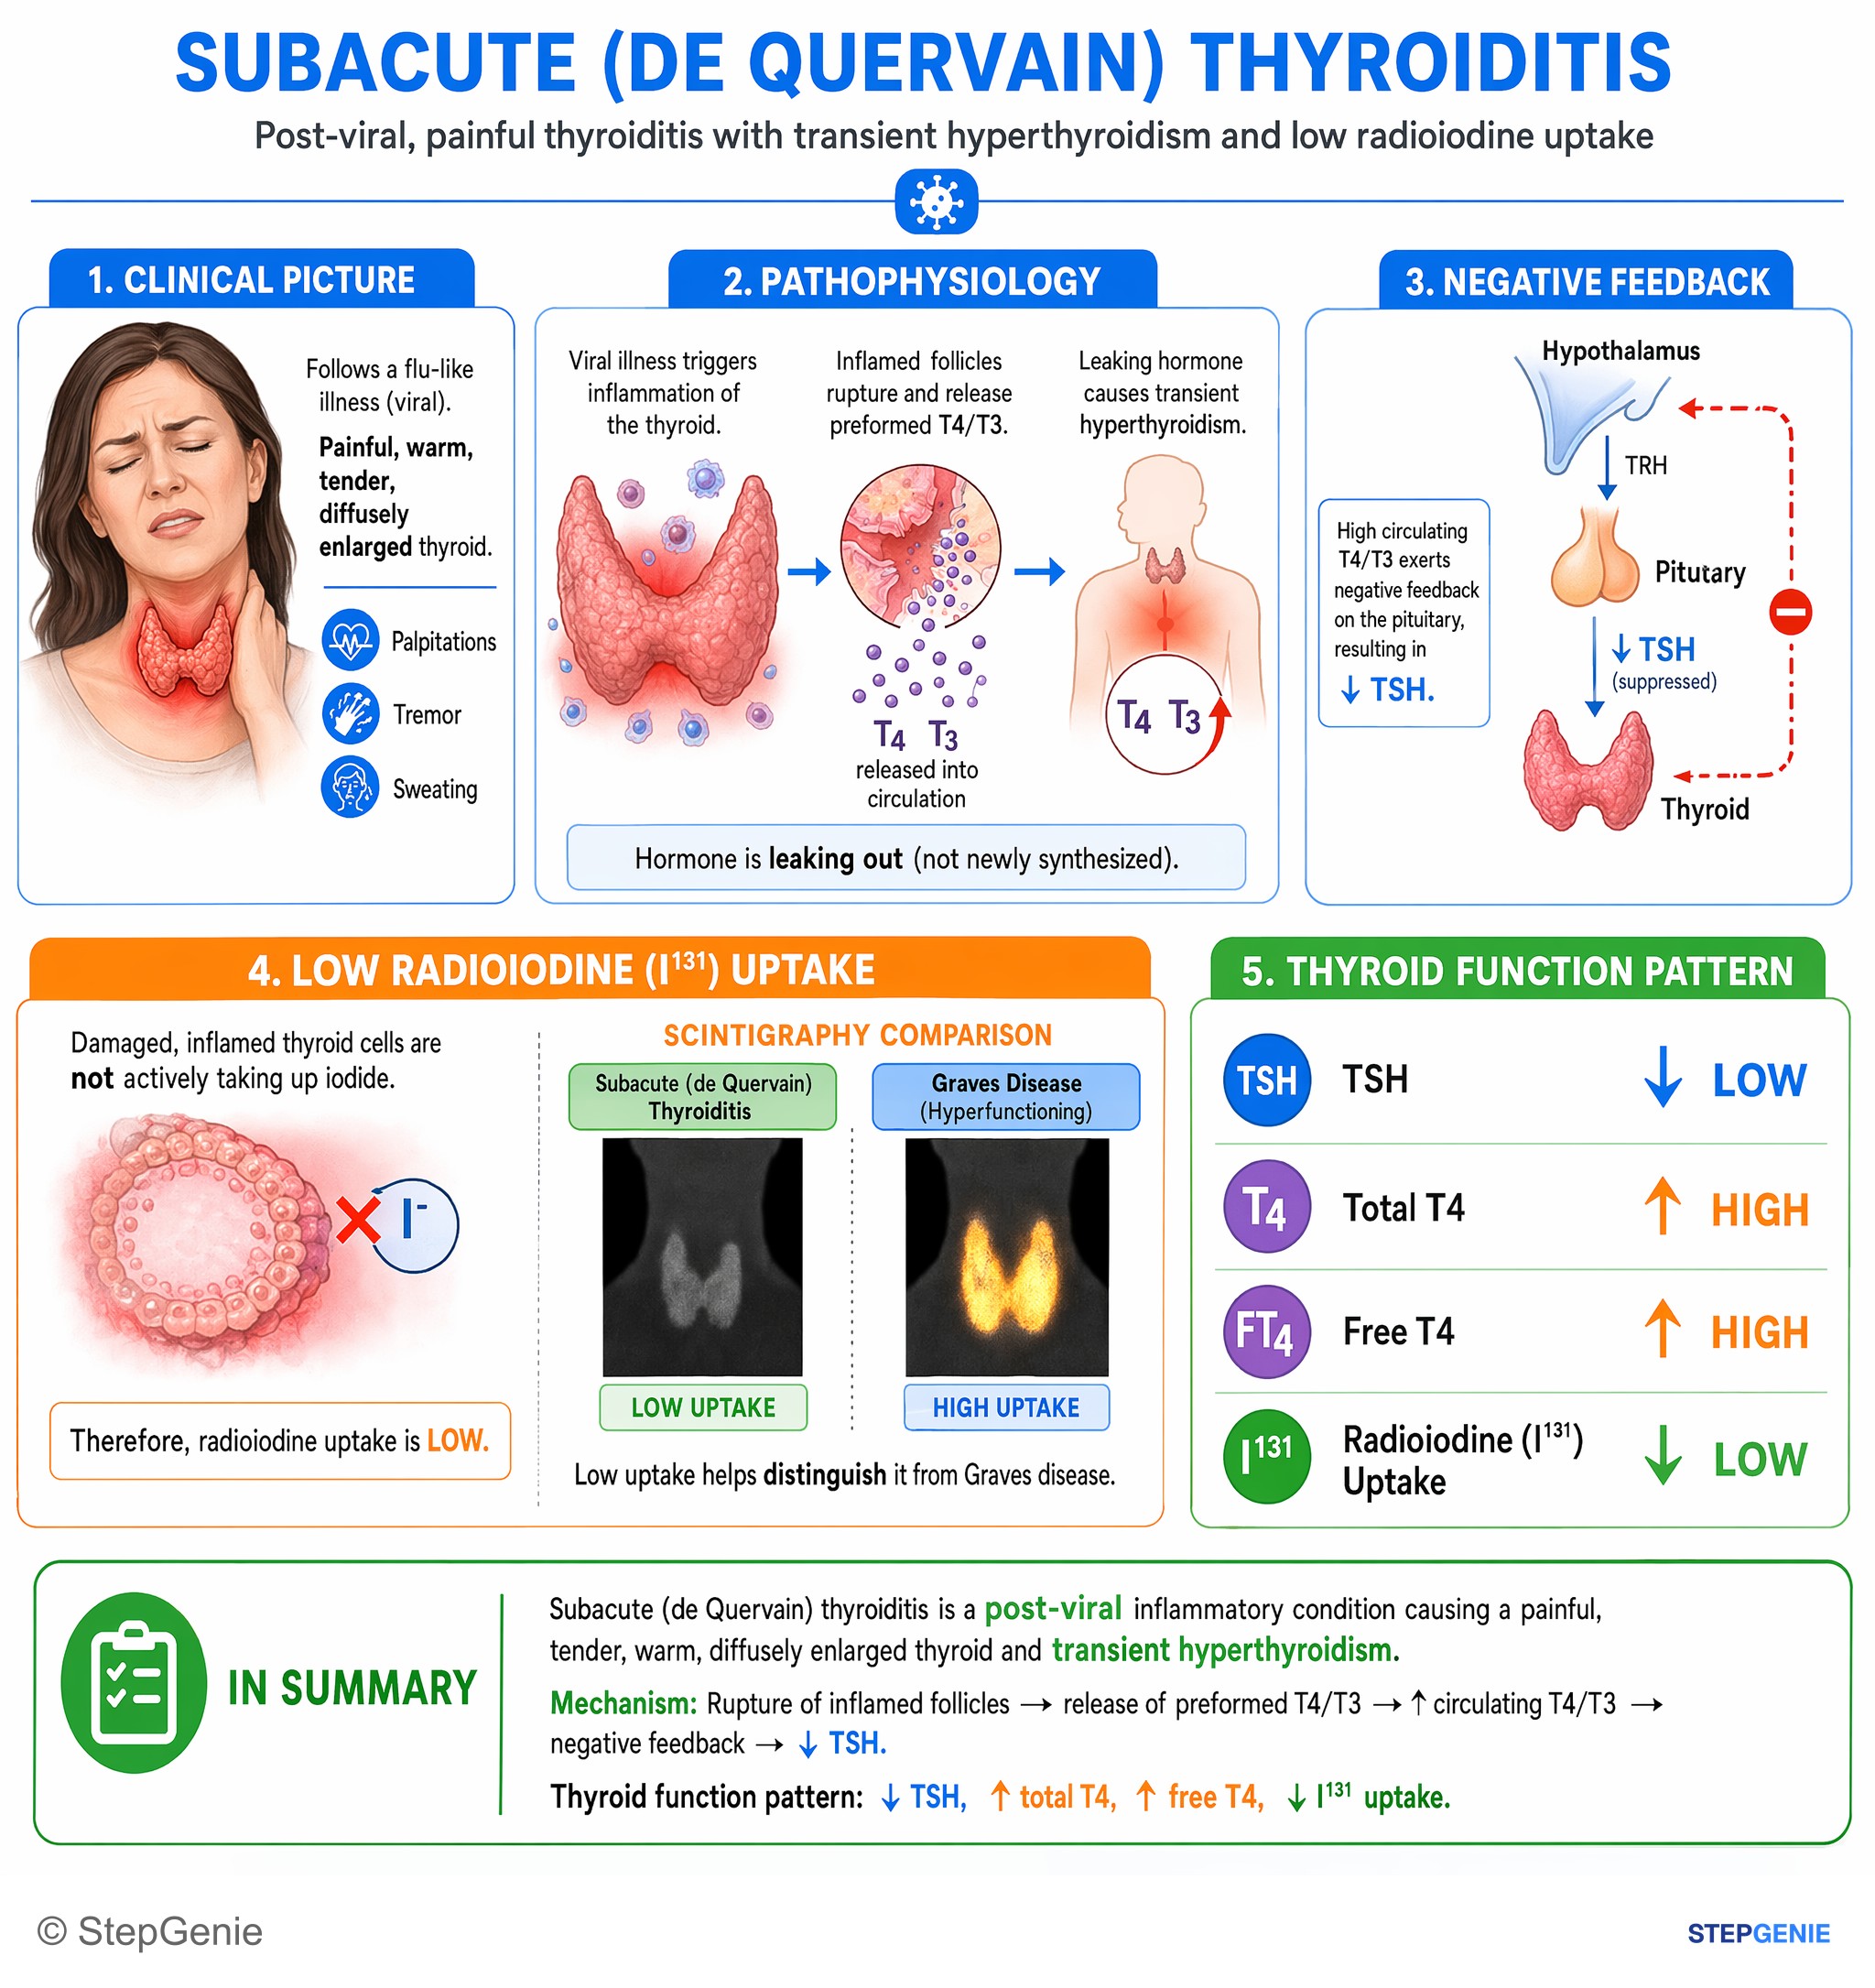
Subacute (de Quervain) thyroiditis: post-viral, painful tender thyroid, transient hyperthyroidism with high T4, low TSH, and low…
USMLE Step 1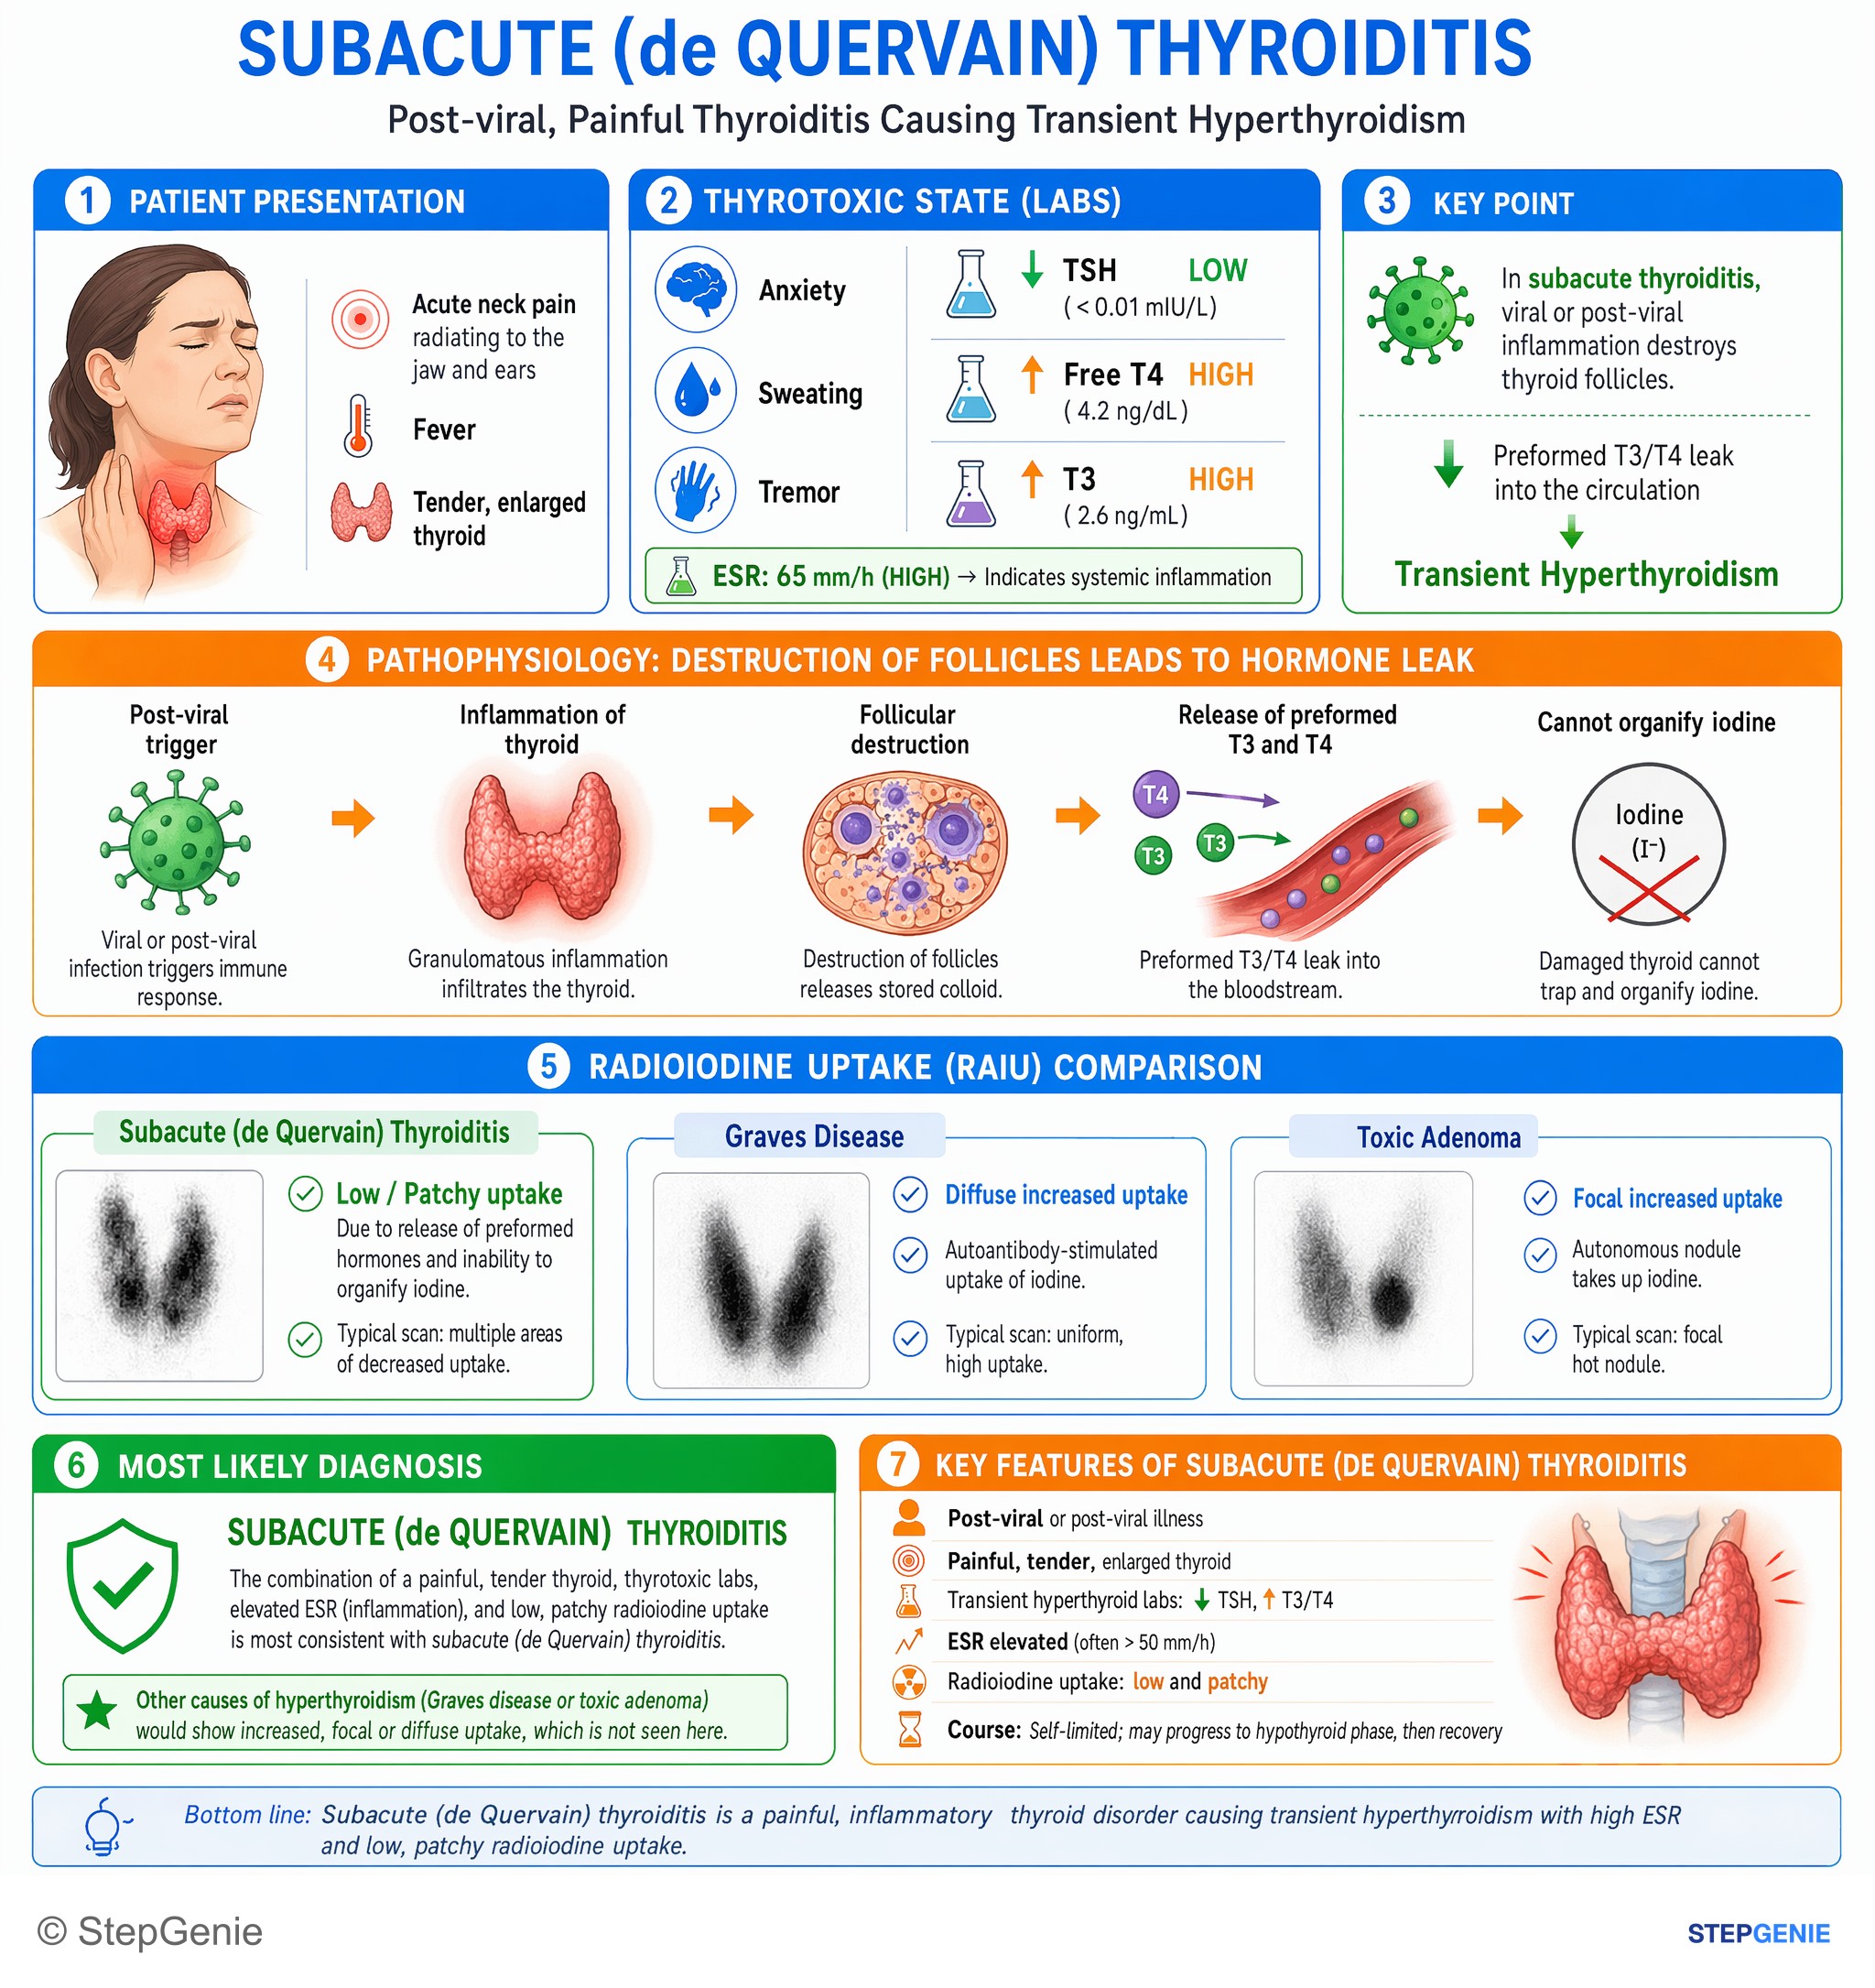
Subacute (de Quervain) thyroiditis: post-viral, painful tender thyroid, transient hyperthyroid labs, high ESR, and low, patchy radioiodine…
USMLE Step 2Frequently Asked Questions
What are the symptoms of subacute (de Quervain) thyroiditis?
The classic picture is anterior neck pain that radiates to the jaw or ears and may shift from side to side, often after an upper respiratory infection, with fever, fatigue and a firm, tender, asymmetrically enlarged thyroid. Early on, leaked thyroid hormone causes palpitations, tremor, heat intolerance and weight loss. Weeks later some patients become hypothyroid before recovering.
Why is radioactive iodine uptake low in subacute thyroiditis?
The thyrotoxicosis comes from inflamed, damaged follicles releasing stored T4 and T3, not from increased hormone synthesis. The damaged gland takes up little iodine while TSH is suppressed, so the 24-hour uptake is low, often near zero. Graves disease and toxic nodules make new hormone and show high uptake.
How is subacute thyroiditis treated?
Mild cases are treated with an NSAID or high-dose aspirin for pain and a beta-blocker such as propranolol for palpitations and tremor. Severe or NSAID-resistant pain is treated with a glucocorticoid, for example prednisone 15 to 30 mg a day tapered over 3 to 4 weeks. Methimazole, PTU and radioactive iodine are not used, and levothyroxine is given only if a hypothyroid phase needs it.
How do you tell subacute thyroiditis from Graves disease?
Subacute thyroiditis causes a painful, tender gland with fever, a high ESR, reduced blood flow on Doppler ultrasound and a near-zero radioiodine uptake. Graves disease is painless and has TSH receptor antibodies, often eye signs or pretibial myxedema, increased Doppler flow and a high, diffuse radioiodine uptake. Methimazole treats Graves disease but has no role in subacute thyroiditis.
What is the difference between subacute thyroiditis and painless (silent) thyroiditis?
Both destroy thyroid follicles, cause temporary thyrotoxicosis with a low radioiodine uptake and follow a thyrotoxic, hypothyroid and recovery course. Subacute thyroiditis is painful, with fever and a high ESR, and is thought to follow a viral infection. Painless thyroiditis has no tenderness and a normal ESR, is autoimmune, often occurs after delivery with positive TPO antibodies and tends to recur after later pregnancies.
How long does subacute thyroiditis last?
It is self-limited and usually subsides within a few months. The thyrotoxic phase lasts several weeks, a hypothyroid phase may follow, and most patients are euthyroid within 6 to 12 months. It occasionally recurs, and extensive destruction can leave permanent hypothyroidism.