You just opened a question stem that screams “hyperthyroidism,” but the real test isn’t picking Graves once—you’re being graded on whether you can exclude everything else just as confidently. This post walks through a classic Graves vignette, then dismantles every distractor the way NBME-style exams want you to: by mechanism, labs, and the one or two clinchers that separate look-alikes.
The Clinical Vignette (Classic Q-bank Style)
A 28-year-old woman comes to clinic for 2 months of palpitations, anxiety, heat intolerance, and unintentional weight loss despite increased appetite. She also reports frequent bowel movements. Exam shows a fine tremor, brisk reflexes, and a diffusely enlarged, nontender thyroid. Her eyes appear “more prominent” than before. Vitals: HR 112/min, BP 128/68, temp 37.1°C (98.8°F). Labs:
| Test | Result |
|---|---|
| TSH | Low |
| Free T4 | High |
Which of the following is the most likely underlying mechanism?
A. Autoantibodies that stimulate the TSH receptor
B. Autoimmune destruction of thyroid follicles
C. Ectopic thyroid hormone production from ovarian tissue
D. Release of preformed thyroid hormone after viral infection
E. Pituitary adenoma secreting TSH
F. Excess iodine intake leading to increased thyroid hormone synthesis
Step 1: Identify the Pattern
This is primary hyperthyroidism until proven otherwise:
- Low TSH + high free T4 = thyroid is overproducing hormone → pituitary appropriately suppresses TSH.
- Symptoms: heat intolerance, weight loss, tremor, palpitations, hyperdefecation.
- Exam: diffuse goiter.
- The extra giveaway: eye findings (proptosis) strongly point to Graves disease.
Correct Answer: A. Autoantibodies that stimulate the TSH receptor (Graves disease)
Why it’s correct
Graves is caused by IgG autoantibodies (thyroid-stimulating immunoglobulins, TSI) that bind and activate the TSH receptor on thyroid follicular cells → increased thyroid hormone synthesis and gland growth.
High-yield Graves hallmarks
- Diffuse goiter (often with a thyroid bruit from increased vascularity)
- Ophthalmopathy (proptosis, diplopia) due to fibroblast activation and glycosaminoglycan deposition in the orbit
- Pretibial myxedema (less common; dermopathy)
- Association with other autoimmune disease
Labs & tests you should expect
- TSH low, free T4 (± T3) high
- TSI / TRAb positive
- Radioactive iodine uptake (RAIU): high, diffuse uptake
(This often separates Graves from thyroiditis/factitious causes.)
Treatment anchors (Step 1 + Step 2)
- Symptom control: beta-blocker (e.g., propranolol; also decreases peripheral T4→T3 conversion at higher doses)
- Decrease synthesis: methimazole (first-line)
- Exception: 1st trimester pregnancy or thyroid storm → PTU
- Definitive: radioiodine ablation or surgery
- Eye disease: smoking worsens; may require glucocorticoids/other immunomodulation in moderate-severe cases
Now the Real Exam Skill: Destroy the Distractors
B. Autoimmune destruction of thyroid follicles (Hashimoto thyroiditis)
Why it’s tempting: autoimmune thyroid disease is common; can have goiter early.
Why it’s wrong here:
- Hashimoto is typically hypothyroidism (fatigue, weight gain, cold intolerance, constipation).
- Labs usually: TSH high, free T4 low (or normal early).
- Antibodies: anti-TPO, anti-thyroglobulin.
- Can rarely cause transient hyperthyroid phase (“hashitoxicosis”), but it does not cause ophthalmopathy and RAIU is not diffusely increased.
Clinchers for Hashimoto:
- Painless goiter + hypothyroid symptoms
- Increased risk of B-cell (MALT) lymphoma
- Histology: Hurthle cells, lymphoid aggregates with germinal centers
C. Ectopic thyroid hormone production from ovarian tissue (Struma ovarii)
Why it’s tempting: hyperthyroidism with a non-thyroid source can suppress TSH.
Why it’s wrong here:
- Struma ovarii is a specialized ovarian teratoma containing thyroid tissue.
- Thyroid gland itself is usually not diffusely enlarged with high uptake.
- RAIU would show low uptake in the thyroid with uptake in the pelvis (if scanned appropriately).
Clinchers for struma ovarii:
- Hyperthyroidism + pelvic mass symptoms (pain, fullness)
- Imaging suggests ovarian tumor
- Thyroid is not “revved up” diffusely on uptake scan
D. Release of preformed thyroid hormone after viral infection (Subacute (de Quervain) thyroiditis)
Why it’s tempting: hyperthyroid symptoms with low TSH happen here too.
Why it’s wrong here:
- De Quervain thyroiditis classically causes painful, tender thyroid often after an upper respiratory infection.
- Mechanism is release of preformed hormone from inflamed follicles → low RAIU (the gland isn’t synthesizing new hormone).
- Eye findings are not a feature.
Clinchers for de Quervain:
- Painful thyroid, fever, malaise
- Elevated ESR/CRP
- Triphasic course: hyperthyroid → hypothyroid → recovery
- Treat pain/inflammation: NSAIDs, sometimes steroids
E. Pituitary adenoma secreting TSH (Secondary hyperthyroidism)
Why it’s tempting: hyperthyroidism can result from too much TSH.
Why it’s wrong here:
- In TSH-secreting adenoma, TSH is inappropriately normal or high, not low.
- You may see other pituitary mass effects: headaches, visual field defects.
- Alpha-subunit may be elevated; MRI pituitary confirms.
Clinchers for TSH adenoma:
- High TSH + high free T4
- Consider also thyroid hormone resistance (but that’s rarer; often family history and less symptomatic)
F. Excess iodine intake leading to increased thyroid hormone synthesis (Jod-Basedow phenomenon)
Why it’s tempting: iodine can trigger hyperthyroidism.
Why it’s wrong here:
- Iodine-induced hyperthyroidism occurs especially in patients with:
- Multinodular goiter
- Latent Graves
- The vignette points to diffuse goiter + ophthalmopathy, which is Graves.
- RAIU is often low after iodine load because the gland is saturated with non-radioactive iodine (depends on timing and context), but clinically this is usually a history-driven diagnosis.
Clinchers for Jod-Basedow:
- Recent iodine exposure: amiodarone, iodinated contrast, supplements
- Often underlying nodular thyroid disease
- No Graves eye/skin findings
Rapid-Fire Comparison Table (High Yield)
| Condition | Thyroid pain? | TSH | Free T4/T3 | RAIU | Key clues |
|---|---|---|---|---|---|
| Graves | No | ↓ | ↑ | High diffuse | Ophthalmopathy, pretibial myxedema, TSI/TRAb+ |
| Toxic multinodular goiter | No | ↓ | ↑ | High patchy | Older patient, nodular thyroid |
| Toxic adenoma | No | ↓ | ↑ | High focal | Single “hot” nodule |
| Subacute (de Quervain) | Yes | ↓ | ↑ early | Low | Viral prodrome, ↑ESR/CRP |
| Silent/postpartum thyroiditis | No | ↓ early | ↑ early | Low | Postpartum, autoimmune history |
| Factitious thyrotoxicosis | No | ↓ | ↑ | Low | Low thyroglobulin, no goiter |
| TSH adenoma | No | ↑/N | ↑ | High diffuse | Pituitary mass symptoms |
“Why Every Answer Choice Matters”: Exam-Takeaway Algorithm
When you see low TSH + high T4/T3:
- Think primary hyperthyroidism first.
- Ask: Is uptake high or low? (even if not given, infer from mechanism)
- High uptake = increased synthesis (Graves, toxic nodules)
- Low uptake = release of preformed hormone or exogenous hormone (thyroiditis, factitious, iodine load)
- Look for one discriminator:
- Eye findings → Graves
- Pain + ↑ESR → de Quervain
- Nodules/older age → toxic multinodular goiter
- No goiter + low thyroglobulin → factitious
- High/normal TSH → central cause (TSH adenoma, resistance)
High-Yield Extras That Show Up on USMLE
Thyroid storm (don’t miss this)
Severe hyperthyroidism with fever, delirium, GI symptoms, tachyarrhythmia. Treatment sequence to remember:
- Beta-blocker
- Thionamide (PTU preferred in storm)
- Iodine (given after thionamide)
- Glucocorticoids (also decreases T4→T3 conversion)
Pregnancy pearl
- Methimazole: teratogenic (aplastic cutis, choanal/esophageal atresia) → avoid in 1st trimester
- PTU: hepatotoxicity risk but preferred in 1st trimester and thyroid storm
Key Takeaways (What to Memorize)
- Graves = TSI/TRAb stimulates TSH receptor → diffuse goiter + ophthalmopathy + high diffuse RAIU
- Thyroiditis (painful or silent) = hormone leakage → low RAIU
- Central hyperthyroidism = TSH not suppressed
- When the stem gives you “extra” clues (eye findings, pain, nodules), it’s telling you exactly which distractors to eliminate.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
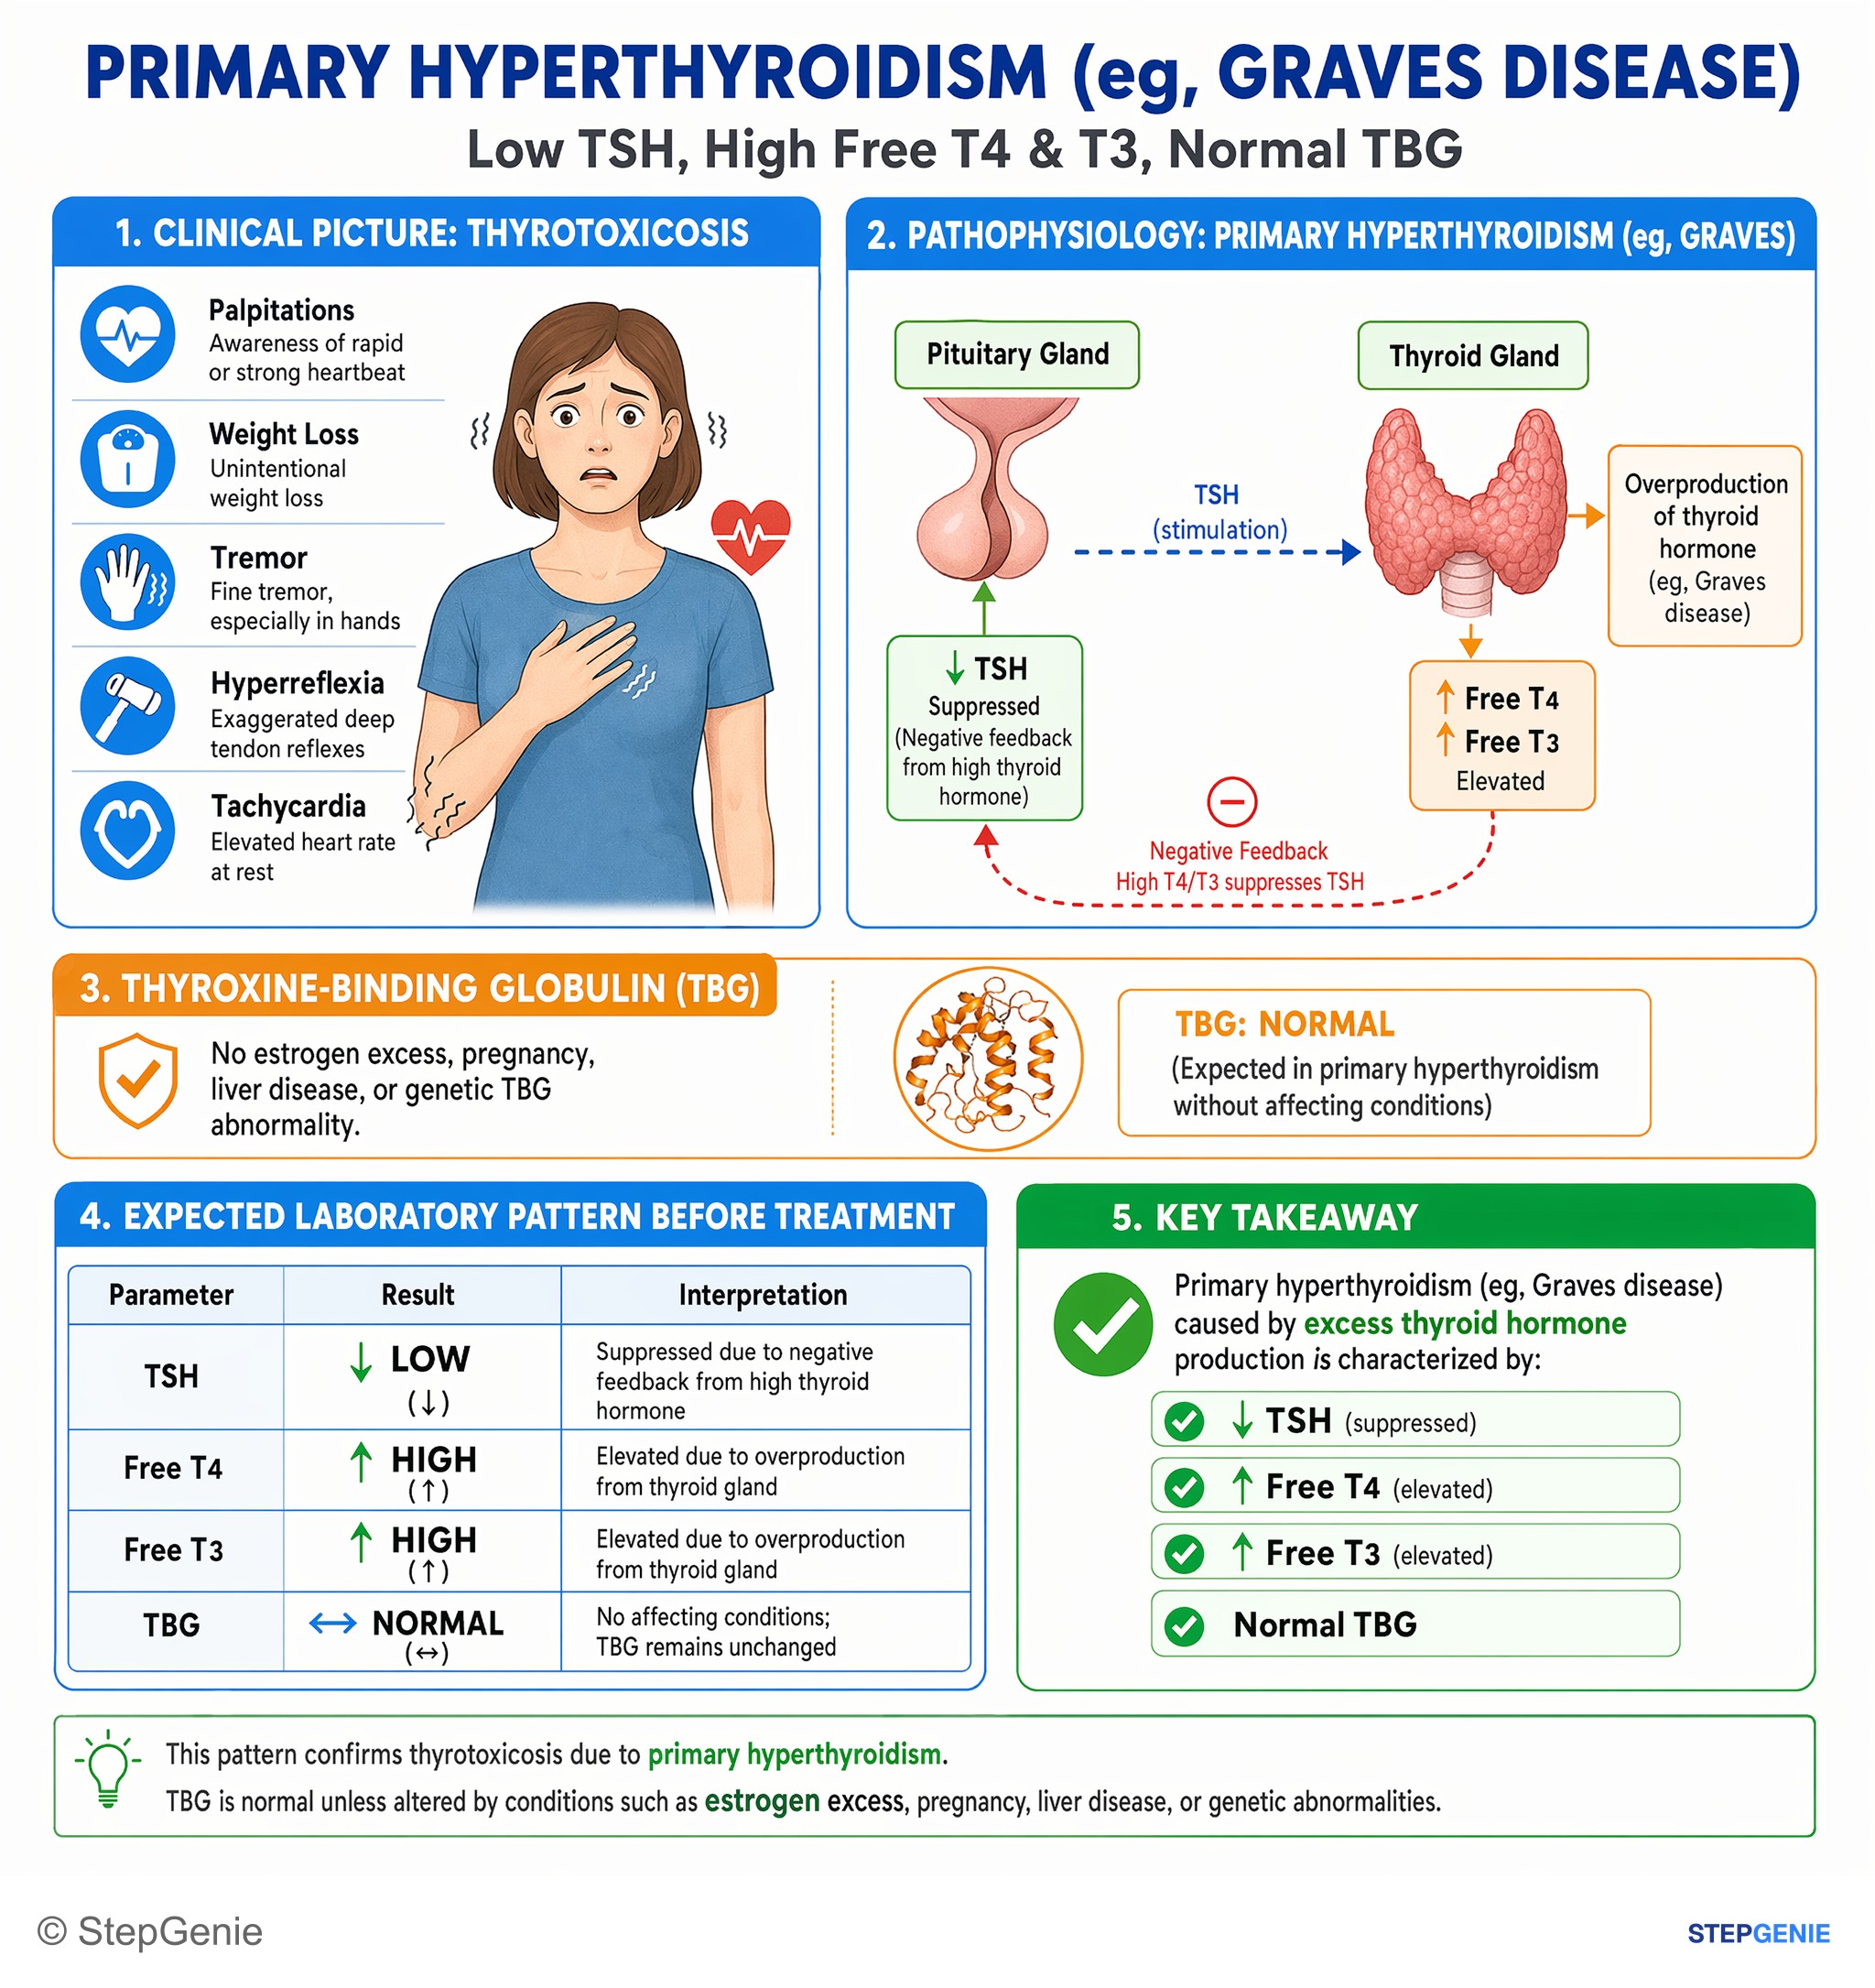
Primary hyperthyroidism from excess thyroid hormone: low TSH, high free T4 and T3, normal thyroxine-binding globulin.
USMLE Step 1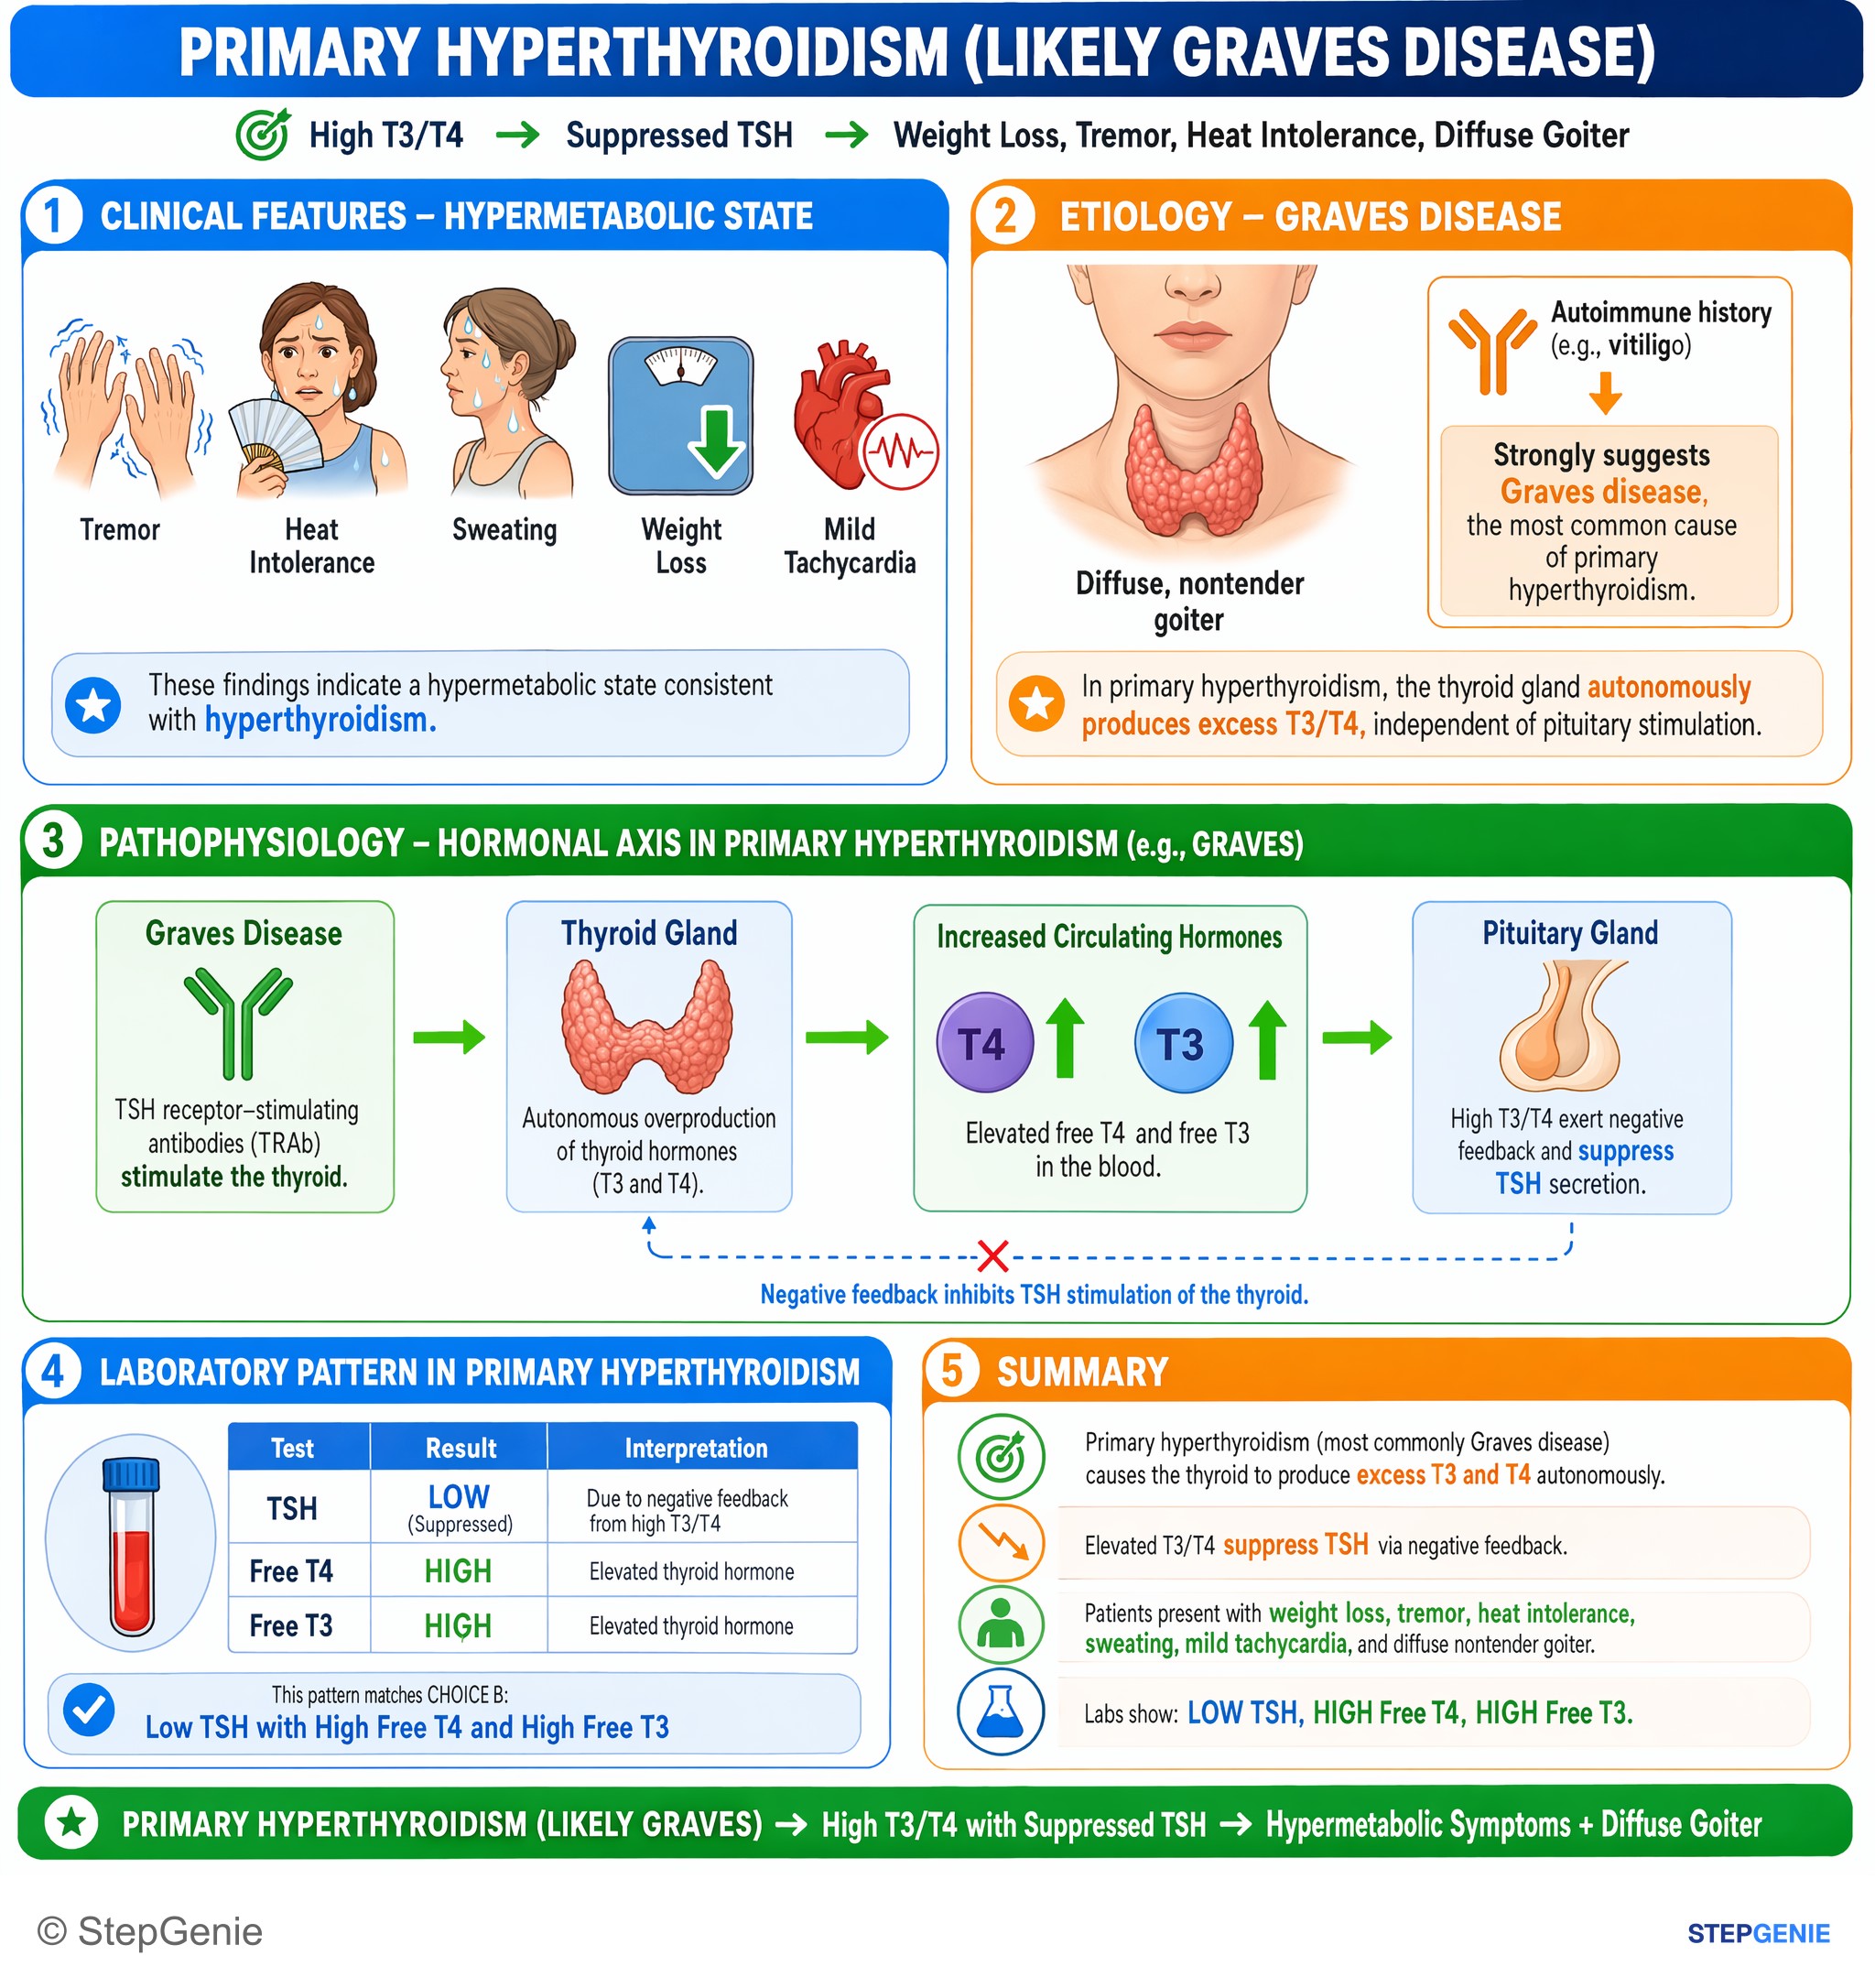
Primary hyperthyroidism (likely Graves) causes high T3/T4 with suppressed TSH, presenting with weight loss, tremor, heat intolerance, and…
USMLE Step 1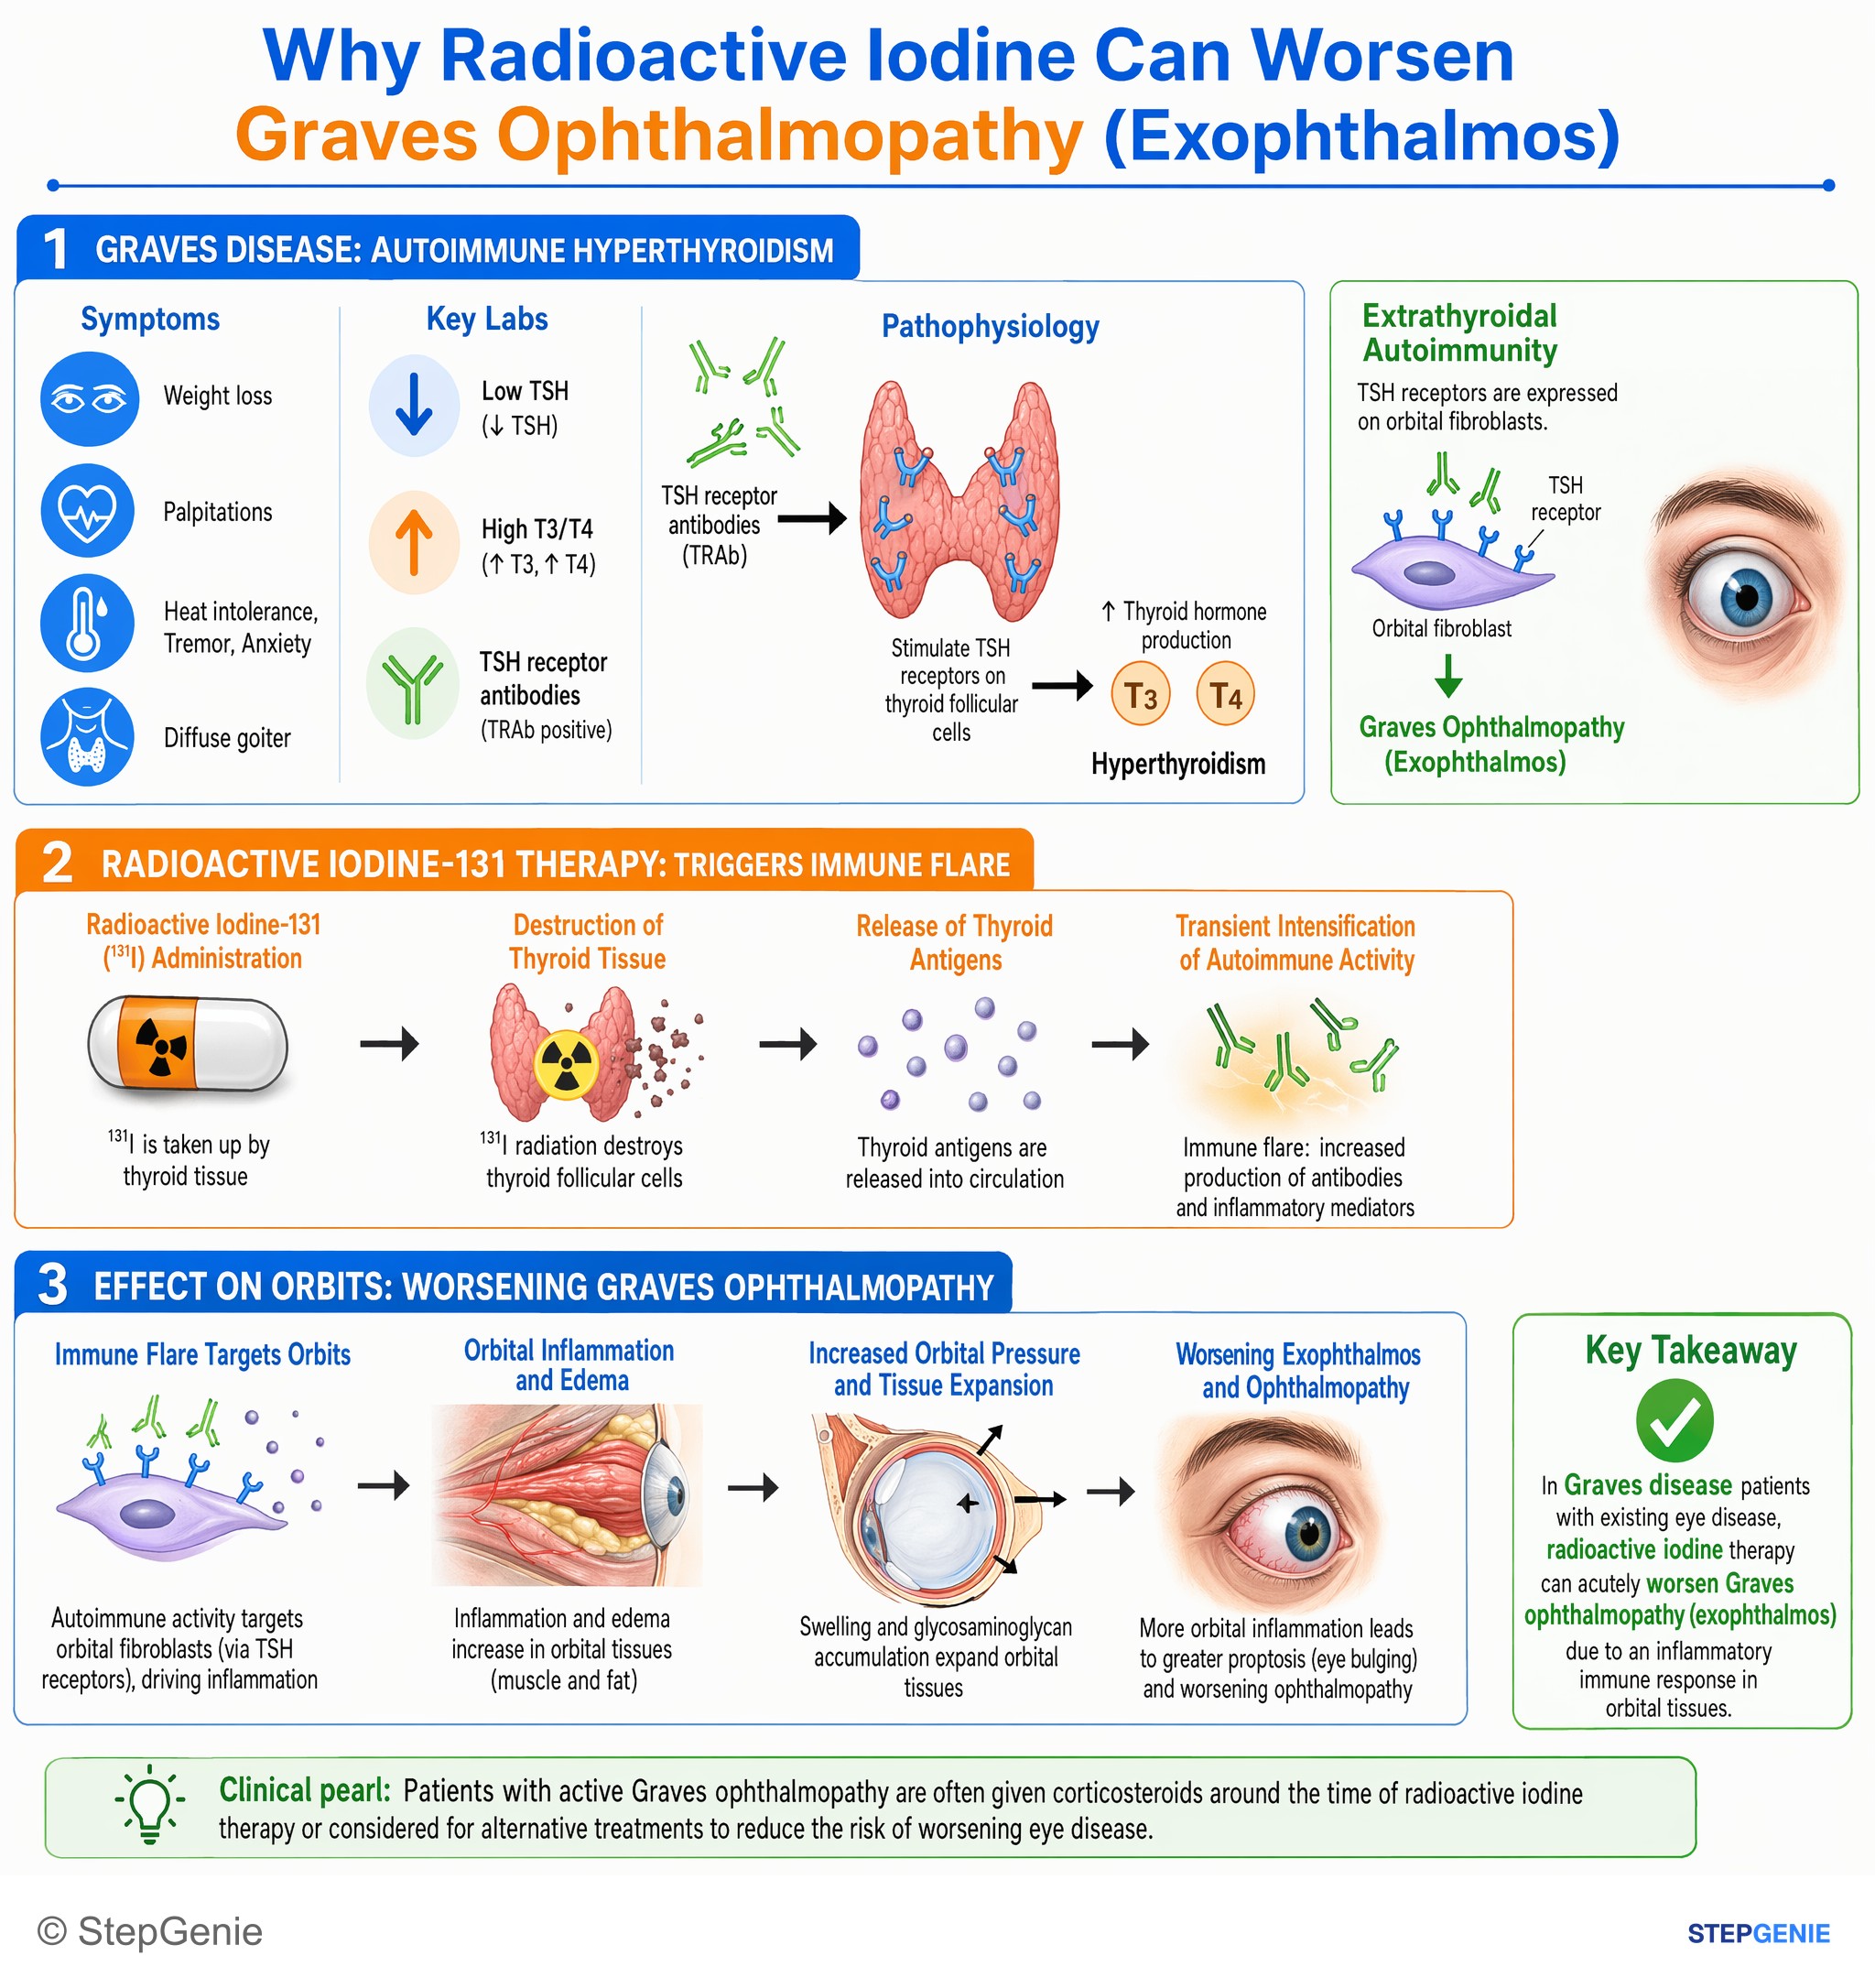
Graves disease treated with radioactive iodine can acutely worsen Graves ophthalmopathy (exophthalmos) due to inflammatory response in…
USMLE Step 1Frequently Asked Questions
Why does Graves disease cause low TSH and high free T4?
Graves disease causes low TSH and high free T4 because IgG autoantibodies stimulate the TSH receptor on thyroid follicular cells, driving excess thyroid hormone synthesis and gland growth. The thyroid overproduces hormone, so the pituitary appropriately suppresses TSH. This pattern indicates primary hyperthyroidism, especially when paired with symptoms like heat intolerance, weight loss, tremor, palpitations, and a diffuse goiter.
What clinical clue most strongly points to Graves disease instead of another cause of hyperthyroidism?
Ophthalmopathy, especially proptosis, is the strongest clue pointing to Graves disease. In Graves, eye findings result from fibroblast activation and glycosaminoglycan deposition in the orbit, and they commonly appear with a diffuse goiter. That combination helps separate Graves from look-alikes such as thyroiditis or Hashimoto thyroiditis, which may affect thyroid function but do not cause ophthalmopathy.
How do you tell Graves disease from subacute de Quervain thyroiditis on an exam question?
Graves disease is distinguished from subacute de Quervain thyroiditis by the thyroid exam, eye findings, and radioactive iodine uptake. Graves typically presents with a diffusely enlarged, nontender thyroid, ophthalmopathy, and high diffuse uptake because the gland is actively synthesizing hormone. De Quervain thyroiditis causes a painful, tender thyroid, often after a viral illness, with low uptake because it releases preformed hormone rather than making new hormone.
How do you differentiate Graves disease from a TSH-secreting pituitary adenoma?
The key difference is the TSH level. Graves disease causes primary hyperthyroidism, so free T4 is high and TSH is low because the pituitary is being suppressed. A TSH-secreting pituitary adenoma causes secondary hyperthyroidism, so TSH is inappropriately normal or high despite elevated free T4. Pituitary adenomas may also cause mass effects such as headaches or visual field defects.
What is the first-line treatment for Graves disease, and when is PTU used instead?
Methimazole is the first-line medication to decrease thyroid hormone synthesis in Graves disease, and a beta-blocker such as propranolol is used for symptom control. Propranolol also decreases peripheral T4-to-T3 conversion at higher doses. PTU is used instead in the first trimester of pregnancy or in thyroid storm. Definitive treatment can be radioiodine ablation or surgery.