Posterior pituitary hormones are some of the most testable “small but deadly” endocrine facts on Step 1: just two hormones (ADH and oxytocin), but they connect neuroanatomy, renal physiology, obstetrics, pharmacology, and a handful of classic pathology vignettes. If you can quickly map where they’re made, how they’re released, what receptors they hit, and what happens when they’re too low or too high, you’ll pick up a lot of easy points.
Posterior Pituitary (Neurohypophysis): The Big Picture
What it is (definition)
The posterior pituitary is neural tissue that stores and releases hormones made in the hypothalamus. It does not synthesize its own hormones.
High-yield anatomy/function
- Synthesized in hypothalamus:
- ADH (vasopressin): primarily supraoptic nucleus
- Oxytocin: primarily paraventricular nucleus
- Transported down axons via the hypothalamo-hypophyseal tract
- Stored in axon terminals and released into blood from posterior pituitary
- Histology clue: Herring bodies = neurosecretory granules in posterior pituitary
First Aid cross-reference: Endocrine → Hypothalamus & Pituitary (posterior pituitary; ADH/oxytocin), and Renal → ADH physiology; Repro → lactation/uterine contraction.
Posterior Pituitary Hormones at a Glance (Table)
| Hormone | Made in | Released from | Key stimuli | Main receptors | Core actions | Classic Step associations |
|---|---|---|---|---|---|---|
| ADH (vasopressin) | Supraoptic (hypothalamus) | Posterior pituitary | ↑ plasma osmolality, ↓ blood volume/pressure, nausea, pain; inhibited by ethanol | V2 (Gs) kidney; V1 (Gq) vascular smooth muscle | ↑ H2O reabsorption (AQP2 insertion), vasoconstriction | DI (central/nephrogenic), SIADH, lithium toxicity, small cell lung carcinoma |
| Oxytocin | Paraventricular (hypothalamus) | Posterior pituitary | Nipple stimulation, cervical stretch | Gq | Milk ejection + uterine contraction | Lactation physiology, postpartum hemorrhage treatment, induction/augmentation of labor |
ADH (Vasopressin): Physiology That Shows Up Everywhere
Receptors and signaling (very testable)
- V2 receptors (kidney collecting duct principal cells): Gs → ↑ cAMP
- Inserts aquaporin-2 into apical membrane → ↑ free water reabsorption
- V1 receptors (vascular smooth muscle): Gq → ↑ IP3/DAG → ↑ Ca²⁺
- Vasoconstriction (helps maintain perfusion in shock)
Renal physiology pearl
- ADH primarily regulates free water, not sodium directly.
- Effect on labs: ADH tends to lower serum osmolality and concentrate urine.
Regulation (how boards phrase it)
ADH release increases with:
- ↑ plasma osmolality (osmoreceptors in hypothalamus)
- ↓ effective arterial blood volume / BP (baroreceptors)
- Nausea (potent stimulus), pain, stress
ADH release decreases with:
- Ethanol (classic “beer diuresis” vignette)
- Water loading, low osmolality
Disorders of ADH
1) Diabetes Insipidus (DI)
Definition
Failure to concentrate urine due to low ADH (central DI) or renal resistance to ADH (nephrogenic DI).
Pathophysiology and causes
Central DI (↓ ADH production/release)
- Idiopathic, autoimmune
- Neurosurgery, head trauma
- Tumors affecting hypothalamus/posterior pituitary (e.g., craniopharyngioma regionally—more classically anterior pituitary dysfunction, but can affect stalk/posterior function)
- Infiltrative disease (sarcoidosis, Langerhans cell histiocytosis)
Nephrogenic DI (ADH present but kidney unresponsive)
- Lithium toxicity (most classic USMLE association)
- Demeclocycline
- Hypercalcemia, hypokalemia
- Congenital mutations (V2 receptor, AQP2)
First Aid cross-reference: Pharmacology (lithium; demeclocycline), Renal (collecting duct physiology), Endocrine (DI).
Clinical presentation
- Polyuria (often >3 L/day), polydipsia
- Nocturia
- Signs of dehydration if water access limited
- Labs (typical):
- ↑ serum osmolality
- ↑ serum sodium (if water intake doesn’t keep up)
- Low urine osmolality (dilute urine)
Diagnosis (high-yield testing algorithm)
Water deprivation test + desmopressin (DDAVP) challenge:
| Condition | After water deprivation | After desmopressin |
|---|---|---|
| Central DI | Urine stays dilute | Urine osmolality increases (responds) |
| Nephrogenic DI | Urine stays dilute | Little/no change (no response) |
| Primary polydipsia | Urine concentrates with deprivation | Minimal added effect |
Tip: If the stem mentions psychiatric history + compulsive water drinking → think primary polydipsia.
Treatment
- Central DI: Desmopressin (DDAVP)
- Selective V2 agonist → fewer V1 vasoconstrictive effects
- Nephrogenic DI:
- Stop offending drug (e.g., lithium) if possible
- Thiazides (paradoxical ↓ polyuria via mild volume depletion → ↑ proximal reabsorption)
- Amiloride for lithium-induced DI (blocks lithium entry via ENaC)
- NSAIDs can reduce urine output (↓ prostaglandins that antagonize ADH)
Classic adverse effect to know
- Over-treatment with desmopressin → hyponatremia.
2) SIADH (Syndrome of Inappropriate ADH)
Definition
Excess ADH → water retention → euvolemic hyponatremia with inappropriately concentrated urine.
Pathophysiology (Step framing)
- Too much ADH → too much free water reabsorbed → dilutional hyponatremia
- Body responds by:
- ↓ aldosterone and ↑ ANP → natriuresis (helps maintain euvolemia)
- Net result: not typically edema-heavy like CHF; classically euvolemic
Causes (must-know list)
- Small cell carcinoma of the lung (ectopic ADH production)
- CNS disturbance: stroke, hemorrhage, infection, trauma
- Pulmonary disease: pneumonia, TB
- Drugs: SSRIs, carbamazepine, cyclophosphamide, chlorpropamide, MDMA
First Aid cross-reference: Pulmonary/Onc (small cell lung carcinoma), Pharm (SSRIs, carbamazepine), Endocrine (SIADH), Renal (free water handling).
Clinical presentation
Symptoms are driven by hyponatremia:
- Mild/moderate: nausea, headache, confusion
- Severe/acute: seizures, coma
Diagnostic pattern (high yield)
Typical labs:
- ↓ serum Na⁺
- ↓ serum osmolality
- Inappropriately ↑ urine osmolality
- ↑ urine sodium (often due to natriuresis)
Differentials to distinguish
- CHF/cirrhosis/nephrotic syndrome: hyponatremia but typically hypervolemic with edema, low effective arterial volume.
- Adrenal insufficiency can also cause hyponatremia—look for hypotension, hyperkalemia, low cortisol.
Treatment
Depends on severity and acuity:
- Fluid restriction (foundation)
- Oral salt/IV saline depending on scenario
- Hypertonic (3%) saline for severe symptoms (e.g., seizures)
- Demeclocycline (induces nephrogenic DI) for chronic SIADH (less used clinically now but still board-relevant)
- Vaptans (ADH receptor antagonists): conivaptan, tolvaptan
Critical safety point: correcting sodium Avoid osmotic demyelination syndrome (central pontine myelinolysis) from overly rapid correction. A commonly tested rule: do not increase Na⁺ by more than about 8–10 mEq/L in 24 hours in most cases (institutions vary slightly).
Oxytocin: The “Positive Feedback” Posterior Pituitary Hormone
Core physiology
Oxytocin is released in response to:
- Nipple stimulation → milk ejection (“let-down” reflex)
- Cervical/uterine stretch → stronger uterine contractions
It works via Gq signaling, increasing intracellular calcium → smooth muscle contraction.
High-yield distinction: prolactin vs oxytocin
| Function | Hormone | Source | Key action |
|---|---|---|---|
| Milk production | Prolactin | Anterior pituitary | Stimulates milk synthesis |
| Milk ejection | Oxytocin | Posterior pituitary (made in hypothalamus) | Contracts myoepithelial cells → milk let-down |
Boards love to ask: postpartum patient can produce milk but can’t eject → think oxytocin problem (often stress/pain inhibiting let-down).
Clinical use (pharm tie-in)
- Oxytocin can be used for:
- Induction/augmentation of labor
- Treatment of postpartum hemorrhage due to uterine atony (contracts uterus)
Adverse effects to recognize
- Uterine hyperstimulation → fetal distress
- Water intoxication/hyponatremia can occur rarely (oxytocin has mild ADH-like activity at high doses)
First Aid cross-reference: Repro/OB pharm (oxytocin; uterine atony), Endocrine (posterior pituitary).
Integrating Posterior Pituitary with Hypothalamic-Pituitary Concepts
Posterior pituitary is “just release”
A classic trap is mixing up anterior vs posterior:
- Anterior pituitary: glandular tissue; regulated by hypothalamic releasing hormones through portal circulation
- Posterior pituitary: neuronal axons; hormones synthesized in hypothalamus, transported down axons, stored/released
Lesions and clinical reasoning
- Pituitary adenomas classically affect the anterior pituitary (prolactin, GH, ACTH, etc.)
- Posterior pituitary dysfunction more often comes from:
- Trauma/surgery
- Stalk damage
- Infiltrative disease
- Ectopic hormone production (SIADH from small cell lung cancer)
Rapid-Fire High-Yield Associations (Exam-Day Bullets)
ADH
- Ethanol inhibits ADH → diuresis
- V2 = 2 kidneys (Gs) → aquaporin-2 insertion
- Lithium → nephrogenic DI
- Desmopressin treats central DI (and some bleeding disorders like vWD; know this as a bonus cross-link)
- SIADH:
- Small cell lung carcinoma
- Euvolemic hyponatremia
- Treat with fluid restriction, vaptans, sometimes demeclocycline
- Overcorrect hyponatremia → osmotic demyelination
Oxytocin
- Milk ejection, not production
- Uterine contraction; used for induction and postpartum hemorrhage
- Positive feedback loops (suckling/stretch → more oxytocin)
Mini Practice Vignettes (How It’s Tested)
-
Psych patient drinking water all day, low-normal sodium, urine becomes concentrated after water deprivation
→ Primary polydipsia -
Post-op neurosurgery patient with polyuria, high serum osmolality, urine remains dilute but concentrates after DDAVP
→ Central DI -
Patient on lithium with polyuria; DDAVP does not improve urine concentration
→ Nephrogenic DI -
Smoker with lung mass, confusion, Na⁺ 118, low serum osmolality, high urine osmolality
→ SIADH from small cell carcinoma -
Postpartum patient: milk present but “won’t let down,” stressed and in pain
→ impaired oxytocin-mediated ejection (supportive measures; reduce stress/pain)
Key Takeaway Map (One-Liner Memory Hooks)
- Posterior pituitary stores/releases; hypothalamus makes.
- ADH: V2 (Gs) collecting duct water; too little = DI, too much = SIADH.
- Oxytocin: let-down + labor via Gq; think postpartum hemorrhage treatment.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
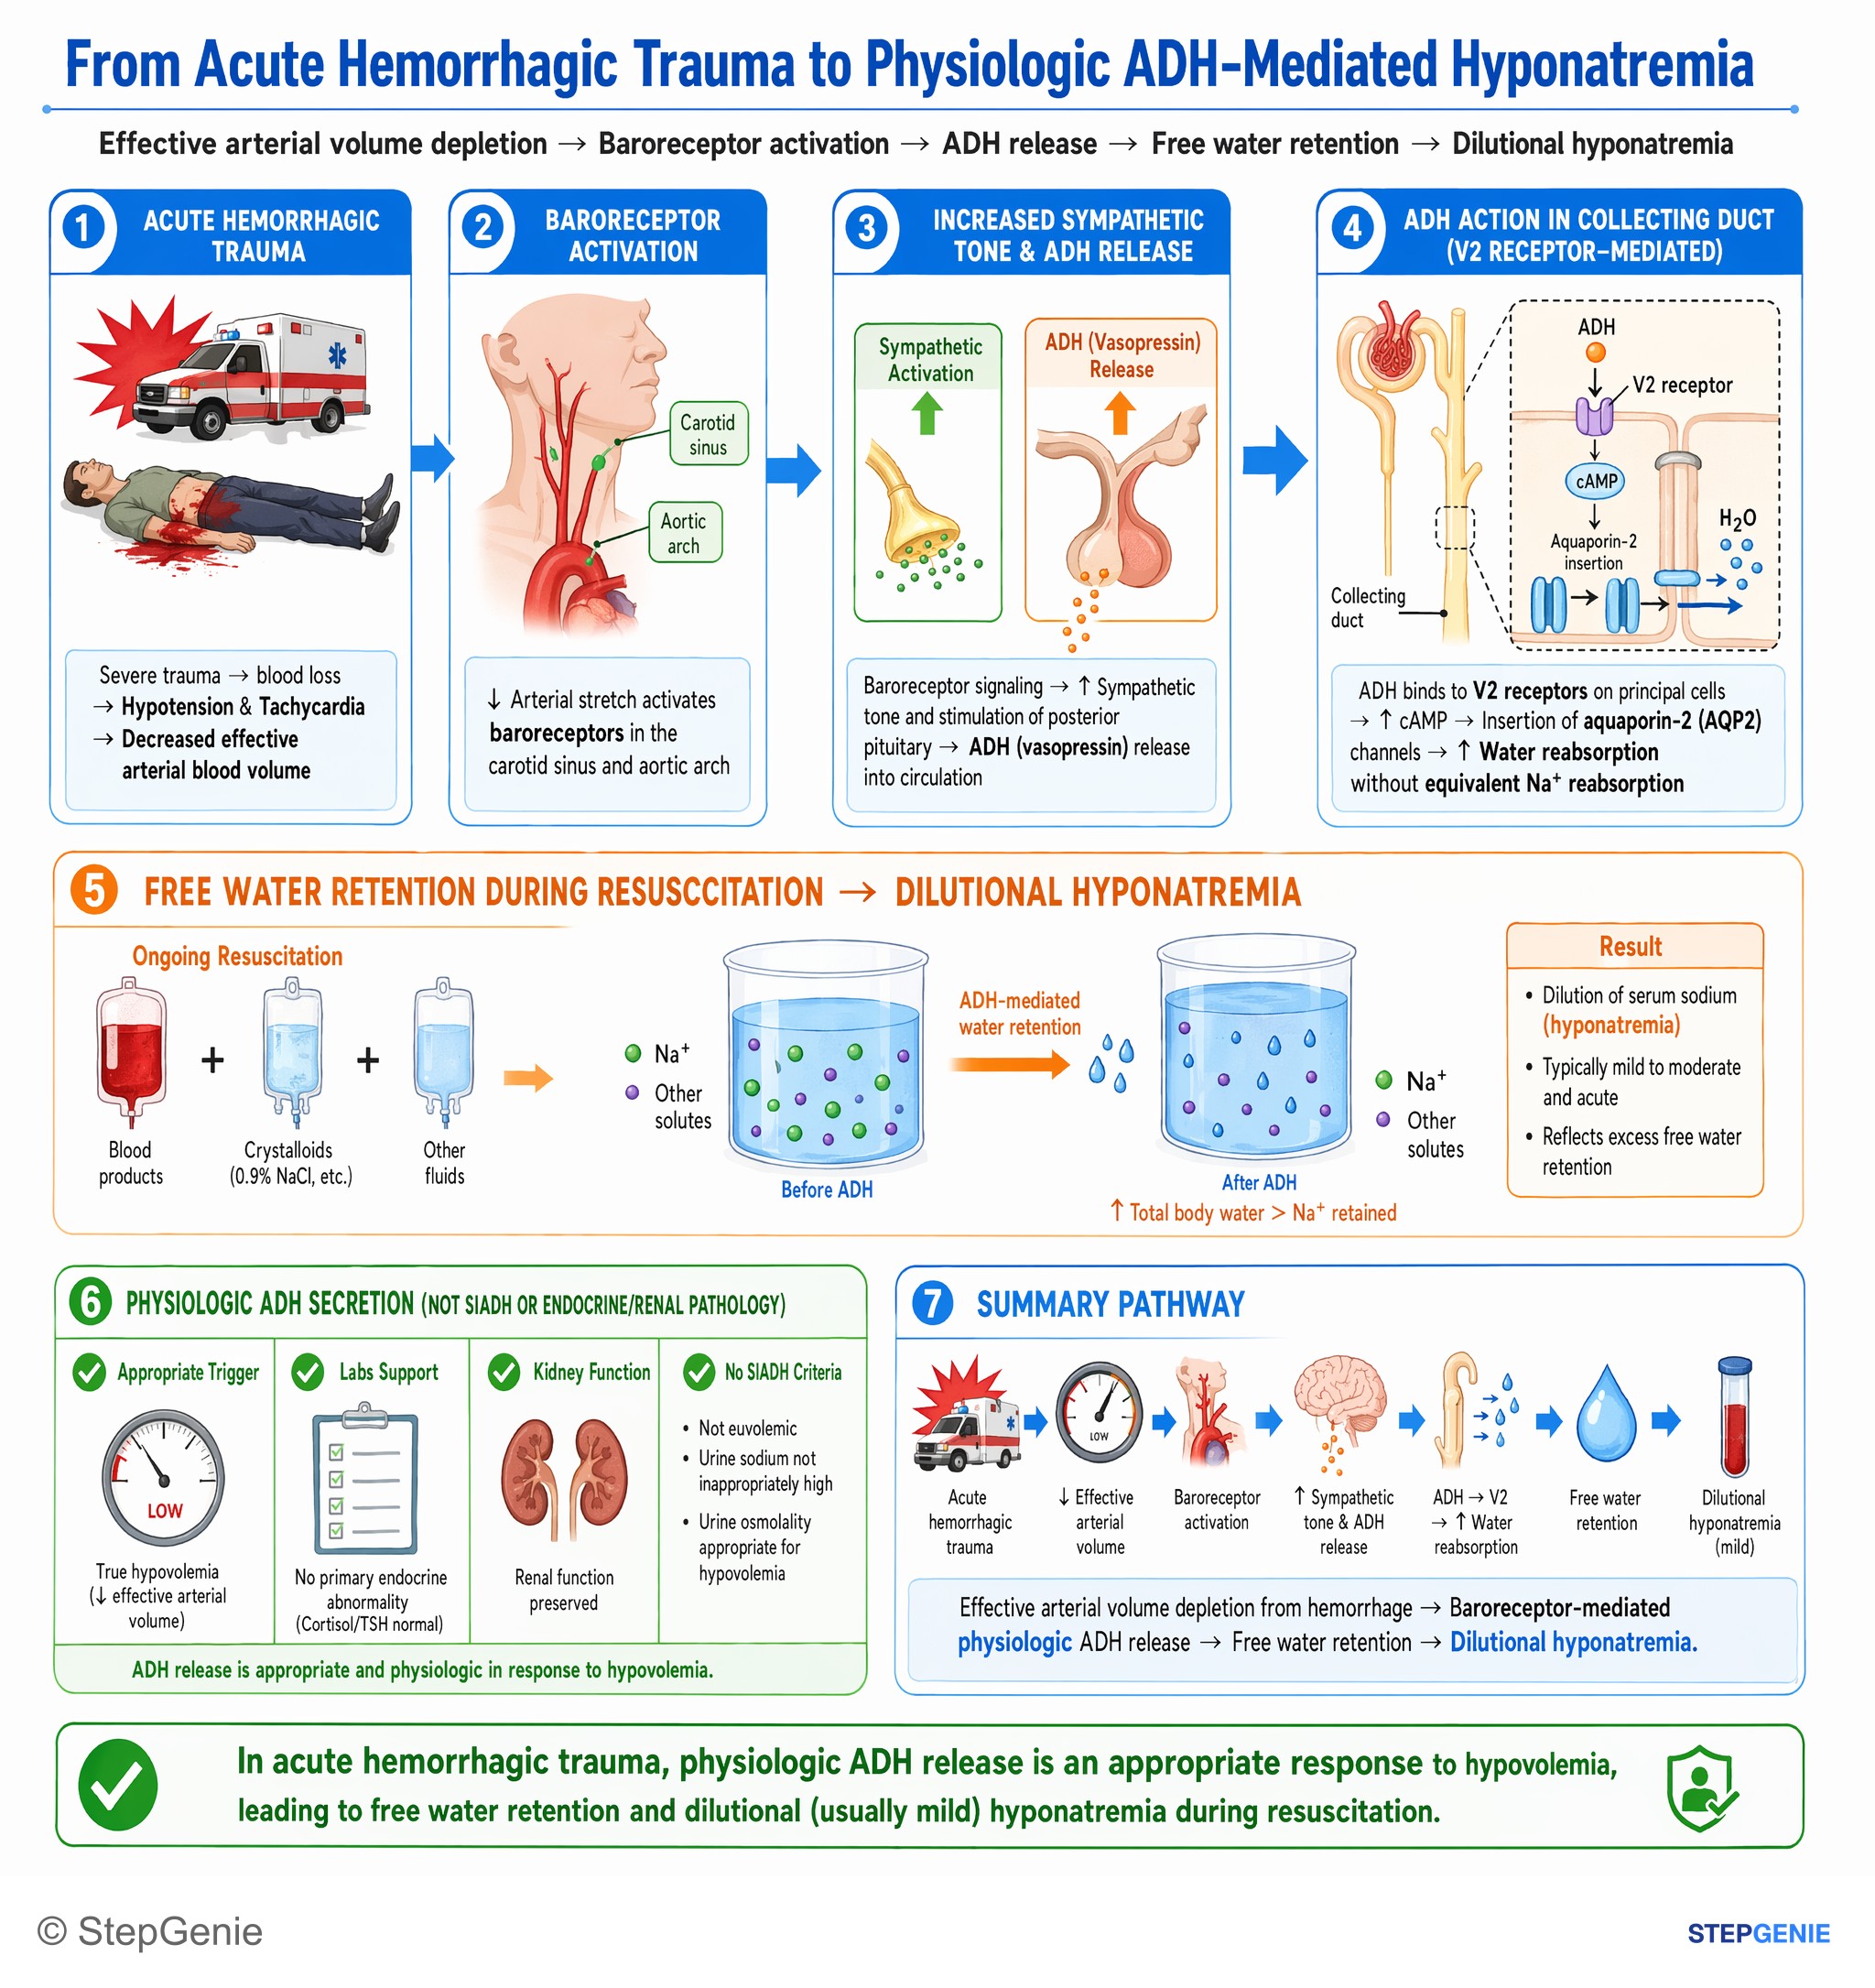
Acute hemorrhagic trauma → effective arterial volume depletion → baroreceptor-mediated physiologic ADH release → free water retention →…
USMLE Step 1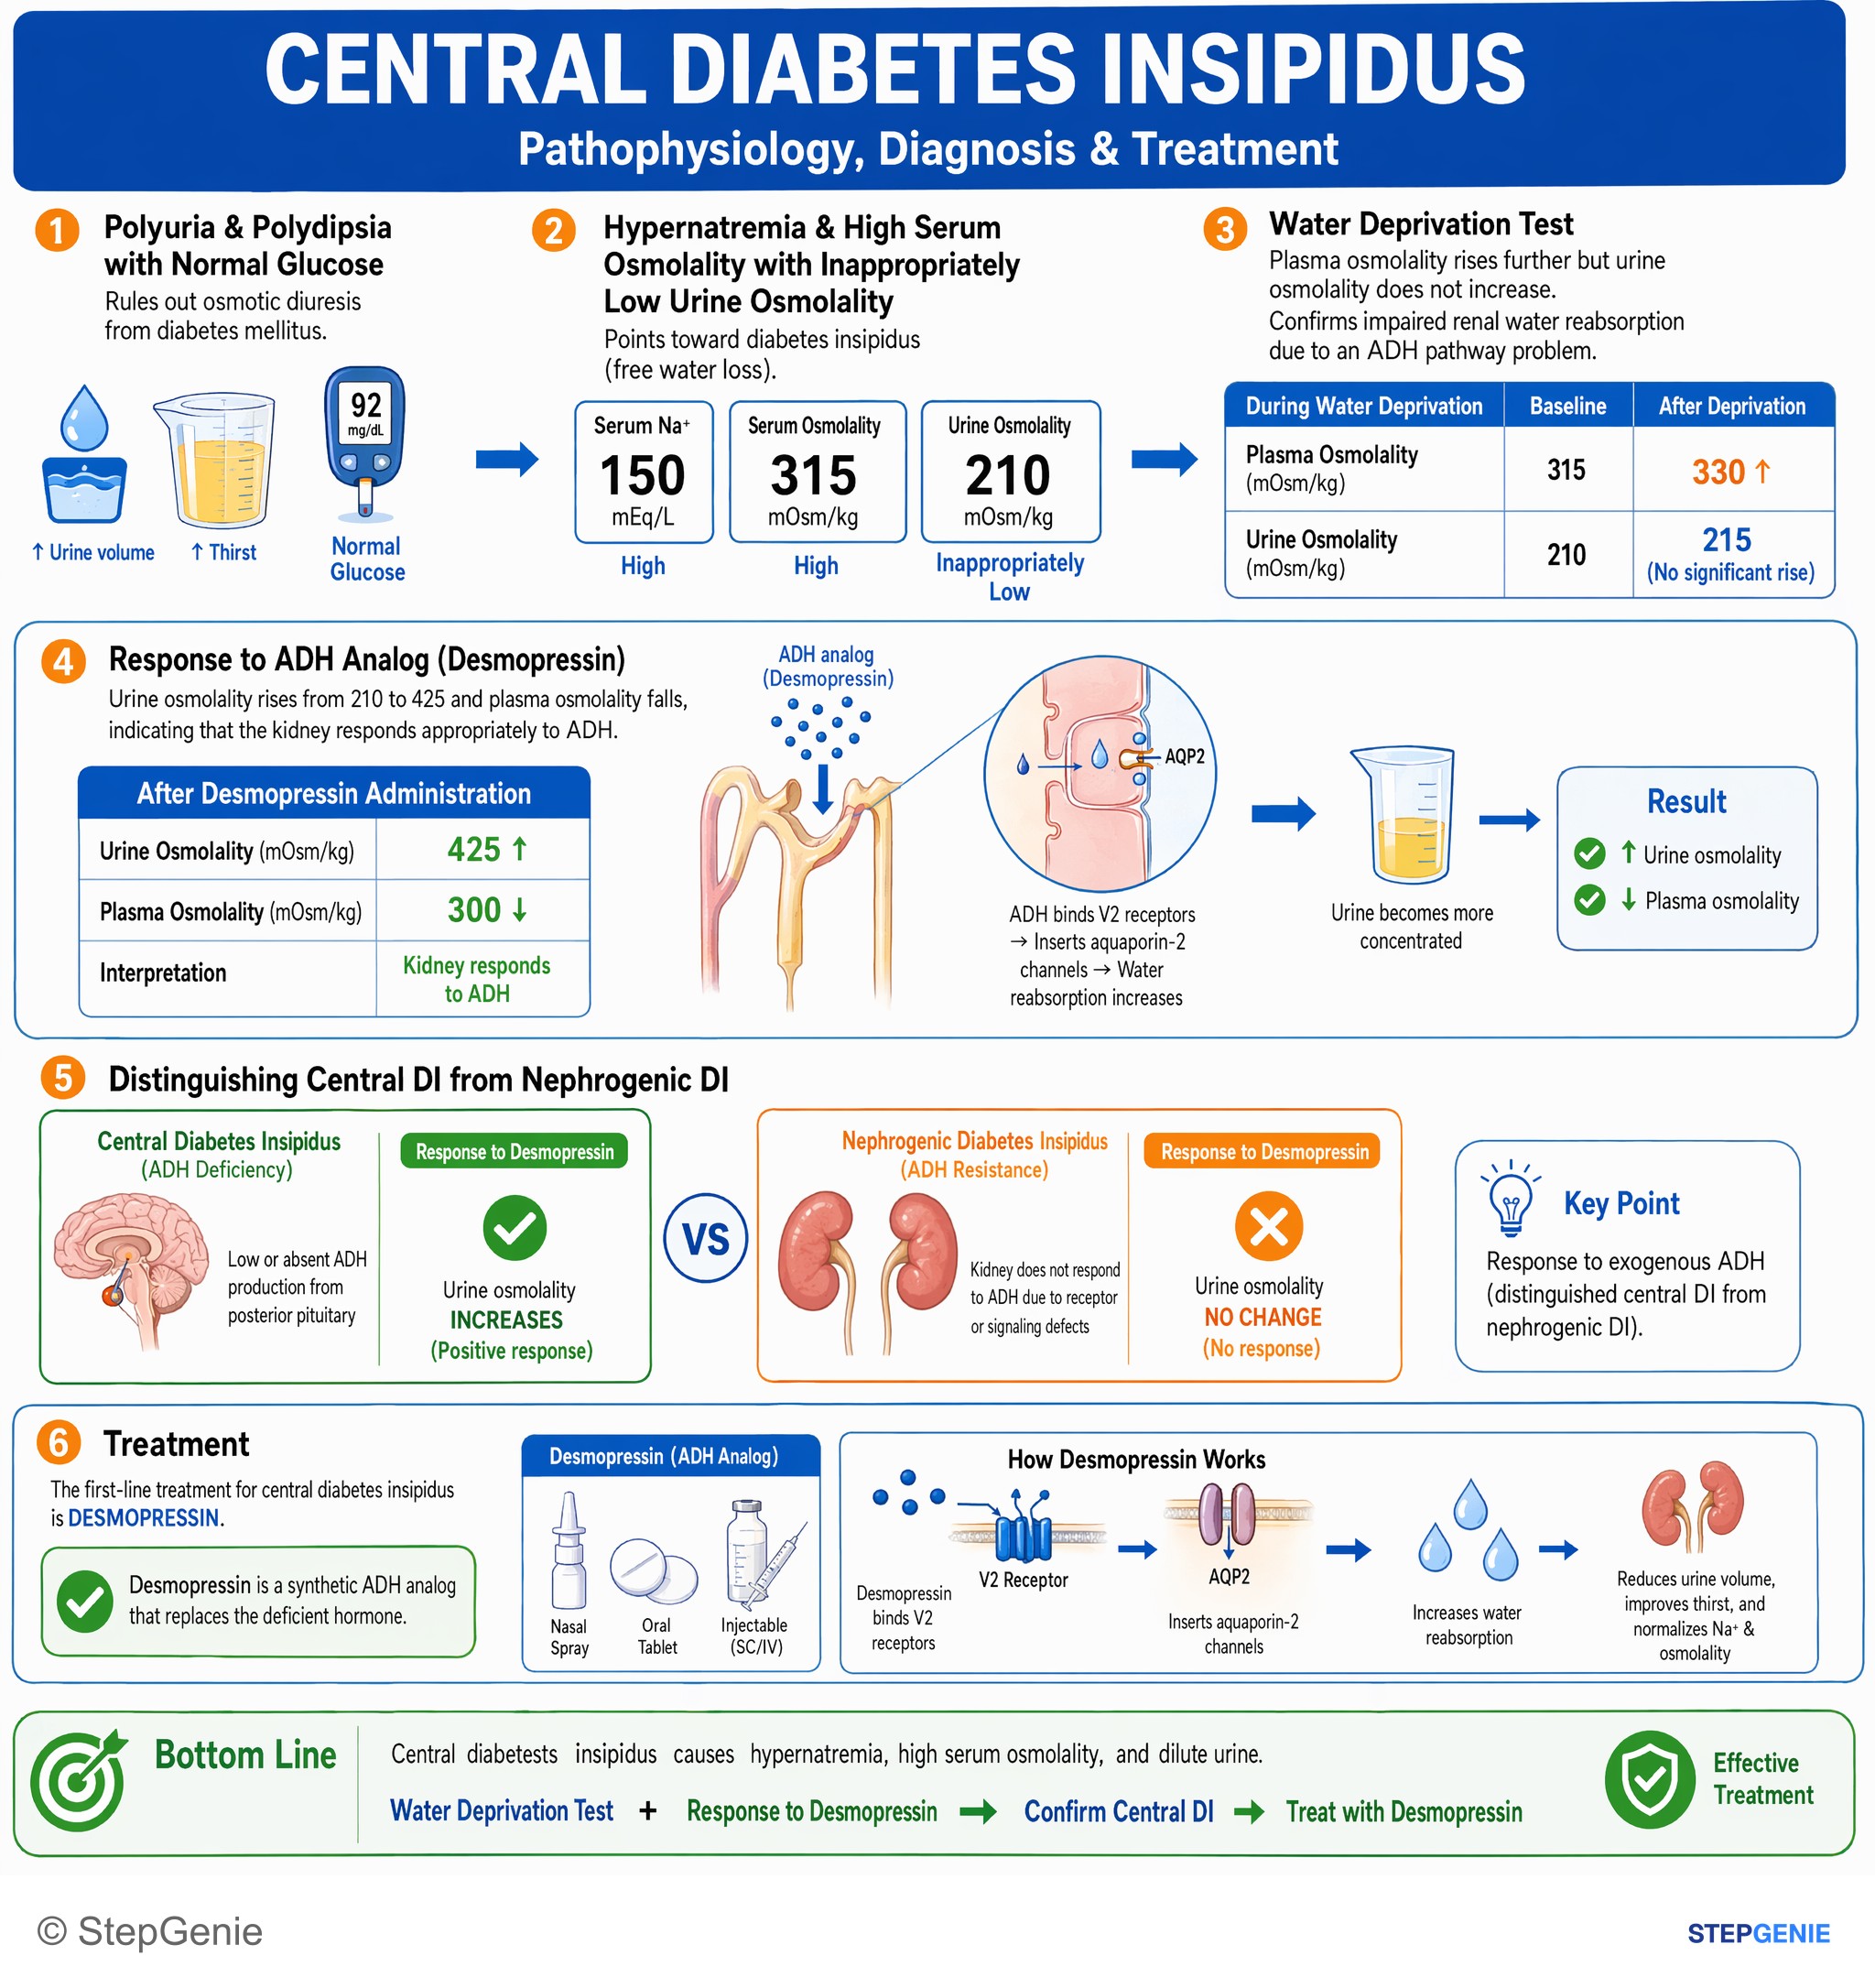
Central diabetes insipidus causes hypernatremia, high serum osmolality, dilute urine; water deprivation + response to ADH analog → treat…
USMLE Step 2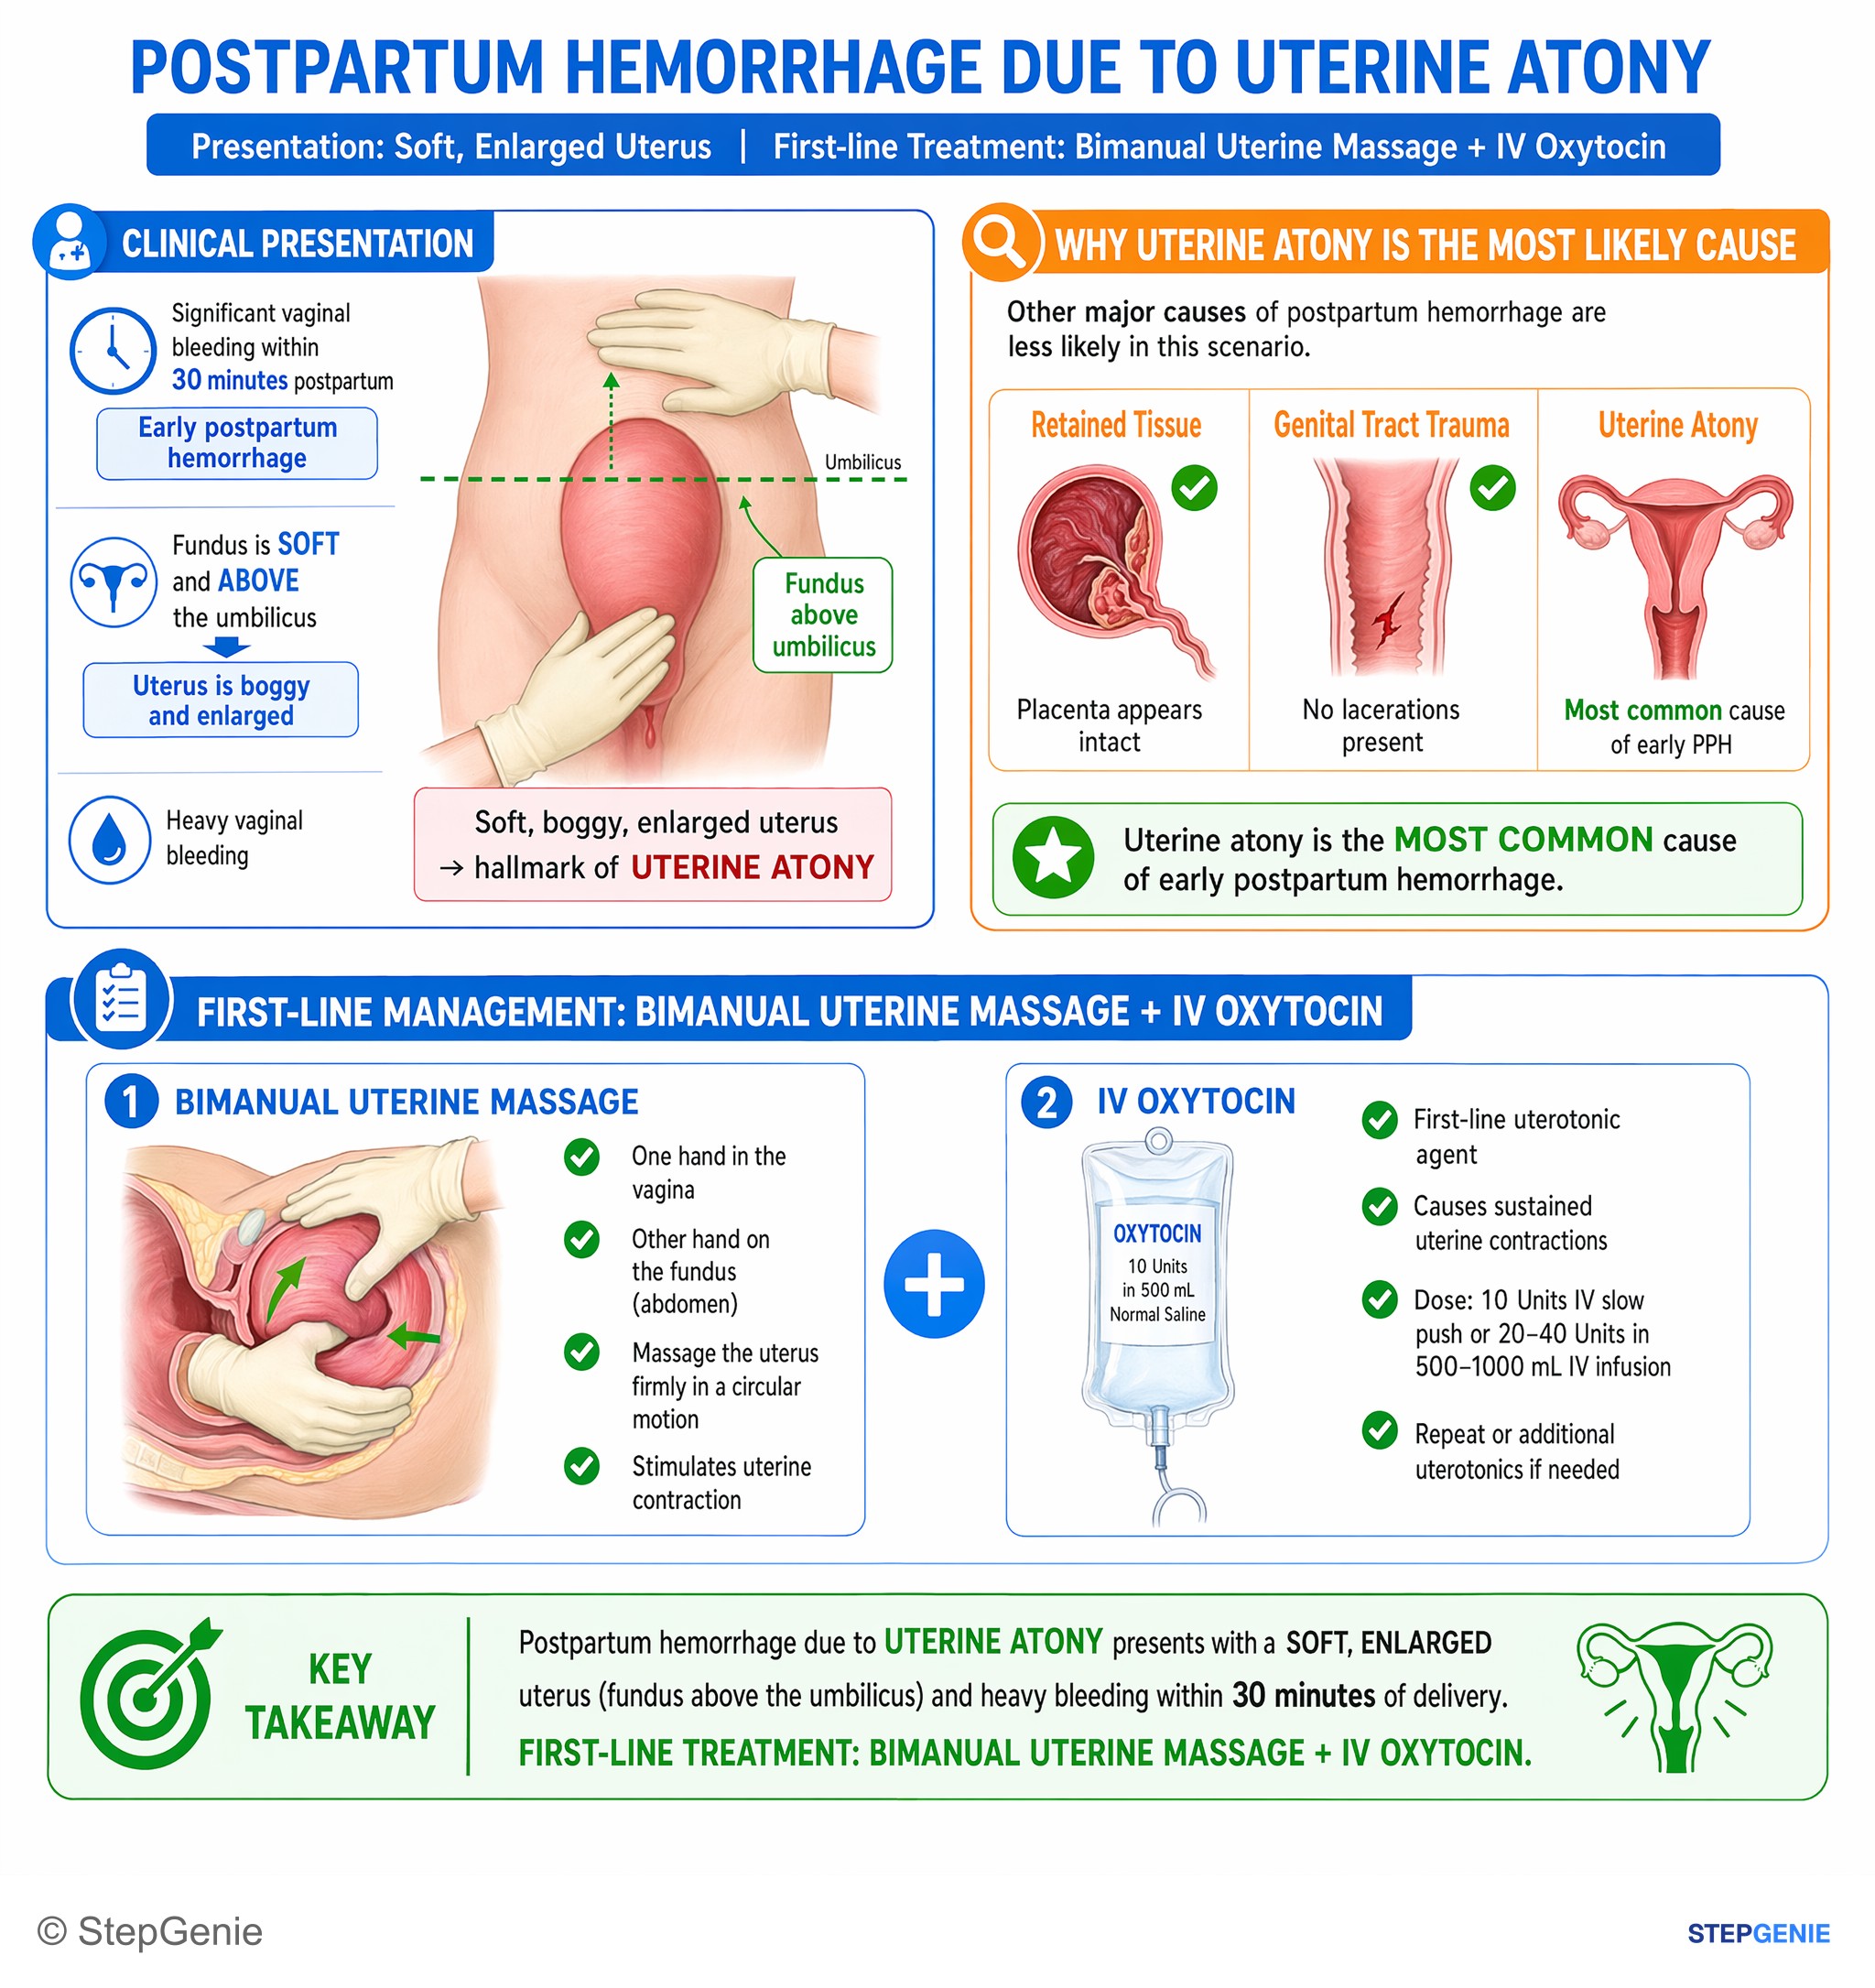
Postpartum hemorrhage due to uterine atony presents with a soft, enlarged uterus; first-line treatment is bimanual uterine massage plus IV…
USMLE Step 2Frequently Asked Questions
Where are ADH and oxytocin made, and what does the posterior pituitary actually do?
ADH and oxytocin are made in the hypothalamus, not in the posterior pituitary. ADH is produced primarily in the supraoptic nucleus, and oxytocin primarily in the paraventricular nucleus. They travel down the hypothalamo-hypophyseal tract, are stored in axon terminals in the posterior pituitary, and are then released into the bloodstream from this neural tissue.
How does ADH work at V1 versus V2 receptors?
ADH acts at V2 receptors in the kidney to increase free water reabsorption, and at V1 receptors in vascular smooth muscle to cause vasoconstriction. V2 signaling uses Gs and increased cAMP in collecting duct principal cells, leading to aquaporin-2 insertion. V1 signaling uses Gq with increased IP3/DAG and calcium, which helps constrict blood vessels and maintain perfusion in shock.
What increases or decreases ADH release on Step 1 questions?
ADH release increases with higher plasma osmolality, lower effective arterial blood volume or blood pressure, and also with nausea, pain, and stress. It decreases with ethanol, water loading, and low osmolality. A classic test vignette is beer diuresis, where ethanol suppresses ADH and leads to increased free water loss in dilute urine.
How do you tell central diabetes insipidus from nephrogenic diabetes insipidus on a water deprivation test?
Both central and nephrogenic diabetes insipidus show persistently dilute urine after water deprivation, but they differ after desmopressin. In central DI, urine osmolality increases because the kidney can respond once ADH activity is replaced. In nephrogenic DI, there is little or no change because the kidney is resistant to ADH. Primary polydipsia instead concentrates urine with water deprivation.
What is the first-line treatment for central DI versus lithium-induced nephrogenic DI?
Central diabetes insipidus is treated with desmopressin, a selective V2 agonist. Lithium-induced nephrogenic DI is treated with amiloride, which blocks lithium entry through ENaC, and stopping lithium if possible. Nephrogenic DI more broadly can also be treated with thiazides, which paradoxically reduce polyuria through mild volume depletion and increased proximal reabsorption.