A pituitary adenoma (now formally a pituitary neuroendocrine tumor, or PitNET) is a usually benign anterior pituitary tumor that causes three problems: hormone excess, mass effect (headache, bitemporal hemianopia) and hypopituitarism. Prolactinoma is the most common secreting type (galactorrhea and amenorrhea in women, low libido and erectile dysfunction in men), and cabergoline comes first even when a macroadenoma presses on the optic chiasm. A GH-secreting adenoma causes acromegaly (gigantism before the growth plates close): screen with IGF-1, confirm if needed by GH that fails to suppress after oral glucose, and treat with transsphenoidal surgery, then somatostatin analogs or pegvisomant. ACTH-secreting tumors cause Cushing disease; nonfunctioning tumors present with mass effect and mildly high prolactin from stalk compression.
Three ways a pituitary adenoma shows up
| Problem | Mechanism | Classic clues |
|---|---|---|
| Hormone excess | Tumor cells secrete prolactin, GH, ACTH or, rarely, TSH | Galactorrhea, acromegaly, Cushing features, hyperthyroidism with a non-suppressed TSH |
| Mass effect | Upward growth hits the optic chiasm; lateral growth enters the cavernous sinus | Headache; bitemporal hemianopia; cranial nerve III, IV or VI palsy |
| Hypopituitarism | Compression of normal gland or stalk | Usually GH lost first, then LH and FSH, then TSH and ACTH (Merck) |
Size matters: a microadenoma is under 10 mm and a macroadenoma is 10 mm or more. Macroadenomas cause the mass effects.
Pituitary adenoma types at a glance
| Tumor | Hormone | Classic picture | Key test | First-line treatment |
|---|---|---|---|---|
| Prolactinoma (lactotroph) | Prolactin | Women: galactorrhea, amenorrhea, infertility. Men: low libido, erectile dysfunction, later headache and vision loss | Serum prolactin (over 200 ng/mL makes prolactinoma likely), then MRI | Cabergoline |
| Somatotroph | GH → IGF-1 | Acromegaly (adults) or gigantism (children) | IGF-1; oral glucose suppression test if equivocal | Transsphenoidal surgery |
| Corticotroph | ACTH → cortisol | Cushing disease: central obesity, striae, proximal weakness, hypertension, hyperglycemia | Cortisol excess confirmed, then ACTH normal or high, MRI, often petrosal sinus sampling | Transsphenoidal surgery |
| Thyrotroph (rare) | TSH → T4 | Hyperthyroidism with a TSH that is normal or high instead of suppressed | High free T4 plus detectable TSH; raised alpha subunit | Surgery |
| Nonfunctioning (mostly gonadotroph) | None clinically | Headache, visual loss, hypogonadism or hypopituitarism, mildly high prolactin | MRI plus a full pituitary hormone panel | Surgery if there is mass effect |
Prolactinoma: dopamine is the brake
Physiology. Hypothalamic dopamine travels down the stalk and suppresses prolactin through D2 receptors; TRH, VIP and estrogen stimulate it, and the kidney clears it (Pituitary Society). Excess prolactin inhibits GnRH, so LH and FSH fall and the patient becomes hypogonadal, with long-term bone loss.
Presentation.
- Women: usually microadenomas at diagnosis; galactorrhea, amenorrhea or oligomenorrhea, infertility, low libido, dyspareunia. Prolactin is an early test in the amenorrhea workup flowchart.
- Men: about two-thirds have low libido and erectile dysfunction, but tumors tend to be larger and more aggressive, so headache and visual loss often bring them in (Merck).
- MEN1: pituitary tumors, most often prolactinomas, join parathyroid and pancreatic tumors; compare in the MEN1 vs MEN2 guide.
Rule out the look-alikes before calling it a prolactinoma:
- Pregnancy, nipple stimulation, stress and kidney failure (reduced clearance).
- Drugs: antipsychotics and other D2 blockers (metoclopramide, haloperidol, phenothiazines), methyldopa, verapamil, opioids, some antidepressants. Stopping or switching the drug (for antipsychotics, with psychiatry, for example to aripiprazole) lowers prolactin; a level over 10 times the upper limit of normal on an antipsychotic suggests a prolactinoma (Pituitary Society).
- Primary hypothyroidism: high TRH drives prolactin; check TSH.
- Stalk effect: any sellar mass that blocks dopamine delivery. Prolactin is usually only modestly raised (Merck: usually no more than 3–4 times normal; Pituitary Society: up to 6 times the upper limit of normal).
Lab traps (Pituitary Society 2023).
- Prolactin over 200 ng/mL makes prolactinoma more likely; at 200 ng/mL or less, consider other causes.
- Hook effect: a giant tumor with a normal or slightly high prolactin can be an assay artifact; re-measure after a 1:100 dilution.
- Macroprolactin: big, biologically inactive prolactin, found in 10–25% of people with hyperprolactinemia; check for it when a moderate elevation does not fit the clinical picture.
Treatment.
- Cabergoline is preferred over bromocriptine: longer half-life (once or twice weekly), more effective and better tolerated. Dopamine agonists lower prolactin, restore gonadal function and shrink the tumor, so they are first-line even for macroadenomas compressing the chiasm (Merck).
- An asymptomatic microadenoma can simply be watched; treat for infertility, amenorrhea, bothersome galactorrhea or hypogonadism.
- Surgery is second-line (resistance or intolerance), though the Pituitary Society says expert surgery can be discussed as a first-line option for microadenomas and well-circumscribed macroadenomas. Radiation is a last resort.
- Adverse effects: nausea and dizziness, impulse control disorders (gambling, sexual urges, spending) and cardiac valvulopathy, seen mainly at the much higher doses used in Parkinson disease. The US label contraindicates cabergoline with valve disease, a history of fibrotic disorders or uncontrolled hypertension, and asks for an echocardiogram before starting and every 6–12 months (or as clinically indicated); the Pituitary Society suggests a dose-based schedule instead (every 2–3 years above 2 mg per week, after 5–6 years at lower doses).
- Pregnancy (Pituitary Society 2023): stop the dopamine agonist once pregnancy is confirmed (continuing it is an option for a large macroprolactinoma). About 30% of macroadenomas enlarge (Merck), so check symptoms monthly and visual fields every 3 months; if growth is suspected, get MRI without gadolinium and restart the agonist. Prolactin is not used to track the tumor. Most centers now prefer cabergoline over bromocriptine.
- Stopping: after at least 2 years of low-dose cabergoline with a normal prolactin and no visible tumor, withdrawal is encouraged.
GH-secreting adenoma: acromegaly and gigantism
Physiology. GHRH stimulates and somatostatin inhibits GH. GH makes the liver release IGF-1, which drives growth, and GH itself is anti-insulin (diabetogenic).
Presentation (Merck).
- Open epiphyses → gigantism; closed epiphyses → acromegaly, usually starting at 20–40 years.
- Coarse face, frontal bossing, prognathism with malocclusion, macroglossia, deep voice, bigger rings, gloves and shoes, heavy sweating, arthropathy and entrapment neuropathy such as carpal tunnel syndrome.
- Obstructive sleep apnea in 40–50%; hypertension in up to a third; cardiac disease, including cardiomyopathy, in about a third, doubling cardiac mortality.
- Impaired glucose tolerance in nearly half, overt diabetes in about 10%; colon polyps with a higher GI cancer risk; mild hyperphosphatemia.
Diagnosis.
- IGF-1 first: GH is pulsatile, IGF-1 is stable.
- Oral glucose tolerance test: glucose normally suppresses GH; in acromegaly it does not. The classic cutoff is a GH nadir under 1 µg/L (Merck). The 2024 international consensus says an IGF-1 above 1.3 times the upper limit of normal with typical features confirms the diagnosis; equivocal cases get a repeat IGF-1 on the same assay or the glucose test, for which lower, BMI-based GH cutoffs can be considered.
- MRI of the sella. No pituitary tumor → look for ectopic GHRH from a pancreatic or lung tumor.
- At diagnosis, screen for diabetes, heart disease (echocardiogram) and colon polyps (colonoscopy).
Treatment.
| Option | How it works | Pearls |
|---|---|---|
| Transsphenoidal surgery | Removes the tumor | First-line for most. Cure is judged by normal IGF-1 (and GH) at about 12 weeks; NIDDK cites about 85% for small tumors and 40–50% for large ones |
| Somatostatin analogs (octreotide, lanreotide; pasireotide second-line) | Stimulate somatostatin receptors, mainly SSTR2, to cut GH release | Can shrink the tumor; gallstones, glucose changes, bradycardia, diarrhea |
| Pegvisomant | GH receptor antagonist | Lowers IGF-1, not GH; titrate to IGF-1 because GH rises and GH assays read falsely high; check liver tests; does not shrink the tumor |
| Cabergoline | Dopamine agonist | For mild disease, alone or added to a somatostatin analog |
| Radiation | Slowly destroys residual tumor | Takes years; hypopituitarism is common later |
ACTH-secreting adenoma: Cushing disease
- Pituitary ACTH excess causes about 8 of 10 cases of Cushing syndrome not caused by steroid medicines (NIDDK), almost always from a small tumor.
- Confirm cortisol excess: 24-hour urine free cortisol, late-night salivary cortisol or a 1 mg overnight dexamethasone test (normal morning cortisol under 1.8 µg/dL).
- Localize: ACTH low → adrenal; ACTH normal or high → pituitary or ectopic. Cushing disease usually responds to CRH or desmopressin with an ACTH rise and suppresses with high-dose dexamethasone (a test most centers have dropped). Tumors are often too small to see on MRI; then inferior petrosal sinus sampling decides: a central-to-peripheral ACTH ratio above 3 after desmopressin virtually excludes an ectopic source.
- Treat: transsphenoidal surgery (NIDDK: cure up to 90% with an experienced surgeon), then glucocorticoid replacement for 6–18 months while the suppressed normal corticotrophs recover. Persistent disease: repeat surgery, radiation or drugs (pasireotide, cabergoline, osilodrostat or metyrapone, mifepristone). Bilateral adrenalectomy is the last resort and can lead to Nelson syndrome: enlargement of the corticotroph tumor with hyperpigmentation.
- The full workup is in Cushing syndrome vs Cushing disease.
Nonfunctioning adenomas and TSH-secreting tumors
- Nonfunctioning adenomas are most often gonadotroph tumors that secrete little active hormone, so they present late with mass effect and hypopituitarism. Stalk compression raises prolactin modestly; cabergoline lowers that prolactin but does not shrink the tumor, which is how a trial of therapy separates them from prolactinomas (Merck). Treatment is surgery when there is mass effect.
- TSH-secreting adenomas are rare: high free T4 with a detectable or high TSH and a raised alpha subunit (resistance to thyroid hormone is the look-alike).
Mass effect and pituitary apoplexy
- Bitemporal hemianopia: the chiasm sits above the sella, and its crossing fibers from the nasal retinas carry the temporal fields. Compression from below hits the superior temporal quadrants first (EyeWiki).
- Cavernous sinus invasion: cranial nerve III is most often affected; IV, V and VI can be too.
- Hypopituitarism clues: secondary adrenal insufficiency causes fatigue and hypotension but no hyperpigmentation or hyperkalemia, because renin still drives aldosterone (Merck). Diabetes insipidus is rare with an adenoma; before surgery it points to a stalk or hypothalamic lesion such as craniopharyngioma. After transsphenoidal surgery, sodium and water disturbances are a known complication; see the central vs nephrogenic diabetes insipidus guide.
- Pituitary apoplexy: hemorrhagic infarction, usually of an existing adenoma. Sudden severe headache, stiff neck, visual loss, ophthalmoplegia and drowsiness; acute ACTH loss can cause shock. Give stress-dose glucocorticoids immediately; urgent transsphenoidal decompression is needed for sudden visual loss, ocular palsies or falling consciousness. It mimics subarachnoid hemorrhage (the CSF can be bloody). Postpartum pituitary infarction after hemorrhage is Sheehan syndrome, which classically presents with failure to lactate.
2022 WHO terminology
- Pituitary adenoma → pituitary neuroendocrine tumor (PitNET).
- Tumors are classified by lineage transcription factor: PIT1 (somatotroph, lactotroph, thyrotroph), TPIT (corticotroph) and SF1 (gonadotroph); null cell tumors express none.
- "Pituitary carcinoma" is now metastatic PitNET.
Practice question
Vignette. A 38-year-old man has 6 months of headaches, low libido and erectile dysfunction, and he keeps bumping into door frames. Visual fields show bitemporal hemianopia, worse superiorly. Serum prolactin is 1,850 ng/mL, IGF-1 is normal, and morning cortisol and free T4 are normal. MRI shows a 2.8-cm sellar mass that extends up to the optic chiasm and invades the right cavernous sinus. What is the most appropriate next step in management?
Answer: Cabergoline. A prolactin this high with a macroadenoma is a macroprolactinoma. Dopamine agonists usually shrink these tumors and improve vision, so they are first-line even with chiasmal compression.
Why not the others?
- Transsphenoidal surgery: this invasive tumor is unlikely to be cured surgically, so medical therapy comes first; surgery is for drug resistance or intolerance, rapidly progressive visual loss or apoplexy (expert surgery is first-line only for microadenomas and well-circumscribed macroadenomas).
- Octreotide: a somatostatin analog for acromegaly and neuroendocrine tumors, not prolactinoma.
- Radiation therapy: reserved for tumors that progress despite other treatment; causes hypopituitarism years later.
- Repeat prolactin after 1:100 dilution: looks for the hook effect when a giant tumor has a normal or only slightly high prolactin; this value is already very high.
- Pegvisomant: a GH receptor antagonist for acromegaly; IGF-1 is normal.
Key takeaways
- Adenomas cause hormone excess, mass effect and hypopituitarism; macroadenoma = 10 mm or more.
- Prolactinoma: exclude pregnancy, drugs, hypothyroidism and kidney failure; cabergoline first, even with chiasmal compression.
- Modest prolactin with a big mass = stalk effect; a giant tumor with normal prolactin = think hook effect.
- Acromegaly: IGF-1 to screen, unsuppressed GH after glucose to confirm when needed; surgery, then somatostatin analogs or pegvisomant (follow IGF-1).
- Cushing disease: ACTH normal or high, petrosal sinus sampling when MRI is unclear, transsphenoidal surgery.
- Apoplexy: thunderclap headache plus visual loss or ophthalmoplegia in a patient with an adenoma; steroids first, then urgent decompression if vision, eye movements or consciousness are affected.
Sources
- Prolactinoma — Merck Manual Professional Edition (2025)
- Gigantism and Acromegaly — Merck Manual Professional Edition (2025)
- Generalized Hypopituitarism — Merck Manual Professional Edition (2025)
- Cushing Syndrome — Merck Manual Professional Edition (2026)
- Petersenn S et al. Diagnosis and management of prolactin-secreting pituitary adenomas: a Pituitary Society international Consensus Statement — Nature Reviews Endocrinology (2023)
- Giustina A et al. Consensus on criteria for acromegaly diagnosis and remission — Pituitary (2024)
- Asa SL, Ezzat S, Mete O. Clinical integration and application of the 2022 WHO pituitary tumor classification — Neuro-Oncology Advances (2025)
- Pituitary Adenoma — EyeWiki, American Academy of Ophthalmology
- SOMAVERT (pegvisomant) prescribing information — DailyMed
- Cabergoline tablets prescribing information — DailyMed (2026)
- Acromegaly — National Institute of Diabetes and Digestive and Kidney Diseases (2020)
- Cushing's Syndrome — National Institute of Diabetes and Digestive and Kidney Diseases (2018)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
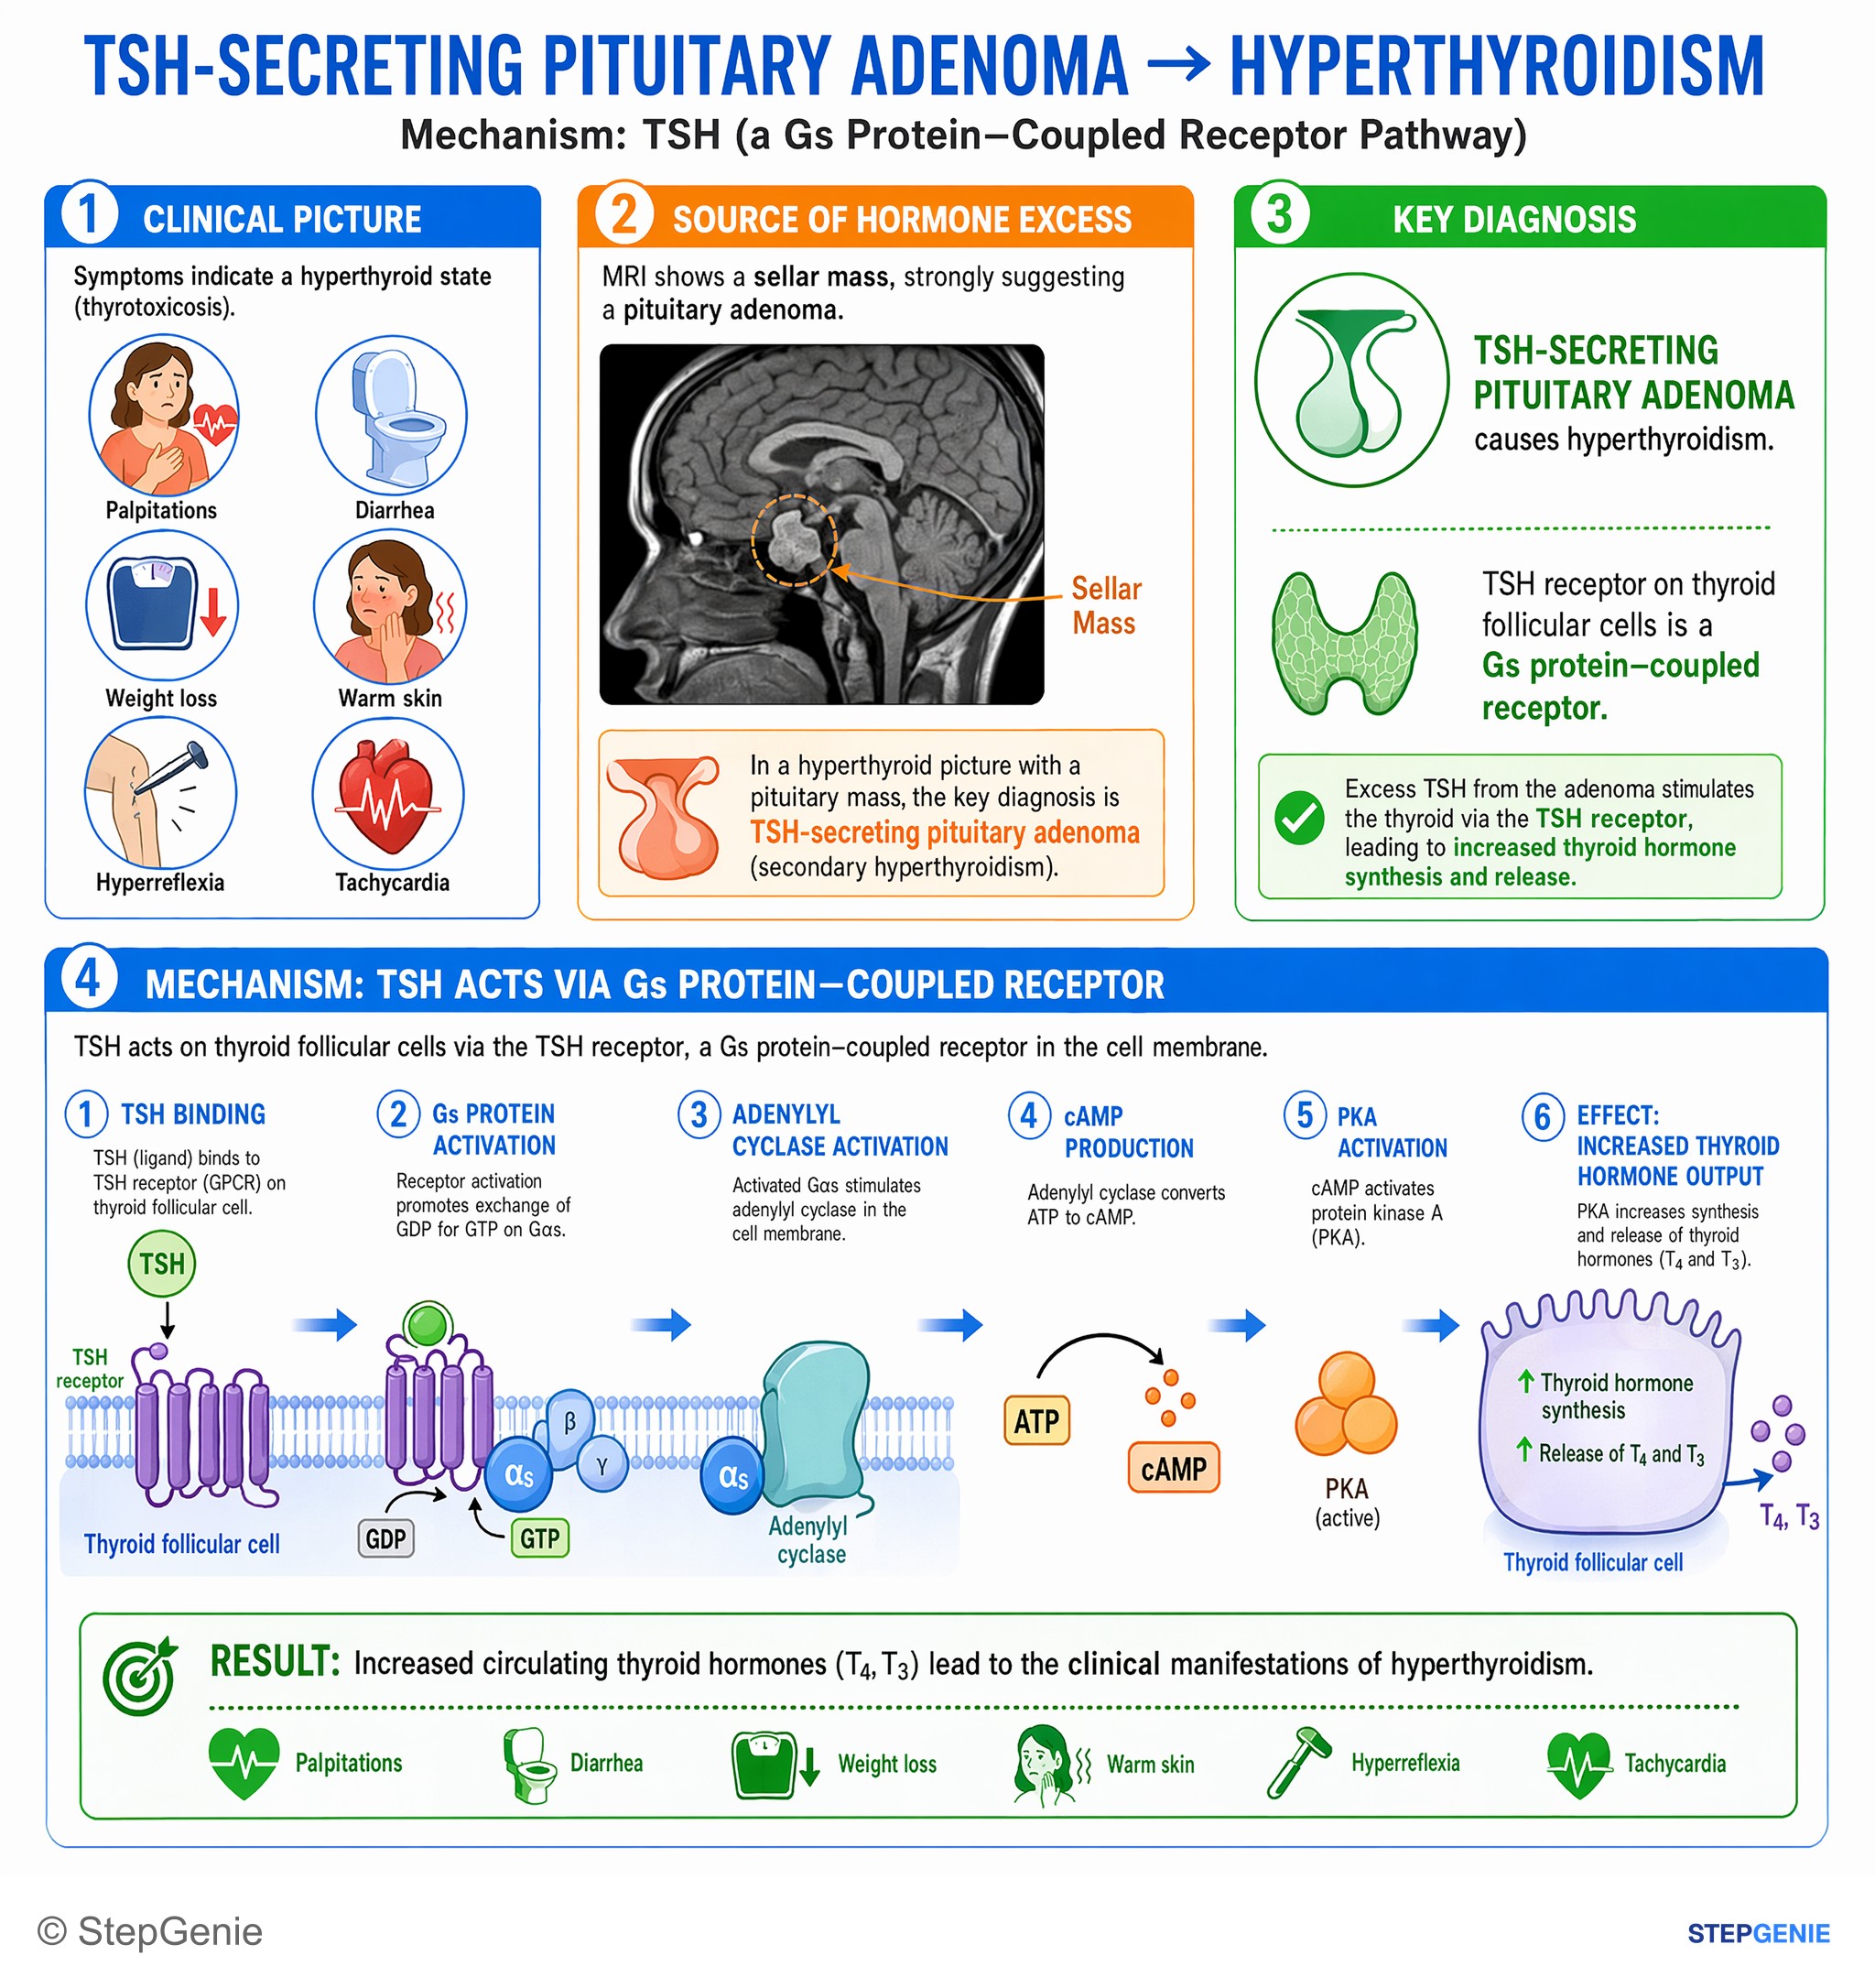
TSH-secreting pituitary adenoma causes hyperthyroidism; TSH receptor on thyroid follicular cells is a Gs protein–coupled receptor.
USMLE Step 1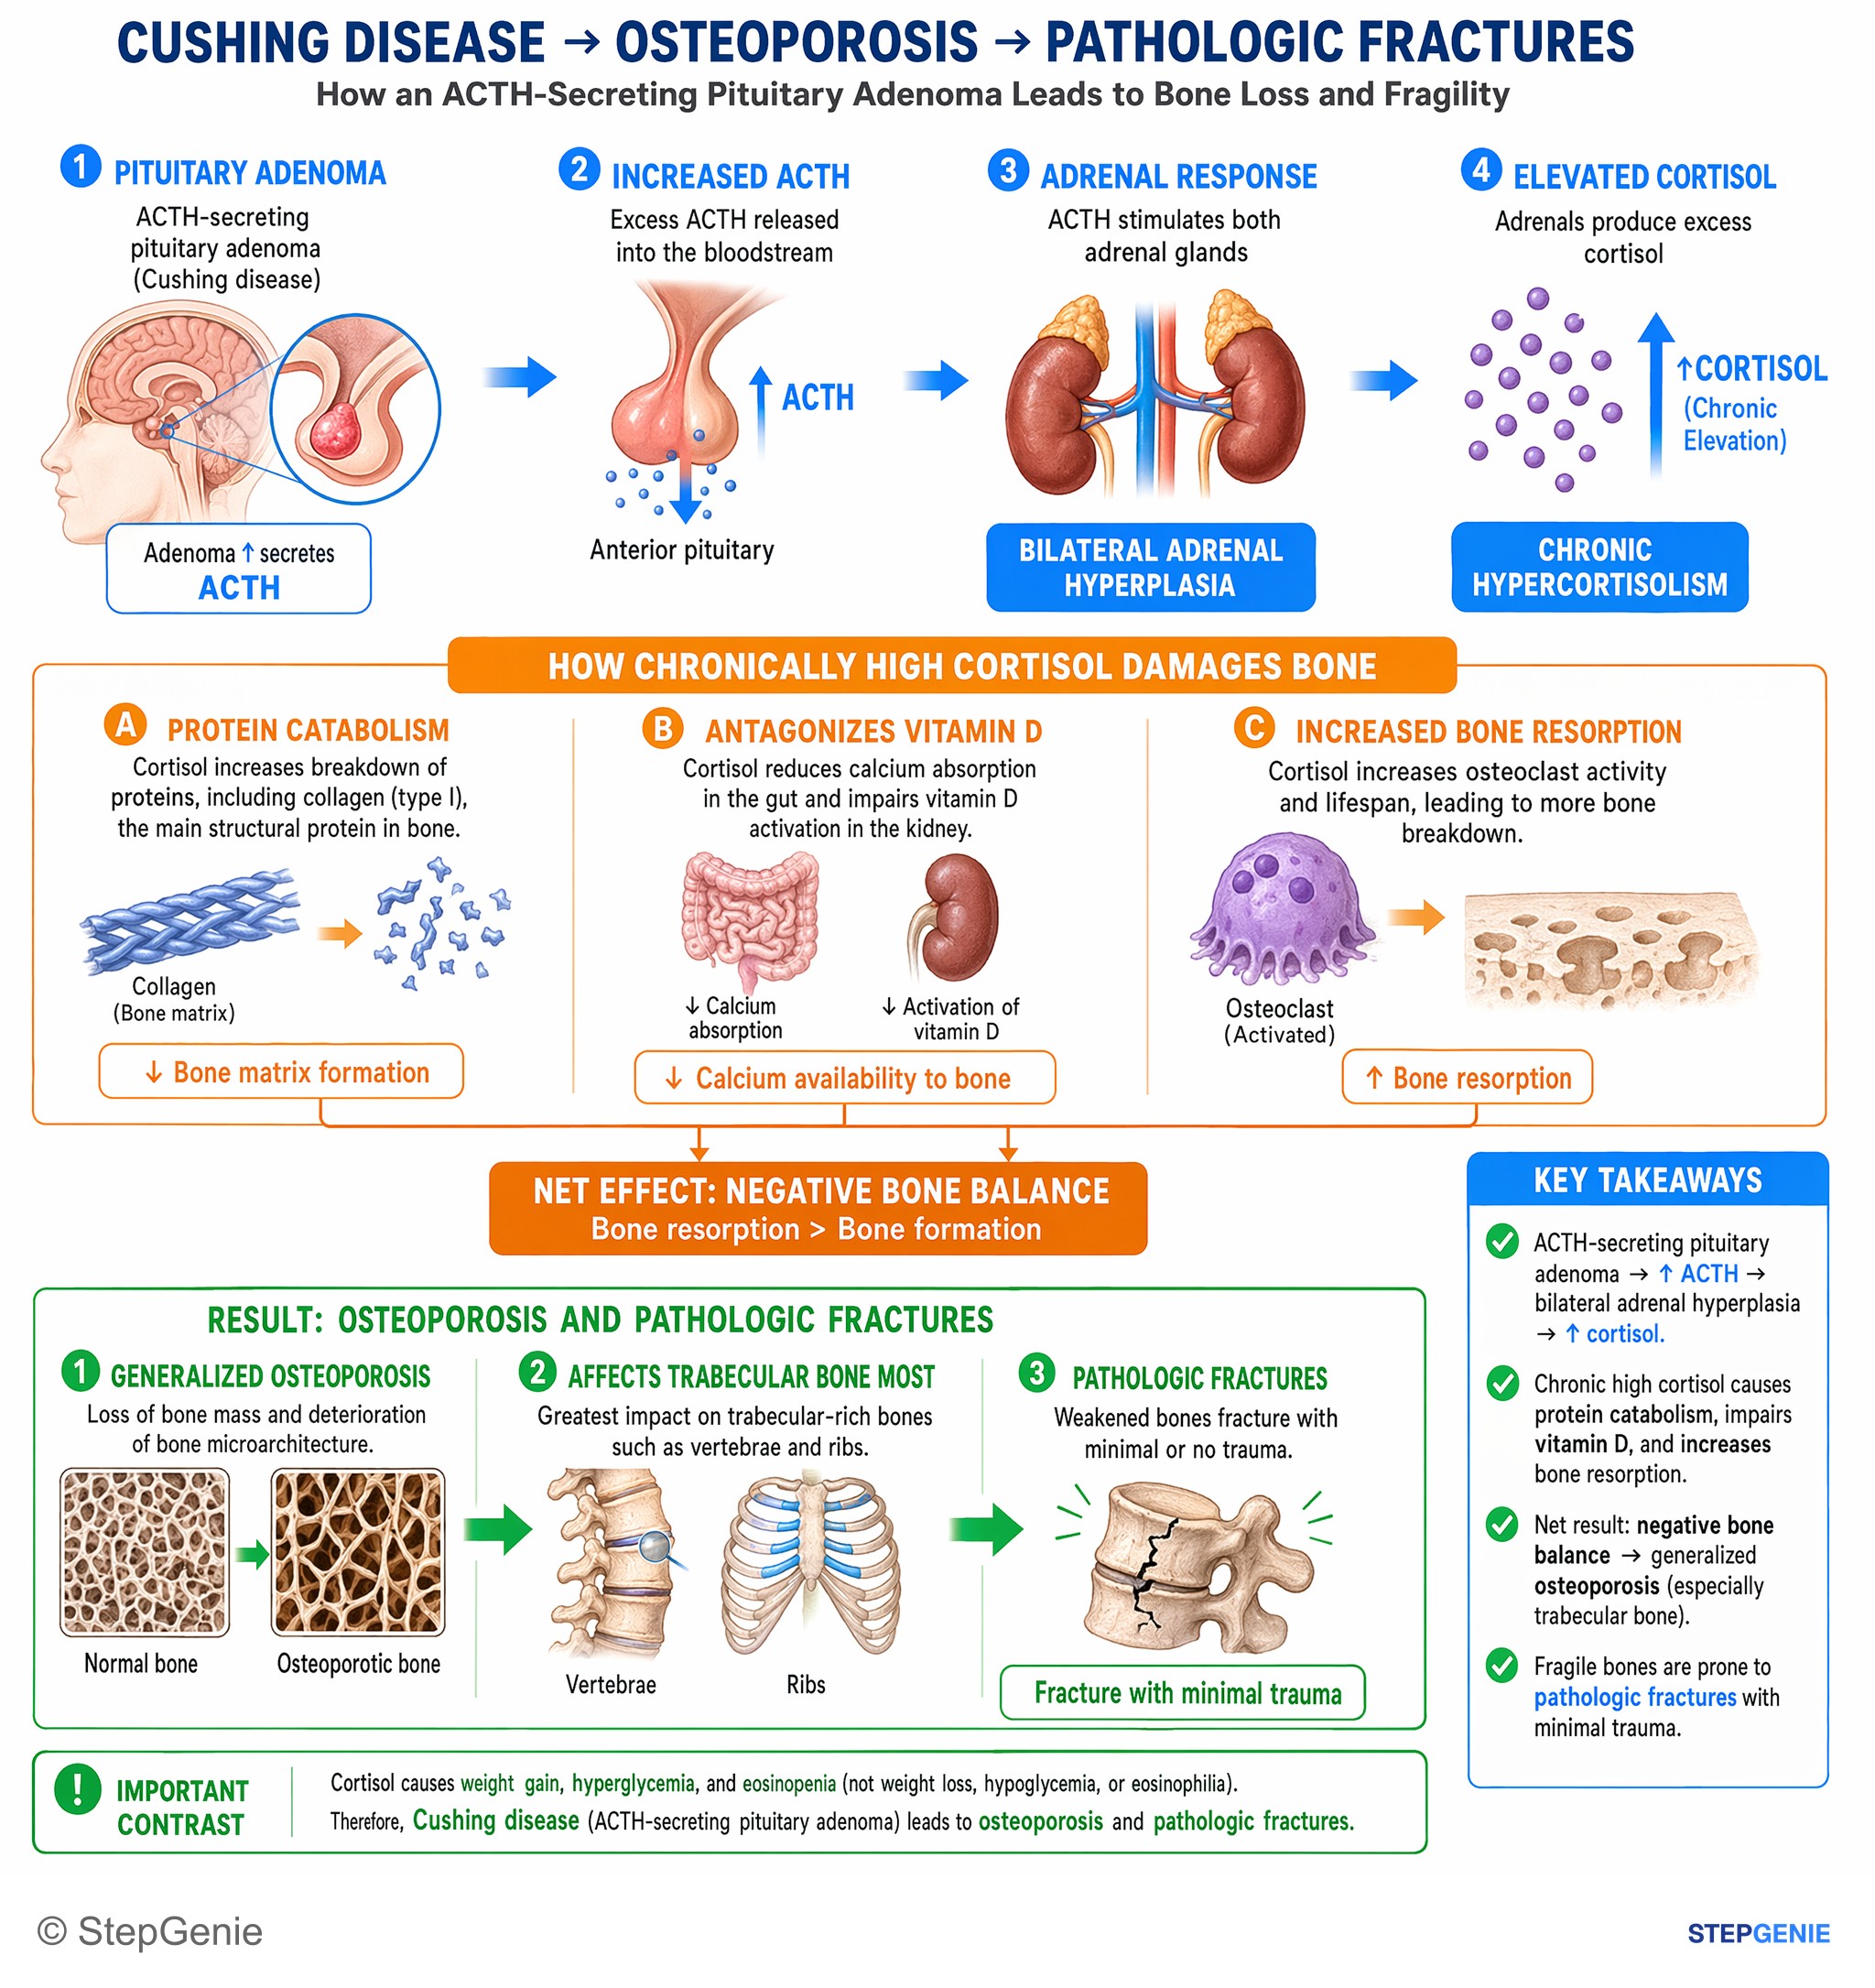
Cushing disease (ACTH-secreting pituitary adenoma) causes chronic hypercortisolism → osteoporosis from bone resorption → increased risk of…
USMLE Step 2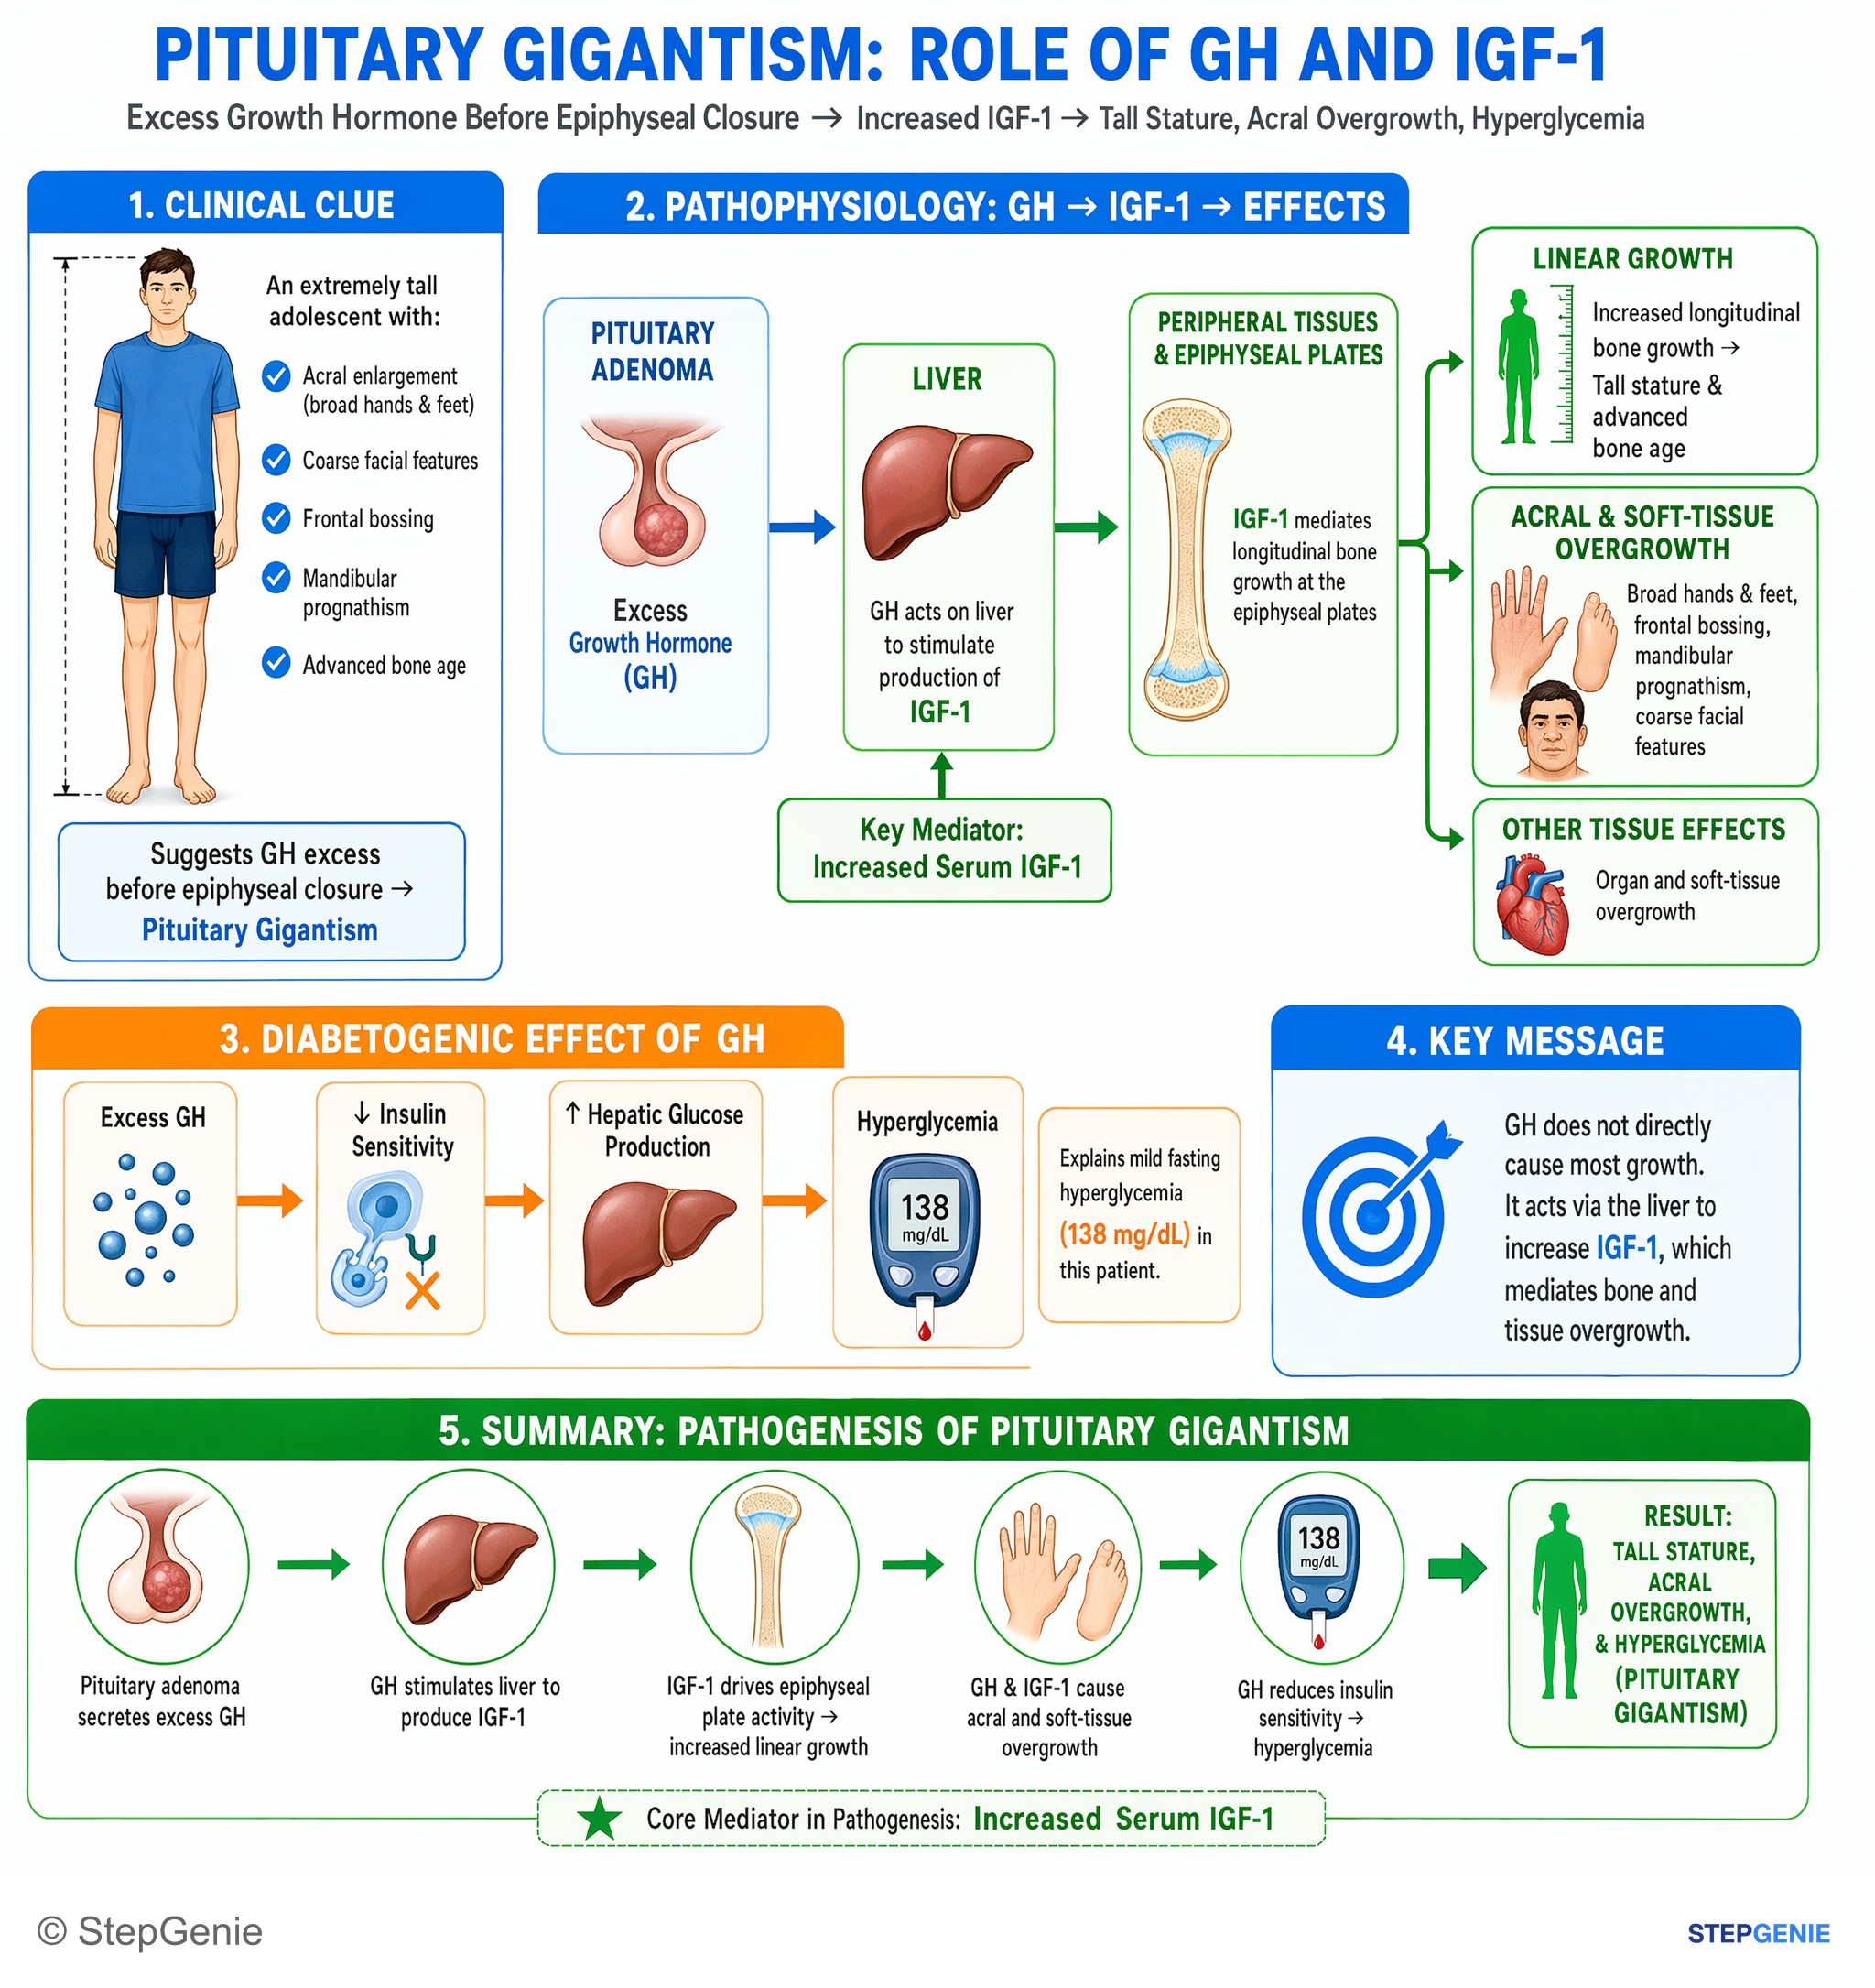
Pituitary gigantism from excess GH → ↑ IGF-1 (liver) before epiphyseal closure → tall stature, acral overgrowth, hyperglycemia.
USMLE Step 1Frequently Asked Questions
What is the most common type of pituitary adenoma?
Prolactinoma is the most common hormone-secreting pituitary adenoma; the Pituitary Society's 2023 consensus puts prolactinomas at about half of all pituitary adenomas. The other large group is nonfunctioning adenomas, most of which are gonadotroph tumors that make little active hormone and come to attention through headache, visual loss or hypopituitarism. GH-secreting, ACTH-secreting and especially TSH-secreting tumors are less common.
Why is cabergoline used instead of surgery for a prolactinoma, even a large one?
Dopamine agonists such as cabergoline lower prolactin, restore gonadal function and shrink most prolactinomas, often improving vision, so they are first-line even for macroadenomas pressing on the optic chiasm. Cabergoline is preferred over bromocriptine because it is more effective, better tolerated and taken only once or twice a week. Surgery is mainly for resistance or intolerance, although expert surgery can be discussed as a first option for microadenomas and well-circumscribed macroadenomas.
How is acromegaly diagnosed?
The first test is serum IGF-1, which is stable through the day while GH is pulsatile. Classically, the diagnosis is confirmed when GH fails to suppress below 1 microgram per liter during an oral glucose tolerance test. A 2024 international consensus adds that an IGF-1 above 1.3 times the upper limit of normal in a patient with typical features confirms the diagnosis, keeping the glucose test for equivocal cases, and MRI then locates the pituitary tumor.
What is the pituitary stalk effect?
The stalk effect is hyperprolactinemia caused by any sellar or suprasellar mass that compresses the pituitary stalk and blocks dopamine from reaching the lactotrophs. The prolactin rise is usually modest, a few times the upper limit of normal, whereas a prolactin above 200 ng/mL favors a true prolactinoma. Cabergoline lowers prolactin in both conditions, but only a prolactinoma shrinks.
What is pituitary apoplexy and how is it treated?
Pituitary apoplexy is sudden hemorrhage or infarction, usually into an existing pituitary adenoma. It causes a sudden severe headache, stiff neck, visual loss, eye movement palsies and drowsiness, and loss of ACTH can cause shock. Stress-dose glucocorticoids are given immediately, and urgent transsphenoidal decompression is needed for sudden visual loss, ocular palsies or declining consciousness.
Why does a pituitary adenoma cause bitemporal hemianopia?
The optic chiasm sits just above the sella, and the nerve fibers crossing in it come from the nasal halves of both retinas, which see the temporal visual fields. A macroadenoma growing upward presses on these crossing fibers from below, so both temporal fields are lost, typically starting in the superior temporal quadrants. Lateral growth into the cavernous sinus can also cause palsies of cranial nerves III, IV or VI.