Central diabetes insipidus means the posterior pituitary releases too little ADH (arginine vasopressin); nephrogenic diabetes insipidus means ADH is present but the collecting duct cannot respond to it. Both produce large volumes of dilute urine (osmolality usually below 300 mOsm/kg) with a high-normal or high serum sodium, and in both the urine stays dilute during water deprivation. The tie-breaker is desmopressin: urine osmolality rises by more than 50% in complete central DI and barely changes in nephrogenic DI (partial central DI gives a smaller rise, about 15–50%). Central DI is treated with desmopressin; nephrogenic DI is treated by removing the cause (most often lithium) and adding a thiazide, an NSAID or amiloride.
In 2022 an international working group proposed new names, arginine vasopressin deficiency (AVP-D) for central DI and arginine vasopressin resistance (AVP-R) for nephrogenic DI, mainly to stop dangerous confusion with diabetes mellitus. Exams and most review books still use the old terms, so know both.
The mnemonic: C = can't create, N = nephron says no
- Central DI: the brain can't create or release enough ADH. ADH (and its stable marker, copeptin) is low, and the kidney responds normally once desmopressin is given.
- Nephrogenic DI: the nephron says no. ADH is normal or high, but the collecting duct ignores it, so desmopressin does little.
Think of ADH as a text message: in central DI the phone never sends it; in nephrogenic DI it arrives, but nobody reads it.
ADH physiology in four lines
- ADH is made mainly in the supraoptic and paraventricular nuclei of the hypothalamus, then stored in and released from the posterior pituitary.
- The strongest stimulus is a rise in plasma osmolality, sensed by osmoreceptors that respond to changes of about 2 mOsm/L; hypovolemia also triggers release.
- On collecting duct principal cells, ADH binds V2 receptors (Gs, cAMP), which move aquaporin-2 channels into the apical membrane so water is reabsorbed.
- V1 receptors on vascular smooth muscle act through phospholipase C to cause vasoconstriction. Desmopressin is a selective V2 agonist, so it concentrates urine rather than raising blood pressure.
Central vs nephrogenic DI at a glance
| Feature | Central DI (AVP deficiency) | Nephrogenic DI (AVP resistance) |
|---|---|---|
| Problem | Too little ADH released | Collecting duct does not respond to ADH |
| ADH or copeptin level | Low | Normal to high; a baseline copeptin of 21.4 pmol/L or more points to it |
| Urine during water deprivation | Stays dilute | Stays dilute |
| Urine after desmopressin | Rises more than 50% when complete (often more than 100%); about 15–50% when partial | Minimal rise (under 50 mOsm/kg) |
| Classic causes | Idiopathic, mostly autoimmune (30–50%); pituitary or hypothalamic surgery; head trauma; tumors of the hypothalamic–pituitary region (craniopharyngioma, metastases); Langerhans cell histiocytosis, sarcoidosis; AVP gene mutations (autosomal dominant); Wolfram syndrome | Lithium (the most common acquired cause); hypercalcemia; hypokalemia; demeclocycline; sickle cell nephropathy; AVPR2 mutations (X-linked, about 90% of inherited cases); AQP2 mutations (autosomal recessive or dominant) |
| Treatment | Desmopressin; treat the underlying lesion | Remove the cause; low-salt, low-protein diet; thiazide; NSAID; amiloride for lithium |
Diagnosis, step by step
- Confirm polyuria: more than 50 mL/kg of urine a day. People with DI often pass 3–30 L daily.
- Prove it is a water diuresis. Urine osmolality is low (under 300 mOsm/kg). Check glucose first, because diabetes mellitus causes an osmotic diuresis in which urine osmolality is not low, and check calcium and potassium for nephrogenic causes.
- Read the serum sodium. High-normal or high favors DI; a low sodium (under 135 mmol/L) suggests primary polydipsia.
- Water deprivation. Healthy kidneys concentrate urine to about 800–1,200 mOsm/kg. In complete DI the urine stays below 300; values between 300 and 800 fit partial DI, and primary polydipsia usually lands in this middle range too.
- Give desmopressin. A rise of more than 50% means central DI (partial central DI may rise only 15–50%); little or no rise means nephrogenic DI.
| Condition | Urine osmolality after deprivation | Response to desmopressin |
|---|---|---|
| Primary polydipsia | Partly concentrated (about 500–600 mOsm/kg) | No change |
| Complete central DI | Stays below 300 mOsm/kg | Rises more than 50%, often more than 100% |
| Partial central DI | 300 mOsm/kg or higher | Rises about 15–50% |
| Nephrogenic DI | Stays low | Minimal (under 50 mOsm/kg) |
How practice is changing: the water deprivation test often misclassifies partial DI and primary polydipsia. A hypertonic saline–stimulated copeptin above 4.9 pmol/L identifies primary polydipsia and was more accurate than water deprivation in a head-to-head study (96.5% vs 76.6%). Board questions still use the classic deprivation-then-desmopressin sequence.
Treatment
Central DI. Desmopressin (intranasal, oral, subcutaneous or IV) replaces the missing hormone. Its main risk is hyponatremia from overtreatment, which can cause seizures. Treat the underlying lesion as well.
Nephrogenic DI.
- Remove the cause: stop lithium if possible, and correct calcium and potassium.
- Amiloride is the targeted drug for lithium-induced DI. Lithium enters collecting duct principal cells mainly through the epithelial sodium channel (ENaC), and amiloride blocks that channel. The rest of the lithium toxicity profile is in the lithium overview.
- Thiazides paradoxically reduce urine output: they cause mild volume depletion, so less water reaches the ADH-sensitive collecting tubules to be lost there.
- NSAIDs such as indomethacin help because prostaglandins oppose ADH action in the kidney.
- A low-salt, low-protein diet lowers the solute load the kidney must excrete, so less water is lost with it.
Exam traps
- Not all polyuria is DI. Hyperglycemia causes an osmotic diuresis with urine osmolality that is not low; check glucose first.
- Primary polydipsia also gives dilute urine, but the serum sodium is low-normal or low and the urine concentrates partly with deprivation. Giving desmopressin to someone who keeps drinking large volumes risks severe hyponatremia; the low-sodium side of this differential is covered in hyponatremia, SIADH and psychogenic polydipsia.
- Hypernatremia needs impaired thirst or no access to water. An alert patient who can drink keeps the sodium near normal, while infants, postoperative patients and people with altered mental status become hypernatremic; the hypernatremia Q-bank breakdown works through that scenario.
- Polyuria right after pituitary surgery is often not DI. Extra IV fluid, mannitol and steroid-induced hyperglycemia are common culprits, so confirm with osmolality and sodium before starting desmopressin.
- Gestational DI: in the second half of pregnancy the placenta secretes vasopressinase, which breaks down ADH; it usually resolves within 2–3 weeks after delivery.
- Lithium, then nephrogenic DI, then amiloride is the high-yield drug chain in this topic.
Worked example
Vignette. A 46-year-old woman with bipolar disorder has taken lithium for 12 years. She passes about 6 L of urine a day and wakes four times a night to drink. Serum sodium is 145 mEq/L, glucose 92 mg/dL and calcium normal; urine osmolality is 110 mOsm/kg. After supervised water deprivation her urine osmolality is 140 mOsm/kg, and 1 hour after desmopressin it is 150 mOsm/kg. Her psychiatrist wants to continue lithium. Which drug best targets the cause of her polyuria?
Answer: Amiloride, for lithium-induced nephrogenic DI.
Reasoning: Urine that stays dilute during water deprivation means DI, and a rise of only about 7% after desmopressin means the kidney cannot respond to ADH, so this is nephrogenic DI. Lithium reaches principal cells through ENaC, amiloride blocks that entry, and a thiazide can be added to reduce urine volume further.
Key takeaways
- Central = can't create ADH; nephrogenic = nephron says no.
- Both cause large volumes of urine below 300 mOsm/kg with a high-normal sodium; hypernatremia appears when thirst or water access fails.
- Desmopressin after deprivation: a rise of more than 50% means complete central DI; a minimal rise means nephrogenic DI.
- Lithium is the leading acquired cause of nephrogenic DI; treat by stopping it or adding amiloride, plus thiazides, NSAIDs and a low-solute diet.
- Central DI is treated with desmopressin; overtreatment causes hyponatremia.
- New names: AVP deficiency and AVP resistance; copeptin-based testing is more accurate than the water deprivation test.
Sources
- Arginine Vasopressin Disorder (Diabetes Insipidus) — StatPearls, NCBI Bookshelf
- Diagnostic Tests for Diabetes Insipidus — Endotext, NCBI Bookshelf
- Arginine Vasopressin Deficiency (Central Diabetes Insipidus) — Merck Manual Professional Edition
- Arginine Vasopressin Resistance — Merck Manual Professional Edition
- Physiology, Vasopressin — StatPearls, NCBI Bookshelf
- Changing the name of diabetes insipidus: a position statement of the Working Group for Renaming Diabetes Insipidus — Endocrine Connections
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
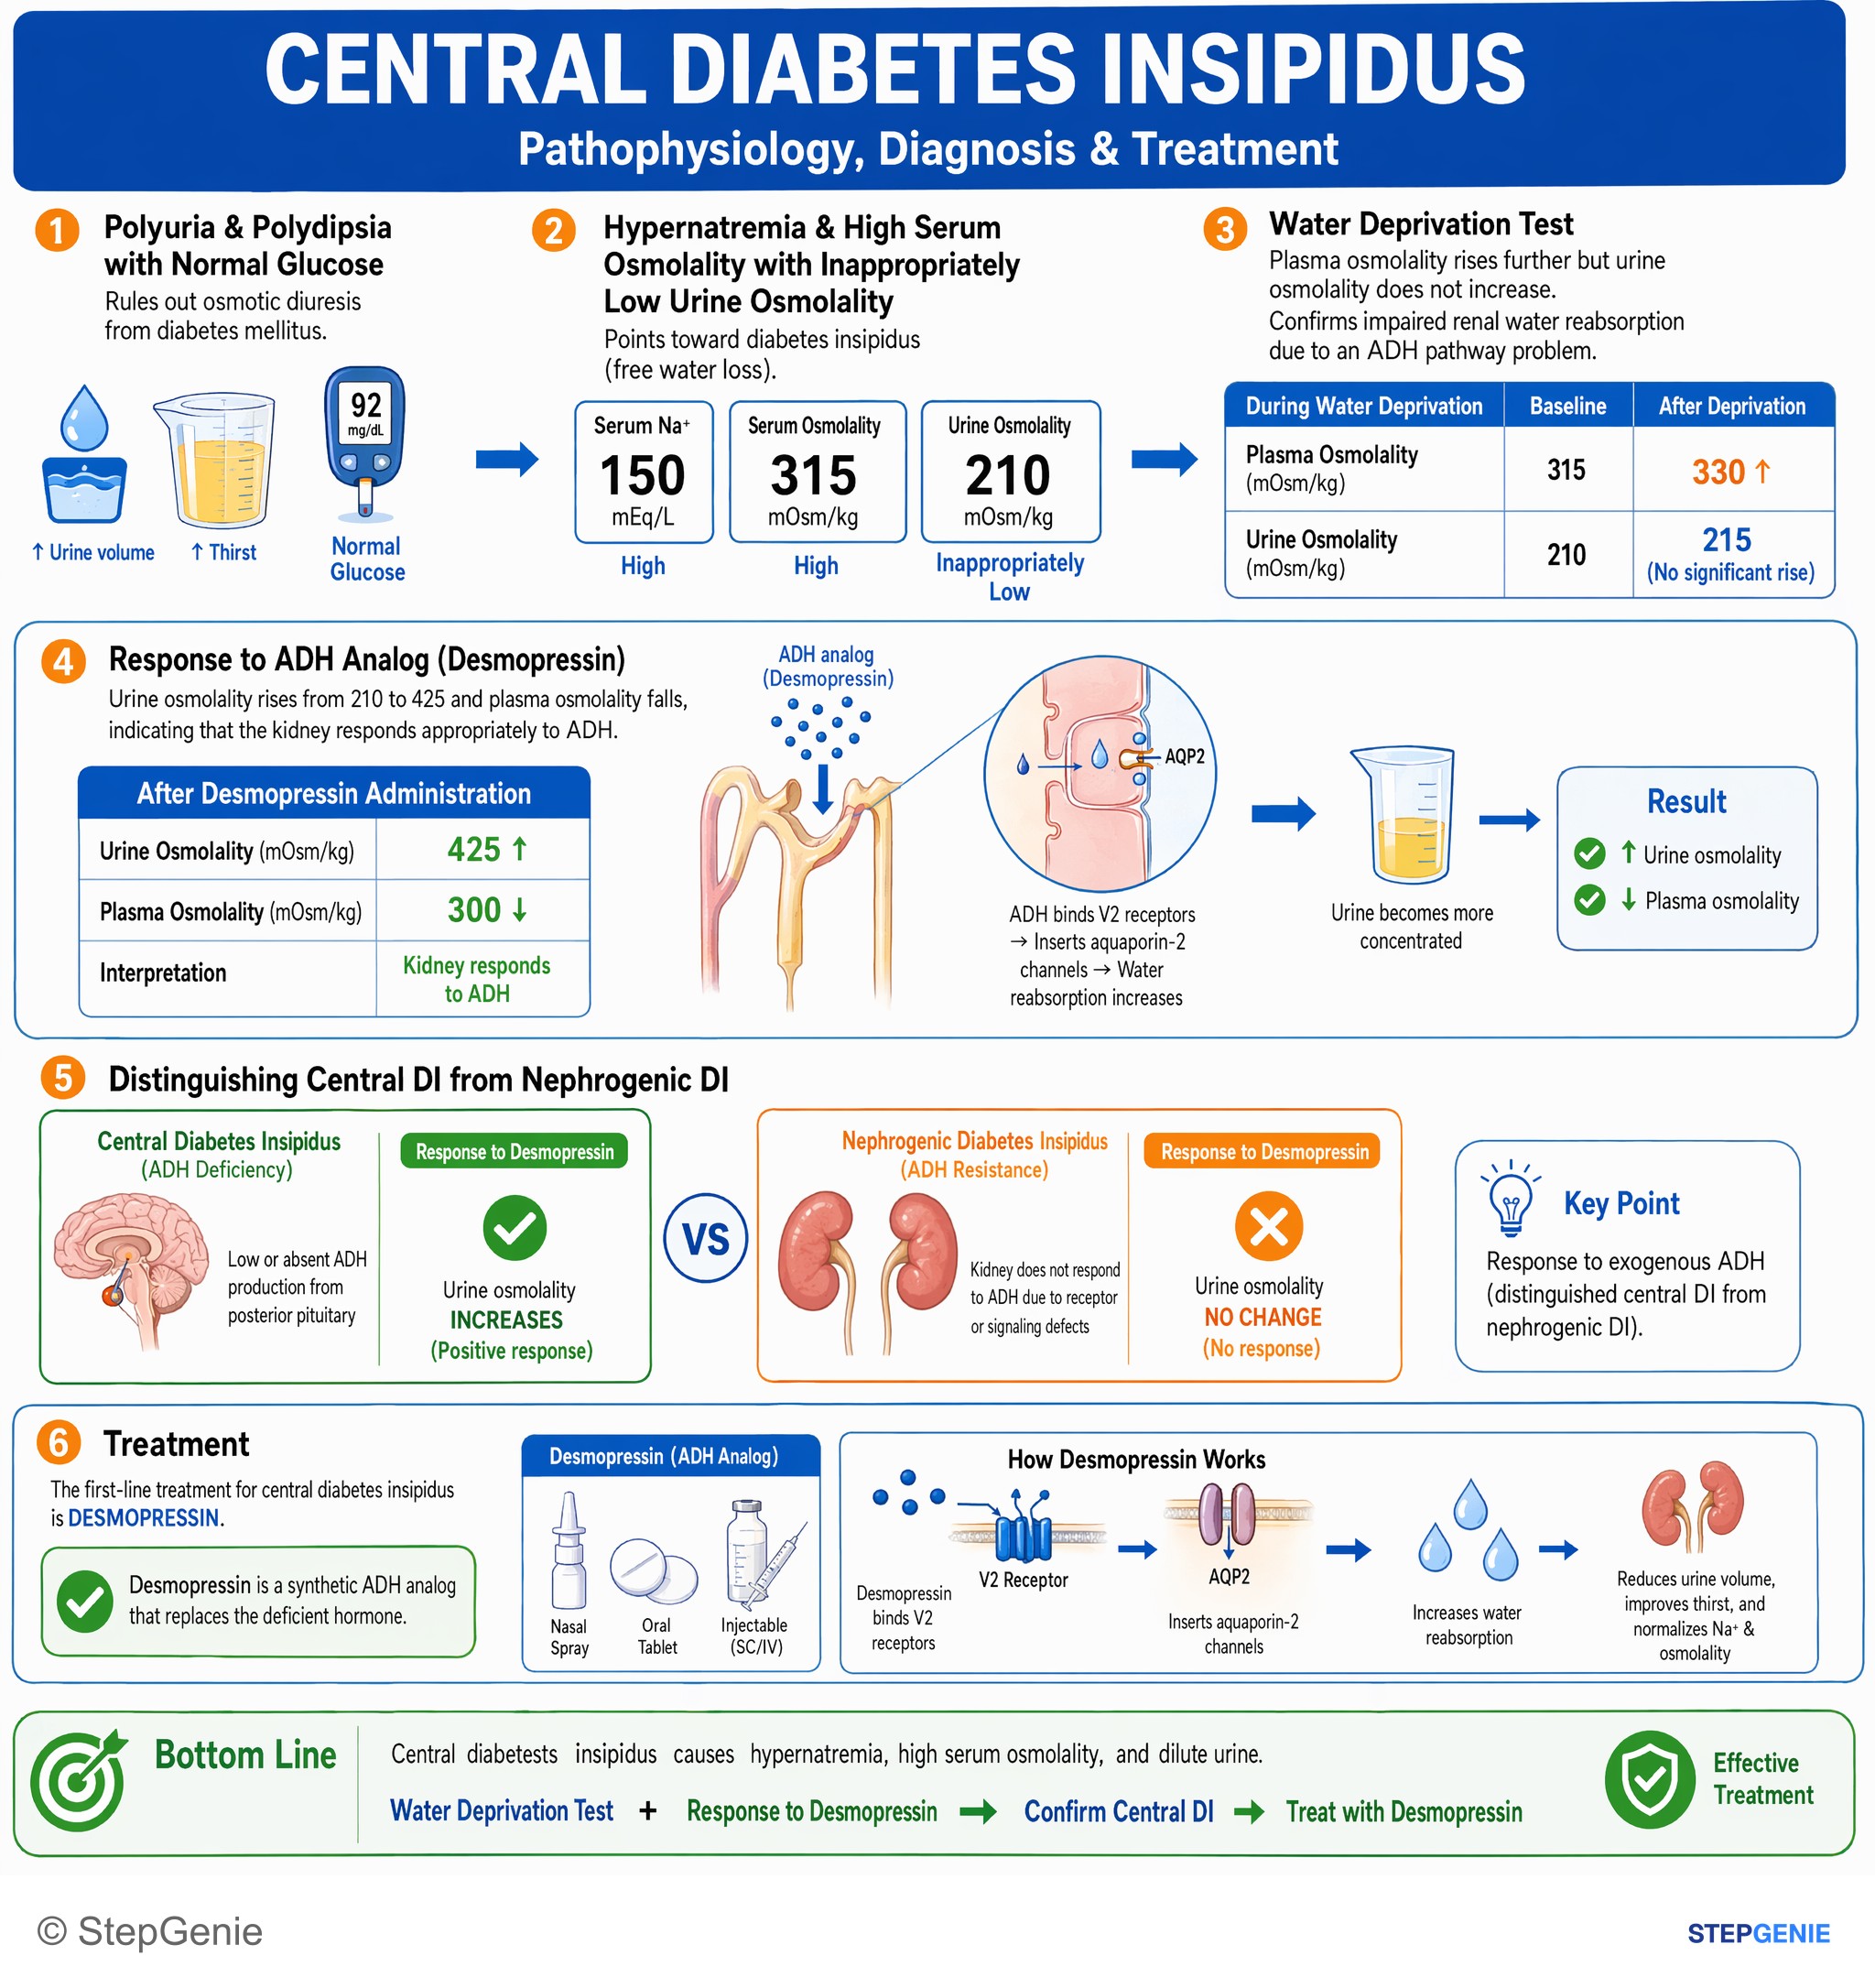
Central diabetes insipidus causes hypernatremia, high serum osmolality, dilute urine; water deprivation + response to ADH analog → treat…
USMLE Step 2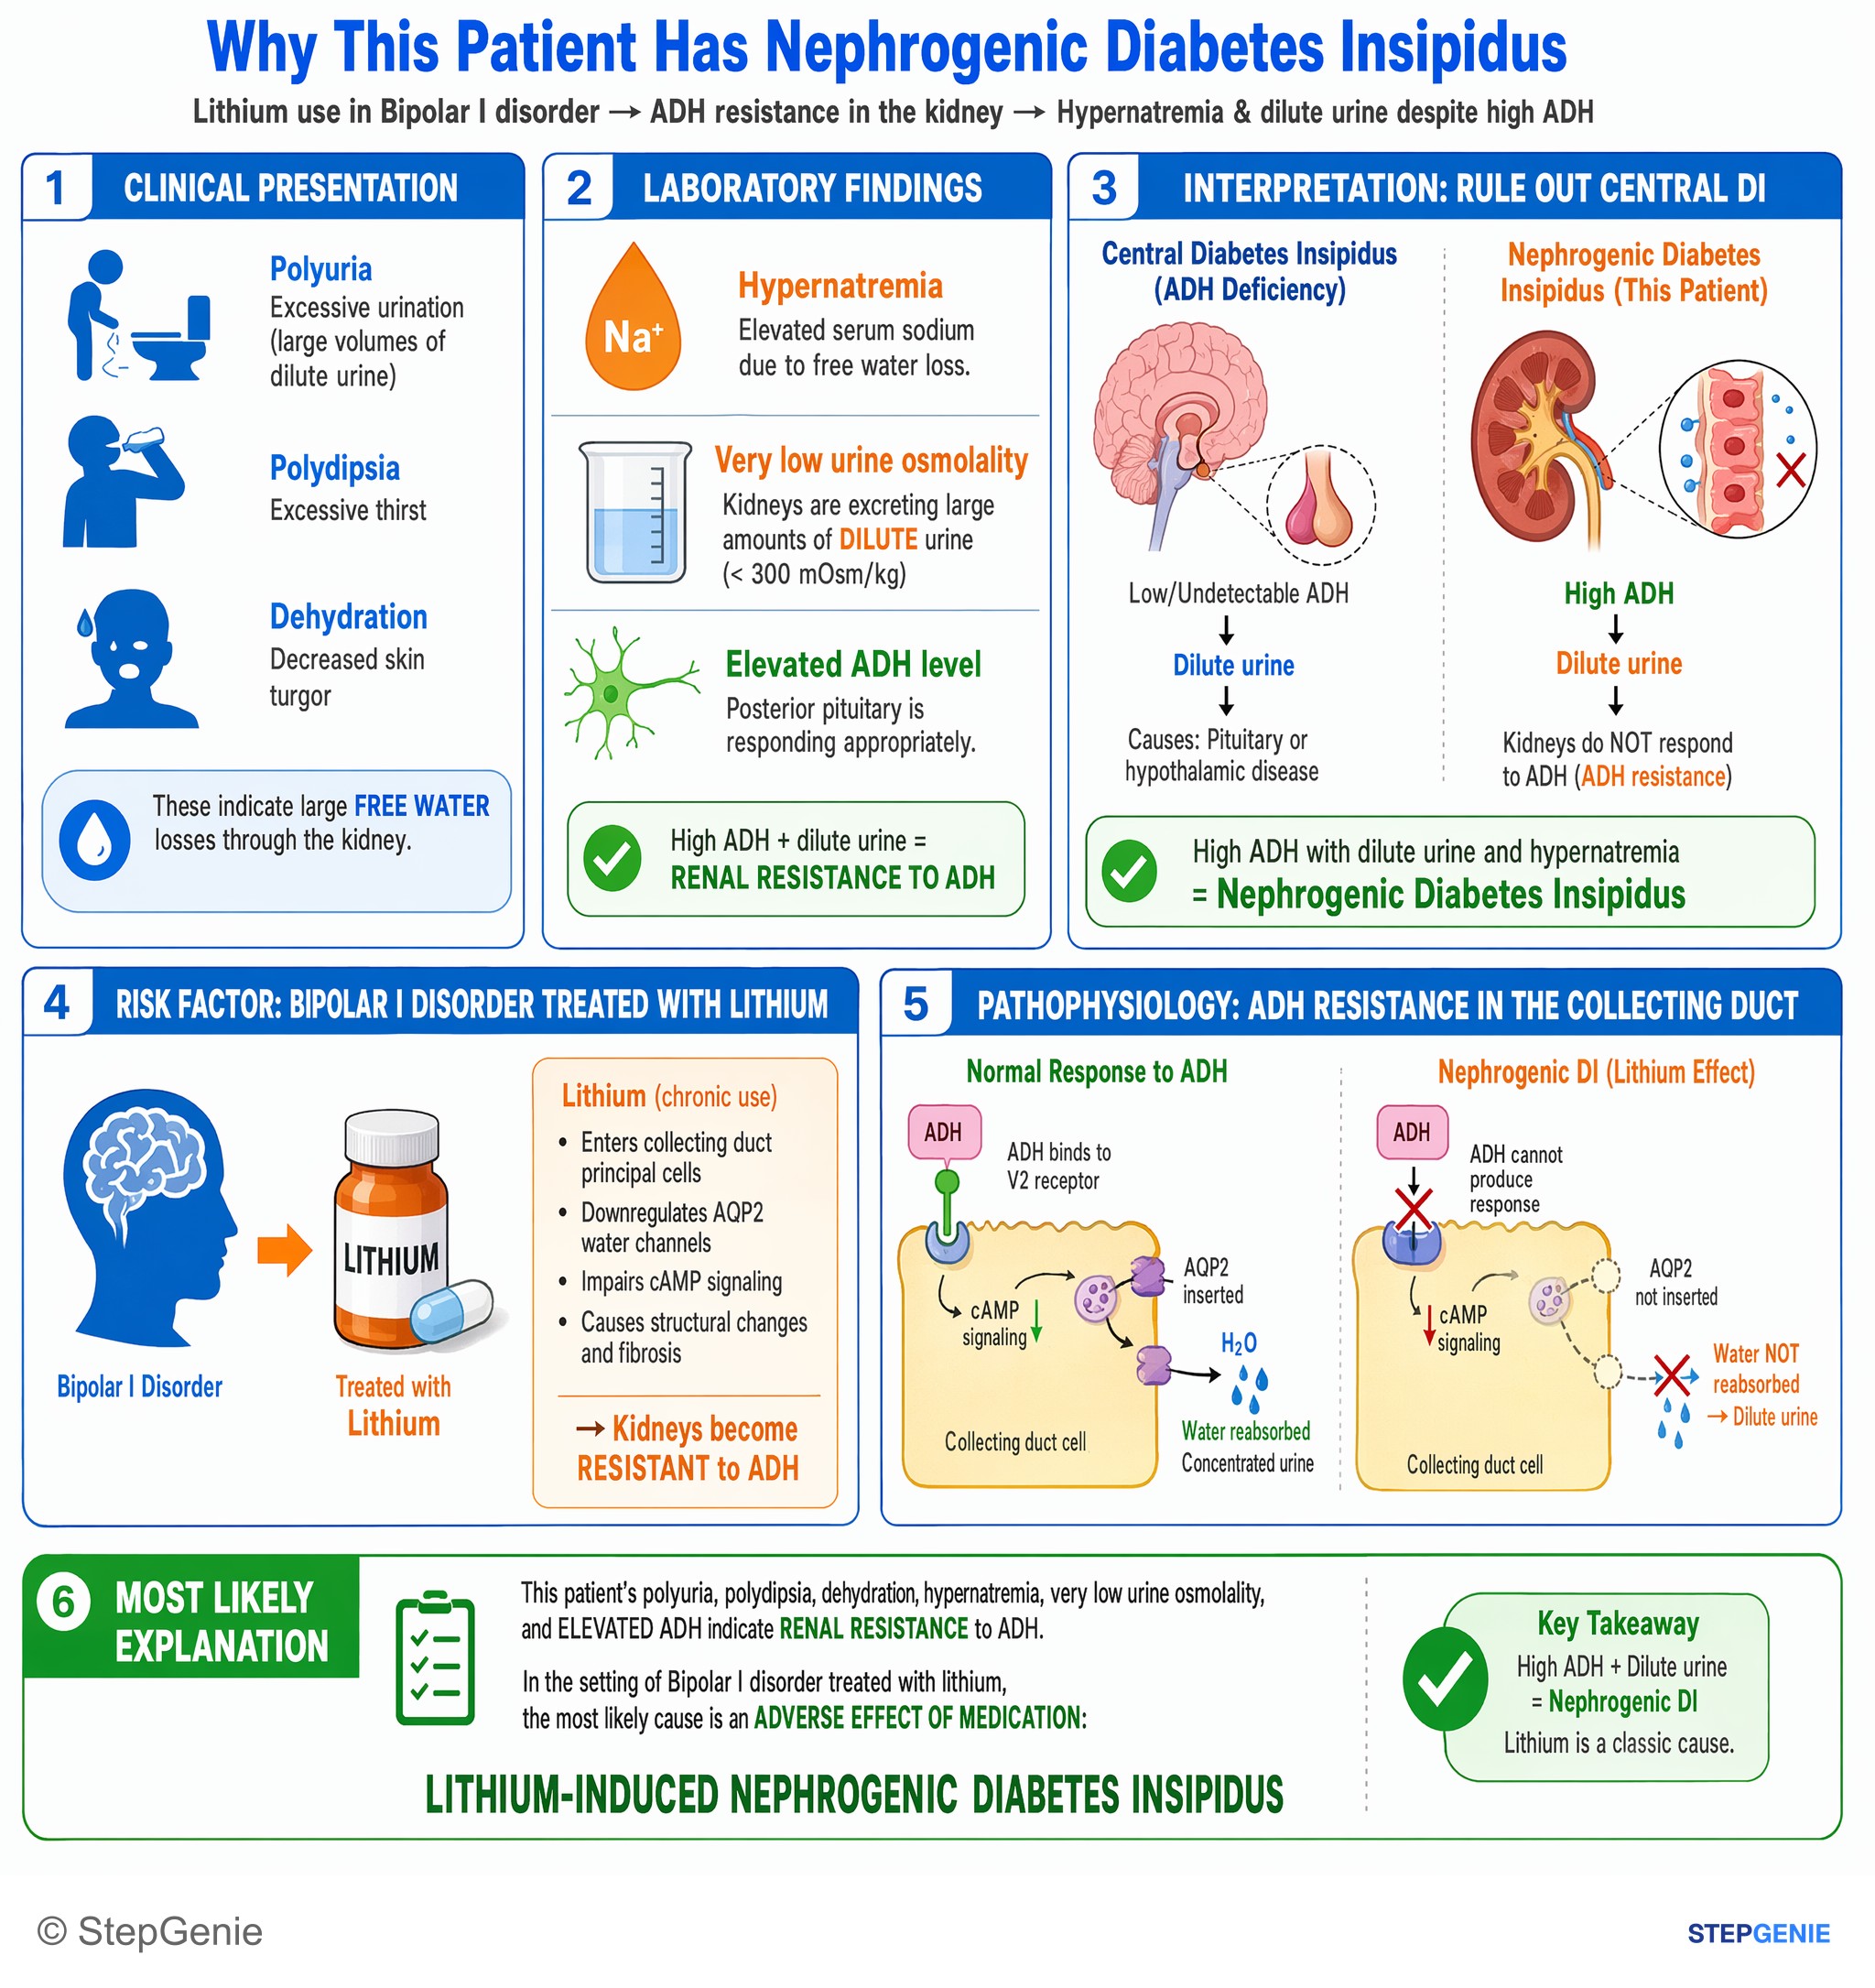
Nephrogenic diabetes insipidus from chronic lithium use in bipolar I: kidneys become ADH-resistant → hypernatremia + low urine osmolality…
USMLE Step 1Frequently Asked Questions
How do you differentiate central and nephrogenic diabetes insipidus?
Both keep the urine dilute during water deprivation, so the key is the response to desmopressin afterward. Urine osmolality rises by more than 50% in complete central DI because the kidney responds once ADH is replaced (partial central DI shows a smaller rise), but barely changes in nephrogenic DI because the collecting duct is resistant. ADH and copeptin levels are low in central DI and normal to high in nephrogenic DI.
What is the most common cause of nephrogenic diabetes insipidus?
Lithium is the most common acquired cause. Other causes include hypercalcemia, hypokalemia, demeclocycline and sickle cell nephropathy. Inherited cases are mostly X-linked mutations in the V2 receptor gene (AVPR2), and the rest involve the aquaporin-2 gene (AQP2).
Why do thiazides help nephrogenic diabetes insipidus?
Thiazides paradoxically reduce urine output by causing mild volume depletion, which cuts the amount of water delivered to the ADH-sensitive collecting tubules. They are combined with a low-salt, low-protein diet, and NSAIDs or amiloride can be added; amiloride is the targeted choice when lithium is the cause.
Does diabetes insipidus cause hypernatremia?
Only when the patient cannot drink enough to keep up. An alert adult with an intact thirst mechanism and access to water usually keeps the serum sodium in the high-normal range despite heavy urine losses. Hypernatremia develops when thirst is impaired or water is unavailable, as in infants, after surgery or with altered mental status, while a low sodium points toward primary polydipsia instead.
What is the new name for diabetes insipidus?
In 2022 an international working group proposed renaming central diabetes insipidus as arginine vasopressin deficiency (AVP-D) and nephrogenic diabetes insipidus as arginine vasopressin resistance (AVP-R). The main reason was to prevent dangerous confusion with diabetes mellitus. Exam questions and many review books still use the older terms.