Thyroid labs feel easy until you’re staring at a TSH/T4 combo that “shouldn’t exist.” The trick is to stop memorizing every disease pattern and instead use a fast, repeatable algorithm—then plug in the high-yield exceptions (pregnancy, pituitary, medications). Here’s a shareable acronym-based approach that will get you through most USMLE-style stems in seconds.
The Core Acronym: “TSH LEADS”
Think: TSH is the boss—unless the pituitary/hypothalamus is the problem.
TSH LEADS =
- Low TSH → Excess thyroid hormone (hyperthyroid pattern)
- Elevated TSH → Deficient thyroid hormone (hypothyroid pattern)
- Abnormal pairing (TSH and T4 “don’t match”) → Secondary/central or “special situations”
One-liner:
If the pituitary is intact, TSH moves opposite free T4. If they move together, think central disease or assay/medication effects.
Visual/Mnemonic Device: The “Opposites Rule” Grid
If the pituitary works, TSH and free T4 are opposites
| Pattern | What you call it | Most common USMLE causes |
|---|---|---|
| TSH ↑, free T4 ↓ | Primary hypothyroidism | Hashimoto (anti-TPO), iodine deficiency, thyroidectomy/ablation, meds (amiodarone, lithium) |
| TSH ↓, free T4 ↑ | Primary hyperthyroidism | Graves (TSI), toxic multinodular goiter, toxic adenoma |
| TSH ↓, free T4 normal | Subclinical hyperthyroidism | Early Graves/toxic nodules, excess levothyroxine |
| TSH ↑, free T4 normal | Subclinical hypothyroidism | Early Hashimoto, recovery from nonthyroidal illness |
If they’re not opposites, think “pituitary or weirdness”
| Pattern | High-yield interpretation |
|---|---|
| TSH low/normal + free T4 low | Central (secondary/tertiary) hypothyroidism |
| TSH normal/high + free T4 high | TSH-secreting pituitary adenoma or thyroid hormone resistance |
The “Mismatch” Add-On Acronym: “PIT or KIT”
When TSH and free T4 move the same direction, ask:
PIT or KIT
- PIT = Pituitary problem (TSH adenoma, central hypo)
- KIT = Kooky interference/Iatrogenic/Tricky physiology (biotin, pregnancy, meds)
One-liner:
Mismatch labs? First rule out pituitary pathology, then rule out assay/medication/physiologic traps.
Step-by-Step USMLE Workflow (Fast)
Step 1: Look at TSH
- Low TSH → go hunting for hyperthyroidism unless free T4 is low (central hypo).
- High TSH → go hunting for hypothyroidism.
Step 2: Check free T4
- Abnormal TSH + abnormal free T4 → overt disease (high yield, treatable).
- Abnormal TSH + normal free T4 → subclinical (management depends on degree + patient factors).
Step 3: Use free T3 when needed
- T3 toxicosis: TSH low, free T4 normal, T3 high (classic early Graves or toxic adenoma).
High-Yield Disease “Signature Moves” (What NBME loves)
Graves disease
- Labs: TSH ↓, free T4 ↑
- Clues: diffuse goiter, ophthalmopathy, pretibial myxedema
- Antibody: TSI (thyroid-stimulating immunoglobulin)
- Scan: diffuse increased uptake
Toxic multinodular goiter / toxic adenoma
- Labs: TSH ↓, free T4 ↑
- Scan: patchy uptake (multinodular) or single hot nodule
- Key: no ophthalmopathy
Thyroiditis (subacute de Quervain, painless/postpartum)
- Labs: often TSH ↓, free T4 ↑ early
- Scan: low uptake (preformed hormone leaking)
- Clues:
- de Quervain: painful/tender thyroid after viral illness, ESR ↑
- postpartum: painless, within 1 year of delivery
Hashimoto thyroiditis
- Labs: classically TSH ↑, free T4 ↓ (or subclinical early)
- Antibodies: anti-TPO, anti-thyroglobulin
- Clues: painless goiter, other autoimmune disease
- High-yield: increased risk of B-cell (MALT) lymphoma
The 3 Most-Tested “Trapdoors”
1) Central hypothyroidism
- Pattern: TSH low/normal + free T4 low
- Why it fools you: TSH may be “normal” but inappropriately normal given low T4.
- USMLE clue: headaches, visual field defects, other pituitary hormone issues.
2) Pregnancy
- hCG weakly stimulates the TSH receptor → TSH falls (especially 1st trimester)
- Estrogen increases TBG → total T4 increases, but free T4 is what matters
- USMLE tip: use trimester-specific TSH ranges if provided; otherwise don’t overcall mild TSH suppression early.
3) Biotin supplement interference
- High-dose biotin can cause falsely low TSH and falsely high T4/T3 on many immunoassays.
- Stem clue: “hair/nails supplement,” bodybuilder, MS patient on high-dose biotin.
Medication Effects You Should Recognize
| Medication | Classic thyroid-related effect | Board-style clue |
|---|---|---|
| Amiodarone | Hypo or hyperthyroidism (iodine load; also inhibits T4→T3) | History of afib, “high iodine,” mixed lab patterns |
| Lithium | Hypothyroidism (inhibits hormone release) | Bipolar disorder |
| Glucocorticoids / propranolol | ↓ peripheral T4→T3 conversion | Used in thyroid storm |
| Heparin | Can artifactually increase measured free T4 | ICU/inpatient setting |
Mini “Acronym Card” You Can Screenshot
TSH LEADS
- Low TSH → Excess T4 (hyper pattern)
- Elevated TSH → Deficient T4 (hypo pattern)
- Abnormal pairing → Secondary/special
PIT or KIT (when labs mismatch)
- PIT: pituitary cause (central hypo, TSH adenoma)
- KIT: assay/meds/physiology (biotin, pregnancy, amiodarone)
Quick Practice (Self-Check)
-
TSH ↓, free T4 ↑, uptake scan low
→ Thyroiditis (preformed hormone leak) -
TSH ↑, free T4 normal
→ Subclinical hypothyroidism (often early Hashimoto) -
TSH normal, free T4 low
→ Central hypothyroidism (inappropriately normal TSH) -
TSH ↓, free T4 normal, T3 ↑
→ T3 toxicosis (early Graves/toxic adenoma)
Bottom Line
Use TSH LEADS to classify the pattern instantly, then apply PIT or KIT for mismatches. Most USMLE thyroid questions are pattern recognition plus one “gotcha” clue (uptake scan, pregnancy, biotin, pituitary symptoms).
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
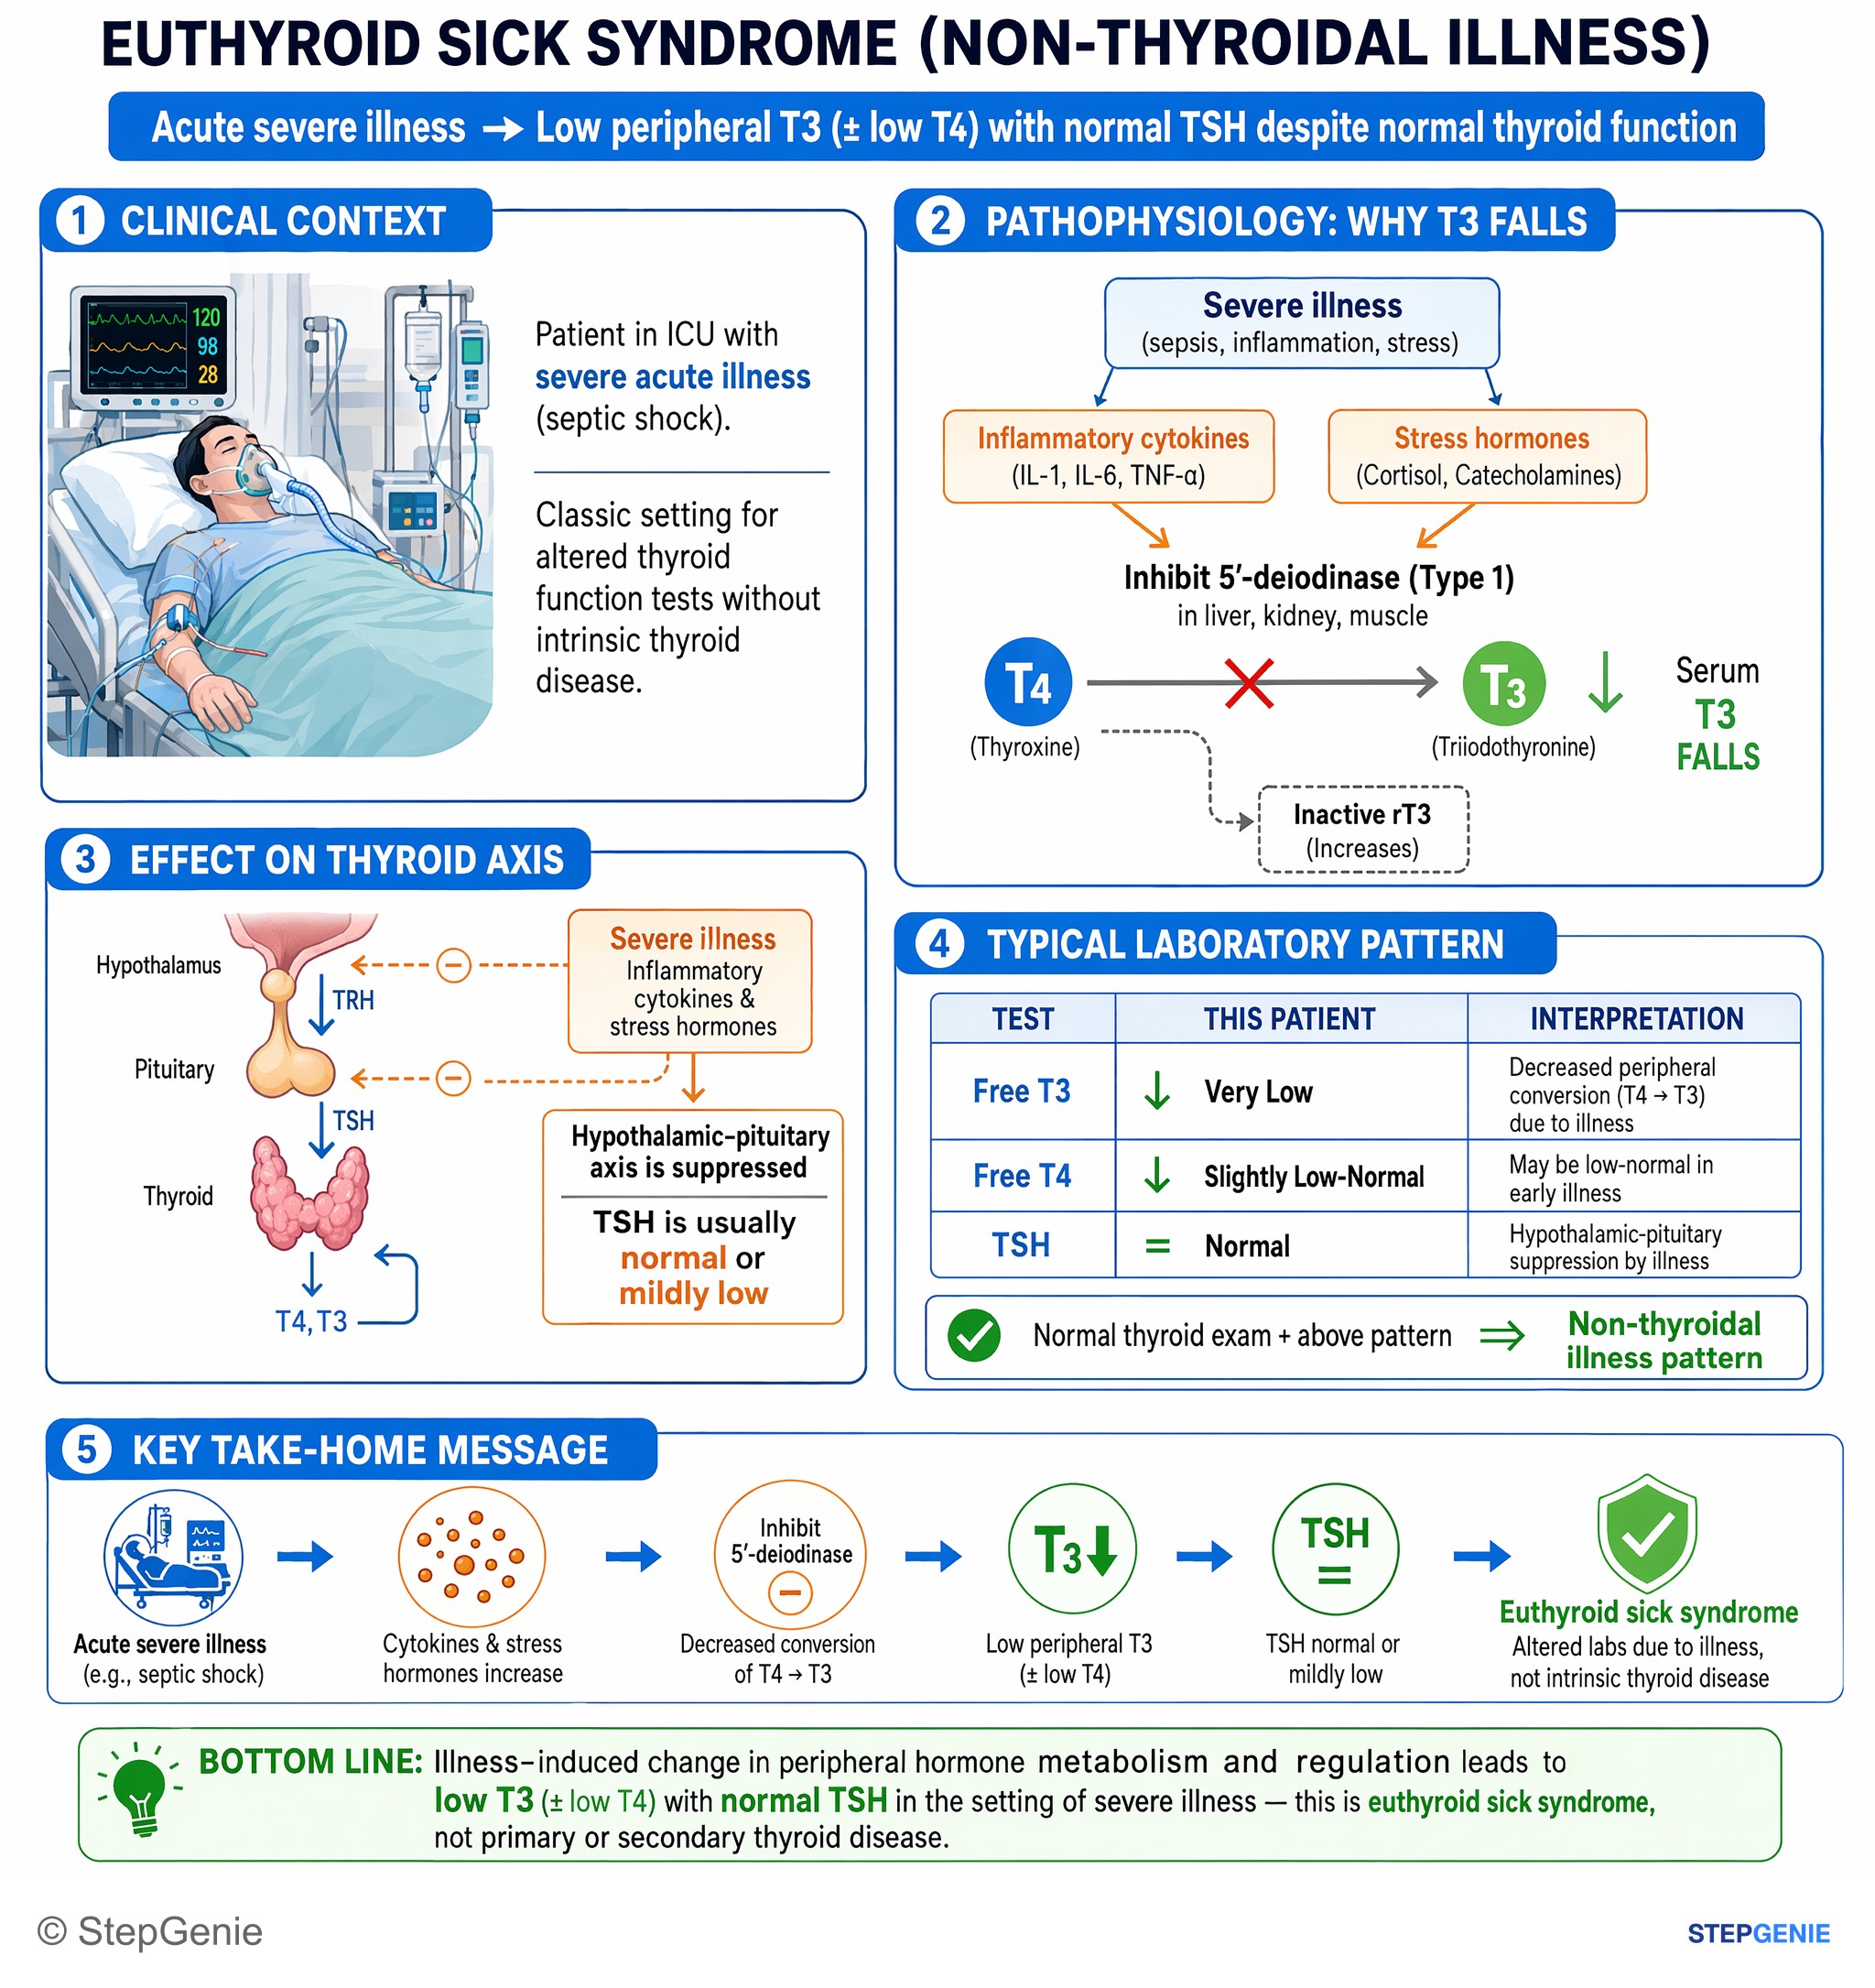
Euthyroid sick syndrome: acute severe illness → low peripheral T3 (± low T4) with normal TSH despite clinically normal thyroid function.
USMLE Step 1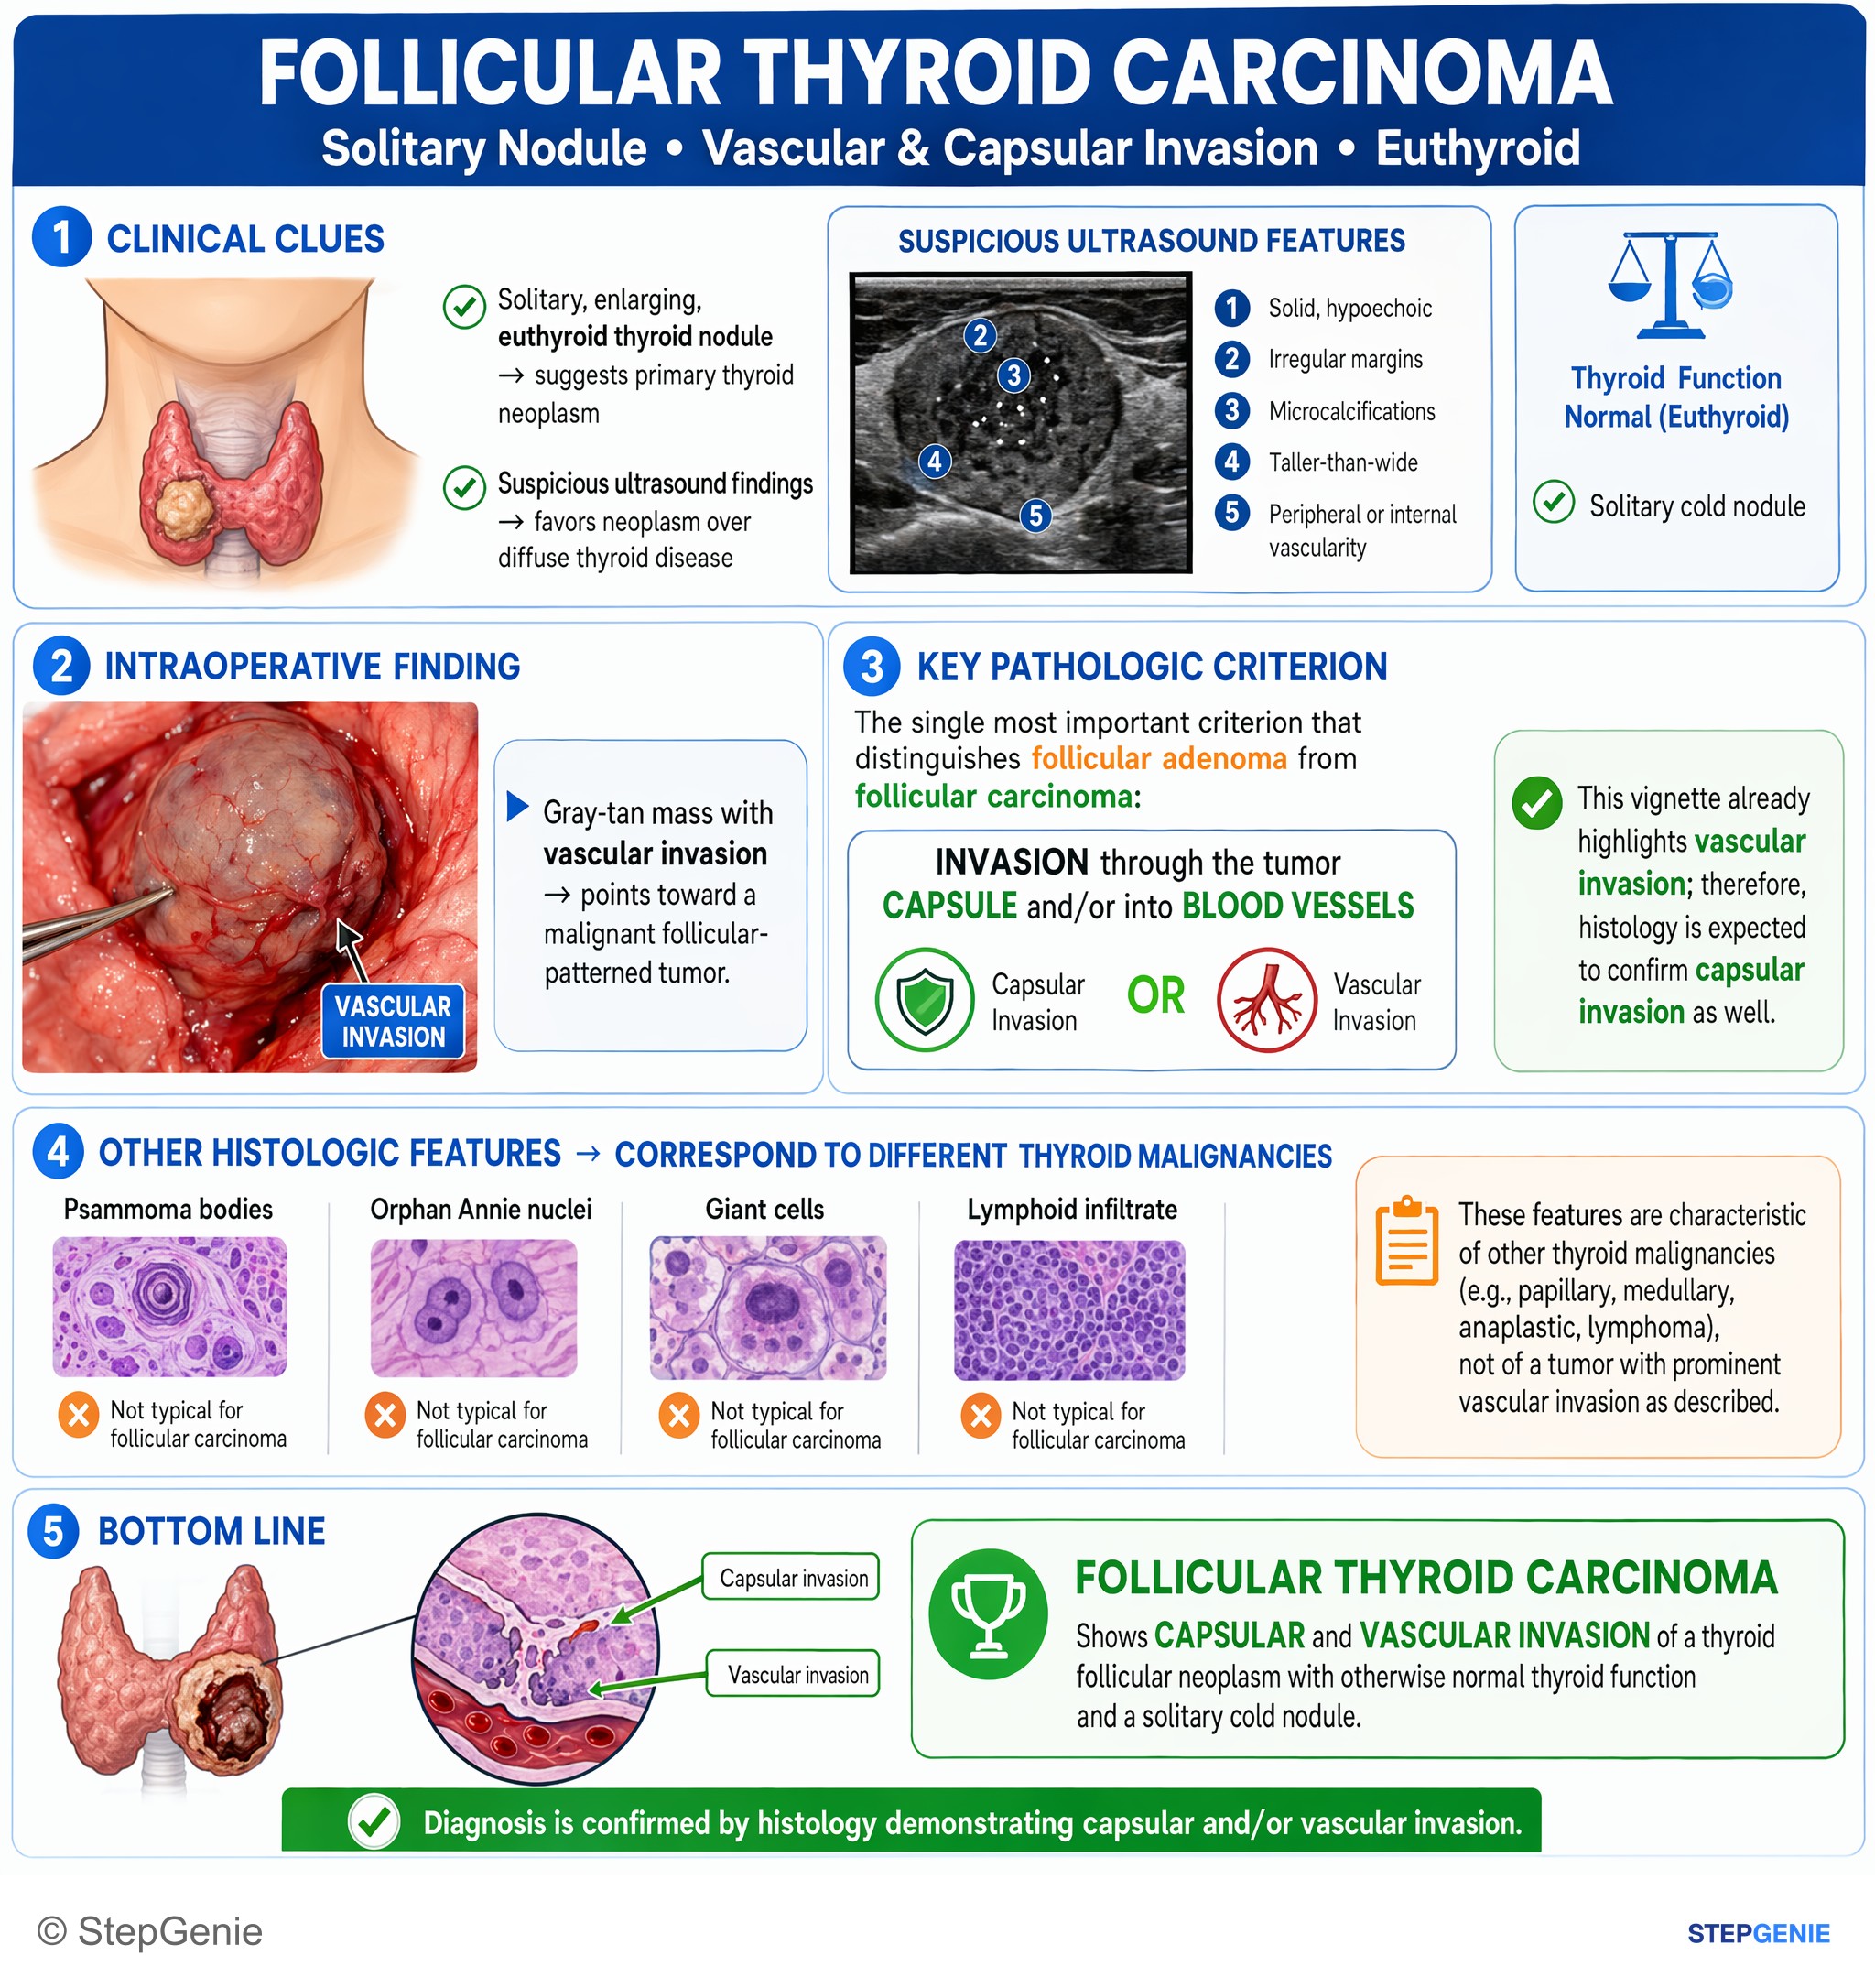
Follicular thyroid carcinoma shows capsular and vascular invasion of a thyroid follicular neoplasm with otherwise normal thyroid function…
USMLE Step 1Frequently Asked Questions
How do you interpret thyroid labs when TSH and free T4 seem to “not match”?
When TSH and free T4 move in the same direction or otherwise do not follow the usual opposite pattern, think central disease or a special situation. If the pituitary is intact, TSH should move opposite free T4. A low or normal TSH with low free T4 suggests central hypothyroidism, while a normal or high TSH with high free T4 suggests a TSH-secreting pituitary adenoma or thyroid hormone resistance. Assay interference, pregnancy, and medications can also create mismatch labs.
What lab pattern suggests central hypothyroidism?
Central hypothyroidism is suggested by low or normal TSH with low free T4. The key trap is that the TSH may look “normal,” but it is inappropriately normal given the low thyroid hormone level. USMLE-style clues include headaches, visual field defects, and other pituitary hormone abnormalities, which point toward a pituitary or hypothalamic cause rather than primary thyroid failure.
How do you tell Graves disease from thyroiditis on thyroid testing?
Graves disease and thyroiditis can both present with low TSH and high free T4, so the uptake scan is the key differentiator. Graves shows diffuse increased uptake and is associated with diffuse goiter, ophthalmopathy, pretibial myxedema, and TSI antibodies. Thyroiditis shows low uptake because preformed hormone is leaking out, and clues include a painful tender thyroid after a viral illness in de Quervain thyroiditis or a painless postpartum presentation.
Why can pregnancy make thyroid labs look abnormal?
Pregnancy can lower TSH because hCG weakly stimulates the TSH receptor, especially in the first trimester. Estrogen also increases thyroid-binding globulin, which raises total T4, so free T4 is the more important value to follow. A mild early TSH suppression should not be overcalled if pregnancy is the context, and trimester-specific TSH ranges should be used if they are provided.
Why does biotin cause misleading thyroid test results?
High-dose biotin can interfere with many thyroid immunoassays and create a false hyperthyroid pattern. It can produce falsely low TSH and falsely high T4 and T3 even when the patient’s true thyroid status is different. A board-style clue is a patient taking a hair and nails supplement, a bodybuilder, or someone with multiple sclerosis using high-dose biotin.