You’re cruising through a GI pharm q-bank set and suddenly you’re staring at five “prokinetic/antiemetic” answer choices that all feel… vaguely similar. This is exactly where Step questions live: not in memorizing drug lists, but in recognizing mechanism → physiologic effect → clinical use → classic adverse effects. Let’s break down a high-yield metoclopramide vignette the way the test writers want you to.
Tag: GI > GI Pharmacology
The Clinical Vignette
A 32-year-old woman with type 1 diabetes presents with 4 months of early satiety, postprandial nausea, bloating, and intermittent non-bilious vomiting. She reports that symptoms are worse after large meals. Physical exam shows mild epigastric distension without guarding. Labs are normal. A gastric emptying study demonstrates delayed gastric emptying. She is started on a medication that improves symptoms by increasing gastric motility and increasing lower esophageal sphincter tone.
Which of the following is the mechanism of action of the medication?
A. Antagonism of dopamine D2 receptors
B. Antagonism of muscarinic M3 receptors
C. Agonism of serotonin 5-HT1B/1D receptors
D. Inhibition of H+/K+ ATPase in parietal cells
E. Antagonism of histamine H2 receptors
Stepwise Diagnosis: What Is This Patient’s Condition?
This is diabetic gastroparesis—classically from autonomic neuropathy affecting gastric motility.
Clues:
- Long-standing diabetes + early satiety, nausea, bloating, vomiting
- Delayed gastric emptying study seals it
- Symptoms worse after meals (especially large/fatty meals)
Correct Answer: A. Antagonism of dopamine D2 receptors (Metoclopramide)
Why Metoclopramide Fits
Metoclopramide is a prokinetic and antiemetic:
- Used for gastroparesis (especially diabetic)
- Also used for GERD refractory to standard therapy (less common on modern practice, still testable)
- Antiemetic via action in the chemoreceptor trigger zone (CTZ)
Mechanism (high-yield)
Metoclopramide:
- Blocks D2 receptors (primary Step mechanism)
- Also activates 5-HT4 receptors (prokinetic effect; often tested as “also has”)
- At higher doses: blocks 5-HT3 receptors (antiemetic contribution)
Physiologic Effects You Should Be Able to Predict
By blocking dopamine in the GI tract, metoclopramide increases acetylcholine release in enteric neurons → enhances motility.
Net effects:
- ↑ gastric emptying
- ↑ LES tone (helps reflux)
- ↑ small intestinal transit
- Minimal effect on colonic motility (relative)
The Adverse Effects They Love to Test
Metoclopramide crosses the BBB and blocks dopamine centrally.
Big 3:
- Extrapyramidal symptoms (EPS): acute dystonia, akathisia, parkinsonism
- Tardive dyskinesia (boxed warning; risk rises with duration—classically avoid >12 weeks when possible)
- Hyperprolactinemia: galactorrhea, amenorrhea, sexual dysfunction (dopamine normally inhibits prolactin)
Pearl: If a stem mentions gastroparesis + a new movement disorder/restlessness → metoclopramide is basically screaming at you.
Why the Other Answers Are Wrong (and What They Actually Describe)
B. Antagonism of muscarinic M3 receptors
This describes antimuscarinics (e.g., atropine, scopolamine, many TCAs have anticholinergic effects).
Why it’s wrong here:
- Blocking M3 would decrease GI motility, worsening gastroparesis.
Classic associations to remember:
- Anticholinergic toxidrome: “dry as a bone, blind as a bat, hot as a hare, mad as a hatter…”
- Urinary retention, constipation, xerostomia, mydriasis
Test takeaway: Prokinetics generally increase cholinergic activity; antimuscarinics do the opposite.
C. Agonism of serotonin 5-HT1B/1D receptors
This is triptans (e.g., sumatriptan) used for acute migraine.
Why it’s wrong here:
- Has nothing to do with gastric emptying or LES tone.
- Mechanism: vasoconstriction of cranial vessels + decreased trigeminal nerve transmission.
High-yield adverse effects/contraindications:
- Avoid in coronary artery disease, vasospastic disease
- Risk of serotonin syndrome with other serotonergic agents
Test takeaway: If you see 5-HT1B/1D, your brain should jump to migraines, not GI.
D. Inhibition of H+/K+ ATPase in parietal cells
This is proton pump inhibitors (PPIs): omeprazole, pantoprazole, etc.
Why it’s wrong here:
- PPIs reduce acid, but don’t fix motility. Gastroparesis is a mechanical/neuromuscular emptying problem, not an acid problem.
High-yield PPI facts:
- Uses: GERD, PUD, Zollinger-Ellison, H. pylori regimens
- Adverse effects (commonly tested):
- C. difficile infection
- Pneumonia
- Hypomagnesemia
- ↓ calcium absorption → fractures
- ↓ B12 absorption (long-term)
Test takeaway: Acid suppression helps heartburn/ulcers; prokinetics help delayed emptying.
E. Antagonism of histamine H2 receptors
This is H2 blockers: famotidine, cimetidine, etc.
Why it’s wrong here:
- Like PPIs, H2 blockers reduce acid secretion but do not improve gastric emptying.
High-yield H2 blocker facts:
- Decrease gastric acid via parietal cell H2 blockade → ↓ cAMP
- Cimetidine is the troublemaker:
- CYP450 inhibitor
- Antiandrogen effects: gynecomastia, impotence
- Can cause confusion in elderly
Test takeaway: H2 blockers = acid control; metoclopramide = motility + antiemetic.
Rapid Comparison Table (Test-Day Friendly)
| Drug/Class | Key Mechanism | Main Use (GI context) | Hallmark Adverse Effects |
|---|---|---|---|
| Metoclopramide | D2 antagonist (also 5-HT4 agonist) | Gastroparesis, antiemetic, sometimes GERD | EPS, tardive dyskinesia, hyperprolactinemia |
| Antimuscarinics | M3 blockade | IBS-D cramps (rarely), motion sickness (scopolamine) | Dry mouth, urinary retention, constipation, delirium |
| Triptans | 5-HT1B/1D agonist | Migraine abortive | Vasoconstriction, serotonin syndrome risk |
| PPIs | Block H+/K+ ATPase | GERD, PUD, H. pylori | C. diff, pneumonia, hypomagnesemia, fractures, ↓B12 |
| H2 blockers | Block H2 receptor → ↓cAMP | GERD, PUD | Cimetidine: CYP inhibition, gynecomastia |
High-Yield “How They’ll Ask It” Patterns
1) Gastroparesis + Diabetes
Think: metoclopramide (or erythromycin as an alternative, see below).
2) Nausea + Movement Disorder After Starting Med
Think: D2 blockade → EPS (metoclopramide or antipsychotics).
3) Patient on Metoclopramide with Galactorrhea/Amenorrhea
Think: hyperprolactinemia due to dopamine blockade.
Quick Sidebar: The Other Prokinetic You Should Know (Erythromycin)
Erythromycin can be used short-term for gastroparesis because it is a motilin receptor agonist → increases migrating motor complexes.
Step-friendly differences vs metoclopramide:
- Erythromycin: QT prolongation, GI cramping/diarrhea, drug interactions (CYP inhibition), tachyphylaxis
- Metoclopramide: EPS/tardive dyskinesia, hyperprolactinemia
The One-Sentence Takeaway
Metoclopramide treats gastroparesis by blocking D2 receptors (and stimulating 5-HT4), increasing gastric motility and LES tone—but watch for EPS, tardive dyskinesia, and hyperprolactinemia.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
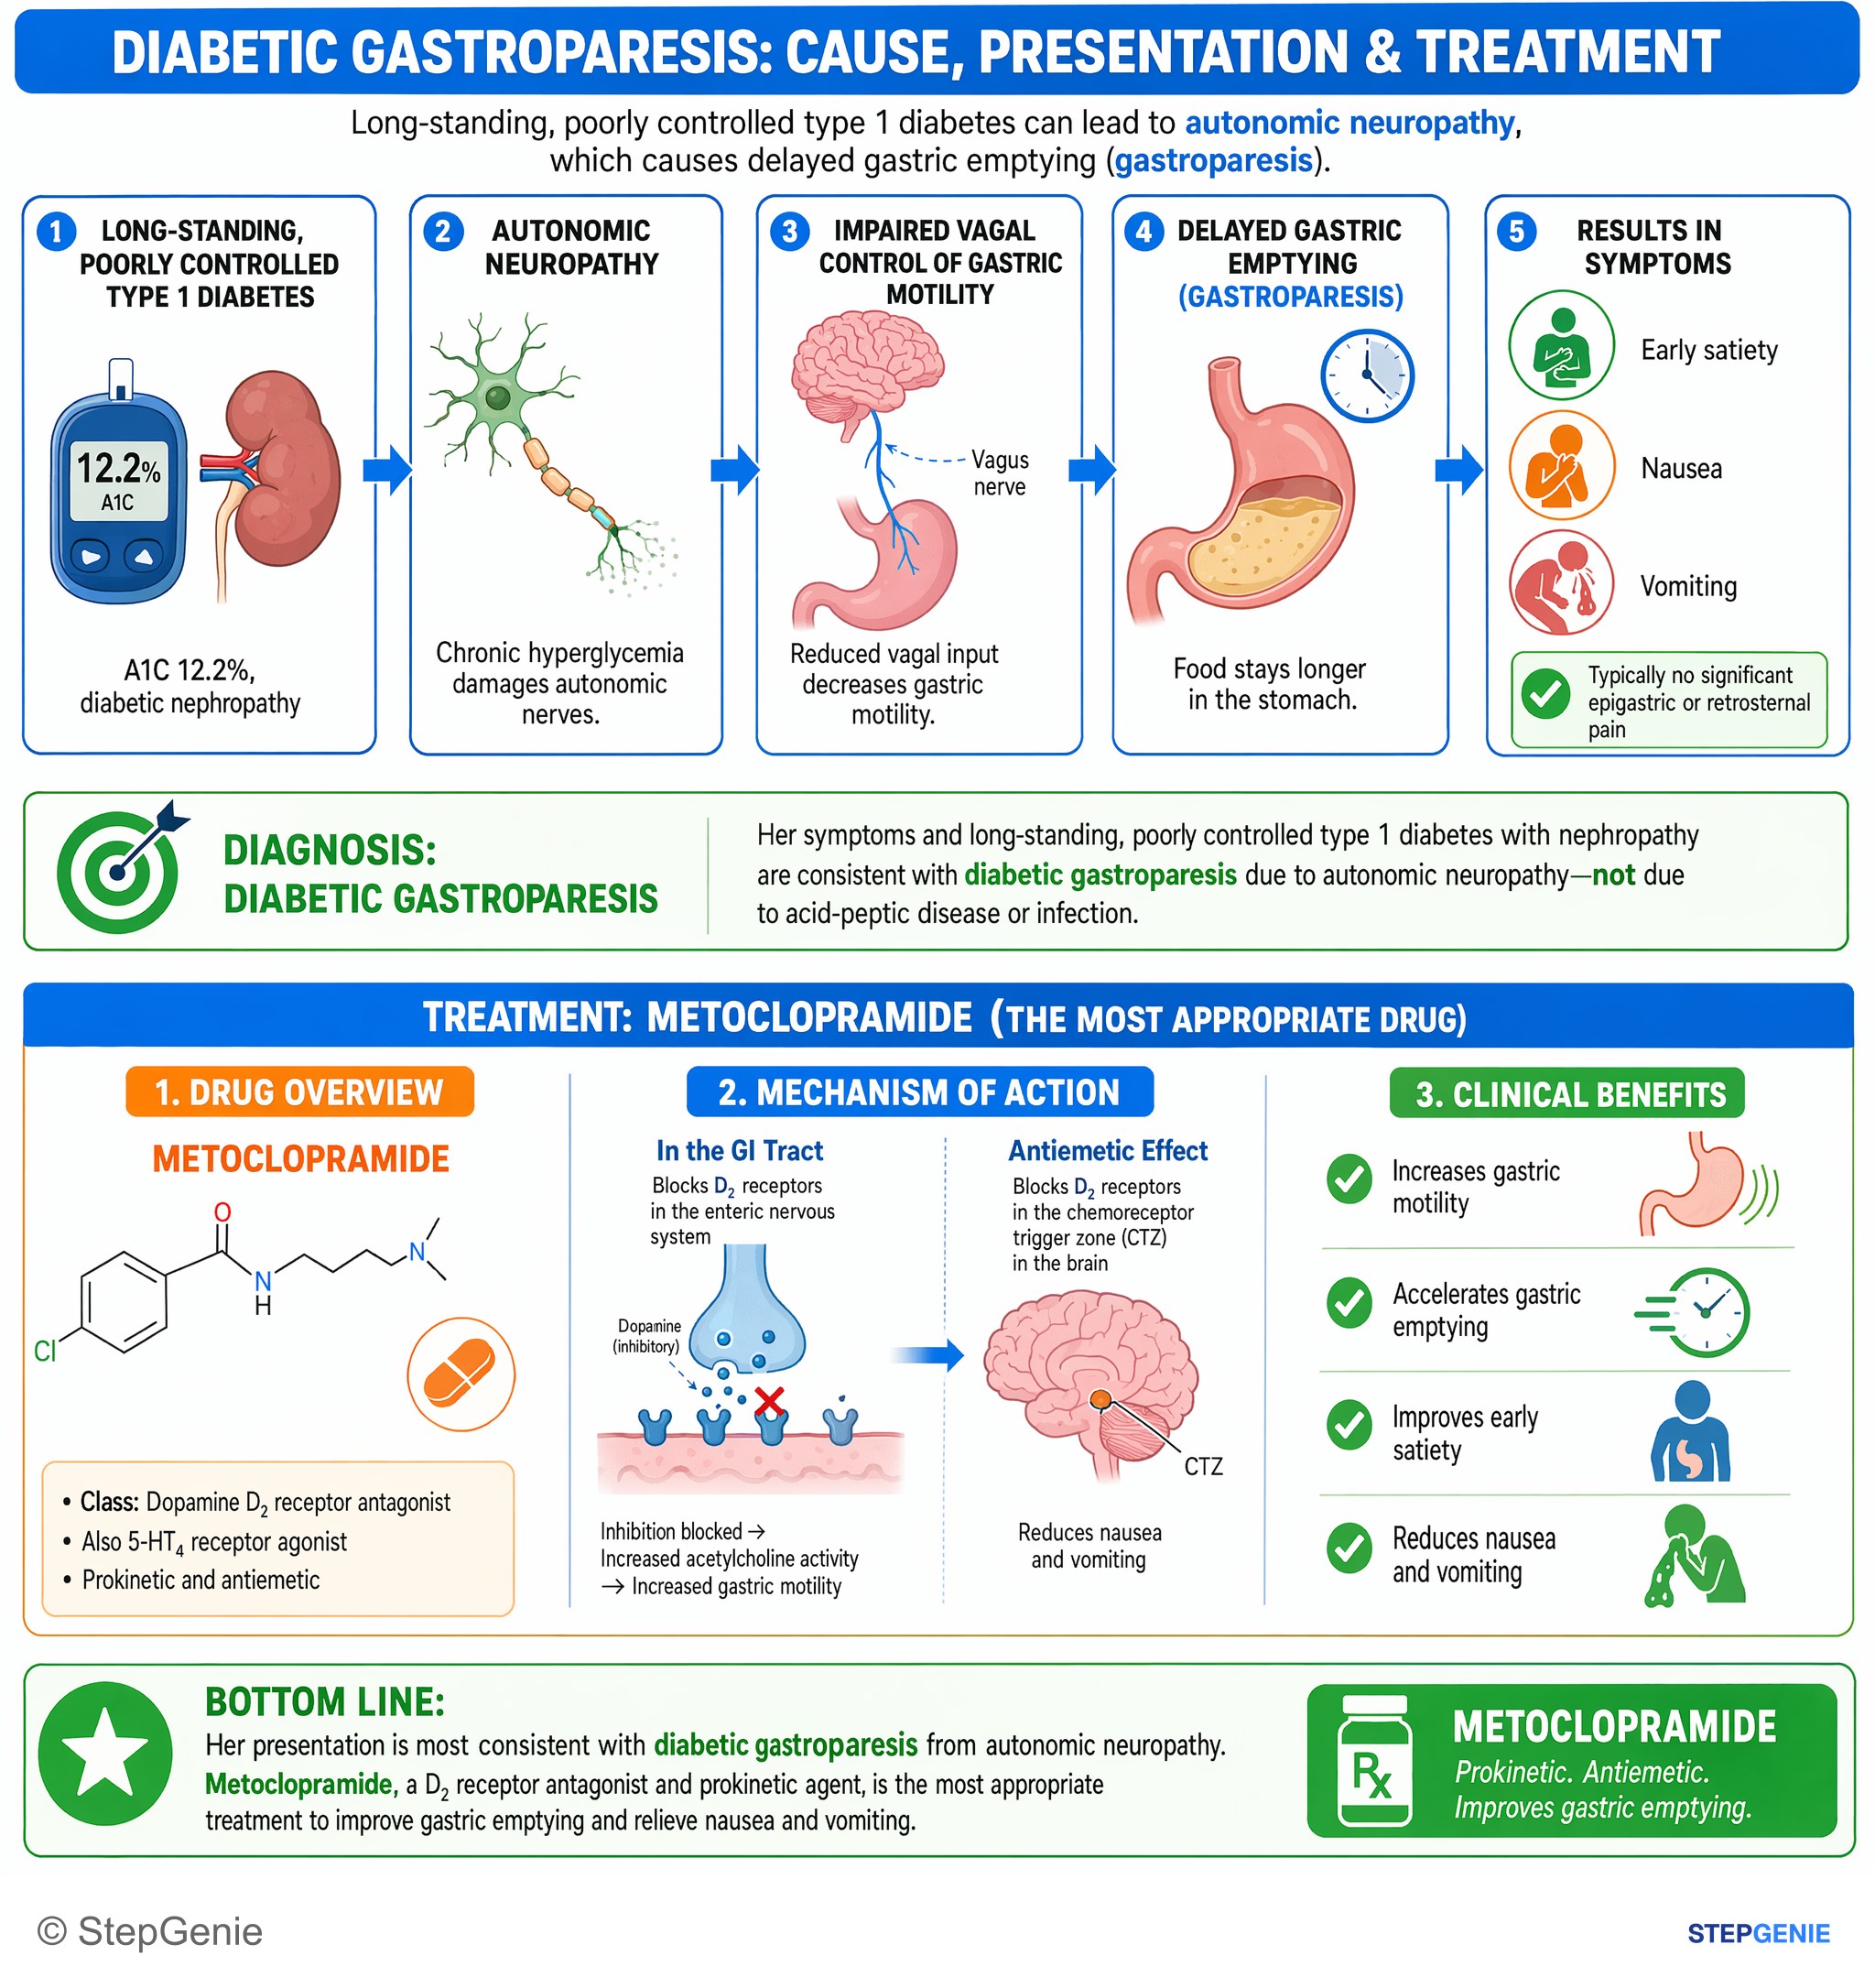
Diabetic gastroparesis from autonomic neuropathy causes early satiety, nausea, vomiting; treat with metoclopramide (D2 antagonist…
USMLE Step 2Frequently Asked Questions
What is the mechanism of action of metoclopramide in diabetic gastroparesis?
Metoclopramide primarily works by antagonizing dopamine D2 receptors. It also activates 5-HT4 receptors, which contributes to its prokinetic effect, and at higher doses it can block 5-HT3 receptors. By blocking dopamine in the GI tract, it increases acetylcholine release in enteric neurons, which enhances gastric motility and helps improve delayed gastric emptying.
Why does metoclopramide increase gastric emptying and lower esophageal sphincter tone?
Metoclopramide increases gastric emptying and lower esophageal sphincter tone because dopamine blockade in the GI tract increases acetylcholine release in enteric neurons. That increase in cholinergic activity enhances motility. The net physiologic effects are increased gastric emptying, increased LES tone, and increased small intestinal transit, with relatively minimal effect on colonic motility.
How do you recognize diabetic gastroparesis on a question stem?
Diabetic gastroparesis is suggested by long-standing diabetes plus early satiety, postprandial nausea, bloating, and intermittent non-bilious vomiting. Symptoms are often worse after meals, especially large or fatty meals. A delayed gastric emptying study confirms the diagnosis. The underlying cause is classically autonomic neuropathy affecting gastric motility.
What adverse effects of metoclopramide are most high-yield for exams?
The most tested adverse effects of metoclopramide are extrapyramidal symptoms, tardive dyskinesia, and hyperprolactinemia. Because it crosses the blood-brain barrier and blocks dopamine centrally, it can cause acute dystonia, akathisia, or parkinsonism. It can also raise prolactin because dopamine normally inhibits prolactin release, leading to galactorrhea, amenorrhea, or sexual dysfunction.
How do you tell metoclopramide apart from PPIs and H2 blockers in GI pharmacology questions?
Metoclopramide improves motility, whereas PPIs and H2 blockers reduce acid secretion. In a stem about delayed gastric emptying or increased lower esophageal sphincter tone, metoclopramide fits because it is a prokinetic and antiemetic. PPIs inhibit the H+/K+ ATPase and H2 blockers antagonize histamine H2 receptors, but neither corrects the motility problem of gastroparesis.