Octreotide is a long-acting somatostatin analog, a cyclic octapeptide that binds mainly SSTR2 and SSTR5 and switches off hormone release (growth hormone, insulin, glucagon, TSH, serotonin, gastrin, VIP and more) while reducing splanchnic blood flow. Its FDA-labeled uses are acromegaly, the diarrhea and flushing of metastatic carcinoid tumors, and VIPoma diarrhea; in practice it is also given for acute variceal bleeding and sulfonylurea-induced hypoglycemia. The side effects follow from shutting everything down: gallstones and sludge, steatorrhea and GI upset, high or low glucose, bradycardia and hypothyroidism.
Mnemonic part 1: the octopus closes the CAVES (uses)
Picture an octopus (OCTreotide, an octapeptide) sealing the mouths of five caves, each pouring out something the body makes too much of.
| Letter | Use | Why octreotide works | Stem clue |
|---|---|---|---|
| C | Carcinoid syndrome | Suppresses serotonin and other tumor products; the label covers the severe diarrhea and flushing of metastatic carcinoid tumors | Flushing, diarrhea, wheezing, right-sided valve disease, liver metastases |
| A | Acromegaly | Lowers GH and IGF-1 | IGF-1 typically 3 to 10 times normal, GH not suppressed by oral glucose; surgery comes first |
| V | VIPoma | Suppresses VIP; the label covers the profuse watery diarrhea of VIP-secreting tumors | Watery diarrhea, hypokalemia, achlorhydria |
| E | Esophageal varices (acute bleeding) | Raises splanchnic vascular resistance by blocking release of splanchnic vasodilator hormones (Merck) | Cirrhosis with hematemesis; given with band ligation and antibiotics |
| S | Sulfonylurea overdose | Suppresses insulin secretion | Severe hypoglycemia after a sulfonylurea; given along with dextrose (Merck) |
The first three are FDA-labeled indications; variceal bleeding and sulfonylurea overdose are off-label uses that Merck includes in its treatment recommendations.
Mnemonic part 2: the 5 S's of side effects
Somatostatin is the body's "stop" signal, so the side effects are things that stop or slow down. Figures below are from the Sandostatin label: the biliary numbers come from trials mainly in acromegaly or psoriasis, the others from patients with acromegaly.
| S | Side effect | Mechanism and numbers |
|---|---|---|
| Stones | Gallstones, sludge; cholecystitis, cholangitis, biliary obstruction | Less gallbladder contraction and bile secretion; biliary abnormalities in 63% (27% gallstones, 24% sludge, 12% duct dilation) |
| Steatorrhea | Diarrhea, loose stools, nausea, abdominal discomfort, fat malabsorption | Reversible inhibition of pancreatic enzyme secretion; vitamin B12 can fall, so B12 monitoring is recommended |
| Sugar swings | Hypoglycemia or hyperglycemia | Shifts the balance of insulin, glucagon and GH; hypoglycemia 3%, hyperglycemia 16% |
| Slow heart | Sinus bradycardia, conduction abnormalities, arrhythmias | Bradycardia below 50/min in 25%; IV use may raise the risk of higher-degree AV block; beta-blocker doses may need adjusting |
| Sleepy thyroid | Hypothyroidism | Suppresses TSH secretion |
Also: pancreatitis, and lower cyclosporine levels because octreotide alters absorption of oral drugs. If complications of gallstones are suspected, the label says to stop the drug and treat. And the irony examiners like: the drug that treats secretory diarrhea can itself cause diarrhea and steatorrhea. Stone types and workup are in the cholelithiasis mnemonic.
Mechanism: one hormone that turns off many others
- Why an analog? Natural somatostatin has a plasma half-life of 1-3 minutes; octreotide's is 1.7-1.9 hours (label).
- Receptors: octreotide binds SSTR2 and SSTR5 with high affinity (Cancers, 2024); lanreotide's label gives it the same profile, with weaker binding to SSTR1, 3 and 4. More than 70% of neuroendocrine tumors express several SSTR subtypes, mainly SSTR2 and SSTR5 (NCI), which is why somatostatin analogs both treat and image these tumors.
- Targets: octreotide is a more potent inhibitor of GH, glucagon and insulin than somatostatin. It also inhibits serotonin, gastrin, VIP, secretin, motilin and pancreatic polypeptide, suppresses the LH response to GnRH, and decreases splanchnic blood flow (label).
| What it turns off | What you see |
|---|---|
| GH, and so IGF-1 | Acromegaly control |
| Serotonin and other tumor products | Carcinoid symptom control |
| VIP | VIPoma diarrhea control |
| Splanchnic vasodilator hormones | Less portal inflow in variceal bleeding |
| Insulin | Treats sulfonylurea hypoglycemia; can cause hyperglycemia |
| Glucagon and GH (counter-regulatory hormones) | Can cause hypoglycemia |
| TSH | Hypothyroidism |
| Pancreatic enzymes | Steatorrhea |
| Gallbladder contraction, bile secretion | Stones and sludge |
Formulations
| Form | Route and schedule | Key rule |
|---|---|---|
| Octreotide injection (Sandostatin) | SC or IV, short-acting | Acute uses such as variceal bleeding (IV bolus, then infusion); short-acting rescue doses |
| Octreotide LAR depot (Sandostatin LAR) | IM into the gluteal muscle every 4 weeks | Only for patients who have responded to and tolerated SC octreotide; never IV or SC |
| Oral octreotide (Mycapssa delayed-release capsules) | Twice daily on an empty stomach, at least 1 hour before or 2 hours after a meal | Long-term acromegaly maintenance after response to octreotide or lanreotide; PPIs, H2 blockers and antacids lower its bioavailability, so higher doses may be needed |
Related drugs: lanreotide, pasireotide and friends
| Drug | What it is | Key facts |
|---|---|---|
| Lanreotide (Somatuline Depot) | Somatostatin analog (high affinity for SSTR2 and SSTR5), deep SC injection every 4 weeks | Acromegaly; unresectable, well- or moderately differentiated, locally advanced or metastatic GEP-NETs; carcinoid syndrome, where it reduces short-acting rescue use |
| Pasireotide (Signifor LAR) | Binds 4 of the 5 SSTRs, with the highest affinity for SSTR5 | Acromegaly and Cushing disease; frequent, sometimes severe hyperglycemia: diabetes prevalence rose from 30% to 60% by month 12 in drug-naive acromegaly patients, so glucose is checked weekly for the first 3 months |
| Pegvisomant | GH receptor antagonist, daily SC injection | Lowers IGF-1 but does not lower GH or act on the pituitary tumor (Merck) |
| Lutetium Lu 177 dotatate (Lutathera) | Radiolabeled somatostatin analog for SSTR-positive GEP-NETs | Stop long-acting analogs at least 4 weeks before starting and short-acting octreotide at least 24 hours before each dose |
| Octreotide scintigraphy | Radiolabeled octreotide to localize tumors | Reported sensitivity for carcinoid tumors up to 90% (NCI) |
Acromegaly drug sequencing sits in the pituitary adenoma guide.
How USMLE tests it: the traps
- Carcinoid syndrome usually means liver metastases. The liver normally breaks down the vasoactive amines, so the syndrome usually needs hepatic metastases, whose products reach the systemic circulation directly. Screen with 24-hour urinary 5-HIAA; carcinoid heart disease mainly damages the right-sided tricuspid and pulmonic valves (NCI); the classic exam pairing is tricuspid regurgitation with pulmonic stenosis.
- VIPoma = watery diarrhea, hypokalemia, achlorhydria (WDHA, Verner-Morrison syndrome). Contrast gastrinoma: Zollinger-Ellison syndrome brings peptic ulcers, diarrhea and gastric hyperacidity.
- Acromegaly: pituitary surgery is first-line; somatostatin analogs come next. Pegvisomant lowers IGF-1 but does not lower GH or shrink the tumor; pasireotide brings hyperglycemia.
- Cushing disease is a pasireotide indication, not an octreotide one.
- Acute variceal bleeding: octreotide plus endoscopic band ligation plus antibiotic prophylaxis (ceftriaxone or norfloxacin); TIPS if bleeding persists. Octreotide has fewer adverse effects than vasopressin or terlipressin. Nonselective beta-blockers are for prevention, not the acute bleed (Merck). Review the full sequence in cirrhosis and portal hypertension.
- Sulfonylurea overdose: octreotide is given with dextrose, not instead of it (see oral hypoglycemics).
- Long-term octreotide plus postprandial right upper quadrant pain = gallstones.
- LAR depot is never given IV or SC.
Practice question
A 61-year-old man has had episodic facial flushing, watery diarrhea and wheezing for a year. CT shows a small ileal mass and multiple liver lesions, and 24-hour urinary 5-HIAA is elevated. He starts long-acting octreotide every 4 weeks, and his symptoms improve. Ten months later he reports right upper quadrant pain after fatty meals. Which effect of his treatment best explains the new symptom?
A. Cholelithiasis from reduced gallbladder contraction B. Peptic ulcer from increased gastrin release C. Acute pancreatitis from increased pancreatic enzyme secretion D. Hypothyroidism from TSH suppression E. Sinus bradycardia from slowed conduction
Answer: A. Octreotide inhibits gallbladder contractility and bile secretion, so stones and sludge are its classic long-term complication (biliary abnormalities in 63% of patients in the label's trials, mostly people with acromegaly or psoriasis). Pain in the right upper quadrant after fatty meals in this setting points to biliary colic.
- B: octreotide inhibits gastrin, so it lowers acid rather than causing ulcers.
- C: pancreatitis is reported with octreotide, including as a complication of gallstones, but the drug reduces pancreatic enzyme secretion; that is why it causes steatorrhea.
- D: a true side effect, but hypothyroidism does not cause meal-related right upper quadrant pain.
- E: also a true side effect, but bradycardia does not cause right upper quadrant pain.
Key takeaways
- Octreotide = somatostatin analog that binds mainly SSTR2 and SSTR5, with a half-life of hours instead of minutes.
- CAVES uses: Carcinoid syndrome, Acromegaly, VIPoma (all FDA-labeled), Esophageal varices, Sulfonylurea overdose (off-label).
- 5 S's of side effects: Stones, Steatorrhea, Sugar swings, Slow heart, Sleepy thyroid; also low B12, pancreatitis and lower cyclosporine levels.
- Formulations: SC or IV injection; monthly IM LAR depot (never IV or SC); twice-daily oral capsules for acromegaly maintenance.
- Relatives: lanreotide (acromegaly, GEP-NETs, carcinoid syndrome); pasireotide (SSTR5, acromegaly and Cushing disease, hyperglycemia); pegvisomant blocks the GH receptor instead.
- In variceal bleeding, octreotide joins band ligation and antibiotics; beta-blockers are for prevention.
Sources
- Sandostatin (Octreotide Acetate) Injection Prescribing Information — DailyMed, NLM (2026)
- Sandostatin LAR Depot Prescribing Information — DailyMed, NLM (2025)
- Mycapssa (Octreotide) Delayed-Release Capsules Prescribing Information — DailyMed, NLM (2025)
- Somatuline Depot (Lanreotide) Prescribing Information — DailyMed, NLM (2024)
- Signifor LAR (Pasireotide) Prescribing Information — DailyMed, NLM (2024)
- Lutathera (Lutetium Lu 177 Dotatate) Prescribing Information — DailyMed, NLM (2026)
- Gigantism and Acromegaly — Merck Manual Professional Edition (2025)
- Varices — Merck Manual Professional Edition (2025)
- Hypoglycemia — Merck Manual Professional Edition (2025)
- Gastrointestinal Neuroendocrine Tumors Treatment (PDQ), Health Professional Version — National Cancer Institute (2026)
- Pancreatic Neuroendocrine Tumors (Islet Cell Tumors) Treatment (PDQ), Health Professional Version — National Cancer Institute (2025)
- The Role of Receptor-Ligand Interaction in Somatostatin Signaling Pathways: Implications for Neuroendocrine Tumors — Cancers (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
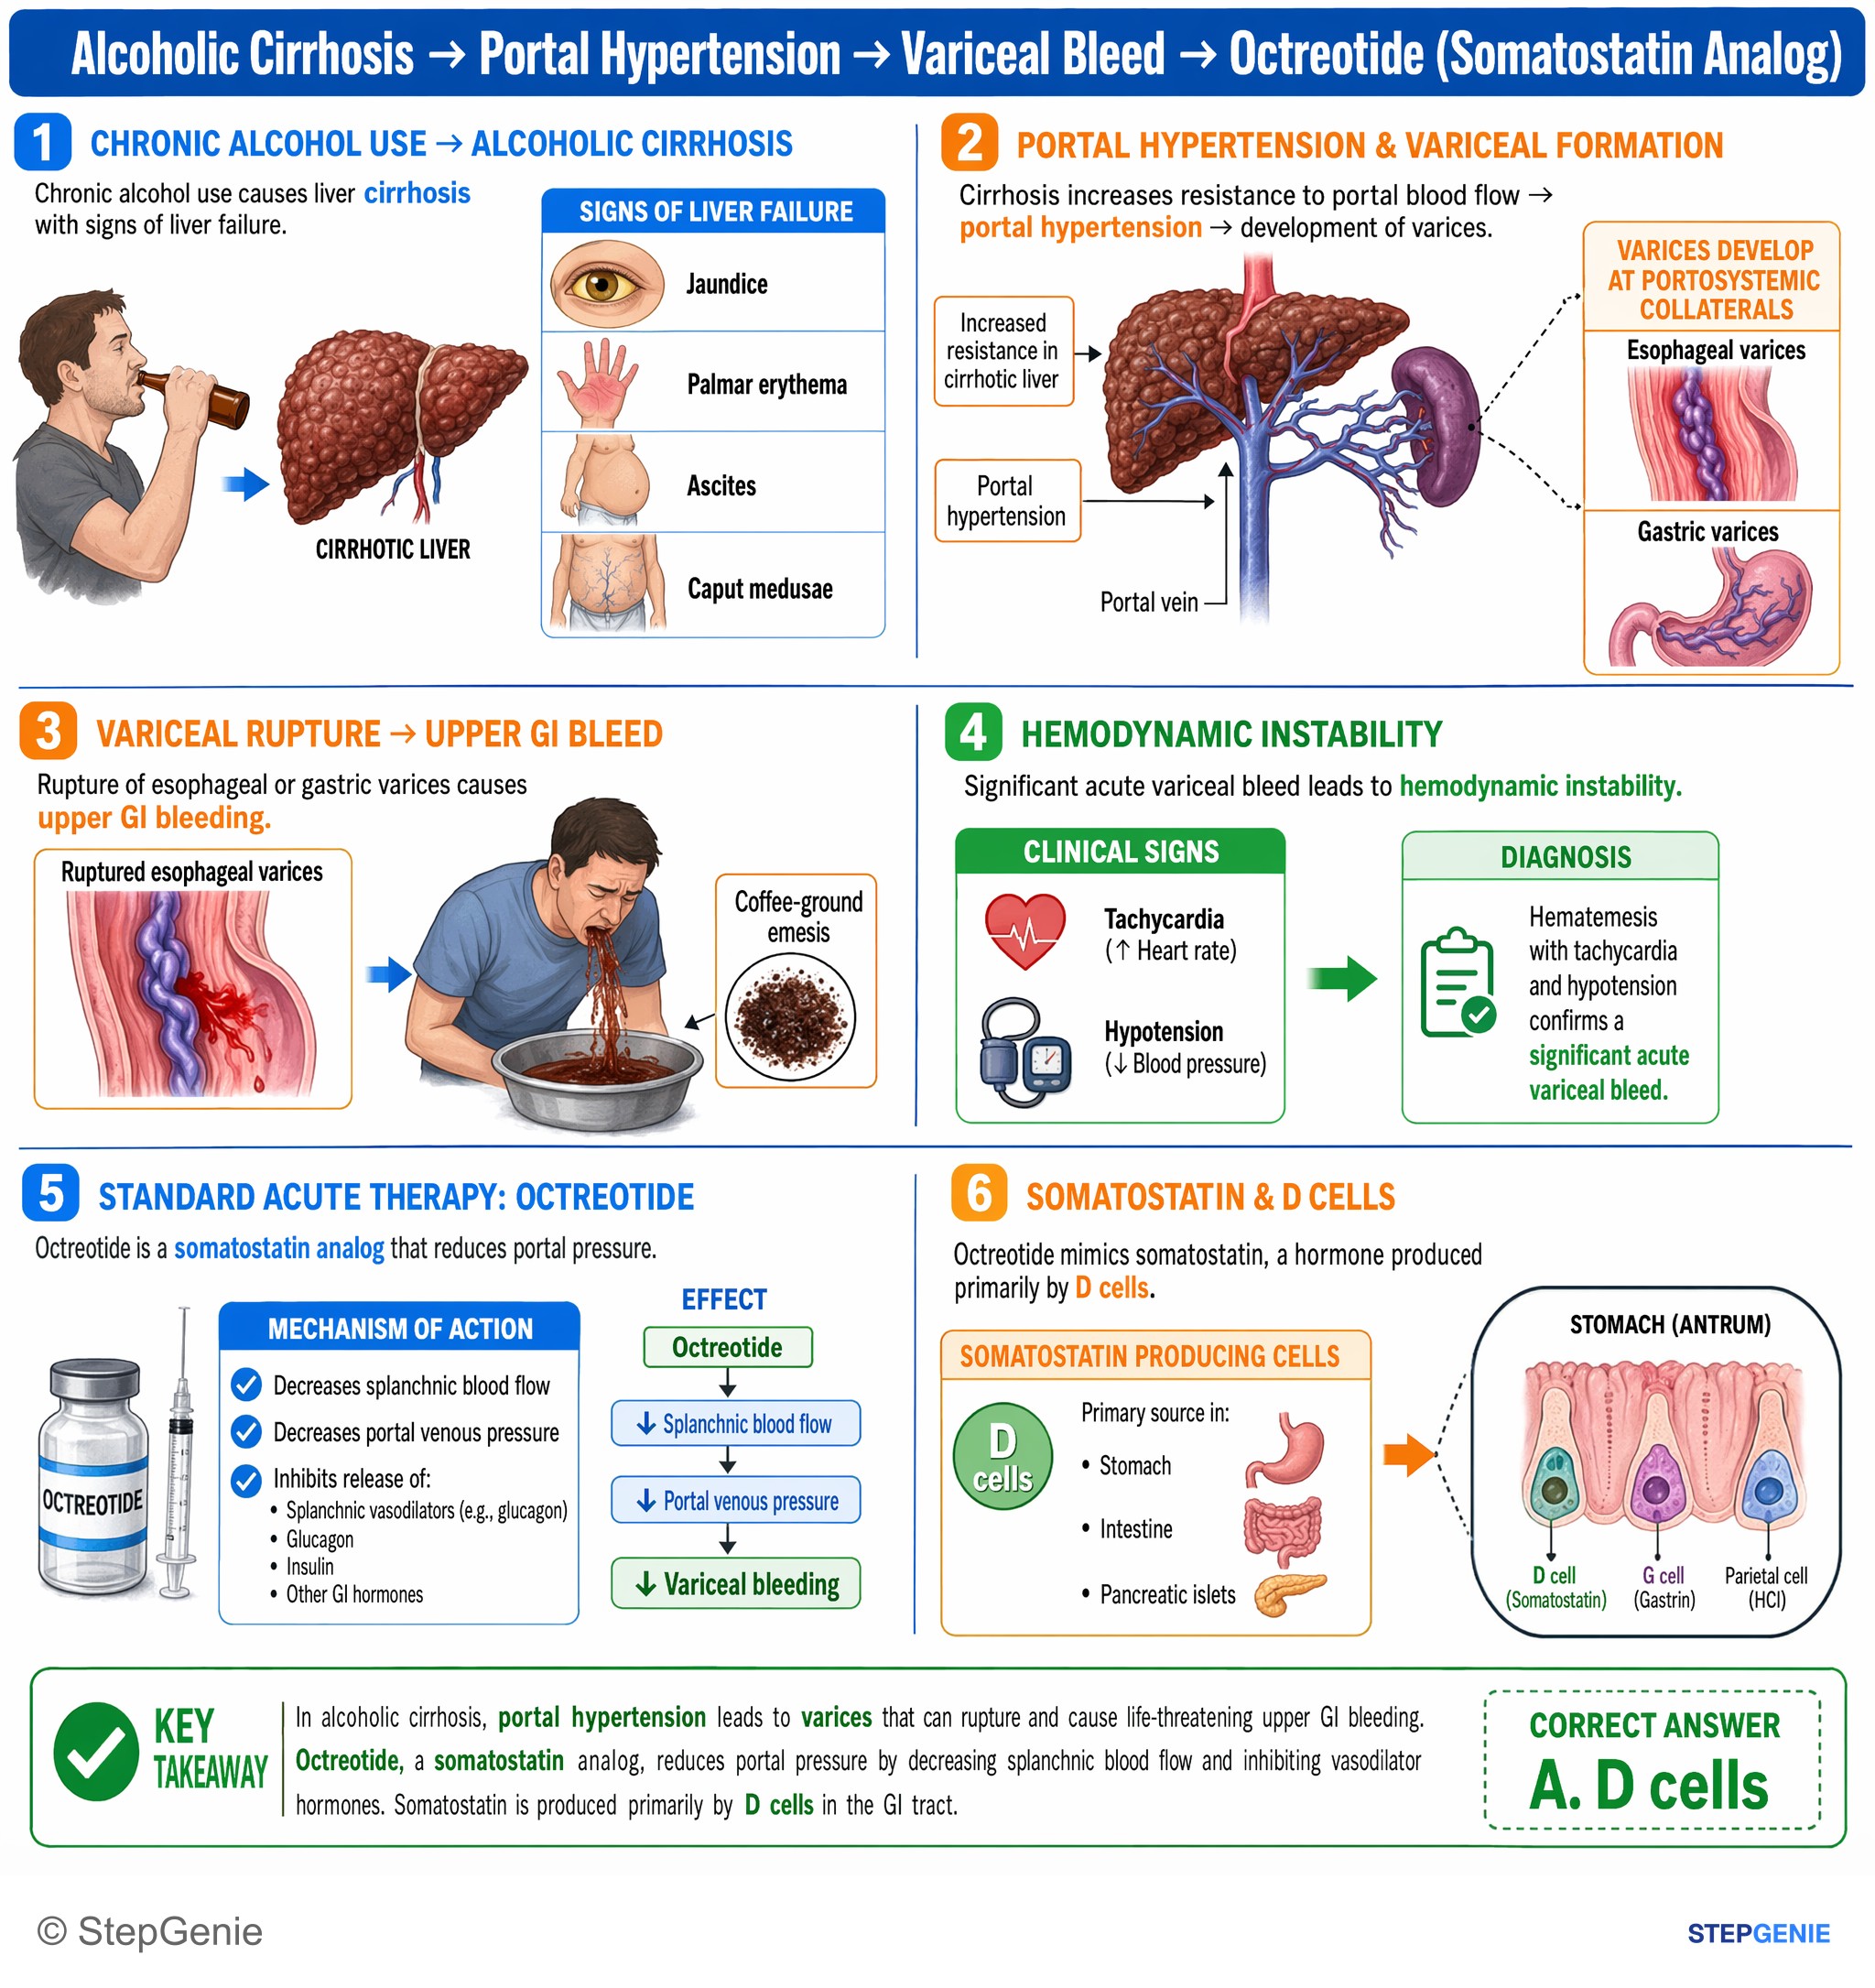
Esophageal variceal bleed in cirrhosis treated with octreotide, a somatostatin analog synthesized primarily by gastric D cells.
USMLE Step 1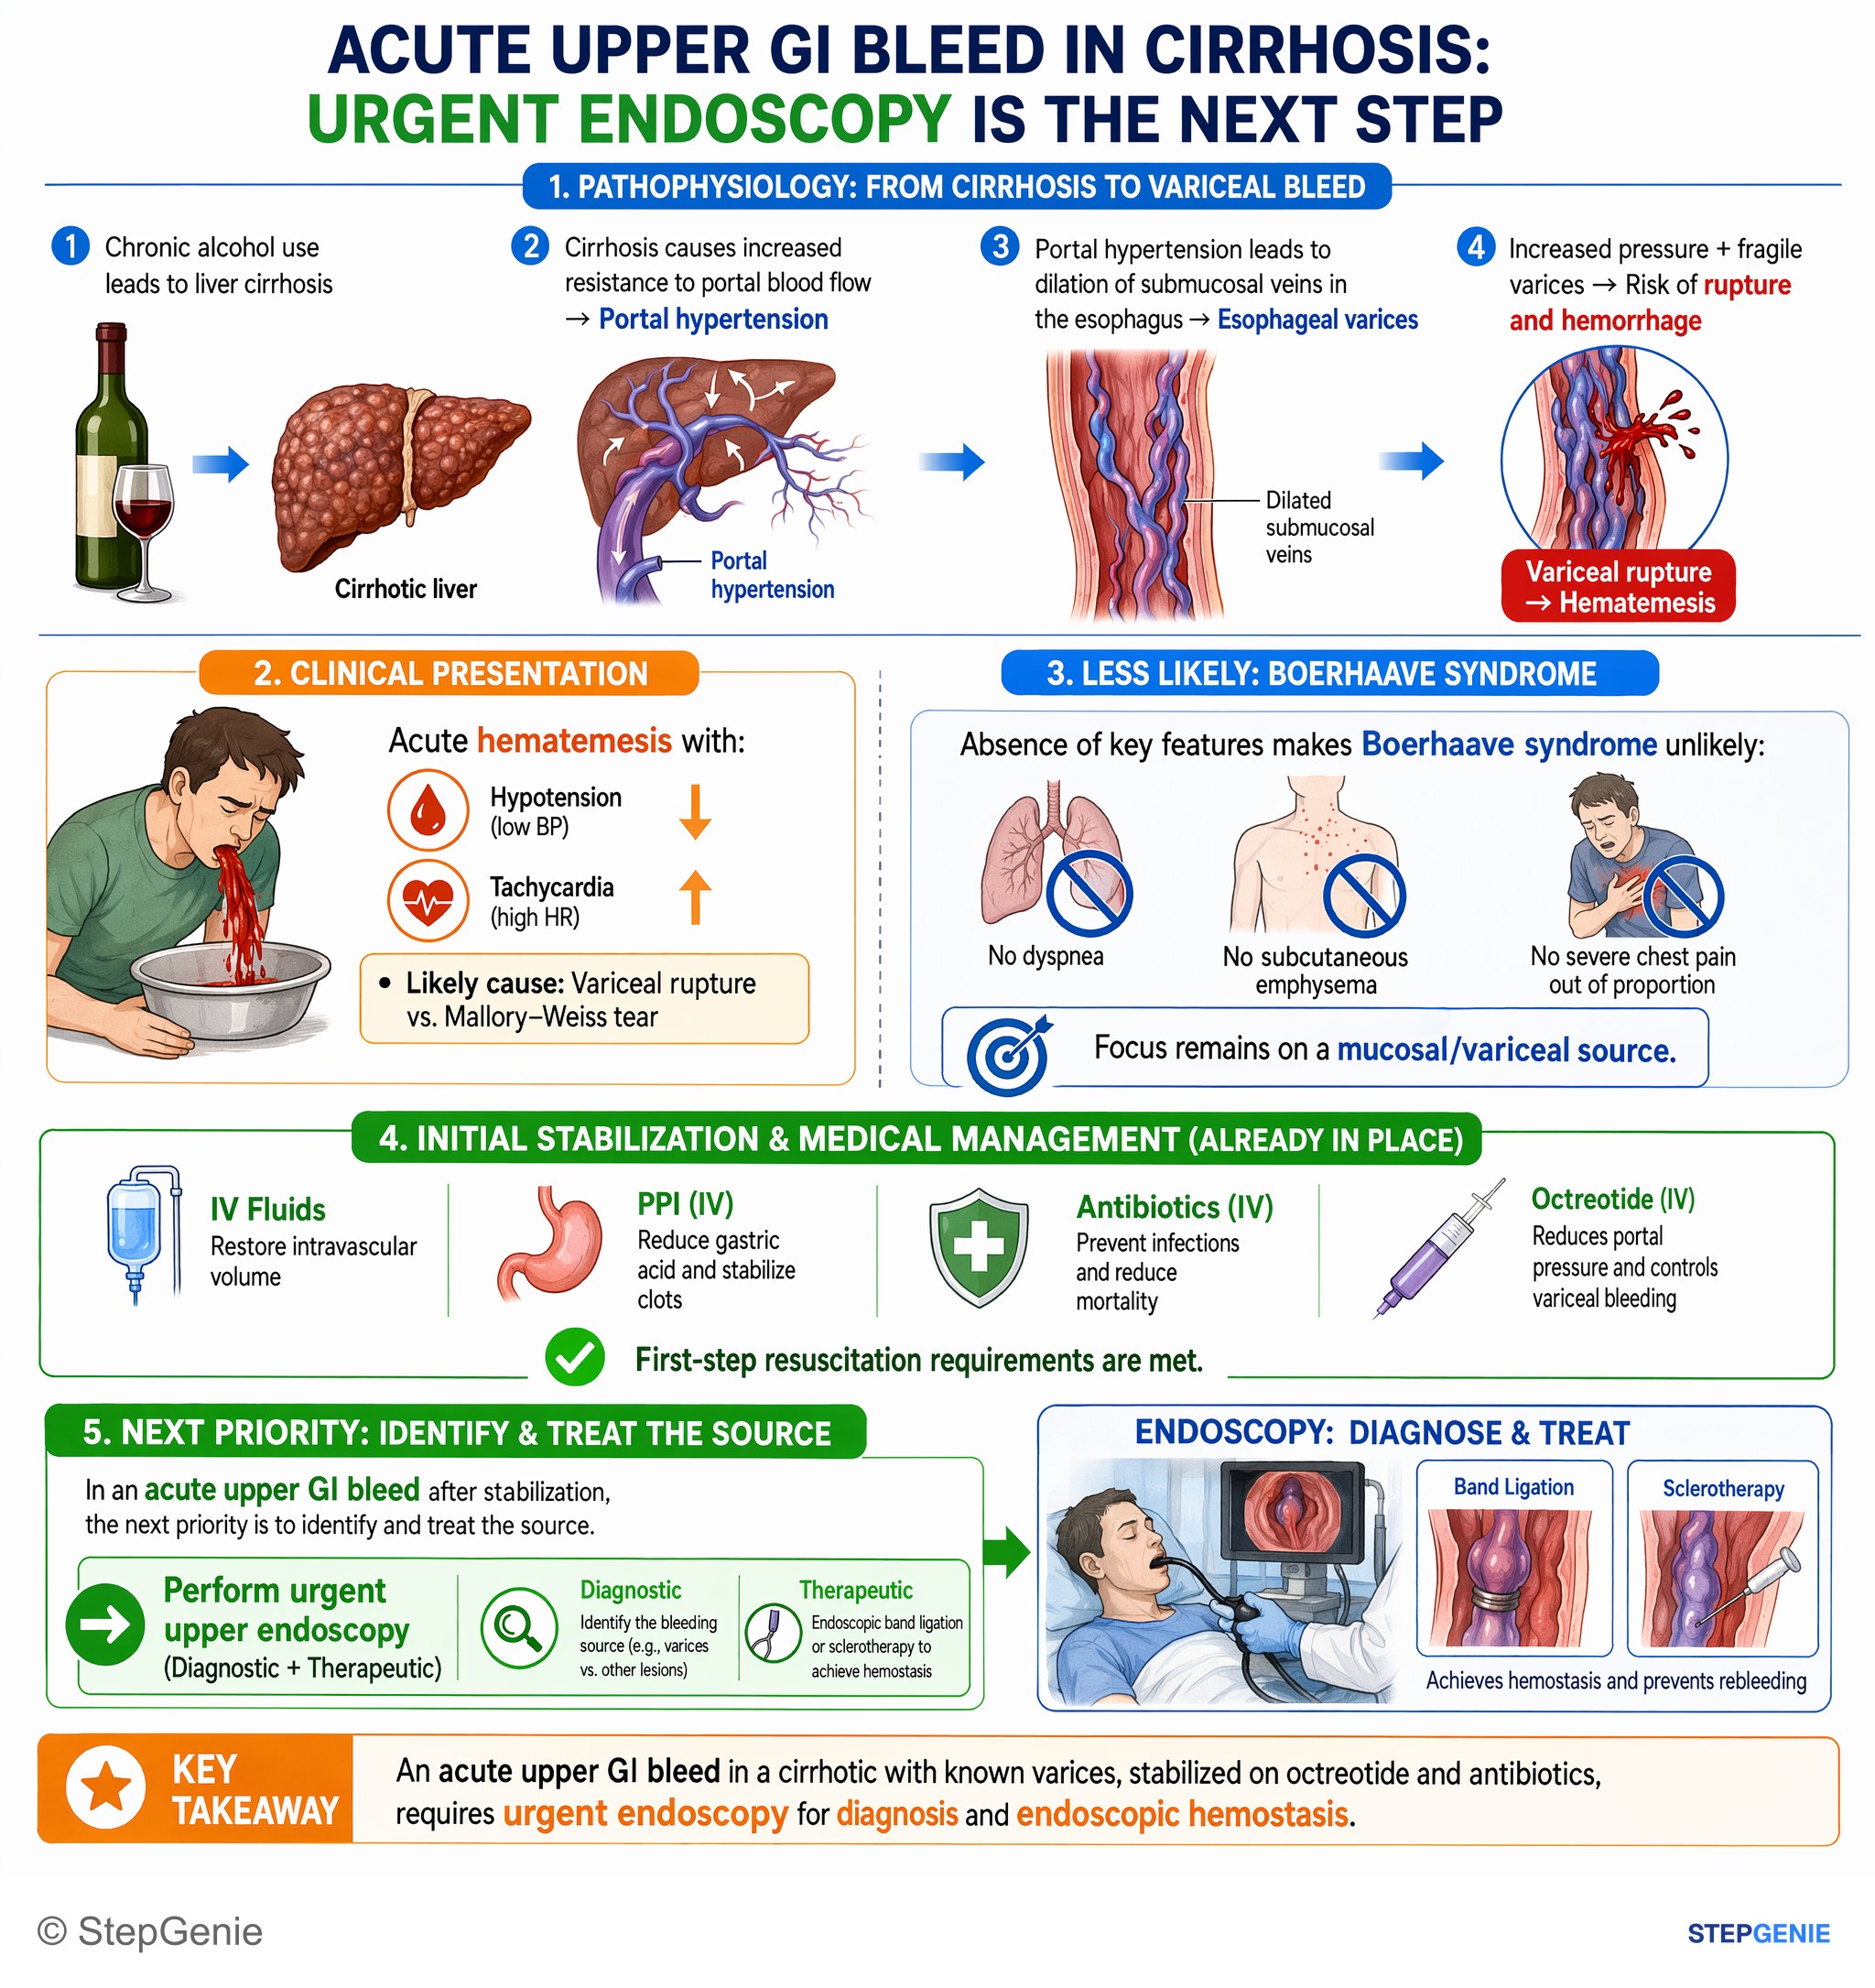
Acute upper GI bleed in a cirrhotic with varices stabilized on octreotide/ABX requires urgent endoscopy for diagnosis and endoscopic…
USMLE Step 2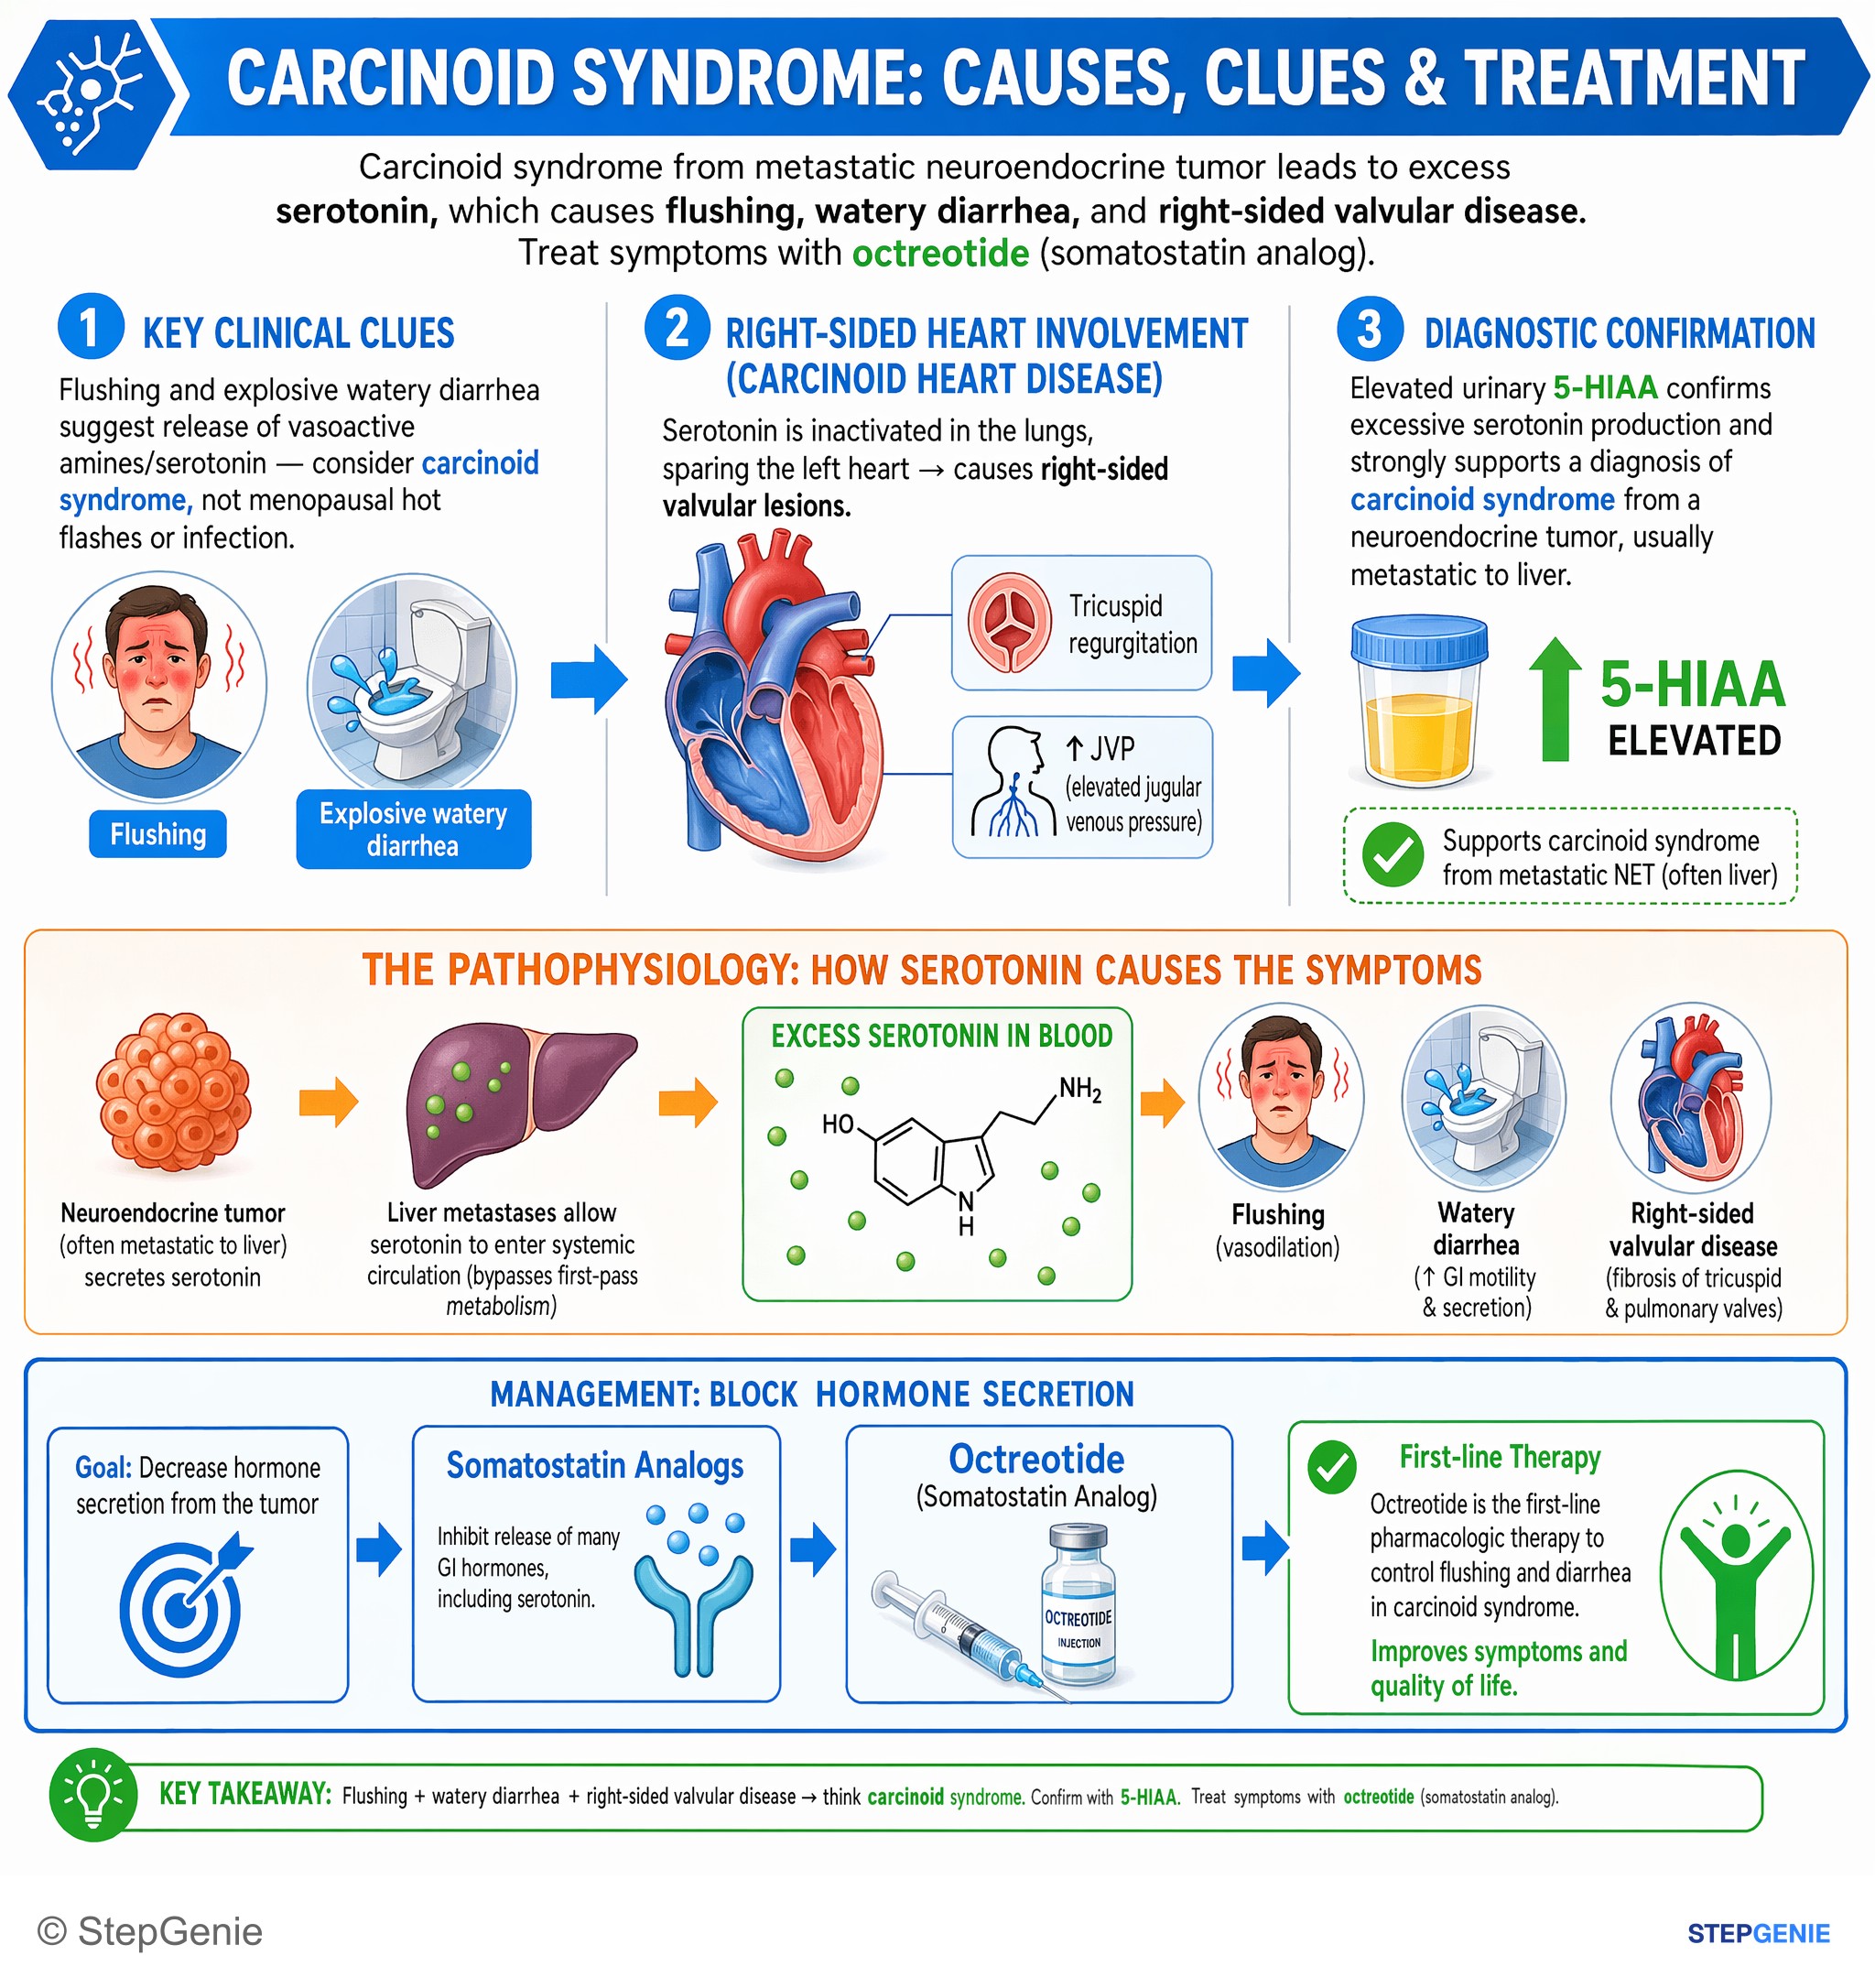
Carcinoid syndrome from metastatic neuroendocrine tumor → excess serotonin → flushing, watery diarrhea, right-sided valvular disease…
USMLE Step 2Frequently Asked Questions
What is octreotide's mechanism of action?
Octreotide is a synthetic, long-acting analog of somatostatin, the body's inhibitory hormone. It binds somatostatin receptors, mainly SSTR2 and SSTR5, and suppresses release of growth hormone, insulin, glucagon, TSH, serotonin, gastrin, VIP, secretin and other gut peptides. It also reduces splanchnic blood flow. Its half-life is about 1.7 to 1.9 hours, compared with 1 to 3 minutes for natural somatostatin, which is why the analog is used clinically.
What is octreotide used for?
Octreotide's FDA-labeled uses are acromegaly, to lower GH and IGF-1, the severe diarrhea and flushing of metastatic carcinoid tumors, and the watery diarrhea of VIP-secreting tumors (VIPomas). It is also used off-label for acute esophageal variceal bleeding, together with band ligation and antibiotics, and for severe sulfonylurea-induced hypoglycemia, where it suppresses insulin release and is given with dextrose. The mnemonic CAVES covers all five: carcinoid, acromegaly, VIPoma, esophageal varices, sulfonylureas.
What are the side effects of octreotide?
Remember the 5 S's: stones (gallstones and sludge, because gallbladder contraction and bile secretion fall), steatorrhea and other GI upset from reduced pancreatic enzyme secretion, sugar swings (hypoglycemia or hyperglycemia), slow heart (sinus bradycardia and conduction abnormalities) and sleepy thyroid (hypothyroidism from TSH suppression). The label also warns about pancreatitis and low vitamin B12 levels, and octreotide can lower cyclosporine levels by altering absorption of oral drugs.
Why does octreotide cause gallstones?
Octreotide inhibits gallbladder contractility and decreases bile secretion, so bile stagnates and forms sludge and stones. In Sandostatin clinical trials, mainly in patients with acromegaly or psoriasis, 63% developed biliary tract abnormalities, including gallstones in 27% and sludge in 24%. Acute cholecystitis, ascending cholangitis, biliary obstruction and pancreatitis have been reported, and the label advises stopping the drug if complications of gallstones are suspected.
How does octreotide help in variceal bleeding?
Octreotide increases splanchnic vascular resistance by inhibiting the release of splanchnic vasodilator hormones, which reduces blood flow into the portal system. In acute variceal bleeding it is given as an IV bolus followed by an infusion for 3 to 5 days after endoscopy, together with endoscopic band ligation and antibiotic prophylaxis. It has fewer adverse effects than vasopressin or terlipressin. Nonselective beta-blockers are used for prevention, not for the acute bleed.
What is the difference between octreotide, lanreotide and pasireotide?
All three are somatostatin analogs. Octreotide comes as a short-acting SC or IV injection, a monthly intramuscular LAR depot and oral capsules for acromegaly maintenance. Lanreotide is a deep subcutaneous injection every 4 weeks for acromegaly, gastroenteropancreatic neuroendocrine tumors and carcinoid syndrome. Pasireotide binds four of the five receptor subtypes, with the highest affinity for SSTR5, is approved for acromegaly and Cushing disease, and frequently causes hyperglycemia.