Proton pump inhibitors (PPIs: omeprazole, esomeprazole, lansoprazole, dexlansoprazole, pantoprazole and rabeprazole) are prodrugs that are activated by acid in the parietal cell's secretory canaliculi and then bind covalently, and irreversibly, to the H+/K+ ATPase, the final step of acid secretion. Because they can only bind pumps that are actively secreting, they work best taken 30-60 minutes before a meal, and acid suppression lasts until the cell makes new pumps. They are the backbone of treatment for GERD and erosive esophagitis, peptic ulcers and Zollinger-Ellison syndrome, and part of most H. pylori regimens. Current US labels warn about C. difficile diarrhea, hypomagnesemia, vitamin B12 deficiency, fractures and acute tubulointerstitial nephritis, and omeprazole and esomeprazole should be avoided with clopidogrel (CYP2C19 inhibition).
How PPIs work
Parietal cells in the gastric body make acid in response to three signals, all of which converge on one pump:
- Histamine from enterochromaffin-like (ECL) cells acts on H2 receptors; circulating gastrin triggers ECL cells to release histamine.
- Gastrin from antral G cells, released when food and vagal input arrive.
- Acetylcholine from vagal fibers, acting on muscarinic (M3) receptors.
- Brake: as antral pH falls, D cells release somatostatin, which inhibits gastrin release.
PPIs act downstream of all three stimuli, at the H+/K+ ATPase, so they suppress acid "irrespective of the stimulus" (pantoprazole label). The sequence that gets tested:
- The drug is given in an enteric-coated (delayed-release) form and absorbed in the proximal small bowel.
- From the blood it reaches the parietal cell, where acid-catalyzed cleavage in the acidic secretory canaliculi turns the prodrug into its active form.
- The active drug forms a covalent bond with the pump, inactivating that pump permanently.
- Acid secretion returns only as new pumps are synthesized, so one dose suppresses acid for more than 24 hours despite a short plasma half-life. PPIs are cleared by hepatic CYP enzymes, mostly CYP2C19.
Timing is part of the mechanism. PPIs bind only pumps that are actively secreting, and meals switch pumps on, so ACG (2022) recommends taking a PPI 30-60 minutes before a meal (usually breakfast) rather than at bedtime. Labels differ on the details: esomeprazole capsules say at least 1 hour before meals, while pantoprazole tablets may be taken with or without food. Full effect builds over several days, which is why PPIs are not for immediate heartburn relief.
PPIs vs other acid drugs
| PPIs | Vonoprazan (P-CAB) | H2 blockers | Antacids | |
|---|---|---|---|---|
| Target | H+/K+ ATPase, covalent, irreversible | H+/K+ ATPase, potassium-competitive, reversible | H2 receptor (competitive) | Neutralize acid already in the lumen |
| Needs acid activation? | Yes (prodrug); take before meals | No; taken with or without food | No | No |
| Onset and duration | Builds over days; more than 24 hours per dose | Antisecretory effect within 2-3 hours of a single dose | Onset 30-60 minutes; lasts 6-20 hours | Minutes; short |
| Typical use | GERD, erosive esophagitis, ulcers, H. pylori, Zollinger-Ellison | Erosive esophagitis, non-erosive GERD heartburn, H. pylori | Milder symptoms; as-needed bedtime add-on for nocturnal symptoms despite a PPI | Short-term symptom relief |
| Classic adverse effects | C. difficile, low Mg, low B12, fractures, AIN | Similar label warnings | Cimetidine: gynecomastia, CYP450 inhibition; confusion | Mg: diarrhea; Al: constipation, low phosphate; Ca carbonate and bicarbonate: alkalosis |
See the H2 blockers question breakdown for that class. Vonoprazan (Voquezna) is a potassium-competitive acid blocker (P-CAB) that binds the pump noncovalently and reversibly and, per its label, "does not require activation by acid." Its current label (revised 11/2025) approves it in adults to heal and maintain healing of all grades of erosive esophagitis, to relieve heartburn in non-erosive GERD, and with amoxicillin (with or without clarithromycin) for H. pylori. AGA (2024) says P-CABs should generally not be first-line for uninvestigated heartburn, non-erosive reflux or mild (LA grade A/B) esophagitis, may be used for severe (LA grade C/D) esophagitis, and should replace PPIs in most H. pylori regimens.
Clinical uses
GERD (ACG 2022). For classic heartburn and regurgitation without alarm features, give an 8-week empiric PPI trial, once daily before a meal. If symptoms respond, try to stop the PPI; if they don't, perform endoscopy, ideally after 2-4 weeks off the drug. Alarm symptoms (dysphagia, weight loss, GI bleeding) call for endoscopy. PPIs beat H2 blockers for healing and maintaining healing of erosive esophagitis, and LA grade C or D esophagitis needs maintenance PPI indefinitely or antireflux surgery. Practice with the GERD question breakdown.
Peptic ulcer disease. Merck's regimens: omeprazole 20 mg or lansoprazole 30 mg daily for 4 weeks for duodenal ulcers and 6-8 weeks for gastric ulcers. Esomeprazole is also labeled to reduce the risk of NSAID-associated gastric ulcers in at-risk patients; misoprostol is the prostaglandin alternative.
H. pylori (ACG 2024). The preferred first-line regimen is optimized bismuth quadruple therapy: PPI twice daily, bismuth, tetracycline and metronidazole. If susceptibility is unknown, alternatives are rifabutin triple therapy (omeprazole, amoxicillin, rifabutin) or vonoprazan-amoxicillin dual therapy; clarithromycin triple therapy is reserved for strains known to be susceptible. Confirm cure at least 4 weeks after treatment, and hold the PPI for 2 weeks before a urea breath test or stool antigen test to avoid false negatives. More in the H. pylori guide.
Zollinger-Ellison syndrome. A gastrinoma drives massive acid output with refractory or unusually located ulcers and diarrhea; high-dose PPI controls it (pantoprazole's label starts at 40 mg twice daily). PPIs themselves raise gastrin, which complicates the gastrin work-up: see the Zollinger-Ellison 5-second rule.
Stress ulcer prophylaxis. A PPI or H2 blocker for selected ICU patients, mainly those with coagulopathy, shock or chronic liver disease (Merck). Acid suppression may raise the risk of hospital-acquired pneumonia (although one large ICU trial found no increase), so it is not given to everyone.
Adverse effects: what the labels warn about
| Label warning | What to remember |
|---|---|
| C. difficile-associated diarrhea | Hospitalized patient on a PPI who develops watery diarrhea; use the lowest dose and shortest course that works |
| Hypomagnesemia | Rare; seen after at least 3 months, most after a year. Can cause tetany, arrhythmias and seizures, plus hypocalcemia and hypokalemia; treatment usually required magnesium replacement and stopping the PPI. Consider checking Mg with digoxin or diuretics |
| Vitamin B12 deficiency | Long-term daily acid suppression (e.g., more than 3 years); acid is needed to free B12 from food protein |
| Bone fracture | Hip, wrist and spine; linked to high-dose (multiple daily doses) and long-term (1 year or more) use |
| Acute tubulointerstitial nephritis | Can occur at any point during therapy; stop the PPI |
| Cutaneous and systemic lupus | Subacute cutaneous lupus is the most common form, weeks to years after starting |
| Severe cutaneous reactions | SJS/TEN, DRESS and AGEP; stop at the first sign |
| Fundic gland polyps | Risk rises with use beyond 1 year |
| Chromogranin A interference | Low acid raises gastrin and CgA, mimicking a neuroendocrine tumor; stop the PPI at least 14 days before testing |
| Masking gastric cancer | Symptom relief does not exclude malignancy |
Other testable points: long-term use raises gastrin and causes ECL cell hyperplasia, with no documented progression to malignancy (Merck); iron absorption falls; stopping after prolonged use can cause rebound acid hypersecretion, although ACG notes strong evidence of worse symptoms after abrupt withdrawal is lacking; and pantoprazole's label notes false-positive urine THC screens. Observational studies have linked PPIs to kidney disease, dementia and more, but ACG says they do not establish cause and effect, and Merck notes that a large randomized trial found more enteric infections but no increase in the other suspected harms.
Drug interactions
- Clopidogrel is a prodrug activated by CYP2C19. Omeprazole and esomeprazole inhibit CYP2C19, so their labels say to avoid the combination. Pantoprazole had no clinically important effect on clopidogrel's active metabolite in its label study, so it is the usual choice. Background: aspirin vs clopidogrel.
- Rilpivirine-containing HIV regimens are contraindicated with PPIs.
- High-dose methotrexate levels may rise; St. John's wort and rifampin lower PPI levels.
- Less acid means less absorption of drugs that need it, such as ketoconazole and iron salts. Omeprazole inhibits CYP2C19 and raises diazepam and phenytoin exposure, and INR rises have been reported when PPIs are given with warfarin, so monitor.
How USMLE tests PPIs
- "Take before breakfast" is the right counseling answer, not "at bedtime" or "with antacids."
- Final common pathway: PPIs block acid whatever the stimulus; H2 blockers block only the histamine signal, so their suppression is less complete.
- High gastrin on a PPI is expected (loss of acid-driven somatostatin); in suspected Zollinger-Ellison, gastrin must be read in the context of acid suppression.
- New watery diarrhea in a hospitalized patient on a PPI: C. difficile.
- Hypocalcemia or hypokalemia that won't correct: check magnesium.
- Stent patient on clopidogrel needing acid suppression: pantoprazole rather than omeprazole.
- Falsely negative H. pylori test: the patient was still taking a PPI.
Practice question
A 54-year-old man with erosive esophagitis has taken omeprazole 40 mg daily for 2 years, and his heartburn is controlled. Which laboratory change is most likely to be present as a direct result of this therapy?
A. Decreased serum chromogranin A B. Increased serum gastrin C. Increased serum magnesium D. Increased vitamin B12 absorption E. Decreased fasting gastric pH
Answer: B. Normally, acid in the antrum makes D cells release somatostatin, which restrains G cells. A PPI removes that acid, so the brake comes off and gastrin rises; chronic hypergastrinemia drives ECL cell hyperplasia.
- A: wrong direction. Chromogranin A rises with acid suppression, which is why labels advise stopping a PPI at least 14 days before measuring it.
- C: PPIs can cause hypomagnesemia (rarely, usually after a year), not high magnesium.
- D: long-term acid suppression reduces absorption of food-bound B12, because acid is needed to release it from protein.
- E: a PPI raises gastric pH; that is the whole point of therapy.
Key takeaways
- PPIs are acid-activated prodrugs that irreversibly block the H+/K+ ATPase, the final step of acid secretion; take them 30-60 minutes before a meal.
- Uses: GERD and erosive esophagitis (8-week empiric trial, then try to stop), peptic ulcers, H. pylori (bismuth quadruple first-line), Zollinger-Ellison (high dose) and selected stress ulcer prophylaxis.
- Label warnings: C. difficile, hypomagnesemia, B12 deficiency, fractures, acute tubulointerstitial nephritis, lupus, severe skin reactions and fundic gland polyps.
- Gastrin and chromogranin A rise on PPIs; hold them 14 days before chromogranin A and 2 weeks before H. pylori breath or stool tests.
- Avoid omeprazole and esomeprazole with clopidogrel; pantoprazole is preferred.
- Vonoprazan blocks the pump reversibly without acid activation; AGA favors it in most H. pylori regimens but generally not first-line for heartburn, non-erosive reflux or mild esophagitis.
Sources
- Medications for the Treatment of Gastric Acidity — Merck Manual Professional Edition (2025)
- Overview of Acid Secretion — Merck Manual Professional Edition (2025)
- Proton Pump Inhibitors (PPI) — StatPearls, NCBI Bookshelf (2023)
- Nexium (esomeprazole) Prescribing Information — DailyMed (2025)
- Protonix (pantoprazole) Prescribing Information — DailyMed (2023)
- Prilosec (omeprazole) Prescribing Information — DailyMed (2024)
- Voquezna (vonoprazan) Prescribing Information — DailyMed (2025)
- ACG Clinical Guideline for the Diagnosis and Management of Gastroesophageal Reflux Disease — American Journal of Gastroenterology (2022)
- ACG Guideline Highlights: Treatment of Helicobacter pylori Infection — American College of Gastroenterology (2024)
- AGA Clinical Practice Update on Integrating Potassium-Competitive Acid Blockers Into Clinical Practice — Gastroenterology (2024)
- Erosive Gastritis — Merck Manual Professional Edition (2025)
- Zollinger-Ellison Syndrome (Gastrinoma) — Merck Manual Professional Edition (2023)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
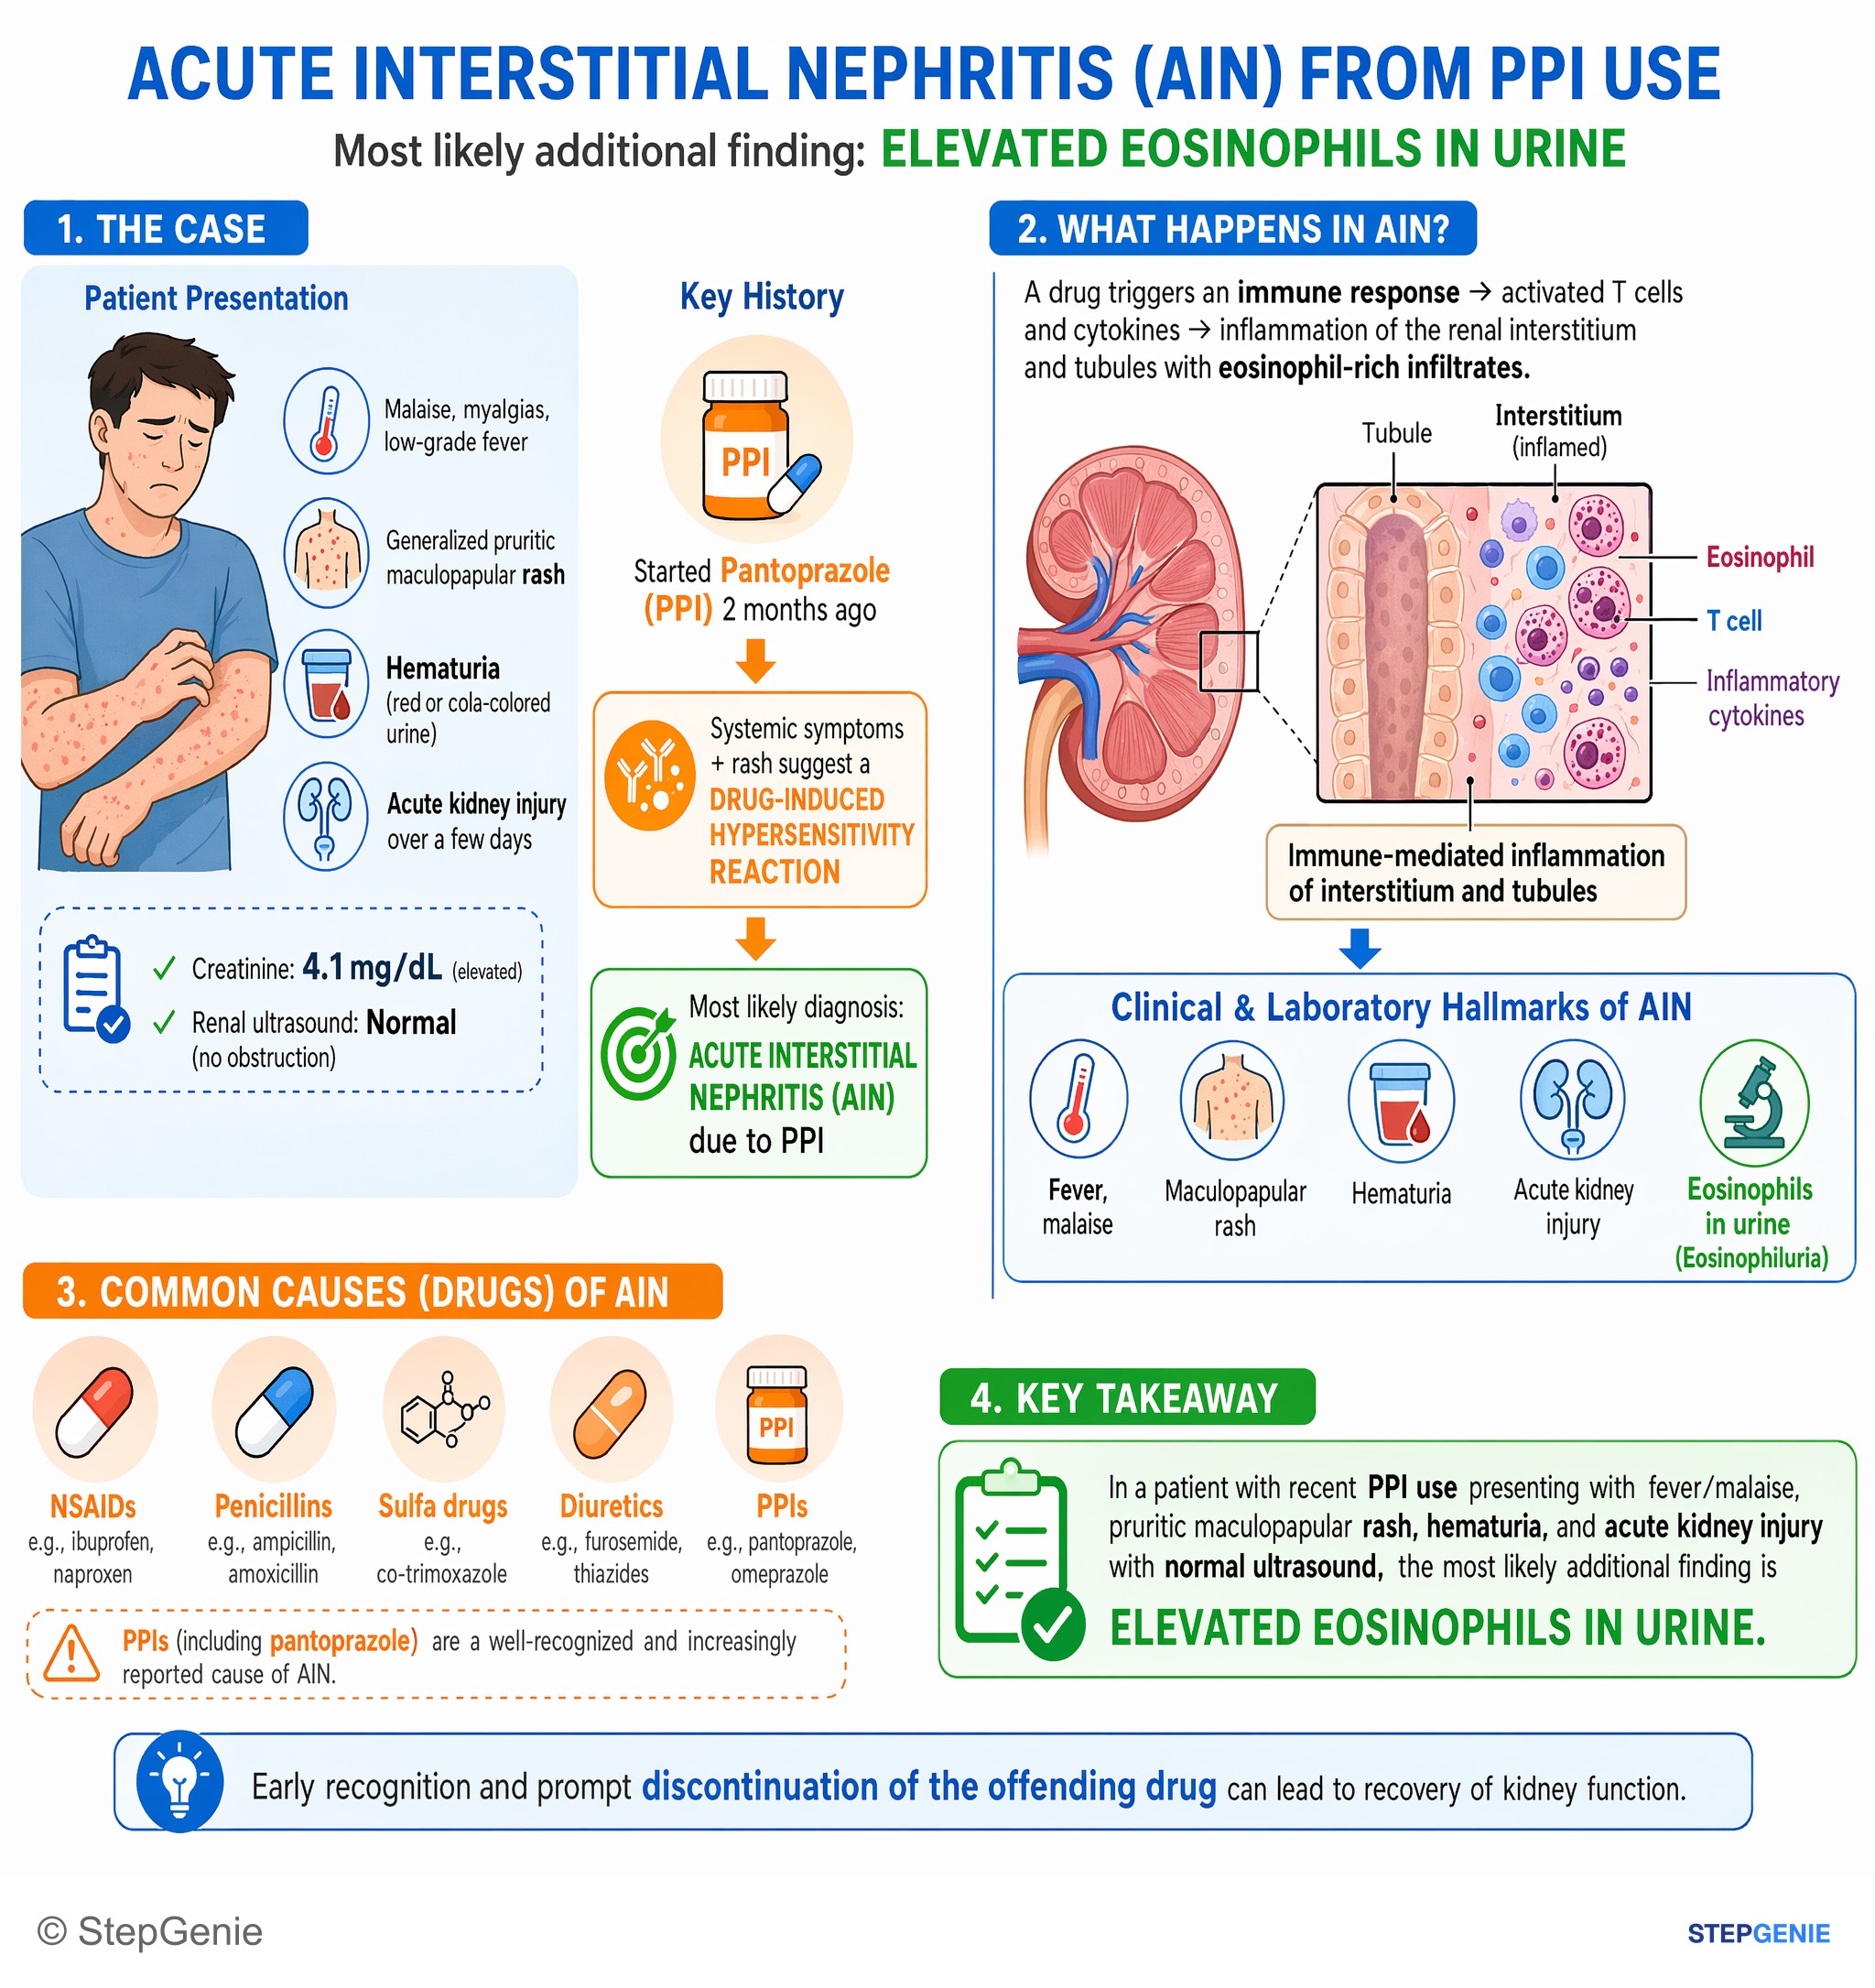
Acute interstitial nephritis from PPI use: fever/malaise, maculopapular rash, hematuria, acute kidney injury, and urinary eosinophils.
USMLE Step 1Frequently Asked Questions
How do proton pump inhibitors work?
PPIs are prodrugs. After absorption, they reach the parietal cell, where acid in the secretory canaliculi converts them to an active form that binds covalently to the H+/K+ ATPase, the proton pump that performs the final step of acid secretion. The binding is irreversible, so acid output recovers only as the cell makes new pumps. That is why one daily dose suppresses acid for more than 24 hours despite a short plasma half-life.
Why should PPIs be taken before meals?
PPIs can only bind proton pumps that are actively secreting acid, and eating switches the pumps on. Taking the dose 30 to 60 minutes before a meal, usually breakfast, means the drug is in the blood when the pumps activate. ACG recommends this timing over bedtime dosing for GERD. Labels vary: esomeprazole capsules should be taken at least an hour before meals, while pantoprazole tablets can be taken with or without food.
What are the side effects of long-term PPI use?
Current US labels warn about C. difficile-associated diarrhea, hypomagnesemia (usually after a year of use), vitamin B12 deficiency with years of daily use, hip, wrist and spine fractures with high-dose or long-term use, acute tubulointerstitial nephritis, cutaneous and systemic lupus, severe skin reactions and fundic gland polyps. PPIs also raise gastrin and chromogranin A. Links to dementia and kidney disease come from observational studies that do not prove cause and effect.
Which PPI should be used with clopidogrel?
Clopidogrel is a prodrug that needs CYP2C19 to form its active metabolite. Omeprazole and esomeprazole inhibit CYP2C19, so their labels say to avoid combining them with clopidogrel. Pantoprazole had no clinically important effect on clopidogrel's active metabolite or platelet inhibition in its label study, and no clopidogrel dose change is needed, which makes it the usual PPI for patients taking clopidogrel.
What is the difference between PPIs, H2 blockers and vonoprazan?
PPIs irreversibly block the proton pump itself after acid activation, so they suppress acid whatever the stimulus. H2 blockers such as famotidine competitively block histamine at the parietal cell H2 receptor, start working within an hour and are less effective. Vonoprazan, a potassium-competitive acid blocker, also blocks the pump but reversibly, needs no acid activation and starts suppressing acid within 2 to 3 hours of the first dose. AGA favors it in most H. pylori regimens but generally not as first-line therapy for heartburn, non-erosive reflux or mild esophagitis.
Do PPIs raise gastrin levels?
Yes. Acid normally makes antral D cells release somatostatin, which restrains gastrin release. When a PPI removes the acid, that brake weakens and serum gastrin rises; long-term hypergastrinemia causes enterochromaffin-like cell hyperplasia. Chromogranin A rises too, so labels advise stopping the PPI at least 14 days before measuring it, and a high gastrin level must be interpreted with care when Zollinger-Ellison syndrome is suspected.