Necrotizing enterocolitis (NEC) is one of those neonatal diagnoses that shows up everywhere—peds wards, NBME vignettes, and “why is the baby’s belly getting bigger?” questions. If you can connect the risk factors (prematurity + formula feeds) to the pathophysiology (intestinal ischemia + bacterial invasion) and the classic imaging clue (pneumatosis intestinalis), you’ll pick up easy points on Step 1—and you’ll understand why management is so time-sensitive.
Quick Definition (What NEC is)
Necrotizing enterocolitis is an acute inflammatory necrosis of the intestinal wall (most often terminal ileum and proximal colon) occurring primarily in premature neonates, strongly associated with enteral feeding (especially formula) and intestinal immaturity/ischemia, with risk of perforation, peritonitis, and sepsis.
High-yield buzzwords:
- Premature infant
- Feeding intolerance
- Abdominal distension
- Bloody stools
- Pneumatosis intestinalis on imaging
Why NEC Happens: Pathophysiology (Step 1-level logic)
NEC is best understood as a “perfect storm”:
1) Immature gut + poor perfusion → mucosal injury
Premature infants have:
- Immature intestinal barrier
- Dysregulated inflammatory responses
- Limited ability to autoregulate splanchnic blood flow
Hypoxic/ischemic stress (even subtle) leads to mucosal breakdown, which sets the stage for invasion.
2) Bacterial translocation → inflammation + gas in the bowel wall
Once the mucosa is injured, bacteria invade the intestinal wall. Gas produced by bacteria becomes trapped in the submucosa/subserosa, causing:
- Pneumatosis intestinalis (air in the bowel wall)
Severe disease can progress to:
- Transmural necrosis
- Perforation → pneumoperitoneum
- Sepsis and shock
3) Feeding (esp. formula) increases risk
Enteral feeds increase substrate for bacterial growth and distension. Breast milk is protective (contains IgA, growth factors, and promotes healthier microbiome).
Major Risk Factors (Know these cold)
| Risk factor | Why it matters |
|---|---|
| Prematurity (biggest risk) | Immature gut barrier + immune/inflammatory regulation |
| Formula feeding | Higher NEC risk than breast milk |
| Intestinal ischemia / hypoxia | Mucosal injury → bacterial invasion |
| Umbilical artery catheterization | Can compromise mesenteric perfusion |
| Congenital heart disease | Low systemic perfusion → gut ischemia |
| Sepsis | Systemic inflammation and poor perfusion |
Exam trap: NEC is not the same as Hirschsprung enterocolitis (different mechanism—aganglionosis), though both can present with distension and severe illness.
Clinical Presentation (How it shows up on exams)
NEC typically presents in the first days to weeks of life, especially after initiating feeds.
GI findings
- Feeding intolerance
- Vomiting (may be bilious)
- Abdominal distension
- Abdominal tenderness
- Bloody stools (hematochezia)
- Decreased bowel sounds, abdominal wall erythema in severe cases
Systemic findings (signals severity)
- Temperature instability
- Lethargy
- Apnea/bradycardia
- Poor perfusion
- Signs of sepsis/shock
Classic vignette: Premature infant started on formula → develops distension + bloody stools → x-ray shows pneumatosis intestinalis.
Diagnosis: The Step 1 Workup
NEC is primarily a clinical + radiographic diagnosis.
Imaging (most tested)
Abdominal x-ray findings:
- Pneumatosis intestinalis (air in bowel wall) — most classic
- Portal venous gas (advanced)
- Pneumoperitoneum (free air) → suggests perforation
Labs (supportive, severity markers)
- Metabolic acidosis (poor perfusion/lactic acidosis)
- Thrombocytopenia (consumption/sepsis)
- Leukocytosis or leukopenia
- Elevated CRP (nonspecific)
High-yield concept: Imaging is key because it distinguishes NEC from simpler feeding intolerance and helps identify perforation.
Differential Diagnosis: Don’t get baited
| Condition | Key distinguishing features |
|---|---|
| Malrotation with volvulus | Sudden onset bilious vomiting, “double bubble” not typical; can show corkscrew/abnormal SMA-SMV relationship; surgical emergency |
| Hirschsprung disease | Failure to pass meconium, chronic constipation; explosive stool on rectal exam; transition zone on contrast enema |
| Meconium ileus (CF) | Failure to pass meconium; soap-bubble/ground-glass on imaging; associated with cystic fibrosis |
| Milk protein allergy | Blood in stool in otherwise well infant; no pneumatosis intestinalis |
Treatment: What to do (and why)
Management depends on severity but starts with stabilizing the gut and preventing progression.
Initial management (high-yield)
- NPO (bowel rest)
- NG/OG decompression
- IV fluids and correct electrolytes
- Broad-spectrum IV antibiotics (cover gram-negatives + anaerobes)
- Common regimens include ampicillin + gentamicin + metronidazole (varies by institution)
- Total parenteral nutrition (TPN) if prolonged bowel rest
When surgery is needed
Indications include:
- Perforation (pneumoperitoneum/free air)
- Worsening clinical status despite medical therapy
- Necrotic bowel/strictures
Surgical options:
- Resection of necrotic bowel
- Possible ostomy placement
Complications to know
- Intestinal strictures (healed injury → fibrosis; can cause obstruction later)
- Short bowel syndrome (after extensive resection)
- Sepsis and death (severe NEC)
High-Yield Associations & “Step-Style” Clues
The “NEC constellation”
- Premature + formula feeding + abdominal distension + bloody stools
- X-ray: pneumatosis intestinalis
Prevention pearls
- Breast milk is protective
- Careful advancement of feeds in very premature infants
Cross-references (First Aid-style hooks)
You’ll commonly see NEC linked alongside other neonatal GI disorders. In First Aid, NEC is typically emphasized under:
- GI pathology / intestinal disorders
- Neonatal intestinal emergencies
- Imaging clue: pneumatosis intestinalis
- Associations: prematurity, formula feeding, bloody stools, abdominal distension
(If you annotate First Aid: write “NEC = premature + formula + pneumatosis” in the neonatal GI section, and underline pneumatosis as the imaging giveaway.)
Rapid Review Table (Last-minute cram)
| Category | High-yield facts |
|---|---|
| Definition | Inflammatory necrosis of bowel wall in premature infants |
| Risk factors | Prematurity, formula feeds, ischemia/hypoxia, UAC, CHD |
| Symptoms | Feeding intolerance, abdominal distension, vomiting, bloody stools, lethargy |
| Imaging | Pneumatosis intestinalis ± portal venous gas; free air if perforated |
| Treatment | NPO, NG decompression, IV fluids, broad-spectrum antibiotics, TPN; surgery if perforation/necrosis |
| Complications | Strictures, short bowel, sepsis, death |
Mini Vignette Pattern (So you recognize it instantly)
A 28-week preterm infant on day 10 of life recently advanced to formula feeds develops abdominal distension, lethargy, and bloody stools. Abdominal x-ray shows linear lucencies in the bowel wall.
Diagnosis: NEC
Next steps: NPO, NG decompression, IV antibiotics, supportive care; evaluate for perforation.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
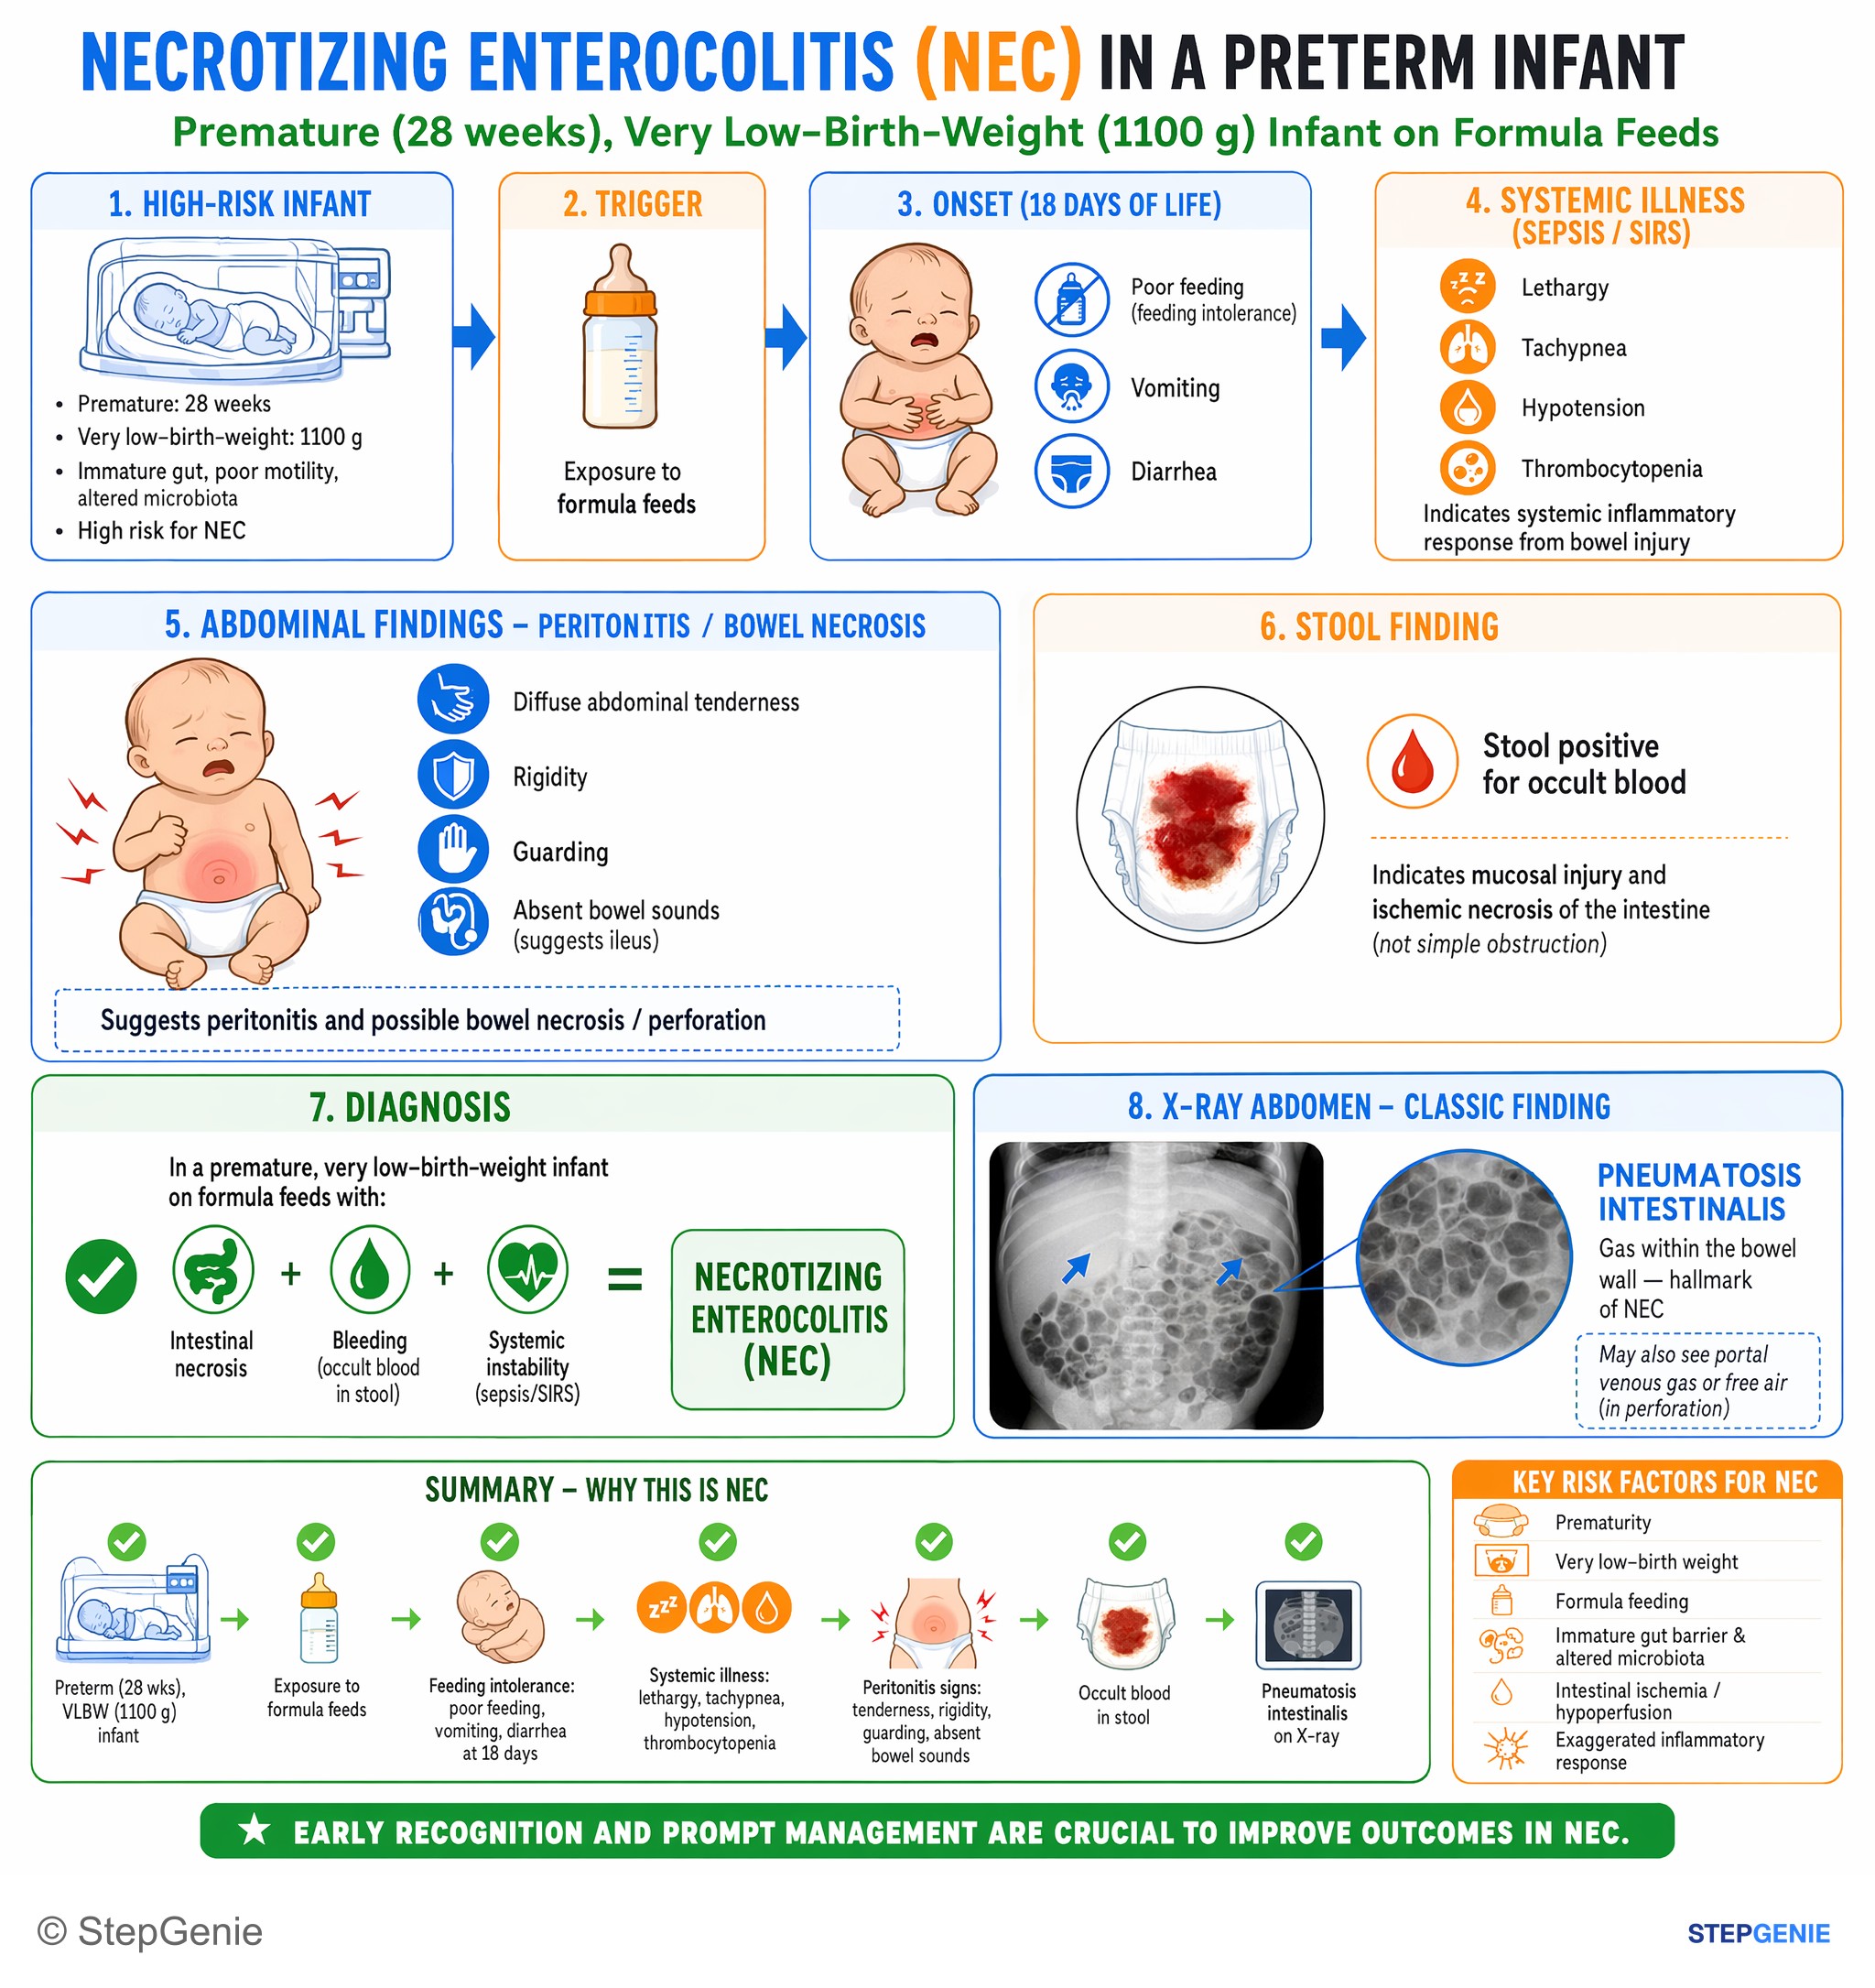
Necrotizing enterocolitis in premature, low–birth-weight infant on formula feeds → bloody stools, abdominal distension/tenderness…
USMLE Step 2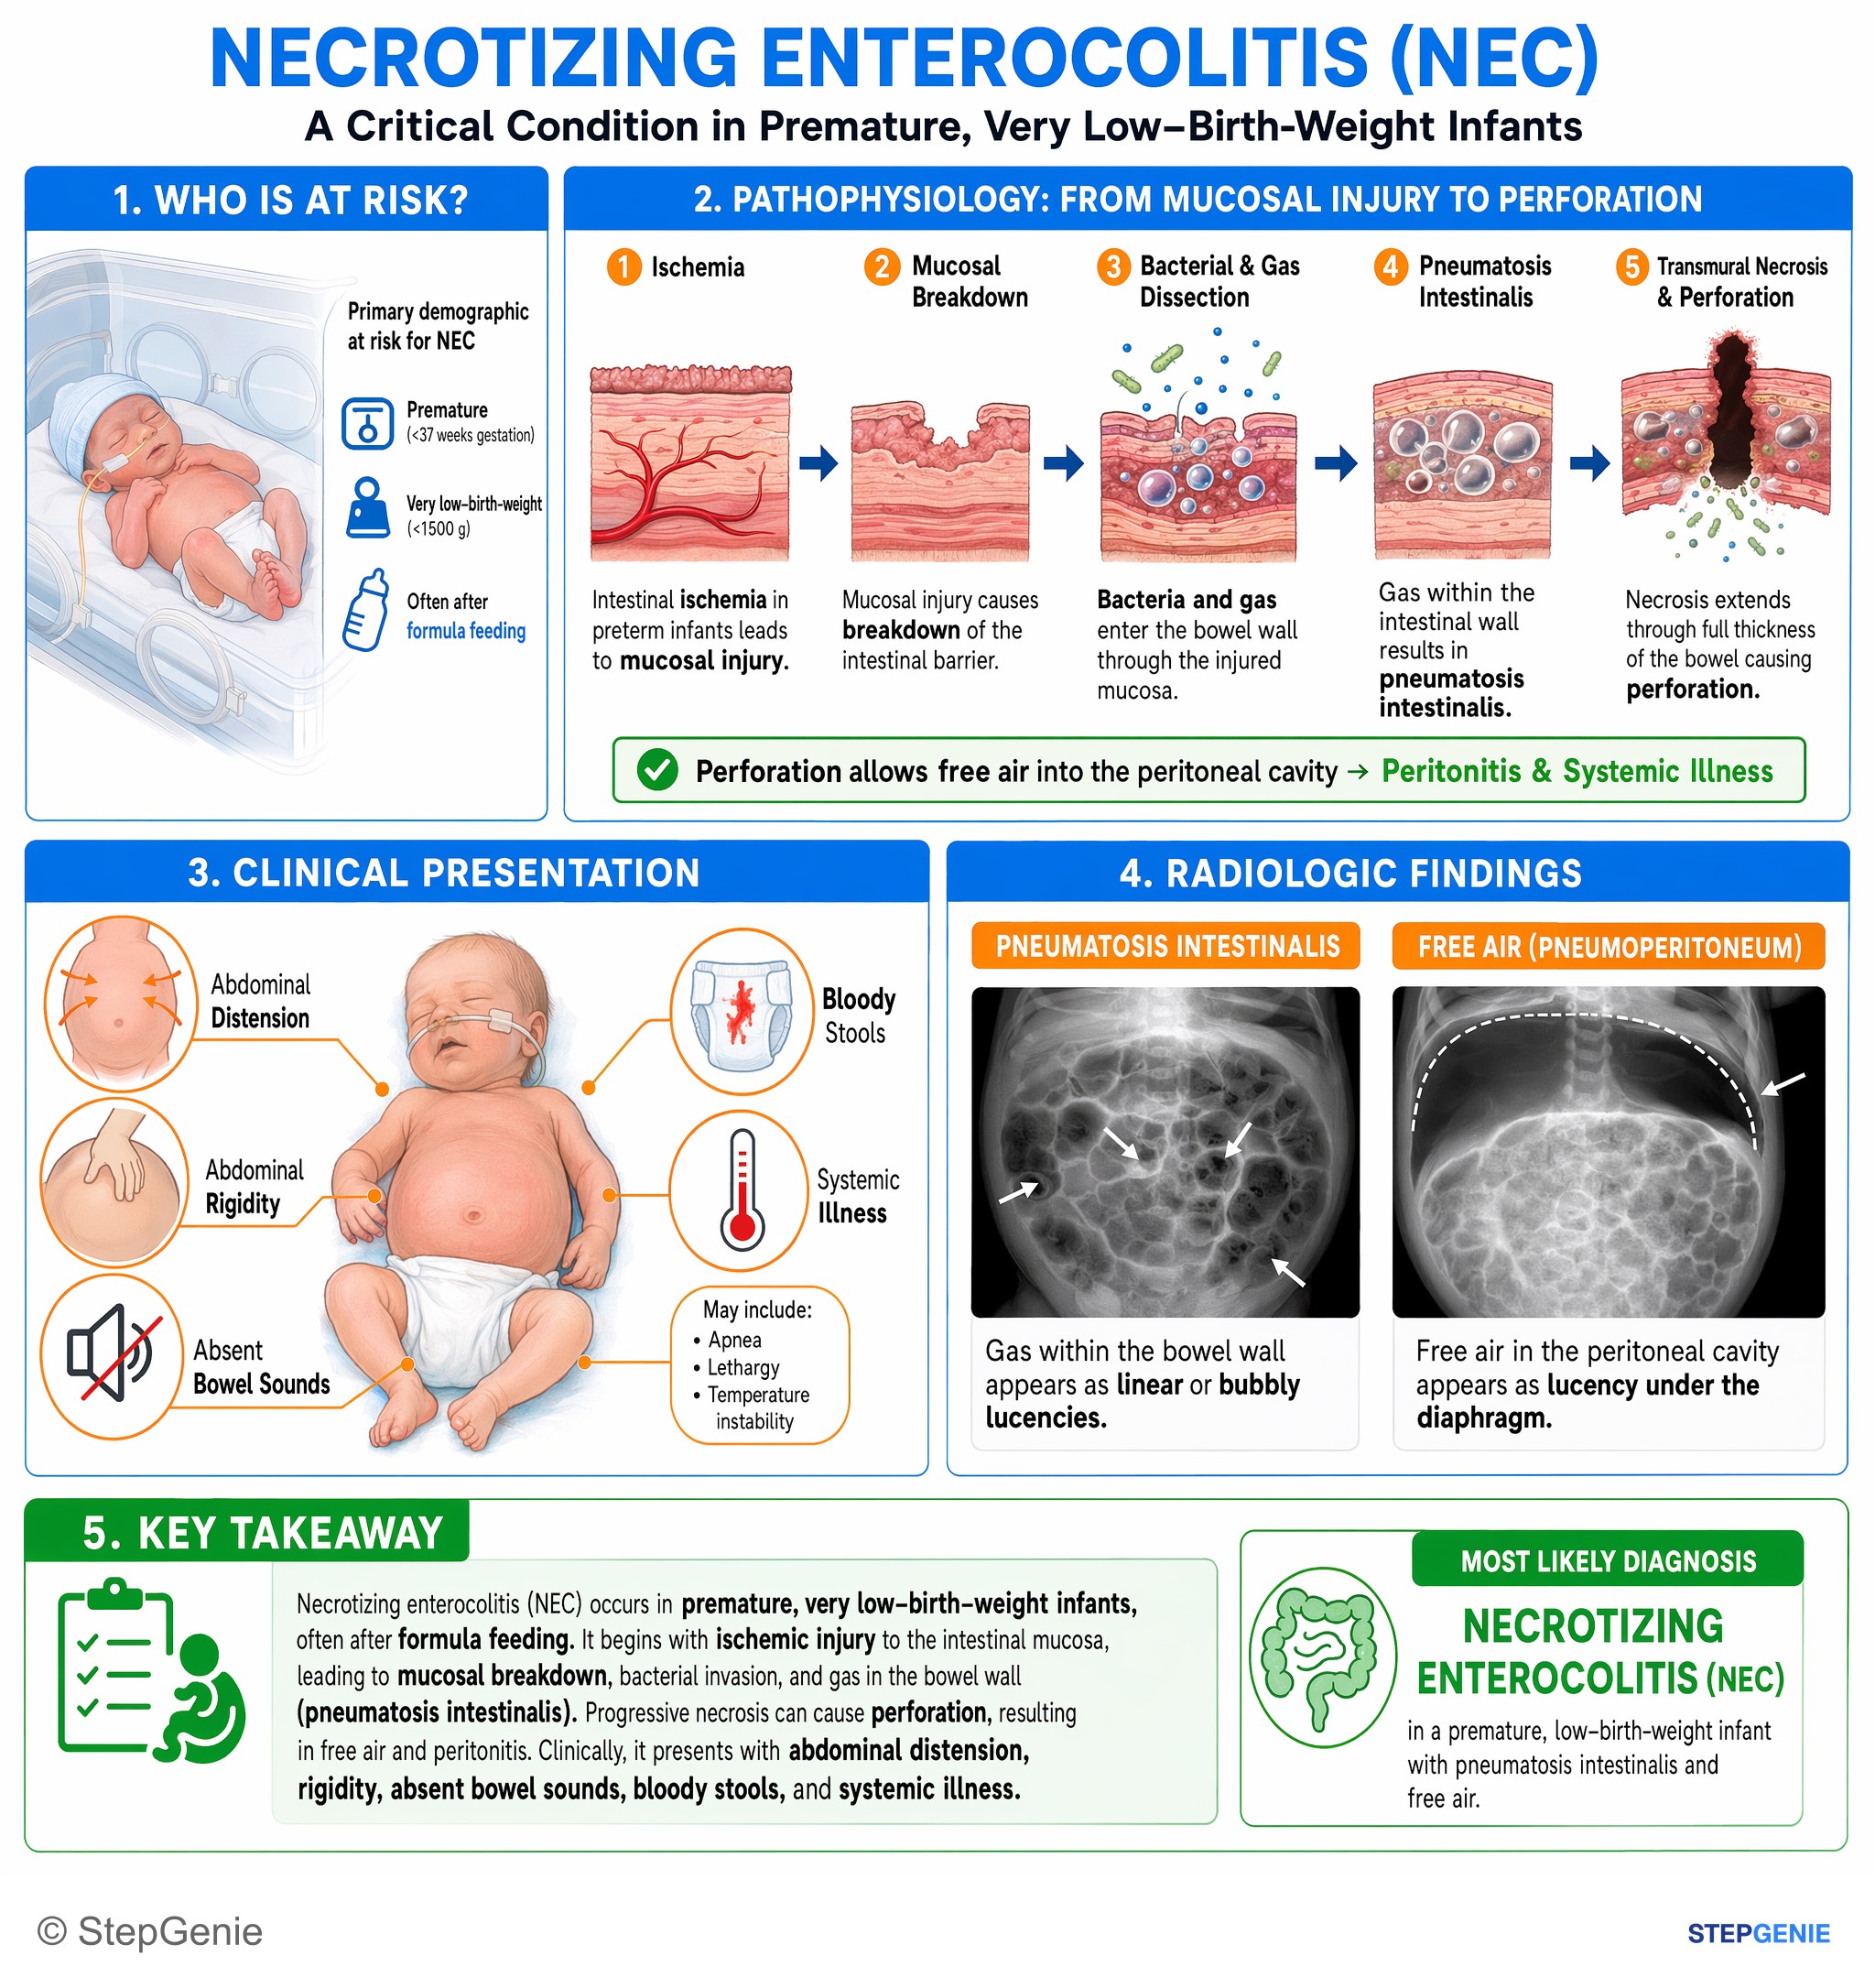
Necrotizing enterocolitis in premature, low–birth-weight infant: abdominal distension, bloody stools, pneumatosis intestinalis, possible…
USMLE Step 2Frequently Asked Questions
Why does necrotizing enterocolitis happen more often in premature infants?
It happens more often in premature infants because prematurity is the biggest risk factor and creates an immature, vulnerable gut. Premature neonates have an immature intestinal barrier, dysregulated inflammatory responses, and limited ability to autoregulate splanchnic blood flow. That makes hypoxic or ischemic stress more likely to cause mucosal injury, which then allows bacterial invasion and progression to intestinal necrosis.
Why does formula feeding increase the risk of necrotizing enterocolitis?
Formula feeding increases NEC risk because enteral feeds, especially formula, provide substrate for bacterial growth and contribute to intestinal distension. In a premature infant with an immature gut and ischemic vulnerability, that promotes bacterial translocation into the injured intestinal wall. Breast milk is protective because it contains IgA and growth factors and supports a healthier microbiome.
What is the classic x-ray finding in necrotizing enterocolitis?
The classic x-ray finding is pneumatosis intestinalis, which is air in the bowel wall. It occurs when bacteria invade the damaged intestinal wall and produce gas that becomes trapped in the submucosa or subserosa. Abdominal x-ray may also show portal venous gas in advanced disease, and pneumoperitoneum suggests bowel perforation.
How do you tell necrotizing enterocolitis from milk protein allergy or Hirschsprung disease?
NEC is suggested by a premature infant with feeding intolerance, abdominal distension, bloody stools, and pneumatosis intestinalis on imaging. Milk protein allergy can also cause blood in the stool, but the infant is otherwise well and there is no pneumatosis intestinalis. Hirschsprung disease is distinguished by failure to pass meconium, chronic constipation, explosive stool on rectal exam, and a transition zone on contrast enema.
What is the first-line treatment for necrotizing enterocolitis?
Initial treatment is bowel rest and supportive medical management. That means making the infant NPO, decompressing the gut with NG or OG suction, giving IV fluids and correcting electrolytes, and starting broad-spectrum IV antibiotics that cover gram-negatives and anaerobes. TPN is used if bowel rest is prolonged, and surgery is needed for perforation, worsening status, or necrotic bowel.