Hirschsprung disease is one of those “tiny embryology mistake, huge clinical consequence” topics that shows up everywhere on Step 1—newborn constipation, failure to pass meconium, abdominal distension, and that classic contrast enema + rectal biopsy combo. If you can connect neural crest migration failure to aganglionosis to functional obstruction, you’ve basically got 80% of the questions.
Big Picture Definition (What it is)
Hirschsprung disease = congenital absence of ganglion cells in the submucosal (Meissner) and myenteric (Auerbach) plexuses of the distal bowel → failure of relaxation of the affected segment → functional obstruction with proximal dilation (megacolon).
Key phrase to remember: Aganglionic segment is narrow; bowel proximal to it dilates.
First Aid cross-reference:
- GI Pathology → Congenital disorders → Hirschsprung disease (often grouped with imperforate anus and other neonatal obstruction causes)
Pathophysiology (Why it happens)
The Step 1 mechanism
- Neural crest cells fail to migrate to the distal colon during development.
- Result: No enteric ganglion cells in:
- Auerbach (myenteric) plexus → impaired peristalsis/relaxation
- Meissner (submucosal) plexus → impaired secretion/local control
- The aganglionic segment stays tonically contracted → functional obstruction.
- Upstream bowel works harder → hypertrophy + dilation → megacolon.
Where it occurs
- Usually starts at the rectum and extends proximally a variable distance.
- Rectosigmoid is the most common location.
High-Yield Associations (USMLE loves these)
Genetics + syndromes
| Association | Why it matters for Step |
|---|---|
| Down syndrome (Trisomy 21) | Classic association; think Hirschsprung in a constipated/distended newborn with T21 features |
| RET mutation | Also implicated in MEN2; Hirschsprung is a “RET-related” disease in many questions |
| Neural crest disorders | Reinforces mechanism: enteric nervous system = neural crest-derived |
First Aid cross-reference:
- Genetics → Trisomy 21 associations (Hirschsprung is a common tie-in)
- Endocrine/Neoplasia → MEN2/RET (RET shows up across systems)
Clinical Presentation (How it shows up)
Newborn presentation (classic)
- Failure to pass meconium within 24–48 hours
- Abdominal distension
- Bilious vomiting
- Feeding intolerance
- Constipation
Exam vignette pearl: “Squirt sign”
- On rectal exam: explosive release of stool and gas after withdrawing the finger
→ temporary decompression because you overcame the distal functional obstruction.
Older child presentation (less classic but tested)
- Chronic constipation since birth
- Poor weight gain / failure to thrive
- Recurrent abdominal distension
Diagnosis (How you prove it)
Stepwise approach (high yield)
- Contrast enema
- Shows a transition zone:
- Narrow distal aganglionic segment
- Dilated proximal colon
- Shows a transition zone:
- Rectal suction biopsy (gold standard)
- Absent ganglion cells
- Hypertrophied nerve trunks
- Increased AChE staining in nerve fibers (a classic histology clue)
What about anorectal manometry?
- Often shows absence of the rectoanal inhibitory reflex (RAIR)
(internal anal sphincter fails to relax with rectal distension) - Useful supportive test, but biopsy confirms.
First Aid cross-reference:
- GI Pathology → Hirschsprung: absent ganglion cells + increased AChE
- Physiology tie-in: enteric plexus control of motility
Complications You Must Know
Hirschsprung-associated enterocolitis (HACE)
This is the scary complication and a favorite for “next best step” questions.
Clues:
- Fever, lethargy
- Explosive/bloody diarrhea
- Abdominal distension, toxicity
- Can progress to sepsis, perforation
Board-relevant take: A baby with Hirschsprung who suddenly develops diarrhea + systemic illness is not “getting better”—think enterocolitis.
Treatment (What you do about it)
Definitive management
- Surgical resection of the aganglionic segment with pull-through procedure (anastomose normal ganglionated bowel to the anus).
Acute/supportive management (especially if obstructed or enterocolitis)
- Rectal irrigations for decompression
- IV fluids/electrolytes
- Broad-spectrum antibiotics if enterocolitis is suspected
- Temporary diverting ostomy may be needed in severe cases before definitive repair
Differentials (Quick separation from similar Step entities)
| Condition | Key distinguishing feature | Typical buzzwords |
|---|---|---|
| Hirschsprung | Aganglionosis → failure to pass meconium, transition zone | Down syndrome, RET, increased AChE |
| Meconium ileus | Obstruction at ileum from thick meconium | Cystic fibrosis, “soap-bubble”/ground-glass on imaging |
| Necrotizing enterocolitis | Premature infant + intestinal ischemia/infection | Pneumatosis intestinalis, portal venous gas |
| Pyloric stenosis | Nonbilious projectile vomiting, “olive” | Hypochloremic metabolic alkalosis |
USMLE High-Yield Rapid Review (What to memorize)
- Definition: congenital aganglionic megacolon.
- Embryology: neural crest migration failure → no Auerbach/Meissner ganglion cells.
- Presentation: failure to pass meconium (24–48h), abdominal distension, bilious emesis; squirt sign.
- Diagnosis: contrast enema shows transition zone; rectal suction biopsy = gold standard.
- Histology: absent ganglion cells, hypertrophied nerves, increased AChE.
- Associations: Down syndrome, RET mutations.
- Complication: enterocolitis (can be life-threatening).
- Treatment: surgical resection + pull-through.
Mini Practice Vignettes (Step-style pattern recognition)
-
Newborn hasn’t passed meconium at 36 hours, distended abdomen, bilious vomiting. Contrast enema shows narrow rectosigmoid with proximal dilation.
→ Diagnosis? Hirschsprung. Next step to confirm? Rectal suction biopsy. -
Infant with known Hirschsprung now has fever + explosive bloody diarrhea + lethargy.
→ Concern for Hirschsprung-associated enterocolitis → fluids + antibiotics + decompression.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
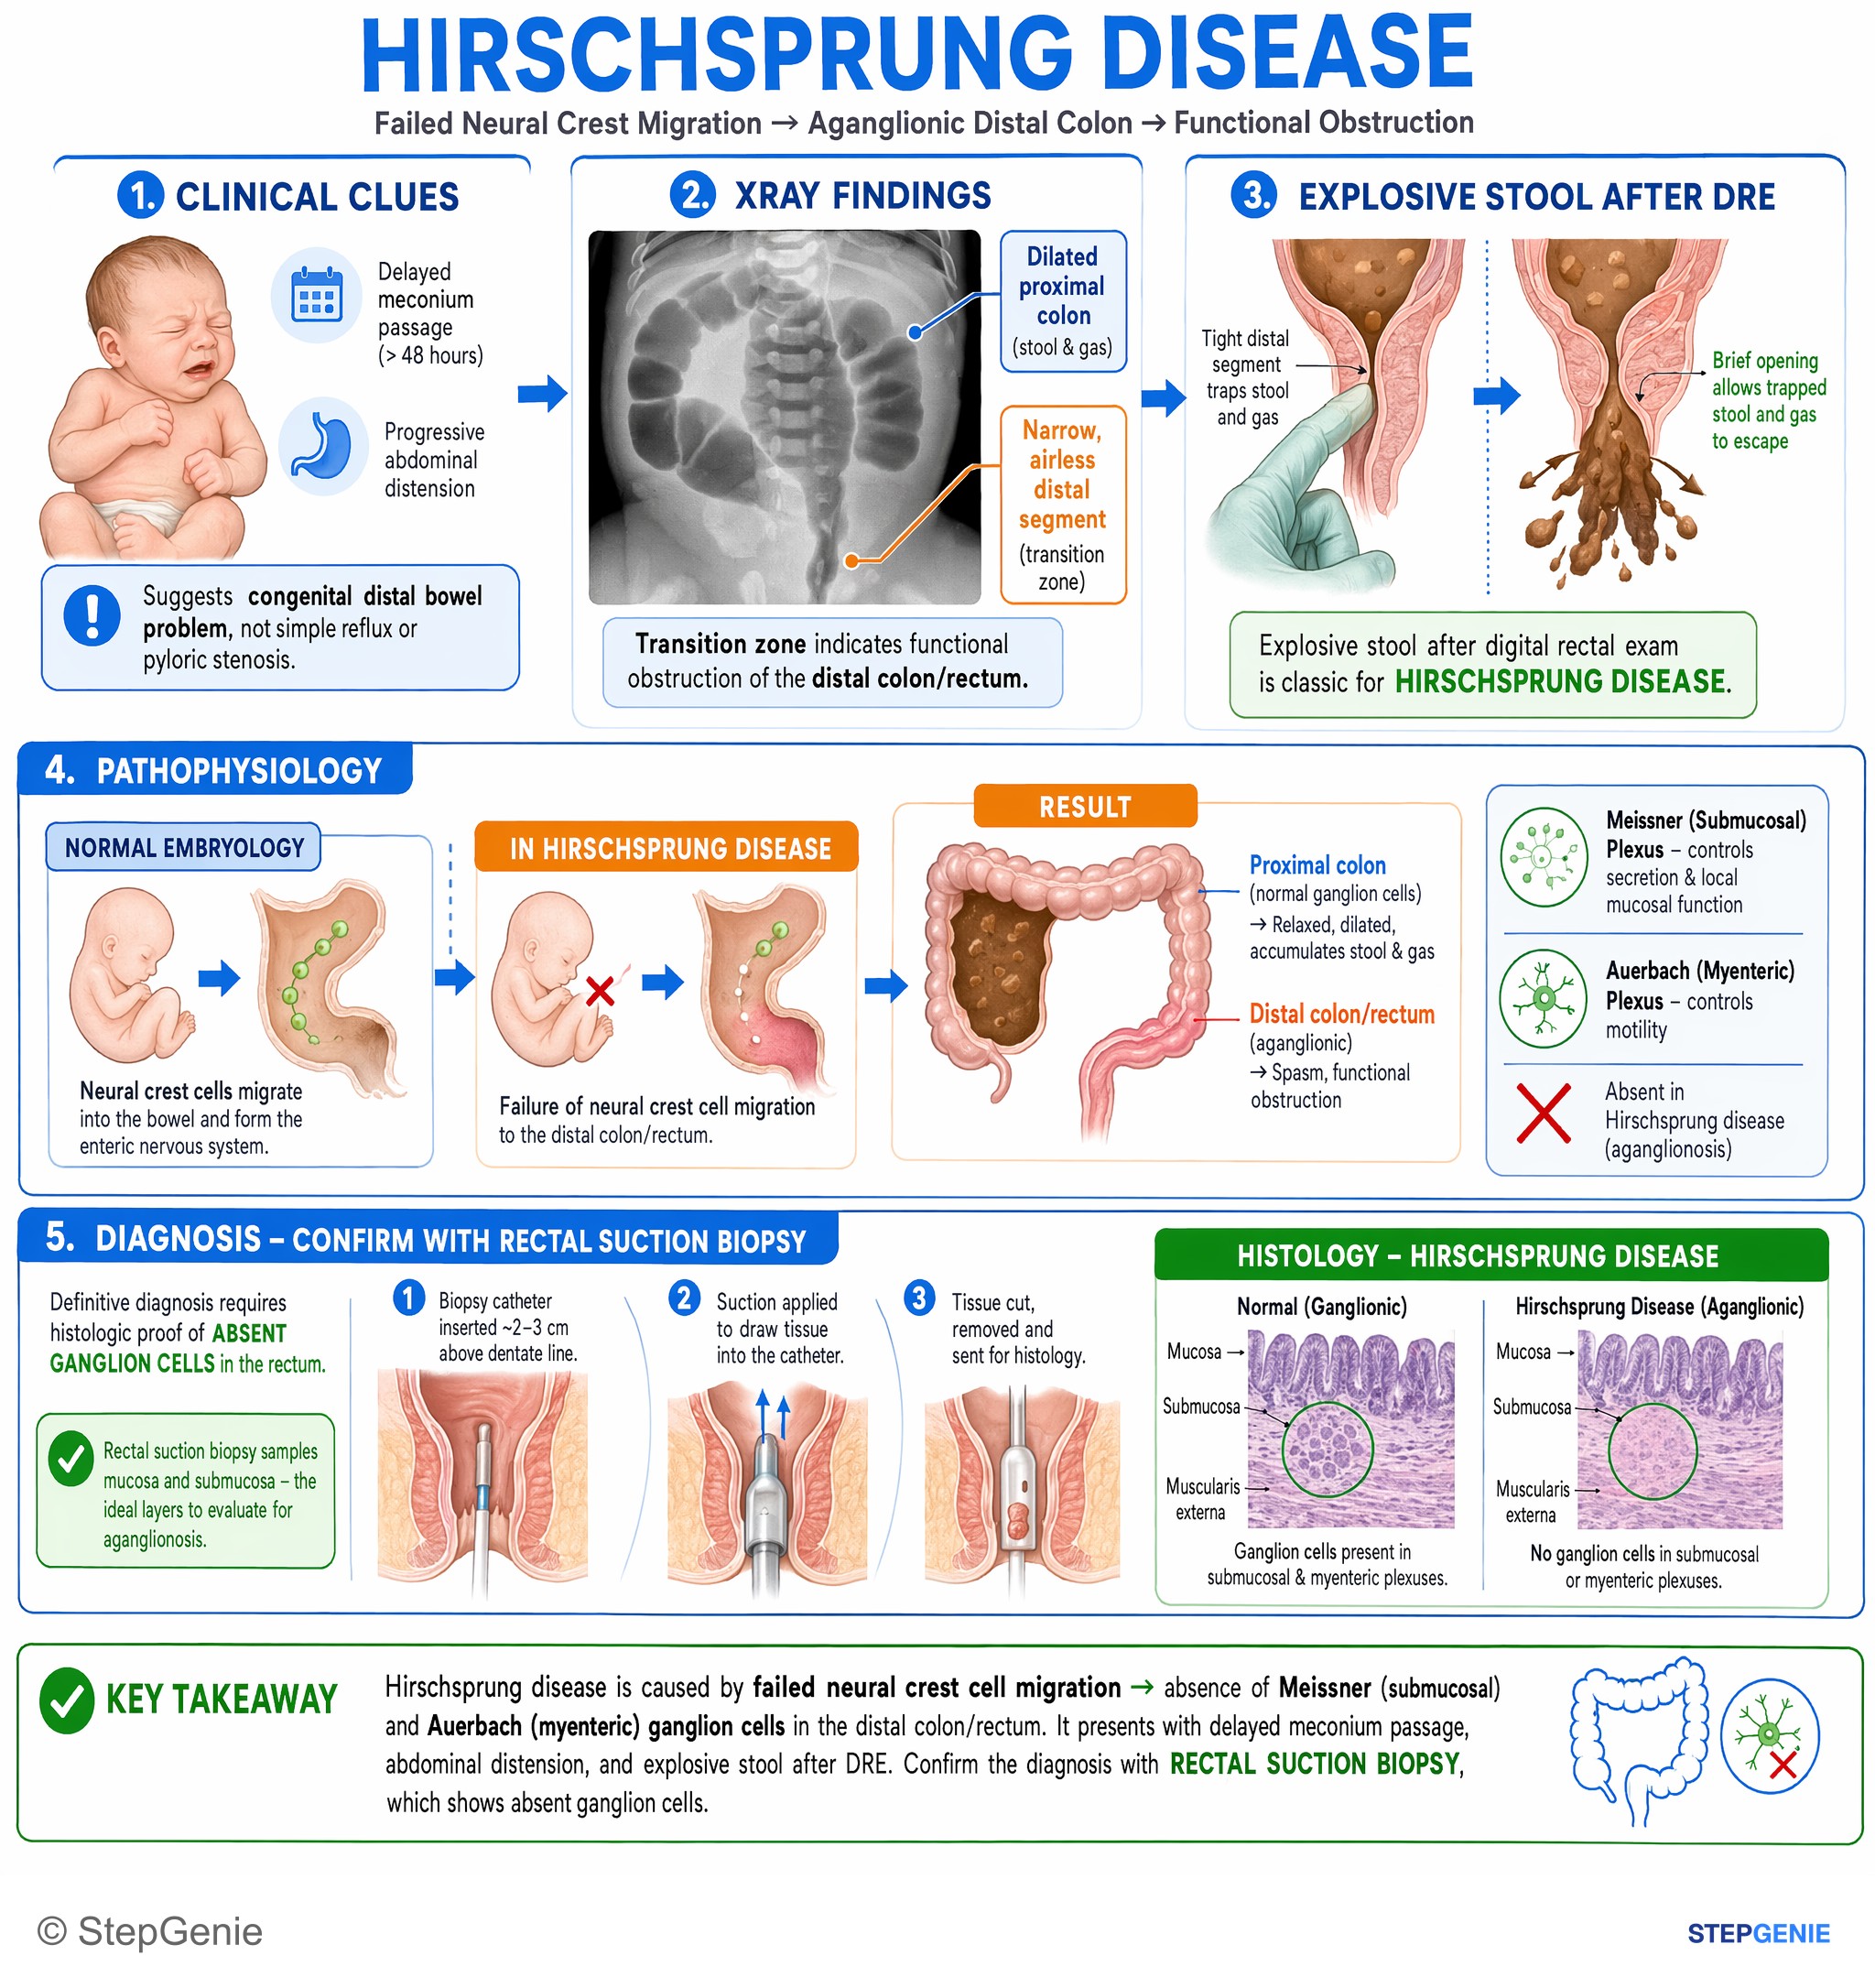
Hirschsprung disease from failed neural crest migration → aganglionic distal colon; confirm with rectal suction biopsy showing absent…
USMLE Step 1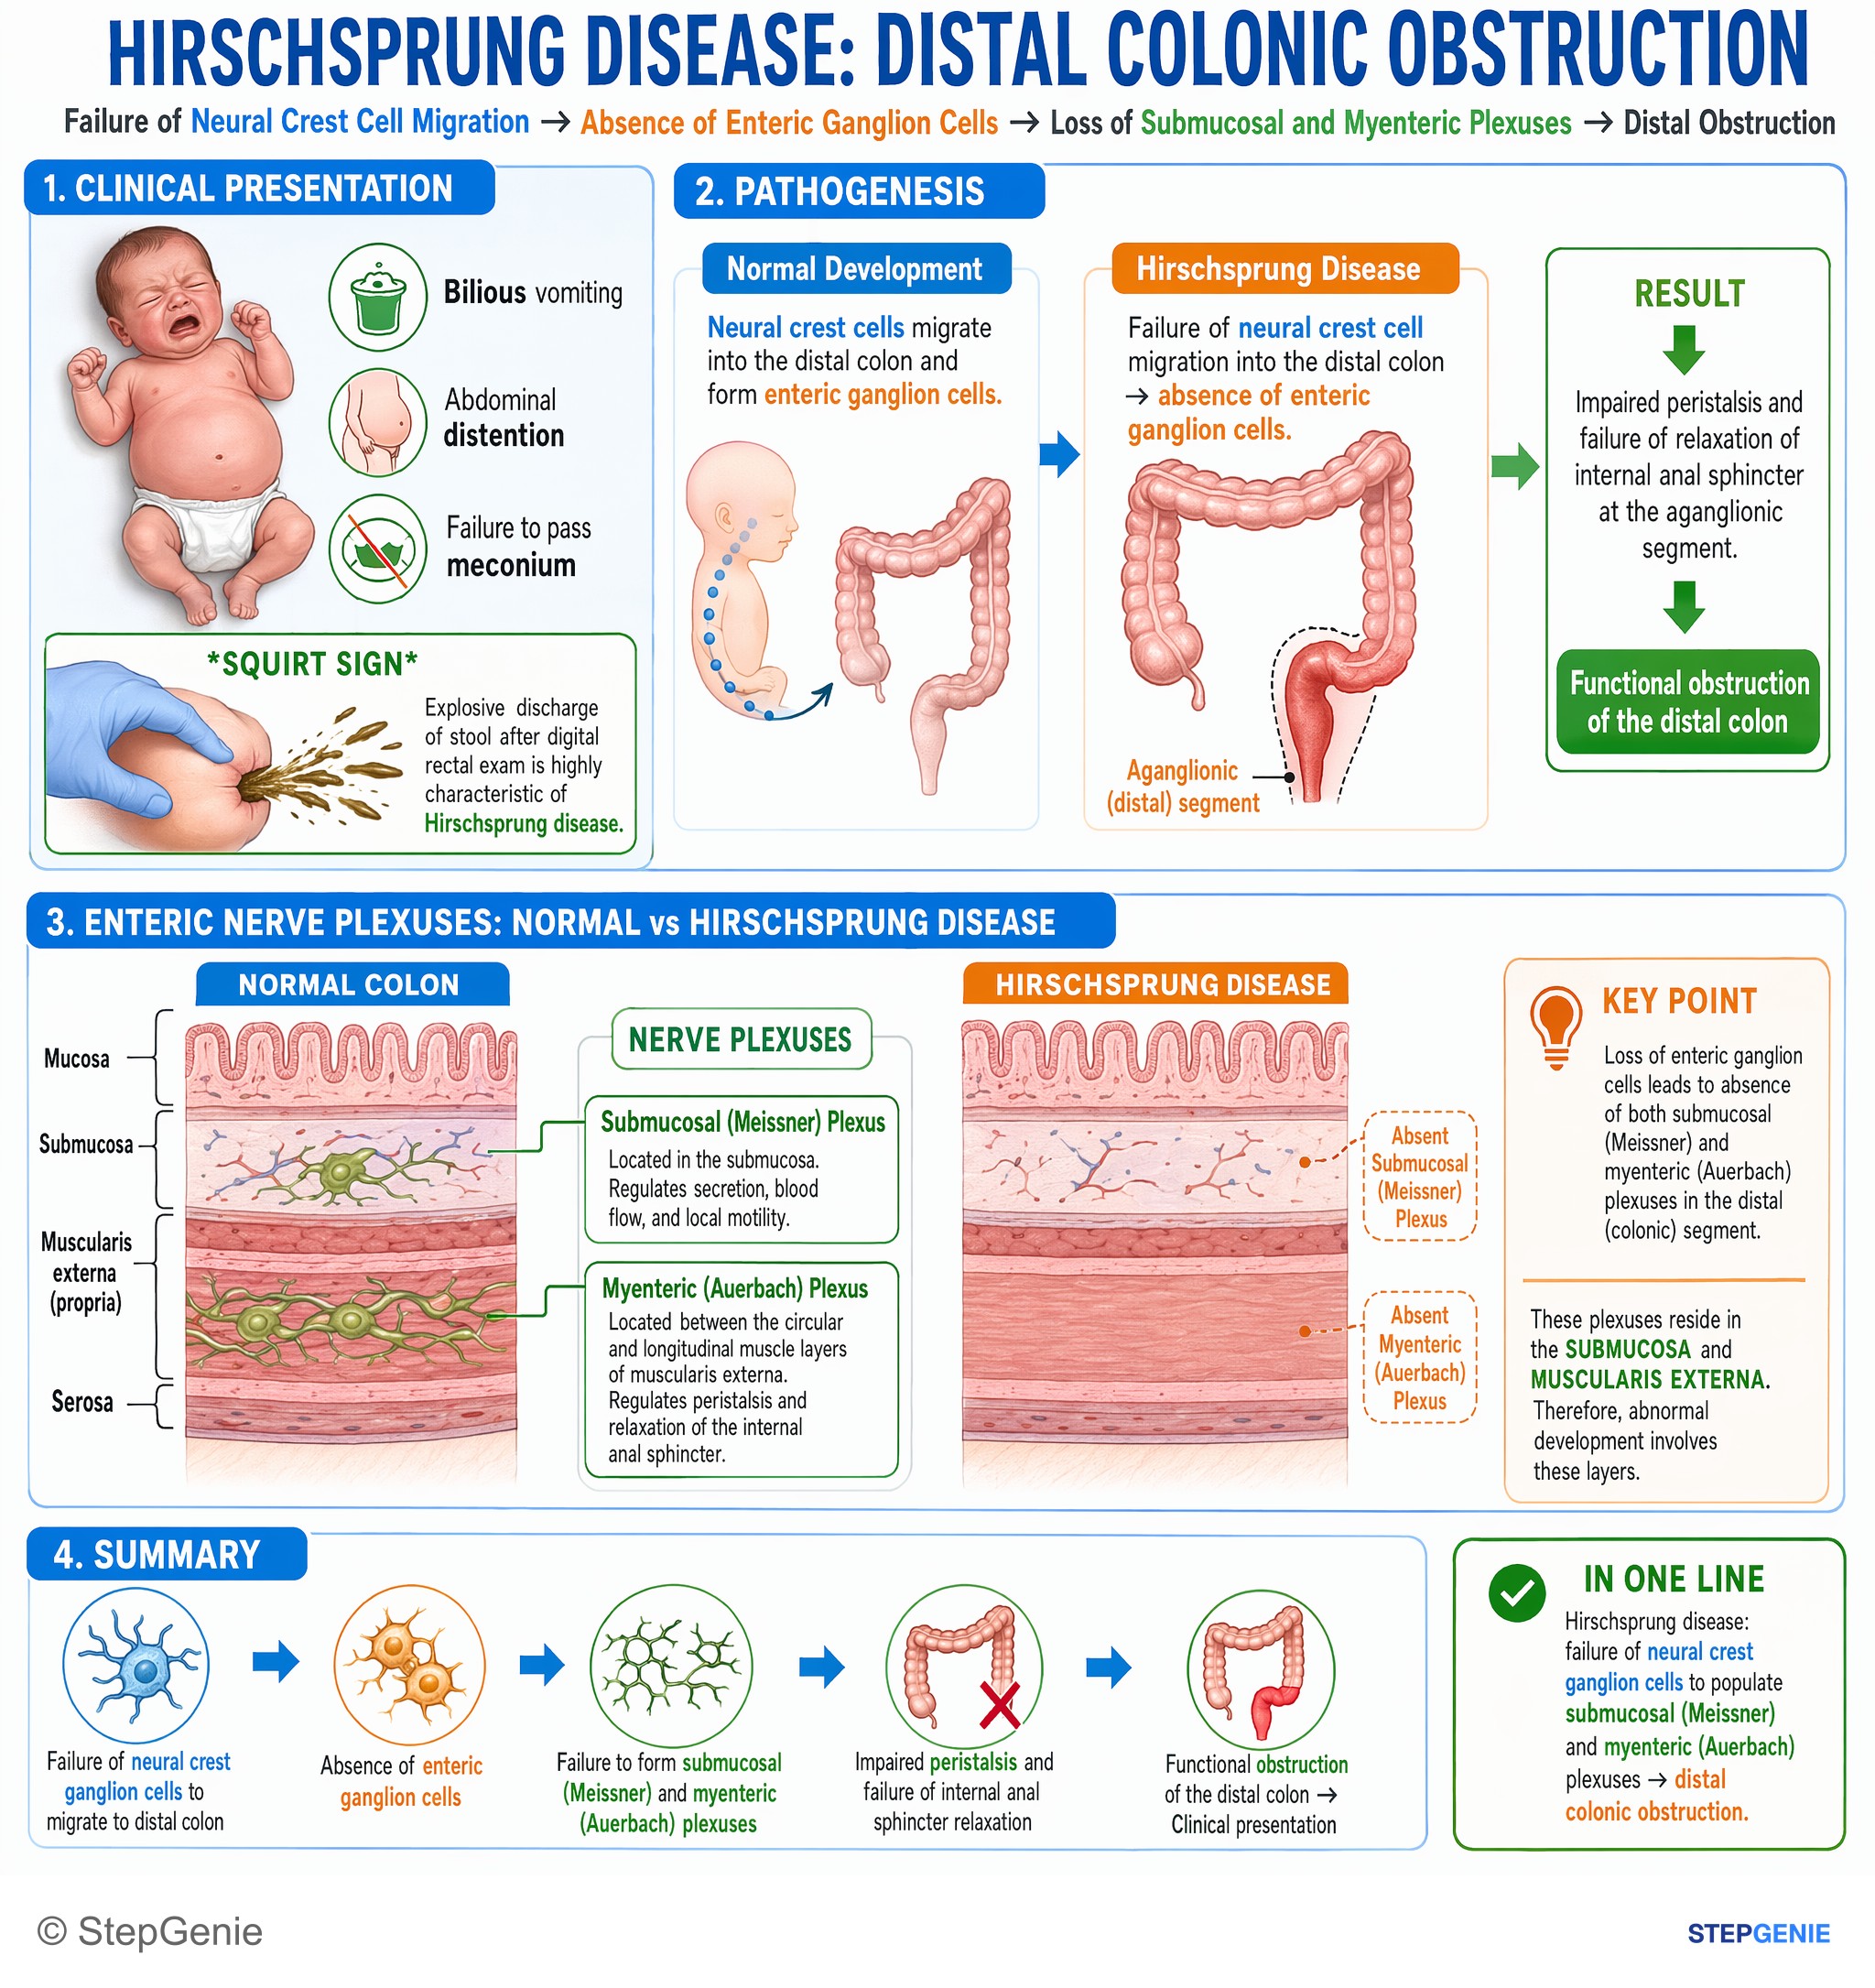
Hirschsprung disease: failure of neural crest ganglion cells to populate submucosal (Meissner) and myenteric (Auerbach) plexuses → distal…
USMLE Step 1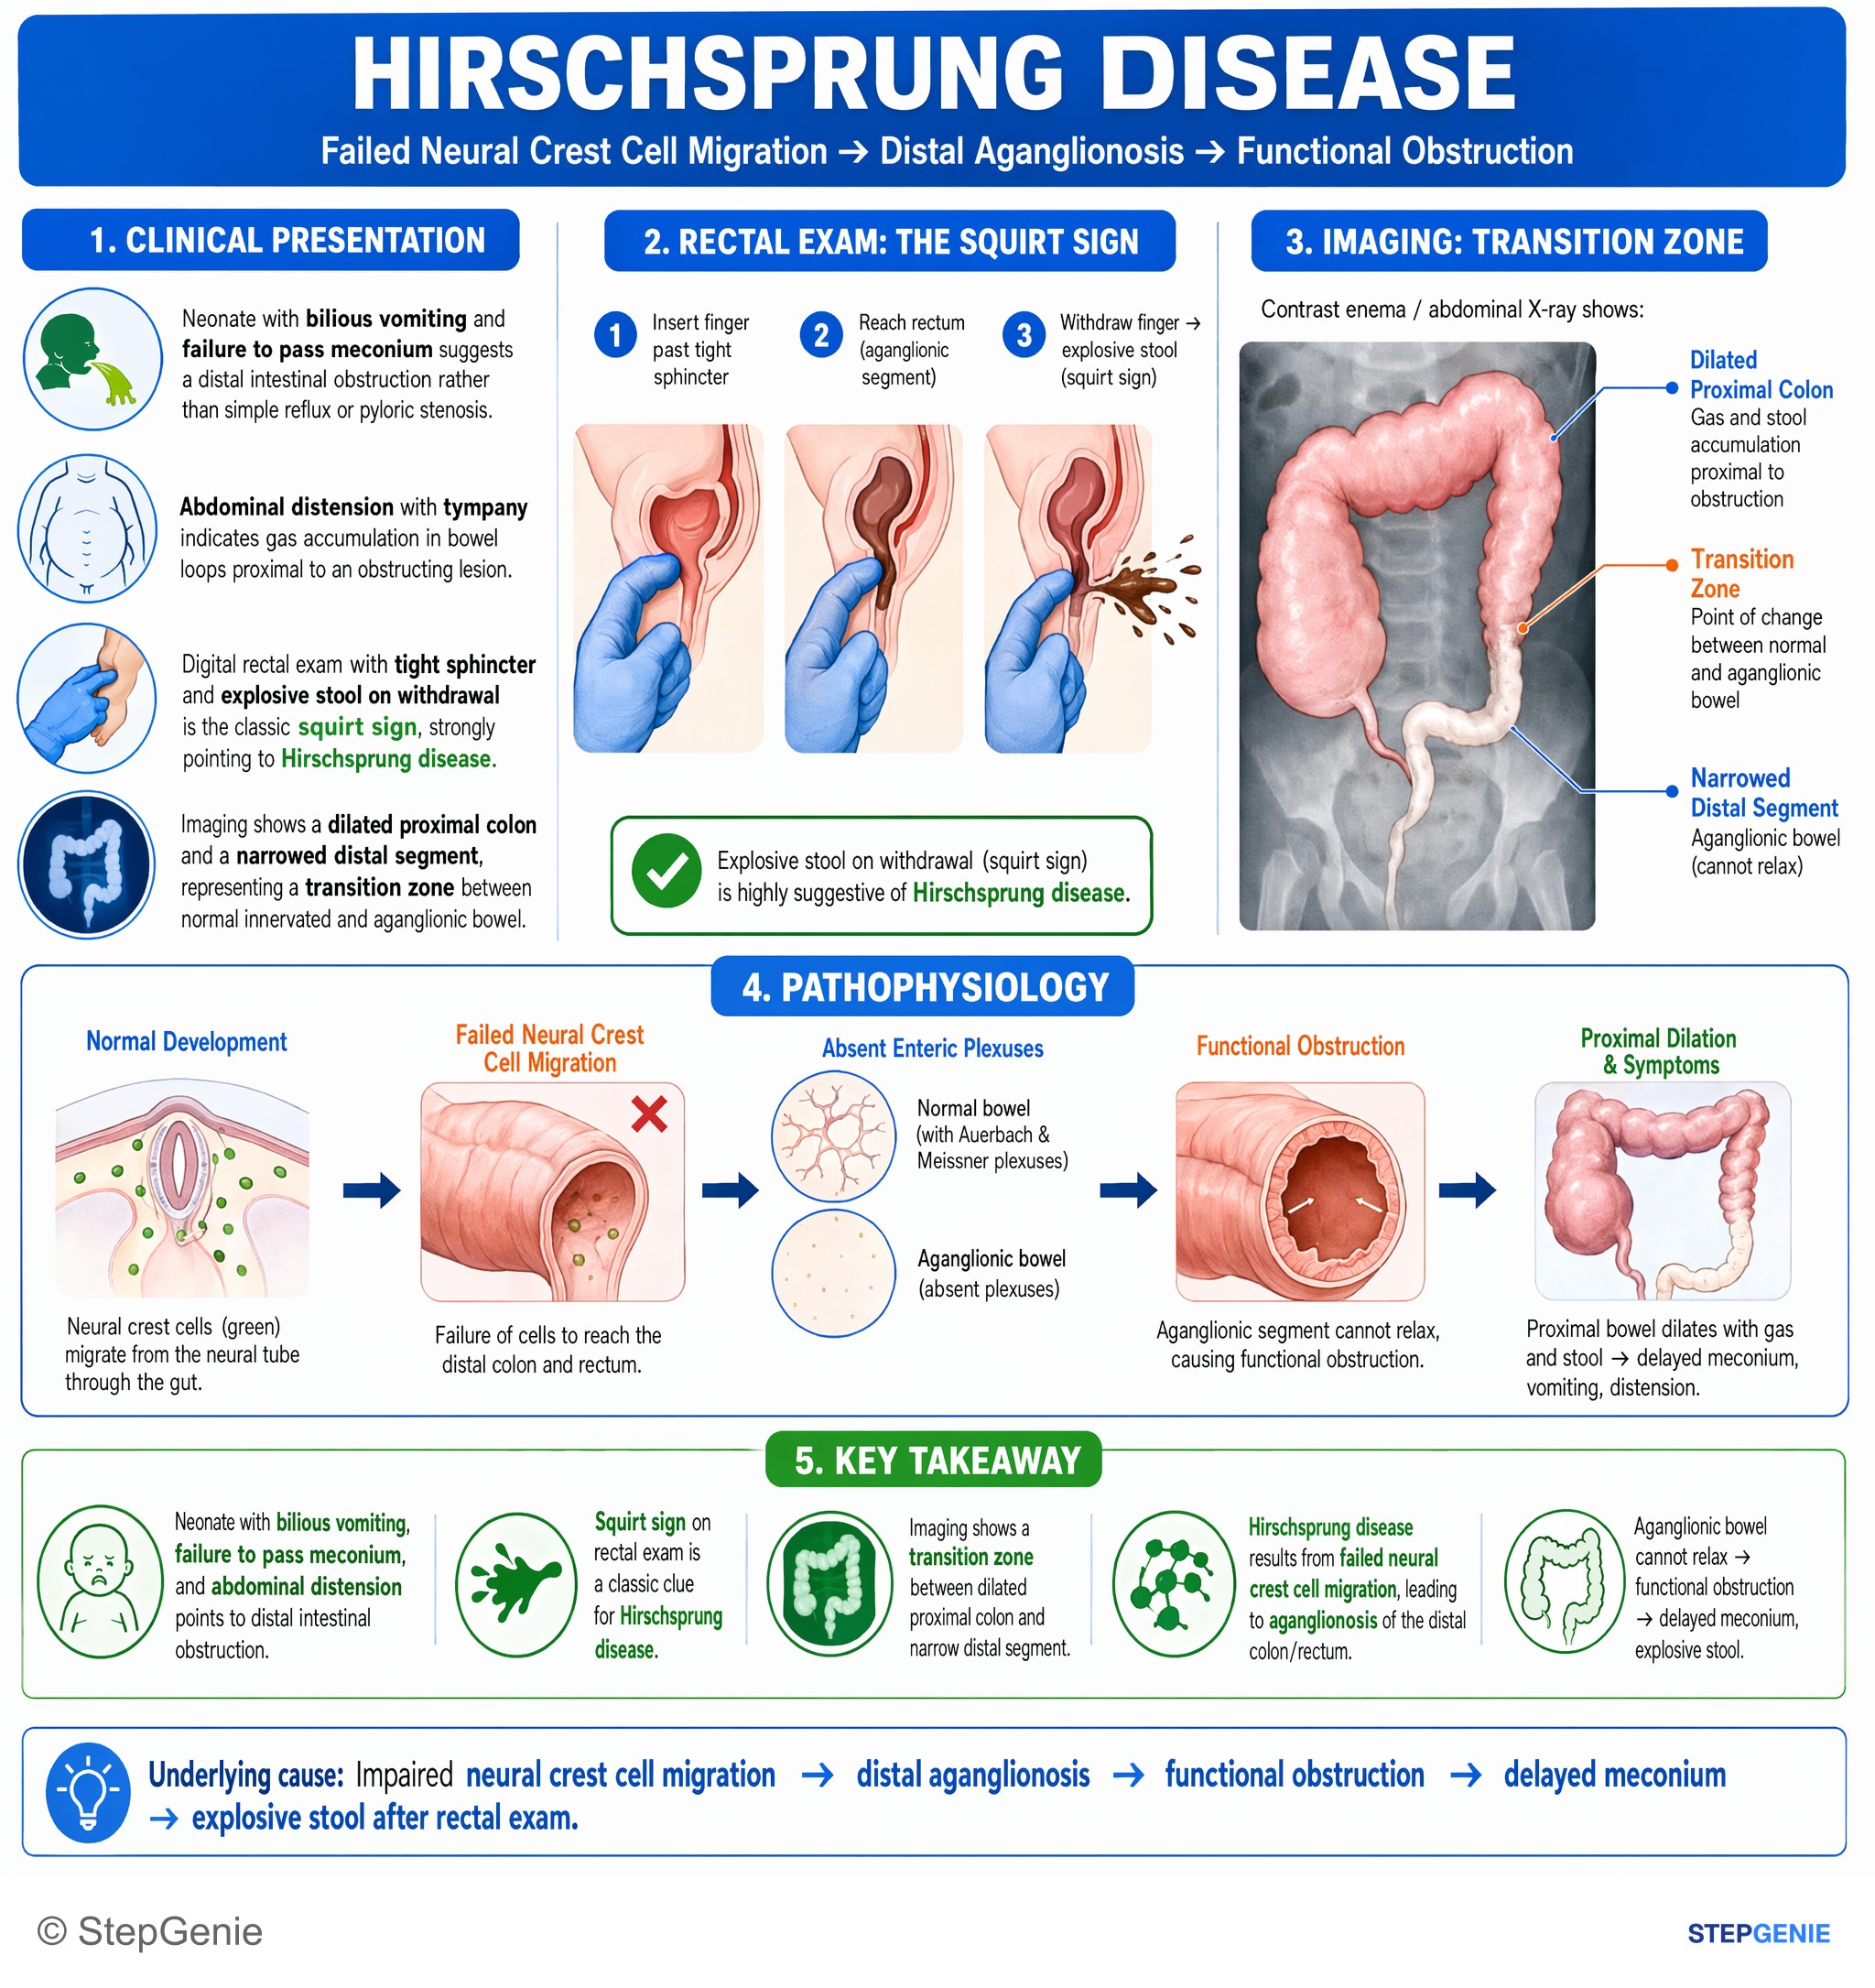
Hirschsprung disease from failed neural crest cell migration → distal aganglionosis, functional obstruction, delayed meconium, explosive…
USMLE Step 1Frequently Asked Questions
Why does Hirschsprung disease cause functional obstruction and megacolon?
Hirschsprung disease causes functional obstruction because neural crest cells fail to migrate to the distal colon, leaving the bowel without ganglion cells in the Meissner and Auerbach plexuses. Without those enteric ganglia, the affected segment cannot relax properly and remains tonically contracted. That narrowed distal segment blocks stool passage, while the proximal bowel becomes hypertrophied and dilated, producing megacolon.
How do you diagnose Hirschsprung disease on Step 1?
The key diagnostic approach is contrast enema followed by rectal suction biopsy, with biopsy being the gold standard. Contrast enema shows a transition zone with a narrow distal aganglionic segment and a dilated proximal colon. Rectal suction biopsy confirms the diagnosis by showing absent ganglion cells, hypertrophied nerve trunks, and increased acetylcholinesterase staining in nerve fibers.
What are the classic clinical clues for Hirschsprung disease in a newborn?
The classic newborn clues are failure to pass meconium within 24 to 48 hours, abdominal distension, bilious vomiting, feeding intolerance, and constipation. A helpful exam pearl is the squirt sign, where rectal examination causes explosive release of stool and gas after the finger is withdrawn. That happens because the exam temporarily relieves the distal functional obstruction caused by the aganglionic segment.
How do you tell Hirschsprung disease from meconium ileus, necrotizing enterocolitis, and pyloric stenosis?
Hirschsprung disease is distinguished by aganglionosis causing failure to pass meconium and a transition zone on contrast enema. Meconium ileus instead causes ileal obstruction from thick meconium and is linked to cystic fibrosis with soap-bubble or ground-glass imaging. Necrotizing enterocolitis is associated with prematurity and shows pneumatosis intestinalis or portal venous gas. Pyloric stenosis presents with nonbilious projectile vomiting and an olive mass.
What is the treatment for Hirschsprung disease, and what do you do if enterocolitis is suspected?
Definitive treatment is surgical resection of the aganglionic segment with a pull-through procedure connecting normal ganglionated bowel to the anus. If the patient is obstructed or enterocolitis is suspected, management also includes rectal irrigations for decompression, IV fluids and electrolyte support, and broad-spectrum antibiotics. In severe cases, a temporary diverting ostomy may be needed before definitive repair.