Lactulose is one of those “simple sugar” drugs that shows up everywhere on exams—constipation, hepatic encephalopathy, ammonia, and a classic “why is this patient now having diarrhea?” vignette. If you can draw the mechanism, you’ll never forget what it does (or why it works).
Where Lactulose Lives (GI Pharm in 10 seconds)
Drug class: Nonabsorbable disaccharide (osmotic laxative)
Primary uses:
- Constipation (osmotic diarrhea → stool softening)
- Hepatic encephalopathy (↓ serum ammonia)
One-liner:
Lactulose stays in the gut, pulls water into the lumen, and traps ammonia as so it can be pooped out.
Draw-It-Out Mechanism (the sketch you should memorize)
Step 1: It’s nonabsorbable → sits in the colon
Lactulose isn’t digested/absorbed in the small intestine → reaches colon intact.
Step 2: Gut bacteria ferment it → acids form
Colonic bacteria metabolize lactulose → organic acids (lactic acid, acetic acid, etc.) → lowers colonic pH.
Step 3: Low pH traps ammonia (“ion trapping”)
In the colon:
- (neutral) can diffuse
- Acidic environment pushes equilibrium toward (charged) → can’t diffuse back → excreted in stool
Key reaction to remember:
Step 4: Osmotic effect = watery stool
Lactulose + metabolites are osmotically active → draw water into the lumen → diarrhea (therapeutic at the right dose, toxic if too much).
The Visual Mnemonic: “LAC-to-LOO-se”
Picture this quick cartoon:
- A toilet labeled “LOO” (diarrhea/laxative effect)
- A cow with a “LAC” tag (lactulose)
- The toilet bowl is full of purple acid (↓ pH)
- Little ammonia ghosts () try to escape but get handcuffed into and flushed
Translation:
- LAC (lactulose) → LOO (poop/diarrhea)
- Acidifies colon → traps as → decreases serum ammonia → improves encephalopathy
Why It Helps Hepatic Encephalopathy (USMLE-style reasoning)
The clinical setup
Liver can’t convert ammonia to urea effectively (think cirrhosis) → ammonia builds up → crosses BBB → neurotoxicity.
Lactulose fixes this via 2 big mechanisms
- Acidifies colon → traps as
- Increases stooling → less time for nitrogenous waste to generate/absorb ammonia
Exam phrasing to recognize:
- “Nonabsorbable disaccharide”
- “Acidifies gut lumen”
- “Traps ammonia”
- “Goal is 2–3 soft stools/day” (common clinical target)
High-Yield Indications & What They’re Testing
| Indication | What the question is really testing | Clue words |
|---|---|---|
| Hepatic encephalopathy | Ammonia handling + colon acidification + stool frequency | Cirrhosis, asterixis, confusion, elevated ammonia |
| Constipation | Osmotic laxative mechanism | Hard stools, low fiber, opioid constipation but lactulose is not first-line there |
Pro tip: For hepatic encephalopathy, you’ll often see rifaximin mentioned as an add-on (↓ ammonia-producing gut bacteria). Lactulose is typically first-line.
Adverse Effects (the ones Step loves)
Common
- Diarrhea
- Abdominal cramping
- Flatulence (bacterial fermentation)
Important testable consequence
- Dehydration → hypernatremia (from excessive diarrhea)
- Can worsen electrolyte disturbances if overused (think volume depletion)
Classic trap: If a cirrhotic patient on lactulose becomes more confused, don’t just blame encephalopathy—check for dehydration/electrolyte derangements from over-diarrhea.
Mini Rapid-Fire: What to Answer in 1 Line
- MOA: Nonabsorbable disaccharide → osmotic diarrhea + colonic acidification → trapping
- Use: Constipation; hepatic encephalopathy
- AE: Diarrhea, cramps, flatulence, dehydration/electrolyte issues
Quick Self-Check (USMLE vignette lens)
If a stem says:
- “Cirrhosis + confusion + asterixis” → treat with lactulose
- Mechanism asked? → acidifies colon, traps ammonia as
- Side effect asked? → diarrhea/flatulence
- Treatment goal? → 2–3 soft stools/day
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
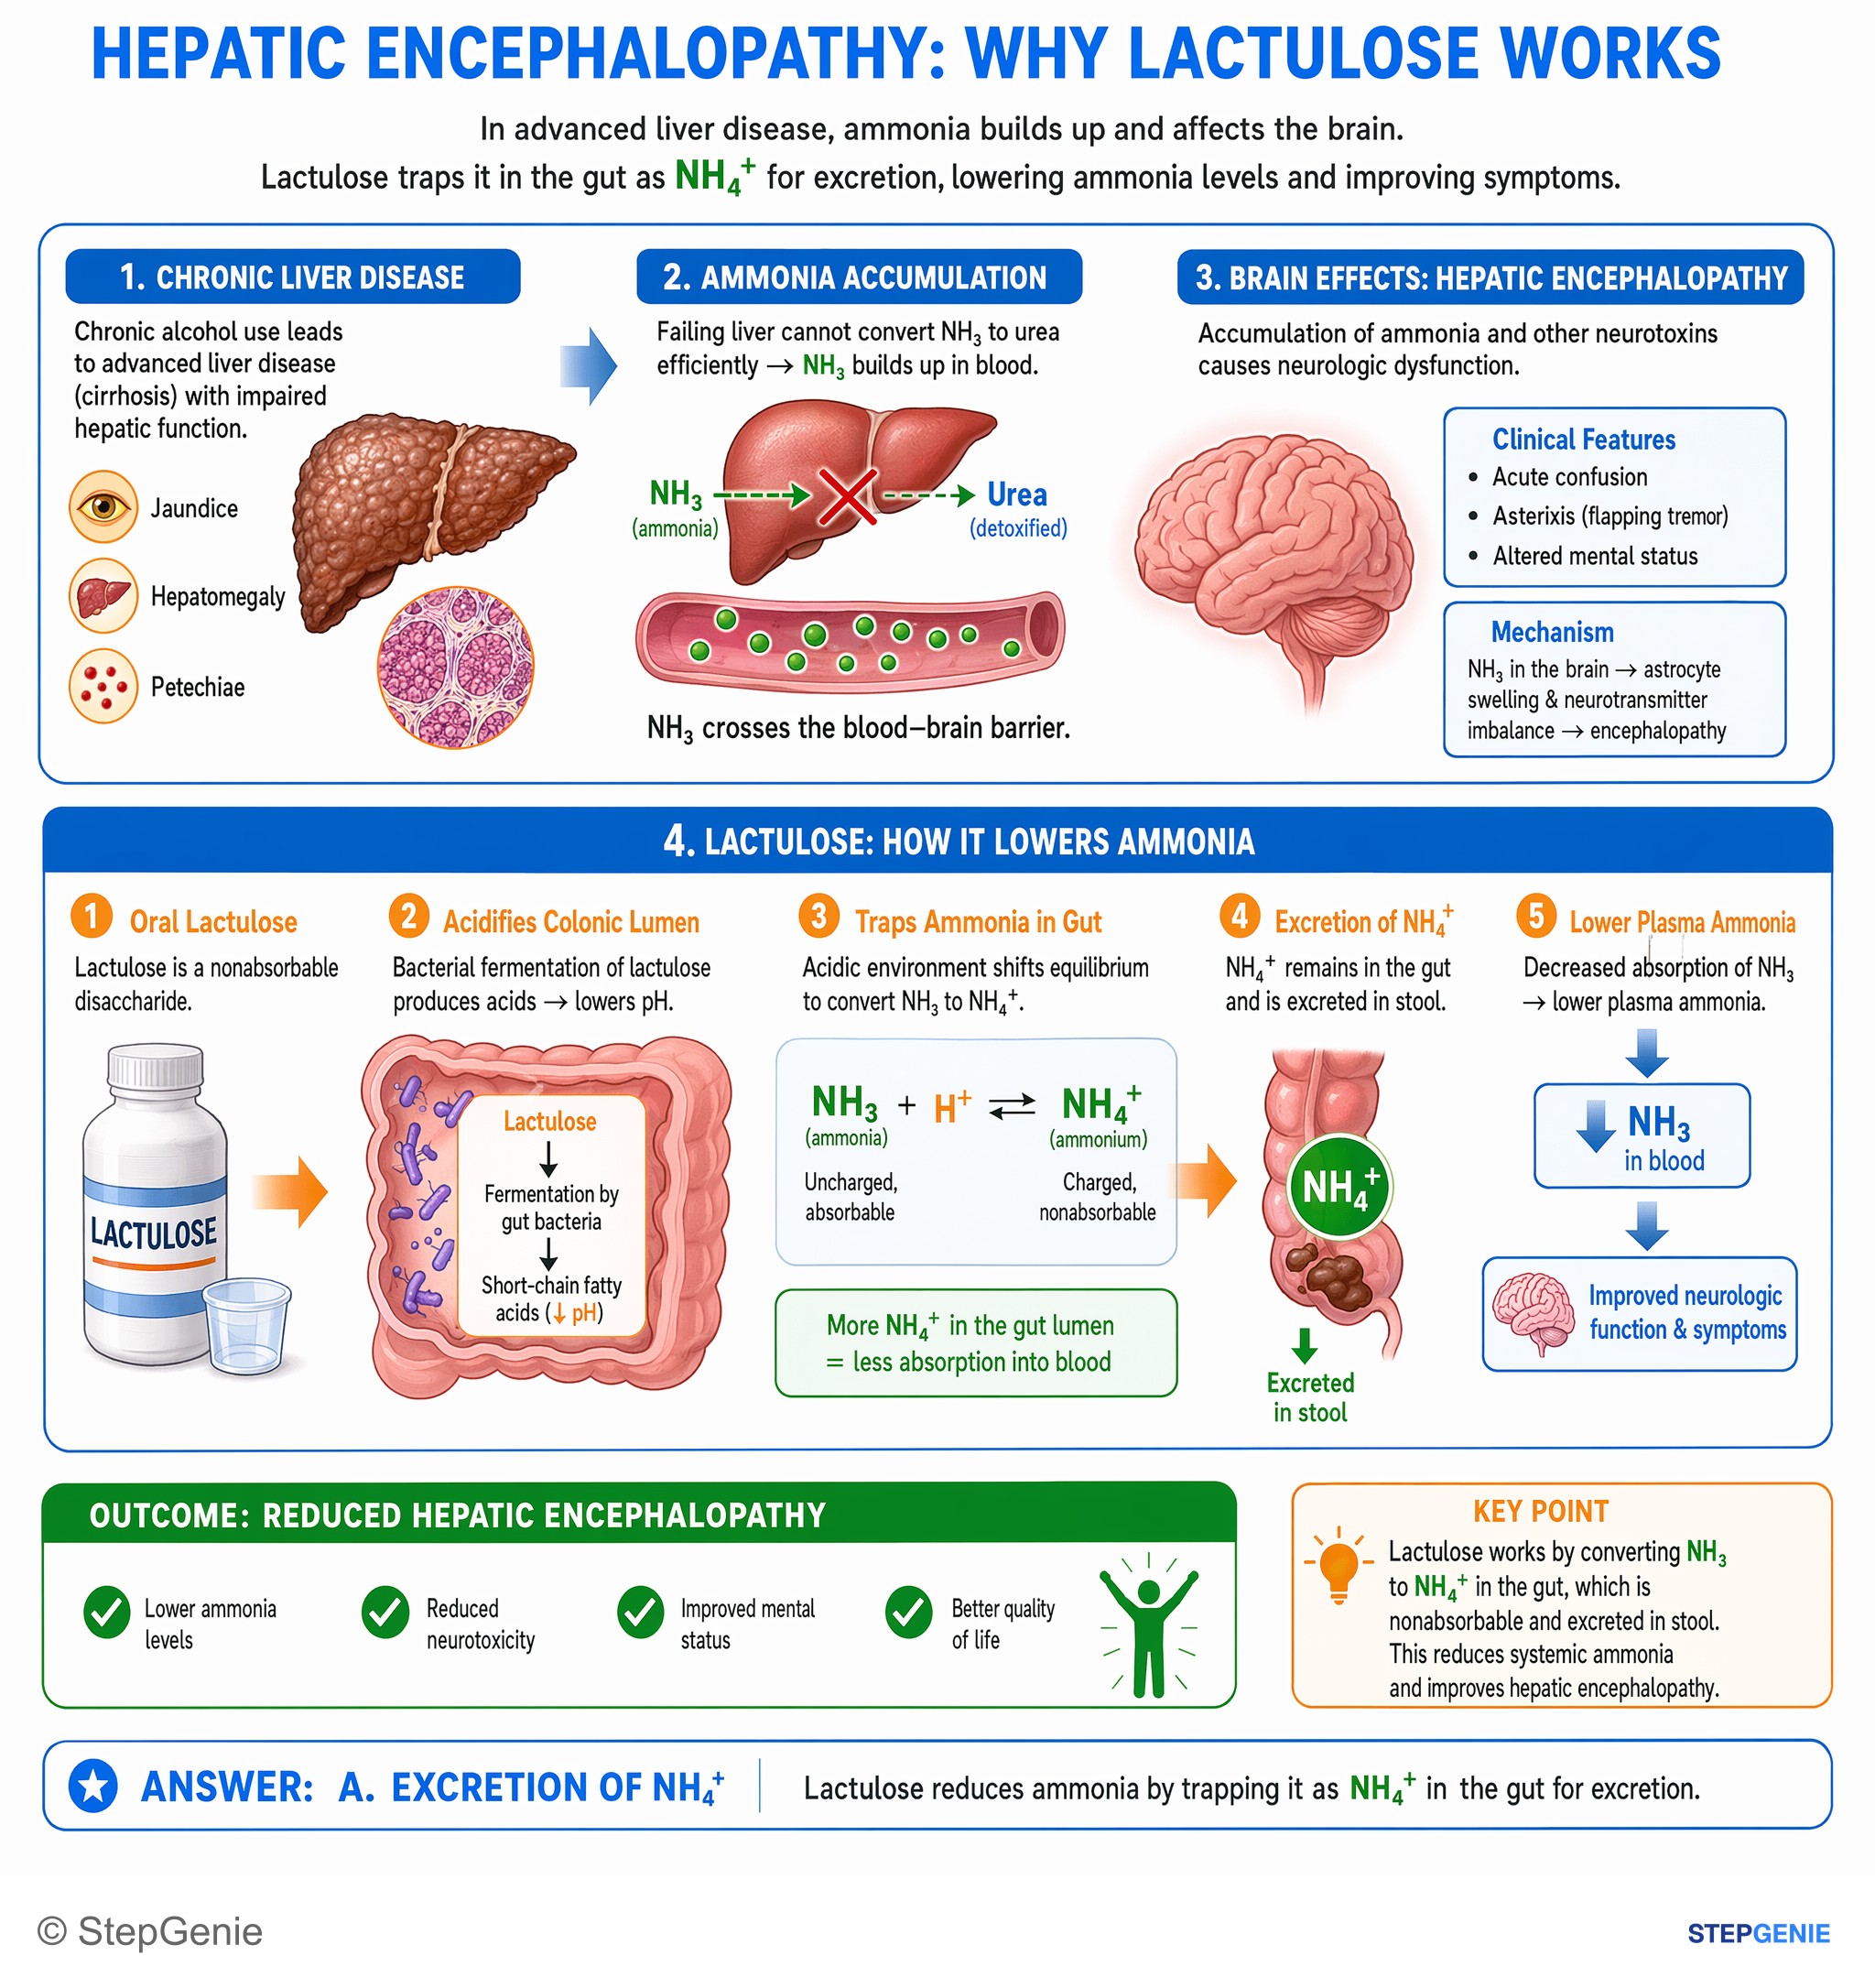
Hepatic encephalopathy from chronic alcohol-related liver failure is treated with lactulose, which reduces ammonia by trapping it as NH4+…
USMLE Step 1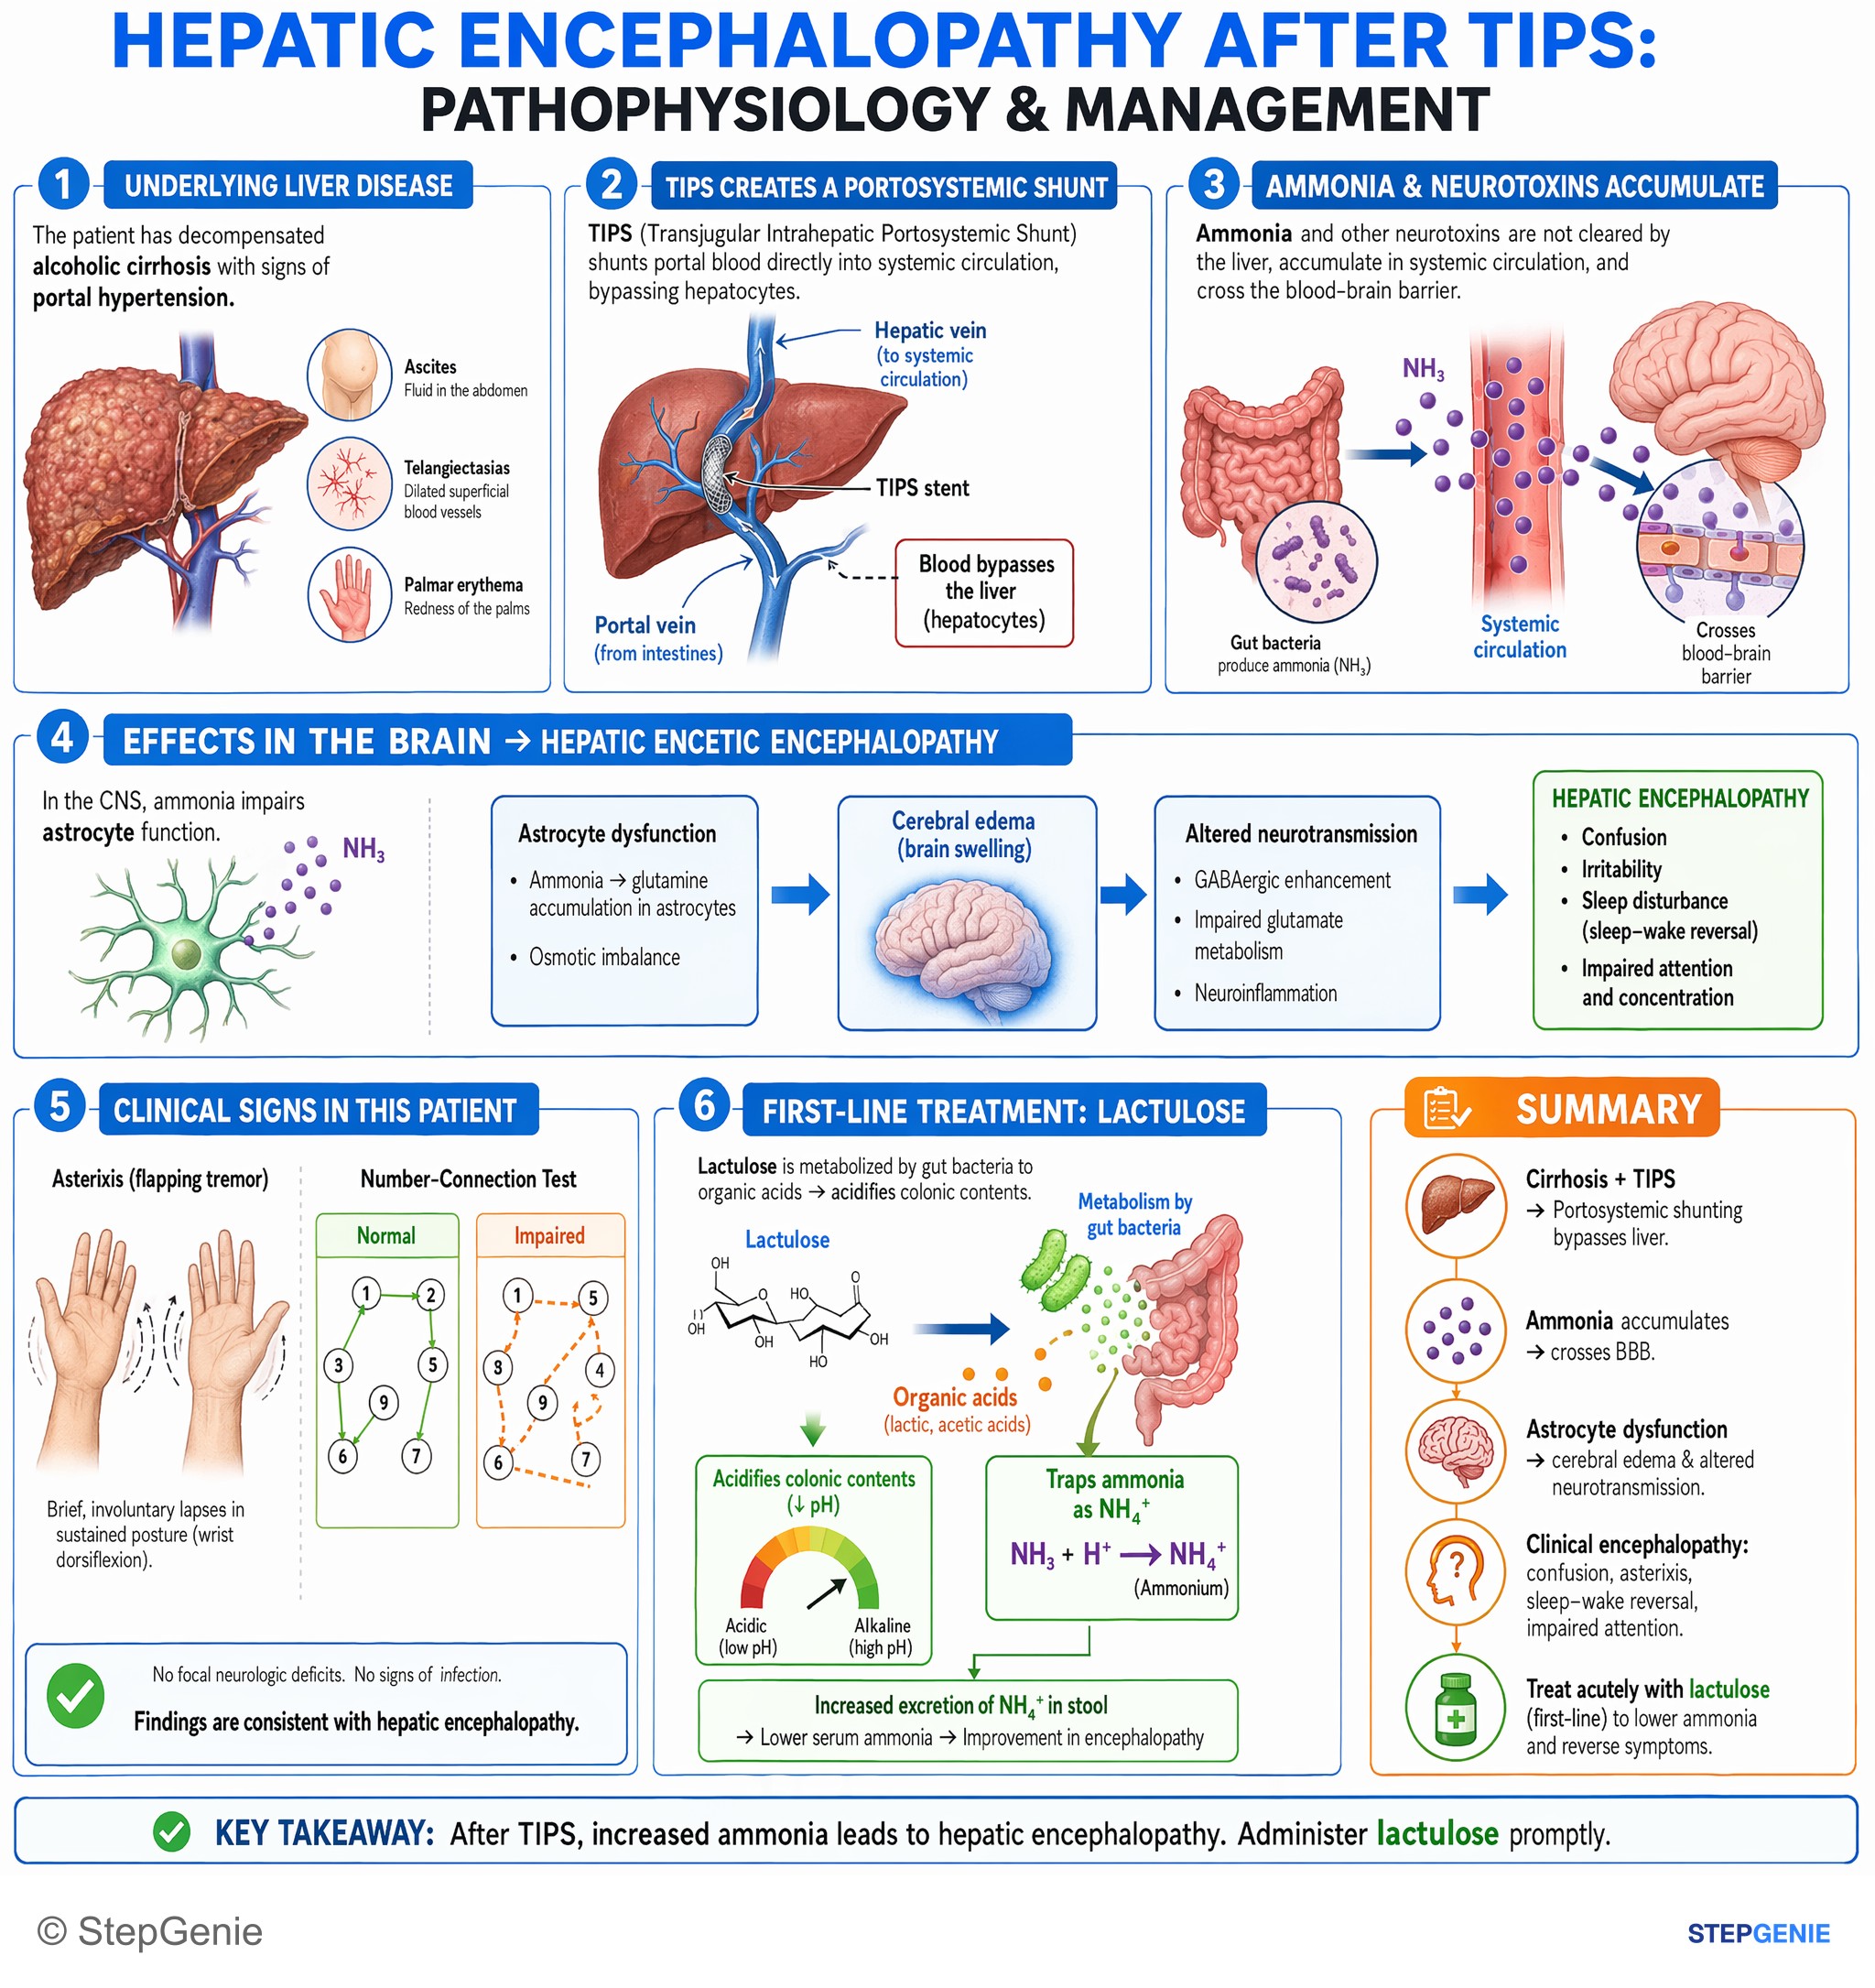
Hepatic encephalopathy after TIPS: portosystemic shunting increases ammonia → confusion, asterixis, sleep-wake reversal; treat acutely…
USMLE Step 2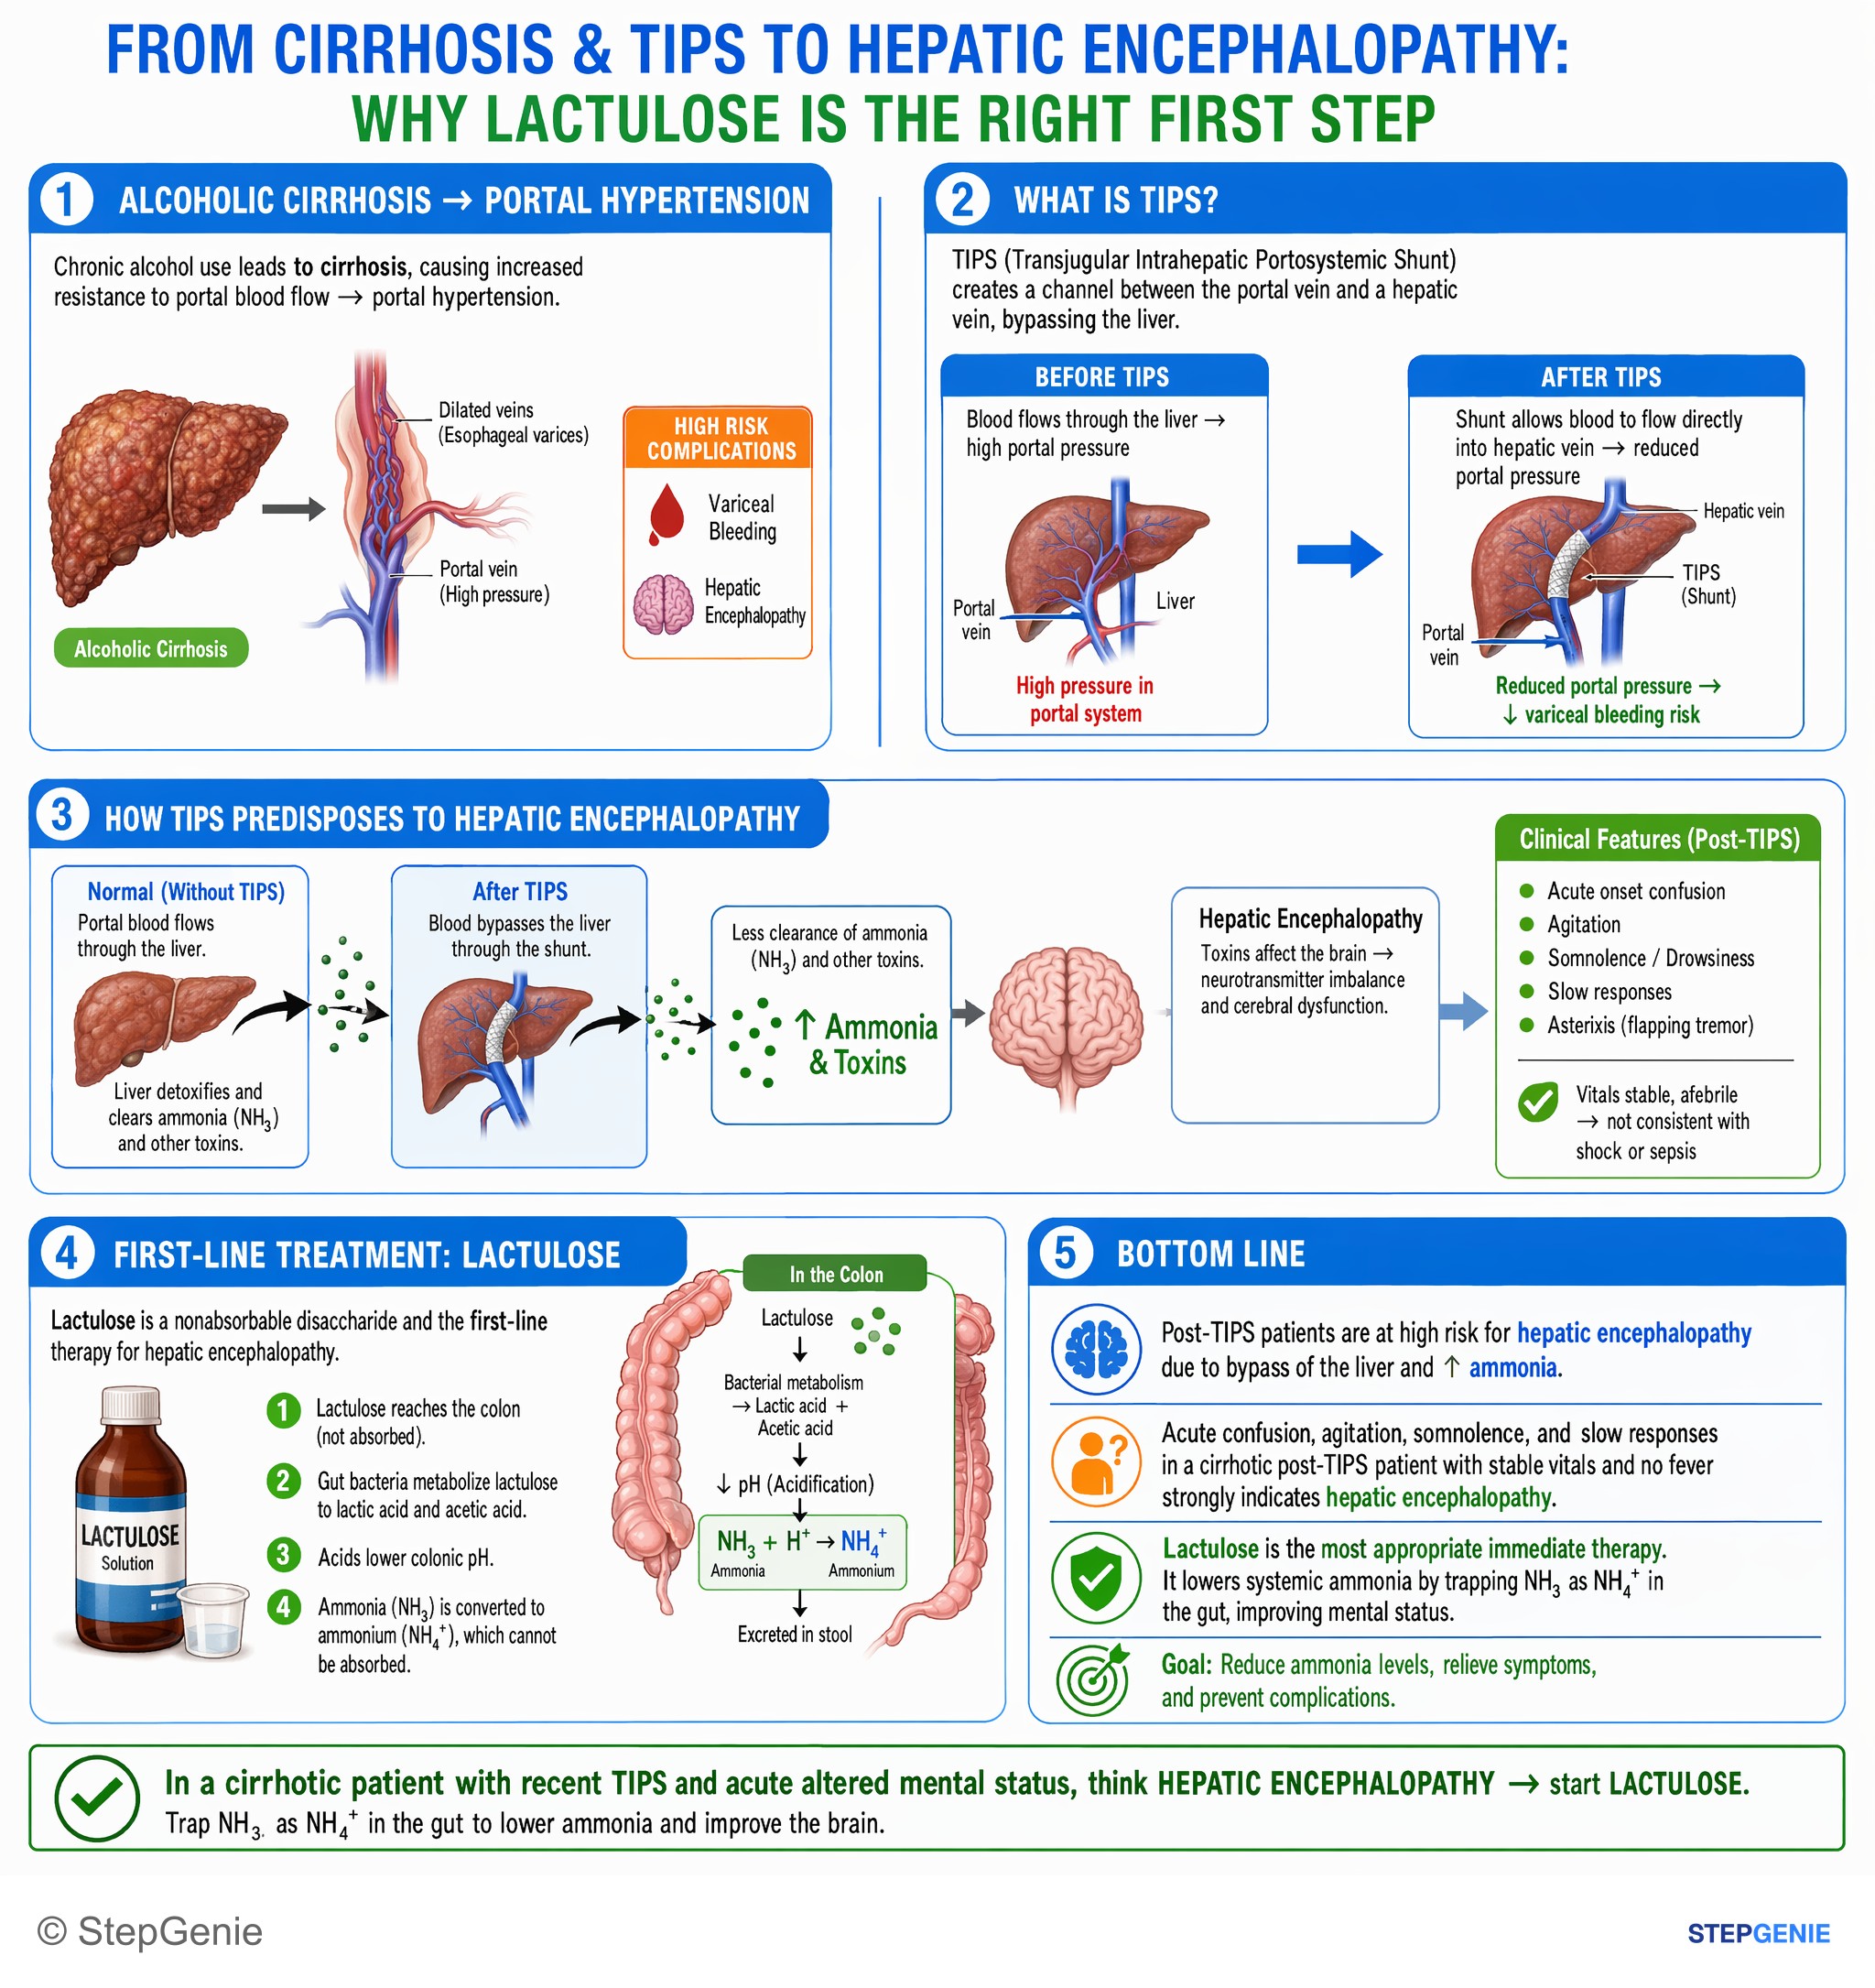
Hepatic encephalopathy after TIPS presents with confusion and somnolence due to ↑ ammonia; treat acutely with lactulose to trap NH3 as…
USMLE Step 2Frequently Asked Questions
How does lactulose lower ammonia in hepatic encephalopathy?
Lactulose lowers ammonia by acidifying the colon and trapping ammonia as NH4+ so it can be excreted in stool. It is a nonabsorbable disaccharide that reaches the colon intact, where gut bacteria ferment it into organic acids. The lower colonic pH shifts NH3 toward NH4+, which is charged and cannot diffuse back, while increased stooling also reduces ammonia generation and absorption.
Why does lactulose cause diarrhea?
Lactulose causes diarrhea because it is osmotically active and pulls water into the intestinal lumen. Since it is not absorbed in the small intestine, it reaches the colon and remains in the gut, where both lactulose and its bacterial metabolites draw water in. This watery stool effect is therapeutic at the right dose but can become excessive if overused.
What is lactulose used for on exams?
Lactulose is used for constipation and hepatic encephalopathy. For constipation, it works as an osmotic laxative that softens stool by causing osmotic diarrhea. For hepatic encephalopathy, it decreases serum ammonia by acidifying the gut lumen, trapping NH3 as NH4+, and increasing stool frequency, which reduces ammonia absorption. Exam clues often include cirrhosis, confusion, asterixis, and elevated ammonia.
What side effects of lactulose are most testable?
The most testable side effects of lactulose are diarrhea, abdominal cramping, flatulence, and dehydration with electrolyte problems such as hypernatremia. Flatulence occurs because gut bacteria ferment lactulose, and excessive diarrhea can lead to volume depletion. In a cirrhotic patient who becomes more confused while taking lactulose, dehydration or electrolyte derangements from over-diarrhea should be considered rather than assuming worsening encephalopathy alone.
What is the treatment goal when giving lactulose for hepatic encephalopathy?
The treatment goal with lactulose for hepatic encephalopathy is 2 to 3 soft stools per day. That target reflects the drug’s therapeutic balance: enough stooling to reduce ammonia generation and absorption, but not so much that the patient develops excessive diarrhea. Overdoing lactulose can cause dehydration and electrolyte disturbances, which can worsen a patient’s overall condition.